
Clopidogrel 300 mg Tablet, 500-count — NDC 52605-083-05 (Billing 52605-0083-05)
This is a package of 500 tablets of Clopidogrel 300 mg Tablet from POLYGEN PHARMACEUTICALS INC., no longer marketed (first marketed Mar 2021), no longer in the FDA NDC Directory. It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 309362
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the P2Y12 Platelet Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Clopidogrel is used to prevent repeat heart attacks or strokes in people who have had a stroke, heart attack, severe chest pain or peripheral arterial disease (poor blood flow in the blood vessels that bring blood to your legs). Clopidogrel is in a class of medications called antiplatelet medications. It works by preventing platelets (a type of blood cell) from collecting and forming clots that may cause a heart attack or stroke.
Read the full MedlinePlus article ↗- It helps prevent heart attacks and strokes in people with acute coronary syndrome, a recent heart attack, a recent stroke or peripheral arterial disease. It works by keeping platel...
- Take it by mouth, usually once a day, with or without food. Your doctor may start with a one-time loading dose. Follow your label and don't stop it unless your prescriber says so.
- Stopping early raises your risk of a heart attack or stroke. If you need surgery, your doctor will tell you whether to pause it, often about 5 days before, and when to restart.
- Bleeding is the most common one, so you may notice nosebleeds or bruise more easily. Call your doctor for bleeding that is heavy, unusual or won't stop, or for black or bloody stoo...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Clopidogrel — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1628 | $81.40 / 500 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 52605-0083-05 You're viewing this Main listing | 500 TABLET in 1 BOTTLE, DISPENSING | 2021-03-01 | — | Discontinued by firm |
| 52605-0083-13 52605-083-13 | 30 TABLET in 1 BOTTLE | 2021-03-01 | — | Discontinued by firm |
You're viewing the largest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 52605-0083-13?
What NDC number is used to bill for this package of Clopidogrel 300 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clopidogrel 300 mg 00904-6467-07 | Major | 1 tablet | $5.291 | AB | Availability likely | — |
| Clopidogrel 300 mg 50268-0184-12 | AvPAK | 1 tablet | $5.291 | AB | Availability likely | — |
| Clopidogrel 300 mg 60505-3532-05 | Apotex | 500 tablets | $5.291 | AB | Availability likely | — |
| Clopidogrel bisulfate 300 mg 63739-0178-30 | McKesson | 6 tablets | $5.291 | AB | Availability likely | — |
| Clopidogrel 300 mg 69367-0194-05 | Westminster | 500 tablets | $5.291 | AB | Availability likely | — |
| Plavix 300 mg 00024-1332-30 | Sanofi-Aventis | 10 tablets | — | AB | FDA listed | — |
| Clopidogrel 300 mg 31722-0759-05 | Camber | 500 tablets | — | AB | FDA listed | — |
| Clopidogrel 300 mg 42543-0714-01 | Vensun | 100 tablets | — | AB | FDA listed | — |
| Clopidogrel bisulfate 300 mg 43598-0122-05 | Dr.Reddy's | 500 tablets | — | AB | FDA listed | — |
| Clopidogrel bisulfate 300 mg 50228-0121-05 | ScieGen | 500 tablets | — | AB | FDA listed | — |
| Clopidogrel 300 mgthis 52605-0083-05 | POLYGEN | 500 tablets | — | AB | Discontinued | — |
| Clopidogrel bisulfate 300 mg 55111-0671-01 | Dr.Reddy's | 100 tablets | — | AB | FDA listed | — |
| Clopidogrel 300 mg 68084-0752-25 | American | 1 tablet | — | AB | FDA listed | — |
| Clopidogrel bisulfate 300 mg 77771-0121-05 | RADHA | 500 tablets | — | AB | FDA listed | — |
| Clopidogrel 300 mg 82804-0986-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
BOXED WARNING WARNING: DIMINISHED ANTIPLATELET EFFECT IN PATIENTS WITH TWO LOSS-OF-FUNCTION ALLELES OF THE CYP2C19 GENE Th e effectiveness of clopidogrel tablets results from its antiplatelet activity, which is dependent on its conversion to an active metabolite by the cytochrome P450 (CYP) system, principally CYP2C19 [see Warnings and Precautions (5.1), Clinical Pharmacology (12.3)] . Clopidogrel at recommended doses forms less of the active metabolite and so has a reduced effect on platelet activity in patients who are homozygous for nonfunctional alleles of the CYP2C19 gene, (termed “CYP2C19 poor metabolizers”).
Tests are available to identify patients who are CYP2C19 poor metabolizers [see Clinical Pharmacology (12.5)] . Consider use of another platelet P2Y 12 inhibitor in patients identified as CYP2C19 poor metabolizers. W ARN ING: DIMINISHED ANTIPLATELET EFFECT IN PATIENTS WITH TWO LOSS-OF-FUNCTION ALLELES OF THE CYP2C19 GENE S e e full prescribing information for complete boxed warning.
E ff ec t i v e n e ss of clopidogrel depends on conversion to an active metabolite by the cytochrome P450 (CYP) system, principally CYP2C19. ( 5.1 , 12.3 ) Te sts are available to identify patients who are CYP2C19 poor metabolizers. ( 12.5 ) Consider use of another platelet P2Y 12 inhibitor in patients identified as CYP2C19 poor metabolizers.
( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS & USAGE Clopidogrel is a P2Y 12 platelet inhibitor indicated for: Acute coronary syndrome –For patients with non–ST-segment elevation ACS (unstable angina [UA]/non–ST-elevation myocardial infarction [NSTEMI]), clopidogrel has been shown to reduce the rate of myocardial infarction (MI) and stroke. ( 1.1 ) –For patients with ST-elevation myocardial infarction (STEMI), clopidogrel has been shown to reduce the rate of MI and stroke. ( 1.1 ) Recent MI, recent stroke, or established peripheral arterial disease.
Clopidogrel has been shown to reduce the rate of MI and stroke. ( 1.2 )
1.1Acute Coronary Syndrome (ACS) Clopidogrel tablets are indicated to reduce the rate of myocardial infarction (MI) and stroke in patients with non-ST-segment elevation ACS (unstable angina [UA]/non-ST -elevation myocardial infarction [NSTEMI]), including patients who are to be managed medically and those who are to be managed with coronary revascularization. Clopidogrel tablets should be administered in conjunction with aspirin. Clopidogrel tablets are indicated to reduce the rate of myocardial infarction and stroke in patients with acute ST-elevation myocardial infarction (STEMI) who are to be managed medically.
Clopidogrel tablets should be administered in conjunction with aspirin.
1.2Recent MI, Recent Stroke, or Established Peripheral Arterial Disease In patients with established peripheral arterial disease or with a history of recent myocardial infarction (MI) or recent stroke clopidogrel tablets are indicated to reduce the rate of MI and stroke.
⏱️ Dosage and Administration ▾
2 DOSAGE & ADMINISTRATION Acute coronary syndrome ( 2.1 ) –Initiate clopidogrel with a single 300-mg oral loading dose and then continue at 75 mg once daily. –Initiating clopidogrel without a loading dose will delay establishment of an antiplatelet effect by several days. Recent MI, recent stroke, or established peripheral arterial disease: 75 mg once daily orally without a loading dose. ( 2.2 )
2.1Acute Coronary Syndrome In patients who need an antiplatelet effect within hours, initiate clopidogrel tablets with a single 300 mg oral loading dose and then continue at 75 mg once daily. Initiating clopidogrel tablets without a loading dose will delay establishment of an antiplatelet effect by several days [see Clinical Pharmacology (12.3) and Clinical Studies (14.1)].
2.2Recent MI, Recent Stroke, or Established Peripheral Arterial Disease 75 mg once daily orally without a loading dose [see Clinical Pharmacology (12.3) and Clinical Studies (14.2)] .
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS & STRENGTHS 75 mg tablets: Pink colored, round, biconvex, film-coated tablet debossed with "P" on one side and "82" on the other side. 300 mg tablets: Pink colored, modified oval shaped, biconvex, film-coated tablet debossed with "P" on one side and "83" on the other side. Tablets: 75 mg, 300 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Active pathological bleeding, such as peptic ulcer or intracranial hemorrhage ( 4.1 ) Hypersensitivity to clopidogrel or any component of the product ( 4.2 )
4.1Active Bleeding Clopidogrel tablets are contraindicated in patients with active pathological bleeding such as peptic ulcer or intracranial hemorrhage.
4.2Hypersensitivity Clopidogrel tablets are contraindicated in patients with hypersensitivity (e.g., anaphylaxis) to clopidogrel or any component of the product [s e e Adverse Reactions (6.2)] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS CYP2C19 inhibitors: Avoid concomitant use of omeprazole or esomeprazole. ( 5.1 ) Bleeding: Clopidogrel increases risk of bleeding. ( 5.2 ) Discontinuation: Premature discontinuation increases risk of cardiovascular events.
Discontinue 5 days prior to elective surgery that has a major risk of bleeding. ( 5.3 ) Thrombotic thrombocytopenic purpura (TTP) has been reported. ( 5.4 ) Cross-reactivity among thienopyridines has been reported.
( 5.5 )
5.1Diminished Antiplatelet Activity in patients with Impaired CYP2C19 Function Clopidogrel is a prodrug. Inhibition of platelet aggregation by clopidogrel is achieved through an active metabolite. The metabolism of clopidogrel to its active metabolite can be impaired by genetic variations in CYP2C19 [s e e Boxed Warning ] .
The metabolism of clopidogrel can also be impaired by drugs that inhibit CYP2C19, such as omeprazole or esomeprazole. Avoid concomitant use of clopidogrel tablets with omeprazole or esomeprazole because both significantly reduce the antiplatelet activity of clopidogrel tablets [s e e D r u g Interactions (7.1)] .
5.2General Risk of Bleeding P2Y12 inhibitors (Thienopyridines), including clopidogrel tablets, increase the risk of bleeding. P2Y12 inhibitors (Thienopyridines), inhibit platelet aggregation for the lifetime of the platelet (7-10 days). Because the half-life of clopidogrel’s active metabolite is short, it may be possible to restore hemostasis by administering exogenous platelets; however, platelet transfusions within 4 hours of the loading dose or 2 hours of the maintenance dose may be less effective.
Use of drugs that induce the activity of CYP2C19 would be expected to result in increased drug levels of the active metabolite of clopidogrel and might potentiate the bleeding risk. As a precaution, avoid concomitant use of strong CYP2C19 inducers [see Drug Interactions (7.1) and Clinical Pharmacology (12.3)].
5.3Discontinuation of Clopidogrel Tablets Discontinuation of clopidogrel tablets increases the risk of cardiovascular events. If clopidogrel tablets must be temporarily discontinued (e.g., to treat bleeding or for surgery with a major risk of bleeding), restart it as soon as possible. When possible, interrupt therapy with clopidogrel tablets for five days prior to such surgery. Resume clopidogrel tablets as soon as hemostasis is achieved.
5.4Thrombotic Thrombocytopenic Purpura (TTP) TTP, sometimes fatal, has been reported following use of clopidogrel tablets, sometimes after a short exposure (<2 weeks). TTP is a serious condition that requires urgent treatment including plasmapheresis (plasma exchange). It is characterized by thrombocytopenia, microangiopathic hemolytic anemia (schistocytes [fragmented RBCs] seen on peripheral smear), neurological findings, renal dysfunction, and fever [see Adverse Reactions (6.2)] .
5.5Cross-Reactivity among Thienopyridines Hypersensitivity including rash, angioedema or hematologic reaction have been reported in patients receiving clopidogrel tablets, including patients with a history of hypersensitivity or hematologic reaction to other thienopyridines [s e e Contraindications (4.2) and Adverse Reactions (6.2)] .
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed below and elsewhere in the labeling: Bleeding [see Warnings and Precautions (5.2)] Thrombotic thrombocytopenic purpura [see Warnings and Precautions (5.4)] Bleeding, including life-threatening and fatal bleeding, is the most commonly reported adverse reaction. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Polygen Pharmaceuticals Inc. at 1-888-291-7337 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions and durations of follow-up, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Clopidogrel tablets have been evaluated for safety in more than 54,000 patients, including over 21,000 patients treated for one year or more. The clinically important adverse reactions observed in trials comparing clopidogrel tablets plus aspirin to placebo plus aspirin and trials comparing clopidogrel tablets alone to aspirin alone are discussed below.
B l ee d i n g CURE In CURE, clopidogrel tablets use with aspirin was associated with an increase in major bleeding (primarily gastrointestinal and at puncture sites) compared to placebo with aspirin (see Table 1). The incidence of intracranial hemorrhage (0.1%) and fatal bleeding (0.2%) were the same in both groups. Other bleeding events that were reported more frequently in the clopidogrel group were epistaxis, hematuria, and bruise.
The overall incidence of bleeding is described in Table 1. T a b l e 1: CURE Incidence of Bleeding Complications (% patients) Event Clopidogrel Tablets (+ aspirin) (n=6259) Placebo (+ aspirin) (n=6303) Major bleeding* 3.7
2.7Life-threatening bleeding 2.2
1.8Fatal 0.2 0.2 5 g/dL hemoglobin drop 0.9
0.9Requiring surgical intervention 0.7
0.7Hemorrhagic strokes 0.1
0.1Requiring ionotropes 0.5
0.5Requiring transfusion ( ≥4 units) 1.2
1.0Other major bleeding 1.6
1.0Significantly disabling 0.4
0.3Intraocular bleeding with significant loss of vision 0.05
0.03Requiring 2-3 units of blood 1.3
0.9Minor bleeding † 5.1 2.4 *Life-threatening and other major bleeding. † Led to interruption of study medication. COMMIT In COMMIT, similar rates of major bleeding were observed in the clopidogrel tablets and placebo groups, both of which also received aspirin (see Table 2). Table 2: Incidence of Bleeding Events in COMMIT (% patients) Type of Bleeding Clopidogrel Tablets (+ aspirin) (n=22961) Placebo (+ aspirin) (n=22891) p-value Major * noncerebral or cerebral bleeding 0.6 0.5
0.59Major noncerebral 0.4 0.3
0.48Fatal 0.2 0.2
0.90Hemorrhagic stroke 0.2 0.2
0.91Fatal 0.2 0.2
0.81Other noncerebral bleeding (nonmajor) 3.6 3.1 0.005 Any noncerebral bleeding 3.9 3.4 0.004 *Major bleeds were cerebral bleeds or noncerebral bleeds thought to have caused death or that required transfusion. C APR I E (Clopidogrel vs Aspirin) In CAPRIE, gastrointestinal hemorrhage occurred at a rate of 2.0% in those taking clopidogrel tablets versus 2.7% in those taking aspirin; bleeding requiring hospitalization occurred in 0.7% and 1.1%, respectively. The incidence of intracranial hemorrhage was 0.4% for clopidogrel tablets compared to 0.5% for aspirin.
Other bleeding events that were reported more frequently in the clopidogrel tablets group were epistaxis and hematoma. O t h e r Adverse Events In CURE and CHARISMA, which compared clopidogrel tablets plus aspirin to aspirin alone, there was no difference in the rate of adverse events (other than bleeding) between clopidogrel tablets and placebo. In CAPRIE, which compared clopidogrel tablets to aspirin, pruritus was more frequently reported in those taking clopidogrel tablets.
No other difference in the rate of adverse events (other than bleeding) was reported.
6.2Postmarketing Experience The following adverse reactions have been ide… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP2C19 inducers: Increases levels of clopidogrel active metabolite and increases platelet inhibition. ( 7.1 ) Opioids: Decreased exposure to clopidogrel. Consider use of parenteral antiplatelet agent.
( 7.3 ) Nonsteroidal anti-inflammatory drugs (NSAIDs), warfarin, selective serotonin and serotonin norepinephrine reuptake inhibitors (SSRIs, SNRIs): Increases risk of bleeding. ( 7.4 , 7.5 , 7.6 ) Repaglinide (CYP2C8 substrates): Increases substrate plasma concentrations. ( 7.7 )
7.1CYP2C19 Inducers Since clopidogrel is metabolized to its active metabolite partly by CYP2C19, use of drugs that induce the activity of this enzyme would be expected to result in increased drug levels of the active metabolite of clopidogrel. Rifampin strongly induces CYP2C19 resulting to both an increase level of clopidogrel active metabolite and platelet inhibition, which in particular might potentiate the risk of bleeding. As a precaution, avoid concomitant use of strong CYP2C19 inducers [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3)].
7.2CYP2C19 Inhibitors Clopidogrel is metabolized to its active metabolite in part by CYP2C19. Concomitant use of drugs that inhibit the activity of this enzyme results in reduced plasma concentrations of the active metabolite of clopidogrel and a reduction in platelet inhibition [s e e Warnings and Precautions (5.1)] . O m e p r a z o l e or Esomeprazole Avoid concomitant use of clopidogrel tablets with omeprazole or esomeprazole.
In clinical studies, omeprazole was shown to reduce significantly the antiplatelet activity of clopidogrel tablets when given concomitantly or 12 hours apart. A similar reduction in antiplatelet activity was observed with esomeprazole when given concomitantly with clopidogrel tablets. Dexlansoprazole, lansoprazole, and pantoprazole had less effect on the antiplatelet activity of clopidogrel tablets than did omeprazole or esomeprazole [see Warnings and Precautions (5.1) and Clinical Pharmacology (12.3)] .
7.3Opioids As with other oral P2Y 12 inhibitors, coadministration of opioid agonists delay and reduce the absorption of clopidogrel, presumably because of slowed gastric emptying, resulting in reduced exposure to its metabolites [s e e Clinical Pharmacology (12.3)] . Consider the use of a parenteral antiplatelet agent in acute coronary syndrome patients requiring coadministration of morphine or other opioid agonists.
7.4Nonsteroidal Anti-inflammatory Drugs (NSAIDs) Coadministration of clopidogrel tablets and NSAIDs increases the risk of gastrointestinal bleeding.
7.5Warfarin (CYP2C9 Substrates) Although the administration of clopidogrel 75 mg per day did not modify the pharmacokinetics of S-warfarin (a CYP2C9 substrate) or INR in patients receiving long-term warfarin therapy, coadministration of clopidogrel tablets with warfarin increases the risk of bleeding because of independent effects on hemostasis. However, at high concentrations in vitro , clopidogrel inhibits CYP2C9.
7.6SSRIs and SNRIs Since selective serotonin reuptake inhibitors (SSRIs) and serotonin norepinephrine reuptake inhibitors (SNRIs) affect platelet activation, the concomitant administration of SSRIs and SNRIs with clopidogrel may increase the risk of bleeding.
7.7Repaglinide (CYP2C8 Substrates) The acyl-β-glucuronide metabolite of clopidogrel is a strong inhibitor of CYP2C8. Clopidogrel tablets can increase the systemic exposure to drugs that are primarily cleared by CYP2C8, thereby needing dose adjustment and appropriate monitoring. Clopidogrel tablets increased repaglinide exposures by 3.9-fold to 5.1-fold [see Clinical Pharmacology (12.3)].
Avoid concomitant use of repaglinide with clopidogrel tablets. If concomitant use cannot be avoided, initiate repaglinide at 0.5 mg before each meal and do not exceed a total daily dose of 4 mg. Increased frequency of glucose monitoring may be required during concomitant use.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from cases reported in published literature and postmarketing surveillance with clopidogrel use in pregnant women have not identified any drug-associated risks for major birth defects or miscarriage [see Data]. There are risks to the pregnant woman and fetus associated with myocardial infarction and stroke [see Clinical Considerations] . No evidence of fetotoxicity was observed when clopidogrel was administered to pregnant rats and rabbits during organogenesis at doses corresponding to 65 and 78 times the recommended daily human dose [see Data] .
The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Myocardial infarction and stroke are medical emergencies. Therapy for the pregnant woman should not be withheld because of potential concerns regarding the effects of clopidogrel on the fetus. Labor or delivery Clopidogrel use during labor or delivery will increase the risk of maternal bleeding and hemorrhage.
Avoid neuraxial blockade during clopidogrel use because of the risk of spinal hematoma. When possible, discontinue clopidogrel 5 to 7 days prior to labor, delivery, or neuraxial blockade. Data Human data The available data from published case reports over two decades of postmarketing use have not identified an association with clopidogrel use in pregnancy and major birth defects, miscarriage, or adverse fetal outcomes.
Animal data Embryo-fetal developmental toxicology studies were performed in pregnant rats and rabbits with doses up to 500 and 300 mg/kg/day, respectively, administered during organogenesis. These doses, corresponding to 65 and 78 times the recommended daily human dose, respectively, on a mg/m 2 basis, revealed no evidence of impaired fertility or fetotoxicity due to clopidogrel.
8.2Lactation Risk Summary There are no data on the presence of clopidogrel in human milk or the effects on milk production. No adverse effects on breastfed infants have been observed with maternal clopidogrel use during lactation in a small number of postmarketing cases. Studies in rats have shown that clopidogrel and/or its metabolites are present in the milk.
When a drug is present in animal milk, it is likely that the drug will be present in human milk. The developmental and health benefits of breastfeeding should be considered along with mother’s clinical need for clopidogrel and any potential adverse effects on the breastfed infant from clopidogrel or from underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric populations have not been established. A randomized, placebo-controlled trial (CLARINET) did not demonstrate a clinical benefit of clopidogrel in neonates and infants with cyanotic congenital heart disease palliated with a systemic-to-pulmonary arterial shunt. Possible factors contributing to this outcome were the dose of clopidogrel, the concomitant administration of aspirin and the late initiation of therapy following shunt palliation.
It cannot be ruled out that a trial with a different design would demonstrate a clinical benefit in this patient population.
8.5Geriatric Use Of the total number of subjects in the CAPRIE and CURE controlled clinical studies, approximately 50% of patients treated with clopidogrel tablets were 65 years of age and older, and 15% were 75 years and older. In COMMIT, approximately 58% of the patients treated with clopidogrel tablets were 60 years and older, 26% of whom were 70 years and older. The observed risk of bleeding events with clopidogrel tablets plus aspirin versus placebo plus aspirin b… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from cases reported in published literature and postmarketing surveillance with clopidogrel use in pregnant women have not identified any drug-associated risks for major birth defects or miscarriage [see Data]. There are risks to the pregnant woman and fetus associated with myocardial infarction and stroke [see Clinical Considerations] . No evidence of fetotoxicity was observed when clopidogrel was administered to pregnant rats and rabbits during organogenesis at doses corresponding to 65 and 78 times the recommended daily human dose [see Data] .
The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defects, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Myocardial infarction and stroke are medical emergencies. Therapy for the pregnant woman should not be withheld because of potential concerns regarding the effects of clopidogrel on the fetus. Labor or delivery Clopidogrel use during labor or delivery will increase the risk of maternal bleeding and hemorrhage.
Avoid neuraxial blockade during clopidogrel use because of the risk of spinal hematoma. When possible, discontinue clopidogrel 5 to 7 days prior to labor, delivery, or neuraxial blockade. Data Human data The available data from published case reports over two decades of postmarketing use have not identified an association with clopidogrel use in pregnancy and major birth defects, miscarriage, or adverse fetal outcomes.
Animal data Embryo-fetal developmental toxicology studies were performed in pregnant rats and rabbits with doses up to 500 and 300 mg/kg/day, respectively, administered during organogenesis. These doses, corresponding to 65 and 78 times the recommended daily human dose, respectively, on a mg/m 2 basis, revealed no evidence of impaired fertility or fetotoxicity due to clopidogrel.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric populations have not been established. A randomized, placebo-controlled trial (CLARINET) did not demonstrate a clinical benefit of clopidogrel in neonates and infants with cyanotic congenital heart disease palliated with a systemic-to-pulmonary arterial shunt. Possible factors contributing to this outcome were the dose of clopidogrel, the concomitant administration of aspirin and the late initiation of therapy following shunt palliation.
It cannot be ruled out that a trial with a different design would demonstrate a clinical benefit in this patient population.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number of subjects in the CAPRIE and CURE controlled clinical studies, approximately 50% of patients treated with clopidogrel tablets were 65 years of age and older, and 15% were 75 years and older. In COMMIT, approximately 58% of the patients treated with clopidogrel tablets were 60 years and older, 26% of whom were 70 years and older. The observed risk of bleeding events with clopidogrel tablets plus aspirin versus placebo plus aspirin by age category is provided in Table 1 and Table 2 for the CURE and COMMIT trials, respectively [see Adverse Reactions (6.1)] .
No dosage adjustment is necessary in elderly patients.
🆘 Overdosage ▾
10 OVERDOSAGE Platelet inhibition by clopidogrel tablets is irreversible and will last for the life of the platelet. Overdose following clopidogrel administration may result in bleeding complications. A single oraldose of clopidogrel at 1500 or 2000 mg/kg was lethal to mice and to rats and at 3000 mg/kg to baboons.
Symptoms of acute toxicity were vomiting, prostration, difficult breathing, and gastrointestinal hemorrhage in animals. Based on biological plausibility, platelet transfusion may restore clotting ability.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Clopidogrel is an inhibitor of platelet activation and aggregation through the irreversible binding of its active metabolite to the P2Y 12 class of ADP receptors on platelets.
12.2Pharmacodynamics Clopidogrel must be metabolized by CYP450 enzymes to produce the active metabolite that inhibits platelet aggregation. The active metabolite of clopidogrel selectively inhibits the binding of adenosine diphosphate (ADP) to its platelet P2Y 12 receptor and the subsequent ADP- mediated activation of the glycoprotein GPIIb/IIIa complex, thereby inhibiting platelet aggregation. This action is irreversible.
Consequently, platelets exposed to clopidogrel’s active metabolite are affected for the remainder of their lifespan (about 7 to 10 days). Platelet aggregation induced by agonists other than ADP is also inhibited by blocking the amplification of platelet activation by released ADP. Dose-dependent inhibition of platelet aggregation can be seen 2 hours after single oral doses of clopidogrel tablets.
Repeated doses of 75 mg clopidogrel tablets per day inhibit ADP-induced platelet aggregation on the first day, and inhibition reaches steady state between Day 3 and Day 7. At steady state, the average inhibition level observed with a dose of 75 mg clopidogrel tablets per day was between 40% and 60%. Platelet aggregation and bleeding time gradually return to baseline values after treatment is discontinued, generally in about 5 days.
G e r i a t r i c Patients Elderly (≥75 years) and young healthy subjects had similar effects on platelet aggregation. Renally Impaired Patients After repeated doses of 75 mg clopidogrel tablets per day, patients with severe renal impairment (creatinine clearance from 5 to 15 mL/min) and moderate renal impairment (creatinine clearance from 30 to 60 mL/min) showed low (25%) inhibition of ADP-induced platelet aggregation. H e pa ti c a ll y I m pa i r e d Patients After repeated doses of 75 mg clopidogrel tablets per day for 10 days in patients with severe hepatic impairment, inhibition of ADP-induced platelet aggregation was similar to that observed in healthy subjects.
G e n d e r In a small study comparing men and women, less inhibition of ADP-induced platelet aggregation was observed in women.
12.3Pharmacokinetics Clopidogrel is a prodrug and is metabolized to a pharmacologically active metabolite and inactive metabolites. A b s o r p ti o n After single and repeated oral doses of 75 mg per day, clopidogrel is rapidly absorbed. Absorption is at least 50%, based on urinary excretion of clopidogrel metabolites.
Effect of food Clopidogrel tablets can be administered with or without food. In a study in healthy male subjects when clopidogrel tablets 75 mg per day was given with a standard breakfast, mean inhibition of ADP-induced platelet aggregation was reduced by less than 9%. The active metabolite AUC 0-24 was unchanged in the presence of food, while there was a 57% decrease in active metabolite C max .
Similar results were observed when a clopidogrel tablet 300 mg loading dose was administered with a high-fat breakfast. Metabolism Clopidogrel is extensively metabolized by two main metabolic pathways: one mediated by esterases and leading to hydrolysis into an inactive carboxylic acid derivative (85% of circulating metabolites) and one mediated by multiple cytochrome P450 enzymes. Cytochromes first oxidize clopidogrel to a 2-oxo-clopidogrel intermediate metabolite.
Subsequent metabolism of the 2-oxo-clopidogrel intermediate metabolite results in formation of the active metabolite, a thiol derivative of clopidogrel. The active metabolite is formed mostly by CYP2C19 with contributions from several other CYP enzymes, including CYP1A2, CYP2B6 and CYP3A. The active thiol metabolite binds rapidly and irreversibly to platelet receptors, thus inhibiting platelet aggregation for the lifespan of the platelet.
The C max of the active metabolite is twice as high following a si… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Clopidogrel is an inhibitor of platelet activation and aggregation through the irreversible binding of its active metabolite to the P2Y 12 class of ADP receptors on platelets.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Clopidogrel Tablets, USP are available containing 97.875 mg of clopidogrel bisulfate, USP equivalent to 75 mg of clopidogrel base or 391.5 mg of clopidogrel bisulfate, USP equivalent to 300 mg of clopidogrel base. The 75 mg tablets are pink colored, round, biconvex, film-coated tablets debossed with “P” on one side and “82” on the other side. They are provided as follows: Bottles of 30 tablets with child-resistant closure, NDC 52605-082-13 Bottles of 1000 tablets, NDC 52605-082-10 The 300 mg tablets are Pink colored, modified oval shaped, biconvex, film-coated tablets debossed with “P” on one side and “83” on the other side.
They are provided as follows: Bottles of 30 tablets with child-resistant closure, NDC 52605-083-13 Bottles of 500 tablets, NDC 52605-083-05 Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Clopidogrel bisulfate is a thienopyridine class inhibitor of P2Y 12 ADP platelet receptors. Chemically it is methyl (+)-( S )-α-(o-chlorophenyl)-6, 7-dihydrothieno[3,2-c]pyridine-5(4 H )-acetate, sulfate (1:1). The empirical formula of clopidogrel bisulfate is C 16 H 16 ClNO 2 S•H 2 SO 4 and its molecular weight is 419.9.
The structural formula is as follows: Clopidogrel bisulfate, USP is a white to off-white powder. It is practically insoluble in water at neutral pH but freely soluble at pH 1. It also dissolves freely in methanol, dissolves sparingly in methylene chloride, and is practically insoluble in ethyl ether.
It has a specific optical rotation of about +56°. Clopidogrel tablets, USP for oral administration are provided as pink, round, debossed, film-coated tablets containing 97.875 mg of clopidogrel bisulfate, USP which is the molar equivalent of 75 mg of clopidogrel base or pink, modified oval, debossed, film-coated tablets containing 391.5 mg of clopidogrel bisulfate, USP which is the molar equivalent of 300 mg of clopidogrel base. Each tablet contains croscarmellose sodium, mannitol, microcrystalline cellulose, hydroxypropyl cellulose, hydrogenated castor oil, hypromellose, iron oxide red, polyethylene glycol, and titanium dioxide. clopidogrel-structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients to read FDA approved patient labeling ( Medication Guide ). Discontinuation Advise patients not to discontinue clopidogrel tablets without first discussing it with the healthcare provider who prescribed it [see Warnings and Precautions (5.3)]. Bleeding Advise patients that they: will bruise and bleed more easily will take longer than usual to stop bleeding must report any unanticipated, prolonged, or excessive bleeding, or blood in their stool or urine [see Warnings and Precautions (5.2 )] Thrombotic Thrombocytopenic Purpura Instruct patients to get prompt medical attention if they experience symptoms of TTP that cannot otherwise be explained [s e e Warnings and Precautions (5.4)] .
Invasive Procedures Advise patients to inform physicians and dentists that they are taking clopidogrel tablets before any surgery or dental procedure [s e e Warnings and Precautions ( 5.2 , 5.3 )] . Proton Pump Inhibitors Advise patients not to take omeprazole or esomeprazole while taking clopidogrel tablets. Dexlansoprazole, lansoprazole, and pantoprazole had less pronounced effects on the antiplatelet activity of clopidogrel tablets than did omeprazole or esomeprazole [s e e Drug Interactions (7.1)] .
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Clopidogrel is a prodrug and is metabolized to a pharmacologically active metabolite and inactive metabolites. A b s o r p ti o n After single and repeated oral doses of 75 mg per day, clopidogrel is rapidly absorbed. Absorption is at least 50%, based on urinary excretion of clopidogrel metabolites.
Effect of food Clopidogrel tablets can be administered with or without food. In a study in healthy male subjects when clopidogrel tablets 75 mg per day was given with a standard breakfast, mean inhibition of ADP-induced platelet aggregation was reduced by less than 9%. The active metabolite AUC 0-24 was unchanged in the presence of food, while there was a 57% decrease in active metabolite C max .
Similar results were observed when a clopidogrel tablet 300 mg loading dose was administered with a high-fat breakfast. Metabolism Clopidogrel is extensively metabolized by two main metabolic pathways: one mediated by esterases and leading to hydrolysis into an inactive carboxylic acid derivative (85% of circulating metabolites) and one mediated by multiple cytochrome P450 enzymes. Cytochromes first oxidize clopidogrel to a 2-oxo-clopidogrel intermediate metabolite.
Subsequent metabolism of the 2-oxo-clopidogrel intermediate metabolite results in formation of the active metabolite, a thiol derivative of clopidogrel. The active metabolite is formed mostly by CYP2C19 with contributions from several other CYP enzymes, including CYP1A2, CYP2B6 and CYP3A. The active thiol metabolite binds rapidly and irreversibly to platelet receptors, thus inhibiting platelet aggregation for the lifespan of the platelet.
The C max of the active metabolite is twice as high following a single 300 mg clopidogrel loading dose as it is after four days of 75 mg maintenance dose. C max occurs approximately 30 to 60 minutes after dosing. In the 75 to 300 mg dose range, the pharmacokinetics of the active metabolite deviates from dose proportionality: 4-fold the dose results in 2.0-fold and 2.7-fold the C max and AUC, respectively.
Elimination Following an oral dose of 14 C-labeled clopidogrel in humans, approximately 50% of total radioactivity was excreted in urine and approximately 46% in feces over the 5 days post dosing. After a single, oral dose of 75 mg, clopidogrel has a half-life of approximately 6 hours. The half-life of the active metabolite is about 30 minutes.
Drug Interactions Effect of other drugs on clopidogrel tablets Clopidogrel is metabolized to its active metabolite in part by CYP2C19. CYP2C19 inducers Concomitant use of strong inducers of CYP2C19 results in increased plasma concentration of the active metabolite of clopidogrel and an increase in platelet inhibition. Rifampin: Coadministration of rifampin 300 mg twice daily for 7 days with 600 mg loading dose of clopidogrel in healthy adults increased the mean AUC and C max of clopidogrel’s thiol metabolites by 3.8-fold.
Mean inhibition of platelet aggregation at 4 hours post-dose was 34% higher in the presence of rifampin compared to clopidogrel administered alone. CYP2C19 inhibitors Concomitant use of certain inhibitors of this enzyme results in reduced plasma concentrations of the active metabolite of clopidogrel and a reduction in platelet inhibition. P r o t o n pump inhibitors (PPI) The effect of proton pump inhibitors (PPI) on the systemic exposure to the clopidogrel active metabolite following multiple doses of clopidogrel tablets 75 mg evaluated in dedicated drug interaction studies is presented in Figure 1.
Figure 1: Exposure to Clopidogrel Active Metabolite Following Multiple Doses of Clopidogrel Tablets 75 mg Alone or with Proton Pump Inhibitors (PPIs) Change relative to Clopidogrel Tablets administered alone Pharmacodynamic and pharmacokinetic parameters measured in these studies showed that the interaction was highest with omeprazole and least with dexlansoprazole. O p i o i d s Coadministration of 5 mg intravenous morphine with 600 mg loading dose of clopidogrel in… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Clopidogrel must be metabolized by CYP450 enzymes to produce the active metabolite that inhibits platelet aggregation. The active metabolite of clopidogrel selectively inhibits the binding of adenosine diphosphate (ADP) to its platelet P2Y 12 receptor and the subsequent ADP- mediated activation of the glycoprotein GPIIb/IIIa complex, thereby inhibiting platelet aggregation. This action is irreversible.
Consequently, platelets exposed to clopidogrel’s active metabolite are affected for the remainder of their lifespan (about 7 to 10 days). Platelet aggregation induced by agonists other than ADP is also inhibited by blocking the amplification of platelet activation by released ADP. Dose-dependent inhibition of platelet aggregation can be seen 2 hours after single oral doses of clopidogrel tablets.
Repeated doses of 75 mg clopidogrel tablets per day inhibit ADP-induced platelet aggregation on the first day, and inhibition reaches steady state between Day 3 and Day 7. At steady state, the average inhibition level observed with a dose of 75 mg clopidogrel tablets per day was between 40% and 60%. Platelet aggregation and bleeding time gradually return to baseline values after treatment is discontinued, generally in about 5 days.
G e r i a t r i c Patients Elderly (≥75 years) and young healthy subjects had similar effects on platelet aggregation. Renally Impaired Patients After repeated doses of 75 mg clopidogrel tablets per day, patients with severe renal impairment (creatinine clearance from 5 to 15 mL/min) and moderate renal impairment (creatinine clearance from 30 to 60 mL/min) showed low (25%) inhibition of ADP-induced platelet aggregation. H e pa ti c a ll y I m pa i r e d Patients After repeated doses of 75 mg clopidogrel tablets per day for 10 days in patients with severe hepatic impairment, inhibition of ADP-induced platelet aggregation was similar to that observed in healthy subjects.
G e n d e r In a small study comparing men and women, less inhibition of ADP-induced platelet aggregation was observed in women.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Acute Coronary Syndrome C U R E The CURE study included 12,562 patients with ACS without ST-elevation (UA or NSTEMI) and presenting within 24 hours of onset of the most recent episode of chest pain or symptoms consistent with ischemia. Patients were required to have either ECG changes compatible with new ischemia (without ST-elevation) or elevated cardiac enzymes or troponin I or T to at least twice the upper limit of normal. Patients were randomized to receive clopidogrel tablets (300 mg loading dose followed by 75 mg once daily) or placebo, and were treated for up to one year.
Patients also received aspirin (75-325 mg once daily) and other standard therapies such as heparin. The use of GPIIb/IIIa inhibitors was not permitted for three days prior to randomization. The patient population was largely White (82%) and included 38% women, and 52% age ≥65 years of age.
Only about 20% of patients underwent revascularization during the initial hospitalization and few underwent emergent or urgent revascularization. The number of patients experiencing the primary outcome (CV death, MI, or stroke) was 582 (9.3%) in the clopidogrel tablets-treated group and 719 (11.4%) in the placebo-treated group, a 20% relative risk reduction (95% CI of 10%-28%; p < 0.001) for the clopidogrel tablets-treated group (see Table 4). T a b l e 4: Outcome Events in the CURE Primary Analysis Outcome Clopidogrel Tablets (+ aspirin) * (n=6259) Placebo (+ aspirin) * ( n=6303) Relative Risk Reduction (%) (95 % CI) Primary outcome (Cardiovascular death, MI, stroke) 582 (9.3 %) 719 (11.4 %) 20 % (10.3, 27.9) P <0.001 All Individual outcome Events: † CV death 318 (5.1 %) 345 (5.5 %) 7 % (-7.7, 20.6) MI 324 (5.2 %) 419 (6.6%) 23 % (11.0, 33.4) Stroke 75 (1.2 %) 87 (1.4%) 14 % (-17.7, 36.6) * Other standard therapies were used as appropriate. † The individual components do not represent a breakdown of the primary and coprimary outcomes, but rather the total number of subjects experiencing an event during the course of the study.
Most of the benefit of clopidogrel tablets occurred in the first two months, but the difference from placebo was maintained throughout the course of the trial (up to 12 months) (see Figure 2). Figure 2: Cardiovascular Death, Myocardial Infarction, and Stroke in the CURE Study The effect of clopidogrel tablets did not differ significantly in various subgroups, as shown in Figure 3. The benefits associated with clopidogrel tablets were independent of the use of other acute and long-term cardiovascular therapies, including heparin/LMWH, intravenous glycoprotein IIb/IIIa (GPIIb/IIIa) inhibitors, lipid-lowering drugs, beta-blockers, and ACE inhibitors.
The efficacy of clopidogrel tablets was observed independently of the dose of aspirin (75-325 mg once daily). The use of oral anticoagulants, nonstudy antiplatelet drugs, and chronic NSAIDs was not allowed in CURE. Figure 3: Hazard Ratio for Patient Baseline Characteristics and On-Study Concomitant Medications/Interventions for the CURE Study F i gure 3: Hazard Ratio for Patient Baseline Characteristics and On-Study Concomitant Medications/Interventions for the CURE Study (continued) The use of clopidogrel tablets in CURE was associated with a decrease in the use of thrombolytic therapy (71 patients [1.1%] in the clopidogrel tablets group, 126 patients [2.0%] in the placebo group; relative risk reduction of 43%), and GPIIb/IIIa inhibitors (369 patients [5.9%] in the clopidogrel tablets group, 454 patients [7.2%] in the placebo group, relative risk reduction of 18%).
The use of clopidogrel tablets in CURE did not affect the number of patients treated with CABG or PCI (with or without stenting) (2253 patients [36.0%] in the clopidogrel tablets group, 2324 patients [36.9%] in the placebo group; relative risk reduction of 4.0%). COMMIT In patients with STEMI, the safety and efficacy of clopidogrel tablets were evaluated in the randomized, placebo-controlled, double-blind study, C… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis & Mutagenesis & Impairment Of Fertility There was no evidence of tumorigenicity when clopidogrel was administered for 78 weeks to mice and 104 weeks to rats at dosages up to 77 mg/kg per day, which afforded plasma exposures >25 times that in humans at the recommended daily dose of 75 mg. Clopidogrel was not genotoxic in four in vitro tests (Ames test, DNA-repair test in rat hepatocytes, gene mutation assay in Chinese hamster fibroblasts, and metaphase chromosome analysis of human lymphocytes) and in one in vivo test (micronucleus test by oral route in mice).
Clopidogrel was found to have no effect on fertility of male and female rats treated prior to pairing and throughout gestation at oral doses up to 400 mg/kg per day (52 times the recommended human dose on a mg/m 2 basis).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis & Mutagenesis & Impairment Of Fertility There was no evidence of tumorigenicity when clopidogrel was administered for 78 weeks to mice and 104 weeks to rats at dosages up to 77 mg/kg per day, which afforded plasma exposures >25 times that in humans at the recommended daily dose of 75 mg. Clopidogrel was not genotoxic in four in vitro tests (Ames test, DNA-repair test in rat hepatocytes, gene mutation assay in Chinese hamster fibroblasts, and metaphase chromosome analysis of human lymphocytes) and in one in vivo test (micronucleus test by oral route in mice).
Clopidogrel was found to have no effect on fertility of male and female rats treated prior to pairing and throughout gestation at oral doses up to 400 mg/kg per day (52 times the recommended human dose on a mg/m 2 basis).
📄 Package Label / Principal Display Panel ▾
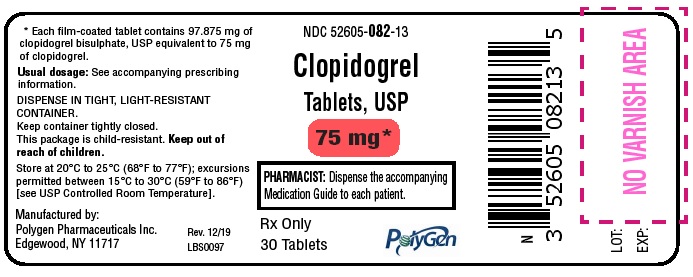
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC - 52605-082-13 Rx Only Clopidogrel Tablets, USP 75 mg 30 Tablets Polygen NDC - 52605-082-10 Rx Only Clopidogrel Tablets, USP 75 mg 1000 Tablets Polygen NDC - 52605-083-13 Rx Only Clopidogrel Tablets, USP 300 mg 30 Tablets Polygen NDC - 52605-083-05 Rx Only Clopidogrel Tablets, USP 300 mg 500 Tablets Polygen clopidogrel-75mg-30s clopidogrel-75mg-1000s clopidogrel-300mg-30s clopidogrel-300mg-500s
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |