
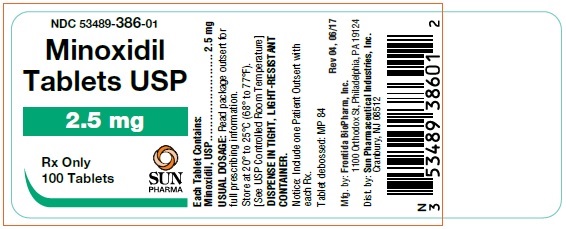
MINOXIDIL 2.5 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Arteriolar Vasodilator class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Minoxidil is used with other medications to treat high blood pressure. It is in a class of medications called vasodilators. It works by relaxing the blood vessels so that blood can flow more easily through the body. High blood pressure is a common condition and when not treated, can cause damage to the brain, heart, blood vessels, kidneys and other parts of the body. Damage to these organs may cause heart disease, a heart attack, heart failure, stroke, kidney failure, loss of vision, and other problems. In addition to taking medication, making lifestyle changes will also help to control your b...
Read the full MedlinePlus article ↗- That's a really common question. Minoxidil tablets are very effective at lowering blood pressure, but they cause two side effects that need to be managed: your heart speeds up, and...
- I've been prescribed minoxidil tablets for blood pressure — why do I need to take other pills with it?
- It takes patience — most people need at least 2 to 4 months of twice-daily use before they notice any regrowth. Some products note that results can start appearing around the 2-mon...
- I'm using a topical minoxidil solution for hair loss. How long before I see results?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Minoxidil — tap one for details:
Minoxidil may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.101 | $10.12 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2616 | $26.16 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.1978 | $19.78 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Minoxidil 2.5 mg 00591-5642-01 | Actavis | 100 tablets | $0.101 | AB | Availability likely | — |
| Minoxidil 2.5 mg 49884-0256-01 | Par | 100 tablets | $0.101 | AB | Availability likely | — |
| Minoxidil 2.5 mgthis 53489-0386-01 | Sun | 100 tablets | $0.101 | AB | Availability likely | — |
| Minoxidil 2.5 mg 68084-0204-01 | American | 100 tablets | $0.101 | AB | Availability likely | — |
| Minoxidil 2.5 mg 42291-0618-01 | AvKARE | 100 tablets | — | — | FDA listed | — |
| Minoxidil 2.5 mg 43353-0342-09 | Aphena | 9000 tablets | — | — | FDA listed | — |
| Minoxidil 2.5 mg 50090-7758-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 51407-0901-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 63629-2232-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 63629-9433-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 68071-3794-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 68788-8273-03 | Preferred | 30 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 71205-0757-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 72162-1489-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 72789-0278-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 82804-0240-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Minoxidil 2.5 mg 71335-3174-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 53489-0386-01 You're viewing this | 100 TABLET in 1 BOTTLE (53489-386-01) | $0.1012 / ea | $10.12 | 1995-12-14 | Active |
| 53489-0386-03 | 250 TABLET in 1 BOTTLE (53489-386-03) | — | — | 1995-12-14 | Active |
| 53489-0386-05 | 500 TABLET in 1 BOTTLE (53489-386-05) | — | — | 1995-12-14 | Active |
| 53489-0386-10 | 1000 TABLET in 1 BOTTLE (53489-386-10) | — | — | 1995-12-14 | Active |
You're viewing the smallest of 4 pack sizes for this product.
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 53489-0386-01?
What is the difference between NDC 53489-0386-01 and NDC 53489-0386-03?
What NDC number is used to bill for this package of MINOXIDIL 2.5 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNINGS Minoxidil tablets contain the powerful antihypertensive agent, minoxidil, which may produce serious adverse effects. It can cause pericardial effusion, occasionally progressing to tamponade, and angina pectoris may be exacerbated. Minoxidil should be reserved for hypertensive patients who do not respond adequately to maximum therapeutic doses of a diuretic and two other antihypertensive agents.
In experimental animals, minoxidil caused several kinds of myocardial lesions as well as other adverse cardiac effects (see Cardiac Lesions in Animals ). Minoxidil must be administered under close supervision, usually concomitantly with therapeutic doses of a beta-adrenergic blocking agent to prevent tachycardia and increased myocardial workload. It must also usually be given with a diuretic, frequently one acting in the ascending limb of the loop of Henle, to prevent serious fluid accumulation.
Patients with malignant hypertension and those already receiving guanethidine (see WARNINGS ) should be hospitalized when minoxidil is first administered so that they can be monitored to avoid too rapid, or large orthostatic, decreases in blood pressure.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Because of the potential for serious adverse effects, minoxidil tablets are indicated only in the treatment of hypertension that is symptomatic or associated with target organ damage and is not manageable with maximum therapeutic doses of a diuretic plus two other antihypertensive drugs. At the present time use in milder degrees of hypertension is not recommended because the benefit-risk relationship in such patients has not been defined. Minoxidil reduced supine diastolic blood pressure by 20 mm Hg or to 90 mm Hg or less in approximately 75% of patients, most of who had hypertension that could not be controlled by other drugs.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Patients over 12 years of age: The recommended initial dosage of minoxidil tablets is 5 mg of minoxidil given as a single daily dose. Daily dosage can be increased to 10, 20 and then to 40 mg in single or divided doses if required for optimum blood pressure control. The effective dosage range is usually 10 to 40 mg per day.
The maximum recommended dosage is 100 mg per day. Patients under 12 years of age: The initial dosage is 0.2 mg/kg minoxidil as a single daily dose. The dosage may be increased in 50 to 100% increments until optimum blood pressure control is achieved.
The effective dosage range is usually 0.25 mg to 1 mg/kg/day. The maximum recommended dosage is 50 mg daily ( see 9. Pediatric Use under PRECAUTIONS ).
Dose frequency: The magnitude of within-day fluctuation of arterial pressure during therapy with minoxidil is directly proportional to the extent of pressure reduction. If supine diastolic pressure has been reduced less than 30 mm Hg, the drug need be administered only once a day; if supine diastolic pressure has been reduced more than 30 mm Hg, the daily dosage should be divided into two equal parts. Frequency of dosage adjustment: Dosage must be titrated carefully according to individual response.
Intervals between dosage adjustments normally should be at least 3 days since the full response to a given dose is not obtained for at least that amount of time. Where a more rapid management of hypertension is required, dose adjustments can be made every 6 hours if the patient is carefully monitored. Concomitant therapy: Diuretic and beta-blocker or other sympathetic nervous system suppressant.
Diuretics: Minoxidil must be used in conjunction with a diuretic in patients relying on renal function for maintaining salt and water balance. Diuretics have been used at the following dosages when starting therapy with minoxidil: hydrochlorothiazide (50 mg, b.i.d.) or other thiazides at equieffective dosage; chlorthalidone (50 to 100 mg, once daily); furosemide (40 mg, b.i.d.). If excessive salt and water retention results in a weight gain of more than 5 pounds, diuretic therapy should be changed to furosemide; if the patient is already taking furosemide, dosage should be increased in accordance with the patient's requirements.
Beta-blocker or other sympathetic nervous system suppressants: When therapy with minoxidil is begun, the dosage of a beta-adrenergic receptor blocking drug should be the equivalent of 80 to 160 mg of propranolol per day in divided doses. If beta-blockers are contraindicated, methyldopa (250 to 750 mg, b.i.d.) may be used instead. Methyldopa must be given for at least 24 hours before starting therapy with minoxidil because of the delay in the onset of methyldopa's action.
Limited clinical experience indicates that clonidine may also be used to prevent tachycardia induced by minoxidil; the usual dosage is 0.1 to 0.2 mg twice daily. Sympathetic nervous system suppressants may not completely prevent an increase in heart rate due to minoxidil but usually do prevent tachycardia. Typically, patients receiving a beta-blocker prior to initiation of therapy with minoxidil have a bradycardia and can be expected to have an increase in heart rate toward normal when minoxidil is added.
When treatment with minoxidil and beta-blocker or other sympathetic nervous system suppressant are begun simultaneously, their opposing cardiac effects usually nullify each other, leading to little change in heart rate.
⛔ Contraindications ▾
CONTRAINDICATIONS Minoxidil tablets are contraindicated in pheochromocytoma, because it may stimulate secretion of catecholamines from the tumor through its antihypertensive action. Minoxidil tablets are contraindicated in those patients with a history of hypersensitivity to any of the components of the preparation.
⚠️ Warnings ▾
WARNINGS 1. Salt and Water Retention Congestive Heart Failure — concomitant use of an adequate diuretic is required — Minoxidil tablets must usually be administered concomitantly with a diuretic adequate to prevent fluid retention and possible congestive heart failure; a high ceiling (loop) diuretic is almost always required. Body weight should be monitored closely.
If minoxidil is used without a diuretic, retention of several hundred milliequivalents of salt and corresponding volumes of water can occur within a few days, leading to increased plasma and interstitial fluid volume and local or generalized edema. Diuretic treatment alone, or in combination with restricted salt intake, will usually minimize fluid retention, although reversible edema did develop in approximately 10% of nondialysis patients so treated. Ascites has also been reported.
Diuretic effectiveness was limited mostly by disease-related impaired renal function. The condition of patients with pre-existing congestive heart failure occasionally deteriorated in association with fluid retention although because of the fall in blood pressure (reduction of afterload), more than twice as many improved than worsened. Rarely, refractory fluid retention may require discontinuation of minoxidil.
Provided that the patient is under close medical supervision, it may be possible to resolve refractory salt retention by discontinuing minoxidil for 1 or 2 days and then resuming treatment in conjunction with vigorous diuretic therapy. 2. Concomitant Treatment to Prevent Tachycardia is Usually Required Minoxidil increases the heart rate.
Angina may worsen or appear for the first time during minoxidil treatment, probably because of the increased oxygen demands associated with increased heart rate and cardiac output. The increase in rate and the occurrence of angina generally can be prevented by the concomitant administration of a beta-adrenergic blocking drug or other sympathetic nervous system suppressant. The ability of beta-adrenergic blocking agents to minimize papillary muscle lesions in animals is further reason to utilize such an agent concomitantly.
Round-the-clock effectiveness of the sympathetic suppressant should be ensured. 3. Pericarditis, Pericardial Effusion and Tamponade There have been reports of pericarditis occurring in association with the use of minoxidil.
The relationship of this association to renal status is uncertain. Pericardial effusion, occasionally with tamponade, has been observed in about 3% of treated patients not on dialysis, especially those with inadequate or compromised renal function. Although in many cases, the pericardial effusion was associated with a connective tissue disease, the uremic syndrome, congestive heart failure, or marked fluid retention, there have been instances in which these potential causes of effusion were not present.
Patients should be observed closely for any suggestion of a pericardial disorder, and echocardiographic studies should be carried out if suspicion arises. More vigorous diuretic therapy, dialysis, pericardiocentesis, or surgery may be required. If the effusion persists, withdrawal of minoxidil should be considered in light of other means of controlling the hypertension and the patient's clinical status.
4. Interaction with Guanethidine Although minoxidil does not itself cause orthostatic hypotension, its administration to patients already receiving guanethidine can result in profound orthostatic effects. If at all possible, guanethidine should be discontinued well before minoxidil is begun.
Where this is not possible, minoxidil therapy should be started in the hospital and the patient should remain institutionalized until severe orthostatic effects are no longer present or the patient has learned to avoid activities that provoke them. 5. Hazard of Rapid Control of Blood Pressure In patients with very severe blood pressure elevation, too rapid control of blood pressure, especially with intravenous agents, can…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS 1. Salt and Water Retention (see WARNINGS: Concomitant Use of Adequate Diuretic is Required ) — Temporary edema developed in 7% of patients who were not edematous at the start of therapy. 2.
Pericarditis, Pericardial Effusion and Tamponade (see WARNINGS ). 3. Dermatologic — Hypertrichosis — Elongation, thickening, and enhanced pigmentation of fine body hair are seen in about 80% of patients taking minoxidil tablets.
This develops within 3 to 6 weeks after starting therapy. It is usually first noticed on the temples, between the eyebrows, between the hairline and the eyebrows, or in the side-burn area of the upper lateral cheek, later extending to the back, arms, legs, and scalp. Upon discontinuation of minoxidil, new hair growth stops, but 1 to 6 months may be required for restoration to pretreatment appearance.
No endocrine abnormalities have been found to explain the abnormal hair growth; thus, it is hypertrichosis without virilism. Hair growth is especially disturbing to children and women and such patients should be thoroughly informed about this effect before therapy with minoxidil is begun. Allergic — Rashes have been reported, including rare reports of bullous eruptions, toxic epidermal necrolysis, and Stevens-Johnson Syndrome.
4. Hematologic — Thrombocytopenia and leukopenia (WBC<3000/mm 3 ) have rarely been reported. 5.
Gastrointestinal — Nausea and/or vomiting has been reported. In clinical trials the incidence of nausea and vomiting associated with the underlying disease has shown a decrease from pretrial levels. 6.
Miscellaneous — Breast tenderness — This developed in less than 1 % of patients. 7. Altered Laboratory Findings — (a) ECG changes — Changes in direction and magnitude of the ECG T-waves occur in approximately 60% of patients treated with minoxidil.
In rare instances a large negative amplitude of the T-wave may encroach upon the S-T segment, but the S-T segment is not independently altered. These changes usually disappear with continuance of treatment and revert to the pretreatment state if minoxidil is discontinued. No symptoms have been associated with these changes, nor have there been alterations in blood cell counts or in plasma enzyme concentrations that would suggest myocardial damage.
Long-term treatment of patients manifesting such changes has provided no evidence of deteriorating cardiac function. At present the changes appear to be nonspecific and without identifiable clinical significance. (b) Effects of hemodilution — hematocrit, hemoglobin and erythrocyte count usually fall about 7% initially and then recover to pretreatment levels.
(c) Other — Alkaline phosphatase increased varyingly without other evidence of liver or bone abnormality. Serum creatinine increased an average of 6% and BUN slightly more, but later declined to pretreatment levels.
🤰 Pregnancy ▾
6. Pregnancy Teratogenic Effects Pregnancy Category C. Oral administration of minoxidil has been associated with evidence of increased fetal resorption in rabbits, but not rats, when administered at five times the maximum recommended oral antihypertensive human dose.
There was no evidence of teratogenic effects in rats and rabbits. Subcutaneous administration of minoxidil to pregnant rats at 80 mg/kg/day was maternally toxic but not teratogenic. Higher subcutaneous doses produced evidence of developmental toxicity.
There are no adequate and well controlled studies in pregnant women. Minoxidil should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. Neonatal hypertrichosis has been reported following exposure to minoxidil during pregnancy.
🧒 Pediatric Use ▾
9. Pediatric Use Use in pediatric patients has been limited to date, particularly in infants. The recommendations under DOSAGE AND ADMINISTRATION can be considered only a rough guide at present and a careful titration is essential.
🧓 Geriatric Use ▾
10. Geriatric Use Clinical studies of minoxidil tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE There have been only a few instances of deliberate or accidental overdosage with minoxidil tablets. One patient recovered after taking 50 mg of minoxidil together with 500 mg of a barbiturate. When exaggerated hypotension is encountered, it is most likely to occur in association with residual sympathetic nervous system blockade from previous therapy (guanethidine-like effects or alpha-adrenergic blockage), which prevents the usual compensatory maintenance of blood pressure.
Intravenous administration of normal saline will help to maintain blood pressure and facilitate urine formation in these patients. Sympathomimetic drugs such as norepinephrine or epinephrine should be avoided because of their excessive cardiac stimulating action. Phenylephrine, angiotensin II, vasopressin, and dopamine all reverse hypotension due to minoxidil, but should only be used if underperfusion of a vital organ is evident.
Radioimmunoassay can be performed to determine the concentration of minoxidil in the blood. At the maximum adult dose of 100 mg/day, peak blood levels of 1641 ng/mL and 2441 ng/mL were observed in two patients, respectively. Due to patient-to-patient variation in blood levels, it is difficult to establish an overdosage warning level.
In general, a substantial increase above 2000 ng/mL should be regarded as overdosage, unless the physician is aware that the patient has taken no more than the maximum dose. Oral LD 50 in rats has ranged from 1321–3492 mg/kg; in mice, 2456–2648 mg/kg.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY 1. General Pharmacologic Properties Minoxidil is an orally effective direct acting peripheral vasodilator that reduces elevated systolic and diastolic blood pressure by decreasing peripheral vascular resistance. Microcirculatory blood flow in animals is enhanced or maintained in all systemic vascular beds.
In man, forearm and renal vascular resistance decline; forearm blood flow increases while renal blood flow and glomerular filtration rate are preserved. Because it causes peripheral vasodilation, minoxidil elicits a number of predictable reactions. Reduction of peripheral arteriolar resistance and the associated fall in blood pressure trigger sympathetic, vagal inhibitory, and renal homeostatic mechanisms, including an increase in renin secretion, that lead to increased cardiac rate and output and salt and water retention.
These adverse effects can usually be minimized by concomitant administration of a diuretic and a beta-adrenergic blocking agent or other sympathetic nervous system suppressant. Minoxidil does not interfere with vasomotor reflexes and therefore does not produce orthostatic hypotension. The drug does not enter the central nervous system in experimental animals in significant amounts, and it does not affect CNS function in man.
2. Effects on Blood Pressure and Target Organs The extent and time-course of blood pressure reduction by minoxidil do not correspond closely to its concentration in plasma. After an effective single oral dose, blood pressure usually starts to decline within one-half hour, reaches a minimum between 2 and 3 hours and recovers at an arithmetically linear rate of about 30%/day.
The total duration of effect is approximately 75 hours. When minoxidil is administered chronically, once or twice a day, the time required to achieve maximum effect on blood pressure with a given daily dose is inversely related to the size of the dose. Thus, maximum effect is achieved on 10 mg/day within 7 days, on 20 mg/day within 5 days, and on 40 mg/day within 3 days.
The blood pressure response to minoxidil is linearly related to the logarithm of the dose administered. The slope of this log-linear dose-response relationship is proportional to the extent of hypertension and approaches zero at a supine diastolic blood pressure of approximately 85 mm Hg. When used in severely hypertensive patients resistant to other therapy, frequently with an accompanying diuretic and beta-blocker, minoxidil tablets usually decreased the blood pressure and reversed encephalopathy and retinopathy.
3. Absorption and Metabolism Minoxidil is at least 90% absorbed from the Gl tract in experimental animals and man. Plasma levels of the parent drug reach maximum within the first hour and decline rapidly thereafter.
The average plasma half-life in man is 4.2 hours. Approximately 90% of the administered drug is metabolized, predominantly by conjugation with glucuronic acid at the N-oxide position in the pyrimidine ring, but also by conversion to more polar products. Known metabolites exert much less pharmacologic effect than minoxidil itself; all are excreted principally in the urine.
Minoxidil does not bind to plasma proteins, and does not cross the bloood brain barrier. Its renal clearance corresponds to the glomerular filtration rate. In the absence of functional renal tissue, minoxidil and its metabolites can be removed by hemodialysis.
4. Cardiac Lesions in Animals Minoxidil produces several cardiac lesions in animals. Some are characteristic of agents that cause tachycardia and diastolic hypotension (beta-agonists like isoproterenol, arterial dilators like hydralazine) while others are produced by a narrower range of agents with arterial dilating properties.
The significance of these lesions for humans is not clear, as they have not been recognized in patients treated with oral minoxidil at systemically active doses, despite formal review of over 150 autopsies of treated patients. (a) Papillary muscle/subendocar…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Minoxidil tablets are available as follows: Minoxidil tablets 2.5 mg are round, scored, white and debossed on one side and on the reverse side. Bottles of 100 NDC 53489-386-01 Bottles of 250 NDC 53489-386-03 Bottles of 500 NDC 53489-386-05 Bottles of 1000 NDC 53489-386-10 Minoxidil tablets 10 mg are round, scored, white and debossed on one side and on the reverse side. Bottles of 100 NDC 53489-387-01 Bottles of 250 NDC 53489-387-03 Bottles of 500 NDC 53489-387-05 Bottles of 1000 NDC 53489-387-10 Figure 2 Figure 3 Figure 4 Figure 5 Store at 20° to 25°C (68° to 77° F). [See USP Controlled Room Temperature] DISPENSE IN TIGHT, LIGHT-RESISTANT CONTAINER.
📦 Storage and Handling ▾
Store at 20° to 25°C (68° to 77° F). [See USP Controlled Room Temperature] DISPENSE IN TIGHT, LIGHT-RESISTANT CONTAINER.
📋 Description ▾
DESCRIPTION Minoxidil tablets contain minoxidil, an antihypertensive peripheral vasodilator. Minoxidil occurs as a white to off-white, crystalline powder, soluble in alcohol and propylene glycol; sparingly soluble in methanol; slightly soluble in water; practically insoluble in chloroform, acetone and ethyl acetate. The chemical name for minoxidil is 2,4-Pyrimidinediamine, 6-(1-piperidinyl)-, 3-oxide.
The structural formula is represented below: Minoxidil tablets for oral administration contain either 2.5 mg or 10 mg of minoxidil. Inactive ingredients: anhydrous lactose, colloidal silicon dioxide, magnesium stearate, microcrystalline cellulose, and sodium starch glycolate. structure
💬 Information for Patients ▾
2. Information for patient The patient should be fully aware of the importance of continuing all of his antihypertensive medications and of the nature of symptoms that would suggest fluid overload. A patient brochure has been prepared and is included with each minoxidil package. The text of this brochure is reprinted at the end of the insert.
💬 Patient Medication Information ▾
PATIENT INFORMATION Minoxidil tablets contain minoxidil, a medicine for the treatment of high blood pressure in the patient who has not been controlled or is experiencing unacceptable side effects with other medications. It must usually be taken with other medicines. Be absolutely sure to take all of your medicines for high blood pressure according to your doctor's instructions.
Do not stop taking minoxidil unless your doctor tells you to. Do not give any of your medicine to other people. It is important that you look for the warning signals of certain undesired effects of minoxidil.
Call your doctor if they occur. Your doctor will need to see you regularly while you are taking minoxidil. Be sure to keep all your appointments or to arrange for new ones if you must miss one.
Do not hesitate to call your doctor if any discomforts or problems occur. The information here is intended to help you take minoxidil properly. It does not tell you all there is to know about minoxidil.
There is a more technical leaflet that you may request from the pharmacist; you may need your doctor's help in understanding parts of that leaflet. What is Minoxidil? Minoxidil tablets contain minoxidil which is a drug for lowering the blood pressure.
It works by relaxing and enlarging certain small blood vessels so that blood flows through them more easily. Why lower blood pressure? Your doctor has prescribed minoxidil to lower your blood pressure and protect vital parts of your body.
Uncontrolled blood pressure can cause stroke, heart failure, blindness, kidney failure and heart attacks. Most people with high blood pressure need to take medicines to treat it for their whole lives. Who should take Minoxidil tablets?
There are many people with high blood pressure, but most of them do not need minoxidil. Minoxidil is used ONLY when your doctor decides that: your high blood pressure is severe; your high blood pressure is causing symptoms or damage to vital organs; and other medicines did not work well enough or had very disturbing side effects. Minoxidil should be taken only when a doctor prescribes it.
Never give any of your minoxidil tablets, or any other high blood pressure medicine, to a friend or relative. Pregnancy: In some cases doctors may prescribe minoxidil for women who are pregnant or who are planning to have children. However, its safe use in pregnancy has not been established.
Laboratory animals had a reduced ability to become pregnant and a reduced survival of offspring while taking minoxidil. If you are pregnant or are planning to become pregnant, be sure to tell your doctor. How to take Minoxidil tablets.
Usually, your doctor will prescribe two other medicines along with minoxidil. These will help lower blood pressure and will help prevent undesired effects of minoxidil. Often, when a medicine like minoxidil lowers blood pressure, your body tries to return the blood pressure to the original higher level.
It does this by holding on to water and salt (so there will be more fluid to pump) and by making your heart beat faster. To prevent this, your doctor will usually prescribe a water tablet to remove the extra salt and water from your body (a diuretic: dye-u-RET-tic) and another medicine to slow your heart beat. You must follow your doctor's instructions exactly, taking all the prescribed medicines, in the right amounts, each day.
These medicines will help keep your blood pressure down. The water tablet and heart beat medicine will help prevent the undesired effects of minoxidil. Minoxidil tablets come in two strengths (2.5 milligrams and 10 milligrams) that are marked on each tablet.
Pay close attention to the tablet markings to be sure you are taking the correct strength. Your doctor may prescribe half a tablet; the tablets are scored (partly cut on one side) so that you can easily break them. When you first start taking minoxidil, your doctor may need to see you often in order to adjust your dosage.
Take all your medicine according to the sch…