
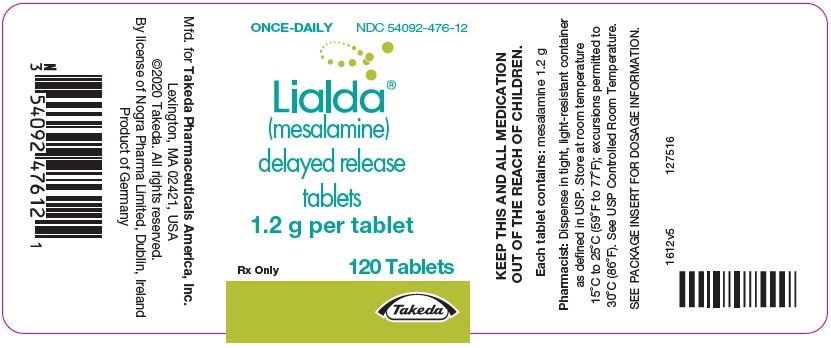
Lialda mesalamine 1.2 g Tablet, Delayed Release, 120-count
Other active recalls for Mesalamine (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Aminosalicylate class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Mesalamine works to reduce inflammation directly in the lining of your colon or rectum. Depending on which product you've been prescribed, it can help bring an active flare of ulce...
- What exactly is mesalamine supposed to do for me?
- It really does matter, and they're not interchangeable. The form your doctor chose depends on where in your bowel the inflammation is. Rectal suppositories (like CANASA) treat infl...
- There are so many different forms — pills, enemas, suppositories. Does it matter which one I use?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mesalamine — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 74G4R6TH13
A synthetic polymer made by combining two plastic-like chemicals. It forms a coating on tablets or capsules that dissolves at a specific point in the digestive tract, controlling where and when the medicine releases.
-
UNII 5KY68S2577
A synthetic plastic polymer made from two chemical compounds combined in a specific ratio. It forms a coating on tablets and capsules to control how and where the medication dissolves in the digestive tract.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 8Z96QXD6UM
Triethyl citrate is a clear liquid derived from citric acid. It acts as a plasticizer and solvent in tablet coatings and film formulations, helping the coating remain flexible and adhere properly to the medicine.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $8.950 | $1,073.94 / 120 tablets |
| Medicaid paysCMS SDUD · 12 mo | $8.82 | $1,057.88 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $9.18 | $1,101.44 / 120 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mesalamine 1.2 g 00527-3012-48 | Lannett | 120 tablets | $0.795 | AB | Availability likely | save 91% |
| Mesalamine 1.2 g 00591-2245-22 | Actavis | 120 tablets | $0.795 | AB | Availability likely | save 91% |
| mesalamine 1.2 g 00904-6832-04 | Major | 1 tablet | $0.795 | AB | Availability likely | save 91% |
| Mesalamine 1.2 g 54092-0100-01 | Takeda | 120 tablets | $0.795 | AB | Availability likely | save 91% |
| Mesalamine 1.2 g 60687-0397-25 | American | 1 tablet | $0.795 | AB | Availability likely | save 91% |
| Mesalamine 1.2 g 62135-0714-12 | Chartwell | 120 tablets | $0.795 | AB | Availability likely | save 91% |
| Mesalamine 1.2 g 63304-0175-13 | Sun | 120 tablets | $0.795 | AB | Availability likely | save 91% |
| mesalamine 1.2 g 68382-0711-19 | Zydus | 120 tablets | $0.795 | AB | Availability likely | save 91% |
| Mesalamine 1.2 g 72603-0304-01 | NorthStar | 120 tablets | $0.795 | AB | Availability likely | save 91% |
| Lialda 1.2 gthis 54092-0476-12 | Takeda | 120 tablets | $8.949 | AB | Availability likely | — |
| Mesalamine 1.2 g 31722-0043-05 | Camber | 500 tablets | — | AB | FDA listed | — |
| mesalamine 1.2 g 51407-0900-12 | Golden | 120 tablets | — | AB | FDA listed | — |
| mesalamine 1.2 g 70771-1071-01 | Zydus | 120 tablets | — | AB | FDA listed | — |
| Mesalamine 1.2 g 72162-2213-02 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Mesalamine 1.2 g 72162-2231-02 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Mesalamine 1.2 g 84612-0175-13 | Nuvaila | 120 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 54092-0476-01 | 120 TABLET, DELAYED RELEASE in 1 BOTTLE (54092-476-01) | $8.95 / ea | $1,073.94 | 2007-01-16 | Active |
| 54092-0476-02 | 12 BOTTLE in 1 CARTON (54092-476-02) / 120 TABLET, DELAYED RELEASE in 1 BOTTLE (54092-476-01) | $8.95 / ea | $12,887.24 | 2007-01-16 | Active |
| 54092-0476-08 | 3 CARTON in 1 CARTON (54092-476-08) / 8 BLISTER PACK in 1 CARTON / 1 TABLET, DELAYED RELEASE in 1 BLISTER PACK | — | — | 2007-01-16 | Active |
| 54092-0476-12 You're viewing this | 120 TABLET, DELAYED RELEASE in 1 BOTTLE (54092-476-12) | $8.95 / ea | $1,073.94 | 2007-01-16 | Active |
This pack effectively ties for the lowest per-ea cost of the 3 priced pack sizes ($8.95 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 54092-0476-12?
What is the difference between NDC 54092-0476-12 and NDC 54092-0476-01?
What NDC number is used to bill for this package of Lialda mesalamine 1.2 g Tablet, Delayed Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE LIALDA ® is indicated for the: induction and maintenance of remission in adult patients with mildly to moderately active ulcerative colitis. treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg. LIALDA is an aminosalicylate indicated for the: induction and maintenance of remission in adult patients with mildly to moderately active ulcerative colitis. ( 1 ) treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Administration Instructions Evaluate renal function prior to initiation of LIALDA and periodically while on therapy. ( 2 , 5.1 ) Swallow LIALDA tablets whole; do not split or crush. ( 2 ) Administer LIALDA tablets with food.
( 2 ) Drink an adequate amount of fluids. ( 2 , 5.8 ) Recommended Dosage in Adults For induction of remission : 2.4 g to 4.8 g (two to four 1.2-g tablets) once daily. ( 2 ) For maintenance of remission : 2.4 g (two 1.2-g tablets) once daily.
( 2 ) Recommended Dosage in Pediatric Patients The recommended dosage for treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg who can swallow tablets whole is shown below: ( 2 ) Weight of Pediatric Patient Once Daily LIALDA Dosage Week 0 to Week 8 After Week 8 24 kg to 35 kg 2.4 g (two 1.2-g tablets) 1.2 g (one 1.2-g tablet) Greater than 35 kg to 50 kg 3.6 g (three 1.2-g tablets) 2.4 g (two 1.2-g tablets) Greater than 50 kg 4.8 g (four 1.2-g tablets) 2.4 g (two 1.2-g tablets) Administration Instructions Evaluate renal function prior to initiation of LIALDA and periodically while on therapy.
Swallow LIALDA tablets whole; do not split or crush. Administer LIALDA tablets with food [see Clinical Pharmacology (12.3) ] . Drink an adequate amount of fluids [see Warnings and Precautions (5.8) ] .
Adults The recommended dosage for the induction of remission in adult patients with mildly to moderately active ulcerative colitis is 2.4 g to 4.8 g (two to four 1.2-g tablets) taken once daily. The recommended dosage for the maintenance of remission is 2.4 g (two 1.2-g tablets) taken once daily. Pediatric Patients The recommended dosage for treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg who can swallow tablets whole is shown in Table 1: Table 1: Recommended Dosage of LIALDA for the Treatment of Mildly to Moderately Active Ulcerative Colitis in Pediatric Patients Weighing at least 24 kg Weight of Pediatric Patient Once Daily LIALDA Dosage Week 0 to Week 8 After Week 8 24 kg to 35 kg 2.4 g (two 1.2-g tablets) 1.2 g (one 1.2-g tablet) Greater than 35 kg to 50 kg 3.6 g (three 1.2-g tablets) 2.4 g (two 1.2-g tablets) Greater than 50 kg 4.8 g (four 1.2-g tablets) 2.4 g (two 1.2-g tablets)
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS The red-brown ellipsoidal delayed-release tablet containing 1.2 g mesalamine is debossed on one side and imprinted with S476. Delayed-Release Tablets: 1.2 g ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS LIALDA is contraindicated in patients with known or suspected hypersensitivity to salicylates, aminosalicylates, or to any of the ingredients of LIALDA [see Warnings and Precautions (5.3) , Adverse Reactions (6.2) , Description (11) ] . Known or suspected hypersensitivity to salicylates or aminosalicylates or to any of the ingredients of LIALDA. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Renal Impairment : Assess renal function at the beginning of treatment and periodically during treatment. Evaluate the risks and benefits of LIALDA in patients with known renal impairment or taking nephrotoxic drugs. Discontinue LIALDA if renal function deteriorates while on therapy.
( 5.1 , 7.1 , 8.6 ) Mesalamine-Induced Acute Intolerance Syndrome : Symptoms may be difficult to distinguish from an ulcerative colitis exacerbation. Monitor for worsening symptoms while on treatment. Discontinue treatment if acute intolerance syndrome is suspected.
( 5.2 ) Hypersensitivity Reactions, including myocarditis and pericarditis : Evaluate patients immediately and discontinue LIALDA if a hypersensitivity reaction is suspected. ( 5.3 ) Hepatic Failure : Evaluate the risks and benefits of using LIALDA in patients with known liver impairment. ( 5.4 ) Severe Cutaneous Adverse Reactions : Discontinue at the first signs or symptoms of severe cutaneous adverse reactions or other signs of hypersensitivity and consider further evaluation.
( 5.5 ) Upper Gastrointestinal Tract Obstruction : Avoid in patients with pyloric stenosis or other organic or functional obstruction. ( 5.6 ) Photosensitivity : Advise patients with pre-existing skin conditions to avoid sun exposure, wear protective clothing, and use a broad-spectrum sunscreen when outdoors. ( 5.7 ) Nephrolithiasis : Cases of nephrolithiasis have been reported with the use of mesalamine.
Mesalamine-containing stones are undetectable by standard radiography or computed tomography (CT). Ensure adequate hydration during treatment. ( 5.8 ) Interference With Laboratory Tests : Use of mesalamine may lead to spuriously elevated test results when measuring urinary normetanephrine by liquid chromatography with electrochemical detection.
( 5.9 )
5.1Renal Impairment Renal impairment, including minimal change disease, acute and chronic interstitial nephritis, and, rarely, renal failure, has been reported in patients given products such as LIALDA that contain mesalamine or are converted to mesalamine. In animal studies, the kidney was the principal organ of mesalamine toxicity [see Adverse Reactions (6.2) , Nonclinical Toxicology (13.2) ] . Evaluate renal function prior to initiation of LIALDA therapy and periodically while on therapy.
Evaluate the risks and benefits of using LIALDA in patients with known renal impairment, history of renal disease, or taking concomitant nephrotoxic drugs. Discontinue LIALDA if renal function deteriorates while on therapy [see Drug Interactions (7.1) , Use in Specific Populations (8.6) ] .
5.2Mesalamine-Induced Acute Intolerance Syndrome Mesalamine has been associated with an acute intolerance syndrome that may be difficult to distinguish from an exacerbation of ulcerative colitis. Although the exact frequency of occurrence has not been determined, it has occurred in 3% of patients in controlled clinical trials of mesalamine or sulfasalazine. Symptoms include cramping, acute abdominal pain, and bloody diarrhea, and sometimes fever, headache, and rash.
Monitor patients closely for worsening of these symptoms while on treatment. If acute intolerance syndrome is suspected, promptly discontinue treatment with LIALDA.
5.3Hypersensitivity Reactions Hypersensitivity reactions have been reported in patients taking sulfasalazine. Some of these patients may have a similar reaction to LIALDA tablets or to other compounds that contain or are converted to mesalamine. As with sulfasalazine, mesalamine-induced hypersensitivity reactions may present as internal organ involvement, including myocarditis, pericarditis, nephritis, hepatitis, pneumonitis, and hematologic abnormalities.
Evaluate patients immediately if signs or symptoms of a hypersensitivity reaction are present. Discontinue LIALDA if an alternative etiology for the signs or symptoms cannot be established.
5.4Hepatic Failure There have been reports of hepatic failure in patients with pre-existing l…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in labeling: Renal impairment, including renal failure [see Warnings and Precautions (5.1) ] Mesalamine-induced acute intolerance syndrome [see Warnings and Precautions (5.2) ] Hypersensitivity reactions [see Warnings and Precautions (5.3) ] Hepatic failure [see Warnings and Precautions (5.4) ] Severe cutaneous adverse reactions [see Warnings and Precautions (5.5) ] Upper gastrointestinal tract obstruction [see Warnings and Precautions (5.6) ] Photosensitivity [see Warnings and Precautions (5.7) ] Nephrolithiasis [see Warnings and Precautions (5.8) ] Most common adverse reactions in: adults (≥2%) are headache, flatulence, liver function test abnormal, abdominal pain, and diarrhea.
( 6.1 ) pediatric patients (≥5%) are abdominal pain, upper respiratory tract infection, vomiting, anemia, headache, and viral infection. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Takeda Pharmaceuticals at 1-800-828-2088 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adults Induction The most common adverse reactions occurring in at least 1% of LIALDA- or placebo-treated adult patients with mildly to moderately active ulcerative colitis in two eight-week, randomized, double-blind, placebo-controlled trials (Study 1 and Study 2) [see Clinical Studies (14.1) ] are listed in Table 2.
Table 2: Adverse Reactions Reported in at least 1% of patients in at least one LIALDA group and greater than placebo in Two Eight-Week, Placebo-Controlled Trials of Induction Therapy (Study 1 and Study 2) in Adults with Mildly to Moderately Active Ulcerative Colitis Adverse Reaction LIALDA 2.4 g once daily LIALDA 4.8 g once daily Placebo (n=177) (n=179) (n=179) Headache 6% 3% <1% Flatulence 4% 3% 3% Liver Function Test Abnormal <1% 2% 1% Alopecia 0 1% 0 Pruritus <1% 1% 1% Pancreatitis occurred in less than 1% of patients during induction in clinical trials and resulted in discontinuation of therapy with LIALDA in patients experiencing this event.
Maintenance of Remission A LIALDA dosage of 2.4 g/day, administered as either 1.2 g twice daily or 2.4 g once daily, was evaluated for safety in three maintenance trials in patients with mildly to moderately active ulcerative colitis: a 6-month double-blind, active-controlled study (Study 3) [see Clinical Studies (14.1) ] and two 12- to 14-month open-label studies. The most common adverse reactions with LIALDA in these maintenance trials are listed in Table 3. Table 3: Adverse Reactions Reported in at least 1% of patients in Three Trials of Maintenance of Remission in Adults with Ulcerative Colitis LIALDA 2.4 g/day Administered either as 1.2 g twice daily or 2.4 g once daily (n=1082) Adverse Reaction % Headache 3% Liver function test abnormal 2% Abdominal pain 2% Diarrhea 2% Abdominal distension 1% Abdominal pain upper 1% Dyspepsia 1% Back pain 1% Rash 1% Arthralgia 1% Fatigue 1% Hypertension 1% The following adverse reactions, presented by body system, were reported in less than 1% of LIALDA-treated patients with ulcerative colitis in either induction or maintenance trials: Cardiac Disorder : tachycardia Ear and Labyrinth Disorders : ear pain Gastrointestinal Disorders : abdominal distention, colitis, diarrhea, flatulence, nausea, pancreatitis, rectal polyp, vomiting General Disorders and Administrative Site Disorders : asthenia, face edema, fatigue, pyrexia Investigations : decreased platelet count Musculoskeletal and Connective Tissue Disorders : arthralgia, back pain Nervous System Disorders : dizziness, somnolence, tremor Respiratory, Thoracic and Mediastinal Disorders : pharyngolaryngeal pain Skin and Subcutaneous Tissue Dis…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Nephrotoxic Agents including NSAIDs : Increased risk of nephrotoxicity; monitor for changes in renal function and mesalamine-related adverse reactions. ( 7.1 ) Azathioprine or 6-Mercaptopurine : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 7.2 )
7.1Nephrotoxic Agents, Including Non-Steroidal Anti-Inflammatory Drugs The concurrent use of mesalamine with known nephrotoxic agents, including non-steroidal anti-inflammatory drugs (NSAIDs), may increase the risk of nephrotoxicity. Monitor patients taking nephrotoxic drugs for changes in renal function and mesalamine-related adverse reactions [see Warnings and Precautions (5.1) ] .
7.2Azathioprine and 6-Mercaptopurine The concurrent use of mesalamine with azathioprine or 6-mercaptopurine and/or any other drugs known to cause myelotoxicity may increase the risk for blood disorders, bone marrow failure, and associated complications. If concomitant use of LIALDA and azathioprine or 6-mercaptopurine cannot be avoided, monitor blood tests, including complete blood cell counts and platelet counts.
7.3Interference with Urinary Normetanephrine Measurements Use of LIALDA may lead to spuriously elevated test results when measuring urinary normetanephrine by liquid chromatography with electrochemical detection [see Warnings and Precautions (5.9) ] . Consider an alternative, selective assay for normetanephrine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Patients : Increased risk of blood dyscrasias; monitor complete blood cell counts and platelet counts. ( 8.5 )
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ). There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations ) . In animal reproduction studies, there were no adverse developmental outcomes with administration of oral mesalamine during organogenesis to pregnant rats and rabbits at doses 1.8 and 2.9 times, respectively, the maximum recommended human dose (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk of major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies with mesalamine during organogenesis have been performed in rats at doses up to 1000 mg/kg/day (1.8 times the maximum recommended human dose based on a body surface area comparison) and rabbits at doses up to 800 mg/kg/day (2.9 times the maximum recommended human dose based on a body surface area comparison) and have revealed no evidence of harm to the fetus due to mesalamine.
8.2Lactation Risk Summary Data from published literature report the presence of mesalamine and its metabolite, N-acetyl-5-aminosalicylic acid in human milk in small amounts with relative infant doses (RID) of 0.1% or less for mesalamine (see Data ) . There are case reports of diarrhea in breastfed infants exposed to mesalamine (see Clinical Considerations ) . There is no information on the effects of the drug on milk production.
The lack of clinical data during lactation precludes a clear determination of the risk of LIALDA to an infant during lactation; therefore, the developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for LIALDA and any potential adverse effects on the breastfed child from LIALDA or from the underlying maternal condition. Clinical Considerations Advise the caregiver to monitor the breastfed infant for diarrhea. Data In published lactation studies, maternal mesalamine doses from various oral and rectal formulations and products ranged from 500 mg to 4.8 g daily.
The average concentration of mesalamine in milk ranged from non-detectable to 0.5 mg/L. The average concentration of…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during pregnancy have not reliably informed an association with mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes (see Data ). There are adverse effects on maternal and fetal outcomes associated with ulcerative colitis in pregnancy (see Clinical Considerations ) . In animal reproduction studies, there were no adverse developmental outcomes with administration of oral mesalamine during organogenesis to pregnant rats and rabbits at doses 1.8 and 2.9 times, respectively, the maximum recommended human dose (see Data ) .
The estimated background risk of major birth defects and miscarriage for the indicated populations is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriages in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and embryo/fetal risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks of gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth. Data Human Data Published data from meta-analyses, cohort studies, and case series on the use of mesalamine during early pregnancy (first trimester) and throughout pregnancy have not reliably informed an association of mesalamine and major birth defects, miscarriage, or adverse maternal or fetal outcomes.
There is no clear evidence that mesalamine exposure in early pregnancy is associated with an increased risk of major congenital malformations, including cardiac malformations. Published epidemiologic studies have important methodological limitations which hinder interpretation of the data, including inability to control for confounders, such as underlying maternal disease, maternal use of concomitant medications, and missing information on the dose and duration of use for mesalamine products. Animal Data Reproduction studies with mesalamine during organogenesis have been performed in rats at doses up to 1000 mg/kg/day (1.8 times the maximum recommended human dose based on a body surface area comparison) and rabbits at doses up to 800 mg/kg/day (2.9 times the maximum recommended human dose based on a body surface area comparison) and have revealed no evidence of harm to the fetus due to mesalamine.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of LIALDA have been established for the treatment of mildly to moderately active ulcerative colitis in pediatric patients weighing at least 24 kg. Use of LIALDA in this population is supported by evidence from adequate and well-controlled trials in adults, a multicenter, randomized, double-blind, parallel group trial in 105 pediatric patients 5 to 17 years of age, and additional pharmacokinetic analyses. The safety profile in pediatric patients was similar to that observed in adults [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14.2) ] .
The safety and effectiveness of LIALDA have not been established in patients weighing less than 24 kg.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of LIALDA did not include sufficient numbers of patients aged 65 years and over to determine whether they respond differently from younger patients. Reports from uncontrolled clinical studies and postmarketing reporting systems suggested a higher incidence of blood dyscrasias (i.e., agranulocytosis, neutropenia, and pancytopenia) in patients who were 65 years or older who were taking mesalamine-containing products such as LIALDA compared to younger patients. Monitor complete blood cell counts and platelet counts in elderly patients during treatment with LIALDA.
Systemic exposures are increased in elderly subjects [see Clinical Pharmacology (12.3) ]. In general, consider the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy in elderly patients when prescribing LIALDA. Consider starting at the low end of the dosing range for induction in elderly patients [see Dosage and Administration (2) , Use in Specific Populations (8.6) ] .
🆘 Overdosage ▾
10 OVERDOSAGE LIALDA is an aminosalicylate, and symptoms of salicylate toxicity may include nausea, vomiting, abdominal pain, tachypnea, hyperpnea, tinnitus, and neurologic symptoms (headache, dizziness, confusion, seizures). Severe intoxication with salicylates may lead to electrolyte and blood pH imbalance, and potentially end organ (e.g., renal and liver) damage. There is no specific known antidote for mesalamine overdose; however, conventional therapy for salicylate toxicity may be beneficial in the event of acute overdosage and may include gastrointestinal tract decontamination to prevent further absorption.
Correct fluid and electrolyte imbalance by the administration of appropriate intravenous therapy and maintain adequate renal function. LIALDA is a pH-dependent, delayed-release product and this factor should be considered when treating a suspected overdose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of mesalamine is not fully understood, but it appears to have a topical anti-inflammatory effect on the colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase and lipoxygenase pathways, is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
12.3Pharmacokinetics Absorption The total absorption of mesalamine from LIALDA 2.4 g or 4.8 g given once daily for 14 days to healthy subjects was found to be approximately 21% to 22% of the administered dose. Gamma-scintigraphy studies have shown that a single dose of LIALDA 1.2 g (one tablet) passed intact through the upper gastrointestinal tract of fasted healthy subjects. Scintigraphic images showed a trail of radio-labeled tracer in the colon, suggesting that mesalamine had distributed through this region of the gastrointestinal tract.
In a single-dose study, LIALDA 1.2 g, 2.4 g, and 4.8 g were administered in the fasted state to healthy subjects. Plasma concentrations of mesalamine were detectable after 2 hours and reached a maximum by 9-12 hours on average for the doses studied. The pharmacokinetic parameters are highly variable among subjects (Table 4).
Mesalamine systemic exposure in terms of area under the plasma concentration-time curve (AUC) was slightly more than dose proportional between 1.2 g and 4.8 g LIALDA. Maximum plasma concentrations (C max ) of mesalamine increased approximately dose proportionately between 1.2 g and 2.4 g and sub-proportionately between 2.4 g and 4.8 g of LIALDA, with the dose normalized value at 4.8 g representing, on average, 74% of that at 2.4 g based on geometric means. Table 4: Mean (SD) Pharmacokinetic Parameters for Mesalamine Following Single-Dose Administration of LIALDA Under Fasting Conditions Parameter Arithmetic mean of parameter values are presented except for T max and T lag . of Mesalamine LIALDA 1.2 g (N=47) LIALDA 2.4 g (N=48) LIALDA 4.8 g (N=48) AUC 0-t (ng∙h/mL) 9039 N=43, (5054) 20538 (12980) 41434 (26640) AUC 0-∞ (ng∙h/mL) 9578 N=27, (5214) 21084 (13185) 44775 N=36, (30302) C max (ng/mL) 857 (638) 1595 (1484) 2154 (1140) T max Median (min, max), (h)
9.0N=46, (4.0-32.1) 12.0 (4.0-34.1) 12.0 (4.0-34.0) T lag (h) 2.0 (0-8.0) 2.0 (1.0-4.0) 2.0 (1.0-4.0) T 1/2 (h) (Terminal Phase) 8.56 (6.38)
7.05N=33 (5.54) 7.25 (8.32) Food Effects Administration of a single dose of LIALDA 4.8 g with a high-fat meal resulted in further delay in absorption, and plasma concentrations of mesalamine were detectable 4 hours following dosing. However, a high-fat meal increased systemic exposure of mesalamine (mean C max : increased 91%; mean AUC: increased 16%) compared to results in the fasted state. LIALDA was administered with food in the controlled clinical trials [see Dosage and Administration (2) ] .
In a single- and multiple-dose pharmacokinetic study of LIALDA, 2.4 g or 4.8 g was administered once daily with standard meals to 28 healthy subjects per dose group. Plasma concentrations of mesalamine were detectable after 4 hours and were maximal by 8 hours after the single dose. Steady state was achieved generally by 2 days after dosing.
Mean AUC at steady state was only modestly greater (1.1- to 1.4-fold) than predictable from single dose pharmacokinetics. Distribution Mesalamine is approximately 43% bound to plasma proteins at the concentration of 2.5 mcg/mL. Elimination Metabolism The only major metabolite of mesalamine (5-aminosalicylic acid) is N-acetyl-5-aminosalicylic acid.
Its formation is brought about by N-acetyltransferase (NAT) activity in the liver and intestinal mucosa cells, principally by NAT-1. Excretion Excretion of mesalamine is mainly via the renal route following metabolism to N-acetyl-5-aminosalicylic acid (acetylation); however, there is also limited excretion of the…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of mesalamine is not fully understood, but it appears to have a topical anti-inflammatory effect on the colonic epithelial cells. Mucosal production of arachidonic acid metabolites, both through the cyclooxygenase and lipoxygenase pathways, is increased in patients with ulcerative colitis, and it is possible that mesalamine diminishes inflammation by blocking cyclooxygenase and inhibiting prostaglandin production in the colon.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING LIALDA is available as red-brown, ellipsoidal, film-coated, delayed-release tablets containing 1.2 g mesalamine, and debossed on one side imprinted with S476. NDC 54092-476-12 HDPE Bottle with a child-resistant closure of 120 delayed-release tablets. Store at room temperature 15°C to 25°C (59°F to 77°F); excursions permitted to 30°C (86°F). See USP Controlled Room Temperature.
📦 Storage and Handling ▾
Store at room temperature 15°C to 25°C (59°F to 77°F); excursions permitted to 30°C (86°F). See USP Controlled Room Temperature.
📋 Description ▾
11 DESCRIPTION Each LIALDA delayed-release tablet for oral administration contains 1.2 g 5-aminosalicylic acid (5-ASA; mesalamine), an anti-inflammatory agent. Mesalamine also has the chemical name 5-amino-2-hydroxybenzoic acid and its structural formula is: Molecular formula: C 7 H 7 NO 3 Molecular weight: 153.14 The tablet is coated with a pH-dependent polymer film, which breaks down at or above pH 6.8, normally in the terminal ileum where mesalamine then begins to be released from the tablet core. The tablet core contains mesalamine with hydrophilic and lipophilic excipients and provides for extended release of mesalamine.
The inactive ingredients of LIALDA are sodium carboxymethylcellulose, carnauba wax, stearic acid, silica (colloidal hydrated), sodium starch glycolate (type A), talc, magnesium stearate, methacrylic acid copolymer types A and B, triethylcitrate, titanium dioxide, red ferric oxide, and polyethylene glycol 6000. image description
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Renal Impairment Inform patients that LIALDA may decrease their renal function, especially if they have known renal impairment or are taking nephrotoxic drugs, and periodic monitoring of renal function will be performed while they are on therapy. Advise patients to complete all blood tests ordered by their healthcare provider [see Warnings and Precautions (5.1) ] . Mesalamine-Induced Acute Intolerance Syndrome and Other Hypersensitivity Reactions Instruct patients to stop taking LIALDA and report to their healthcare provider if they experience new or worsening symptoms of acute intolerance syndrome (cramping, abdominal pain, bloody diarrhea, fever, headache, and rash) or other symptoms suggestive of mesalamine-induced hypersensitivity [see Warnings and Precautions (5.2 , 5.3) ] .
Hepatic Failure Advise patients with known liver disease to contact their healthcare provider if they experience signs or symptoms of worsening liver function [see Warnings and Precautions (5.4) ] . Severe Cutaneous Adverse Reactions Inform patients of the signs and symptoms of severe cutaneous adverse reactions. Instruct patients to stop taking LIALDA and report to their healthcare provider at first appearance of a severe cutaneous adverse reaction or other sign of hypersensitivity [see Warnings and Precautions (5.5) ] .
Upper Gastrointestinal Tract Obstruction Advise patients to contact their healthcare provider if they experience signs and symptoms of upper gastrointestinal tract obstruction [see Warnings and Precautions (5.6) ] . Photosensitivity Advise patients with pre-existing skin conditions to avoid sun exposure, wear protective clothing, and use a broad-spectrum sunscreen when outdoors [see Warnings and Precautions (5.7) ] . Nephrolithiasis Instruct patients to drink an adequate amount of fluids during treatment in order to minimize the risk of kidney stone formation and to contact their healthcare provider if they experience signs or symptoms of a kidney stone (e.g., severe side or back pain, blood in the urine) [see Warnings and Precautions (5.8) ] .
Blood Disorders Inform elderly patients and those taking azathioprine or 6-mercaptopurine of the risk for blood disorders and the need for periodic monitoring of complete blood cell counts and platelet counts while on therapy. Advise patients to complete all blood tests ordered by their healthcare provider [see Drug Interactions (7.2) , Use in Specific Populations (8.5) ] . Administration Instruct patients: Swallow LIALDA tablets whole; do not split or crush.
Take LIALDA tablets with food [see Clinical Pharmacology (12.3) ] . Urine may become discolored reddish-brown while taking LIALDA when it comes in contact with surfaces or water treated with hypochlorite-containing bleach. If discolored urine is observed, advise patients to observe their urine flow.
Report to the healthcare provider only if urine is discolored on leaving the body, before contact with any surface or water (e.g., in the toilet). Drink an adequate amount of fluids [see Warnings and Precautions (5.8) ] .