
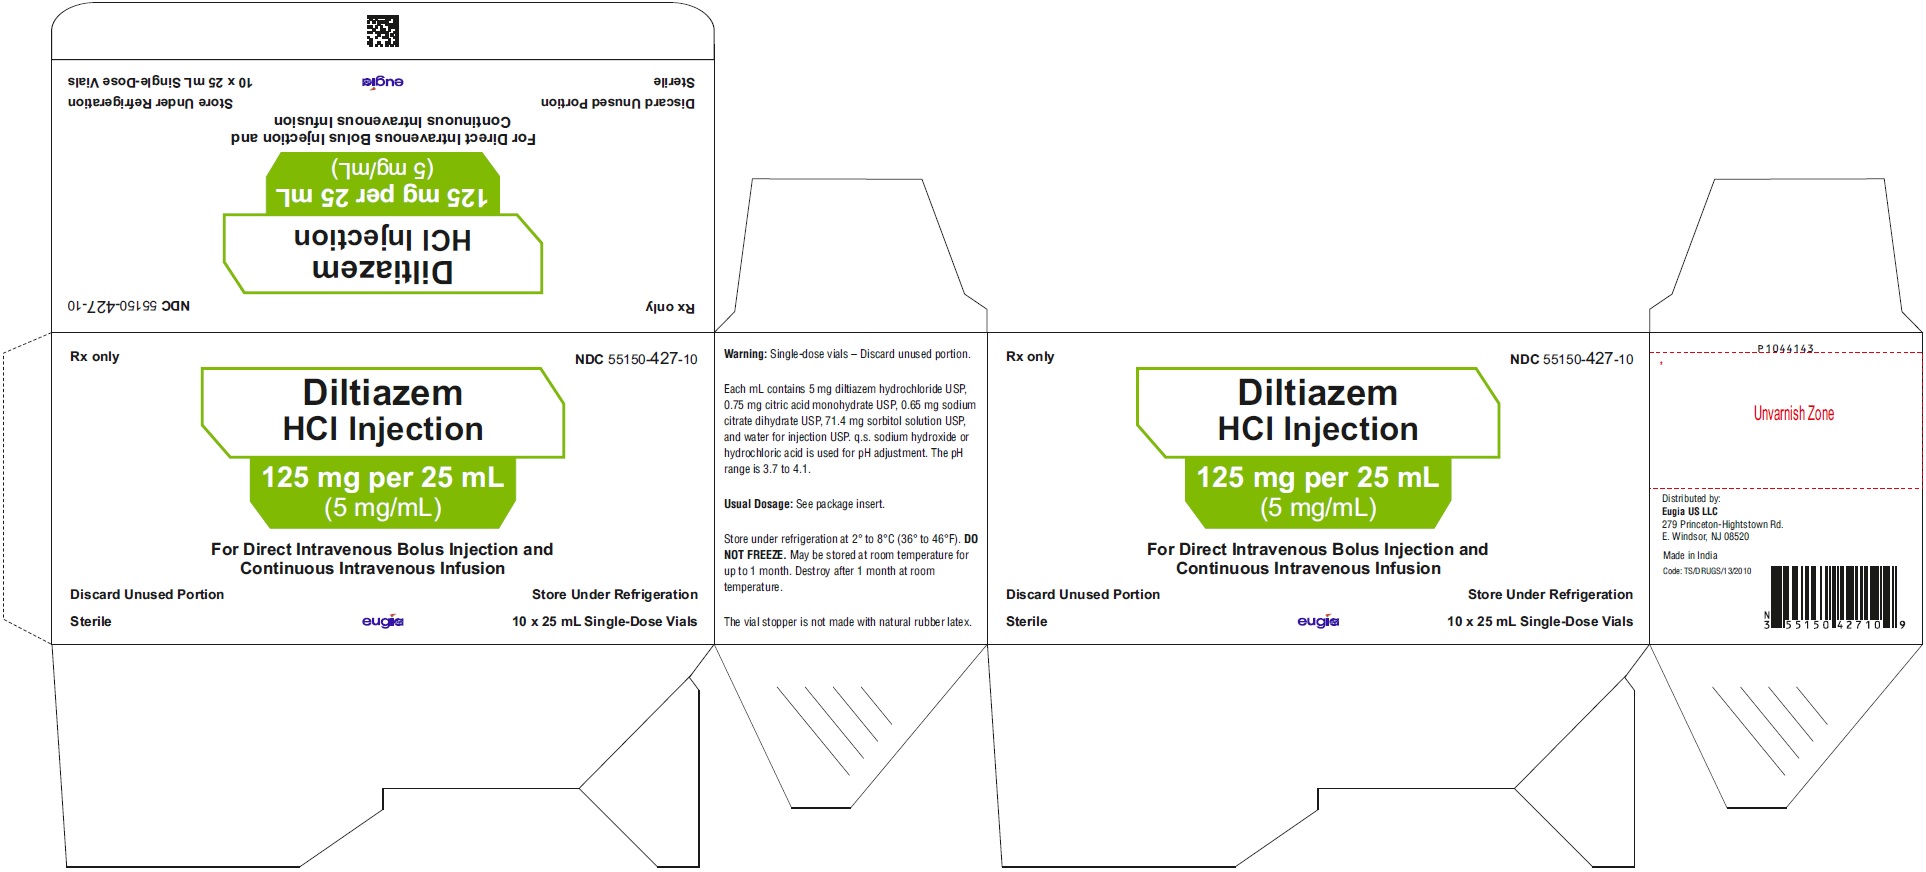
DILTIAZEM HYDROCHLORIDE 5 mg/mL Injection, Solution
Other active recalls for Diltiazem Hydrochloride (different manufacturers) — 6 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcium Channel Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Diltiazem is used for a few different heart and blood vessel conditions depending on the form you have. The oral extended-release tablets and capsules treat high blood pressure and...
- It depends on the specific product you have. Extended-release tablets like Matzim LA or Cardizem LA can be taken with or without food — food doesn't meaningfully affect their absor...
- Does it matter what time of day I take diltiazem, or whether I take it with food?
- No — please don't do that with extended-release forms of diltiazem. Crushing, chewing, or opening an extended-release capsule or tablet destroys the time-release mechanism, which m...
Patient education
Supplement & herbal interactions
Diltiazem may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2968PHW8QP
A weak organic acid derived from citrus fruits or made through fermentation. It works as a buffer to control pH, a preservative to extend shelf life, and a flavoring agent in medications.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII B22547B95K
A salt derived from citric acid that helps maintain the proper acid-base balance in the medicine. It's used as a buffer to keep the product stable and at the right pH level.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J1163 | $0.028 / J1163 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diltiazem Hydrochloride 5 mg/mL 00641-6015-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 00641-9219-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 25021-0319-05 | Sagent | 10 vials | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mLthis 55150-0427-10 | Eugia | 10 vials | — | — | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 71872-7063-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 00641-6013-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 84549-0319-05 | ProPharma | 5 ml | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 55150-0426-10 | Eugia | 10 vials | — | — | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 00641-9217-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 00641-9218-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 71872-7345-01 | Medical | 1 vial | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 00641-6014-10 | Hikma | 10 vials | — | AP | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 55150-0425-10 | Eugia | 10 vials | — | — | FDA listed | — |
| Diltiazem Hydrochloride 5 mg/mL 51662-1712-01 | HF | 5 ml | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 55150-0427-10 You're viewing this | 10 VIAL, SINGLE-DOSE in 1 CARTON (55150-427-10) / 25 mL in 1 VIAL, SINGLE-DOSE (55150-427-01) | 2023-03-29 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Diltiazem hydrochloride injection is indicated for the following: Atrial Fibrillation or Atrial Flutter Temporary control of rapid ventricular rate in atrial fibrillation or atrial flutter. It should not be used in patients with atrial fibrillation or atrial flutter associated with an accessory bypass tract such as in Wolff-Parkinson-White (WPW) syndrome or short PR syndrome. Paroxysmal Supraventricular Tachycardia Rapid conversion of paroxysmal supraventricular tachycardias (PSVT) to sinus rhythm.
This includes AV nodal reentrant tachycardias and reciprocating tachycardias associated with an extranodal accessory pathway such as the WPW syndrome or short PR syndrome. Unless otherwise contraindicated, appropriate vagal maneuvers should be attempted prior to administration of diltiazem hydrochloride injection. The use of diltiazem hydrochloride injection should be undertaken with caution when the patient is compromised hemodynamically or is taking other drugs that decrease any or all of the following: peripheral resistance, myocardial filling, myocardial contractility, or electrical impulse propagation in the myocardium.
For either indication and particularly when employing continuous intravenous infusion, the setting should include continuous monitoring of the ECG and frequent measurement of blood pressure. A defibrillator and emergency equipment should be readily available. In domestic controlled trials in patients with atrial fibrillation or atrial flutter, bolus administration of diltiazem hydrochloride injection was effective in reducing heart rate by at least 20% in 95% of patients.
Diltiazem hydrochloride injection rarely converts atrial fibrillation or atrial flutter to normal sinus rhythm. Following administration of one or two intravenous bolus doses of diltiazem hydrochloride injection, response usually occurs within 3 minutes and maximal heart rate reduction generally occurs in 2 to 7 minutes. Heart rate reduction may last from 1 to 3 hours.
If hypotension occurs, it is generally short-lived, but may last from 1 to 3 hours. A 24 hour continuous infusion of diltiazem hydrochloride injection in the treatment of atrial fibrillation or atrial flutter maintained at least a 20% heart rate reduction during the infusion in 83% of patients. Upon discontinuation of infusion, heart rate reduction may last from 0.5 hours to more than 10 hours (median duration 7 hours).
Hypotension, if it occurs, may be similarly persistent. In the controlled clinical trials, 3.2% of patients required some form of intervention (typically, use of intravenous fluids or the Trendelenburg position) for blood pressure support following diltiazem hydrochloride injection. In domestic controlled trials, bolus administration of diltiazem hydrochloride injection was effective in converting PSVT to normal sinus rhythm in 88% of patients within 3 minutes of the first or second bolus dose.
Symptoms associated with the arrhythmia were improved in conjunction with decreased heart rate or conversion to normal sinus rhythm following administration of diltiazem hydrochloride injection.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Direct Intravenous Single Injections (Bolus) The initial dose of diltiazem hydrochloride injection should be 0.25 mg/kg actual body weight as a bolus administered over 2 minutes (20 mg is a reasonable dose for the average patient). If response is inadequate, a second dose may be administered after 15 minutes. The second bolus dose of diltiazem hydrochloride injection should be 0.35 mg/kg actual body weight administered over 2 minutes (25 mg is a reasonable dose for the average patient).
Subsequent intravenous bolus doses should be individualized for each patient. Patients with low body weights should be dosed on a mg/kg basis. Some patients may respond to an initial dose of 0.15 mg/kg, although duration of action may be shorter.
Experience with this dose is limited. Continuous Intravenous Infusion For continued reduction of the heart rate (up to 24 hours) in patients with atrial fibrillation or atrial flutter, an intravenous infusion of diltiazem hydrochloride injection may be administered. Immediately following bolus administration of 20 mg (0.25 mg/kg) or 25 mg (0.35 mg/kg) diltiazem hydrochloride injection and reduction of heart rate, begin an intravenous infusion of diltiazem hydrochloride injection.
The recommended initial infusion rate of diltiazem hydrochloride injection is 10 mg/h. Some patients may maintain response to an initial rate of 5 mg/h. The infusion rate may be increased in 5 mg/h increments up to 15 mg/h as needed, if further reduction in heart rate is required.
The infusion may be maintained for up to 24 hours. Diltiazem shows dose-dependent, non-linear pharmacokinetics. Duration of infusion longer than 24 hours and infusion rates greater than 15 mg/h have not been studied.
Therefore, infusion duration exceeding 24 hours and infusion rates exceeding 15 mg/h are not recommended. Dilution: To prepare diltiazem hydrochloride injection for continuous intravenous infusion, aseptically transfer the appropriate quantity (see chart) of diltiazem hydrochloride injection to the desired volume of either Normal Saline, D5W, or D5W/0.45% NaCl. Mix thoroughly.
Keep diluted diltiazem hydrochloride injection refrigerated until use. Use within 24 hours. Diluent Volume Quantity of Diltiazem hydrochloride injection Final Concentration Administration Dose* Infusion Rate 100mL 125 mg(25mL) Final Volume 125 mL 1 mg/mL 10 mg/h 15 mg/h 10 mL/h 15 mL/h 250 mL 250 mg (50 mL) Final Volume 300 mL 0.83 mg/mL 10 mg/h 15 mg/h 12 mL/h 18 mL/h 500mL 250 mg(50mL) Final Volume 550 mL 0.45 mg/mL 10 mg/h 15 mg/h 22 mL/h 33 mL/h * 5 mg/h may be appropriate for some patients.
Compatibility: Diltiazem hydrochloride injection was tested for compatibility with three commonly used intravenous fluids at a maximal concentration of 1 mg diltiazem hydrochloride per milliliter. Diltiazem hydrochloride injection was found to be physically compatible and chemically stable in the following parenteral solutions for at least 24 hours when stored in glass or polyvinylchloride (PVC) bags at controlled room temperature 15° to 30°C (59° to 86°F) or under refrigeration 2° to 8°C (36° to 46°F). dextrose (5%) injection, USP sodium chloride (0.9%) injection, USP dextrose (5%) and sodium chloride (0.45%) injection, USP Physical Incompatibilities: Because of potential physical incompatibilities, it is recommended that diltiazem hydrochloride injection not be mixed with any other drugs in the same container.
If possible, it is recommended that diltiazem hydrochloride injection not be co-infused in the same intravenous line. Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever solution and container permit. Physical incompatibilities (precipitate formation or cloudiness) were observed when diltiazem hydrochloride injection was infused in the same intravenous line with the following drugs: acetazolamide, acyclovir, aminophylline, ampicillin, ampicillin sodium/sulbactam sod…
⛔ Contraindications ▾
CONTRAINDICATIONS Injectable forms of diltiazem are contraindicated in: 1. Patients with sick sinus syndrome except in the presence of a functioning ventricular pacemaker. 2.
Patients with second- or third-degree AV block except in the presence of a functioning ventricular pacemaker. 3. Patients with severe hypotension or cardiogenic shock.
4. Patients who have demonstrated hypersensitivity to the drug. 5.
Intravenous diltiazem and intravenous beta-blockers should not be administered together or in close proximity (within a few hours). 6. Patients with atrial fibrillation or atrial flutter associated with an accessory bypass tract such as in WPW syndrome or short PR syndrome.
As with other agents which slow AV nodal conduction and do not prolong the refractoriness of the accessory pathway (e.g., verapamil, digoxin), in rare instances patients in atrial fibrillation or atrial flutter associated with an accessory bypass tract may experience a potentially life-threatening increase in heart rate accompanied by hypotension when treated with diltiazem hydrochloride injection. As such, the initial use of diltiazem hydrochloride injection should be, if possible, in a setting where monitoring and resuscitation capabilities, including DC cardioversion/defibrillation, are present (see OVERDOSAGE).
Once familiarity of the patient's response is established, use in an office setting may be acceptable. 7. Patients with ventricular tachycardia.
Administration of other calcium channel blockers to patients with wide complex tachycardia (QRS ≥0.12 seconds) has resulted in hemodynamic deterioration and ventricular fibrillation. It is important that an accurate pretreatment diagnosis distinguish wide complex QRS tachycardia of supraventricular origin from that of ventricular origin prior to administration of diltiazem hydrochloride injection.
⚠️ Warnings ▾
WARNINGS 1. Cardiac Conduction - Diltiazem prolongs AV nodal conduction and refractoriness that may rarely result in second- or third-degree AV block in sinus rhythm. Concomitant use of diltiazem with agents known to affect cardiac conduction may result in additive effects (see Drug Interactions).
If high-degree AV block occurs in sinus rhythm, intravenous diltiazem should be discontinued and appropriate supportive measures instituted (see OVERDOSAGE). 2. Congestive Heart Failure - Although diltiazem has a negative inotropic effect in isolated animal tissue preparations, hemodynamic studies in humans with normal ventricular function and in patients with a compromised myocardium, such as severe CHF, acute MI, and hypertrophic cardiomyopathy, have not shown a reduction in cardiac index nor consistent negative effects on contractility (dp/dt).
Administration of oral diltiazem in patients with acute myocardial infarction and pulmonary congestion documented by x-ray on admission is contraindicated. Experience with the use of diltiazem hydrochloride injection in patients with impaired ventricular function is limited. Caution should be exercised when using the drug in such patients.
3. Hypotension - Decreases in blood pressure associated with diltiazem hydrochloride injection therapy may occasionally result in symptomatic hypotension (3.2%). The use of intravenous diltiazem for control of ventricular response in patients with supraventricular arrhythmias should be undertaken with caution when the patient is compromised hemodynamically.
In addition, caution should be used in patients taking other drugs that decrease peripheral resistance, intravascular volume, myocardial contractility or conduction. 4. Acute Hepatic Injury - In rare instances, significant elevations in enzymes such as alkaline phosphatase, LDH, SGOT, SGPT, and other phenomena consistent with acute hepatic injury have been noted following oral diltiazem.
Therefore, the potential for acute hepatic injury exists following administration of intravenous diltiazem. 5. Ventricular Premature Beats (VPBs) - VPBs may be present on conversion of PSVT to sinus rhythm with diltiazem hydrochloride injection.
These VPBs are transient, are typically considered to be benign, and appear to have no clinical significance. Similar ventricular complexes have been noted during cardioversion, other pharmacologic therapy, and during spontaneous conversion of PSVT to sinus rhythm.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reaction rates are based on the use of diltiazem hydrochloride injection in over 400 domestic clinical trial patients with atrial fibrillation/flutter or PSVT under double-blind or open-label conditions. Worldwide experience in over 1,300 patients was similar. Adverse events reported in controlled and uncontrolled clinical trials were generally mild and transient.
Hypotension was the most commonly reported adverse event during clinical trials. Asymptomatic hypotension occurred in 4.3% of patients. Symptomatic hypotension occurred in 3.2% of patients.
When treatment for hypotension was required, it generally consisted of administration of saline or placing the patient in the Trendelenburg position. Other events reported in at least 1% of the diltiazem-treated patients were injection site reactions (e.g., itching, burning) 3.9%, vasodilation (flushing) 1.7%, and arrhythmia (junctional rhythm or isorhythmic dissociation) 1.0 %. In addition, the following events were reported infrequently (less than 1%): Cardiovascular: Asystole, atrial flutter, AV block first degree, AV block second degree, bradycardia, chest pain, congestive heart failure, sinus pause, sinus node dysfunction, syncope, ventricular arrhythmia, ventricular fibrillation, ventricular tachycardia Dermatologic: Pruritus, sweating Gastrointestinal: Constipation, elevated SGOT or alkaline phosphatase, nausea, vomiting Nervous System: Dizziness, paresthesia Other: Amblyopia, asthenia, dry mouth, dyspnea, edema, headache, hyperuricemia Although not observed in clinical trials with diltiazem hydrochloride injection, the following events associated with oral diltiazem may occur: Cardiovascular: AV block (third degree), bundle branch block, ECG abnormality, palpitations, syncope, tachycardia, ventricular extrasystoles Dermatologic: Alopecia, erythema multiforme (including Stevens-Johnson syndrome, toxic epidermal necrolysis), exfoliative dermatitis, leukocytoclastic vasculitis, petechiae, photosensitivity, purpura, rash, urticaria Gastrointestinal: Anorexia, diarrhea, dysgeusia, dyspepsia, mild elevations of SGPT and LDH, thirst, weight increase Nervous System: Abnormal dreams, amnesia, depression, extrapyramidal symptoms, gait abnormality, hallucinations, insomnia, nervousness, personality change, somnolence, tremor Other: acute generalized exanthematous pustulosis, allergic reactions, angioedema (including facial or periorbital edema), CPK elevation, epistaxis, eye irritation, gingival hyperplasia, hemolytic anemia, hyperglycemia, impotence, increased bleeding time, leukopenia, muscle cramps, myopathy, nasal congestion, nocturia, osteoarticular pain, photosensitivity (including lichenoid keratosis and hyperpigmentation at sun-exposed skin areas), polyuria, retinopathy, sexual difficulties, thrombocytopenia, tinnitus.
Events such as myocardial infarction have been observed which are not readily distinguishable from the natural history of the disease for the patient.
🆘 Overdosage ▾
OVERDOSAGE Overdosage experience is limited. In the event of overdosage or an exaggerated response, appropriate supportive measures should be employed. The following measures may be considered: Bradycardia: Administer atropine (0.6 to 1.0 mg).
If there is no response to vagal blockade administer isoproterenol cautiously. High-degree AV Block: Treat as for bradycardia above. Fixed high-degree AV block should be treated with cardiac pacing.
Cardiac Failure: Administer inotropic agents (isoproterenol, dopamine, or dobutamine) and diuretics. Hypotension: Vasopressors (e.g., dopamine or norepinephrine). The effectiveness of intravenous calcium administration to reverse the pharmacological effects of diltiazem overdose has been inconsistent.
In a few reported cases, overdose with calcium channel blockers associated with hypotension and bradycardia that was initially refractory to atropine became more responsive to atropine after the patients received intravenous calcium. In some cases intravenous calcium has been administered (1 g calcium chloride or 3 g calcium gluconate) over 5 minutes, and repeated every 10 to 20 minutes as necessary. Calcium gluconate has also been administered as a continuous infusion at a rate of 2 g per hour for 10 hours.
Infusions of calcium for 24 hours or more may be required. Patients should be monitored for signs of hypercalcemia. Actual treatment and dosage should depend on the severity of the clinical situation and the judgment and experience of the treating physician.
Diltiazem does not appear to be removed by peritoneal or hemodialysis. Limited data suggest that plasmapheresis or charcoal hemoperfusion may hasten diltiazem elimination following overdose. The intravenous LD 50 's in mice and rats were 60 and 38 mg/kg, respectively.
The toxic dose in man is not known.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanisms of Action Diltiazem inhibits the influx of calcium (Ca 2+ ) ions during membrane depolarization of cardiac and vascular smooth muscle. The therapeutic benefits of diltiazem in supraventricular tachycardias are related to its ability to slow AV nodal conduction time and prolong AV nodal refractoriness. Diltiazem exhibits frequency (use) dependent effects on AV nodal conduction such that it may selectively reduce the heart rate during tachycardias involving the AV node with little or no effect on normal AV nodal conduction at normal heart rates.
Diltiazem slows the ventricular rate in patients with a rapid ventricular response during atrial fibrillation or atrial flutter. Diltiazem converts paroxysmal supraventricular tachycardia (PSVT) to normal sinus rhythm by interrupting the reentry circuit in AV nodal reentrant tachycardias and reciprocating tachycardias, e.g., Wolff- Parkinson-White syndrome (WPW). Diltiazem prolongs the sinus cycle length.
It has no effect on the sinus node recovery time or on the sinoatrial conduction time in patients without SA nodal dysfunction. Diltiazem has no significant electrophysiologic effects on tissues in the heart that are fast sodium channel dependent, e.g., His-Purkinje tissue, atrial and ventricular muscle, and extranodal accessory pathways. Like other calcium channel antagonists, because of its effect on vascular smooth muscle, diltiazem decreases total peripheral resistance resulting in a decrease in both systolic and diastolic blood pressure.
Hemodynamics In patients with cardiovascular disease, diltiazem hydrochloride injection administered intravenously in single bolus doses, followed in some cases by a continuous infusion, reduced blood pressure, systemic vascular resistance, the rate-pressure product, and coronary vascular resistance and increased coronary blood flow. In a limited number of studies of patients with compromised myocardium (severe congestive heart failure, acute myocardial infarction, hypertrophic cardiomyopathy), administration of intravenous diltiazem produced no significant effect on contractility, left ventricular end diastolic pressure, or pulmonary capillary wedge pressure.
The mean ejection fraction and cardiac output/index remained unchanged or increased. Maximal hemodynamic effects usually occurred within 2 to 5 minutes of an injection. However, in rare instances, worsening of congestive heart failure has been reported in patients with preexisting impaired ventricular function.
Pharmacodynamics The prolongation of PR interval correlated significantly with plasma diltiazem concentration in normal volunteers using the Sigmoidal E max model. Changes in heart rate, systolic blood pressure, and diastolic blood pressure did not correlate with diltiazem plasma concentrations in normal volunteers. Reduction in mean arterial pressure correlated linearly with diltiazem plasma concentration in a group of hypertensive patients.
In patients with atrial fibrillation and atrial flutter, a significant correlation was observed between the percent reduction in HR and plasma diltiazem concentration using the Sigmoidal E max model. Based on this relationship, the mean plasma diltiazem concentration required to produce a 20% decrease in heart rate was determined to be 80 ng/mL. Mean plasma diltiazem concentrations of 130 ng/mL and 300 ng/mL were determined to produce reductions in heart rate of 30% and 40%.
Pharmacokinetics and Metabolism Following a single intravenous injection in healthy male volunteers, diltiazem hydrochloride appears to obey linear pharmacokinetics over a dose range of 10.5 to 21.0 mg. The plasma elimination half-life is approximately 3.4 hours. The apparent volume of distribution of diltiazem hydrochloride is approximately 305 L.
Diltiazem hydrochloride is extensively metabolized in the liver with a systemic clearance of approximately 65 L/h. After constant rate intravenous infusion to healthy male volunteers, diltiazem exhib…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Diltiazem hydrochloride injection is clear, colorless, sterile, nonpyrogenic solution and is supplied as follows: 25 mg per 5 mL (5 mg/mL) 5 mL Single-Dose Vials Packaged in a Carton of 10 NDC 55150-425-10 50 mg per 10 mL (5 mg/mL) 10 mL Single-Dose Vials Packaged in a Carton of 10 NDC 55150-426-10 125 mg per 25 mL (5 mg/mL) 25 mL Single-Dose Vials Packaged in a Carton of 10 NDC 55150-427-10 Store product under refrigeration 2° to 8°C (36° to 46°F). Do not freeze. May be stored at room temperature for up to 1 month.
Destroy after 1 month at room temperature. Single-dose vials. Discard unused portion.
The vial stopper is not made with natural rubber latex. Distributed by: Eugia US LLC 279 Princeton-Hightstown Rd. E.
Windsor, NJ 08520 Manufactured by: Eugia Pharma Specialities Limited Hyderabad – 500032 India Revised: April 2023
📋 Description ▾
DESCRIPTION Diltiazem hydrochloride is a calcium ion cellular influx inhibitor (slow channel blocker or calcium channel antagonist). Chemically, diltiazem hydrochloride is 1,5-benzothiazepin-4-(5H)-one,3-(Acetyloxy)-5-[2-(dimethylamino)ethyl]-2,3-dihydro-2-(-4-methoxyphenyl)-, monohydrochloride, (+)-cis-. The chemical structure is: Diltiazem hydrochloride, USP is a white crystalline powder with a bitter taste.
It is soluble in water, methanol, and chloroform. It has a molecular weight of 451.0. Diltiazem hydrochloride injection is a clear, colorless, sterile, nonpyrogenic solution.
It has a pH range of 3.7 to 4.1. Diltiazem hydrochloride injection is for direct intravenous bolus injection and continuous intravenous infusion. 25-mg, 5-mL vial–each sterile vial contains 25 mg diltiazem hydrochloride, 3.75 mg citric acid USP, 3.25 mg sodium citrate dihydrate USP, 357 mg sorbitol solution USP, and water for injection USP up to 5 mL.
Sodium hydroxide or hydrochloric acid is used for pH adjustment. 50-mg, 10-mL vial–each sterile vial contains 50 mg diltiazem hydrochloride, 7.5 mg citric acid USP, 6.5 mg sodium citrate dihydrate USP, 714 mg sorbitol solution USP, and water for injection USP up to 10 mL. Sodium hydroxide or hydrochloric acid is used for pH adjustment.
125-mg, 25-mL vial–each sterile vial contains 125 mg diltiazem hydrochloride, 18.75 mg citric acid USP, 16.25 mg sodium citrate dihydrate USP, 1,785 mg sorbitol solution USP, and water for injection USP up to 25 mL. Sodium hydroxide or hydrochloric acid is used for pH adjustment. diltiazem-structure