
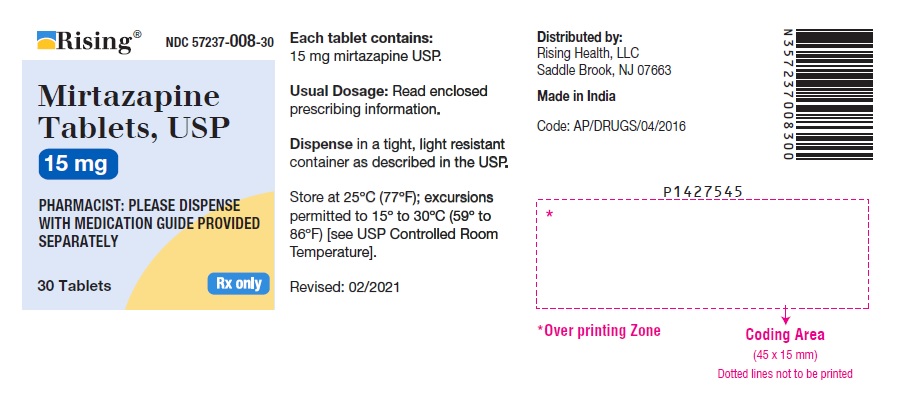
Mirtazapine 15 mg Tablet, Film Coated, 500-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Other antidepressants class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Mirtazapine is prescribed to treat major depressive disorder (MDD) in adults. That's a medical condition involving a persistently low mood, loss of interest in daily activities, ch...
- Mirtazapine causes significant drowsiness — it's one of its most common effects. Taking it in the evening before bed means that sleepiness works in your favor rather than interferi...
- Why is it recommended to take mirtazapine in the evening?
- Yes, weight gain and increased appetite are well-documented side effects of mirtazapine. In clinical trials, about 12% of patients on mirtazapine gained weight, compared to 2% on p...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mirtazapine — tap one for details:
Mirtazapine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 2165RE0K14
A plant-based thickener made from cellulose that helps control how quickly the medicine dissolves and releases its active ingredient. It also binds ingredients together and improves the tablet's texture and handling during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.065 | $32.25 / 500 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.3265 | $163.25 / 500 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.6699 | $334.95 / 500 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mirtazapine 15 mg 00378-3515-01 | Mylan | 100 tablets | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mg 00904-6519-61 | Major | 1 tablet | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mg 51079-0086-20 | Mylan | 1 tablet | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mgthis 57237-0008-05 | Rising | 500 tablets | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mg 57664-0499-18 | Sun | 1000 tablets | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mg 60505-0247-01 | Apotex | 30 tablets | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mg 63739-0098-10 | McKesson | 10 tablets | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mg 66993-0607-04 | Prasco | 500 tablets | $0.065 | AB | Availability likely | — |
| Mirtazapine 15 mg 68084-0119-01 | American | 1 tablet | $0.065 | AB | Availability likely | — |
| Remeron 15 mg 78206-0160-01 | Organon | 30 tablets | $6.363 | AB | Availability likely | +9759% |
| Mirtazapine 15 mg 00615-8268-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 13107-0031-01 | Aurolife | 100 tablets | — | AB | FDA listed | — |
| mirtazapine 15 mg 31722-0408-05 | Camber | 500 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 48433-0076-20 | Safecor | 1 tablet | — | AB | FDA listed | — |
| Mirtazapine 15 mg 50090-2140-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 50090-2800-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 51407-0350-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 55154-5355-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Mirtazapine 15 mg 55154-7297-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| Mirtazapine 15 mg 61919-0153-60 | Direct_Rx | 60 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 63187-0206-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 63629-2366-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 63629-2367-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 65862-0031-01 | Aurobindo | 100 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 67046-1590-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 68788-7251-01 | Preferred | 15 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 70518-0180-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 70518-1397-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 70518-1838-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 70518-2453-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 70518-4322-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 71205-0481-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 71335-0286-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 71335-0664-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 71335-1055-01 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Mirtazapine 15 mg 71610-0115-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 71610-0475-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 71610-0717-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 71610-0853-15 | Aphena | 15 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 72162-1639-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 80425-0305-01 | Advanced | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 87441-0058-01 | Unit | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 55154-0280-00 | Cardinal | 1 tablet | — | AB | FDA listed | — |
| mirtazapine 15 mg 72865-0369-05 | XLCare | 500 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 67046-0319-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Mirtazapine 15 mg 68071-2784-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 57237-0008-05 You're viewing this | 500 TABLET, FILM COATED in 1 BOTTLE (57237-008-05) | $0.0645 / ea | $32.27 | 2004-10-22 | Active |
| 57237-0008-30 | 30 TABLET, FILM COATED in 1 BOTTLE (57237-008-30) | $0.0645 / ea | $1.94 | 2004-10-22 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.0645 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 75% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 57237-0008-05?
What is the difference between NDC 57237-0008-05 and NDC 57237-0008-30?
What NDC number is used to bill for this package of Mirtazapine 15 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS Antidepressants increased the risk of suicidal thoughts and behaviors in pediatric and young adult patients in short-term studies. Closely monitor all antidepressant-treated patients for clinical worsening, and for emergence of suicidal thoughts and behaviors [see Warnings and Precautions (5.1) ] . Mirtazapine tablets are not approved for use in pediatric patients [see Use in Specific Populations (8.4) ].
WARNING: SUICIDAL THOUGHTS AND BEHAVIORS See full prescribing information for complete boxed warning. Increased risk of suicidal thoughts and behavior in pediatric and young adult patients taking antidepressants. Closely monitor all antidepressant-treated patients for clinical worsening and emergence of suicidal thoughts and behaviors.
Mirtazapine tablets are not approved for use in pediatric patients. ( 5.1 , 8.4 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Mirtazapine tablets are indicated for the treatment of major depressive disorder (MDD) in adults [see Clinical Studies (14) ]. Mirtazapine tablets are indicated for the treatment of major depressive disorder (MDD) in adults. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Starting dose: 15 mg once daily; may increase up to maximum recommended dose of 45 mg once daily. ( 2.1 ) Administer orally once daily, preferably in the evening prior to sleep. ( 2.1 ) Reduce dose gradually when discontinuing mirtazapine tablets. ( 2.6 , 5.14 )
2.1Recommended Dosage The recommended starting dose of mirtazapine tablets is 15 mg once daily, administered orally, preferably in the evening prior to sleep. If patients do not have an adequate response to the initial 15 mg dose, increase the dose up to a maximum of 45 mg per day. Dose changes should not be made in intervals of less than 1 to 2 weeks to allow sufficient time for evaluation of response to a given dose [see Clinical Pharmacology (12.3) ].
2.3Screen for Bipolar Disorder Prior to Starting Mirtazapine Tablets Prior to initiating treatment with mirtazapine tablets or another antidepressant, screen patients for a personal or family history of bipolar disorder, mania, or hypomania [see Warnings and Precautions (5.9) ].
2.4Switching Patients to or from a Monoamine Oxidase Inhibitor Antidepressant At least 14 days must elapse between discontinuation of a monoamine oxidase inhibitor (MAOI) antidepressant and initiation of mirtazapine tablets. In addition, at least 14 days must elapse after stopping mirtazapine tablets before starting an MAOI antidepressant [see Contraindications (4) and Warnings and Precautions (5.3) ].
2.5Dosage Modifications Due to Drug Interactions Strong CYP3A Inducers An increase in dosage of mirtazapine tablets may be needed with concomitant strong CYP3A inducer (e.g., carbamazepine, phenytoin, rifampin) use. Conversely, a decrease in dosage of mirtazapine tablets may be needed if the CYP3A inducer is discontinued [see Drug Interactions (7) ]. Strong CYP3A Inhibitors A decrease in dosage of mirtazapine tablets may be needed with concomitant use of strong CYP3A4 inhibitors (e.g., ketoconazole, clarithromycin).
Conversely, an increase in dosage of mirtazapine tablets may be needed if the CYP3A4 inhibitor is discontinued [see Drug Interactions (7) ]. Cimetidine A decrease in dosage of mirtazapine tablets may be needed with concomitant use of cimetidine. Conversely, an increase in dosage of mirtazapine tablets may be needed if cimetidine is discontinued [see Drug Interactions (7) ].
2.6Discontinuation of Mirtazapine Tablets Treatment Adverse reactions may occur upon discontinuation or dose reduction of mirtazapine tablets [see Warnings and Precautions (5.14) ]. Gradually reduce the dosage of mirtazapine tablets rather than stopping abruptly whenever possible.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Mirtazapine tablets USP are supplied as: 7.5 mg tablets: White, biconvex, capsule shaped film coated tablets with “11” debossed on one side and “A” debossed on the other side. 15 mg tablets: Yellow, biconvex, capsule shaped film coated tablets with a score line in between “0” and “8” on one side and “A” debossed on the other side. 30 mg tablets: Reddish brown, biconvex, capsule shaped film coated tablets with a score line in between “0” and “9” on one side and “A” debossed on the other side.
45 mg tablets: White, biconvex, capsule shaped film coated tablets with “10” debossed on one side and “A” debossed on the other side. Tablets: 7.5 mg unscored, 15 mg scored, 30 mg scored and 45 mg unscored. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Mirtazapine tablets are contraindicated in patients: Taking, or within 14 days of stopping, MAOIs (including the MAOIs linezolid and intravenous methylene blue) because of an increased risk of serotonin syndrome [see Warnings and Precautions (5.3) , Drug Interactions (7) ]. With a known hypersensitivity to mirtazapine or to any of the excipients in mirtazapine tablets. Severe skin reactions, including drug reaction with eosinophilia and systemic symptoms (DRESS), Stevens-Johnson syndrome, bullous dermatitis, erythema multiforme and toxic epidermal necrolysis have been reported following the use of mirtazapine tablets [see Warnings and Precautions (5.6) , Adverse Reactions (6.2) ].
Concomitant use of monoamine oxidase inhibitors (MAOIs) or use within 14 days of stopping MAOIs. ( 2.4 , 4 , 7 ) Known hypersensitivity to mirtazapine or any of the excipients in mirtazapine tablets. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Agranulocytosis: If sore throat, fever, stomatitis or signs of infection occur, along with a low white blood cell count, treatment with mirtazapine should be discontinued and the patient should be closely monitored. ( 5.2 ) Serotonin Syndrome: Increased risk when co-administered with other serotonergic drugs (e.g., SSRI, SNRI, triptans), but also when taken alone. If it occurs, discontinue mirtazapine and initiate supportive treatment.
( 2.4 , 4 , 5.3 , 7 ) Angle-Closure Glaucoma: Angle closure glaucoma has occurred in patients with untreated anatomically narrow angles treated with antidepressants. ( 5.4 ) QT Prolongation: Use mirtazapine with caution in patients with risk factors for QT prolongation. ( 5.5 , 7 ) Drug Reaction with Eosinophilia and System Symptoms (DRESS) : Discontinue mirtazapine if DRESS is suspected.
( 5.6 ) Increased Appetite/Weight Gain: mirtazapine has been associated with increased appetite and weight gain. ( 5.7 ) Somnolence: May impair judgment, thinking and/or motor skills. Use with caution when engaging in activities requiring alertness, such as driving or operating machinery.
( 5.8 , 7 ) Activation of Mania/Hypomania: Screen patients for bipolar disorder prior to initiating treatment. ( 2.3 , 5.9 ) Seizures: Use with caution in patients with a seizure disorder. ( 5.10 ) Elevated Cholesterol/Triglycerides: Has been reported with mirtazapine use.
( 5.11 ) Hyponatremia: May occur as a result of treatment with serotonergic antidepressants, including mirtazapine. ( 5.12 ) Transaminase Elevations: Clinically significant elevations have occurred. Use with caution in patients with impaired hepatic function.
( 5.13 )
5.1Suicidal Thoughts and Behaviors in Adolescents and Young Adults In pooled analyses of placebo-controlled trials of antidepressant drugs (SSRIs and other antidepressant classes) that included approximately 77,000 adult patients and 4,500 pediatric patients, the incidence of suicidal thoughts and behaviors in antidepressant-treated patients age 24 years and younger was greater than in placebo-treated patients. There was considerable variation in risk of suicidal thoughts and behaviors among drugs, but there was an increased risk identified in young patients for most drugs studied.
There were differences in absolute risk of suicidal thoughts and behaviors across the different indications, with the highest incidence in patients with MDD. The drug-placebo differences in the number of cases of suicidal thoughts and behaviors per 1000 patients treated are provided in Table 1. Table 1: Risk Differences of the Number of Patients with Suicidal Thoughts and Behavior in the Pooled Placebo-Controlled Trials of Antidepressants in Pediatric and Adult Patients Age Range Drug-Placebo Difference in Number of Patients with Suicidal Thoughts or Behaviors per 1000 Patients Treated Increases Compared to Placebo <18 years old 14 additional patients 18 to 24 years old 5 additional patients Decreases Compared to Placebo 25 to 64 years old 1 fewer patient ≥65 years old 6 fewer patients It is unknown whether the risk of suicidal thoughts and behaviors in children, adolescents, and young adults extends to longer-term use, i.e., beyond four months.
However, there is substantial evidence from placebo-controlled maintenance trials in adults with MDD that antidepressants delay the recurrence of depression and that depression itself is a risk factor for suicidal thoughts and behaviors. Monitor all antidepressant-treated patients for any indication of clinical worsening and emergence of suicidal thoughts and behaviors, especially during the initial few months of drug therapy, and at times of dosage changes. Counsel family members or caregivers of patients to monitor for changes in behavior and to alert the healthcare provider.
Consider changing the therapeutic regimen, including possibly discontinuing mirtazapine, in patients whose depression is persistently worse, or who are experiencing emergent…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described in more detail in other sections of the prescribing information: Hypersensitivity [see Contraindications (4) ] Suicidal Thoughts and Behaviors [see Warnings and Precautions (5.1) ] Agranulocytosis [see Warnings and Precautions (5.2) ] Serotonin Syndrome [see Contraindications (4) , Warnings and Precautions (5.3) , Drug Interactions (7) ] Angle-Closure Glaucoma [see Warnings and Precautions (5.4) ] QT Prolongation and Torsades de Pointes [see Warnings and Precautions (5.5) ] Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) [see Warnings and Precautions (5.6) ] Increased Appetite and Weight Gain [see Warnings and Precautions (5.7) ] Somnolence [see Warnings and Precautions (5.8) ] Activation of Mania or Hypomania [see Warnings and Precautions (5.9) ] Seizures [see Warnings and Precautions (5.10) ] Elevated Cholesterol and Triglycerides [see Warnings and Precautions (5.11) ] Hyponatremia [see Warnings and Precautions (5.12) ] Transaminase Elevations [see Warnings and Precautions (5.13) ] Discontinuation Syndrome [see Warnings and Precautions (5.14) ] Use in Patients with Concomitant Illness [see Warnings and Precautions (5.15) ] Most common adverse reactions (≥5% or greater and twice placebo) were somnolence, increased appetite, weight gain, and dizziness.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Rising Pharma Holdings, Inc. at 1-844-874-7464 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below are from clinical trials in which mirtazapine was administered to 2796 patients in phase 2 and 3 clinical studies. The trials consisted of double-blind controlled and open-label studies, inpatient and outpatient studies, fixed dose, and titration studies.
Adverse Reactions Leading to Discontinuation of Treatment Approximately 16% of the 453 patients who received mirtazapine in U.S. 6-week placebo-controlled clinical trials discontinued treatment due to an adverse reaction, compared to 7% of the 361 placebo-treated patients in those studies. The most common reactions leading to discontinuation (≥1% and at a rate at least twice that of placebo) are included in Table 2.
Table 2: Adverse Reactions (≥1% and at least twice placebo) Leading to Discontinuation of Mirtazapine in 6-Week Clinical Trials in Patients with MDD Mirtazapine (n=453) Placebo (n=361) Somnolence 10.4% 2.2% Nausea 1.5% 0% Common Adverse Reactions The most common adverse reactions (≥5% and twice placebo) associated with the use of mirtazapine are listed in Table 3. Table 3: Adverse Reactions (≥5% and twice placebo) in 6-Week U.S. Clinical Trials of Mirtazapine in Patients with MDD Mirtazapine (n=453) Placebo (n=361) Somnolence 54% 18% Increased Appetite 17% 2% Weight Gain 12% 2% Dizziness 7% 3% Table 4 enumerates adverse reactions that occurred in ≥1% of mirtazapine-treated patients, and were more frequent than the placebo-treated patients, who participated in 6-week, U.S. placebo-controlled trials in which patients were dosed in a range of 5 to 60 mg/day.
This table shows the percentage of patients in each group who had at least 1 episode of an adverse reaction at some time during their treatment. Table 4: Adverse Reactions (≥1% and greater than placebo) in 6-Week U.S. Clinical Studies of Mirtazapine in Patients with MDD Mirtazapine (n=453) Placebo (n=361) Body as a Whole Asthenia 8% 5% Flu Syndrome 5% 3% Back Pain 2% 1% Digestive System Dry Mouth 25% 15% Increased Appetite 17% 2% Constipation 13% 7% Metabolic and Nutritional Disorders Weight Gain 12% 2% Peripheral Edema 2% 1% Edema 1% 0% Musculoskeletal System Myalgia 2% 1% Nervous System Somnolence 54% 18% Dizziness 7% 3% A…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 5 includes clinically important drug interactions with mirtazapine [see Clinical Pharmacology (12.3) ]. Table 5: Clinically Important Drug Interactions with Mirtazapine Monoamine Oxidase Inhibitors (MAOIs) Clinical Impact The concomitant use of serotonergic drugs, including mirtazapine, and MAOIs increases the risk of serotonin syndrome. Intervention Mirtazapine is contraindicated in patients taking MAOIs, including MAOIs such as linezolid or intravenous methylene blue [see Dosage and Administration (2.4) , Contraindications (4) , Warnings and Precautions (5.3) ].
Examples selegiline, tranylcypromine, isocarboxazid, phenelzine, linezolid, methylene blue Other Serotonergic Drugs Clinical Impact The concomitant use of serotonergic drugs with mirtazapine increases the risk of serotonin syndrome. Intervention Monitor patients for signs and symptoms of serotonin syndrome, particularly during treatment initiation and dosage increases. If serotonin syndrome occurs, consider discontinuation of mirtazapine and/or concomitant serotonergic drugs [see Warnings and Precautions (5.3) ].
Examples SSRIs, SNRIs, triptans, tricyclic antidepressants, fentanyl, lithium, amphetamines, St. John’s Wort, tramadol, tryptophan, buspirone Strong CYP3A Inducers Clinical Impact The concomitant use of strong CYP3A inducers with mirtazapine decreases the plasma concentration of mirtazapine [see Clinical Pharmacology (12.3) ]. Intervention Increase the dose of mirtazapine if needed with concomitant CYP3A inducer use.
Conversely, a decrease in dosage of mirtazapine may be needed if the CYP3A inducer is discontinued [see Dosage and Administration (2.5) ]. Examples phenytoin, carbamazepine, rifampin Strong CYP3A Inhibitors Clinical Impact The concomitant use of strong CYP3A inhibitors with mirtazapine may increase the plasma concentration of mirtazapine [see Clinical Pharmacology (12.3) ]. Intervention Decrease the dose of mirtazapine if needed with concomitant strong CYP3A inhibitor use.
Conversely, an increase in dosage of mirtazapine may be needed if the CYP3A inhibitor is discontinued [see Dosage and Administration (2.5) ]. Examples itraconazole, ritonavir, nefazodone Cimetidine Clinical Impact The concomitant use of cimetidine, a CYP1A2, CYP2D6, and CYP3A inhibitor, with mirtazapine may increase the plasma concentration of mirtazapine [see Clinical Pharmacology (12.3) ]. Intervention Decrease the dose of mirtazapine if needed with concomitant cimetidine use.
Conversely, an increase in dosage of mirtazapine may be needed if cimetidine is discontinued [see Dosage and Administration (2.5) ]. Benzodiazepines and Alcohol Clinical Impact The concomitant use of benzodiazepines or alcohol with mirtazapine increases the impairment of cognitive and motor skills produced by mirtazapine alone. Intervention Avoid concomitant use of benzodiazepines and alcohol with mirtazapine [see Warnings and Precautions (5.8) , Clinical Pharmacology (12.3) ].
Examples diazepam, alprazolam, alcohol Drugs that Prolong QTc Interval Clinical Impact The concomitant use of other drugs which prolong the QTc interval with mirtazapine, increase the risk of QT prolongation and/or ventricular arrhythmias (e.g., Torsades de Pointes). Intervention Use caution when using mirtazapine concomitantly with drugs that prolong the QTc interval [see Warnings and Precautions (5.5) , Clinical Pharmacology (12.3) ]. Warfarin Clinical Impact The concomitant use of warfarin with mirtazapine may result in an increase in INR [see Clinical Pharmacology (12.3) ].
Intervention Monitor INR during concomitant use of warfarin with mirtazapine. Strong CYP3A inducers: Dosage increase may be needed for mirtazapine with concomitant use of strong CYP3A inducers. ( 2.5 , 7 ) Strong CYP3A inhibitors: Dosage decrease may be needed when mirtazapine is coadministered with strong CYP3A inhibitors.
( 2.5 , 7 ) Cimetidine: Dosage decrease may be needed when mirtazapine is coadministered with cimetidine. (…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatric Use : Use with caution in elderly patients. ( 5.12 , 5.15 , 8.5 ) Renal impairment: Dosage decrease may be needed in patients with moderate to severe renal impairment. ( 8.6 ) Hepatic impairment : Dosage decrease may be needed in patients with hepatic impairment. ( 8.6 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185 or visiting online at https://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/antidepressants/. Risk Summary Prolonged experience with mirtazapine in pregnant women, based on published observational studies and postmarketing reports, has not reliably identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
There are risks associated with untreated depression in pregnancy (see Clinical Considerations). In animal reproduction studies, oral administration of mirtazpine to pregnant rats and rabbits during the period of organogenesis revealed no evidence of teratogenic effects up to 20 and 17 times the maximum recommended human dose (MRHD) of 45 mg, respectively, based on mg/m 2 body surface area. However, in rats, there was an increase in postimplantation loss at 20 times the MRHD based on mg/m 2 body surface area.
Oral administration of mirtazapine to pregnant rats during pregnancy and lactation resulted in an increase in pup deaths and a decrease in pup birth weights at doses 20 times the MRHD based on mg/m 2 body surface area (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Women who discontinue antidepressants during pregnancy are more likely to experience a relapse of major depression than women who continue antidepressants. This finding is from a prospective, longitudinal study that followed 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy.
Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Data Animal Data Mirtazapine was administered orally to pregnant rats and rabbits during the period of organogenesis at doses of 2.5, 15, and 100 mg/kg/day and 2.5, 10, and 40 mg/kg/day, respectively, which are up to 20 and 17 times the maximum recommended human dose (MRHD) of 45 mg based on mg/m 2 body surface area, respectively. No evidence of teratogenic effects was observed.
However, in rats, there was an increase in postimplantation loss in dams treated with mirtazapine at 100 mg/kg/day which is 20 times the MRHD based on mg/m 2 body surface area. Oral administration of mirtazapine at doses of 2.5, 15, and 100 mg/kg/day to pregnant rats during pregnancy and lactation resulted in an increase in pup deaths during the first 3 days of lactation and a decrease in pup birth weights at 20 times the MRHD based on mg/m 2 body surface area. The cause of these deaths is not known.
The no effect dose level is 3 times the MRHD based on mg/m 2 body surface area.
8.2Lactation Risk Summary Data from published literature report the presence of mirtazapine in human milk at low levels with relative infant doses for mirtazapine ranging between 0.6 and 2.8% of the maternal weight-adjusted dose (see Data) . No adverse effects on the breastfed infant have been reported in most cases o…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to antidepressants during pregnancy. Healthcare providers are encouraged to register patients by calling the National Pregnancy Registry for Antidepressants at 1-844-405-6185 or visiting online at https://womensmentalhealth.org/clinical-and-research-programs/pregnancyregistry/antidepressants/. Risk Summary Prolonged experience with mirtazapine in pregnant women, based on published observational studies and postmarketing reports, has not reliably identified a drug-associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes.
There are risks associated with untreated depression in pregnancy (see Clinical Considerations). In animal reproduction studies, oral administration of mirtazpine to pregnant rats and rabbits during the period of organogenesis revealed no evidence of teratogenic effects up to 20 and 17 times the maximum recommended human dose (MRHD) of 45 mg, respectively, based on mg/m 2 body surface area. However, in rats, there was an increase in postimplantation loss at 20 times the MRHD based on mg/m 2 body surface area.
Oral administration of mirtazapine to pregnant rats during pregnancy and lactation resulted in an increase in pup deaths and a decrease in pup birth weights at doses 20 times the MRHD based on mg/m 2 body surface area (see Data). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo/Fetal Risk Women who discontinue antidepressants during pregnancy are more likely to experience a relapse of major depression than women who continue antidepressants. This finding is from a prospective, longitudinal study that followed 201 pregnant women with a history of major depressive disorder who were euthymic and taking antidepressants at the beginning of pregnancy.
Consider the risk of untreated depression when discontinuing or changing treatment with antidepressant medication during pregnancy and postpartum. Data Animal Data Mirtazapine was administered orally to pregnant rats and rabbits during the period of organogenesis at doses of 2.5, 15, and 100 mg/kg/day and 2.5, 10, and 40 mg/kg/day, respectively, which are up to 20 and 17 times the maximum recommended human dose (MRHD) of 45 mg based on mg/m 2 body surface area, respectively. No evidence of teratogenic effects was observed.
However, in rats, there was an increase in postimplantation loss in dams treated with mirtazapine at 100 mg/kg/day which is 20 times the MRHD based on mg/m 2 body surface area. Oral administration of mirtazapine at doses of 2.5, 15, and 100 mg/kg/day to pregnant rats during pregnancy and lactation resulted in an increase in pup deaths during the first 3 days of lactation and a decrease in pup birth weights at 20 times the MRHD based on mg/m 2 body surface area. The cause of these deaths is not known.
The no effect dose level is 3 times the MRHD based on mg/m 2 body surface area.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of mirtazapine have not been established in pediatric patients with MDD. Two placebo-controlled trials in 258 pediatric patients with MDD have been conducted with mirtazapine, and the data were insufficient to establish the safety and effectiveness of mirtazapine in pediatric patients with MDD. Antidepressants increased the risk of suicidal thoughts and behaviors in pediatric patients [see Boxed Warning and Warnings and Precautions (5.1) ].
In an 8-week-long clinical trial in pediatric patients receiving doses between 15 to 45 mg per day, 49% of mirtazapine-treated patients had a weight gain of at least 7%, compared to 5.7% of placebo-treated patients. The mean increase in weight was 4 kg (2 kg SD) for mirtazapine-treated patients versus 1 kg (2 kg SD) for placebo-treated patients [see Warnings and Precautions (5.7) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Approximately 190 patients ≥65 years of age participated in clinical studies with mirtazapine. Mirtazapine is known to be substantially excreted by the kidney (75%), and the risk of decreased clearance of this drug is greater in patients with impaired renal function. Pharmacokinetic studies revealed a decreased clearance of mirtazapine in the elderly [see Clinical Pharmacology (12.3) ].
Sedating drugs, including mirtazapine, may cause confusion and over-sedation in the elderly. Elderly patients may be at greater risk of developing hyponatremia. Caution is indicated when administering mirtazapine to elderly patients [see Warnings and Precautions (5.12) , (5.15) and Clinical Pharmacology (12.3) ] .
In general, dose selection for an elderly patient should be conservative, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Human Experience In premarketing clinical studies, there were reports of mirtazapine overdose alone or in combination with other pharmacological agents. Signs and symptoms reported in association with overdose included disorientation, drowsiness, impaired memory, and tachycardia. Based on postmarketing reports, serious outcomes (including fatalities) may occur at dosages higher than the recommended doses, especially with mixed overdoses.
In these cases, QT prolongation and Torsades de Pointes have also been reported [see Warnings and Precautions (5.5) , Adverse Reactions (6.2) , and Drug Interactions (7) ]. Overdose Management No specific antidotes for mirtazapine are known. Contact Poison Control (1-800-222-1222) for the latest recommendations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of action of mirtazapine for the treatment of major depressive disorder, is unclear. However, its efficacy could be mediated through its activity as an antagonist at central presynaptic α 2 -adrenergic inhibitory autoreceptors and heteroreceptors and enhancing central noradrenergic and serotonergic activity.
12.2Pharmacodynamics In preclinical studies, mirtazapine acts as an antagonist at α 2 -adrenergic inhibitory autoreceptors and heteroreceptors and as an antagonist at serotonin 5-HT 2 and 5-HT 3 receptors. Mirtazapine has no significant affinity for the 5-HT 1A and 5-HT 1B receptors. Mirtazapine also acts as an antagonist of histamine (H 1 ) receptors, peripheral α 1 -adrenergic receptors, and muscarinic receptors.
Actions at these receptors may explain some of the other clinical effects of mirtazapine (e.g., its prominent somnolent effects and orthostatic hypotension may be explained by its inhibition of histamine (H 1 ) receptors and peripheral α 1 -adrenergic receptors, respectively). Cardiac Electrophysiology The effect of mirtazapine on QTc interval was assessed in healthy subjects. At a dose of 75 mg (1.67 times the maximum recommended dosage), mirtazapine does not prolong the QTc interval to a clinically meaningful extent.
12.3Pharmacokinetics Plasma levels of mirtazapine are linearly related to dose over a dose range of 15 to 80 mg (1.78 times the maximum recommended dose). Steady state plasma levels of mirtazapine are attained within 5 days, with about 50% accumulation (accumulation ratio=1.5). The (–) enantiomer has an elimination half-life that is approximately twice as long as the (+) enantiomer and therefore achieves plasma levels that are about 3 times as high as that of the (+) enantiomer.
Absorption Mirtazapine has an absolute bioavailability of about 50% following oral administration. Peak plasma concentrations of mirtazapine are reached within about 2 hours post dose. Food Effect The presence of food in the stomach has a minimal effect on both the rate and extent of absorption.
Distribution Mirtazapine is approximately 85% bound to plasma proteins over a concentration range of 0.01 to 10 mcg/mL. Elimination Mirtazapine has a half-life of about 20 to 40 hours following oral administration of mirtazapine. Metabolism Mirtazapine is extensively metabolized after oral administration.
Major pathways of bio-transformation are demethylation and hydroxylation followed by glucuronide conjugation. In vitro data from human liver microsomes indicate that CYP2D6 and CYP1A2 are involved in the formation of the 8-hydroxy metabolite of mirtazapine, whereas CYP3A is considered to be responsible for the formation of the N-desmethyl and N-oxide metabolite. Several unconjugated metabolites possess pharmacological activity but are present in the plasma at very low levels.
Excretion Mirtazapine and its metabolites are eliminated predominantly (75%) via urine with 15% in feces. Specific Populations Geriatric Patients Following oral administration of mirtazapine tablets 20 mg/day for 7 days to subjects of varying ages (range 25 to 74 years old), oral clearance of mirtazapine was reduced in the elderly compared to the younger subjects. The clearance in elderly males was 40% lower compared to younger males, while the clearance was 10% lower in elderly females compared to younger females [see Warnings and Precautions (5.15) , Use in Specific Populations (8.5) ].
Male and Female Patients The mean elimination half-life of mirtazapine after oral administration ranges from approximately 20 to 40 hours across age and gender subgroups, with females of all ages exhibiting significantly longer elimination half-lives than males (mean half-life of 37 hours for females vs. 26 hours for males). Race There have been no clinical studies to evaluate the effect of race on the pharmacokinetics of mirtazapine.
Patients with Renal Impairment When compared to subjects with normal renal f…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of mirtazapine for the treatment of major depressive disorder, is unclear. However, its efficacy could be mediated through its activity as an antagonist at central presynaptic α 2 -adrenergic inhibitory autoreceptors and heteroreceptors and enhancing central noradrenergic and serotonergic activity.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Mirtazapine tablets, USP are supplied as: 7.5 mg Tablets – White, biconvex, capsule shaped film coated tablets with “11” debossed on one side and “A” debossed on the other side. Bottles of 30 NDC 57237-007-30 Bottles of 500 NDC 57237-007-05 15 mg Tablets – Yellow, biconvex, capsule shaped film coated tablets with a score line in between “0” and “8” on one side and “A” debossed on the other side. Bottles of 30 NDC 57237-008-30 Bottles of 500 NDC 57237-008-05 30 mg Tablets – Reddish brown, biconvex, capsule shaped film coated tablets with a score line in between “0” and “9” on one side and “A” debossed on the other side.
Bottles of 30 NDC 57237-009-30 Bottles of 500 NDC 57237-009-05 45 mg Tablets – White, biconvex, capsule shaped film coated tablets with “10” debossed on one side and “A” debossed on the other side. Bottles of 30 NDC 57237-010-30 Bottles of 500 NDC 57237-010-05 Storage Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from light and moisture.
📋 Description ▾
11 DESCRIPTION Mirtazapine tablets, USP contain mirtazapine USP. Mirtazapine has a tetracyclic chemical structure and belongs to the piperazino-azepine group of compounds. It is designated 1,2,3,4,10,14b-hexahydro-2-methylpyrazino [2,1-a] pyrido [2,3-c][2] benzazepine and has the molecular formula of C 17 H 19 N 3 .
Its molecular weight is 265.35. The structural formula is the following and it is the racemic mixture: Mirtazapine is a white to creamy white crystalline powder which is practically insoluble in water. Mirtazapine tablets, USP are available for oral administration as scored film-coated tablets containing 15 or 30 mg of mirtazapine USP, and unscored film-coated tablets containing 7.5 or 45 mg of mirtazapine USP.
Each tablet contains the following inactive ingredients: colloidal silicon dioxide, corn starch, hydroxypropyl cellulose, hypromellose, lactose monohydrate, magnesium stearate, and titanium dioxide. In addition, the 15 mg contains iron oxide yellow and 30 mg contains iron oxide red, iron oxide black, and iron oxide yellow. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Suicidal Thoughts and Behaviors Advise patients and caregivers to look for the emergence of suicidality, especially early during treatment and when the dosage is adjusted up or down, and instruct them to report such symptoms to the healthcare provider [see Boxed Warning and Warnings and Precautions (5.1) ]. Agranulocytosis Advise patients to contact their physician if they experience fever, chills, sore throat, mucous membrane ulceration, flu-like complaints, or other symptoms that might suggest infection [see Warnings and Precautions (5.2) ].
Serotonin Syndrome Caution patients about the risk of serotonin syndrome, particularly with the concomitant use of mirtazapine with other serotonergic drugs including triptans, tricyclic antidepressants, fentanyl, lithium, tramadol, tryptophan, buspirone, amphetamines, St. John’s Wort, and with drugs that impair metabolism of serotonin (in particular, MAOIs, both those intended to treat psychiatric disorders and also others, such as linezolid). Advise patients to contact their healthcare provider or report to the emergency room if they experience signs or symptoms of serotonin syndrome [see Dosage and Administration (2.4) , Contraindications (4) , Warnings and Precautions (5.3) , Drug Interactions (7) ].
QT Prolongation and Torsades de Pointes Inform patients to consult their physician immediately if they feel faint, lose consciousness, or have heart palpitations [see Warnings and Precautions (5.5) , Drug Interactions (7) , Overdosage (10) ]. Advise patients to inform physicians that they are taking mirtazapine before any new drug is taken. Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) Advise patients to report to their healthcare provider at the earliest onset of fever, rash, swollen lymph nodes, or other signs and symptoms suggestive of Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS) [see Contraindications (4) , Warnings and Precautions (5.6) ].
Somnolence Advise patients that mirtazapine may impair judgment, thinking, and particularly, motor skills, because of its prominent sedative effect. Caution patients about performing activities requiring mental alertness, such as operating hazardous machinery or operating a motor vehicle, until they are reasonably certain that mirtazapine therapy does not adversely affect their ability to engage in such activities . [see Warnings and Precautions (5.8) ]. Alcohol Advise patients to avoid alcohol while taking mirtazapine [see Warnings and Precautions (5.8) , Drug Interactions (7) ].
Activation of Mania/Hypomania Advise patients and their caregivers to observe for signs of activation of mania/hypomania and instruct them to report such symptoms to the healthcare provider [see Warnings and Precautions (5.9) ]. Discontinuation Syndrome Advise patients not to abruptly discontinue mirtazapine and to discuss any tapering regimen with their healthcare provider. Adverse reactions can occur when mirtazapine is discontinued [see Dosage and Administration (2.6) , Warnings and Precautions (5.14) ].
Allergic Reactions Advise patients to notify their healthcare provider if they develop an allergic reaction such as rash, hives, swelling, or difficulty breathing [see Contraindications (4) , Adverse Reactions (6.2) ]. Pregnancy Advise patients to notify their physician if they become pregnant or intend to become pregnant during mirtazapine therapy. Advise patients that there is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to mirtazapine during pregnancy [see Use in Specific Populations (8.1) ].
Lactation Advise patients to notify their physician if they are breastfeeding an infant [see Use in Specific Populations (8.2) ]. Angle-Closure Glaucoma Patients should be advised that taking mirtazapine can cause mild pupillary dilation, which in susceptible individuals, can lead to an episode of…
💬 Medication Guide ▾
MEDICATION GUIDE Mirtazapine Tablets, USP for oral use (mir taz’ a peen) What is the most important information I should know about mirtazapine tablets? Mirtazapine tablets may cause serious side effects, including: Increased risk of suicidal thoughts or actions in some children and young adults . Mirtazapine tablets, and other antidepressant medicines may increase suicidal thoughts or actions in some people 24 years of age and younger, especially within the first few months of treatment or when the dose is changed.
Mirtazapine tablets are not for use in children. Depression or other serious mental illnesses are the most important causes of suicidal thoughts or actions. How can I watch for and try to prevent suicidal thoughts and actions?
Pay close attention to any changes, especially sudden changes in mood, behavior, thoughts, or feelings, or if you develop suicidal thoughts or actions. This is very important when an antidepressant medicine is started or when the dose is changed. Call your healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings.
Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you have concerns about symptoms. Call your healthcare provider or get emergency medical help right away if you or your family member have any of the following symptoms, especially if they are new, worse, or worry you: attempts to commit suicide acting on dangerous impulses acting aggressive, being angry or violent thoughts about suicide or dying new or worse depression new or worse anxiety panic attacks feeling very agitated or restless new or worse irritability trouble sleeping an extreme increase in activity or talking (mania) other unusual changes in behavior or mood What are mirtazapine tablets?
Mirtazapine tablets are prescription medicines used to treat a certain type of depression called Major Depressive Disorder (MDD) in adults. It is not known if mirtazapine tablets are safe and effective for use to treat MDD in children. Who should not take mirtazapine tablets?
Do not take mirtazapine tablets if you: take a Monoamine Oxidase Inhibitor (MAOI) have stopped taking an MAOI in the last 14 days are being treated with the antibiotic linezolid or intravenous methylene blue if you are allergic to mirtazapine or any of the ingredients in mirtazapine tablets. See the end of this Medication Guide for a complete list of ingredients in mirtazapine tablets. Ask your healthcare provider or pharmacist if you are not sure if you take an MAOI, including the antibiotic linezolid or intravenous methylene blue.
Do not start taking an MAOI for at least 14 days after you stop treatment with mirtazapine tablets. Before taking mirtazapine tablets, tell your healthcare provider about all your medical conditions, including if you: have a history of suicide or depression have a history or family history of bipolar disorder, mania or hypomania have a low white blood cell count have glaucoma (high pressure in the eye) have or had heart problems or stroke have an abnormal heart beat called QT prolongation or a family history of QT prolongation have seizures have high cholesterol or triglyceride levels have low sodium levels in your blood have or had kidney or liver problems have low blood pressure are pregnant or plan to become pregnant.
It is not known if mirtazapine tablets will harm your unborn baby. Talk to your healthcare provider if you become pregnant or think you may be pregnant during treatment with mirtazapine tablets. If you become pregnant while taking mirtazapine tablets, talk to your healthcare provider about registering with the National Pregnancy Registry for Antidepressants.
You can register by calling 1-844-405-6185 or visiting online at https://womensmentalhealth.org/clinical-and-researchprograms/pregnancyregistry/antidepressants/. The purpose of this registry is to monitor the pregnancy outcomes in w…