
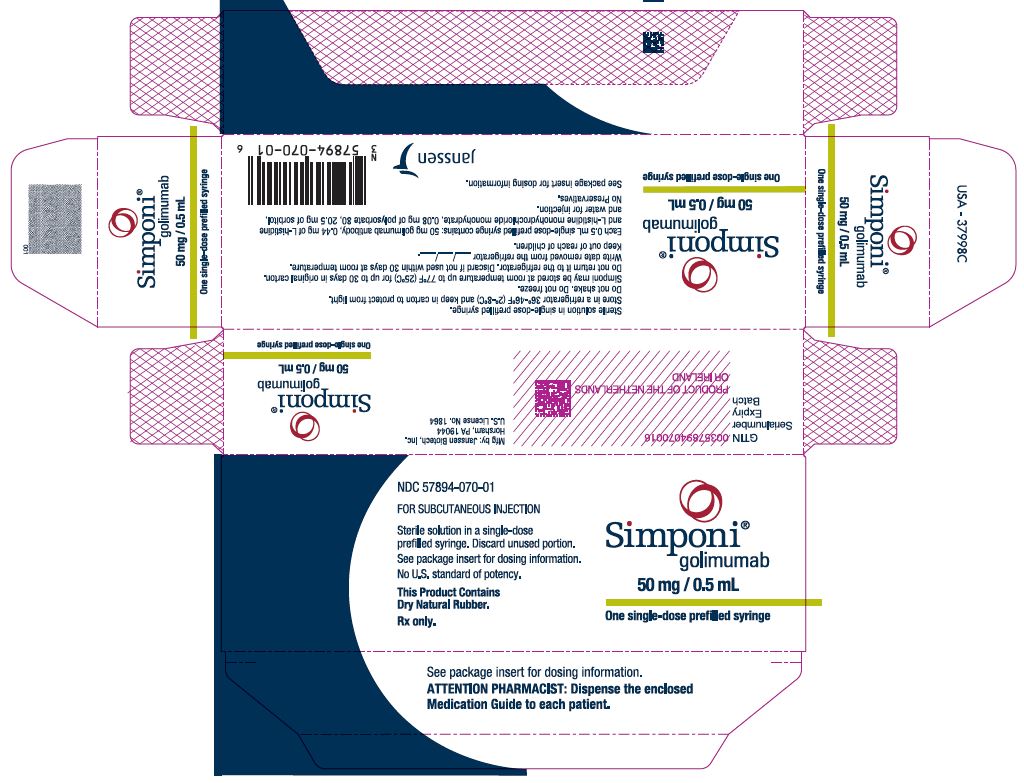
Simponi golimumab 50 mg/.5mL Injection, Solution, 1 syringe
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Golimumab injection is used to treat the symptoms of: rheumatoid arthritis (condition in which the body attacks its own joints causing pain, swelling, and loss of function). ankylosing spondylitis (condition in which the body attacks the joints of the spine and other areas, causing pain and joint damage). psoriatic arthritis (condition that causes joint pain and swelling and scales on the skin). ulcerative colitis (a condition which causes swelling and sores in the lining of the colon [large intestine] and rectum). polyarticular juvenile idiopathic arthritis (PJIA; a type of childhood...
Read the full MedlinePlus article ↗- Golimumab is approved for several inflammatory conditions, and which ones depend on the product you're using. Simponi — the version you inject under your own skin — treats rheumato...
- What conditions does golimumab actually treat?
- Before injecting, take the prefilled syringe or autoinjector out of the refrigerator and let it sit at room temperature for at least 30 minutes — don't try to warm it up any other...
- How do I give myself the Simponi injection at home?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Golimumab — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.44 mg / 0.5 mL
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
UNII X573657P6P
Histidine monohydrochloride monohydrate is an amino acid salt used as a buffer in medicines. It helps maintain the proper acidity level of liquid formulations to keep the drug stable and effective.
-
0.08 mg / 0.5 mL
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
20.5 mg / 0.5 mL
UNII 506T60A25R
Sorbitol is a natural sugar alcohol derived from glucose. It serves as a sweetener, humectant, and bulking agent in medications to improve taste and help maintain moisture in the product.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $13,144.95 | $6,572.47 / 0.5 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Simponi 50 mg/.5mLthis 57894-0070-90 | Janssen | 1 syringe | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
Biologics have no small-molecule generics; biosimilar competition is tracked in the FDA Purple Book.
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9,487,810 ↗ | Biologic patent | — | Mar 14, 2033 |
| US 8,017,325 ↗ | Biologic patent | — | Jan 13, 2029 |
| US 8,852,889 ↗ | Biologic patent | — | Jul 6, 2032 |
| US 8,956,830 ↗ | Biologic patent | — | Mar 14, 2033 |
| US 9,170,249 ↗ | Biologic patent | — | Mar 12, 2032 |
| US 9,217,168 ↗ | Biologic patent | — | Mar 14, 2033 |
| US 9,475,858 ↗ | Biologic patent | — | Jul 6, 2032 |
| US 9,663,810 ↗ | Biologic patent | — | Mar 14, 2033 |
| US 9,890,410 ↗ | Biologic patent | — | Mar 12, 2032 |
| US 10,421,986 ↗ | Biologic patent | — | Aug 8, 2035 |
| US 10,500,348 ↗ | Biologic patent | — | Nov 20, 2031 |
| US 11,225,516 ↗ | Biologic patent | — | May 3, 2039 |
| US 11,633,546 ↗ | Biologic patent | — | Nov 8, 2032 |
| US 12,139,735 ↗ | Biologic patent | — | Jul 6, 2032 |
Is there a biosimilar for SIMPONI 50 MG/0.5 ML PEN INJEC?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 57894-0070-01 | 1 SYRINGE, GLASS in 1 CARTON (57894-070-01) / .5 mL in 1 SYRINGE, GLASS | $12,977.20 / mL | $6,488.60 | 2009-04-25 | Active |
| 57894-0070-02 | 1 SYRINGE in 1 CARTON (57894-070-02) / .5 mL in 1 SYRINGE | $12,890.30 / mL | $6,445.15 | 2009-04-25 | Active |
| 57894-0070-89 | 1 SYRINGE in 1 CARTON (57894-070-89) / .5 mL in 1 SYRINGE | — | — | 2009-04-25 | Active |
| 57894-0070-90 You're viewing this | 1 SYRINGE, GLASS in 1 CARTON (57894-070-90) / .5 mL in 1 SYRINGE, GLASS | — | — | 2009-04-25 | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 57894-0070-90?
What is the difference between NDC 57894-0070-90 and NDC 57894-0070-01?
What NDC number is used to bill for this package of Simponi golimumab 50 mg/.5mL Injection, Solution?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SERIOUS INFECTIONS AND MALIGNANCY WARNING: SERIOUS INFECTIONS AND MALIGNANCY See full prescribing information for complete boxed warning. Serious infections leading to hospitalization or death including tuberculosis (TB), bacterial sepsis, invasive fungal (such as histoplasmosis), and other opportunistic infections have occurred in patients receiving SIMPONI ( 5.1 ) Discontinue SIMPONI if a patient develops a serious infection or sepsis ( 5.1 ) Perform test for latent TB; if positive, start treatment for TB prior to starting SIMPONI ( 5.1 ) Monitor all patients for active TB during treatment, even if initial latent TB test is negative ( 5.1 ) Lymphoma and other malignancies, some fatal, have been reported in children and adolescent patients treated with TNF blockers, of which SIMPONI is a member ( 5.2 ) SERIOUS INFECTIONS Patients treated with SIMPONI are at increased risk for developing serious infections that may lead to hospitalization or death [see Warnings and Precautions (5.1) ] .
Most patients who developed these infections were taking concomitant immunosuppressants such as methotrexate or corticosteroids. Discontinue SIMPONI if a patient develops a serious infection. Reported infections with TNF blockers, of which SIMPONI is a member, include: Active tuberculosis, including reactivation of latent tuberculosis.
Patients with tuberculosis have frequently presented with disseminated or extrapulmonary disease. Test patients for latent tuberculosis before SIMPONI use and during therapy. Initiate treatment for latent TB prior to SIMPONI use.
Invasive fungal infections including histoplasmosis, coccidioidomycosis, candidiasis, aspergillosis, blastomycosis, and pneumocystosis. Patients with histoplasmosis or other invasive fungal infections may present with disseminated, rather than localized, disease. Antigen and antibody testing for histoplasmosis may be negative in some patients with active infection.
Consider empiric antifungal therapy in patients at risk for invasive fungal infections who develop severe systemic illness. Bacterial, viral, and other infections due to opportunistic pathogens, including Legionella and Listeria. Consider the risks and benefits of treatment with SIMPONI prior to initiating therapy in patients with chronic or recurrent infection.
Monitor patients closely for the development of signs and symptoms of infection during and after treatment with SIMPONI, including the possible development of tuberculosis in patients who tested negative for latent tuberculosis infection prior to initiating therapy [see Warnings and Precautions (5.1) ] . MALIGNANCY Lymphoma and other malignancies, some fatal, have been reported in children and adolescent patients treated with TNF blockers, of which SIMPONI is a member [see Warnings and Precautions (5.2) ] .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE SIMPONI is a tumor necrosis factor (TNF) blocker indicated for the treatment of: adult patients with moderately to severely active rheumatoid arthritis (RA) in combination with methotrexate ( 1.1 ) adult patients with active psoriatic arthritis (PsA) alone, or in combination with methotrexate ( 1.2 ) adult patients with active ankylosing spondylitis (AS) ( 1.3 ) adult and pediatric patients weighing at least 15 kg with moderately to severely active ulcerative colitis (UC) ( 1.4 )
1.1Rheumatoid Arthritis SIMPONI, in combination with methotrexate, is indicated for the treatment of adult patients with moderately to severely active rheumatoid arthritis.
1.2Psoriatic Arthritis SIMPONI, alone or in combination with methotrexate, is indicated for the treatment of adult patients with active psoriatic arthritis.
1.3Ankylosing Spondylitis SIMPONI is indicated for the treatment of adult patients with active ankylosing spondylitis.
1.4Ulcerative Colitis SIMPONI is indicated for the treatment of adults and pediatric patients weighing at least 15 kg with moderately to severely active ulcerative colitis .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION RA, PsA, and AS : 50 mg administered by subcutaneous injection once a month ( 2.2 ) UC : The recommended dosage and administration by subcutaneous injection in adults and pediatric patients weighing at least 15 kg is shown in the table ( 2.3 ) Recommended Dosage Weight for Patients with UC Week 0 Week 2 Week 6 and every 4 weeks thereafter Adults and pediatric patients 40 kg and greater For pediatric patients weighing 15 kg or greater, administer the appropriate dose using the prefilled syringe (50 mg/0.5 mL or 100 mg/mL).
200 mg 100 mg 100 mg Pediatric patients at least 15 kg to less than 40 kg 100 mg 50 mg 50 mg
2.1Recommended Evaluations and Immunizations Before Initiating SIMPONI Prior to initiating treatment with SIMPONI: Evaluate patients for active tuberculosis and test for latent infection [see Warnings and Precautions (5.1) ]. Test patients for hepatitis B viral infection. If possible, complete all age-appropriate vaccinations according to current immunization guidelines [see Warnings and Precautions (5.11) ] .
2.2Recommended Dosage for Rheumatoid Arthritis, Psoriatic Arthritis, Ankylosing Spondylitis The recommended SIMPONI dosage in adults is 50 mg administered by subcutaneous injection once a month. For patients with rheumatoid arthritis (RA), SIMPONI should be given in combination with methotrexate and for patients with psoriatic arthritis (PsA) or ankylosing spondylitis (AS), SIMPONI may be given with or without methotrexate or other nonbiologic Disease-Modifying Antirheumatic Drugs (DMARDs). For patients with RA, PsA, or AS, corticosteroids, non-biologic DMARDs, and/or NSAIDs may be continued during treatment with SIMPONI.
2.3Recommended Dosage for Moderately to Severely Active Ulcerative Colitis in Adults and Pediatric Patients Weighing at least 15 kg The recommended dosage is shown in Table 1. Table 1: Recommended Subcutaneous Dosage for Adults and Pediatric Patients Weighing at least 15 kg with Moderately to Severely Active Ulcerative Colitis Weight for Patients with UC Recommended Dosage of SIMPONI Week 0 Week 2 Week 6 and every 4 weeks thereafter Adults and pediatric patients 40 kg and greater For pediatric patients weighing 15 kg or greater, administer the appropriate dose using the prefilled syringe (50 mg/0.5 mL or 100 mg/mL).
200 mg 100 mg 100 mg Pediatric patients at least 15 kg to less than 40 kg 100 mg 50 mg 50 mg
2.4Preparation and Administration Instructions SIMPONI is intended for use under the guidance and supervision of a healthcare provider after proper training in subcutaneous injection technique. Patients may self-inject with SIMPONI if a physician determines that it is appropriate. Instruct patients to follow the directions provided in the Instructions for Use.
SIMPONI Prefilled Syringe Adult and pediatric patients 12 years of age and older may self-inject with SIMPONI prefilled syringe. SIMPONI SmartJect ® Autoinjector Adult patients may self-inject with SIMPONI SmartJect ® autoinjector. Use of the SmartJect ® autoinjector for pediatric self-administration has not been evaluated. • To ensure proper use, allow the prefilled syringe or autoinjector to sit at room temperature outside the carton for at least 30 minutes prior to subcutaneous injection.
Do not warm SIMPONI in any other way. • Prior to administration, visually inspect the solution for particles and discoloration through the viewing window. SIMPONI is clear to slightly opalescent and colorless to light yellow. Do not use SIMPONI, if the solution is discolored, or cloudy, or if foreign particles are present. • Do not use any leftover product remaining in the prefilled syringe or prefilled autoinjector. • Instruct patients sensitive to latex not to handle the needle cover on the prefilled syringe or the needle cover of the prefilled syringe within the autoinjector cap because it contains dry natural rubber (a derivative of latex). • At the time of dosing, if multiple injections are required, administer…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Injection: 50 mg/0.5 mL and 100 mg/mL clear to slightly opalescent, colorless to light yellow solution in a single-dose prefilled syringe or single-dose SmartJect ® autoinjector. Injection ( 3 ): 50 mg/0.5 mL in a single-dose prefilled syringe or single-dose prefilled SmartJect ® autoinjector 100 mg/mL in a single-dose prefilled syringe or single-dose prefilled SmartJect ® autoinjector
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serious Infections: Do not start SIMPONI during an active infection. If an infection develops, monitor carefully, and stop SIMPONI if infection becomes serious ( 5.1 ) Invasive Fungal Infections: For patients who develop a systemic illness on SIMPONI, consider empiric antifungal therapy for those who reside in or travel to regions where mycoses are endemic ( 5.1 ) Malignancies: Incidence of lymphoma was greater than in the general U.S. population. Cases of other malignancies have been observed among patients receiving TNF blockers ( 5.2 ) Congestive Heart Failure: Worsening, or new onset, may occur.
Stop SIMPONI if new or worsening symptoms occur ( 5.3 ) Demyelinating Disorders: Exacerbation or new onset may occur ( 5.4 ) Hepatitis B Reactivation: Monitor HBV carriers during and several months after therapy. If reactivation occurs, stop SIMPONI and begin antiviral therapy ( 5.5 ) Lupus-like Syndrome: Discontinue SIMPONI if symptoms develop ( 5.6 ) Hypersensitivity Reactions: Serious systemic hypersensitivity reactions including anaphylaxis may occur ( 5.12 )
5.1Serious Infections Patients treated with SIMPONI are at increased risk for developing serious infections involving various organ systems and sites that may lead to hospitalization or death. Opportunistic infections due to bacterial, mycobacterial, invasive fungal, viral, or parasitic organisms including aspergillosis, blastomycosis, candidiasis, coccidioidomycosis, histoplasmosis, legionellosis, listeriosis, pneumocystosis, and tuberculosis have been reported with TNF blockers. Patients have frequently presented with disseminated rather than localized disease.
The concomitant use of a TNF blocker and abatacept or anakinra was associated with a higher risk of serious infections; therefore, the concomitant use of SIMPONI and these biologic products is not recommended [see Warnings and Precautions (5.6 , 5.7) and Drug Interactions (7.2) ] . Treatment with SIMPONI should not be initiated in patients with an active infection, including clinically important localized infections. Patients greater than 65 years of age, patients with co-morbid conditions and/or patients taking concomitant immunosuppressants such as corticosteroids or methotrexate may be at greater risk of infection.
Consider the risks and benefits of treatment prior to initiating SIMPONI in patients: with chronic or recurrent infection; who have been exposed to tuberculosis; with a history of an opportunistic infection; who have resided or traveled in areas of endemic tuberculosis or endemic mycoses, such as histoplasmosis, coccidioidomycosis, or blastomycosis; or with underlying conditions that may predispose them to infection. Monitoring Closely monitor patients for the development of signs and symptoms of infection during and after treatment with SIMPONI.
Discontinue SIMPONI if a patient develops a serious infection, an opportunistic infection, or sepsis. For a patient who develops a new infection during treatment with SIMPONI, perform a prompt and complete diagnostic workup appropriate for an immunocompromised patient, initiate appropriate antimicrobial therapy, and closely monitor them. Serious Infection in Clinical Trials In controlled Phase 3 trials through Week 16 in patients with RA, PsA, and AS, serious infections were observed in 1.4% of SIMPONI-treated patients and 1.3% of control-treated patients.
In the controlled Phase 3 trials through Week 16 in patients with RA, PsA, and AS, the incidence of serious infections per 100 patient-years of follow-up was 5.7 (95% CI: 3.8, 8.2) for the SIMPONI group and 4.2 (95% CI: 1.8, 8.2) for the placebo group. In the controlled Phase 2/3 trial through Week 6 of SIMPONI induction in UC, the incidence of serious infections in SIMPONI 200/100 mg-treated patients was similar to the incidence of serious infections in placebo-treated patients. Through Week 60, the incidence of serious infections was similar in patients who received SIMPONI in…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are described elsewhere in the labeling: Serious Infections [see Warnings and Precautions (5.1) ] Malignancies [see Warnings and Precautions (5.2) ] Congestive Heart Failure [see Warnings and Precautions (5.3) ] Demyelinating Disorders [see Warnings and Precautions (5.4) ] Hepatitis B Reactivation [see Warnings and Precautions (5.5) ] Autoimmunity [see Warnings and Precautions (5.6) ] Hematologic Cytopenias [see Warnings and Precautions (5.10) ] Hypersensitivity Reactions [see Warnings and Precautions (5.12) ] Most common adverse reactions in adults (incidence > 5%) are upper respiratory tract infection, nasopharyngitis, injection site reactions ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Janssen Biotech, Inc. at 1-800-JANSSEN (1-800-526-7736) or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. The safety data described below are based on: Five pooled, randomized, double-blind, controlled Phase 3 trials in patients with RA, PsA, and AS (Trials RA-1, RA-2, RA-3, PsA, and AS) [see Clinical Studies (14.1 , 14.2 , and 14.3) ] .
These 5 trials included 639 control-treated patients and 1659 SIMPONI-treated patients including 1089 with RA, 292 with PsA, and 278 with AS. Three pooled, randomized, double-blind, controlled Phase 2/3 in 1233 SIMPONI-treated adult patients with UC (Trials UC-1, UC-2, and UC-3 (NCT03596645)) [see Clinical Studies (14.4) ] . An open-label trial in 69 SIMPONI-treated pediatric patients weighing at least 15 kg with UC (Trial UC-3) (NCT03596645) [see Clinical Studies (14.5) ] .
The proportion of adult patients who discontinued treatment due to adverse reactions in the controlled Phase 3 trials through Week 16 in RA, PsA and AS was 2% for SIMPONI-treated patients and 3% for placebo-treated patients. The most common adverse reactions leading to discontinuation of SIMPONI in the controlled Phase 3 trials in RA, PsA and AS through Week 16 were sepsis (0.2%), alanine aminotransferase increased (0.2%), and aspartate aminotransferase increased (0.2%). The most common adverse drug reactions leading to discontinuation through Week 60 of the UC trials in adult patients who received SIMPONI induction and 100 mg during maintenance compared with patients who received SIMPONI induction and placebo during maintenance were tuberculosis (0.3% vs.
0.6%) and anemia (0.3% vs. 0%), respectively. Upper respiratory tract infection and nasopharyngitis were the most common adverse reactions reported in the combined Phase 3 RA, PsA and AS trials in adults through Week 16, occurring in 7% and 6% of SIMPONI-treated patients as compared with 6% and 5% of control-treated patients, respectively.
Infections In adult controlled Phase 3 trials through Week 16 in RA, PsA, and AS, infections were observed in 28% of SIMPONI-treated patients compared to 25% of control-treated patients. For serious infections, see the Warnings and Precautions section [see Warnings and Precautions (5.1) ] . In Trial UC-1, the rates of infections were similar in SIMPONI 200/100 mg-treated patients and placebo-treated patients, or approximately 12%.
Through Week 60, the incidence per patient year of infections was similar in patients who received SIMPONI induction and 100 mg during maintenance compared with patients who received SIMPONI induction and placebo during the maintenance period Trial UC-2. Demyelinating Disorders In Trial UC-1 of SIMPONI induction through Week 6, no cases of demyelination were observed in SIMPONI 200/100 mg-treated patients or placebo-treated patients. Through Week 60 in Trial UC-2, there were no cases of demyelination in the SIMPONI 100 mg group during mainten…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Abatacept: Increased risk of serious infection ( 5.1 , 5.7 , 7.2 ) Anakinra: Increased risk of serious infection ( 5.1 , 5.8 , 7.2 ) Live vaccines/therapeutic infectious agents: Avoid use with SIMPONI ( 5.11 , 7.3 ).
7.1Methotrexate For the treatment of RA, SIMPONI should be used with methotrexate (MTX) [see Clinical Studies (14.1) ] . Since the presence or absence of concomitant MTX did not appear to influence the efficacy or safety of SIMPONI in the treatment of PsA or AS, SIMPONI can be used with or without MTX in the treatment of PsA and AS [see Clinical Studies (14.2 , 14.3) and Clinical Pharmacology (12.3) ] .
7.2Biological Products for RA, PsA, and/or AS An increased risk of serious infections has been seen in clinical RA trials of other TNF blockers used in combination with anakinra or abatacept, with no added benefit; therefore, use of SIMPONI with abatacept or anakinra is not recommended [see Warnings and Precautions (5.7 , 5.8) ] . A higher rate of serious infections has also been observed in RA patients treated with rituximab who received subsequent treatment with a TNF blocker. The concomitant use of SIMPONI with biologics approved to treat RA, PsA, or AS is not recommended because of the possibility of an increased risk of infection.
7.3Live Vaccines/Therapeutic Infectious Agents Live vaccines should not be given concurrently with SIMPONI [see Warnings and Precautions (5.11) ] . Therapeutic infectious agents should not be given concurrently with SIMPONI [see Warnings and Precautions (5.11) ] . Infants born to women treated with SIMPONI during their pregnancy may be at increased risk of infection for up to 6 months.
Administration of live vaccines to infants exposed to SIMPONI in utero is not recommended for 6 months following the mother's last SIMPONI injection during pregnancy [see Use in Specific Populations (8.1) ] .
7.4Cytochrome P450 Substrates The formation of CYP450 enzymes may be suppressed by increased levels of cytokines (e.g., TNFα) during chronic inflammation. Therefore, it is expected that for a molecule that antagonizes cytokine activity, such as golimumab, the formation of CYP450 enzymes could be normalized. Upon initiation or discontinuation of SIMPONI in patients being treated with CYP450 substrates with a narrow therapeutic index, monitoring of the effect (e.g., warfarin) or drug concentration (e.g., cyclosporine or theophylline) is recommended and the individual dose of the drug product may be adjusted as needed.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Available data from postmarketing case reports with golimumab use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. An observational study of northern European births observed similar unadjusted rates of major birth defects in infants exposed in utero to golimumab compared to no treatment or non-biologic systemic therapy. However, this study had important limitations (see Data ) .
Monoclonal antibodies, such as golimumab, are transported across the placenta during the third trimester of pregnancy and may affect immune response in the in utero exposed infant (see Clinical Considerations ) . In an animal reproductive study, golimumab administered by the subcutaneous route to pregnant monkeys, during the period of organogenesis, at doses that produced exposures approximately 360 times the maximum recommended human dose (MRHD) had no adverse fetal effects (see Data ) . In a pre- and post-natal development study with pregnant monkeys, subcutaneous administration of golimumab, during the later gestational and lactation periods, at doses producing maximal maternal blood concentrations approximately 460 times those found with the MRHD had no adverse developmental effects on infants (see Data ) .
Data suggest that there are risks to the mother and the fetus associated with rheumatoid arthritis and ulcerative colitis in pregnancy (see Clinical Considerations ) . All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and of miscarriage is 15–20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with rheumatoid arthritis or ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth.
Fetal/Neonatal Adverse Reactions Golimumab crosses the placenta during pregnancy. Another TNF-blocking monoclonal antibody administered during pregnancy was detected for up to 6 months in the serum of infants. Consequently, these infants may be at increased risk of infection.
Administration of live vaccines to infants exposed to SIMPONI in utero is not recommended for 6 months following the mother's last SIMPONI injection during pregnancy [see Warnings and Precautions (5.11) and Drug Interactions (7.3) ] . Data Human Data An observational, exposure-based, cohort study based on data from the Swedish, Danish, and Finnish Medical Birth Registers conducted between 2006–2020 (Sweden and Denmark) and 2006–2019 (Finland) compared the risk of major birth defects in 134 live-born infants exposed to golimumab (116 from women treated for rheumatic conditions, 18 from women treated for ulcerative colitis) to no treatment or non-biologic systemic therapy.
The unadjusted rate of major birth defects in infants exposed in utero was similar across all groups. However, this study had important limitations such as a small number of pregnant women exposed to golimumab, a wide exposure ascertainment window, and incomplete risk adjustment for potential confounders. Animal Data In an embryofetal developmental toxicology study in which pregnant cynomolgus monkeys were treated with golimumab during the period organogenesis from gestation days (GD) 20 to 51, exposures up to 360 times greater than the exposure at the MRHD (on an area under the curve (AUC) basis with maternal subcutaneous doses up to 50 mg/kg twice weekly) produced no evidence of fetal malformations or embry…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from postmarketing case reports with golimumab use in pregnant women have not identified a drug-associated risk of major birth defects, miscarriage, or adverse maternal or fetal outcomes. An observational study of northern European births observed similar unadjusted rates of major birth defects in infants exposed in utero to golimumab compared to no treatment or non-biologic systemic therapy. However, this study had important limitations (see Data ) .
Monoclonal antibodies, such as golimumab, are transported across the placenta during the third trimester of pregnancy and may affect immune response in the in utero exposed infant (see Clinical Considerations ) . In an animal reproductive study, golimumab administered by the subcutaneous route to pregnant monkeys, during the period of organogenesis, at doses that produced exposures approximately 360 times the maximum recommended human dose (MRHD) had no adverse fetal effects (see Data ) . In a pre- and post-natal development study with pregnant monkeys, subcutaneous administration of golimumab, during the later gestational and lactation periods, at doses producing maximal maternal blood concentrations approximately 460 times those found with the MRHD had no adverse developmental effects on infants (see Data ) .
Data suggest that there are risks to the mother and the fetus associated with rheumatoid arthritis and ulcerative colitis in pregnancy (see Clinical Considerations ) . All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. The background risk of major birth defects and miscarriage for the indicated populations is unknown.
In the U.S. general population, the estimated background risks of major birth defects and miscarriage in clinically recognized pregnancies is 2–4% and of miscarriage is 15–20%, respectively. Clinical Considerations Disease-associated Maternal and/or Embryo/Fetal Risk Published data suggest that increased disease activity is associated with the risk of developing adverse pregnancy outcomes in women with rheumatoid arthritis or ulcerative colitis. Adverse pregnancy outcomes include preterm delivery (before 37 weeks gestation), low birth weight (less than 2500 g) infants, and small for gestational age at birth.
Fetal/Neonatal Adverse Reactions Golimumab crosses the placenta during pregnancy. Another TNF-blocking monoclonal antibody administered during pregnancy was detected for up to 6 months in the serum of infants. Consequently, these infants may be at increased risk of infection.
Administration of live vaccines to infants exposed to SIMPONI in utero is not recommended for 6 months following the mother's last SIMPONI injection during pregnancy [see Warnings and Precautions (5.11) and Drug Interactions (7.3) ] . Data Human Data An observational, exposure-based, cohort study based on data from the Swedish, Danish, and Finnish Medical Birth Registers conducted between 2006–2020 (Sweden and Denmark) and 2006–2019 (Finland) compared the risk of major birth defects in 134 live-born infants exposed to golimumab (116 from women treated for rheumatic conditions, 18 from women treated for ulcerative colitis) to no treatment or non-biologic systemic therapy.
The unadjusted rate of major birth defects in infants exposed in utero was similar across all groups. However, this study had important limitations such as a small number of pregnant women exposed to golimumab, a wide exposure ascertainment window, and incomplete risk adjustment for potential confounders. Animal Data In an embryofetal developmental toxicology study in which pregnant cynomolgus monkeys were treated with golimumab during the period organogenesis from gestation days (GD) 20 to 51, exposures up to 360 times greater than the exposure at the MRHD (on an area under the curve (AUC) basis with maternal subcutaneous doses up to 50 mg/kg twice weekly) produced no evidence of fetal malformations or embryotoxicity.
There was no eviden…
🧒 Pediatric Use ▾
8.4Pediatric Use Ulcerative Colitis The safety and effectiveness of SIMPONI for the treatment of moderately to severely active ulcerative colitis have been established in pediatric patients weighing at least 15 kg. Use of SIMPONI for this indication is supported by evidence from adequate and well-controlled studies in adults with additional safety and efficacy data from an open-label, study in 69 pediatric patients (4 to 17 years of age). The adverse reaction profile in these pediatric patients was similar to adults [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , and Clinical Studies (14.5) ] .
Additionally, headache (17%) and pyrexia (10%) were reported in at least 10% of pediatric patients in the trial. The safety and effectiveness of SIMPONI for the treatment of moderately to severely active ulcerative colitis have not been established in pediatric patients weighing less than 15 kg. Polyarticular Juvenile Idiopathic Arthritis (pJIA) The safety and efficacy of SIMPONI were evaluated in a multicenter, placebo-controlled, double-blind, randomized-withdrawal, parallel group study in 173 children (2 to 17 years of age) with active polyarticular juvenile idiopathic arthritis (pJIA) despite treatment with MTX for at least 3 months.
Subjects were maintained on their stable dose of MTX at the same dose (mg/week) at study entry. Concurrent use of stable doses of oral corticosteroids (≤10 mg/day or 0.2 mg/kg/day prednisone or equivalent, whichever was less) and/or NSAIDs was permitted. In the 16 week open-label phase, all patients received MTX and SIMPONI 30 mg/m 2 (maximum 50 mg) subcutaneously every 4 weeks.
Patients who achieved an ACR Ped 30 response at Week 16 entered the randomized-withdrawal phase of the study and received MTX and either SIMPONI 30 mg/m 2 (maximum 50 mg) or placebo every 4 weeks through Week 48. The primary endpoint of the study was the proportion of patients who did not experience a flare between Week 16 and Week 48, among all subjects who entered the randomized withdrawal phase. The efficacy of SIMPONI in the treatment of pJIA was not demonstrated in this study because there was no statistical evidence of differences in flare rate between SIMPONI-treated patients and placebo patients between Weeks 16 and 48.
In this study, the frequency and type of the adverse reactions seen in children were generally similar to those observed in adults.
🧓 Geriatric Use ▾
8.5Geriatric Use In the Phase 3 trials in RA, PsA, and AS, there were no overall differences in SAEs, serious infections, and AEs in SIMPONI-treated patients ages 65 or older (N=155) compared with younger SIMPONI-treated patients. Clinical studies of SIMPONI in patients with moderately to severely active ulcerative colitis did not include sufficient numbers of patients aged 65 and over to determine whether they respond differently than younger adult patients. Because there is a higher incidence of infections in the geriatric population in general, caution should be used in treating geriatric patients with SIMPONI [see Warnings and Precautions (5.1 , 5.5) ] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Golimumab is a human monoclonal antibody that binds to both the soluble and transmembrane bioactive forms of human TNFα. This interaction prevents the binding of TNFα to its receptors, thereby inhibiting the biological activity of TNFα (a cytokine protein). There was no evidence of the golimumab antibody binding to other TNF superfamily ligands; in particular, the golimumab antibody did not bind or neutralize human lymphotoxin.
Golimumab did not lyse human monocytes expressing transmembrane TNF in the presence of complement or effector cells. Elevated TNFα levels in the blood, synovium, and joints have been implicated in the pathophysiology of several chronic inflammatory diseases such as rheumatoid arthritis, psoriatic arthritis, and ankylosing spondylitis. TNFα is an important mediator of the articular inflammation that is characteristic of these diseases.
The exact mechanism by which golimumab treats ulcerative colitis is unknown. Golimumab modulated the in vitro biological effects mediated by TNF in several bioassays, including the expression of adhesion proteins responsible for leukocyte infiltration (E-selectin, ICAM-1 and VCAM-1) and the secretion of proinflammatory cytokines (IL-6, IL-8, G-CSF and GM-CSF).
12.2Pharmacodynamics In clinical trials, decreases in C-reactive protein (CRP), interleukin (IL)-6, matrix metalloproteinase-3 (MMP-3), intercellular adhesion molecule (ICAM)-1 and vascular endothelial growth factor (VEGF) were observed following SIMPONI administration in patients with RA, PsA, and AS.
12.3Pharmacokinetics Absorption Following subcutaneous administration of SIMPONI to healthy subjects and patients with active RA, the median time to reach maximum serum concentrations (T max ) ranged from 2 to 6 days. A subcutaneous injection of 50 mg SIMPONI to healthy subjects produced a mean ± standard deviation maximum serum concentration (C max ) of 3.2 ± 1.4 mcg/mL. By cross-trial comparisons of mean AUC inf values following an IV or subcutaneous administration of SIMPONI, the absolute bioavailability of subcutaneous SIMPONI was estimated to be approximately 53%.
Distribution Following a single IV administration over the dose range of 0.1 to 10.0 mg/kg in patients with active RA, mean volume of distribution ranged from 58 to 126 mL/kg. The volume of distribution for golimumab indicates that golimumab is distributed primarily in the circulatory system with limited extravascular distribution. Metabolism The exact metabolic pathway of golimumab is unknown.
Elimination Following a single IV administration over the dose range of 0.1 to 10.0 mg/kg in patients with active RA, mean systemic clearance of SIMPONI was estimated to be 4.9 to 6.7 mL/day/kg. Median terminal half-life values were estimated to be approximately 2 weeks in healthy subjects and patients with active RA, PsA or AS. Population PK analyses indicated that concomitant use of NSAIDs, oral corticosteroids, or sulfasalazine did not influence the apparent clearance of golimumab.
Patients who developed anti-golimumab antibodies generally had lower steady-state serum trough concentrations of golimumab. Dose Linearity Golimumab exhibited dose-proportional pharmacokinetics (PK) in patients with active RA over the dose range of 0.1 to 10 mg/kg following a single intravenous (IV) dose. Following a single SC dose in healthy subjects, dose proportional pharmacokinetics were also observed over a dose range of 50 mg to 400 mg.
Single Dose Versus Multiple Doses When 50 mg SIMPONI was administered subcutaneous to patients with RA, PsA, or AS every 4 weeks, serum concentrations appeared to reach steady state by Week 12. With concomitant use of methotrexate (MTX), treatment with 50 mg SIMPONI subcutaneous every 4 weeks resulted in a mean steady-state trough serum concentration of approximately 0.4–0.6 mcg/mL in patients with active RA, approximately 0.5 mcg/mL in patients with active PsA, and approximately 0.8 mcg/mL in…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Golimumab is a human monoclonal antibody that binds to both the soluble and transmembrane bioactive forms of human TNFα. This interaction prevents the binding of TNFα to its receptors, thereby inhibiting the biological activity of TNFα (a cytokine protein). There was no evidence of the golimumab antibody binding to other TNF superfamily ligands; in particular, the golimumab antibody did not bind or neutralize human lymphotoxin.
Golimumab did not lyse human monocytes expressing transmembrane TNF in the presence of complement or effector cells. Elevated TNFα levels in the blood, synovium, and joints have been implicated in the pathophysiology of several chronic inflammatory diseases such as rheumatoid arthritis, psoriatic arthritis, and ankylosing spondylitis. TNFα is an important mediator of the articular inflammation that is characteristic of these diseases.
The exact mechanism by which golimumab treats ulcerative colitis is unknown. Golimumab modulated the in vitro biological effects mediated by TNF in several bioassays, including the expression of adhesion proteins responsible for leukocyte infiltration (E-selectin, ICAM-1 and VCAM-1) and the secretion of proinflammatory cytokines (IL-6, IL-8, G-CSF and GM-CSF).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING SIMPONI ® (golimumab) Injection is a preservative-free, sterile, clear to slightly opalescent, colorless to light yellow solution for subcutaneous use in a single-dose prefilled autoinjector (contains a prefilled glass syringe) or a single-dose prefilled glass syringe. The Type 1 glass syringe has a coated stopper. The fixed stainless-steel needle (5 bevel, 27G, ½ inch) is covered with a needle shield to prevent leakage of the solution through the needle and to protect the needle during handling prior to subcutaneous administration.
The needle shield is made of a dry natural rubber containing latex. 50 mg/0.5 mL single-dose prefilled syringe 1 pack NDC 57894-070-01 100 mg/mL single-dose prefilled syringe 1 pack NDC 57894-071-01 50 mg/0.5 mL single-dose prefilled SmartJect ® autoinjector 1 pack NDC 57894-070-02 100 mg/mL single-dose prefilled SmartJect ® autoinjector 1 pack NDC 57894-071-02 Storage and Handling Refrigerate SIMPONI between 36 °F to 46 °F (2 °C to 8 °C) in the original carton to protect from light until the time of use. Do not freeze.
Do not shake. Do not use SIMPONI beyond the expiration date (EXP) on the carton or the expiration date on the prefilled syringe (observed through the viewing window) or the prefilled SmartJect ® autoinjector. If needed, SIMPONI may be stored at room temperature up to 77 °F (25 °C) for a maximum single period of 30 days in the original carton to protect from light.
Once a syringe or autoinjector has been stored at room temperature, do not return the product to the refrigerator. If not used within 30 days at room temperature, discard SIMPONI.
📦 Storage and Handling ▾
Storage and Handling Refrigerate SIMPONI between 36 °F to 46 °F (2 °C to 8 °C) in the original carton to protect from light until the time of use. Do not freeze. Do not shake.
Do not use SIMPONI beyond the expiration date (EXP) on the carton or the expiration date on the prefilled syringe (observed through the viewing window) or the prefilled SmartJect ® autoinjector. If needed, SIMPONI may be stored at room temperature up to 77 °F (25 °C) for a maximum single period of 30 days in the original carton to protect from light. Once a syringe or autoinjector has been stored at room temperature, do not return the product to the refrigerator.
If not used within 30 days at room temperature, discard SIMPONI.
📋 Description ▾
11 DESCRIPTION Golimumab is a human IgG1κ monoclonal antibody specific for human tumor necrosis factor alpha (TNFα) that exhibits multiple glycoforms with molecular masses of approximately 150 to 151 kilodaltons. Golimumab was created using genetically engineered mice immunized with human TNF, resulting in an antibody with human-derived antibody variable and constant regions. Golimumab is produced by a recombinant cell line cultured by continuous perfusion and is purified by a series of steps that includes measures to inactivate and remove viruses.
SIMPONI ® (golimumab) Injection is a preservative-free, sterile, clear to slightly opalescent, colorless to light yellow solution of the golimumab antibody supplied in a single-dose prefilled syringe (with a passive needle safety guard) or a single-dose prefilled autoinjector. Each 0.5 mL prefilled syringe and autoinjector contains 50 mg golimumab, L-histidine and L-histidine monohydrochloride monohydrate (0.44 mg), polysorbate 80 (0.08 mg), sorbitol (20.5 mg) and Water for Injection. Each 1 mL prefilled syringe and autoinjector contains 100 mg golimumab, L-histidine and L-histidine monohydrochloride monohydrate (0.87 mg), polysorbate 80 (0.15 mg), sorbitol (41.0 mg) and Water for Injection.
The pH is approximately 5.5.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling (Medication Guide and Instructions for Use) Patients should be advised of the potential benefits and risks of SIMPONI. Physicians should instruct their patients to read the Medication Guide before starting SIMPONI therapy and to read it each time the prescription is renewed. Infections Inform patients that SIMPONI may lower the ability of their immune system to fight infections.
Advise patients not to start taking SIMPONI if they have an active infection. Instruct patients to contact their healthcare provider if they develop any symptoms of infection, including tuberculosis, invasive fungal infections, and hepatitis B reactivation [see Warnings and Precautions (5.1 , 5.5) ] . Malignancies Inform patients that SIMPONI may increase their risk of lymphoma and other malignancies while receiving SIMPONI [see Warnings and Precautions (5.2) ] .
Hypersensitivity Reactions Advise patients to stop taking SIMPONI and contact their healthcare provider immediately if they experience any symptoms of hypersensitivity reactions while taking SIMPONI [see Warnings and Precautions (5.12) ] . Advise latex-sensitive patients that the needle cover on the prefilled syringe as well as the prefilled syringe in the prefilled SmartJect ® autoinjector contains dry natural rubber (a derivative of latex) [see How Supplied/Storage and Handling (16) ] . Other Medical Conditions Advise patients to report any signs of new or worsening medical conditions such as congestive heart failure, demyelinating disorders, autoimmune diseases, liver disease, or cytopenias [see Warnings and Precautions (5.3 , 5.4 , 5.5 , 5.6 , 5.10) ] .
Instructions for Safe Administration The first injection should be performed under the supervision of a qualified healthcare professional. Only the prefilled syringe is recommended for pediatric self-injection. SIMPONI Prefilled Syringe Adult and pediatric patients 12 years of age and older may self-inject with SIMPONI prefilled syringe.
SIMPONI SmartJect ® Autoinjector Adult patients may self-inject with SIMPONI SmartJect ® autoinjector. Use of the SmartJect ® autoinjector for pediatric self-administration has not been evaluated. If a patient or caregiver is to administer SIMPONI, he/she should be instructed in injection techniques and their ability to inject subcutaneously should be assessed to ensure the proper administration of SIMPONI.
Advise the patient to read the FDA-approved Instructions for Use and provide the following instructions to patients: Prior to use, remove the prefilled syringe or the prefilled SmartJect ® autoinjector from the refrigerator and allow SIMPONI to sit at room temperature outside of the carton for at least 30 minutes and out of the reach of children. Do not warm SIMPONI in any other way. For example, do not warm SIMPONI in a microwave or in hot water.
Do not remove the prefilled syringe needle cover or SmartJect ® autoinjector cap while allowing SIMPONI to reach room temperature. Remove these immediately before injection. Do not pull the autoinjector away from the skin until you hear a first "click" sound and then a second "click" sound (the injection is finished and the needle is pulled back).
It usually takes about 3 to 6 seconds but may take up to 15 seconds for you to hear the second "click" after the first "click". If the autoinjector is pulled away from the skin before the injection is completed, a full dose of SIMPONI may not be administered. A puncture-resistant container for disposal of needles and syringes should be used.
Patients or caregivers should be instructed in the technique of proper syringe and needle disposal, and be advised not to reuse these items.
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: Oct 2025 MEDICATION GUIDE SIMPONI ® (SIM-po-nee) (golimumab) injection, for subcutaneous use What is the most important information I should know about SIMPONI?
SIMPONI is a medicine that affects your immune system. SIMPONI can lower the ability of your immune system to fight infections. Some people have serious infections while taking SIMPONI, including tuberculosis (TB), and infections caused by bacteria, fungi, or viruses that spread throughout their body.
Some people have died from these serious infections. Your doctor should test you for TB and hepatitis B before starting SIMPONI. Your doctor should monitor you closely for signs and symptoms of TB during treatment with SIMPONI.
You should not start taking SIMPONI if you have any kind of infection unless your doctor says it is okay. Before starting SIMPONI, tell your doctor if you: think you have an infection or have symptoms of an infection such as: fever, sweat, or chills muscle aches cough shortness of breath blood in phlegm weight loss warm, red, or painful skin or sores on your body diarrhea or stomach pain burning when you urinate or urinate more often than normal feel very tired are being treated for an infection. get a lot of infections or have infections that keep coming back. have diabetes, HIV, or a weak immune system.
People with these conditions have a higher chance for infections. have TB, or have been in close contact with someone with TB. live, have lived, or traveled to certain parts of the country (such as the Ohio and Mississippi River valleys and the Southwest) where there is an increased chance for getting certain kinds of fungal infections (histoplasmosis, coccidioidomycosis, blastomycosis). These infections may happen or become more severe if you use SIMPONI. Ask your doctor if you do not know if you have lived in an area where these infections are common. have or have had hepatitis B. use the medicine ORENCIA (abatacept), KINERET (anakinra), ACTEMRA (tocilizumab) or RITUXAN (rituximab).
After starting SIMPONI , call your doctor right away if you have any symptoms of an infection. SIMPONI can make you more likely to get infections or make worse any infection that you have. Cancer For children and adults taking TNF-blocker medicines, including SIMPONI, the chances of getting cancer may increase.
There have been cases of unusual cancers in children and teenage patients taking TNF-blocking agents. People with inflammatory diseases including rheumatoid arthritis, psoriatic arthritis, or ankylosing spondylitis, especially those with very active disease, may be more likely to get lymphoma. Some people receiving medicines that are like SIMPONI, called TNF blockers, developed a rare type of cancer called hepatosplenic T cell lymphoma.
This type of cancer often results in death. Most of these people were male teenagers or young men. Also, most people were being treated for Crohn's disease or ulcerative colitis with a TNF blocker and another medicine called azathioprine or 6 mercaptopurine (6-MP).
Some people treated with SIMPONI have developed certain kinds of skin cancer. If any changes in the appearance of your skin or growths on your skin occur during or after your treatment with SIMPONI, tell your doctor. You should see your doctor periodically for skin examinations, especially if you have a history of skin cancer.
What is SIMPONI? SIMPONI is a prescription medicine called a Tumor Necrosis Factor (TNF) blocker. SIMPONI is used to treat: adults with the medicine methotrexate to treat moderately to severely active rheumatoid arthritis (RA) adults with active psoriatic arthritis (PsA) alone or with methotrexate adults with active ankylosing spondylitis (AS) adults and children weighing at least 33 pounds (15 kg) with moderately to severely active ulcerative colitis (UC) You may continue to use other medicines that help treat your condition while taking SIMPONI, such as…