
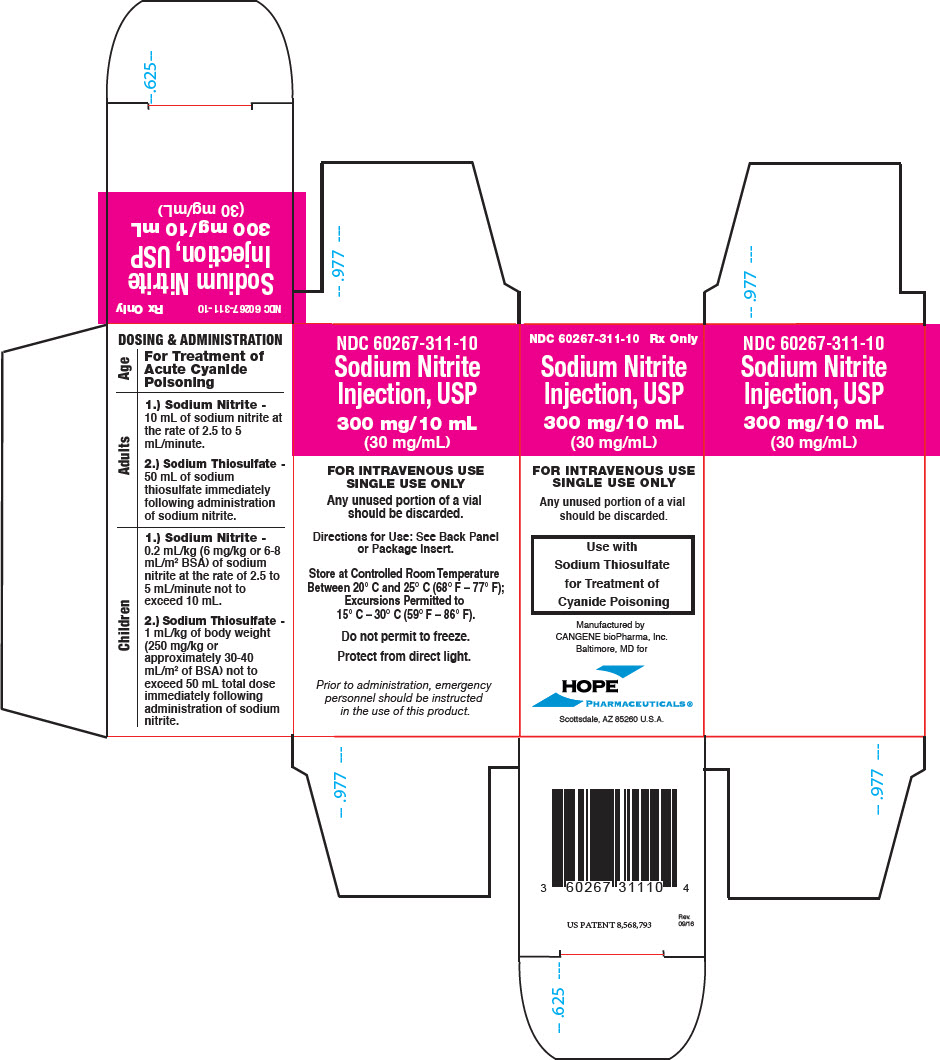
Sodium Nitrite 30 mg/mL Injection, Solution, 10 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Antidotes class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII N762921K75
A colorless, odorless gas that makes up most of the air we breathe. In medicines, it's used as a packaging gas or propellant to protect products from oxidation and maintain freshness.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Sodium Nitrite 30 mg/mLthis 60267-0311-10 | Hope | 10 ml | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9687506 ↗ | Method of use | U-3394 | Feb 10, 2030 |
| US 9687506 ↗ | Method of use | U-3395 | Feb 10, 2030 |
| US 8568793 ↗ | Drug substance | — | Dec 24, 2031 |
Is there a generic version of SODIUM NITRITE 300 MG/10 ML VL?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 60267-0311-10 You're viewing this | 10 mL in 1 VIAL, SINGLE-USE (60267-311-10) | 2012-02-14 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LIFE THREATENING HYPOTENSION AND METHEMOGLOBIN FORMATION Sodium nitrite can cause serious adverse reactions and death in humans, even at doses less than twice the recommended therapeutic dose. Sodium nitrite causes hypotension and methemoglobin formation, which diminishes oxygen carrying capacity. Hypotension and methemoglobin formation can occur concurrently or separately.
Because of these risks, sodium nitrite should be used to treat acute life-threatening cyanide poisoning and be used with caution in patients where the diagnosis of cyanide poisoning is uncertain . Patients should be closely monitored to ensure adequate perfusion and oxygenation during treatment with sodium nitrite. Alternative therapeutic approaches should be considered in patients known to have diminished oxygen or cardiovascular reserve (e.g., smoke inhalation victims, pre-existing anemia, cardiac or respiratory compromise), and those at higher risk of developing methemoglobinemia (e.g., congenital methemoglobin reductase deficiency) as they are at greater risk for potentially life-threatening adverse events related to the use of sodium nitrite . [see Warnings and Precautions (5.1 and 5.2) ] WARNING: LIFE-THREATENING HYPOTENSION AND METHEMOGLOBIN FORMATION See full prescribing information for complete boxed warning .
Sodium nitrite can cause serious adverse reactions and death from: Hypotension ( 5.1 ) Methemoglobin formation ( 5.2 ) Patients should be closely monitored to ensure adequate perfusion and oxygenation during treatment with sodium nitrite.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Sodium Nitrite Injection, an antidote, is indicated for sequential use with sodium thiosulfate for the treatment of acute cyanide poisoning that is judged to be serious or life-threatening. When the diagnosis of cyanide poisoning is uncertain, the potentially life-threatening risks associated with Sodium Nitrite Injection should be carefully weighed against the potential benefits, especially if the patient is not in extremis. Sodium Nitrite Injection, an antidote, is indicated for sequential use with sodium thiosulfate for treatment of acute cyanide poisoning that is judged to be serious or life-threatening.
( 1 ) Use with caution if the diagnosis of cyanide poisoning is uncertain. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION If clinical suspicion of cyanide poisoning is high, administer Sodium Nitrite Injection without delay and in conjunction with appropriate airway, ventilatory, and circulatory support. ( 2.1 ) The expert advice of a regional poison control center may be obtained by calling 1-800-222-1222. ( 2.1 ) Dosing : Age Intravenous Dose of Sodium Nitrite and Sodium Thiosulfate Adults 1.) Sodium Nitrite -10 mL of sodium nitrite at the rate of 2.5 to 5 mL/minute 2.) Sodium Thiosulfate - 50 mL of sodium thiosulfate immediately following administration of sodium nitrite.
Children 1.) Sodium Nitrite - 0.2 mL/kg (6 mg/kg or 6-8 mL/m 2 BSA) of sodium nitrite at the rate of 2.5 to 5 mL/minute not to exceed 10 mL 2.) Sodium Thiosulfate - 1 mL/kg of body weight (250 mg/kg or approximately 30-40 mL/m 2 of BSA) not to exceed 50 mL total dose immediately following administration of sodium nitrite. Redosing : If signs of cyanide poisoning reappear, repeat treatment using one-half the original dose of both sodium nitrite and sodium thiosulfate. ( 2.2 ) Monitoring : Blood pressure must be monitored during treatment.
( 2.2 ) Sodium nitrite is chemically incompatible with hydroxocobalamin and should not be administered via the same intravenous line. ( 2.4 )
2.1Important Dosage and Administration Instructions If clinical suspicion of cyanide poisoning is high, administer Sodium Nitrite Injection without delay. Comprehensive treatment of acute cyanide intoxication requires support of vital functions. Administration of sodium nitrite and sodium thiosulfate should be considered adjunctive to appropriate supportive therapies.
Airway, ventilatory and circulatory support, and oxygen administration should not be delayed in order to administer sodium nitrite and sodium thiosulfate [ see Warnings and Precautions (5.1) ]. The expert advice of a regional poison control center may be obtained by calling 1-800-222-1222. Identifying Patients with Cyanide Poisoning Cyanide poisoning may result from inhalation, ingestion, or dermal exposure to various cyanide-containing compounds, including smoke from closed-space fires.
Sources of cyanide poisoning include hydrogen cyanide and its salts, cyanogenic plants, aliphatic nitriles, and prolonged exposure to sodium nitroprusside.. The presence and extent of cyanide poisoning are often initially unknown. There is no widely available, rapid, confirmatory cyanide blood test.
Treatment decisions must be made on the basis of clinical history and signs and symptoms of cyanide intoxication Table 1. Common Signs and Symptoms of Cyanide Poisoning Symptoms Headache Confusion Dyspnea Chest Tightness Nausea Signs Altered Mental Status (e.g., confusion, disorientation) Seizures or Coma Mydriasis Tachypnea/Hyperpnea (early) Bradypnea/Apnea (late) Hypertension (early)/ Hypotension (late) Cardiovascular Collapse Vomiting Plasma Lactate Concentration ≥ 8 mmol/L In some settings, panic symptoms including tachypnea and vomiting may mimic early cyanide poisoning signs.
The presence of altered mental status (e.g., confusion and disorientation) and/or mydriasis is suggestive of true cyanide poisoning although these signs can occur with other toxic exposures as well. Smoke Inhalation Not all smoke inhalation victims will have cyanide poisoning and may present with burns, trauma, and exposure to other toxic substances making a diagnosis of cyanide poisoning particularly difficult. Prior to administration of Sodium Nitrite Injection, smoke-inhalation victims should be assessed for the following: Exposure to fire or smoke in an enclosed area Presence of soot around the mouth, nose, or oropharynx Altered mental status Although hypotension is highly suggestive of cyanide poisoning, it is only present in a small percentage of cyanide-poisoned smoke inhalation victims.
Also indicative of cyanide poisoning is a plasma lactate concentration greater than or equal to 10 mmol/L (a value higher than that typically listed in the table o…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Sodium Nitrite Injection consists of: One vial of sodium nitrite injection, USP 300 mg/10mL (30 mg/mL) Administration of the contents of one vial constitutes a single dose. Sodium Nitrite Injection consists of: one vial of sodium nitrite injection, USP 300 mg/10 mL (30 mg/mL) ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Methemoglobinemia: Sodium nitrite reacts with hemoglobin to form methemoglobin and should be used with caution in patients known to have anemia. Monitor oxyhemoglobin and methemoglobin levels by pulse co-oximetry or other measurements. Optimally, the sodium nitrite dose should be reduced in proportion to the oxygen carrying capacity.
( 5.2 ) Smoke inhalation: Carbon monoxide contained in smoke can result in the formation of carboxyhemoglobin that can reduce the oxygen carrying capacity of the blood. Sodium nitrite should be used with caution in patients with smoke inhalation injury because of the potential for worsening hypoxia due to methemoglobin formation. Carboxyhemoglobin and oxyhemoglobin levels should be monitored by pulse oximetry or other measurements in patients that present with evidence of smoke inhalation.
Optimally, the sodium nitrite dose should be reduced in proportion to the oxygen carrying capacity. ( 5.4 )
5.1Hypotension Sodium nitrite has been associated with severe hypotension, methemoglobinemia, and death at doses less than twice recommended therapeutic doses. Hypotension may occur concurrently or separately. Sodium nitrite should be used to treat life-threatening cyanide poisoning.
When the diagnosis of cyanide poisoning is uncertain and/or the patient is not in extremis, special consideration should be given to administration of sodium nitrite if the patient is known or suspected to have diminished oxygen or cardiovascular reserve (e.g., smoke inhalation victims, pre-existing anemia, substantial blood loss, cardiac or respiratory compromise) or to be at higher risk of developing methemoglobinemia (e.g., congenital methemoglobin reductase deficiency).
5.2Methemoglobinemia Supportive care alone may be sufficient treatment without administration of antidotes for many cases of cyanide intoxication, particularly in conscious patients without signs of severe toxicity. Monitor patients closely to ensure adequate perfusion and oxygenation during treatment with sodium nitrite. Monitor methemoglobin levels and administer oxygen during treatment with sodium nitrite whenever possible.
When sodium nitrite is administered to humans a wide range of methemoglobin concentrations occur. Methemoglobin concentrations as high as 58% have been reported after two 300-mg doses of sodium nitrite administered to an adult. Sodium nitrite should be used with caution in the presence of other drugs that may cause methemoglobinemia such as procaine and nitroprusside.
Sodium nitrite should be used with caution in patients who may be particularly susceptible to injury from vasodilation and its related hemodynamic sequelae. Hemodynamics should be monitored closely during and after administration of sodium nitrite, and infusion rates should be slowed if hypotension occurs.
5.3Anemia Use sodium nitrite with caution in patients with known anemia. Patients with anemia will form more methemoglobin (as a percentage of total hemoglobin) than persons with normal red blood cell (RBC) volumes. Optimally, these patients should receive a sodium nitrite dose that is reduced in proportion to their oxygen carrying capacity.
5.4Smoke Inhalation Injury Use sodium nitrite should be used with caution in persons with smoke inhalation injury or carbon monoxide poisoning because of the potential for worsening hypoxia due to methemoglobin formation.
5.5Neonates and Infants Neonates and infants may be more susceptible than adults and older pediatric patients to severe methemoglobinemia when sodium nitrite is administered. Follow reduced dosing guidelines in pediatric patients.
5.6G6PD Deficiency Because patients with G6PD deficiency are at increased risk of a hemolytic crisis with sodium nitrite administration, consider alternative therapeutic approaches in these patients. Monitor patients with known or suspected G6PD deficiency for an acute drop in hematocrit. Exchange transfusion may be needed for patients with G6PD deficienc…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS There have been no controlled clinical trials conducted to systematically assess the adverse events profile of sodium nitrite. The medical literature has reported the following adverse events in association with sodium nitrite administration. These adverse events were not reported in the context of controlled trials or with consistent monitoring and reporting methodologies for adverse events.
Therefore, frequency of occurrence of these adverse events cannot be assessed. Cardiovascular system: syncope, hypotension, tachycardia, methemoglobinemia, palpitations, dysrhythmia Hematological: methemoglobinemia Central nervous system: headache, dizziness, blurred vision, seizures, confusion, coma Gastrointestinal system: nausea, vomiting, abdominal pain Respiratory system: tachypnea, dyspnea Body as a Whole : anxiety, diaphoresis, lightheadedness, injection site tingling, cyanosis, acidosis, fatigue, weakness, urticaria, generalized numbness and tingling Severe hypotension, methemoglobinemia, cardiac dysrhythmias, coma and death have been reported in patients without life-threatening cyanide poisoning but who were treated with injection of sodium nitrite at doses less than twice those recommended for the treatment of cyanide poisoning.
Most common adverse reactions are: Syncope, hypotension, tachycardia, palpitations, dysrhythmia, methemoglobinemia, headache, dizziness, blurred vision, seizures, confusion, coma ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Hope Pharmaceuticals at 1-800-755-9595 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Formal drug interaction studies have not been conducted with Sodium Nitrite Injection.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding not recommended. ( 8.2 ) Renal impairment: Sodium nitrite is substantially excreted by the kidney. The risk of toxic reactions to this drug may be greater in patients with impaired renal function. ( 8.6 ).
8.1Pregnancy Risk Summary Life-sustaining therapy should not be withheld. Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated (see Clinical Considerations ). Therefore, if a pregnant woman has known or suspected cyanide poisoning, Sodium Nitrite Injection for sequential use with Sodium Thiosulfate Injection is recommended [see Indications and Usage (1) ].
There are no available data on Sodium Nitrite Injection use in pregnant women to establish a drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes. If available, consider alternative therapies not associated with methemoglobinemia. There are no intravenous animal studies to evaluate the effect of sodium nitrite on embryofetal development.
In published animal studies, fetal mortality was reported when pregnant guinea pigs were subcutaneously administered sodium nitrite at 1.7 times the maximum recommended human dose (MRHD) of 450 mg sodium nitrite when maternal and fetal methemoglobin concentrations were at their peak. In other published studies, no evidence of malformations were reported in guinea pigs, mice, or rats; however, severe anemia, reduced growth, and increased pup mortality was reported when pregnant rats were treated with 4.7 times the MRHD of sodium nitrite via drinking water during gestation and throughout lactation (see Data ) .
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Cyanide readily crosses the placenta. Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated. Treatment for cyanide poisoning should not be withheld because of potential concerns regarding the effects of Sodium Nitrite Injection on the fetus.
Fetal/neonatal adverse reactions Sodium nitrite produces methemoglobin. Fetal hemoglobin is oxidized to methemoglobin more easily than adult hemoglobin. In addition, the fetus has lower levels of methemoglobin reductase than adults [see Use in Specific Populations (8.4) ] .
Based on animal studies, prenatal exposure to sodium nitrite resulted in impaired neural development likely the result of prenatal hypoxia (see Data ) . If available, consider alternative therapy not known to be associated with methemoglobinemia. Data Animal Data There are no intravenous toxicology studies of sodium nitrite that evaluate the potential for reproductive and developmental toxicity.
In a published study, sodium nitrite treatment of pregnant guinea pigs with 60 or 70 mg/kg/day resulted in abortion of the litters within 1-4 days of treatment. All animals treated subcutaneously with 70 mg/kg, sodium nitrite died within 60 minutes of treatment. Further studies demonstrated that a dose of 60 mg/kg resulted in measurable blood levels of methemoglobin in the dams and their fetuses for up to 6 hours post treatment.
Maternal methemoglobin levels were higher than the levels in the offspring at all times measured. Based on a body surface area comparison, a 60 mg/kg dose in the guinea pig that resulted in death was only 1.7 times higher than the highest clinical dose of sodium nitrite that would be used to treat cyanide poisoning (based on a body surface area comparison). In a published study, treatment of pregnant rats via drinking water with sodium nitrite at concentrations of either 2000 or 3000 mg/L during gestation and throughout lactation resulted in severe anemia, reduced growth and increased mortality in the offspring.
This exposure regimen in the rat model would result in dosing of approximately 220 and 300 mg/kg/day (4.7 and 6.5 times the highest clinical dose of sodium nitrite that would be used to tre…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Life-sustaining therapy should not be withheld. Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated (see Clinical Considerations ). Therefore, if a pregnant woman has known or suspected cyanide poisoning, Sodium Nitrite Injection for sequential use with Sodium Thiosulfate Injection is recommended [see Indications and Usage (1) ].
There are no available data on Sodium Nitrite Injection use in pregnant women to establish a drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes. If available, consider alternative therapies not associated with methemoglobinemia. There are no intravenous animal studies to evaluate the effect of sodium nitrite on embryofetal development.
In published animal studies, fetal mortality was reported when pregnant guinea pigs were subcutaneously administered sodium nitrite at 1.7 times the maximum recommended human dose (MRHD) of 450 mg sodium nitrite when maternal and fetal methemoglobin concentrations were at their peak. In other published studies, no evidence of malformations were reported in guinea pigs, mice, or rats; however, severe anemia, reduced growth, and increased pup mortality was reported when pregnant rats were treated with 4.7 times the MRHD of sodium nitrite via drinking water during gestation and throughout lactation (see Data ) .
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Cyanide readily crosses the placenta. Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated. Treatment for cyanide poisoning should not be withheld because of potential concerns regarding the effects of Sodium Nitrite Injection on the fetus.
Fetal/neonatal adverse reactions Sodium nitrite produces methemoglobin. Fetal hemoglobin is oxidized to methemoglobin more easily than adult hemoglobin. In addition, the fetus has lower levels of methemoglobin reductase than adults [see Use in Specific Populations (8.4) ] .
Based on animal studies, prenatal exposure to sodium nitrite resulted in impaired neural development likely the result of prenatal hypoxia (see Data ) . If available, consider alternative therapy not known to be associated with methemoglobinemia. Data Animal Data There are no intravenous toxicology studies of sodium nitrite that evaluate the potential for reproductive and developmental toxicity.
In a published study, sodium nitrite treatment of pregnant guinea pigs with 60 or 70 mg/kg/day resulted in abortion of the litters within 1-4 days of treatment. All animals treated subcutaneously with 70 mg/kg, sodium nitrite died within 60 minutes of treatment. Further studies demonstrated that a dose of 60 mg/kg resulted in measurable blood levels of methemoglobin in the dams and their fetuses for up to 6 hours post treatment.
Maternal methemoglobin levels were higher than the levels in the offspring at all times measured. Based on a body surface area comparison, a 60 mg/kg dose in the guinea pig that resulted in death was only 1.7 times higher than the highest clinical dose of sodium nitrite that would be used to treat cyanide poisoning (based on a body surface area comparison). In a published study, treatment of pregnant rats via drinking water with sodium nitrite at concentrations of either 2000 or 3000 mg/L during gestation and throughout lactation resulted in severe anemia, reduced growth and increased mortality in the offspring.
This exposure regimen in the rat model would result in dosing of approximately 220 and 300 mg/kg/day (4.7 and 6.5 times the highest clinical dose of sodium nitrite that would be used to treat cyanide poisoning, based on a body surface area comparison). In a published study, treatment of pregnant mice with approximately 243 mg/kg sodium nitrite daily (2.6 times the maximum recommended daily dose of 450 mg/day based on body surface are) via the dri…
🧒 Pediatric Use ▾
8.4Pediatric Use There are case reports in the medical literature of sodium nitrite in conjunction with sodium thiosulfate being administered to pediatric patients with cyanide poisoning; however, there have been no clinical studies to evaluate the safety or efficacy of sodium nitrite in the pediatric population. As for adult patients, dosing recommendations for pediatric patients have been based on theoretical calculations of antidote detoxifying potential, extrapolation from animal experiments, and a small number of human case reports.
Sodium nitrite must be used with caution in patients less than 6 months of age because they may be at higher risk of developing severe methemoglobinemia compared to older children and adults. The presence of fetal hemoglobin, which is oxidized to methemoglobin more easily than adult hemoglobin, and lower methemoglobin reductase levels compared to older children and adults may contribute to risk. Mortality attributed to sodium nitrite was reported following administration of an adult dose (300 mg IV followed by a second dose of 150 mg) to a 17-month old child. [see Dosage and Administration (2) , Warnings and Precautions, (5) , Adverse Reactions (6) ]
🧓 Geriatric Use ▾
8.5Geriatric Use Sodium nitrite is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Large doses of sodium nitrite result in severe hypotension and toxic levels of methemoglobin which may lead to cardiovascular collapse. Sodium nitrite administration has been reported to cause or significantly contribute to mortality in adults at oral doses as low as 1 g and intravenous doses as low as 600 mg. A death attributed to sodium nitrite has been reported following administration of an adult dose (300 mg IV followed by a second dose of 150 mg) to a 17-month old child.
Cyanosis may become apparent at a methemoglobin level of 10-20%. Other clinical signs and symptoms of sodium nitrite toxicity (anxiety, dyspnea, nausea, and tachycardia) can be apparent at methemoglobin levels as low as 15%. More serious signs and symptoms, including cardiac dysrhythmias, circulatory failure, and central nervous system depression are seen as methemoglobin levels increase, and levels above 70% are usually fatal.
Treatment of overdose involves supplemental oxygen and supportive measures such as exchange transfusion. Treatment of severe methemoglobinemia with intravenous methylene blue has been described in the medical literature; however, this may also cause release of cyanide bound to methemoglobin. Because hypotension appears to be mediated primarily by an increase in venous capacitance, measures to increase venous return may be most appropriate to treat hypotension.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Exposure to a high dose of cyanide can result in death within minutes due to the inhibition of cytochrome oxidase resulting in arrest of cellular respiration. Specifically, cyanide binds rapidly with cytochrome a3, a component of the cytochrome c oxidase complex in mitochondria. Inhibition of cytochrome a3 prevents the cell from using oxygen and forces anaerobic metabolism, resulting in lactate production, cellular hypoxia and metabolic acidosis.
In massive acute cyanide poisoning, the mechanism of toxicity may involve other enzyme systems as well. The synergy resulting from treatment of cyanide poisoning with the combination of sodium nitrite and sodium thiosulfate is the result of differences in their primary mechanisms of action as antidotes for cyanide poisoning. Sodium Nitrite Sodium nitrite is thought to exert its therapeutic effect by reacting with hemoglobin to form methemoglobin, an oxidized form of hemoglobin incapable of oxygen transport but with high affinity for cyanide.
Cyanide preferentially binds to methemoglobin over cytochrome a 3 , forming the nontoxic cyanomethemoglobin. Methemoglobin displaces cyanide from cytochrome oxidase, allowing resumption of aerobic metabolism. The chemical reaction is as follows: NaNO 2 + Hemoglobin → Methemoglobin HCN + Methemoglobin → Cyanomethemoglobin Vasodilation has also been cited to account for at least part of the therapeutic effect of sodium nitrite.
It has been suggested that sodium nitrite-induced methemoglobinemia may be more efficacious against cyanide poisoning than comparable levels of methemoglobinemia induced by other oxidants. Also, sodium nitrite appears to retain some efficacy even when the formation of methemoglobin is inhibited by methylene blue. Sodium Thiosulfate The primary route of endogenous cyanide detoxification is by enzymatic transulfuration to thiocyanate (SCN - ), which is relatively nontoxic and readily excreted in the urine.
Sodium thiosulfate is thought to serve as a sulfur donor in the reaction catalyzed by the enzyme rhodanese, thus enhancing the endogenous detoxification of cyanide in the following chemical reaction: Rhodanese Na 2 S 2 O 3 + CN - → SCN - + Na 2 SO 3 .
12.2Pharmacodynamics Sodium Nitrite When 4 mg/kg sodium nitrite was administered intravenously to six healthy human volunteers, the mean peak methemoglobin concentration was 7%, achieved at 30-60 minutes after injection, consistent with reports in cyanide poisoning victims. Supine systolic and diastolic blood pressures dropped approximately 20% within 10 minutes, a drop which was sustained throughout the 40 minutes of testing. This was associated with a 20 beat per minute increase in pulse rate that returned to baseline in 10 minutes.
Five of these subjects were unable to withstand orthostatic testing due to fainting. One additional subject, who received a 12 mg/kg dose of sodium nitrite, experienced severe cardiovascular effects and achieved a peak methemoglobin concentration of 30% at 60 minutes following injection. Oral doses of 120 to 180 mg of sodium nitrite administered to healthy volunteers caused minimal cardiovascular changes when subjects were maintained in the horizontal position.
However, minutes after being placed in the upright position subjects exhibited tachycardia and hypotension with syncope. The half life for conversion of methemoglobin to normal hemoglobin in a cyanide poisoning victim who has been administered sodium nitrite is estimated to be 55 minutes.
12.3Pharmacokinetics Sodium Nitrite Sodium nitrite is a strong oxidant, and reacts rapidly with hemoglobin to form methemoglobin. The pharmacokinetics of free sodium nitrite in humans have not been well studied. It has been reported that approximately 40% of sodium nitrite is excreted unchanged in the urine while the remaining 60% is metabolized to ammonia and related small molecules.
Cyanide The apparent terminal elimination half life and volume of distri…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Exposure to a high dose of cyanide can result in death within minutes due to the inhibition of cytochrome oxidase resulting in arrest of cellular respiration. Specifically, cyanide binds rapidly with cytochrome a3, a component of the cytochrome c oxidase complex in mitochondria. Inhibition of cytochrome a3 prevents the cell from using oxygen and forces anaerobic metabolism, resulting in lactate production, cellular hypoxia and metabolic acidosis.
In massive acute cyanide poisoning, the mechanism of toxicity may involve other enzyme systems as well. The synergy resulting from treatment of cyanide poisoning with the combination of sodium nitrite and sodium thiosulfate is the result of differences in their primary mechanisms of action as antidotes for cyanide poisoning. Sodium Nitrite Sodium nitrite is thought to exert its therapeutic effect by reacting with hemoglobin to form methemoglobin, an oxidized form of hemoglobin incapable of oxygen transport but with high affinity for cyanide.
Cyanide preferentially binds to methemoglobin over cytochrome a 3 , forming the nontoxic cyanomethemoglobin. Methemoglobin displaces cyanide from cytochrome oxidase, allowing resumption of aerobic metabolism. The chemical reaction is as follows: NaNO 2 + Hemoglobin → Methemoglobin HCN + Methemoglobin → Cyanomethemoglobin Vasodilation has also been cited to account for at least part of the therapeutic effect of sodium nitrite.
It has been suggested that sodium nitrite-induced methemoglobinemia may be more efficacious against cyanide poisoning than comparable levels of methemoglobinemia induced by other oxidants. Also, sodium nitrite appears to retain some efficacy even when the formation of methemoglobin is inhibited by methylene blue. Sodium Thiosulfate The primary route of endogenous cyanide detoxification is by enzymatic transulfuration to thiocyanate (SCN - ), which is relatively nontoxic and readily excreted in the urine.
Sodium thiosulfate is thought to serve as a sulfur donor in the reaction catalyzed by the enzyme rhodanese, thus enhancing the endogenous detoxification of cyanide in the following chemical reaction: Rhodanese Na 2 S 2 O 3 + CN - → SCN - + Na 2 SO 3 .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each Sodium Nitrite carton (NDC 60267-311-10) consists of the following: One 10 mL glass vial of sodium nitrite injection 30 mg/mL (containing 300 mg of sodium nitrite); Storage Store at controlled room temperature between 20°C and 25°C (68°F to 77°F); excursions permitted from 15 to 30°C (59 to 86°F). Protect from direct light. Do not freeze. (Note: Sodium Thiosulfate must be obtained separately.)
📦 Storage and Handling ▾
Storage Store at controlled room temperature between 20°C and 25°C (68°F to 77°F); excursions permitted from 15 to 30°C (59 to 86°F). Protect from direct light. Do not freeze. (Note: Sodium Thiosulfate must be obtained separately.)
📋 Description ▾
11 DESCRIPTION Sodium nitrite has the chemical name nitrous acid sodium salt. The chemical formula is NaNO 2 and the molecular weight is 69.0. The structural formula is: Structure of Sodium Nitrite Sodium Nitrite Injection is a cyanide antidote which contains one 10 mL glass vial of a 3% solution of sodium nitrite injection.
Sodium nitrite injection is a sterile aqueous solution and is intended for intravenous injection. Each vial contains 300 mg of sodium nitrite in 10 mL solution (30 mg/mL). Sodium nitrite injection is a clear solution with a pH between 7.0 and 9.0.
Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Sodium Nitrite Injection is indicated for cyanide poisoning and in this setting, patients will likely be unresponsive or may have difficulty in comprehending counseling information. Hypotension and Methemoglobin Formation When feasible, patients should be informed of the possibility of life-threatening hypotension and methemoglobin formation. Monitoring Where feasible, patients should be informed of the need for close monitoring of blood pressure and oxygenation.
Lactation Advise women that breastfeeding is not recommended during treatment with Sodium Nitrite Injection [see Use in Specific Populations (8.2) ].