
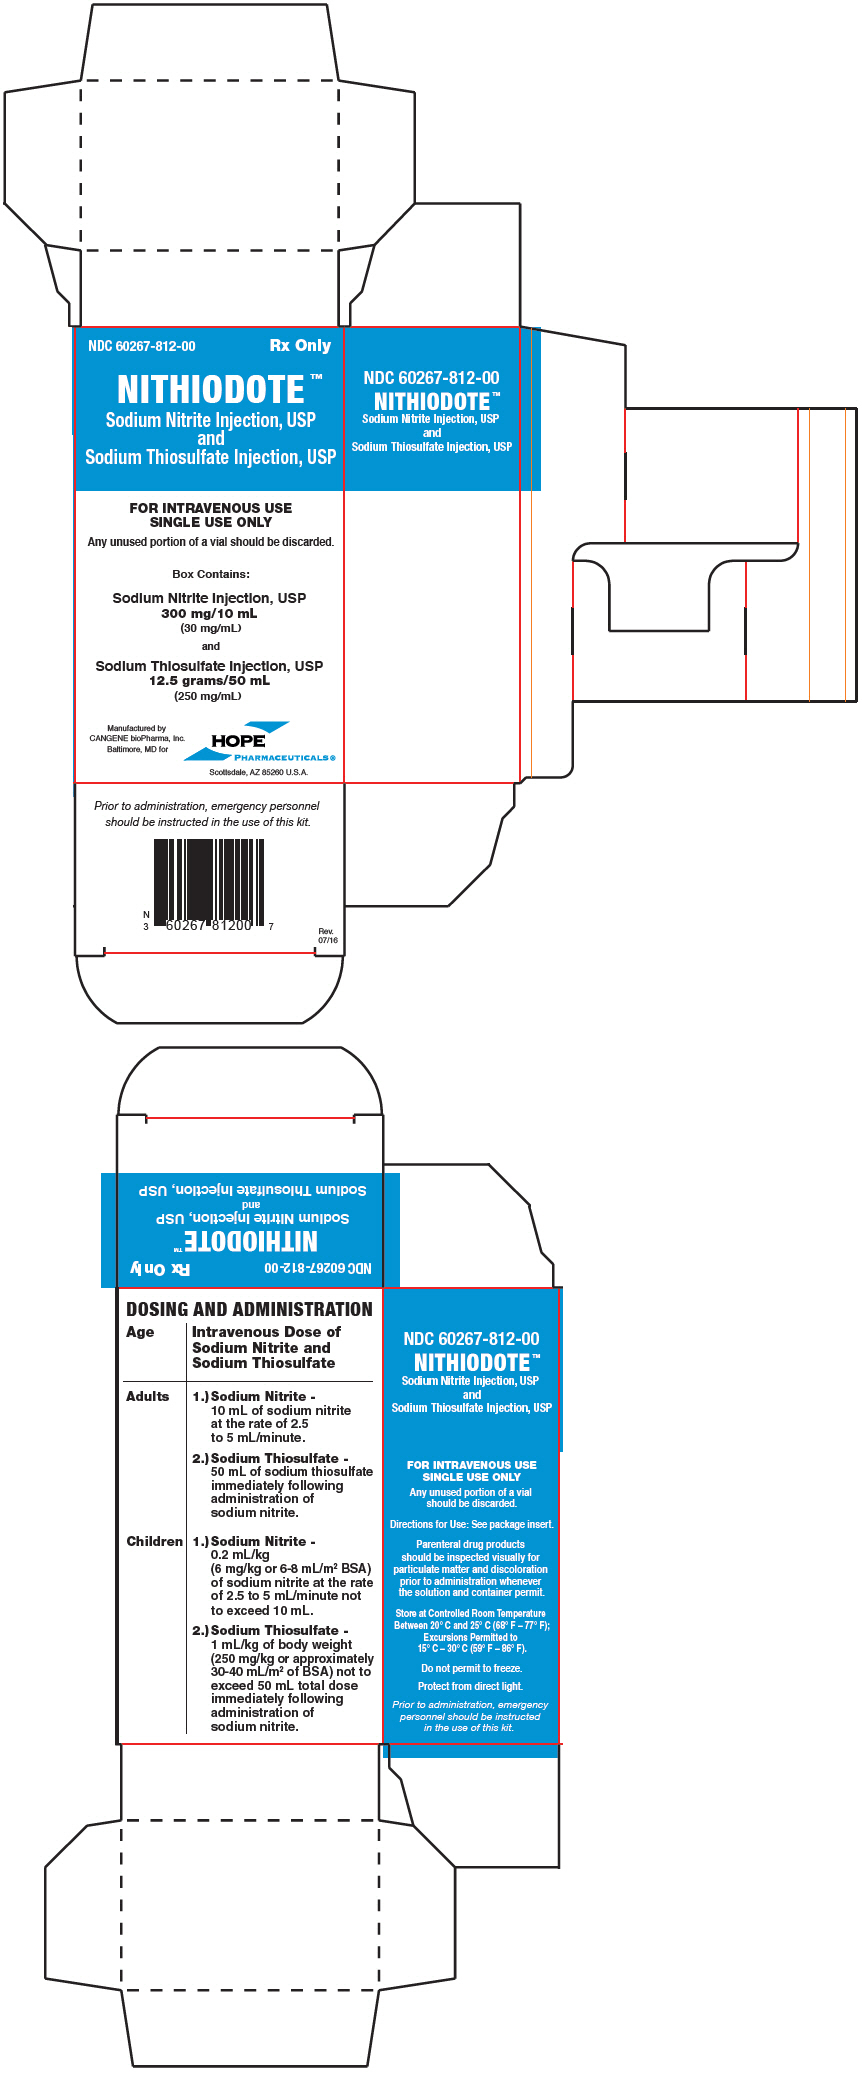
NITHIODOTE Sodium Nitrite and Sodium Thiosulfate Kit — NDC 60267-812-00 (Billing 60267-0812-00)
This is a package of NITHIODOTE Sodium Nitrite and Sodium Thiosulfate Kit from Hope Pharmaceuticals, marketed since Jan 2011 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 60267-812-00 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 60267 labeler · 812 product · 00 package
- Package marketed since
- Jan 14, 2011
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 6026781200 7
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 067182
- GCN: 29675
- GPI-14 (Medi-Span): 93990002706430
- HICL (First Databank): 037488
- AHFS class code: 84:04.08.92
- RxCUI (RxNorm): 237832
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Antidotes class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 60267-0812-00 You're viewing this Main listing | 1 KIT in 1 CARTON * 10 mL in 1 VIAL, SINGLE-USE * 50 mL in 1 VIAL, SINGLE-DOSE | 2011-01-14 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nithiodotethis 60267-0812-00 | Hope | 1 kit | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 8496973 ↗ | Drug substance | U-1419 | Mar 29, 2031 |
| US 11753301 ↗ | Drug substance | U-3681 | Feb 10, 2030 |
| US 9345724 ↗ | Drug substance | U-2015 | Jul 7, 2030 |
| US 9687506 ↗ | Method of use | U-3394 | Feb 10, 2030 |
| US 9687506 ↗ | Method of use | U-3395 | Feb 10, 2030 |
| US 10479686 ↗ | Method of use | U-3390 | Jul 7, 2030 |
| US 12304813 ↗ | Drug product | — | Feb 10, 2030 |
| US 9585912 ↗ | Drug substance | — | Jul 7, 2030 |
| US 8568793 ↗ | Drug substance | — | Dec 24, 2031 |
Is there a generic version of NITHIODOTE 300 MG-12.5 GRAM?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Hope Pharmaceuticals labeler code 60267
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: LIFE THREATENING HYPOTENSION AND METHEMOGLOBIN FORMATION Sodium nitrite can cause serious adverse reactions and death in humans, even at doses less than twice the recommended therapeutic dose. Sodium nitrite causes hypotension and methemoglobin formation, which diminishes oxygen carrying capacity. Hypotension and methemoglobin formation can occur concurrently or separately.
Because of these risks, sodium nitrite should be used to treat acute life-threatening cyanide poisoning and be used with caution in patients where the diagnosis of cyanide poisoning is uncertain . Patients should be closely monitored to ensure adequate perfusion and oxygenation during treatment with sodium nitrite. Alternative therapeutic approaches should be considered in patients known to have diminished oxygen or cardiovascular reserve (e.g. smoke inhalation victims, pre-existing anemia, cardiac or respiratory compromise), and those at higher risk of developing methemoglobinemia (e.g., congenital methemoglobin reductase deficiency) as they are at greater risk for potentially life-threatening adverse events related to the use of sodium nitrite . [See Warnings and Precautions (5.1 and 5.2) ] WARNING: LIFE-THREATENING HYPOTENSION AND METHEMOGLOBIN FORMATION See full prescribing information for complete boxed warning .
Sodium nitrite can cause serious adverse reactions and death from: Hypotension ( 5.1 ) Methemoglobin formation ( 5.2 ) Patients should be closely monitored to ensure adequate perfusion and oxygenation during treatment with sodium nitrite.
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE NITHIODOTE is indicated for the treatment of acute cyanide poisoning that is judged to be serious or life-threatening. When the diagnosis of cyanide poisoning is uncertain, carefully weigh the potentially life-threatening risks associated with NITHIODOTE against the potential benefits, especially if the patient is not in extremis. NITHIODOTE, an antidote, is indicated for the treatment of acute cyanide poisoning that is judged to be serious or life-threatening.
( 1 ) Use with caution if the diagnosis of cyanide poisoning is uncertain. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION If clinical suspicion of cyanide poisoning is high, administer NITHIODOTE without delay and in conjunction with appropriate airway, ventilatory, and circulatory support. ( 2.1 ) The expert advice of a regional poison control center may be obtained by calling 1-800-222-1222. ( 2.1 ) Dosing : Age Intravenous Dose of Sodium Nitrite and Sodium Thiosulfate Adults 1) Sodium Nitrite -10 mL of sodium nitrite at the rate of 2.5 to 5 mL/minute 2) Sodium Thiosulfate - 50 mL of sodium thiosulfate immediately following administration of sodium nitrite.
Children 1) Sodium Nitrite - 0.2 mL/kg (6 mg/kg or 6-8 mL/m 2 BSA) of sodium nitrite at the rate of 2.5 to 5 mL/minute not to exceed 10 mL 2) Sodium Thiosulfate - 1 mL/kg of body weight (250 mg/kg or approximately 30-40 mL/m 2 of BSA) not to exceed 50 mL total dose immediately following administration of sodium nitrite. Redosing : If signs of cyanide poisoning reappear, repeat treatment using one-half the original dose of both sodium nitrite and sodium thiosulfate. ( 2.2 ) Monitoring : Blood pressure must be monitored during treatment.
( 2.2 ) NITHIODOTE is chemically incompatible with hydroxocobalamin and should not be administered via the same intravenous line. ( 2.4 )
2.1Important Dosage and Administration Instructions If clinical suspicion of cyanide poisoning is high, administer NITHIODOTE without delay. Comprehensive treatment of acute cyanide intoxication requires support of vital functions. Administration of sodium nitrite and sodium thiosulfate should be considered adjunctive to appropriate supportive therapies.
Airway, ventilatory and circulatory support, and oxygen administration should not be delayed in order to administer sodium nitrite and sodium thiosulfate [see Warnings and Precautions (5.1) ] . The expert advice of a regional poison control center may be obtained by calling 1-800-222-1222. Identifying Patients with Cyanide Poisoning Cyanide poisoning may result from inhalation, ingestion, or dermal exposure to various cyanide-containing compounds, including smoke from closed-space fires.
Sources of cyanide poisoning include hydrogen cyanide and its salts, cyanogenic plants, aliphatic nitriles, and prolonged exposure to sodium nitroprusside. The presence and extent of cyanide poisoning are often initially unknown. There is no widely available, rapid, confirmatory cyanide blood test.
Treatment decisions must be made on the basis of clinical history and signs and symptoms of cyanide intoxication. Table 1. Common Signs and Symptoms of Cyanide Poisoning Symptoms Signs Headache Confusion Dyspnea Chest Tightness Nausea Altered Mental Status (e.g., confusion, disorientation) Seizures or Coma Mydriasis Tachypnea/Hyperpnea (early) Bradypnea/Apnea (late) Hypertension (early)/ Hypotension (late) Cardiovascular Collapse Vomiting Plasma Lactate Concentration ≥ 8 mmol/L In some settings, panic symptoms including tachypnea and vomiting may mimic early cyanide poisoning signs.
The presence of altered mental status (e.g., confusion and disorientation) and/or mydriasis is suggestive of true cyanide poisoning although these signs can occur with other toxic exposures as well. Smoke Inhalation Not all smoke inhalation victims will have cyanide poisoning and may present with burns, trauma, and exposure to other toxic substances making a diagnosis of cyanide poisoning particularly difficult. Prior to administration of NITHIODOTE, smoke-inhalation victims should be assessed for the following: Exposure to fire or smoke in an enclosed area Presence of soot around the mouth, nose, or oropharynx Altered mental status Although hypotension is highly suggestive of cyanide poisoning, it is only present in a small percentage of cyanide-poisoned smoke inhalation victims.
Also indicative of cyanide poisoning is a plasma lactate concentration greater than or equal to 10 mmol/L (a value higher than that typically listed in the table of signs and symptoms of isolated cyanide poisoning…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS NITHIODOTE Injection consists of: One vial of sodium nitrite injection, USP 300 mg/10 mL (30 mg/mL) and One vial of sodium thiosulfate injection USP 12.5 grams/50 mL (250 mg/mL) Administration of one vial of each medication constitutes a single dose. NITHIODOTE consists of: one vial of sodium nitrite injection, USP 300 mg/10 mL (30 mg/mL) and one vial of sodium thiosulfate injection, USP 12.5 grams/50 mL (250 mg/mL). ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Methemoglobinemia: Sodium nitrite reacts with hemoglobin to form methemoglobin and should be used with caution in patients known to have anemia. Monitor oxyhemoglobin and methemoglobin levels by pulse co-oximetry or other measurements. Optimally, the sodium nitrite dose should be reduced in proportion to the oxygen carrying capacity.
( 5.2 ) Smoke inhalation: Carbon monoxide contained in smoke can result in the formation of carboxyhemoglobin that can reduce the oxygen carrying capacity of the blood. Sodium nitrite should be used with caution in patients with smoke inhalation injury because of the potential for worsening hypoxia due to methemoglobin formation. Carboxyhemoglobin and oxyhemoglobin levels should be monitored by pulse oximetry or other measurements in patients that present with evidence of smoke inhalation.
Optimally, the sodium nitrite dose should be reduced in proportion to the oxygen carrying capacity. ( 5.4 )
5.1Hypotension Sodium nitrite has been associated with severe hypotension, methemoglobinemia, and death at doses less than twice recommended therapeutic doses. Hypotension may occur concurrently or separately. Sodium nitrite should be used to treat life-threatening cyanide poisoning.
When the diagnosis of cyanide poisoning is uncertain and/or the patient is not in extremis, special consideration should be given to administration of sodium nitrite if the patient is known or suspected to have diminished oxygen or cardiovascular reserve (e.g., smoke inhalation victims, pre-existing anemia, substantial blood loss, cardiac or respiratory compromise) or to be at higher risk of developing methemoglobinemia (e.g., congenital methemoglobin reductase deficiency).
5.2Methemoglobinemia Supportive care alone may be sufficient treatment without administration of antidotes for many cases of cyanide intoxication, particularly in conscious patients without signs of severe toxicity. Monitor patients closely to ensure adequate perfusion and oxygenation during treatment with sodium nitrite. Monitor methemoglobin levels and administer oxygen during treatment with sodium nitrite whenever possible.
When sodium nitrite is administered to humans a wide range of methemoglobin concentrations occur. Methemoglobin concentrations as high as 58% have been reported after two 300-mg doses of sodium nitrite administered to an adult. Sodium nitrite should be used with caution in the presence of other drugs that may cause methemoglobinemia such as procaine and nitroprusside.
Use sodium nitrite with caution in patients who may be particularly susceptible to injury from vasodilation and its related hemodynamic sequelae. Monitor hemodynamics closely during and after administration of sodium nitrite and sodium thiosulfate, and reduce infusion rates if hypotension occurs.
5.3Anemia Use sodium nitrite with caution in patients with known anemia. Patients with anemia will form more methemoglobin (as a percentage of total hemoglobin) than persons with normal red blood cell (RBC) volumes. Optimally, these patients should receive a sodium nitrite dose that is reduced in proportion to their oxygen carrying capacity.
5.4Smoke Inhalation Injury Use sodium nitrite with caution in persons with smoke inhalation injury or carbon monoxide poisoning because of the potential for worsening hypoxia due to methemoglobin formation.
5.5Neonates and Infants Neonates and infants may be more susceptible than adults and older pediatric patients to severe methemoglobinemia when sodium nitrite is administered. Follow reduced dosing guidelines in pediatric patients.
5.6G6PD Deficiency Because patients with G6PD deficiency are at increased risk of a hemolytic crisis with sodium nitrite administration, consider alternative therapeutic approaches in these patients. Monitor patients with known or suspected G6PD deficiency for an acute drop in hematocrit. Exchange transfusion may be needed for patients with G6PD deficiency who receive sodium nitr…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS There have been no controlled clinical trials conducted to systematically assess the adverse events profile of sodium nitrite or sodium thiosulfate. The medical literature has reported the following adverse events in association with sodium nitrite or sodium thiosulfate administration. These adverse events were not reported in the context of controlled trials or with consistent monitoring and reporting methodologies for adverse events.
Therefore, frequency of occurrence of these adverse events cannot be assessed. Most common adverse reactions are: Sodium nitrite : syncope, hypotension, tachycardia, palpitations, dysrhythmia, methemoglobinemia, headache, dizziness, blurred vision, seizures, confusion, coma ( 6 ) Sodium thiosulfate : hypotension, headache, disorientation ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Hope Pharmaceuticals at 1-800-755-9595 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch . S odium Nitrite Cardiovascular system: syncope, hypotension, tachycardia, methemoglobinemia, palpitations, dysrhythmia Hematological: methemoglobinemia Central nervous system: headache, dizziness, blurred vision, seizures, confusion, coma Gastrointestinal system: nausea, vomiting, abdominal pain Respiratory system: tachypnea, dyspnea Body as a Whole : anxiety, diaphoresis, lightheadedness, injection site tingling, cyanosis, acidosis, fatigue, weakness, urticaria, generalized numbness and tingling Severe hypotension, methemoglobinemia, cardiac dysrhythmias, coma and death have been reported in patients without life-threatening cyanide poisoning but who were treated with injection of sodium nitrite at doses less than twice those recommended for the treatment of cyanide poisoning.
Sodium Thiosulfate Cardiovascular system: hypotension Central nervous system: headache, disorientation Gastrointestinal system: nausea, vomiting Hematological : prolonged bleeding time Body as a Whole: salty taste in mouth, warm sensation over body In humans, rapid administration of concentrated solutions or solutions not freshly prepared, and administration of large doses of sodium thiosulfate have been associated with a higher incidence of nausea and vomiting. However, administration of 0.1 g sodium thiosulfate per pound up to a maximum of 15 g in a 10-15% solution over 10-15 minutes was associated with nausea and vomiting in 7 of 26 patients without concomitant cyanide intoxication.
In a series of 11 human subjects, a single intravenous infusion of 50 mL of 50% sodium thiosulfate was associated with increases in clotting time 1-3 days after administration. However, no significant changes were observed in other hematological parameters.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Formal drug interaction studies have not been conducted with NITHIODOTE.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding not recommended. ( 8.2 ) Renal impairment: Sodium nitrite and sodium thiosulfate are substantially excreted by the kidney. The risk of toxic reactions to these drugs may be greater in patients with impaired renal function. ( 8.6 ).
8.1Pregnancy Risk Summary Life-sustaining therapy should not be withheld. Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated (see Clinical Considerations ). Therefore, if a pregnant woman has known or suspected cyanide poisoning, Sodium Nitrite Injection for sequential use with Sodium Thiosulfate Injection is recommended [see Indications and Usage (1) ].
There are no available data on NITHIODOTE use in pregnant women to establish a drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes. If available, consider alternative therapies not associated with methemoglobinemia. There are no intravenous animal studies to evaluate the effect of sodium nitrite, sodium thiosulfate, or the combination on embryofetal development.
In published animal studies, fetal mortality was reported when pregnant guinea pigs were subcutaneously administered sodium nitrite at 1.7 times the maximum recommended human dose (MRHD) of 450 mg sodium nitrite when maternal and fetal methemoglobin concentrations were at their peak. In other published studies, no evidence of malformations were reported in guinea pigs, mice, or rats; however, severe anemia, reduced growth, and increased pup mortality was reported when pregnant rats were treated with 4.7 times the MRHD of sodium nitrite via drinking water during gestation and throughout lactation.
In published animal studies, no evidence of embryotoxicity or malformations was reported when sodium thiosulfate was administered orally during organogenesis to pregnant mice, rats, hamsters, or rabbits at 0.2 to 0.9 times the human daily dose of 12.5 g for cyanide poisoning. The sodium thiosulfate studies did not test doses that were comparable to the human dose for cyanide poisoning (see Data ). Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Cyanide readily crosses the placenta.
Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated. Treatment for cyanide poisoning should not be withheld because of potential concerns regarding the effects of Nithiodote on the fetus. Fetal/neonatal adverse reactions Sodium nitrite produces methemoglobin.
Fetal hemoglobin is oxidized to methemoglobin more easily than adult hemoglobin. In addition, the fetus has lower levels of methemoglobin reductase than adults [see Use in Specific Populations (8.4) ] . Based on animal studies, prenatal exposure to sodium nitrite resulted in impaired neural development likely the result of prenatal hypoxia (see Data ).
If available, consider alternative therapy not known to be associated with methemoglobinemia. Data Animal Data Sodium nitrite There are no intravenous toxicology studies of sodium nitrite that evaluate the potential for reproductive and developmental toxicity. In a published study, sodium nitrite treatment of pregnant guinea pigs with 60 or 70 mg/kg/day resulted in abortion of the litters within 1-4 days of treatment.
All animals treated subcutaneously with 70 mg/kg, sodium nitrite died within 60 minutes of treatment. Further studies demonstrated that a dose of 60 mg/kg resulted in measurable blood levels of methemoglobin in the dams and their fetuses for up to 6 hours post treatment. Maternal methemoglobin levels were higher than the levels in the offspring at all times measured.
Based on a body surface area comparison, a 60 mg/kg dose in the guinea pig that resulted in death was only 1.7 times higher than the highest clinical dose of sodium nitrite that would be used to treat cyanide poisoning (based on a body surface area comparison). In a publ…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Life-sustaining therapy should not be withheld. Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated (see Clinical Considerations ). Therefore, if a pregnant woman has known or suspected cyanide poisoning, Sodium Nitrite Injection for sequential use with Sodium Thiosulfate Injection is recommended [see Indications and Usage (1) ].
There are no available data on NITHIODOTE use in pregnant women to establish a drug-associated risk for major birth defects, miscarriage, or adverse maternal or fetal outcomes. If available, consider alternative therapies not associated with methemoglobinemia. There are no intravenous animal studies to evaluate the effect of sodium nitrite, sodium thiosulfate, or the combination on embryofetal development.
In published animal studies, fetal mortality was reported when pregnant guinea pigs were subcutaneously administered sodium nitrite at 1.7 times the maximum recommended human dose (MRHD) of 450 mg sodium nitrite when maternal and fetal methemoglobin concentrations were at their peak. In other published studies, no evidence of malformations were reported in guinea pigs, mice, or rats; however, severe anemia, reduced growth, and increased pup mortality was reported when pregnant rats were treated with 4.7 times the MRHD of sodium nitrite via drinking water during gestation and throughout lactation.
In published animal studies, no evidence of embryotoxicity or malformations was reported when sodium thiosulfate was administered orally during organogenesis to pregnant mice, rats, hamsters, or rabbits at 0.2 to 0.9 times the human daily dose of 12.5 g for cyanide poisoning. The sodium thiosulfate studies did not test doses that were comparable to the human dose for cyanide poisoning (see Data ). Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Cyanide readily crosses the placenta.
Cyanide poisoning is a medical emergency in pregnancy, which can be fatal for the pregnant woman and fetus if left untreated. Treatment for cyanide poisoning should not be withheld because of potential concerns regarding the effects of Nithiodote on the fetus. Fetal/neonatal adverse reactions Sodium nitrite produces methemoglobin.
Fetal hemoglobin is oxidized to methemoglobin more easily than adult hemoglobin. In addition, the fetus has lower levels of methemoglobin reductase than adults [see Use in Specific Populations (8.4) ] . Based on animal studies, prenatal exposure to sodium nitrite resulted in impaired neural development likely the result of prenatal hypoxia (see Data ).
If available, consider alternative therapy not known to be associated with methemoglobinemia. Data Animal Data Sodium nitrite There are no intravenous toxicology studies of sodium nitrite that evaluate the potential for reproductive and developmental toxicity. In a published study, sodium nitrite treatment of pregnant guinea pigs with 60 or 70 mg/kg/day resulted in abortion of the litters within 1-4 days of treatment.
All animals treated subcutaneously with 70 mg/kg, sodium nitrite died within 60 minutes of treatment. Further studies demonstrated that a dose of 60 mg/kg resulted in measurable blood levels of methemoglobin in the dams and their fetuses for up to 6 hours post treatment. Maternal methemoglobin levels were higher than the levels in the offspring at all times measured.
Based on a body surface area comparison, a 60 mg/kg dose in the guinea pig that resulted in death was only 1.7 times higher than the highest clinical dose of sodium nitrite that would be used to treat cyanide poisoning (based on a body surface area comparison). In a published study, treatment of pregnant rats via drinking water with sodium nitrite at concentrations of either 2000 or 3000 mg/L during gestation and throughout lactation resulted in severe anemia, reduced growth, and increased mortality in the offspring.
This exposure regimen in the rat mo…
🧒 Pediatric Use ▾
8.4Pediatric Use There are case reports in the medical literature of sodium nitrite in conjunction with sodium thiosulfate being administered to pediatric patients with cyanide poisoning; however, there have been no clinical studies to evaluate the safety or efficacy of sodium thiosulfate or sodium nitrite in the pediatric population. As for adult patients, dosing recommendations for pediatric patients have been based on theoretical calculations of antidote detoxifying potential, extrapolation from animal experiments, and a small number of human case reports.
Use Sodium nitrite with caution in patients less than 6 months of age because they may be at higher risk of developing severe methemoglobinemia compared to older children and adults. The presence of fetal hemoglobin, which is oxidized to methemoglobin more easily than adult hemoglobin, and lower methemoglobin reductase levels compared to older children and adults may contribute to risk. Mortality attributed to sodium nitrite was reported following administration of an adult dose (300 mg IV followed by a second dose of 150 mg) to a 17-month old child. [see Dosage and Administration (2) , Warnings and Precautions, (5) , Adverse Reactions (6) ]
🧓 Geriatric Use ▾
8.5Geriatric Use Sodium nitrite and sodium thiosulfate are known to be substantially excreted by the kidney, and the risk of adverse reactions to these drugs may be greater in patients with impaired renal function. Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and it may be useful to monitor renal function.
🆘 Overdosage ▾
10 OVERDOSAGE Sodium Nitrite Large doses of sodium nitrite result in severe hypotension and toxic levels of methemoglobin which may lead to cardiovascular collapse. Sodium nitrite administration has been reported to cause or significantly contribute to mortality in adults at oral doses as low as 1 g and intravenous doses as low as 600 mg. A death attributed to sodium nitrite has been reported following administration of an adult dose (300 mg IV followed by a second dose of 150 mg) to a 17-month old child.
Cyanosis may become apparent at a methemoglobin level of 10-20%. Other clinical signs and symptoms of sodium nitrite toxicity (anxiety, dyspnea, nausea, and tachycardia) can be apparent at methemoglobin levels as low as 15%. More serious signs and symptoms, including cardiac dysrhythmias, circulatory failure, and central nervous system depression are seen as methemoglobin levels increase, and levels above 70% are usually fatal.
Treatment of overdose involves supplemental oxygen and supportive measures such as exchange transfusion. Treatment of severe methemoglobinemia with intravenous methylene blue has been described in the medical literature; however, this may also cause release of cyanide bound to methemoglobin. Because hypotension appears to be mediated primarily by an increase in venous capacitance, measures to increase venous return may be most appropriate to treat hypotension.
Sodium Thiosulfate There is limited information about the effects of large doses of sodium thiosulfate in humans. Oral administration of 3 g sodium thiosulfate per day for 1-2 weeks in humans resulted in reductions in room air arterial oxygen saturation to as low as 75%, which was due to a rightward shift in the oxygen hemoglobin dissociation curve. The subjects returned to baseline oxygen saturations 1 week after discontinuation of sodium thiosulfate.
A single intravenous administration of 20 mL of 10% sodium thiosulfate reportedly did not change oxygen saturations.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Cyanide is an extremely toxic poison. In the absence of rapid and adequate treatment, exposure to a high dose of cyanide can result in death within minutes due to the inhibition of cytochrome oxidase resulting in arrest of cellular respiration. Specifically, cyanide binds rapidly with cytochrome a3, a component of the cytochrome c oxidase complex in mitochondria.
Inhibition of cytochrome a3 prevents the cell from using oxygen and forces anaerobic metabolism, resulting in lactate production, cellular hypoxia and metabolic acidosis. In massive acute cyanide poisoning, the mechanism of toxicity may involve other enzyme systems as well. Signs and symptoms of acute systemic cyanide poisoning may develop rapidly within minutes, depending on the route and extent of cyanide exposure.
The synergy resulting from treatment of cyanide poisoning with the combination of sodium nitrite and sodium thiosulfate is the result of differences in their primary mechanisms of action as antidotes for cyanide poisoning. Sodium Nitrite Sodium nitrite is thought to exert its therapeutic effect by reacting with hemoglobin to form methemoglobin, an oxidized form of hemoglobin incapable of oxygen transport but with high affinity for cyanide. Cyanide preferentially binds to methemoglobin over cytochrome a 3 , forming the nontoxic cyanomethemoglobin.
Methemoglobin displaces cyanide from cytochrome oxidase, allowing resumption of aerobic metabolism. The chemical reaction is as follows: NaNO 2 + Hemoglobin → Methemoglobin HCN + Methemoglobin → Cyanomethemoglobin Vasodilation has also been cited to account for at least part of the therapeutic effect of sodium nitrite. It has been suggested that sodium nitrite-induced methemoglobinemia may be more efficacious against cyanide poisoning than comparable levels of methemoglobinemia induced by other oxidants.
Also, sodium nitrite appears to retain some efficacy even when the formation of methemoglobin is inhibited by methylene blue. Sodium Thiosulfate The primary route of endogenous cyanide detoxification is by enzymatic transulfuration to thiocyanate (SCN - ), which is relatively nontoxic and readily excreted in the urine. Sodium thiosulfate is thought to serve as a sulfur donor in the reaction catalyzed by the enzyme rhodanese, thus enhancing the endogenous detoxification of cyanide in the following chemical reaction: Rhodanese Na 2 S 2 O 3 + CN - → SCN - + Na 2 SO 3 .
12. 2 Pharmacodynamics Sodium Nitrite When 4 mg/kg sodium nitrite was administered intravenously to six healthy human volunteers, the mean peak methemoglobin concentration was 7%, achieved at 30-60 minutes after injection, consistent with reports in cyanide poisoning victims. Supine systolic and diastolic blood pressures dropped approximately 20% within 10 minutes, a drop which was sustained throughout the 40 minutes of testing.
This was associated with a 20 beat per minute increase in pulse rate that returned to baseline in 10 minutes. Five of these subjects were unable to withstand orthostatic testing due to fainting. One additional subject, who received a 12 mg/kg dose of sodium nitrite, experienced severe cardiovascular effects and achieved a peak methemoglobin concentration of 30% at 60 minutes following injection.
Oral doses of 120 to 180 mg of sodium nitrite administered to healthy volunteers caused minimal cardiovascular changes when subjects were maintained in the horizontal position. However, minutes after being placed in the upright position subjects exhibited tachycardia and hypotension with syncope. The half life for conversion of methemoglobin to normal hemoglobin in a cyanide poisoning victim who has been administered sodium nitrite and sodium thiosulfate is estimated to be 55 minutes.
Sodium Thiosulfate In dogs, pretreatment with sodium thiosulfate to achieve a steady state level of 2 μmol/mL increased the rate of conversion of cyanide to thiocyanate over 30-fold.
12.3 Pharmacokinetics…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Cyanide is an extremely toxic poison. In the absence of rapid and adequate treatment, exposure to a high dose of cyanide can result in death within minutes due to the inhibition of cytochrome oxidase resulting in arrest of cellular respiration. Specifically, cyanide binds rapidly with cytochrome a3, a component of the cytochrome c oxidase complex in mitochondria.
Inhibition of cytochrome a3 prevents the cell from using oxygen and forces anaerobic metabolism, resulting in lactate production, cellular hypoxia and metabolic acidosis. In massive acute cyanide poisoning, the mechanism of toxicity may involve other enzyme systems as well. Signs and symptoms of acute systemic cyanide poisoning may develop rapidly within minutes, depending on the route and extent of cyanide exposure.
The synergy resulting from treatment of cyanide poisoning with the combination of sodium nitrite and sodium thiosulfate is the result of differences in their primary mechanisms of action as antidotes for cyanide poisoning. Sodium Nitrite Sodium nitrite is thought to exert its therapeutic effect by reacting with hemoglobin to form methemoglobin, an oxidized form of hemoglobin incapable of oxygen transport but with high affinity for cyanide. Cyanide preferentially binds to methemoglobin over cytochrome a 3 , forming the nontoxic cyanomethemoglobin.
Methemoglobin displaces cyanide from cytochrome oxidase, allowing resumption of aerobic metabolism. The chemical reaction is as follows: NaNO 2 + Hemoglobin → Methemoglobin HCN + Methemoglobin → Cyanomethemoglobin Vasodilation has also been cited to account for at least part of the therapeutic effect of sodium nitrite. It has been suggested that sodium nitrite-induced methemoglobinemia may be more efficacious against cyanide poisoning than comparable levels of methemoglobinemia induced by other oxidants.
Also, sodium nitrite appears to retain some efficacy even when the formation of methemoglobin is inhibited by methylene blue. Sodium Thiosulfate The primary route of endogenous cyanide detoxification is by enzymatic transulfuration to thiocyanate (SCN - ), which is relatively nontoxic and readily excreted in the urine. Sodium thiosulfate is thought to serve as a sulfur donor in the reaction catalyzed by the enzyme rhodanese, thus enhancing the endogenous detoxification of cyanide in the following chemical reaction: Rhodanese Na 2 S 2 O 3 + CN - → SCN - + Na 2 SO 3 .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Each NITHIODOTE carton (NDC 60267-812-00) consists of the following: One 10 mL glass vial of sodium nitrite injection 30 mg/mL (containing 300 mg of sodium nitrite); One 50 mL glass vial of sodium thiosulfate injection 250 mg/mL (containing 12.5 grams of sodium thiosulfate); One package insert. Storage Store at controlled room temperature between 20°C and 25°C (68°F - 77°F); excursions permitted to 15-30°C (59 to 86°F). Protect from direct light.
Do not freeze.
📦 Storage and Handling ▾
Storage Store at controlled room temperature between 20°C and 25°C (68°F - 77°F); excursions permitted to 15-30°C (59 to 86°F). Protect from direct light. Do not freeze.
📋 Description ▾
11 DESCRIPTION Sodium nitrite, one of the active ingredients in NITHIODOTE has the chemical name nitrous acid sodium salt. The chemical formula is NaNO 2 and the molecular weight is 69.0. Sodium thiosulfate, the second active ingredient in NITHIODOTE has the chemical name thiosulfuric acid, disodium salt, pentahydrate.
The chemical formula is Na 2 S 2 O 3 ∙ 5H 2 O and the molecular weight is 248.17. The structural formulae are: Structure of Sodium Nitrite Structure of Sodium Thiosulfate Pentahydrate NITHIODOTE is a cyanide antidote which contains one 10 mL glass vial of a 3% solution of sodium nitrite injection and one 50 mL glass vial containing a 25% solution of sodium thiosulfate injection. Sodium nitrite injection is a sterile aqueous solution and is intended for intravenous injection.
Each vial contains 300 mg of sodium nitrite in 10 mL solution (30 mg/mL). Sodium nitrite injection is a clear solution with a pH between 7.0 and 9.0. Sodium thiosulfate injection is a sterile aqueous solution and is intended for intravenous injection.
Each vial contains 12.5 grams of sodium thiosulfate in 50 mL solution (250 mg/mL). Each mL also contains 2.8 mg boric acid and 4.4 mg of potassium chloride. The pH of the solution is adjusted with boric acid and/or sodium hydroxide.
Sodium thiosulfate injection is a clear solution with a pH between 7.5 and 9.0. Chemical Structure Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION NITHIODOTE is indicated for cyanide poisoning and in this setting, patients will likely be unresponsive or may have difficulty in comprehending counseling information. Hypotension and Methemoglobin Formation When feasible, patients should be informed of the possibility of life-threatening hypotension and methemoglobin formation. Monitoring Where feasible, patients should be informed of the need for close monitoring of blood pressure and oxygenation.
Lactation Advise women that breastfeeding is not recommended during treatment with NITHIODOTE [ see Use in Specific Populations (8.2) ] .
About this NDC listing & data coverage
Kit / multi-component package
This NDC identifies a kit — a package containing more than one component. Structured data (pricing, ingredients, equivalents) is often reported per component rather than for the kit NDC itself, which can make this page look thinner than the components' own pages.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |