
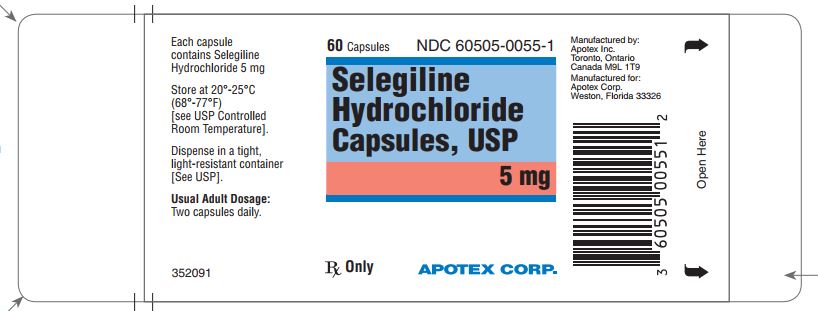
SELEGILINE HYDROCHLORIDE 5 mg Capsule, 60-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Monoamine Oxidase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Selegiline is used to help control the symptoms of Parkinson's disease (PD; a disorder of the nervous system that causes difficulties with movement, muscle control, and balance) in people who are taking levodopa and carbidopa combination (Sinemet). Selegiline may help people with Parkinson's disease by decreasing the dose of levodopa/carbidopa needed to control symptoms, stopping the effects of levodopa/carbidopa from wearing off between doses, and increasing the length of time that levodopa/carbidopa will continue to control symptoms. Selegiline is in a group of medications called monoamine o...
Read the full MedlinePlus article ↗- That's a really common question. Selegiline isn't meant to replace your levodopa — it's designed to make it work better. Over time, many people find their levodopa starts wearing o...
- Why am I taking selegiline if I'm already on levodopa? Isn't one medication enough?
- It is a bit different! You peel back the blister pack — don't push the tablet through the foil — and with dry hands, gently take out the tablet and immediately place it on top of y...
- How do I take the dissolving tablet? It seems different from regular pills.
Patient education
Supplement & herbal interactions
Selegiline may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 8PJ61P6TS3
Butyl alcohol is a clear liquid organic solvent derived from petroleum or natural sources. In medicines, it helps dissolve active ingredients and serves as a solvent in liquid formulations and some topical products.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII ND2M416302
Isopropyl alcohol is a clear liquid solvent derived from petroleum. In medicines, it dissolves active ingredients and other components, helps the product flow smoothly, and aids in sterilization during manufacturing.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
17 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.731 | $43.84 / 60 capsules |
| Medicaid paysCMS SDUD · 12 mo | $0.7842 | $47.05 / 60 capsules |
| Medicare drug plans payPart D · Q2 2026 | $0.9319 | $55.91 / 60 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Selegiline Hydrochloride 5 mg 16571-0659-06 | Rising | 60 capsules | $0.731 | AB | Availability likely | — |
| Selegiline Hydrochloride 5 mgthis 60505-0055-01 | Apotex | 60 capsules | $0.731 | AB | Availability likely | — |
| Selegiline Hydrochloride 5 mg 70954-0504-10 | Novitium | 60 capsules | $0.731 | AB | Availability likely | — |
| Selegiline Hydrochloride 5 mg 10135-0737-60 | Marlex | 60 capsules | — | AB | FDA listed | — |
| Selegiline Hydrochloride 5 mg 71205-0888-00 | Proficient | 100 capsules | — | AB | FDA listed | — |
| Selegiline Hydrochloride 5 mg 71335-2673-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Selegiline Hydrochloride 5 mg 71335-2676-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 60505-0055-01 You're viewing this | 60 CAPSULE in 1 BOTTLE (60505-0055-1) | $0.7307 / ea | $43.84 | 1997-07-15 | Active |
| 60505-0055-02 | 1000 CAPSULE in 1 BOTTLE (60505-0055-2) | $0.7307 / ea | $730.70 | 1997-07-15 | Active |
| 60505-0055-03 | 500 CAPSULE in 1 BOTTLE (60505-0055-3) | — | — | 1997-07-15 | Active |
You're viewing the smallest of 3 pack sizes for this product.
This pack has the lowest per-ea cost of the 2 priced pack sizes ($0.7307 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 60505-0055-01?
What is the difference between NDC 60505-0055-01 and NDC 60505-0055-03?
What NDC number is used to bill for this package of SELEGILINE HYDROCHLORIDE 5 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Selegiline capsules, USP are indicated as an adjunct in the management of Parkinsonian patients being treated with levodopa/carbidopa who exhibit deterioration in the quality of their response to this therapy. There is no evidence from controlled studies that selegiline has any beneficial effect in the absence of concurrent levodopa therapy. Evidence supporting this claim was obtained in randomized controlled clinical investigations that compared the effects of added selegiline or placebo in patients receiving levodopa/carbidopa.
Selegiline was significantly superior to placebo on all three principal outcome measures employed: change from baseline in daily levodopa/carbidopa dose, the amount of 'off' time, and patient self-rating of treatment success. Beneficial effects were also observed on other measures of treatment success (e.g., measures of reduced end of dose akinesia, decreased tremor and sialorrhea, improved speech and dressing ability and improved overall disability as assessed by walking and comparison to previous state).
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Selegiline hydrochloride capsules are intended for administration to Parkinsonian patients receiving levodopa/carbidopa therapy who demonstrate a deteriorating response to this treatment. The recommended regimen for the administration of selegiline hydrochloride is 10 mg per day administered as divided doses of 5 mg each taken at breakfast and lunch. There is no evidence that additional benefit will be obtained from the administration of higher doses.
Moreover, higher doses should ordinarily be avoided because of the increased risk of side effects. After two to three days of selegiline treatment, an attempt may be made to reduce the dose of levodopa/carbidopa. A reduction of 10 to 30% was achieved with the typical participant in the domestic placebo controlled trials who was assigned to selegiline treatment.
Further reductions of levodopa/carbidopa may be possible during continued selegiline therapy.
⛔ Contraindications ▾
CONTRAINDICATIONS Selegiline is contraindicated in patients with a known hypersensitivity to this drug. Selegiline is contraindicated for use with meperidine (DEMEROL & other trade names). This contraindication is often extended to other opioids. (See Drug Interactions .)
⚠️ Warnings ▾
WARNINGS Selegiline should not be used at daily doses exceeding those recommended (10 mg/day) because of the risks associated with non-selective inhibition of MAO. (See CLINICAL PHARMACOLOGY .) The selectivity of selegiline for MAO B may not be absolute even at the recommended daily dose of 10 mg a day. Rare cases of hypertensive reactions associated with ingestion of tyramine-containing foods have been reported in patients taking the recommended daily dose of selegiline.
The selectivity is further diminished with increasing daily doses. The precise dose at which selegiline becomes a non-selective inhibitor of all MAO is unknown, but may be in the range of 30 to 40 mg a day. Severe CNS toxicity associated with hyperpyrexia and death have been reported with the combination of tricyclic antidepressants and non-selective MAOIs (Phenelzine, Tranylcypromine).
A similar reaction has been reported for a patient on amitriptyline and selegiline. Another patient receiving protriptyline and selegiline developed tremors, agitation, and restlessness followed by unresponsiveness and death two weeks after selegiline was added. Related adverse events including hypertension, syncope, asystole, diaphoresis, seizures, changes in behavioral and mental status, and muscular rigidity have also been reported in some patients receiving selegiline and various tricyclic antidepressants.
Serious, sometimes fatal, reactions with signs and symptoms that may include hyperthermia, rigidity, myoclonus, autonomic instability with rapid fluctuations of the vital signs, and mental status changes that include extreme agitation progressing to delirium and coma have been reported with patients receiving a combination of fluoxetine hydrochloride and non- selective MAOIs. Similar signs have been reported in some patients on the combination of selegiline (10 mg a day) and selective serotonin reuptake inhibitors including fluoxetine, sertraline and paroxetine.
Since the mechanisms of these reactions are not fully understood, it seems prudent, in general, to avoid this combination of selegiline and tricyclic antidepressants as well as selegiline and selective serotonin reuptake inhibitors. At least 14 days should elapse between discontinuation of selegiline and initiation of treatment with a tricyclic antidepressant or selective serotonin reuptake inhibitors. Because of the long half-lives of fluoxetine and its active metabolite, at least five weeks (perhaps longer, especially if fluoxetine has been prescribed chronically and/or at higher doses) should elapse between discontinuation of fluoxetine and initiation of treatment with selegiline.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Introduction The number of patients who received selegiline in prospectively monitored pre-marketing studies is limited. While other sources of information about the use of selegiline are available (e.g., literature reports, foreign post-marketing reports, etc.) they do not provide the kind of information necessary to estimate the incidence of adverse events. Thus, overall incidence figures for adverse reactions associated with the use of selegiline cannot be provided.
Many of the adverse reactions seen have also been reported as symptoms of dopamine excess. Moreover, the importance and severity of various reactions reported often cannot be ascertained. One index of relative importance, however, is whether or not a reaction caused treatment discontinuation.
In prospective pre-marketing studies, the following events led, in decreasing order of frequency, to discontinuation of treatment with selegiline: nausea, hallucinations, confusion, depression, loss of balance, insomnia, orthostatic hypotension, increased akinetic involuntary movements, agitation, arrhythmia, bradykinesia, chorea, delusions, hypertension, new or increased angina pectoris, and syncope. Events reported only once as a cause of discontinuation are ankle edema, anxiety, burning lips/mouth, constipation, drowsiness/lethargy, dystonia, excess perspiration, increased freezing, gastrointestinal bleeding, hair loss, increased tremor, nervousness, weakness, and weight loss.
Experience with selegiline obtained in parallel, placebo controlled, randomized studies provides only a limited basis for estimates of adverse reaction rates. The following reactions that occurred with greater frequency among the 49 patients assigned to selegiline as compared to the 50 patients assigned to placebo in the only parallel, placebo controlled trial performed in patients with Parkinson's disease are shown in the following Table. None of these adverse reactions led to a discontinuation of treatment.
INCIDENCE OF TREATMENT-EMERGENT ADVERSE EXPERIENCES IN THE PLACEBO-CONTROLLED CLINICAL TRIAL Adverse Event Number of Patients Reporting Events selegiline hydrochloride N = 49 Placebo N = 50 Nausea 10 3 Dizziness/Lightheaded/Fainting 7 1 Abdominal Pain 4 2 Confusion 3 0 Hallucinations 3 1 Dry mouth 3 1 Vivid Dreams 2 0 Dyskinesias 2 5 Headache 2 1 The following events were reported once in either or both groups: Ache, generalized 1 0 Anxiety/Tension 1 1 Anemia 0 1 Diarrhea 1 0 Hair Loss 0 1 Insomnia 1 1 Lethargy 1 0 Leg pain 1 0 Low back pain 1 0 Malaise 0 1 Palpitations 1 0 Urinary Retention 1 0 Weight Loss 1 0 In all prospectively monitored clinical investigations, enrolling approximately 920 patients, the following adverse events, classified by body system, were reported.
Central Nervous System Motor/Coordination/Extrapyramidal increased tremor, chorea, loss of balance, restlessness, blepharospasm, increased bradykinesia, facial grimace, falling down, heavy leg, muscle twitch*, myoclonic jerks*, stiff neck, tardive dyskinesia, dystonic symptoms, dyskinesia, involuntary movements, freezing, festination, increased apraxia, muscle cramps. Mental Status/Behavioral/Psychiatric hallucinations, dizziness, confusion, anxiety, depression, drowsiness, behavior/mood change, dreams/nightmares, tiredness, delusions, disorientation, lightheadedness, impaired memory*, increased energy*, transient high*, hollow feeling, lethargy/malaise, apathy, overstimulation, vertigo, personality change, sleep disturbance, restlessness, weakness, transient irritability.
Pain/Altered Sensation headache, back pain, leg pain, tinnitus, migraine, supraorbital pain, throat burning, generalized ache, chills, numbness of toes/fingers, taste disturbance. Autonomic Nervous System dry mouth, blurred vision, sexual dysfunction. Cardiovascular orthostatic hypotension, hypertension, arrhythmia, palpitations, new or increased angina pectoris, hypotension, tachycardia, peripheral edema, sinus bradycardia, syncope.
Gas…
🆘 Overdosage ▾
OVERDOSAGE Selegiline No specific information is available about clinically significant overdoses with selegiline. However, experience gained during selegiline's development reveals that some individuals exposed to doses of 600 mg of d,l-selegiline suffered severe hypotension and psychomotor agitation. Since the selective inhibition of MAO B by selegiline hydrochloride is achieved only at doses in the range recommended for the treatment of Parkinson's disease (e.g., 10 mg/day), overdoses are likely to cause significant inhibition of both MAO A and MAO B.
Consequently, the signs and symptoms of overdose may resemble those observed with marketed non-selective MAO inhibitors [e.g., tranylcypromine, isocarboxazide, and phenelzine]. Overdose with Non-Selective MAO Inhibition NOTE: This section is provided for reference; it does not describe events that have actually been observed with selegiline in overdose. Characteristically, signs and symptoms of non‑selective MAOI overdose may not appear immediately.
Delays of up to 12 hours between ingestion of drug and the appearance of signs may occur. Importantly, the peak intensity of the syndrome may not be reached for upwards of a day following the overdose. Death has been reported following overdosage.
Therefore, immediate hospitalization, with continuous patient observation and monitoring for a period of at least two days following the ingestion of such drugs in overdose, is strongly recommended. The clinical picture of MAOI overdose varies considerably; its severity may be a function of the amount of drug consumed. The central nervous and cardiovascular systems are prominently involved.
Signs and symptoms of overdosage may include, alone or in combination, any of the following: drowsiness, dizziness, faintness, irritability, hyperactivity, agitation, severe headache, hallucinations, trismus, opisthotonus, convulsions, and coma; rapid and irregular pulse, hypertension, hypotension and vascular collapse; precordial pain, respiratory depression and failure, hyperpyrexia, diaphoresis, and cool, clammy skin. Treatment Suggestions For Overdose NOTE: Because there is no recorded experience with selegiline overdose, the following suggestions are offered based upon the assumption that selegiline overdose may be modeled by non-selective MAOI poisoning.
In any case, up-to-date information about the treatment of overdose can often be obtained from a certified Regional Poison Control Center. Telephone numbers of certified Poison Control Centers are listed in the Physicians' Desk Reference (PDR). Treatment of overdose with non-selective MAOIs is symptomatic and supportive.
Induction of emesis or gastric lavage with instillation of charcoal slurry may be helpful in early poisoning, provided the airway has been protected against aspiration. Signs and symptoms of central nervous system stimulation, including convulsions, should be treated with diazepam, given slowly intravenously. Phenothiazine derivatives and central nervous system stimulants should be avoided.
Hypotension and vascular collapse should be treated with intravenous fluids and, if necessary, blood pressure titration with an intravenous infusion of a dilute pressor agent. It should be noted that adrenergic agents may produce a markedly increased pressor response. Respiration should be supported by appropriate measures, including management of the airway, use of supplemental oxygen, and mechanical ventilatory assistance, as required.
Body temperature should be monitored closely. Intensive management of hyperpyrexia may be required. Maintenance of fluid and electrolyte balance is essential.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The mechanisms accounting for selegiline's beneficial adjunctive action in the treatment of Parkinson's disease are not fully understood. Inhibition of monoamine oxidase, type B, activity is generally considered to be of primary importance; in addition, there is evidence that selegiline may act through other mechanisms to increase dopaminergic activity. Selegiline is best known as an irreversible inhibitor of monoamine oxidase (MAO), an intracellular enzyme associated with the outer membrane of mitochondria.
Selegiline inhibits MAO by acting as a 'suicide' substrate for the enzyme; that is, it is converted by MAO to an active moiety which combines irreversibly with the active site and/or the enzyme's essential FAD cofactor. Because selegiline has greater affinity for type B rather than for type A active sites, it can serve as a selective inhibitor of MAO type B if it is administered at the recommended dose. MAOs are widely distributed throughout the body; their concentration is especially high in liver, kidney, stomach, intestinal wall, and brain.
MAOs are currently subclassified into two types, A and B, which differ in their substrate specificity and tissue distribution. In humans, intestinal MAO is predominantly type A, while most of that in brain is type B. In CNS neurons, MAO plays an important role in the catabolism of catecholamines (dopamine, norepinephrine and epinephrine) and serotonin.
MAOs are also important in the catabolism of various exogenous amines found in a variety of foods and drugs. MAO in the GI tract and liver (primarily type A), for example, is thought to provide vital protection from exogenous amines (e.g., tyramine) that have the capacity, if absorbed intact, to cause a 'hypertensive crisis,' the so-called 'cheese reaction.' (If large amounts of certain exogenous amines gain access to the systemic circulation - e.g., from fermented cheese, red wine, herring, over-the-counter cough/cold medications, etc. - they are taken up by adrenergic neurons and displace norepinephrine from storage sites within membrane bound vesicles.
Subsequent release of the displaced norepinephrine causes the rise in systemic blood pressure, etc.) In theory, since MAO A of the gut is not inhibited, patients treated with selegiline at a dose of 10 mg a day should be able to take medications containing pharmacologically active amines and consume tyramine-containing foods without risk of uncontrolled hypertension. Although rare, a few reports of hypertensive reactions have occurred in patients receiving selegiline at the recommended dose, with tyramine-containing foods.
In addition, one case of hypertensive crisis has been reported in a patient taking the recommended dose of selegiline and a sympathomimetic medication, ephedrine. The pathophysiology of the 'cheese reaction' is complicated and, in addition to its ability to inhibit MAO B selectively, selegiline's relative freedom from this reaction has been attributed to an ability to prevent tyramine and other indirect acting sympathomimetics from displacing norepinephrine from adrenergic neurons. However, until the pathophysiology of the ‘cheese reaction’ is more completely understood, it seems prudent to assume that selegiline can ordinarily only be used safely without dietary restrictions at doses where it presumably selectively inhibits MAO B (e.g., 10 mg/day).
In short, attention to the dose dependent nature of selegiline's selectivity is critical if it is to be used without elaborate restrictions being placed on diet and concomitant drug use although, as noted above, a few cases of hypertensive reactions have been reported at the recommended dose. (See WARNINGS and PRECAUTIONS .) It is important to be aware that selegiline may have pharmacological effects unrelated to MAO B inhibition. As noted above, there is some evidence that it may increase dopaminergic activity by other mechanisms, including interfering with dopamine re-uptake at the synapse.
Effect…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Selegiline Hydrochloride Capsules, USP 5 mg are available for oral administration as hard gelatin capsules with a white opaque body and an aqua blue opaque cap. “APO 055” is imprinted on each capsule in black ink. They are supplied as bottles of 60 (NDC 60505-0055-1), bottles of 500 (NDC 60505-0055-3) and bottles of 1000 (NDC 60505-0055-2). Storage Store at 20º to 25ºC (68º to 77Fº) [see USP Controlled Room Temperature].
APOTEX INC. SELEGILINE HYDROCHLORIDE CAPSULES, USP 5 MG Manufactured by: Manufactured for: Apotex Inc. Apotex Corp.
Toronto, Ontario Weston, Florida Canada 33326 M9L 1T9 Revised: June 2014 Rev. 5
📋 Description ▾
DESCRIPTION Selegiline hydrochloride is a levorotatory acetylenic derivative of phenethylamine. It is commonly referred to in the clinical and pharmacological literature as l- deprenyl. The chemical name is: (R)-(-)- N ,α-Dimethyl- N-2 -propynylphenethylamine hydrochloride.
It is a white to near white crystalline powder, freely soluble in water, chloroform, and methanol, and has a molecular weight of 223.75. The molecular formula is C 13 H 17 N . HCI and the structural formula is as follows: Each capsule, for oral administration contains 5 mg of selegiline hydrochloride.
In addition, each capsule contains the following inactive ingredients: Anhydrous Lactose NF, Citric Acid Anhydrous USP, Microcrystalline Cellulose NF PH102, Stearic Acid NF and Talc USP. The capsule shell contains Gelatin NF, FD & C Blue #1 and Titanium Dioxide. The capsule logo ink Black SW-9008/SW-9009 contains the following inactive ingredients: Ammonium Hydroxide; Black Iron Oxide, Bacteria Controlled EEC No.
172; n-Butyl NF; Ethyl Alcohol, Anhydrous, 200 Proof; Isopropyl Alcohol USP; Potassium Hydroxide NF; Propylene Glycol USP; Purified Water USP and Shellac NF.