
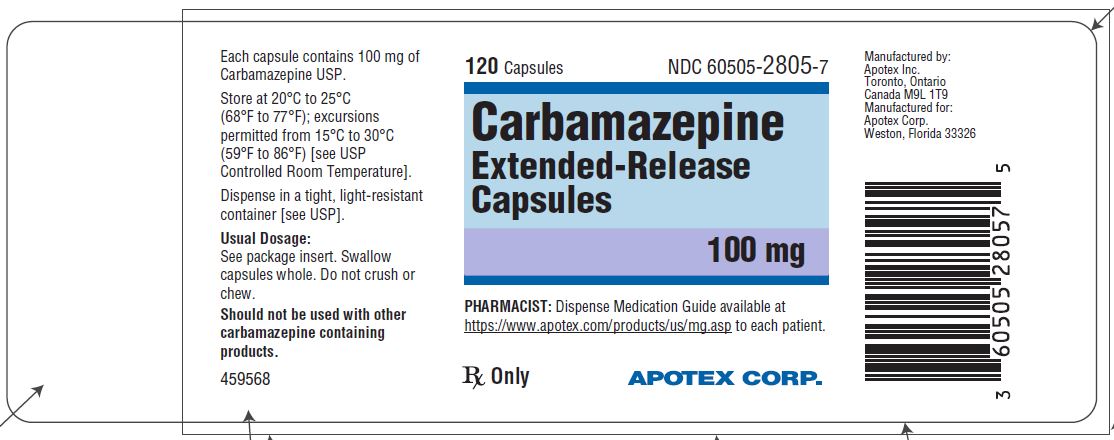
Carbamazepine 100 mg Capsule, Extended Release, 30-count
Other active recalls for Carbamazepine (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- That depends on why your doctor prescribed it. If you have epilepsy, it helps prevent certain types of seizures by calming overactive electrical signals in the brain. If you have t...
- What exactly is carbamazepine supposed to do for me?
- Please don't stop it suddenly without talking to your doctor first — this is really important. Stopping carbamazepine abruptly can trigger serious seizures or even a dangerous cond...
- Can I just stop taking it if I feel better or if I don't like the side effects?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Carbamazepine — tap one for details:
Carbamazepine may be associated with lower levels of 11 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Carbamazepine 100 mg 50268-0170-13 | AvPAK | 1 capsule | $1.107 | AB | Availability likely | — |
| Carbamazepine 100 mg 62559-0484-12 | ANI | 120 capsules | $1.107 | AB | Availability likely | — |
| Carbatrol 100 mg 54092-0171-12 | Takeda | 120 capsules | $1.700 | AB | Availability likely | — |
| Equetro 100 mg 30698-0419-12 | Validus | 120 capsules | $3.653 | — | Availability likely | — |
| Carbamazepine 100 mgthis 60505-2805-03 | Apotex | 30 capsules | — | AB | Discontinued | — |
| Carbamazepine 100 mg 67046-1558-03 | Coupler | 30 capsules | — | AB | FDA listed | — |
| Carbamazepine 100 mg 71335-2921-01 | Bryant | 120 capsules | — | AB | FDA listed | — |
| Carbamazepine 100 mg 71335-3077-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 60505-2805-03 You're viewing this | 30 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (60505-2805-3) | — | — | 2012-03-23 | Discontinued by firm |
| 60505-2805-07 | 120 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (60505-2805-7) | $1.11 / ea | $132.87 | 2012-03-23 | Active |
| 60505-2805-08 | 1000 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (60505-2805-8) | — | — | 2012-03-23 | Discontinued by firm |
You're viewing the smallest of 3 pack sizes for this product.
This pack shows little to no recent Medicaid volume — the 120 capsules pack carries most fills. See all packs ↓
Pack size FAQ
What quantity is in NDC 60505-2805-03?
What is the difference between NDC 60505-2805-03 and NDC 60505-2805-07?
What NDC number is used to bill for this package of Carbamazepine 100 mg Capsule, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING SERIOUS DERMATOLOGIC REACTIONS AND HLA-B*1502 ALLELE SERIOUS AND SOMETIMES FATAL DERMATOLOGIC REACTIONS, INCLUDING TOXIC EPIDERMAL NECROLYSIS (TEN) AND STEVENS-JOHNSON SYNDROME (SJS), HAVE BEEN REPORTED DURING TREATMENT WITH CARBAMAZEPINE. THESE REACTIONS ARE ESTIMATED TO OCCUR IN 1 TO 6 PER 10,000 NEW USERS IN COUNTRIES WITH MAINLY CAUCASIAN POPULATIONS, BUT THE RISK IN SOME ASIAN COUNTRIES IS ESTIMATED TO BE ABOUT 10 TIMES HIGHER. STUDIES IN PATIENTS OF CHINESE ANCESTRY HAVE FOUND A STRONG ASSOCIATION BETWEEN THE RISK OF DEVELOPING SJS/TEN AND THE PRESENCE OF HLA-B*1502, AN INHERITED ALLELIC VARIANT OF THE HLA-B GENE.
HLA-B*1502 IS FOUND ALMOST EXCLUSIVELY IN PATIENTS WITH ANCESTRY ACROSS BROAD AREAS OF ASIA. PATIENTS WITH ANCESTRY IN GENETICALLY AT-RISK POPULATIONS SHOULD BE SCREENED FOR THE PRESENCE OF HLA-B*1502 PRIOR TO INITIATING TREATMENT WITH CARBAMAZEPINE EXTENDED-RELEASE CAPSULES. PATIENTS TESTING POSITIVE FOR THE ALLELE SHOULD NOT BE TREATED WITH CARBAMAZEPINE EXTENDED-RELEASE CAPSULES UNLESS THE BENEFIT CLEARLY OUTWEIGHS THE RISK ( SEE WARNINGS AND PRECAUTIONS/LABORATORY TESTS ).
APLASTIC ANEMIA AND AGRANULOCYTOSIS APLASTIC ANEMIA AND AGRANULOCYTOSIS HAVE BEEN REPORTED IN ASSOCIATION WITH THE USE OF CARBAMAZEPINE. DATA FROM A POPULATION-BASED CASE-CONTROL STUDY DEMONSTRATE THAT THE RISK OF DEVELOPING THESE REACTIONS IS 5 to 8 TIMES GREATER THAN IN THE GENERAL POPULATION. HOWEVER, THE OVERALL RISK OF THESE REACTIONS IN THE UNTREATED GENERAL POPULATION IS LOW, APPROXIMATELY SIX PATIENTS PER ONE MILLION POPULATION PER YEAR FOR AGRANULOCYTOSIS AND TWO PATIENTS PER ONE MILLION POPULATION PER YEAR FOR APLASTIC ANEMIA.
ALTHOUGH REPORTS OF TRANSIENT OR PERSISTENT DECREASED PLATELET OR WHITE BLOOD CELL COUNTS ARE NOT UNCOMMON IN ASSOCIATION WITH THE USE OF CARBAMAZEPINE, DATA ARE NOT AVAILABLE TO ESTIMATE ACCURATELY THEIR INCIDENCE OR OUTCOME. HOWEVER, THE VAST MAJORITY OF THE CASES OF LEUKOPENIA HAVE NOT PROGRESSED TO THE MORE SERIOUS CONDITIONS OF APLASTIC ANEMIA OR AGRANULOCYTOSIS. BECAUSE OF THE VERY LOW INCIDENCE OF AGRANULOCYTOSIS AND APLASTIC ANEMIA, THE VAST MAJORITY OF MINOR HEMATOLOGIC CHANGES OBSERVED IN MONITORING OF PATIENTS ON CARBAMAZEPINE ARE UNLIKELY TO SIGNAL THE OCCURRENCE OF EITHER ABNORMALITY.
NONETHELESS, COMPLETE PRETREATMENT HEMATOLOGICAL TESTING SHOULD BE OBTAINED AS A BASELINE. IF A PATIENT IN THE COURSE OF TREATMENT EXHIBITS LOW OR DECREASED WHITE BLOOD CELL OR PLATELET COUNTS, THE PATIENT SHOULD BE MONITORED CLOSELY. DISCONTINUATION OF THE DRUG SHOULD BE CONSIDERED IF ANY EVIDENCE OF SIGNIFICANT BONE MARROW DEPRESSION DEVELOPS.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Epilepsy Carbamazepine extended-release capsules are indicated for use as an anticonvulsant drug. Evidence supporting efficacy of carbamazepine as an anticonvulsant was derived from active drug-controlled studies that enrolled patients with the following seizure types: Partial seizures with complex symptomatology (psychomotor, temporal lobe). Patients with these seizures appear to show greater improvements than those with other types.
Generalized tonic-clonic seizures (grand mal). Mixed seizure patterns which include the above, or other partial or generalized seizures. Absence seizures (petit mal) do not appear to be controlled by carbamazepine (see PRECAUTIONS, General ).
Trigeminal Neuralgia Carbamazepine extended-release capsules are indicated in the treatment of the pain associated with true trigeminal neuralgia. Beneficial results have also been reported in glossopharyngeal neuralgia. This drug is not a simple analgesic and should not be used for the relief of trivial aches or pains.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Monitoring of blood levels has increased the efficacy and safety of anticonvulsants (see PRECAUTIONS, Laboratory Tests ). Dosage should be adjusted to the needs of the individual patients. A low initial daily dosage with gradual increase is advised.
As soon as adequate control is achieved, the dosage may be reduced very gradually to the minimum effective level. Carbamazepine extended-release capsules may be taken with or without food. Carbamazepine extended-release capsules may be swallowed whole or may be opened and all the beads sprinkled on a teaspoon of soft food such as applesauce.
Make sure all of the food and medicine mixture is swallowed. Do not crush or chew carbamazepine extended-release capsules or the sprinkled beads. Carbamazepine extended-release capsule is an extended-release formulation for twice a day administration.
When converting patients from immediate release carbamazepine to carbamazepine extended-release capsules, the same total daily mg dose of carbamazepine should be administered. Following conversion to carbamazepine, patients should be closely monitored for seizure control. Depending on the therapeutic response after conversion, the total daily dose may need to be adjusted within the recommended dosing instructions.
Epilepsy (see INDICATIONS AND USAGE ) Adults and children over 12 years of age. Initial: 200 mg twice daily. Increase at weekly intervals by adding up to 200 mg/day until the optimal response is obtained.
Dosage generally should not exceed 1,000 mg per day in children 12 to 15 years of age, and 1,200 mg daily in patients above 15 years of age. Doses up to 1,600 mg daily have been used in adults. Maintenance: Adjust dosage to the minimum effective level, usually 800 to 1,200 mg daily.
Children under 12 years of age: Children taking total daily dosages of immediate-release carbamazepine of 400 mg or greater may be converted to the same total daily dosage of carbamazepine extended-release capsules, using a twice daily regimen. Ordinarily, optimal clinical response is achieved at daily doses below 35 mg/kg. If satisfactory clinical response has not been achieved, plasma levels should be measured to determine whether or not they are in the therapeutic range.
No recommendation regarding the safety of carbamazepine extended-release capsules for use at doses above 35 mg/kg/24 hours can be made. Combination Therapy: Carbamazepine extended-release capsules may be used alone or with other anticonvulsants. When added to existing anticonvulsant therapy, the drug should be added gradually while the other anticonvulsants are maintained or gradually decreased, except phenytoin, which may have to be increased (see PRECAUTIONS, Drug Interactions ).
Trigeminal Neuralgia (see INDICATIONS AND USAGE ) Initial: On the first day, start with one 200 mg capsule. This daily dose may be increased by up to 200 mg/day every 12 hours only as needed to achieve freedom from pain. Do not exceed 1,200 mg daily.
Maintenance: Control of pain can be maintained in most patients with 400 to 800 mg daily. However, some patients may be maintained on as little as 200 mg daily, while others may require as much as 1200 mg daily. At least once every 3 months throughout the treatment period, attempts should be made to reduce the dose to the minimum effective level or even to discontinue the drug.
⛔ Contraindications ▾
CONTRAINDICATIONS Carbamazepine should not be used in patients with a history of previous bone marrow depression, hypersensitivity to the drug, or known sensitivity to any of the tricyclic compounds, such as amitriptyline, desipramine, imipramine, protriptyline and nortriptyline. Likewise, on theoretical grounds its use with monoamine oxidase inhibitors is not recommended. Before administration of carbamazepine, MAO inhibitors should be discontinued for a minimum of 14 days, or longer if the clinical situation permits.
Coadministration of carbamazepine and nefazodone may result in insufficient plasma concentrations of nefazodone and its active metabolite to achieve a therapeutic effect. Coadministration of carbamazepine with nefazodone is contraindicated. Coadministration of carbamazepine is contraindicated with delavirdine due to the potential for loss of virologic response and possible resistance to delavirdine or to the class of non-nucleoside reverse transcriptase inhibitors.
⚠️ Warnings ▾
WARNINGS Serious Dermatologic Reactions Serious and sometimes fatal dermatologic reactions, including toxic epidermal necrolysis (TEN) and Stevens-Johnson syndrome (SJS), have been reported with carbamazepine treatment. The risk of these events is estimated to be about 1 to 6 per 10,000 new users in countries with mainly Caucasian populations. However, the risk in some Asian countries is estimated to be about 10 times higher.
Carbamazepine extended-release capsules should be discontinued at the first sign of a rash, unless the rash is clearly not drug-related. If signs or symptoms suggest SJS/TEN, use of this drug should not be resumed and alternative therapy should be considered. SJS/TEN and HLA-B*1502 Allele Retrospective case-control studies have found that in patients of Chinese ancestry there is a strong association between the risk of developing SJS/TEN with carbamazepine treatment and the presence of an inherited variant of the HLA-B gene, HLA-B*1502.
The occurrence of higher rates of these reactions in countries with higher frequencies of this allele suggests that the risk may be increased in allele-positive individuals of any ethnicity. Across Asian populations, notable variation exists in the prevalence of HLA-B*1502. Greater than 15% of the population is reported positive in Hong Kong, Thailand, Malaysia, and parts of the Philippines, compared to about 10% in Taiwan and 4% in North China.
South Asians, including Indians, appear to have intermediate prevalence of HLA-B*1502, averaging 2 to 4%, but higher in some groups. HLA-B*1502 is present in <1% of the population in Japan and Korea. HLA-B*1502 is largely absent in individuals not of Asian origin (e.g., Caucasians, African-Americans, Hispanics, and Native Americans).
Prior to initiating carbamazepine extended-release capsules therapy, testing for HLA-B*1502 should be performed in patients with ancestry in populations in which HLA-B*1502 may be present. In deciding which patients to screen, the rates provided above for the prevalence of HLA-B*1502 may offer a rough guide, keeping in mind the limitations of these figures due to wide variability in rates even within ethnic groups, the difficulty in ascertaining ethnic ancestry, and the likelihood of mixed ancestry. Carbamazepine extended-release capsules should not be used in patients positive for HLA-B*1502 unless the benefits clearly outweigh the risks.
Tested patients who are found to be negative for the allele are thought to have a low risk of SJS/TEN (see WARNINGS and PRECAUTIONS/Laboratory Tests ). Over 90% of carbamazepine treated patients who will experience SJS/TEN have this reaction within the first few months of treatment. This information may be taken into consideration in determining the need for screening of genetically at-risk patients currently on carbamazepine extended-release capsules.
The HLA-B*1502 allele has not been found to predict risk of less severe adverse cutaneous reactions from carbamazepine, such as maculopapular eruption [MPE] or to predict Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS). Limited evidence suggests that HLA-B*1502 may be a risk factor for the development of SJS/TEN in patients of Chinese ancestry taking other anti-epileptic drugs associated with SJS/TEN, including phenytoin. Consideration should be given to avoiding use of other drugs associated with SJS/TEN in HLA-B*1502 positive patients, when alternative therapies are otherwise equally acceptable.
Patients should be made aware that carbamazepine extended-release capsules contain carbamazepine and should not be used in combination with any other medications containing carbamazepine. Hypersensitivity Reactions and HLA-A*3101 Allele Retrospective case-control studies in patients of European, Korean, and Japanese ancestry have found a moderate association between the risk of developing hypersensitivity reactions and the presence of HLA-A*3101, an inherited allelic variant of the HLA-A gene, in patients using…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS General : If adverse reactions are of such severity that the drug must be discontinued, the physician must be aware that abrupt discontinuation of any anticonvulsant drug in a responsive patient with epilepsy may lead to seizures or even status epilepticus with its life-threatening hazards. The most severe adverse reactions previously observed with carbamazepine were reported in the hemopoietic system and skin (see BOXED WARNING ), and the cardiovascular system. The most frequently observed adverse reactions, particularly during the initial phases of therapy, are dizziness, drowsiness, unsteadiness, nausea, and vomiting.
To minimize the possibility of such reactions, therapy should be initiated at the lowest dosage recommended. The following additional adverse reactions were previously reported with carbamazepine: Hemopoietic System: Aplastic anemia, agranulocytosis, pancytopenia, bone marrow depression, thrombocytopenia, leukopenia, leukocytosis, eosinophilia, acute intermittent porphyria. Skin: Toxic epidermal necrolysis (TEN) and Stevens-Johnson syndrome (SJS) (see BOXED WARNING ), Acute Generalized Exanthematous Pustulosis (AGEP), pruritic and erythematous rashes, urticaria, photosensitivity reactions, alterations in skin pigmentation, exfoliative dermatitis, erythema multiforme and nodosum, purpura, aggravation of disseminated lupus erythematosus, alopecia, diaphoresis, onychomadesis and hirsutism.
In certain cases, discontinuation of therapy may be necessary. Cardiovascular System : Congestive heart failure, edema, aggravation of hypertension, hypotension, syncope and collapse, aggravation of coronary artery disease, arrhythmias and AV block, thrombophlebitis, thromboembolism, and adenopathy or lymphadenopathy. Some of these cardiovascular complications have resulted in fatalities.
Myocardial infarction has been associated with other tricyclic compounds. Immune system disorders : Hypogammaglobulinemia. Liver : Abnormalities in liver function tests, cholestatic and hepatocellular jaundice, hepatitis, and hepatic failure.
Pancreatic : Pancreatitis. Respiratory System: Pulmonary hypersensitivity characterized by fever, dyspnea, pneumonitis, or pneumonia. Genitourinary System : Urinary frequency, acute urinary retention, oliguria with elevated blood pressure, azotemia, renal failure, and impotence.
Albuminuria, glycosuria, elevated BUN, and microscopic deposits in the urine have also been reported. There have been rare reports of impaired male fertility and/or abnormal spermatogenesis. Testicular atrophy occurred in rats receiving carbamazepine orally from 4 to 52 weeks at dosage levels of 50 to 400 mg/kg/day.
Additionally, rats receiving carbamazepine in the diet for 2 years at dosage levels of 25, 75, and 250 mg/kg/day had a dose-related incidence of testicular atrophy and aspermatogenesis. In dogs, it produced a brownish discoloration, presumably a metabolite, in the urinary bladder at dosage levels of 50 mg/kg/day and higher. Relevance of these findings to humans is unknown.
Nervous System : Dizziness, drowsiness, disturbances of coordination, confusion, headache, fatigue, blurred vision, visual hallucinations, transient diplopia, oculomotor disturbances, nystagmus, speech disturbances, abnormal involuntary movements, peripheral neuritis and paresthesias, depression with agitation, talkativeness, tinnitus, and hyperacusis. There have been reports of associated paralysis and other symptoms of cerebral arterial insufficiency, but the exact relationship of these reactions to the drug has not been established.
Isolated cases of neuroleptic malignant syndrome have been reported with concomitant use of psychotropic drugs. Digestive System : Nausea, vomiting, gastric distress and abdominal pain, diarrhea, constipation, anorexia, and dryness of the mouth and pharynx, including glossitis and stomatitis. Eyes: Scattered punctate cortical lens opacities, as well as conjunctivitis, have been reported.
Although a di…
🔄 Drug Interactions ▾
Drug Interactions Clinically meaningful drug interactions have occurred with concomitant medications and include, but are not limited to the following: Agents Highly Bound to Plasma Protein: Carbamazepine is not highly bound to plasma proteins; therefore, administration of carbamazepine extended-release capsules to a patient taking another drug that is highly protein bound should not cause increased free concentrations of the other drug. Agents that Inhibit Cytochrome P450 Isoenzymes and/or Epoxide Hydrolase: Carbamazepine is metabolized mainly by cytochrome P450 (CYP) 3A4 to the active carbamazepine 10, 11-epoxide, which is further metabolized to the trans-diol by epoxide hydrolase.
Therefore, the potential exists for interaction between carbamazepine and any agent that inhibits CYP3A4 and/or epoxide hydrolase. Agents that are CYP3A4 inhibitors that have been found, or are expected, to increase plasma levels of carbamazepine extended-release capsules include, for example, the following: Acetazolamide, aprepitant, azole antifungals (e.g., ketoconazole, itraconazole, fluconazole, voriconazole), cimetidine, ciprofloxacin, clarithromycin, dalfopristin, danazol, dantrolene, delavirdine, diltiazem, erythromycin, fluoxetine, fluvoxamine, grapefruit juice, ibuprofen, isoniazid, loratadine, macrolides, nefazodone, niacinamide, nicotinamide, olanzapine, omeprazole, oxybutynin, protease inhibitors, propoxyphene, quinine, quinupristin, ticlopidine, troleandomycin, valproate, verapamil, zileuton.
Human microsomal epoxide hydrolase has been identified as the enzyme responsible for the formation of the 10,11-transdiol derivative from carbamazepine-10,11 epoxide. Coadministration of inhibitors of human microsomal epoxide hydrolase may result in increased carbamazepine-10,11 epoxide plasma concentrations. Accordingly, the dosage of carbamazepine extended-release capsules should be adjusted and/or the plasma levels monitored when used concomitantly with loxapine, quetiapine, or valproic acid.
Thus, if a patient has been titrated to a stable dosage of carbamazepine extended-release capsules, and then begins a course of treatment with one of these CYP3A4 or epoxide hydrolase inhibitors, it is reasonable to expect that a dose reduction for carbamazepine extended-release capsules may be necessary. Agents that Induce Cytochrome P450 Isoenzymes : Carbamazepine is metabolized by CYP3A4. Therefore, the potential exists for interaction between carbamazepine and any agent that induces CYP3A4.
Agents that are CYP inducers that have been found, or are expected, to decrease plasma levels of carbamazepine extended-release capsules include, for example, the following: Aminophylline, cisplatin, doxorubicin HCL, felbamate, fosphenytoin, methsuximide, phenobarbital, phenytoin( 1 ), primidone, rifampin and theophylline. (1) Phenytoin plasma levels have also been reported to increase and decrease in the presence of carbamazepine, see below. Thus, if a patient has been titrated to a stable dosage on carbamazepine extended-release capsules, and then begins a course of treatment with one of these CYP3A4 inducers, it is reasonable to expect that a dose increase for carbamazepine extended-release capsules may be necessary.
Agents with Decreased Levels in the Presence of Carbamazepine due to Induction of Cytochrome P450 Enzymes: Carbamazepine is a potent inducer of hepatic CYP3A4 and is also known to be an inducer of CYP1A2, 2B6, 2C9/19 and may therefore reduce plasma concentrations of co-medications mainly metabolized by CYP 1A2, 2B6, 2C9/19 and 3A4, through induction of their metabolism. When used concomitantly with carbamazepine extended-release capsules, monitoring of concentrations or dosage adjustment of these agents may be necessary: When carbamazepine is added to aripiprazole, the aripiprazole dose should be doubled.
Additional dose increases should be based on clinical evaluation. If carbamazepine is later withdrawn, the aripiprazole dose should be reduced. Wh…
🤰 Pregnancy ▾
Usage in Pregnancy (See WARNINGS )
🧒 Pediatric Use ▾
Pediatric Use Substantial evidence of carbamazepine effectiveness for use in the management of children with epilepsy (see INDICATIONS for specific seizure types) is derived from clinical investigations performed in adults and from studies in several in vitro systems which support the conclusion that (1) the pathogenic mechanisms underlying seizure propagation are essentially identical in adults and children, and (2) the mechanism of action of carbamazepine in treating seizures is essentially identical in adults and children.
Taken as a whole, this information supports a conclusion that the generally acceptable therapeutic range of total carbamazepine in plasma (i.e., 4 to 12 mcg/mL) is the same in children and adults. The evidence assembled was primarily obtained from short-term use of carbamazepine. The safety of carbamazepine in children has been systematically studied up to 6 months.
No longer term data from clinical trials is available.
🧓 Geriatric Use ▾
Geriatric Use No systematic studies in geriatric patients have been conducted.
🆘 Overdosage ▾
OVERDOSAGE Acute Toxicity Lowest known lethal dose: adults, >60 g (39-year-old man). Highest known doses survived: adults, 30 g (31-year-old woman); children, 10 g (6-year-old boy); small children, 5 g (3-year-old girl). Oral LD 50 in animals (mg/kg): mice, 1100 to 3750; rats, 3850 to 4025; rabbits, 1500 to 2680; guinea pigs, 920.
Signs and Symptoms The first signs and symptoms appear after 1 to 3 hours. Neuromuscular disturbances are the most prominent. Cardiovascular disorders are generally milder, and severe cardiac complications occur only when very high doses (>60 g) have been ingested.
Respiration: Irregular breathing, respiratory depression. Cardiovascular System: Tachycardia, hypotension or hypertension, shock, conduction disorders. Nervous System and Muscles: Impairment of consciousness ranging in severity to deep coma.
Convulsions, especially in small children. Motor restlessness, muscular twitching, tremor, athetoid movements, opisthotonos, ataxia, drowsiness, dizziness, mydriasis, nystagmus, adiadochokinesia, ballism, psychomotor disturbances, dysmetria. Initial hyperreflexia, followed by hyporeflexia.
Gastrointestinal Tract: Nausea, vomiting. Kidneys and Bladder: Anuria or oliguria, urinary retention. Laboratory Findings: Isolated instances of overdosage have included leukocytosis, reduced leukocyte count, glycosuria, and acetonuria.
ECG may show dysrhythmias. Combined Poisoning: When alcohol, tricyclic antidepressants, barbiturates, or hydantoins are taken at the same time, the signs and symptoms of acute poisoning with carbamazepine may be aggravated or modified. Treatment For the most up to date information on management of carbamazepine overdose, please contact the poison center for your area by calling 1-800-222-1222.
The prognosis in cases of carbamazepine poisoning is generally favorable. Of 5,645 cases of carbamazepine exposures reported to US poison centers in 2002, a total of 8 deaths (0.14% mortality rate) occurred. Over 39% of the cases reported to these poison centers were managed safely at home with conservative care.
Successful management of large or intentional carbamazepine exposures requires implementation of supportive care, frequent monitoring of serum drug concentrations, as well as aggressive but appropriate gastric decontamination. Elimination of the Drug: The primary method for gastric decontamination of carbamazepine overdose is use of activated charcoal. For substantial recent ingestions, gastric lavage may also be considered.
Administration of activated charcoal prior to hospital assessment has the potential to significantly reduce drug absorption. There is no specific antidote. In overdose, absorption of carbamazepine may be prolonged and delayed.
More than one dose of activated charcoal may be beneficial in patients that have evidence of continued absorption (e.g., rising serum carbamazepine levels). Measures to Accelerate Elimination: The data on use of dialysis to enhance elimination in carbamazepine is scarce. Dialysis, particularly high flux or high efficiency hemodialysis, may be considered in patients with severe carbamazepine poisoning associated with renal failure or in cases of status epilepticus, or where there are rising serum drug levels and worsening clinical status despite appropriate supportive care and gastric decontamination.
For severe cases of carbamazepine overdose unresponsive to other measures, charcoal hemoperfusion may be used to enhance drug clearance. Respiratory Depression: Keep the airways free; resort, if necessary, to endotracheal intubation, artificial respiration, and administration of oxygen. Hypotension, Shock: Keep the patient's legs raised and administer a plasma expander.
If blood pressure fails to rise despite measures taken to increase plasma volume, use of vasoactive substances should be considered. Convulsions: Diazepam or barbiturates. Warning: Diazepam or barbiturates may aggravate respiratory depression (especially in children), hypotension,…
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY In controlled clinical trials, carbamazepine has been shown to be effective in the treatment of psychomotor and grand mal seizures, as well as trigeminal neuralgia. Mechanism of Action Carbamazepine has demonstrated anticonvulsant properties in rats and mice with electrically and chemically induced seizures. It appears to act by reducing polysynaptic responses and blocking the post-tetanic potentiation.
Carbamazepine greatly reduces or abolishes pain induced by stimulation of the infraorbital nerve in cats and rats. It depresses thalamic potential and bulbar and polysynaptic reflexes, including the linguomandibular reflex in cats. Carbamazepine is chemically unrelated to other anticonvulsants or other drugs used to control the pain of trigeminal neuralgia.
The mechanism of action remains unknown. The principal metabolite of carbamazepine, carbamazepine-10, 11-epoxide, has anticonvulsant activity as demonstrated in several in vivo animal models of seizures. Though clinical activity for the epoxide has been postulated, the significance of its activity with respect to the safety and efficacy of carbamazepine has not been established.
Pharmacokinetics Carbamazepine (CBZ): Taken every 12 hours, carbamazepine extended-release capsules provide steady state plasma levels comparable to immediate-release carbamazepine tablets given every 6 hours, when administered at the same total mg daily dose. Following a single 200 mg oral extended-release dose of carbamazepine, peak plasma concentration was 1.9 ± 0.3 mcg/mL and the time to reach the peak was 19 ± 7 hours. Following chronic administration (800 mg every 12 hours), the peak levels were 11.0 ± 2.5 mcg/mL and the time to reach the peak was 5.9 ± 1.8 hours.
The pharmacokinetics of extended-release carbamazepine is linear over the single dose range of 200 to 800 mg. Carbamazepine is 76% bound to plasma proteins. Carbamazepine is primarily metabolized in the liver.
Cytochrome P450 3A4 was identified as the major isoform responsible for the formation of carbamazepine-10, 11-epoxide. Since carbamazepine induces its own metabolism, the half-life is also variable. Following a single extended-release dose of carbamazepine, the average half-life range from 35 to 40 hours and 12 to 17 hours on repeated dosing.
The apparent oral clearance following a single dose was 25 ± 5 mL/min and following multiple dosing was 80 ± 30 mL/min. After oral administration of 14 C-carbamazepine, 72% of the administered radioactivity was found in the urine and 28% in the feces. This urinary radioactivity was composed largely of hydroxylated and conjugated metabolites, with only 3% of unchanged carbamazepine.
Carbamazepine-10, 11-epoxide (CBZ-E): Carbamazepine-10, 11-epoxide is considered to be an active metabolite of carbamazepine. Following a single 200 mg oral extended-release dose of carbamazepine, the peak plasma concentration of carbamazepine-10, 11-epoxide was 0.11 ± 0.012 mcg/mL and the time to reach the peak was 36 ± 6 hours. Following chronic administration of an extended-release dose of carbamazepine (800 mg every 12 hours), the peak levels of carbamazepine-10, 11-epoxide were 2.2 ± 0.9 mcg/mL and the time to reach the peak was 14 ± 8 hours.
The plasma half-life of carbamazepine-10, 11-epoxide following administration of carbamazepine is 34 ± 9 hours. Following a single oral dose of extended-release carbamazepine (200 to 800 mg) the AUC and C max of carbamazepine-10, 11-epoxide were less than 10% of carbamazepine. Following multiple dosing of extended-release carbamazepine (800 to 1,600 mg daily for 14 days), the AUC and C max of carbamazepine-10, 11-epoxide were dose related, ranging from 15.7 mcg·hr/mL and 1.5 mcg/mL at 800 mg/day to 32.6 mcg·hr/mL and 3.2 mcg/mL at 1,600 mg/day, respectively, and were less than 30% of carbamazepine.
Carbamazepine-10, 11-epoxide is 50% bound to plasma proteins. Food Effect: A high fat meal diet increased the rate of absorption of a single 400 mg dose…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Carbamazepine extended-release capsules 100 mg are hard gelatin capsules with white opaque body and blue-green opaque cap, imprinted “APO C100” in black ink with white to off-white granule fill. They are supplied as follows: Bottles of 30s (NDC 60505-2805-3) Bottles of 120s (NDC 60505-2805-7) Bottles of 1000s (NDC 60505-2805-8) Carbamazepine extended-release capsules 200 mg are hard gelatin capsules with white opaque body and blue-green opaque cap, imprinted “APO C200” in black ink with white to off-white granule fill.
They are supplied as follows: Bottles of 30s (NDC 60505-2806-3) Bottles of 120s (NDC 60505-2806-7) Bottles of 1000s (NDC 60505-2806-8) Carbamazepine extended-release capsules 300 mg are hard gelatin capsules with white opaque body and blue-green opaque cap, imprinted “APO C300” in black ink with white to off-white granule fill. They are supplied as follows: Bottles of 30s (NDC 60505-2807-3) Bottles of 120s (NDC 60505-2807-7) Bottles of 500s (NDC 60505-2807-5) Store at 20˚C to 25°C (68˚F to 77°F); excursions permitted to 15˚C to 30°C (59˚F to 86°F) [see USP Controlled Room Temperature].
Dispense in a tight, light-resistant container [see USP]. Dispense with Medication Guide available at https://www.apotex.com/products/us/mg.asp APOTEX INC. CARBAMAZEPINE EXTENDED-RELEASE CAPSULES 100 mg, 200 mg and 300 mg Manufactured by: Apotex Inc.
Toronto, Ontario Canada M9L 1T9 Manufactured for: Apotex Corp. Weston, Florida USA 33326 Rev. 11
📋 Description ▾
DESCRIPTION Carbamazepine extended-release capsules are an anticonvulsant and specific analgesic for trigeminal neuralgia, available for oral administration as 100 mg, 200 mg and 300 mg extended-release capsules of Carbamazepine, USP. Carbamazepine is a white to off-white powder, practically insoluble in water and soluble in alcohol and in acetone. Its molecular weight is 236.27 g/mol.
Its chemical name is 5H-dibenz[b,f]azepine-5-carboxamide, and its structural formula is: Carbamazepine extended-release capsules are a multi-component capsule formulation consisting of extended-release granules. Inactive ingredients: colloidal silicon dioxide, ethylcellulose, and stearic acid. The 100 mg, 200 mg and 300 mg capsule shells contain FD&C Blue #2, gelatin, iron oxide yellow, titanium dioxide and are imprinted with black ink (S-1-8114 and S-1-8115) contain FD&C BLUE #2, FD&C RED #40, FD&C BLUE #1, D&C YELLOW #10 and shellac. carbamazepine-figure-1
💬 Information for Patients ▾
Information for Patients Patients should be informed of the availability of a Medication Guide and they should be instructed to read the Medication Guide before taking carbamazepine extended-release capsules. Patients should be made aware of the early toxic signs and symptoms of potential hematologic, dermatologic, hypersensitivity, or hepatic reactions. These symptoms may include, but are not limited to, fever, sore throat, rash, ulcers in the mouth, easy bruising, lymphadenopathy and petechial or purpuric hemorrhage, and in the case of liver reactions, anorexia, nausea/vomiting, or jaundice.
Patients should be advised that, because these signs and symptoms may signal a serious reaction, they must report any occurrence immediately to their physicians. In addition, the patient should be advised that these signs and symptoms should be reported even if mild or when occurring after extended use. Patients should be advised that serious skin reactions have been reported in association with carbamazepine extended-release capsules.
In the event a skin reaction should occur while taking carbamazepine extended-release capsules, patients should consult with their physician immediately (see WARNINGS ). Patients should be advised that anaphylactic reactions and angioedema may occur during treatment with carbamazepine extended-release capsules (see WARNINGS ). Advise patients to immediately report signs and symptoms suggesting angioedema (swelling of the face, eyes, lips, or tongue, or difficulty in swallowing or breathing) and to stop taking the drug until they have consulted with their healthcare provider.
Patients, their caregivers, and families should be counseled that AEDs, including carbamazepine, may increase the risk of suicidal thoughts and behavior and should be advised of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm. Behaviors of concern should be reported immediately to healthcare providers. Carbamazepine extended-release capsules may interact with some drugs.
Therefore, patients should be advised to report to their doctors the use of any other prescription or nonprescription medications or herbal products. Caution should be exercised if alcohol is taken in combination with carbamazepine therapy, due to a possible additive sedative effect. Since dizziness and drowsiness may occur, patients should be cautioned about the hazards of operating machinery or automobiles or engaging in other potentially dangerous tasks.
Patients should be encouraged to enroll in the NAAED Pregnancy Registry if they become pregnant. This registry is collecting information about the safety of antiepileptic drugs during pregnancy. To enroll, patients can call the toll-free number 1-888-233-2334 (see Warnings-Usage in Pregnancy ).
If necessary, the carbamazepine extended-release capsules can be opened and the contents sprinkled over food, such as a teaspoon of applesauce or other similar food products. Carbamazepine extended-release capsules or their contents should not be crushed or chewed. Carbamazepine extended-release capsules may interact with some drugs.
Therefore, patients should be advised to report to their doctors the use of any other prescription or non-prescription medication or herbal products. Patients, their caregivers, and families should be informed of the availability of a Medication Guide, and they should be instructed to read the Medication Guide prior to taking carbamazepine extended-release capsules. See FDA approved Medication Guide.
💬 Medication Guide ▾
Medication Guide Carbamazepine Extended-Release Capsules (kar” ba maz’ e peen) Medication Guide available at https://www.apotex.com/products/us/mg.asp Read this Medication Guide before you start taking carbamazepine extended-release capsules and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about carbamazepine extended-release capsules? Do not stop taking carbamazepine extended-release capsules without first talking to your healthcare provider. Stopping carbamazepine extended-release capsules suddenly can cause serious problems.
Carbamazepine extended-release capsules can cause serious side effects, including: 1. Carbamazepine extended-release capsules may cause rare but serious rashes that may lead to death. These serious skin reactions are more likely to happen within the first four months of carbamazepine extended-release capsules treatment but may occur at later times.
These reactions can happen in anyone, but are more likely in people of Asian descent. If you are of Asian descent you may need a genetic blood test before you take carbamazepine extended-release capsules to see if you are at a higher risk for serious skin reactions with this medicine. Symptoms may include: skin rash hives sores in your mouth blistering or peeling of the skin 2.
Carbamazepine extended-release capsules can also cause other types of allergic reactions or serious problems that may affect organs and other parts of your body such as your liver or blood cells. You may or may not have a rash when you get these types of reactions. Call your healthcare provider right away if you have any of these symptoms: swelling of your face, eyes, lips, or tongue trouble swallowing or breathing frequent fevers or fevers that do not go away frequent infections or an infection that does not go away unusual bruising or bleeding red or purple spots on your body severe fatigue or weakness unexpected muscle pain that does not go away swollen glands that do not go away yellowing of your skin or the whites of your eyes loss of appetite (anorexia) that does not go away nausea or vomiting that does not go away These symptoms may be the first signs of a serious reaction.
A healthcare provider should examine you to decide if you should continue taking carbamazepine extended-release capsules. 3. Like other antiepileptic drugs, carbamazepine extended-release capsules may cause suicidal thoughts or actions in a very small number of people, about 1 in 500.
Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempt to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Do not stop carbamazepine extended-release capsules without first talking to a healthcare provider. Stopping carbamazepine extended-release capsules suddenly can cause serious problems. Suicidal thoughts or actions can be caused by things other than medicines.
If you have suicidal thoughts or actions, your healthcare provider may check for other causes. What is carbamazepine extended-release capsule? Carbamazepine extended-release capsule is a medicine used to treat: certain types of seizures (partial, tonic-clonic, mixed) cert…