
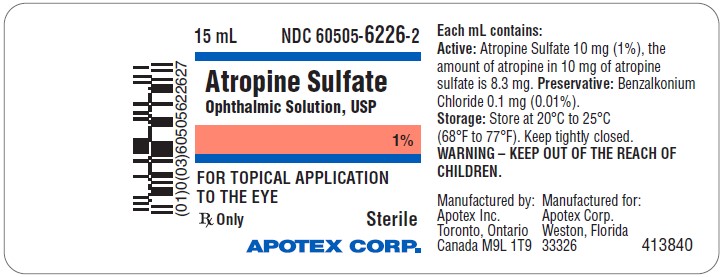
Atropine 10 mg/mL Solution/ Drops
Other active recalls for Atropine Sulfate (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Anticholinergic class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ophthalmic atropine is used before eye examinations to dilate (open) the pupil, the black part of the eye through which you see. It is also used to relieve pain caused by swelling and inflammation of the eye.
Read the full MedlinePlus article ↗- Atropine works by blocking a nerve signal that, when overactive, can cause a dangerously slow heart rate, flooding secretions, or — in poisoning — life-threatening over-stimulation...
- Why am I being given atropine — what does it actually do?
- It's very common to notice a dry mouth, blurred vision, light sensitivity, a faster heartbeat, flushing, or difficulty urinating — those are expected effects of how atropine works...
- What side effects should I expect, and which ones mean I need to call for help?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Atropine Sulfate — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII F5UM2KM3W7
Benzalkonium chloride is a chemical compound that works as a preservative and antimicrobial agent in medications. It prevents bacterial and fungal growth in liquid formulations to keep the product safe during storage and use.
-
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII RN3152OP35
Hypromellose is a plant-based thickener and film-former derived from cellulose. In medicines, it's used to create coatings on tablets and capsules, control how fast the drug dissolves, and improve the product's texture and stability.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII GR686LBA74
Sodium phosphate, dibasic is a salt derived from phosphoric acid. It acts as a buffer to help maintain the medicine's pH balance and may serve as a binder or filler in tablets and capsules.
-
UNII 3980JIH2SW
A salt form of phosphoric acid that acts as a buffer and pH adjuster in medicines. It helps keep the product at the correct acidity level for stability and effectiveness.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3.916 | $58.74 / 15 ml |
| Medicaid paysCMS SDUD · 12 mo | $11.51 | $172.67 / 15 ml |
| Medicare drug plans payPart D · Q2 2026 | $7.91 | $118.59 / 15 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Atropine 10 mg/mL 60219-1750-08 | Amneal | 1 bottle | $3.916 | AT1 | Availability likely | — |
| Atropine 10 mg/mLthis 60505-6226-02 | Apotex | 1 bottle | $3.916 | AT1 | Availability likely | — |
| Atropine sulfate 10 mg/mL 70069-0583-01 | Somerset | 1 bottle | $3.916 | AT1 | Availability likely | — |
| Atropine Sulfate 10 mg/mL 70756-0653-35 | Lifestar | 1 bottle | $3.916 | AT1 | Availability likely | — |
| Atropine 10 mg/mL 60219-1749-03 | Amneal | 1 bottle | $5.540 | AT1 | Availability likely | +41% |
| Atropine sulfate 10 mg/mL 70069-0582-01 | Somerset | 1 bottle | $5.540 | AT1 | Availability likely | +41% |
| Atropine Sulfate 10 mg/mL 70756-0652-25 | Lifestar | 1 bottle | $5.540 | AT1 | Availability likely | +41% |
| Isopto Atropine 10 mg/mL 00065-0303-55 | Alcon | 1 bottle | $9.701 | AT2 | Discontinued | +148% |
| atropine sulfate 10 mg/mL 00065-0817-01 | Alcon | 1 bottle | $11.605 | AT2 | Availability likely | +196% |
| Atropine Sulfate 10 mg/mL 70069-0716-01 | Somerset | 1 bottle | $11.605 | AT2 | Availability likely | +196% |
| Atropine sulfate 10 mg/mL 42799-0826-01 | Edenbridge | 1 bottle | $12.878 | AT1 | Availability likely | +229% |
| Atropine 10 mg/mL 60219-1748-02 | Amneal | 1 bottle | $12.878 | AT1 | Availability likely | +229% |
| Atropine sulfate 10 mg/mL 70069-0581-01 | Somerset | 1 bottle | $12.878 | AT1 | Availability likely | +229% |
| Atropine Sulfate 10 mg/mL 70756-0651-25 | Lifestar | 1 bottle | $12.878 | AT1 | Availability likely | +229% |
| Atropine Sulfate 10 mg/mL 72603-0264-01 | NorthStar | 1 bottle | $12.878 | AT1 | Availability likely | +229% |
| Atropine Sulfate 10 mg/mL 24208-0965-01 | Bausch | 10 vials | — | — | FDA listed | — |
| Atropine 10 mg/mL 50090-7000-00 | A-S | 1 bottle | — | AT1 | FDA listed | — |
| Atropine 10 mg/mL 50090-7313-00 | A-S | 1 bottle | — | AT1 | FDA listed | — |
| Atropine Sulfate 10 mg/mL 67296-2124-05 | Redpharm | 1 bottle | — | AT1 | FDA listed | — |
| Atropine 10 mg/mL 67296-2200-05 | Redpharm | 1 bottle | — | AT1 | FDA listed | — |
| Atropine Sulfate 10 mg/mL 82260-0001-01 | Bausch | 10 vials | — | — | FDA listed | — |
| Atropine 10 mg/mL 68083-0671-01 | Gland | 1 bottle | — | AT1 | FDA listed | — |
| Atropine 10 mg/mL 68083-0669-01 | Gland | 1 bottle | — | AT1 | FDA listed | — |
| Atropine 10 mg/mL 68083-0670-01 | Gland | 1 bottle | — | AT1 | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 60505-6226-00 | 1 BOTTLE, DROPPER in 1 CARTON (60505-6226-0) / 2 mL in 1 BOTTLE, DROPPER | $12.88 / mL | $25.76 | 2021-11-26 | Active |
| 60505-6226-01 | 1 BOTTLE, DROPPER in 1 CARTON (60505-6226-1) / 5 mL in 1 BOTTLE, DROPPER | $5.54 / mL | $27.70 | 2021-11-26 | Active |
| 60505-6226-02 You're viewing this | 1 BOTTLE, DROPPER in 1 CARTON (60505-6226-2) / 15 mL in 1 BOTTLE, DROPPER | $3.92 / mL | $58.74 | 2022-02-07 | Active |
This pack has the lowest per-mL cost of the 3 priced pack sizes ($3.92 NADAC).
This pack accounts for about 5.2% of this product's recent Medicaid fills; most go to a different pack size. See all packs ↓
Pack size FAQ
What quantity is in NDC 60505-6226-02?
What NDC number is used to bill for this package of Atropine 10 mg/mL Solution/ Drops?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1. INDICATIONS AND USAGE Atropine sulfate ophthalmic solution, 1% is indicated in adults and pediatric patients aged three (3) months and older for: Atropine is an anticholinergic agent indicated in adults and pediatric patients aged three (3) months and older for: Cycloplegia ( 1.1 ) Mydriasis ( 1.2 ) Penalization of the healthy eye in the treatment of amblyopia ( 1.3 )
1.1 Cycloplegia
1.2 Mydriasis
1.3 Penalization of the Healthy Eye in the Treatment of Amblyopia
⏱️ Dosage and Administration ▾
2. DOSAGE AND ADMINISTRATION Apply 1 drop topically to the cul-de-sac of the conjunctiva, forty minutes prior to the intended maximal dilation time ( 2 ) In adults and pediatric patients 3 years and older, doses may be repeated up to twice daily as needed. ( 2 ) Apply 1 drop topically to the cul-de-sac of the conjunctiva, forty minutes prior to the intended maximal dilation time.
In adults and pediatric patients aged 3 years and older, doses may be repeated up to twice daily as needed.
💊 Dosage Forms and Strengths ▾
3. DOSAGE FORMS AND STRENGTHS Atropine sulfate ophthalmic solution, USP: 1% atropine sulfate. Ophthalmic solution 1% atropine sulfate ( 3 )
⛔ Contraindications ▾
4. CONTRAINDICATIONS Hypersensitivity or allergic reaction to any ingredient in formulation ( 4.1 )
4.1Hypersensitivity Atropine sulfate ophthalmic solution 1% is contraindicated in patients who have demonstrated a previous hypersensitivity or known allergic reaction to any ingredient of the formulation.
⚠️ Warnings and Cautions ▾
5. WARNINGS AND PRECAUTIONS Photophobia and blurred vision due to pupil unresponsiveness and cycloplegia may last up to 2 weeks. ( 5.1 ) Risk of blood pressure increase from systemic absorption ( 5.2 )
5.1Photophobia and Blurred Vision Photophobia and blurred vision due to pupil unresponsiveness and cycloplegia may last up to 2 weeks.
5.2Elevation of Blood Pressure Elevations in blood pressure from systemic absorption has been reported following conjunctival instillation of recommended doses of atropine sulfate ophthalmic solution, 1%.
5.3Risk of Contamination Do not touch the dropper tip to the eye, eyelids, or any other surface as this may contaminate the solution.
🤒 Adverse Reactions ▾
6. ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: Photophobia and Blurred Vision [See Warnings and Precautions ( 5.1 )] Elevation in Blood Pressure [See Warnings and Precautions ( 5.2 )] The following adverse reactions were identified in clinical studies or postmarketing reports following use of atropine sulfate ophthalmic solution. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure.
Most common adverse reactions that have been reported are eye pain and stinging on administration, blurred vision, photophobia, decreased lacrimation, increased heart rate and blood pressure. ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Apotex Corp. at 1-800-706-5575 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Ocular Adverse Reactions Eye pain and stinging occurs upon instillation. Other commonly occurring adverse reactions include, blurred vision, photophobia, superficial keratitis and decreased lacrimation. Allergic reactions such as papillary conjunctivitis, contact dermatitis, and lid edema may also occur less commonly.
6.2Systemic Adverse Reactions Systemic effects of atropine are related to its anti-muscarinic activity. Systemic adverse events reported include dryness of skin, mouth, and throat from decreased secretions from mucus membranes; restlessness, irritability or delirium from stimulation of the central nervous system; tachycardia; flushed skin of the face and neck.
🔄 Drug Interactions ▾
7. DRUG INTERACTIONS The use of atropine and monoamine oxidase inhibitors (MAOI) is generally not recommended because of the potential to precipitate hypertensive crisis. ( 7 )
7.1Monoamine Oxidase Inhibitors (MAOI) The use of atropine and monoamine oxidase inhibitors (MAOI) is generally not recommended because of the potential to precipitate hypertensive crisis.
👥 Use in Specific Populations ▾
8. USE IN SPECIFIC POPULATIONS Should only be used in pregnant women if clearly needed. ( 8.1 )
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of atropine sulfate administration in pregnant women to inform a drug-associated risk. Adequate animal development and reproduction studies have not been conducted with atropine sulfate. In humans, 1% atropine sulfate is systemically bioavailable following topical ocular administration [see Clinical Pharmacology ( 12.3 ) ].
Atropine sulfate ophthalmic solution, 1% should only be used during pregnancy if the potential benefit justifies the potential risk to the fetus.
8.2Lactation Risk Summary There is no information to inform risk regarding the presence of atropine in human milk following ocular administration of atropine sulfate to the mother. The effects on breastfed infants and the effects on milk production are also unknown. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for atropine sulfate and any potential adverse effects on the breastfed child from atropine sulfate.
8.4Pediatric Use The safety and effectiveness of Atropine Sulfate Ophthalmic Solution 1% have been established in pediatric patients aged 3 months and older. Use of Atropine Sulfate Ophthalmic Solution 1% is supported by evidence from adequate and well-controlled trials with additional safety data from published literature. Due to the potential for systemic absorption, the use of atropine sulfate ophthalmic solution, 1% in pediatric patients aged 3 months to 3 years should be limited to no more than one drop per eye per day.
Use in pediatric patients younger than 3 months of age is not recommended.
8.5Geriatric Use No overall differences in safety and effectiveness have been observed between elderly and younger adult patients.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of atropine sulfate administration in pregnant women to inform a drug-associated risk. Adequate animal development and reproduction studies have not been conducted with atropine sulfate. In humans, 1% atropine sulfate is systemically bioavailable following topical ocular administration [see Clinical Pharmacology ( 12.3 ) ].
Atropine sulfate ophthalmic solution, 1% should only be used during pregnancy if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of Atropine Sulfate Ophthalmic Solution 1% have been established in pediatric patients aged 3 months and older. Use of Atropine Sulfate Ophthalmic Solution 1% is supported by evidence from adequate and well-controlled trials with additional safety data from published literature. Due to the potential for systemic absorption, the use of atropine sulfate ophthalmic solution, 1% in pediatric patients aged 3 months to 3 years should be limited to no more than one drop per eye per day.
Use in pediatric patients younger than 3 months of age is not recommended.
🧓 Geriatric Use ▾
8.5Geriatric Use No overall differences in safety and effectiveness have been observed between elderly and younger adult patients.
🆘 Overdosage ▾
10. OVERDOSAGE In the event of accidental ingestion or toxic overdosage with atropine sulfate ophthalmic solution, supportive care may include a short acting barbiturate or diazepam as needed to control marked excitement and convulsions. Large doses for sedation should be avoided because central depressant action may coincide with the depression occurring late in atropine poisoning.
Central stimulants are not recommended. Physostigmine, given by slow intravenous injection of 1 to 4 mg (0.5 to 1 mg in pediatric populations), rapidly abolishes delirium and coma caused by large doses of atropine. Since physostigmine is rapidly destroyed, the patient may again lapse into coma after one to two hours, and repeated doses may be required.
Artificial respiration with oxygen may be necessary. Cooling measures may be needed to help to reduce fever, especially in pediatric populations. The fatal adult dose of atropine is not known.
In pediatric patients, 10 mg or less may be fatal.
🧬 Clinical Pharmacology ▾
12. CLINICAL PHARMACOLOGY
12.1Mechanism of Action Atropine is a reversible antagonist of muscarine-like actions of acetyl-choline and is therefore classified as an antimuscarinic agent. Atropine is relatively selective for muscarinic receptors. Its potency at nicotinic receptors is much lower, and actions at non-muscarinic receptors are generally undetectable clinically.
Atropine does not distinguish among the M1, M2, and M3 subgroups of muscarinic receptors. The pupillary constrictor muscle depends on muscarinic cholinoceptor activation. This activation is blocked by topical atropine resulting in unopposed sympathetic dilator activity and mydriasis.
Atropine also weakens the contraction of the ciliary muscle, or cycloplegia. Cycloplegia results in loss of the ability to accommodate such that the eye cannot focus for near vision.
12.2Pharmacodynamics The onset of action after administration of atropine sulfate ophthalmic solution 1%, is usually within 40 minutes with maximal effect being reached in about 2 hours. The effect can last for up to 2 weeks in a normal eye.
12.3Pharmacokinetics The bioavailability of atropine sulfate ophthalmic solution, 1% was assessed in six healthy subjects, 24 to 29 years of age. Subjects received either 0.3 mg atropine sulfate administered as bolus intravenous injection or 0.3 mg administered as 30 mcL instilled unilaterally in the cul-de-sac of the eye. Plasma l-hyoscyamine concentrations were determined over selected intervals up to eight hours after dose administration.
The mean bioavailability of topically applied atropine was 63.5 ± 29% (range 19 to 95%) with large inter-individual differences. Mean maximum observed plasma concentration for the ophthalmic solution was 288 ± 73 pg/mL. Maximum concentration was reached in 28 ± 27 min after administration.
Terminal half-life of l-hyoscamine was not affected by route of administration and was calculated to be 3 ± 1.2 hours (intravenous) and 2.5 ± 0.8 hours (topical ophthalmic). In another placebo-controlled study, the systemic exposure to l-hyoscyamine, and the anti-cholinergic effects of atropine were investigated in eight ocular surgery patients 56 to 66 years of age, following single topical ocular 0.4 mg atropine dose (given as 40 microliters of atropine sulfate ophthalmic solution, 1%). The mean (± standard deviation (SD)) C max of l-hyoscyamine in these patients was 860 ± 402 pg/mL, achieved within 8 minutes of eyedrop instillation.
Following intravenous administration, the mean (± SD) elimination half-life (t 1/2 ) of atropine was reported to be longer in pediatric subjects under 2 years (6.9 ± 3.3 hours) and in geriatric patients 65 to 75 years (10 ± 7.3 hours), compared to in children over 2 years (2.5 ± 1.2 hours) and in adults 16 to 58 years (3 ± 0.9 hours) [see Use in Specific Populations ( 8.4 )] . Atropine is destroyed by enzymatic hydrolysis, particularly in the liver; from 13 to 50% is excreted unchanged in the urine. Traces are found in various secretions, including milk.
The major metabolites of atropine are noratropine, atropin-n-oxide, tropine, and tropic acid. Atropine readily crosses the placental barrier and enters the fetal circulation but is not found in amniotic fluid. Atropine binds poorly (about 44%) to plasma protein, mainly to alpha-1 acid glycoprotein; age has no effect on the serum protein binding of atropine.
Atropine binding to α-1 acid glycoprotein was concentration dependent (2 to 20 mcg/mL) and nonlinear in vitro and in vivo . There is no gender effect on the pharmacokinetics of atropine administered by injection.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Atropine is a reversible antagonist of muscarine-like actions of acetyl-choline and is therefore classified as an antimuscarinic agent. Atropine is relatively selective for muscarinic receptors. Its potency at nicotinic receptors is much lower, and actions at non-muscarinic receptors are generally undetectable clinically.
Atropine does not distinguish among the M1, M2, and M3 subgroups of muscarinic receptors. The pupillary constrictor muscle depends on muscarinic cholinoceptor activation. This activation is blocked by topical atropine resulting in unopposed sympathetic dilator activity and mydriasis.
Atropine also weakens the contraction of the ciliary muscle, or cycloplegia. Cycloplegia results in loss of the ability to accommodate such that the eye cannot focus for near vision.
📦 How Supplied / Storage and Handling ▾
16. HOW SUPPLIED/STORAGE AND HANDLING Atropine sulfate ophthalmic solution, USP 1% is supplied in a plastic dropper bottle with a red cap in the following sizes: NDC 60505-6226-0 2 mL bottle NDC 60505-6226-1 5 mL bottle NDC 60505-6226-2 15 mL bottle Storage: Store at 20°C to 25°C (68°F to 77°F) [see USP Controlled Room Temperature]. Keep tightly closed. After opening, atropine sulfate ophthalmic solution can be used until the expiration date on the bottle.
📦 Storage and Handling ▾
Storage: Store at 20°C to 25°C (68°F to 77°F) [see USP Controlled Room Temperature]. Keep tightly closed. After opening, atropine sulfate ophthalmic solution can be used until the expiration date on the bottle.
📋 Description ▾
11. DESCRIPTION Atropine sulfate ophthalmic solution, USP 1% contains atropine an anticholinergic, in a sterile colorless, clear solution for topical ophthalmic use. The active ingredient is represented by the chemical structure Chemical Name: Benzeneacetic acid, α-(hydroxymethyl)-, 8-methyl-8-azabicyclo[3.2.1.]oct-3-yl ester, endo –(±)-, sulfate (2:1) (salt), monohydrate.
Molecular Formula: (C 17 H 23 NO 3 ) 2 •H 2 SO 4 •H 2 O Molecular Weight: 694.84 g/mol Atropine sulfate appears as white or almost white, crystalline powder, or colorless crystals. It is very soluble in water and freely soluble in ethanol (96%). Atropine sulfate ophthalmic solution, USP 1% is a clear, colorless, slightly viscous solution.
Each mL of Atropine Sulfate Ophthalmic Solution, USP 1% contains: Active : atropine sulfate 10 mg (equivalent to 8.3 mg of atropine). Inactives: benzalkonium chloride 0.1 mg (0.01%), edetate disodium dihydrate, hypromellose (methocel E4M premium), sodium phosphate dibasic heptahydrate, sodium phosphate monobasic monohydrate, hydrochloric acid and/or sodium hydroxide may be added to adjust pH (3.5 to 6.0), and water for injection USP. Chemical Structure
💬 Information for Patients ▾
17. PATIENT COUNSELING INFORMATION Risk of Contamination Advise patients not to touch the dropper tip to the eye, eyelids, or any other surface as this may contaminate the solution. Keep the bottle tightly closed.
Instillation Site Pain Advise patients that drops will sting upon instillation. Sensitivity to Light and Blurred Vision Advise patients that they will experience sensitivity to light and blurred vision which may last for a couple of weeks. Manufactured By Manufactured For Apotex Inc.
Apotex Corp. Toronto, Ontario Weston, Florida Canada M9L 1T9 USA 33326 Revised: March 2026 Rev. 5