
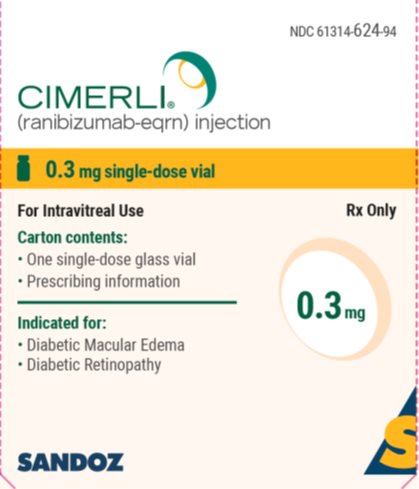
CIMERLI ranibizumab-eqrn .3 mg/.05mL Injection, Solution, 1 vial
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Vascular Endothelial Growth Factor Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ranibizumab implant is used to treat wet age-related macular degeneration (AMD; an eye disease that causes central vision loss [ability to see straight ahead]), diabetic macular edema (an eye disease caused by diabetes that can lead to vision loss) and diabetic retinopathy (damage to the eyes caused by diabetes). Ranibizumab is in a class of medications called vascular endothelial growth factor A (VEGF-A) antagonists. It works by stopping abnormal blood vessel growth and leakage in the eye(s) that may cause vision loss.
Read the full MedlinePlus article ↗- It's blocking a protein called VEGF-A that tells blood vessels in your eye to grow in abnormal ways and leak fluid — both of which can damage your retina and blur your vision. By b...
- What exactly is ranibizumab doing inside my eye?
- Both contain ranibizumab, but they're delivered differently. Lucentis is given as a direct injection into the eye on a schedule your doctor sets. Susvimo is a small implant surgica...
- What's the difference between Lucentis and Susvimo?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 4QD397987E
An amino acid used as a buffer and stabilizer in medications. It helps maintain the pH balance and protects the active drug from breaking down during storage and use.
-
UNII X573657P6P
Histidine monohydrochloride monohydrate is an amino acid salt used as a buffer in medicines. It helps maintain the proper acidity level of liquid formulations to keep the drug stable and effective.
-
UNII 7T1F30V5YH
A synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together and keeps them from separating in liquid formulations.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $9,625.82 | $481.29 / 0.05 ml |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · Q5128 | $82.528 / Q5128 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cimerli .3 mg/.05mLthis 61314-0624-94 | Sandoz | 1 vial | — | — | FDA listed | — |
| Cimerli .3 mg/.05mL 70114-0440-01 | Coherus | 1 vial | — | — | FDA listed | — |
Where does this data come from?
⏳ Availability & biosimilar status
3 interchangeables are FDA-licensed for this reference biologic — see the list below. (Biologics have no small-molecule generics.)
Why the date isn’t exact: Biosimilar timing can change because patents may be challenged, settled, licensed, added or removed, and litigation can move the real date earlier or later.
🛈 What do these terms mean?
- Biologic patent
- A patent the reference product’s maker has publicly listed. A biosimilar generally can’t launch until these expire — unless they’re invalidated or resolved in a settlement.
- Reference-product exclusivity
- A flat 12 years of FDA market protection from the biologic’s first licensure (the BPCIA). No biosimilar can be licensed before it ends, regardless of patents.
- Interchangeable exclusivity
- The first interchangeable biosimilar can earn a period as the only interchangeable version (pharmacists can substitute it without the prescriber).
- Earliest biosimilar (LOE)
- The latest of all the dates above — the soonest a biosimilar can realistically reach the market. Litigation and settlements can move it earlier.
Biologics have no small-molecule “generics” — competition comes from FDA-licensed biosimilars, tracked in the FDA Purple Book.
| Code | What it grants | Expires |
|---|---|---|
| RefProduct | Reference-product exclusivity (12-year, BPCIA) — no biosimilar can be licensed before this date | Aug 2, 2034 |
Is there a biosimilar for CIMERLI 0.3 MG/0.05 ML VIAL?
Why do different websites show different biosimilar dates?
Can a biosimilar launch before the last patent expires?
What does “current Purple Book estimate” mean?
What does “FDA listed” mean?
What does a patent or protection date mean here?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2025 (Q1-Q4)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 61314-0624-94 You're viewing this | 1 VIAL, SINGLE-DOSE in 1 CARTON (61314-624-94) / .05 mL in 1 VIAL, SINGLE-DOSE | 2024-12-12 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE CIMERLI is indicated for the treatment of patients with: CIMERLI, a vascular endothelial growth factor (VEGF) inhibitor, is indicated for the treatment of patients with: • Neovascular (Wet) Age-Related Macular Degeneration (AMD) ( 1.1 ) • Macular Edema Following Retinal Vein Occlusion (RVO) ( 1.2 ) • Diabetic Macular Edema (DME) ( 1.3 ) • Diabetic Retinopathy (DR) ( 1.4 ) • Myopic Choroidal Neovascularization (mCNV) ( 1.5 )
1.1 Neovascular (Wet) Age-Related Macular Degeneration (AMD)
1.2 Macular Edema Following Retinal Vein Occlusion (RVO)
1.3 Diabetic Macular Edema (DME)
1.4 Diabetic Retinopathy (DR)
1.5 Myopic Choroidal Neovascularization (mCNV)
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION For ophthalmic intravitreal injection only ( 2.1 ) • Neovascular (Wet) Age-Related Macular Degeneration (AMD) ( 2.2 ): CIMERLI 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days). • Although not as effective, patients may be treated with 3 monthly doses followed by less frequent dosing with regular assessment. • Although not as effective, patients may also be treated with one dose every 3 months after 4 monthly doses.
Patients should be assessed regularly. • Macular Edema Following Retinal Vein Occlusion (RVO) ( 2.3 ): CIMERLI 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days). • Diabetic Macular Edema (DME) and Diabetic Retinopathy (DR) ( 2.4 ): CIMERLI 0.3 mg (0.05 mL of 6 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days). • Myopic Choroidal Neovascularization (mCNV) ( 2.5 ): CIMERLI 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be initially administered by intravitreal injection once a month (approximately 28 days) for up to three months.
Patients may be retreated if needed.
2.1General Dosing Information FOR OPHTHALMIC INTRAVITREAL INJECTION. Vials : A 5-micron sterile filter needle (19-gauge × 1-1/2 inch), a 1-mL Luer lock syringe and a 30-gauge × 1/2 inch sterile injection needle are needed but not included.
2.2Neovascular (Wet) Age-Related Macular Degeneration (AMD) CIMERLI 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days). Although not as effective, patients may be treated with 3 monthly doses followed by less frequent dosing with regular assessment. In the 9 months after three initial monthly doses, less frequent dosing with 4-5 doses on average is expected to maintain visual acuity while monthly dosing may be expected to result in an additional average 1-2 letter gain.
Patients should be assessed regularly [see Clinical Studies ( 14.1 )] . Although not as effective, patients may also be treated with one dose every 3 months after 4 monthly doses. Compared with continued monthly dosing, dosing every 3 months over the next 9 months will lead to an approximate 5-letter (1-line) loss of visual acuity benefit, on average.
Patients should be assessed regularly [see Clinical Studies ( 14.1 )] .
2.3Macular Edema Following Retinal Vein Occlusion (RVO) CIMERLI 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days). In Studies RVO-1 and RVO-2, patients received monthly injections of ranibizumab for 6 months. In spite of being guided by optical coherence tomography and visual acuity re-treatment criteria, patients who were then not treated at Month 6 experienced on average, a loss of visual acuity at Month 7, whereas patients who were treated at Month 6 did not.
Patients should be treated monthly [see Clinical Studies ( 14.2 )] .
2.4Diabetic Macular Edema (DME) and Diabetic Retinopathy (DR) CIMERLI 0.3 mg (0.05 mL of 6 mg/mL solution) is recommended to be administered by intravitreal injection once a month (approximately 28 days).
2.5Myopic Choroidal Neovascularization (mCNV) CIMERLI 0.5 mg (0.05 mL of 10 mg/mL solution) is recommended to be initially administered by intravitreal injection once a month (approximately 28 days) for up to 3 months. Patients may be retreated if needed [see Clinical Studies ( 14.5 )] .
2.6Preparation for Administration Vial: Using aseptic technique, all of the CIMERLI vial contents are withdrawn through a 5-micron (19-gauge × 1-1/2 inch), sterile filter needle attached to a 1 mL syringe (not included). The filter needle should be discarded after withdrawal of the vial contents and should not be used for intravitreal injection. The filter needle should be replaced with a s…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Single-dose glass vial designed to provide 0.05 mL for intravitreal injection. • Colorless to pale yellow 10 mg/mL solution (0.5 mg) • Colorless to pale yellow 6 mg/mL solution (0.3 mg) • Single-dose glass vial designed to provide 0.05 mL for intravitreal injections: • 10 mg/mL solution (CIMERLI 0.5 mg) ( 3 ) • 6 mg/mL solution (CIMERLI 0.3 mg) ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Ocular or periocular infections ( 4.1 ) • Hypersensitivity ( 4.2 )
4.1Ocular or Periocular Infections CIMERLI is contraindicated in patients with ocular or periocular infections.
4.2Hypersensitivity CIMERLI is contraindicated in patients with known hypersensitivity to ranibizumab products or any of the excipients in CIMERLI. Hypersensitivity reactions may manifest as severe intraocular inflammation.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Endophthalmitis and retinal detachments may occur following intravitreal injections. Patients should be monitored following the injection ( 5.1 ). • Increases in intraocular pressure (IOP) have been noted both pre- and post-intravitreal injection ( 5.2 ). • There is a potential risk of arterial thromboembolic events following intravitreal use of VEGF inhibitors ( 5.3 ). • Fatal events occurred more frequently in patients with DME and DR at baseline, who were treated monthly with ranibizumab compared with control ( 5.4 ).
5.1Endophthalmitis and Retinal Detachments Intravitreal injections, including those with ranibizumab products, have been associated with endophthalmitis and retinal detachments. Proper aseptic injection technique should always be used when administering CIMERLI. In addition, patients should be monitored following the injection to permit early treatment should an infection occur [see Dosage and Administration ( 2.6 , 2.7) and Patient Counseling Information ( 17 )] .
5.2Increases in Intraocular Pressure Increases in intraocular pressure have been noted both pre-injection and post-injection (at 60 minutes) while being treated with ranibizumab products. Monitor intraocular pressure prior to and following intravitreal injection with CIMERLI and manage appropriately [see Dosage and Administration ( 2.7 )] .
5.3Thromboembolic Events Although there was a low rate of arterial thromboembolic events (ATEs) observed in the ranibizumab clinical trials, there is a potential risk of ATEs following intravitreal use of VEGF inhibitors. Arterial thromboembolic events are defined as nonfatal stroke, nonfatal myocardial infarction, or vascular death (including deaths of unknown cause). Neovascular (Wet) Age-Related Macular Degeneration The ATE rate in the three controlled neovascular AMD studies (AMD-1, AMD-2, AMD-3) during the first year was 1.9% (17 of 874) in the combined group of patients treated with 0.3 mg or 0.5 mg ranibizumab compared with 1.1% (5 of 441) in patients from the control arms [see Clinical Studies ( 14.1 )] .
In the second year of Studies AMD-1 and AMD-2, the ATE rate was 2.6% (19 of 721) in the combined group of ranibizumab-treated patients compared with 2.9% (10 of 344) in patients from the control arms. In Study AMD-4, the ATE rates observed in the 0.5 mg arms during the first and second year were similar to rates observed in Studies AMD-1, AMD-2, and AMD-3. In a pooled analysis of 2-year controlled studies [AMD-1, AMD-2, and a study of ranibizumab used adjunctively with verteporfin photodynamic therapy (PDT)], the stroke rate (including both ischemic and hemorrhagic stroke) was 2.7% (13 of 484) in patients treated with 0.5 mg ranibizumab compared to 1.1% (5 of 435) in patients in the control arms [odds ratio 2.2 (95% confidence interval (0.8-7.1)].
Macular Edema Following Retinal Vein Occlusion The ATE rate in the two controlled RVO studies during the first 6 months was 0.8% in both the ranibizumab and control arms of the studies (4 of 525 in the combined group of patients treated with 0.3 mg or 0.5 mg ranibizumab and 2 of 260 in the control arms) [see Clinical Studies ( 14.2 )] . The stroke rate was 0.2% (1 of 525) in the combined group of ranibizumab-treated patients compared to 0.4% (1 of 260) in the control arms. Diabetic Macular Edema and Diabetic Retinopathy Safety data are derived from studies D-1 and D-2.
All enrolled patients had DME and DR at baseline [see Clinical Studies ( 14.3 , 14.4) ] . In a pooled analysis of Studies D-1 and D-2 [see Clinical Studies ( 14.3 )] , the ATE rate at 2 years was 7.2% (18 of 250) with 0.5 mg ranibizumab, 5.6% (14 of 250) with 0.3 mg ranibizumab, and 5.2% (13 of 250) with control. The stroke rate at 2 years was 3.2% (8 of 250) with 0.5 mg ranibizumab, 1.2% (3 of 250) with 0.3 mg ranibizumab, and 1.6% (4 of 250) with control.
At 3 years, the ATE rate was 10.4% (26 of 249) with 0.5 mg ranibizumab and 10.8% (27 of 250) with 0.3 mg rani…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label: • Endophthalmitis and Retinal Detachments [see Warnings and Precautions ( 5.1 )] • Increases in Intraocular Pressure [see Warnings and Precautions ( 5.2 )] • Thromboembolic Events [see Warnings and Precautions ( 5.3 )] • Fatal Events in patients with DME and DR at baseline [see Warnings and Precautions ( 5.4 )] The most common adverse reactions (reported more frequently in ranibizumab-treated subjects than control subjects) are conjunctival hemorrhage, eye pain, vitreous floaters, and increased IOP ( 6.2 ).
To report SUSPECTED ADVERSE REACTIONS, contact Sandoz Inc. at 1-800-525-8747 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Injection Procedure Serious adverse reactions related to the injection procedure have occurred in < 0.1% of intravitreal injections, including endophthalmitis [see Warnings and Precautions ( 5.1 )] , rhegmatogenous retinal detachment, and iatrogenic traumatic cataract.
6.2Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data below reflect exposure to 0.5 mg ranibizumab in 440 patients with neovascular AMD in Studies AMD-1, AMD-2, and AMD-3; in 259 patients with macular edema following RVO. The data also reflect exposure to 0.3 mg ranibizumab in 250 patients with DME and DR at baseline [see Clinical Studies ( 14 )] .
Safety data observed in 224 patients with mCNV, as well as Studies AMD-4 and D-3, were consistent with these results. On average, the rates and types of adverse reactions in patients were not significantly affected by dosing regimen. Ocular Reactions Table 1 shows frequently reported ocular adverse reactions in ranibizumab-treated patients compared with the control group.
Table 1 Ocular Reactions in the DME and DR, AMD, and RVO Studies Adverse Reaction DME and DR 2-year AMD 2-year AMD 1-year RVO 6-month Ranibizumab 0.3 mg Control Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control n=250 n=250 n=379 n=379 n=440 n=441 n=259 n=260 Conjunctival hemorrhage 47% 32% 74% 60% 64% 50% 48% 37% Eye pain 17% 13% 35% 30% 26% 20% 17% 12% Vitreous floaters 10% 4% 27% 8% 19% 5% 7% 2% Intraocular pressure increased 18% 7% 24% 7% 17% 5% 7% 2% Vitreous detachment 11% 15% 21% 19% 15% 15% 4% 2% Intraocular inflammation 4% 3% 18% 8% 13% 7% 1% 3% Cataract 28% 32% 17% 14% 11% 9% 2% 2% Foreign body sensation in eyes 10% 5% 16% 14% 13% 10% 7% 5% Eye irritation 8% 5% 15% 15% 13% 12% 7% 6% Lacrimation increased 5% 4% 14% 12% 8% 8% 2% 3% Blepharitis 3% 2% 12% 8% 8% 5% 0% 1% Dry eye 5% 3% 12% 7% 7% 7% 3% 3% Visual disturbance or vision blurred 8% 4% 18% 15% 13% 10% 5% 3% Eye pruritis 4% 4% 12% 11% 9% 7% 1% 2% Ocular hyperemia 9% 9% 11% 8% 7% 4% 5% 3% Retinal disorder 2% 2% 10% 7% 8% 4% 2% 1% Maculopathy 5% 7% 9% 9% 6% 6% 11% 7% Retinal degeneration 1% 0% 8% 6% 5% 3% 1% 0% Ocular discomfort 2% 1% 7% 4% 5% 2% 2% 2% Conjunctival hyperemia 1% 2% 7% 6% 5% 4% 0% 0% Posterior capsule opacification 4% 3% 7% 4% 2% 2% 0% 1% Injection site hemorrhage 1% 0% 5% 2% 3% 1% 0% 0% Non-Ocular Reactions Non-ocular adverse reactions with an incidence of ≥ 5% in patients receiving ranibizumab for DR, DME, AMD, and/or RVO and which occurred at a ≥ 1% higher frequency in patients treated with ranibizumab compared to control are shown in Table 2.
Though less common, wound healing complications were also observed in some studies. Table 2 Non-Ocular Reactions in the DME and DR, AMD, and RVO Studies Adverse Reaction DME and DR 2-year AMD 2-year AMD 1-year RVO 6-month Ranibizumab 0.3 mg Control Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control Ranibizumab 0.5 mg Control n=250 n=250 n=379 n=379 n=440 n=441 n=259 n=260 Nasopharyngitis 12% 6% 16% 13% 8% 9%…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Drug interaction studies have not been conducted with ranibizumab products. Ranibizumab intravitreal injection has been used adjunctively with PDT. Twelve of 105 (11%) patients with neovascular AMD developed serious intraocular inflammation; in 10 of the 12 patients, this occurred when ranibizumab was administered 7 days (± 2 days) after PDT.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of ranibizumab products administered in pregnant women. Administration of ranibizumab to pregnant monkeys throughout the period of organogenesis resulted in a low incidence of skeletal abnormalities at intravitreal doses 13-times the predicted human exposure (based on maximal serum trough levels [C max ]) after a single eye treatment at the recommended clinical dose. No skeletal abnormalities were observed at serum trough levels equivalent to the predicted human exposure after a single eye treatment at the recommended clinical dose [see Animal Data] .
Animal reproduction studies are not always predictive of human response, and it is not known whether ranibizumab products can cause fetal harm when administered to a pregnant woman. Based on the anti-VEGF mechanism of action for ranibizumab products [see Clinical Pharmacology ( 12.1 )] , treatment with ranibizumab products may pose a risk to human embryofetal development. CIMERLI should be given to a pregnant woman only if clearly needed.
Data Animal Data An embryo-fetal developmental toxicity study was performed on pregnant cynomolgus monkeys. Pregnant animals received intravitreal injections of ranibizumab every 14 days starting on Day 20 of gestation, until Day 62 at doses of 0, 0.125, and 1 mg/eye. Skeletal abnormalities including incomplete and/or irregular ossification of bones in the skull, vertebral column, and hindlimbs and shortened supernumerary ribs were seen at a low incidence in fetuses from animals treated with 1 mg/eye of ranibizumab.
The 1 mg/eye dose resulted in trough serum ranibizumab levels up to 13 times higher than predicted C max levels with single eye treatment in humans. No skeletal abnormalities were seen at the lower dose of 0.125 mg/eye, a dose which resulted in trough exposures equivalent to single eye treatment in humans. No effect on the weight or structure of the placenta, maternal toxicity, or embryotoxicity was observed.
8.2Lactation Risk Summary There are no data available on the presence of ranibizumab products in human milk, the effects of ranibizumab products on the breastfed infant or the effects of ranibizumab products on milk production/excretion. Because many drugs are excreted in human milk, and because the potential for absorption and harm to infant growth and development exists, caution should be exercised when CIMERLI is administered to a nursing woman. The developmental and health benefits of breastfeeding should be considered along with the mother's clinical need for CIMERLI and any potential adverse effects on the breastfed child from CIMERLI.
8.3Females and Males of Reproductive Potential Infertility No studies on the effects of ranibizumab products on fertility have been conducted and it is not known whether ranibizumab products can affect reproduction capacity. Based on the anti-VEGF mechanism of action for ranibizumab products, treatment with ranibizumab products may pose a risk to reproductive capacity.
8.4Pediatric Use The safety and effectiveness of CIMERLI in pediatric patients have not been established.
8.5Geriatric Use In the clinical studies, approximately 76% (2449 of 3227) of patients randomized to treatment with ranibizumab were ≥ 65 years of age and approximately 51% (1644 of 3227) were ≥ 75 years of age [see Clinical Studies ( 14 )] . No notable differences in efficacy or safety were seen with increasing age in these studies. Age did not have a significant effect on systemic exposure.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate and well-controlled studies of ranibizumab products administered in pregnant women. Administration of ranibizumab to pregnant monkeys throughout the period of organogenesis resulted in a low incidence of skeletal abnormalities at intravitreal doses 13-times the predicted human exposure (based on maximal serum trough levels [C max ]) after a single eye treatment at the recommended clinical dose. No skeletal abnormalities were observed at serum trough levels equivalent to the predicted human exposure after a single eye treatment at the recommended clinical dose [see Animal Data] .
Animal reproduction studies are not always predictive of human response, and it is not known whether ranibizumab products can cause fetal harm when administered to a pregnant woman. Based on the anti-VEGF mechanism of action for ranibizumab products [see Clinical Pharmacology ( 12.1 )] , treatment with ranibizumab products may pose a risk to human embryofetal development. CIMERLI should be given to a pregnant woman only if clearly needed.
Data Animal Data An embryo-fetal developmental toxicity study was performed on pregnant cynomolgus monkeys. Pregnant animals received intravitreal injections of ranibizumab every 14 days starting on Day 20 of gestation, until Day 62 at doses of 0, 0.125, and 1 mg/eye. Skeletal abnormalities including incomplete and/or irregular ossification of bones in the skull, vertebral column, and hindlimbs and shortened supernumerary ribs were seen at a low incidence in fetuses from animals treated with 1 mg/eye of ranibizumab.
The 1 mg/eye dose resulted in trough serum ranibizumab levels up to 13 times higher than predicted C max levels with single eye treatment in humans. No skeletal abnormalities were seen at the lower dose of 0.125 mg/eye, a dose which resulted in trough exposures equivalent to single eye treatment in humans. No effect on the weight or structure of the placenta, maternal toxicity, or embryotoxicity was observed.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of CIMERLI in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use In the clinical studies, approximately 76% (2449 of 3227) of patients randomized to treatment with ranibizumab were ≥ 65 years of age and approximately 51% (1644 of 3227) were ≥ 75 years of age [see Clinical Studies ( 14 )] . No notable differences in efficacy or safety were seen with increasing age in these studies. Age did not have a significant effect on systemic exposure.
🆘 Overdosage ▾
10 OVERDOSAGE More concentrated doses as high as 2 mg ranibizumab in 0.05 mL have been administered to patients. No additional unexpected adverse reactions were seen.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ranibizumab products bind to the receptor binding site of active forms of VEGF-A, including the biologically active, cleaved form of this molecule, VEGF 110 . VEGF-A has been shown to cause neovascularization and leakage in models of ocular angiogenesis and vascular occlusion and is thought to contribute to pathophysiology of neovascular AMD, mCNV, DR, DME and macular edema following RVO. The binding of ranibizumab products to VEGF-A prevents the interaction of VEGF-A with its receptors (VEGFR1 and VEGFR2) on the surface of endothelial cells, reducing endothelial cell proliferation, vascular leakage, and new blood vessel formation.
12.2Pharmacodynamics Increased retinal thickness (i.e., center point thickness (CPT) or central foveal thickness (CFT)), as assessed by optical coherence tomography (OCT) is associated with neovascular AMD, mCNV, macular edema following RVO, and DME. Leakage from choroidal neovascularization (CNV) as assessed by fluorescein angiography (FA) is associated with neovascular AMD and mCNV. Microvascular retinal changes and neovascularization, as assessed by color fundus photography, are associated with diabetic retinopathy.
Neovascular (Wet) Age-Related Macular Degeneration In Study AMD-3, CPT was assessed by time domain (TD)-OCT in 118 of 184 patients. TD-OCT measurements were collected at baseline, Months 1, 2, 3, 5, 8, and 12. In patients treated with ranibizumab, CPT decreased, on average, more than in the sham group from baseline through Month 12.
CPT decreased by Month 1 and decreased further at Month 3, on average. In this study, CPT data did not provide information useful in influencing treatment decisions [see Clinical Studies ( 14.1 )] . In Study AMD-4, CFT was assessed by spectral domain (SD)-OCT in all patients; on average, CFT reductions were observed beginning at Day 7 following the first ranibizumab injection through Month 24.
CFT data did not provide information capable of predicting final visual acuity results [see Clinical Studies ( 14.1 )] . In patients treated with ranibizumab, the area of CNV leakage, on average, decreased by Month 3 as assessed by FA. The area of CNV leakage for an individual patient was not correlated with visual acuity.
Macular Edema Following Retinal Vein Occlusion On average, CPT reductions were observed in Studies RVO-1 and RVO-2 beginning at Day 7 following the first ranibizumab injection through Month 6. CPT was not evaluated as a means to guide treatment decisions [see Clinical Studies ( 14.2 )] . Diabetic Macular Edema On average, CPT reductions were observed in Studies D-1 and D-2 beginning at Day 7 following the first ranibizumab injection through Month 36.
CPT data did not provide information useful in influencing treatment decisions [see Clinical Studies ( 14.3 )] . Diabetic Retinopathy Improvements from baseline in DR severity as assessed on fundus photography were observed in Studies D-1 and D-2 at Month 3 (first scheduled DR photographic assessment after randomization) through Month 36 [see Clinical Studies ( 14.4 )] . Myopic Choroidal Neovascularization On average CFT reductions were observed as early as Month 1, and were greater in the ranibizumab groups compared to PDT [see Clinical Studies ( 14.5 )] .
12.3Pharmacokinetics In patients with neovascular AMD, following monthly intravitreal administration of 0.5 mg ranibizumab, mean (±SD) maximum ranibizumab serum concentrations were 1.7 (± 1.1) ng/mL. These concentrations were below the concentration range of ranibizumab (11 to 27 ng/mL) that was necessary to inhibit the biological activity of VEGF-A by 50%, as measured in an in vitro cellular proliferation assay (based on human umbilical vein endothelial cells (HUVEC)). No significant change from baseline was observed in the mean plasma VEGF concentrations following three monthly 0.5 mg intravitreal injections.
The maximum observed serum concentration was dose proportional over the dose range of 0.…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ranibizumab products bind to the receptor binding site of active forms of VEGF-A, including the biologically active, cleaved form of this molecule, VEGF 110 . VEGF-A has been shown to cause neovascularization and leakage in models of ocular angiogenesis and vascular occlusion and is thought to contribute to pathophysiology of neovascular AMD, mCNV, DR, DME and macular edema following RVO. The binding of ranibizumab products to VEGF-A prevents the interaction of VEGF-A with its receptors (VEGFR1 and VEGFR2) on the surface of endothelial cells, reducing endothelial cell proliferation, vascular leakage, and new blood vessel formation.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING CIMERLI (ranibizumab-eqrn) injection is a colorless to pale yellow solution supplied in: • Each CIMERLI 0.5 mg carton (NDC 61314-625-94) contains a single-dose, 2-mL glass vial with a BLUE CAP designed to deliver 0.05 mL of 10 mg/mL ranibizumab-eqrn solution. • Each CIMERLI 0.3 mg carton (NDC 61314-624-94) contains a single-dose, 2-mL glass vial with a WHITE CAP designed to deliver 0.05 mL of 6 mg/mL ranibizumab-eqrn solution. EACH CARTON IS FOR SINGLE-EYE USE ONLY. CIMERLI should be refrigerated at 2°C to 8°C (36°F to 46°F).
DO NOT FREEZE. Do not use beyond the expiry date stamped on the label. Protect CIMERLI vials from light and store in the original carton until time of use.
📦 Storage and Handling ▾
CIMERLI should be refrigerated at 2°C to 8°C (36°F to 46°F). DO NOT FREEZE. Do not use beyond the expiry date stamped on the label. Protect CIMERLI vials from light and store in the original carton until time of use.
📋 Description ▾
11 DESCRIPTION Ranibizumab-eqrn is a recombinant humanized IgG1 kappa isotype monoclonal antibody fragment designed for intraocular use. Ranibizumab-eqrn binds to and inhibits the biologic activity of human vascular endothelial growth factor A (VEGF-A). Ranibizumab-eqrn, which lacks an Fc region, has a molecular weight of approximately 48 kilodaltons and is produced by an E. coli expression system.
CIMERLI (ranibizumab-eqrn) injection is a sterile, colorless to pale yellow solution in a single-dose glass vial for intravitreal injection. CIMERLI is supplied as a preservative-free, sterile solution in a single-dose container designed to deliver 0.05 mL of 10 mg/mL ranibizumab-eqrn (0.5 mg dose vial) or 6 mg/mL ranibizumab-eqrn (0.3 mg dose vial) aqueous solution with 10 mM histidine HCl, 10% α,α trehalose dihydrate, 0.01% polysorbate 20, pH 5.5.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients that in the days following CIMERLI administration, patients are at risk of developing endophthalmitis and retinal vasculitis with or without occlusion. If the eye becomes red, sensitive to light, painful, or develops a change in vision, advise the patient to seek immediate care from an ophthalmologist [see Warnings and Precautions ( 5.1 , 5.5) ] .