
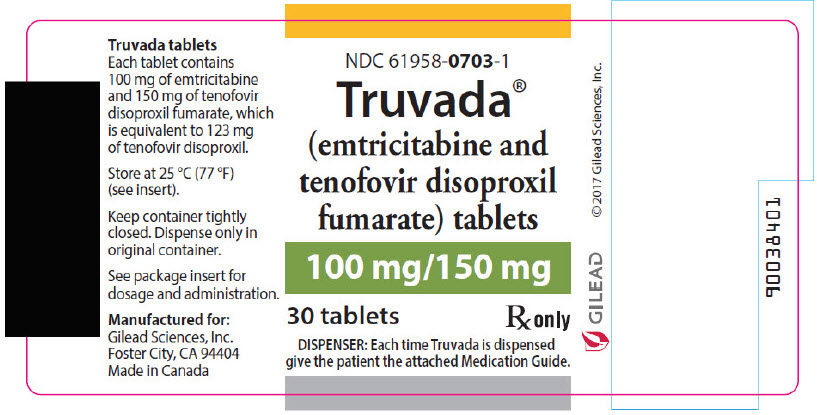
Truvada emtricitabine and tenofovir disoproxil fumarate 100 mg; 150 mg Tablet, Film Coated, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Human Immunodeficiency Virus Nucleoside Analog Reverse Transcriptase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- If you already have HIV-1, this medication is part of your treatment — taken every day alongside other antivirals to keep the virus suppressed. PrEP is for people who are HIV-negat...
- What exactly is the difference between using this for HIV treatment versus PrEP?
- Please don't stop without talking to your doctor first. If you also have hepatitis B, stopping suddenly can trigger a serious and potentially dangerous flare-up of that infection....
- Common things like nausea, headache, diarrhea, and trouble sleeping often improve in the first few weeks. The ones that need immediate attention are symptoms that could signal a ra...
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $61.17 | $1,835.05 / 30 tablets |
| Medicare Part B allowsASP · J0750 | $0.453 / J0750 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Emtricitabine and Tenofovir Disoproxil Fumarate 100 mg/1; 150 mg 59651-0165-30 | Aurobindo | 30 tablets | $10.195 | AB | Availability likely | — |
| Emtricitabine and Tenofovir Disoproxil Fumarate 100 mg/1; 150 mg 69238-2092-03 | Amneal | 30 tablets | $10.195 | AB | Availability likely | — |
| Emtricitabine and tenofovir disoproxil fumarate 100 mg/1; 150 mg 70710-1364-03 | Zydus | 30 tablets | $10.195 | AB | Availability likely | — |
| Truvada 100 mg/1; 150 mgthis 61958-0703-01 | Gilead | 30 tablets | — | AB | FDA listed | — |
| Emtricitabine and tenofovir disoproxil fumarate 100 mg/1; 150 mg 70771-1620-03 | Zydus | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 61958-0703-01 You're viewing this | 30 TABLET, FILM COATED in 1 BOTTLE, PLASTIC (61958-0703-1) | 2016-03-10 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Does this product have a billing J-code?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B and RISK OF DRUG RESISTANCE WITH USE OF TRUVADA FOR HIV-1 PRE-EXPOSURE PROPHYLAXIS (PrEP) IN UNDIAGNOSED EARLY HIV-1 INFECTION Severe acute exacerbations of hepatitis B (HBV) have been reported in HBV-infected individuals who have discontinued TRUVADA. Hepatic function should be monitored closely with both clinical and laboratory follow-up for at least several months in individuals who are infected with HBV and discontinue TRUVADA. If appropriate, anti-hepatitis B therapy may be warranted [see Warnings and Precautions (5.1) ] .
TRUVADA used for HIV-1 PrEP must only be prescribed to individuals confirmed to be HIV-negative immediately prior to initiating and at least every 3 months during use. Drug-resistant HIV-1 variants have been identified with use of TRUVADA for HIV-1 PrEP following undetected acute HIV-1 infection. Do not initiate TRUVADA for HIV-1 PrEP if signs or symptoms of acute HIV-1 infection are present unless negative infection status is confirmed [see Warnings and Precautions (5.2) ] .
WARNING: POSTTREATMENT ACUTE EXACERBATION OF HEPATITIS B and RISK OF DRUG RESISTANCE WITH USE OF TRUVADA FOR HIV-1 PRE-EXPOSURE PROPHYLAXIS (PrEP) IN UNDIAGNOSED EARLY HIV-1 INFECTION See full prescribing information for complete boxed warning. Severe acute exacerbations of hepatitis B (HBV) have been reported in HBV-infected individuals who have discontinued TRUVADA. Hepatic function should be monitored closely in these individuals who discontinue TRUVADA.
If appropriate anti-hepatitis B therapy may be warranted. ( 5.1 ) TRUVADA used for HIV-1 PrEP must only be prescribed to individuals confirmed to be HIV-negative immediately prior to initiating and at least every 3 months during use. Drug-resistant HIV-1 variants have been identified with the use of TRUVADA for HIV-1 PrEP following undetected acute HIV-1 infection.
Do not initiate TRUVADA for HIV-1 PrEP if signs or symptoms of acute HIV infection are present unless negative infection status is confirmed. ( 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE HIV-1 Treatment ( 1.1 ) TRUVADA is a two-drug combination of emtricitabine (FTC) and tenofovir disoproxil fumarate (TDF), both HIV-1 nucleoside analog reverse transcriptase inhibitors, and is indicated: in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients weighing at least 17 kg. HIV-1 PrEP ( 1.2 ): TRUVADA is indicated in at-risk adults and adolescents weighing at least 35 kg for pre-exposure prophylaxis (PrEP) to reduce the risk of sexually acquired HIV-1 infection.
Individuals must have a negative HIV-1 test immediately prior to initiating TRUVADA for HIV-1 PrEP.
1.1Treatment of HIV-1 Infection TRUVADA is indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection in adults and pediatric patients weighing at least 17 kg [see Clinical Studies (14) ] .
1.2HIV-1 Pre-Exposure Prophylaxis (PrEP) TRUVADA is indicated in at-risk adults and adolescents weighing at least 35 kg for pre-exposure prophylaxis (PrEP) to reduce the risk of sexually acquired HIV-1 infection. Individuals must have a negative HIV-1 test immediately prior to initiating TRUVADA for HIV-1 PrEP [see Dosage and Administration (2.2) , Warnings and Precautions (5.2) ] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Testing: Prior to or when initiating TRUVADA test for hepatitis B virus infection. Prior to initiation and during use of TRUVADA, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose, and urine protein in all individuals. In individuals with chronic kidney disease, also assess serum phosphorus.
( 2.1 ) HIV-1 Screening: Screen all individuals for HIV-1 infection immediately prior to initiating TRUVADA for HIV-1 PrEP and at least once every 3 months while taking TRUVADA, and upon diagnosis of any other sexually transmitted infections (STIs). ( 2.2 ) Treatment of HIV-1 Infection Recommended dosage in adults and pediatric patients weighing at least 35 kg: One TRUVADA tablet (containing 200 mg of FTC and 300 mg of TDF) once daily taken orally with or without food. ( 2.3 ) Recommended dosage in pediatric patients weighing at least 17 kg: One TRUVADA low-strength tablet (100 mg/150 mg, 133 mg/200 mg, or 167 mg/250 mg based on body weight) once daily taken orally with or without food.
( 2.4 ) Recommended dosage in renally impaired HIV-1 infected adult patients: Creatinine clearance (CrCl) 30−49 mL/min: 1 tablet every 48 hours. ( 2.6 ) CrCl below 30 mL/min or hemodialysis: TRUVADA is not recommended. ( 2.6 ) HIV-1 Pre-Exposure Prophylaxis (PrEP) Recommended dosage in HIV-1 uninfected adults and adolescents weighing at least 35 kg: One TRUVADA tablet (containing 200 mg of FTC and 300 mg of TDF) once daily taken orally with or without food.
( 2.5 ) Recommended dosage in renally impaired HIV-uninfected individuals: TRUVADA is not recommended in HIV-uninfected individuals if CrCl is below 60 mL/min. ( 2.6 )
2.1Testing Prior to Initiation of TRUVADA for Treatment of HIV-1 Infection or for HIV-1 PrEP Prior to or when initiating TRUVADA, test individuals for hepatitis B virus infection [see Warnings and Precautions (5.1) ] . Prior to initiation, and during use of TRUVADA, on a clinically appropriate schedule, assess serum creatinine, estimated creatinine clearance, urine glucose, and urine protein in all individuals. In individuals with chronic kidney disease, also assess serum phosphorus [see Warnings and Precautions (5.3) ].
2.2HIV-1 Screening for Individuals Receiving TRUVADA for HIV-1 PrEP Screen all individuals for HIV-1 infection immediately prior to initiating TRUVADA for HIV-1 PrEP and at least once every 3 months while taking TRUVADA, and upon diagnosis of any other sexually transmitted infections (STIs) [see Indications and Usage (1.2) , Contraindications (4) , and Warnings and Precautions (5.2) ]. If recent (<1 month) exposures to HIV-1 are suspected or clinical symptoms consistent with acute HIV-1 infection are present, use a test approved or cleared by the FDA as an aid in the diagnosis of acute or primary HIV-1 infection [see Warnings and Precautions (5.2) , Use in Specific Populations (8.4) , and Clinical Studies (14.3 and 14.4) ].
2.3Recommended Dosage for Treatment of HIV-1 Infection in Adults and Pediatric Patients Weighing at Least 35 kg TRUVADA is a two-drug fixed dose combination product containing emtricitabine (FTC) and tenofovir disoproxil fumarate (TDF). The recommended dosage of TRUVADA in adults and in pediatric patients weighing at least 35 kg is one tablet (containing 200 mg of FTC and 300 mg of TDF) once daily taken orally with or without food [see Clinical Pharmacology (12.3) ] .
2.4Recommended Dosage for Treatment of HIV-1 Infection in Pediatric Patients Weighing at Least 17 kg and Able to Swallow a Tablet The recommended oral dosage of TRUVADA for pediatric patients weighing at least 17 kg and who can swallow a tablet is presented in Table 1. Tablets should be taken once daily with or without food. Weight should be monitored periodically and the TRUVADA dose adjusted accordingly.
Table 1 Dosing for Treatment of HIV-1 Infection in Pediatric Patients Weighing 17 kg to less than 35 kg Body Weight (kg) Dosing of TRUVADA (FTC/TD…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS TRUVADA tablets are available in four dose strengths. 100 mg/150 mg Tablets: 100 mg of emtricitabine (FTC) and 150 mg of tenofovir disoproxil fumarate (TDF) (equivalent to 123 mg of tenofovir disoproxil): blue, oval shaped, film coated, debossed with "GSI" on one side and with "703" on the other side. 133 mg/200 mg Tablets: 133 mg of FTC and 200 mg of TDF (equivalent to 163 mg of tenofovir disoproxil): blue, rectangular shaped, film coated, debossed with "GSI" on one side and with "704" on the other side.
167 mg/250 mg Tablets: 167 mg of FTC and 250 mg of TDF (equivalent to 204 mg of tenofovir disoproxil): blue, modified capsule shaped, film coated, debossed with "GSI" on one side and with "705" on the other side. 200 mg/300 mg Tablets: 200 mg of FTC and 300 mg of TDF (equivalent to 245 mg of tenofovir disoproxil): blue, capsule shaped, film coated, debossed with "GILEAD" on one side and with "701" on the other side. Tablets: 200 mg/300 mg, 167 mg/250 mg, 133 mg/200 mg, and 100 mg/150 mg of emtricitabine and tenofovir disoproxil fumarate, respectively.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS TRUVADA for HIV-1 PrEP is contraindicated in individuals with unknown or positive HIV-1 status [see Warnings and Precautions (5.2) ] . TRUVADA for HIV-1 PrEP is contraindicated in individuals with unknown or positive HIV-1 status. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Comprehensive management to reduce the risk of acquiring HIV-1 when TRUVADA is used for HIV-1 PrEP: Use as part of a comprehensive prevention strategy including other prevention measures; strictly adhere to dosing schedule. ( 5.2 ) Management to reduce the risk of acquiring HIV-1 drug resistance when TRUVADA is used for HIV-1 PrEP: refer to full prescribing information for additional detail. ( 5.2 ) New onset or worsening renal impairment: Can include acute renal failure and Fanconi syndrome.
Avoid administering TRUVADA with concurrent or recent use of nephrotoxic drugs. ( 5.3 ) Immune reconstitution syndrome during treatment of HIV-1 infection: May necessitate further evaluation and treatment. ( 5.4 ) Decreases in bone mineral density (BMD): Consider assessment of BMD in individuals with a history of pathologic fracture or other risk factors for osteoporosis or bone loss.
( 5.5 ) Lactic acidosis/severe hepatomegaly with steatosis: Discontinue TRUVADA in individuals who develop symptoms or laboratory findings suggestive of lactic acidosis or pronounced hepatotoxicity. ( 5.6 )
5.1Severe Acute Exacerbation of Hepatitis B in Individuals with HBV Infection All individuals should be tested for the presence of chronic hepatitis B virus (HBV) before or when initiating TRUVADA [see Dosage and Administration (2.1) ] . Severe acute exacerbations of hepatitis B (e.g., liver decompensation and liver failure) have been reported in HBV-infected individuals who have discontinued TRUVADA. Individuals infected with HBV who discontinue TRUVADA should be closely monitored with both clinical and laboratory follow-up for at least several months after stopping treatment.
If appropriate, anti-hepatitis B therapy may be warranted, especially in individuals with advanced liver disease or cirrhosis, since posttreatment exacerbation of hepatitis may lead to hepatic decompensation and liver failure. HBV-uninfected individuals should be offered vaccination.
5.2Comprehensive Management to Reduce the Risk of Sexually Transmitted Infections, Including HIV-1, and Development of HIV-1 Resistance When TRUVADA Is Used for HIV-1 PrEP Use TRUVADA for HIV-1 PrEP to reduce the risk of HIV-1 infection as part of a comprehensive prevention strategy that includes other prevention measures, including adherence to daily administration and safer sex practices, including condoms, to reduce the risk of sexually transmitted infections (STIs). The time from initiation of TRUVADA for HIV-1 PrEP to maximal protection against HIV-1 infection is unknown .
Risk for HIV-1 acquisition includes behavioral, biological, or epidemiologic factors including but not limited to condomless sex, past or current STIs, self-identified HIV risk, having sexual partners of unknown HIV-1 viremic status, or sexual activity in a high prevalence area or network. Counsel individuals on the use of other prevention measures (e.g., consistent and correct condom use, knowledge of partner(s)' HIV-1 status, including viral suppression status, regular testing for STIs that can facilitate HIV-1 transmission).
Inform uninfected individuals about and support their efforts in reducing sexual risk behavior. Use TRUVADA to reduce the risk of acquiring HIV-1 only in individuals confirmed to be HIV-negative . HIV-1 resistance substitutions may emerge in individuals with undetected HIV-1 infection who are taking only TRUVADA, because TRUVADA alone does not constitute a complete regimen for HIV-1 treatment [see Microbiology (12.4) ]; therefore, care should be taken to minimize the risk of initiating or continuing TRUVADA before confirming the individual is HIV-1 negative.
Some HIV-1 tests only detect anti-HIV antibodies and may not identify HIV-1 during the acute stage of infection. Prior to initiating TRUVADA for HIV-1 PrEP, ask seronegative individuals about recent (in past month) potential exposure events (e.g., condomless sex or condom breaking during sex with a partner of unknown HIV-1…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in other sections of the labeling: Severe Acute Exacerbations of Hepatitis B in Patients with HBV Infection [see Warnings and Precautions (5.1) ] . New Onset or Worsening Renal Impairment [see Warnings and Precautions (5.3) ] . Immune Reconstitution Syndrome [see Warnings and Precautions (5.4) ] .
Bone Loss and Mineralization Defects [see Warnings and Precautions (5.5) ] . Lactic Acidosis/Severe Hepatomegaly with Steatosis [see Warnings and Precautions (5.6) ] . In HIV-1 infected patients, the most common adverse reactions (incidence greater than or equal to 10%) are diarrhea, nausea, fatigue, headache, dizziness, depression, insomnia, abnormal dreams, and rash.
( 6.1 ) In HIV-1 uninfected adults in PrEP trials, adverse reactions that were reported by more than 2% of TRUVADA participants and more frequently than by placebo participants were headache, abdominal pain, and weight decreased. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Gilead Sciences, Inc. at 1-800-445-3235 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions from Clinical Trials Experience in HIV-1 Infected Subjects Clinical Trials in Adult Subjects In Study 934, 511 antiretroviral-naïve subjects received efavirenz (EFV) administered in combination with either FTC+TDF (N=257) or zidovudine (AZT)/lamivudine (3TC) (N=254) for 144 weeks.
The most common adverse reactions (incidence greater than or equal to 10%, all grades) included diarrhea, nausea, fatigue, headache, dizziness, depression, insomnia, abnormal dreams, and rash. Table 3 provides the treatment-emergent adverse reactions (Grades 2–4) occurring in greater than or equal to 5% of subjects treated in any treatment group. Skin discoloration, manifested by hyperpigmentation, occurred in 3% of subjects taking FTC+TDF, and was generally mild and asymptomatic.
The mechanism and clinical significance are unknown. Table 3 Selected Adverse Reactions Frequencies of adverse reactions are based on all treatment-emergent adverse events, regardless of relationship to study drug. (Grades 2–4) Reported in ≥5% in Any Treatment Group in Study 934 (0–144 Weeks) FTC+TDF+EFV From Weeks 96 to 144 of the trial, subjects received TRUVADA with efavirenz in place of FTC+TDF with efavirenz.
AZT/3TC+EFV N=257 N=254 Fatigue 9% 8% Depression 9% 7% Nausea 9% 7% Diarrhea 9% 5% Dizziness 8% 7% Upper respiratory tract infections 8% 5% Sinusitis 8% 4% Rash event Rash event includes rash, exfoliative rash, rash generalized, rash macular, rash maculo-papular, rash pruritic, and rash vesicular. 7% 9% Headache 6% 5% Insomnia 5% 7% Nasopharyngitis 5% 3% Vomiting 2% 5% Laboratory Abnormalities: Laboratory abnormalities observed in this trial were generally consistent with those seen in other trials of TDF and/or FTC (Table 4).
Table 4 Significant Laboratory Abnormalities Reported in ≥1% of Subjects in Any Treatment Group in Study 934 (0–144 Weeks) FTC+TDF+EFV From Weeks 96 to 144 of the trial, subjects received TRUVADA with efavirenz in place of FTC+TDF with efavirenz. AZT/3TC+EFV N=257 N=254 Any ≥ Grade 3 Laboratory Abnormality 30% 26% Fasting Cholesterol (>240 mg/dL) 22% 24% Creatine Kinase (M: >990 U/L) (F: >845 U/L) 9% 7% Serum Amylase (>175 U/L) 8% 4% Alkaline Phosphatase (>550 U/L) 1% 0% AST (M: >180 U/L) (F: >170 U/L) 3% 3% ALT (M: >215 U/L) (F: >170 U/L) 2% 3% Hemoglobin (<8.0 mg/dL) 0% 4% Hyperglycemia (>250 mg/dL) 2% 1% Hematuria (>75 RBC/HPF) 3% 2% Glycosuria (≥3+) <1% 1% Neutrophils (<750/mm 3 ) 3% 5% Fasting Triglycerides (>750 mg/dL) 4% 2% Clinical Trials in Pediatric Subjects Emtricitabine: In addition to the adverse reactions reported in adults, anemia…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Tenofovir disoproxil fumarate increases didanosine concentrations. Dose reduction and close monitoring for didanosine toxicity are warranted. ( 7.2 ) Coadministration decreases atazanavir concentrations.
When coadministered with TRUVADA, use atazanavir given with ritonavir. ( 7.2 ) Coadministration of TRUVADA with certain HIV-1 protease inhibitors or certain drugs to treat HCV increases tenofovir concentrations. Monitor for evidence of tenofovir toxicity.
( 7.2 ) Consult Full Prescribing Information prior to and during treatment for important drug interactions. ( 7.2 )
7.1Drugs Affecting Renal Function FTC and tenofovir are primarily excreted by the kidneys by a combination of glomerular filtration and active tubular secretion [see Clinical Pharmacology (12.3) ] . No drug-drug interactions due to competition for renal excretion have been observed; however, coadministration of TRUVADA with drugs that are eliminated by active tubular secretion may increase concentrations of FTC, tenofovir, and/or the coadministered drug. Some examples include, but are not limited to, acyclovir, adefovir dipivoxil, cidofovir, ganciclovir, valacyclovir, valganciclovir, aminoglycosides (e.g., gentamicin), and high-dose or multiple NSAIDs [see Warnings and Precautions (5.3) ] .
Drugs that decrease renal function may increase concentrations of FTC and/or tenofovir.
7.2Established and Significant Interactions Table 7 provides a listing of established or clinically significant drug interactions. The drug interactions described are based on studies conducted with either TRUVADA, the components of TRUVADA (FTC and TDF) as individual agents and/or in combination, or are predicted drug interactions that may occur with TRUVADA [see Clinical Pharmacology (12.3) ]. Table 7 Established and Significant This table is not all inclusive.
Drug Interactions: Alteration in Dose or Regimen May Be Recommended Based on Drug Interaction Trials Concomitant Drug Class: Drug Name Effect on Concentration ↑=Increase, ↓=Decrease Clinical Comment NRTI: didanosine Indicates that a drug-drug interaction trial was conducted. ↑ didanosine Patients receiving TRUVADA and didanosine should be monitored closely for didanosine-associated adverse reactions. Discontinue didanosine in patients who develop didanosine-associated adverse reactions. Higher didanosine concentrations could potentiate didanosine-associated adverse reactions, including pancreatitis, and neuropathy.
Suppression of CD4+ cell counts has been observed in patients receiving TDF with didanosine 400 mg daily. In patients weighing greater than 60 kg, reduce the didanosine dose to 250 mg when it is coadministered with TRUVADA. Data are not available to recommend a dose adjustment of didanosine for adult or pediatric patients weighing less than 60 kg.
When coadministered, TRUVADA and Videx EC may be taken under fasted conditions or with a light meal (less than 400 kcal, 20% fat). HIV-1 Protease Inhibitors: atazanavir ↓ atazanavir When coadministered with TRUVADA, atazanavir 300 mg should be given with ritonavir 100 mg. lopinavir/ritonavir atazanavir/ritonavir darunavir/ritonavir ↑ tenofovir Monitor patients receiving TRUVADA concomitantly with lopinavir/ritonavir, ritonavir-boosted atazanavir, or ritonavir-boosted darunavir for TDF-associated adverse reactions. Discontinue TRUVADA in patients who develop TDF-associated adverse reactions.
Hepatitis C Antiviral Agents: sofosbuvir/velpatasvir sofosbuvir/velpatasvir/voxilaprevir ↑ tenofovir Monitor patients receiving TRUVADA concomitantly with EPCLUSA ® (sofosbuvir/velpatasvir) or VOSEVI ® (sofosbuvir/velpatasvir/voxilaprevir) for adverse reactions associated with TDF. ledipasvir/sofosbuvir Monitor patients receiving TRUVADA concomitantly with HARVONI ® (ledipasvir/sofosbuvir) without an HIV-1 protease inhibitor/ritonavir or an HIV-1 protease inhibitor/cobicistat combination for adverse reactions associated with TDF.
In patients receiving TRUVADA concomita…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Mothers infected with HIV-1 or suspected of having acquired HIV-1 infection should be instructed not to breastfeed due to the potential for HIV transmission. ( 8.2 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to TRUVADA during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Data on the use of TRUVADA during pregnancy from observational studies have shown no increased risk of major birth defects.
Available data from the APR show no significant difference in the overall risk of major birth defects with first trimester exposure for emtricitabine (FTC) (2.3%) or tenofovir disoproxil fumarate (TDF) (2.1%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data ) . The rate of miscarriage for individual drugs is not reported in the APR. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15–20%.
In animal reproduction studies, no adverse developmental effects were observed when the components of TRUVADA were administered separately at doses/exposures ≥60 (FTC), ≥14 (TDF) and 2.7 (tenofovir) times those of the recommended daily dose of TRUVADA ( see Data ). Clinical Considerations Disease-associated maternal and/or embryo/fetal risk HIV-1 PrEP: Published studies indicate an increased risk of HIV-1 infection during pregnancy and an increased risk of mother to child transmission during acute HIV-1 infection. In women at risk of acquiring HIV-1, consideration should be given to methods to prevent acquisition of HIV, including continuing or initiating TRUVADA for HIV-1 PrEP, during pregnancy.
Data Human Data TRUVADA for HIV-1 PrEP: In an observational study based on prospective reports to the APR, 78 HIV-seronegative women exposed to TRUVADA during pregnancy delivered live-born infants with no major malformations. All but one were first trimester exposures, and the median duration of exposure was 10.5 weeks. There were no new safety findings in the women receiving TRUVADA for HIV-1 PrEP compared with HIV-1 infected women treated with other antiretroviral medications.
Emtricitabine: Based on prospective reports to the APR of exposures to FTC-containing regimens during pregnancy resulting in live births (including over 3,300 exposed in the first trimester and over 1,300 exposed in the second/third trimester), the prevalence of major birth defects in live births was 2.6% (95% CI: 2.1% to 3.2%) and 2.3% (95% CI: 1.6% to 3.3%) following first and second/third trimester exposure, respectively, to FTC-containing regimens. Tenofovir Disoproxil Fumarate: Based on prospective reports to the APR of exposures to TDF-containing regimens during pregnancy resulting in live births (including over 4,000 exposed in the first trimester and over 1,700 exposed in the second/third trimester), the prevalence of major birth defects in live births was 2.4% (95% CI: 2.0% to 2.9%) and 2.4% (95% CI: 1.7% to 3.2%) following first and second/third trimester exposure, respectively, to TDF-containing regimens.
Methodologic limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation. Additionally, published observational studies on emtricitabine and tenofovir exposure in pregnancy have not shown an increased risk for major malformations.
Animal Data Emtricitabine: FTC was administered orally to pregnant mice (at 0, 250, 500, or 1,000 mg/kg/day), and rabbits (at 0, 100, 300, or 1,000 mg/kg/day) through organogenesis (on gestation days 6 through 15, and 7 through…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to TRUVADA during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Data on the use of TRUVADA during pregnancy from observational studies have shown no increased risk of major birth defects.
Available data from the APR show no significant difference in the overall risk of major birth defects with first trimester exposure for emtricitabine (FTC) (2.3%) or tenofovir disoproxil fumarate (TDF) (2.1%) compared with the background rate for major birth defects of 2.7% in a U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) (see Data ) . The rate of miscarriage for individual drugs is not reported in the APR. In the U.S. general population, the estimated background risk of miscarriage in clinically recognized pregnancies is 15–20%.
In animal reproduction studies, no adverse developmental effects were observed when the components of TRUVADA were administered separately at doses/exposures ≥60 (FTC), ≥14 (TDF) and 2.7 (tenofovir) times those of the recommended daily dose of TRUVADA ( see Data ). Clinical Considerations Disease-associated maternal and/or embryo/fetal risk HIV-1 PrEP: Published studies indicate an increased risk of HIV-1 infection during pregnancy and an increased risk of mother to child transmission during acute HIV-1 infection. In women at risk of acquiring HIV-1, consideration should be given to methods to prevent acquisition of HIV, including continuing or initiating TRUVADA for HIV-1 PrEP, during pregnancy.
Data Human Data TRUVADA for HIV-1 PrEP: In an observational study based on prospective reports to the APR, 78 HIV-seronegative women exposed to TRUVADA during pregnancy delivered live-born infants with no major malformations. All but one were first trimester exposures, and the median duration of exposure was 10.5 weeks. There were no new safety findings in the women receiving TRUVADA for HIV-1 PrEP compared with HIV-1 infected women treated with other antiretroviral medications.
Emtricitabine: Based on prospective reports to the APR of exposures to FTC-containing regimens during pregnancy resulting in live births (including over 3,300 exposed in the first trimester and over 1,300 exposed in the second/third trimester), the prevalence of major birth defects in live births was 2.6% (95% CI: 2.1% to 3.2%) and 2.3% (95% CI: 1.6% to 3.3%) following first and second/third trimester exposure, respectively, to FTC-containing regimens. Tenofovir Disoproxil Fumarate: Based on prospective reports to the APR of exposures to TDF-containing regimens during pregnancy resulting in live births (including over 4,000 exposed in the first trimester and over 1,700 exposed in the second/third trimester), the prevalence of major birth defects in live births was 2.4% (95% CI: 2.0% to 2.9%) and 2.4% (95% CI: 1.7% to 3.2%) following first and second/third trimester exposure, respectively, to TDF-containing regimens.
Methodologic limitations of the APR include the use of MACDP as the external comparator group. The MACDP population is not disease-specific, evaluates women and infants from a limited geographic area, and does not include outcomes for births that occurred at <20 weeks gestation. Additionally, published observational studies on emtricitabine and tenofovir exposure in pregnancy have not shown an increased risk for major malformations.
Animal Data Emtricitabine: FTC was administered orally to pregnant mice (at 0, 250, 500, or 1,000 mg/kg/day), and rabbits (at 0, 100, 300, or 1,000 mg/kg/day) through organogenesis (on gestation days 6 through 15, and 7 through 19, respectively). No significant toxicological effects were observed in embryo-fetal toxicity studies performed with FTC in mice at exposures (AUC) approximately 60 times higher and in rabbits at approxima…
🧒 Pediatric Use ▾
8.4Pediatric Use Treatment of HIV-1 Infection No pediatric clinical trial was conducted to evaluate the safety and efficacy of TRUVADA in patients with HIV-1 infection. Data from previously conducted trials with the individual drug products, FTC and TDF, were relied upon to support dosage recommendations for TRUVADA. For additional information, consult the prescribing information for EMTRIVA and VIREAD.
TRUVADA should only be administered to HIV-1 infected pediatric patients with body weight greater than or equal to 17 kg and who are able to swallow a tablet. Because it is a fixed-dose combination tablet, TRUVADA cannot be adjusted for patients of lower weight [see Warnings and Precautions (5.5) , Adverse Reactions (6.1) and Clinical Pharmacology (12.3) ] . TRUVADA is not approved for use in pediatric patients weighing less than 17 kg.
HIV-1 PrEP The safety and effectiveness of TRUVADA for HIV-1 PrEP in at-risk adolescents weighing at least 35 kg is supported by data from adequate and well-controlled studies of TRUVADA for HIV-1 PrEP in adults with additional data from safety and pharmacokinetic studies in previously conducted trials with the individual drug products, FTC and TDF, in HIV-1 infected adults and pediatric subjects [see Dosage and Administration (2.5) , Adverse Reactions (6.1) , Clinical Pharmacology (12.3 and 12.4) , and Clinical Studies (14.3 and 14.4) ].
Safety, adherence, and resistance were evaluated in a single-arm, open-label clinical trial (ATN113) in which 67 HIV-1 uninfected at-risk adolescent men who have sex with men received TRUVADA once daily for HIV-1 PrEP. The mean age of subjects was 17 years (range 15 to 18 years); 46% were Hispanic, 52% Black, and 37% White. The safety profile of TRUVADA in ATN113 was similar to that observed in the adult HIV-1 PrEP trials [see Adverse Reactions (6.1) ] .
In the ATN113 trial, HIV-1 seroconversion occurred in 3 subjects. Tenofovir diphosphate levels in dried blood spot assays indicate that these subjects had poor adherence. No tenofovir- or FTC-associated HIV-1 resistance substitutions were detected in virus isolated from the 3 subjects who seroconverted [see Microbiology (12.4) ].
Adherence to study drug, as demonstrated by tenofovir diphosphate levels in dried blood spot assays, declined markedly after Week 12 once subjects switched from monthly to quarterly visits, suggesting that adolescents may benefit from more frequent visits and counseling [see Warnings and Precautions (5.2) ] . Safety and effectiveness of Truvada for HIV-1 PrEP in pediatric patients weighing less than 35 kg have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical trials of FTC, TDF, or TRUVADA did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects.
🆘 Overdosage ▾
10 OVERDOSAGE If overdose occurs, the patient must be monitored for evidence of toxicity, and standard supportive treatment applied as necessary. Emtricitabine: Hemodialysis treatment removes approximately 30% of the FTC dose over a 3-hour dialysis period starting within 1.5 hours of FTC dosing (blood flow rate of 400 mL/min and a dialysate flow rate of 600 mL/min). It is not known whether FTC can be removed by peritoneal dialysis.
Tenofovir Disoproxil Fumarate: Tenofovir is efficiently removed by hemodialysis with an extraction coefficient of approximately 54%. Following a single 300 mg dose of TDF, a four-hour hemodialysis session removed approximately 10% of the administered tenofovir dose.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action TRUVADA is a fixed-dose combination of antiviral drugs FTC and TDF [see Microbiology (12.4) ].
12.3Pharmacokinetics TRUVADA: One TRUVADA tablet was comparable to one FTC capsule (200 mg) plus one TDF tablet (300 mg) following single-dose administration to fasting healthy subjects (N=39). Emtricitabine: The pharmacokinetic properties of FTC are summarized in Table 8. Following oral administration of FTC, FTC is rapidly absorbed with peak plasma concentrations occurring at 1–2 hours postdose.
Less than 4% of FTC binds to human plasma proteins in vitro, and the binding is independent of concentration over the range of 0.02–200 μg/mL. Following administration of radiolabelled FTC, approximately 86% is recovered in the urine and 13% is recovered as metabolites. The metabolites of FTC include 3′-sulfoxide diastereomers and their glucuronic acid conjugate.
Emtricitabine is eliminated by a combination of glomerular filtration and active tubular secretion. Following a single oral dose of FTC, the plasma FTC half-life is approximately 10 hours. Tenofovir Disoproxil Fumarate: The pharmacokinetic properties of TDF are summarized in Table 8.
Following oral administration of TDF, maximum tenofovir serum concentrations are achieved in 1.0 ± 0.4 hour. Less than 0.7% of tenofovir binds to human plasma proteins in vitro, and the binding is independent of concentration over the range of 0.01–25 µg/mL. Approximately 70–80% of the intravenous dose of tenofovir is recovered as unchanged drug in the urine.
Tenofovir is eliminated by a combination of glomerular filtration and active tubular secretion. Following a single oral dose of TDF, the terminal elimination half-life of tenofovir is approximately 17 hours. Table 8 Single Dose Pharmacokinetic Parameters for FTC and Tenofovir in Adults NC=Not calculated FTC Tenofovir Fasted Oral Bioavailability Median (range) (%) 92 (83.1–106.4) 25 (NC–45.0) Plasma Terminal Elimination Half-Life (hr) 10 (7.4–18.0) 17 (12.0–25.7) C max Mean (± SD) (μg/mL) 1.8±0.72 Data presented as steady state values 0.30±0.09 AUC (μg ∙ hr/mL) 10.0±3.12 2.29±0.69 CL/F (mL/min) 302±94 1043±115 CL renal (mL/min) 213±89 243±33 Effects of Food on Oral Absorption TRUVADA may be administered with or without food.
Administration of TRUVADA following a high fat meal (784 kcal; 49 grams of fat) or a light meal (373 kcal; 8 grams of fat) delayed the time of tenofovir C max by approximately 0.75 hour. The mean increases in tenofovir AUC and C max were approximately 35% and 15%, respectively, when administered with a high fat or light meal, compared to administration in the fasted state. In previous safety and efficacy trials, TDF (tenofovir) was taken under fed conditions.
FTC systemic exposures (AUC and C max ) were unaffected when TRUVADA was administered with either a high fat or a light meal. Specific Populations Race Emtricitabine: No pharmacokinetic differences due to race have been identified following the administration of FTC. Tenofovir Disoproxil Fumarate: There were insufficient numbers from racial and ethnic groups other than Caucasian to adequately determine potential pharmacokinetic differences among these populations following the administration of TDF.
Gender Emtricitabine and Tenofovir Disoproxil Fumarate: FTC and tenofovir pharmacokinetics are similar in male and female subjects. Pediatric Patients Treatment of HIV-1 Infection: The pharmacokinetic data for tenofovir and FTC following administration of TRUVADA in pediatric subjects weighing 17 kg and above are not available. The dosage recommendations of TRUVADA in this population are based on the dosage recommendations of FTC and TDF in this population.
Refer to the EMTRIVA and VIREAD prescribing information for pharmacokinetic information on the individual products in pediatric patients. HIV-1 PrEP: The pharmacokinetic data for tenofovir and FTC following administration of TRUVADA in HIV-1 uninfected adolescents weighing 3…
🧬 Mechanism of Action ▾
12.1Mechanism of Action TRUVADA is a fixed-dose combination of antiviral drugs FTC and TDF [see Microbiology (12.4) ].
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING TRUVADA tablets are available in bottles containing 30 tablets with child-resistant closure as follows: 100 mg of FTC and 150 mg of TDF (equivalent to 123 mg of tenofovir disoproxil) tablets are blue, oval shaped, film coated, debossed with "GSI" on one side and with "703" on the other side (NDC 61958-0703-1). 133 mg of FTC and 200 mg of TDF (equivalent to 163 mg of tenofovir disoproxil) tablets are blue, rectangular shaped, film coated, debossed with "GSI" on one side and with "704" on the other side (NDC 61958-0704-1).
167 mg of FTC and 250 mg of TDF (equivalent to 204 mg of tenofovir disoproxil) tablets are blue, modified capsule shaped, film coated, debossed with "GSI" on one side and with "705" on the other side (NDC 61958-0705-1). 200 mg of FTC and 300 mg of TDF (equivalent to 245 mg of tenofovir disoproxil) tablets are blue, capsule shaped, film coated, debossed with "GILEAD" on one side and with "701" on the other side (NDC 61958-0701-1). Store at 25 °C (77 °F), excursions permitted to 15 °C–30 °C (59 °F–86 °F) (see USP Controlled Room Temperature).
Keep container tightly closed. Dispense only in original container.
📦 Storage and Handling ▾
Store at 25 °C (77 °F), excursions permitted to 15 °C–30 °C (59 °F–86 °F) (see USP Controlled Room Temperature). Keep container tightly closed. Dispense only in original container.
📋 Description ▾
11 DESCRIPTION TRUVADA tablets are fixed-dose combination tablets containing emtricitabine (FTC) and tenofovir disoproxil fumarate (TDF). FTC is a synthetic nucleoside analog of cytidine. TDF is converted in vivo to tenofovir, an acyclic nucleoside phosphonate (nucleotide) analog of adenosine 5′-monophosphate.
Both FTC and tenofovir exhibit inhibitory activity against HIV-1 reverse transcriptase. Emtricitabine: The chemical name of FTC is 5-fluoro-1-(2 R ,5 S )-[2-(hydroxymethyl)-1,3-oxathiolan-5-yl]cytosine. FTC is the (-) enantiomer of a thio analog of cytidine, which differs from other cytidine analogs in that it has a fluorine in the 5-position.
It has a molecular formula of C 8 H 10 FN 3 O 3 S and a molecular weight of 247.24. It has the following structural formula: FTC is a white to off-white crystalline powder with a solubility of approximately 112 mg/mL in water at 25 °C. The partition coefficient (log p) for emtricitabine is −0.43 and the pKa is 2.65.
Chemical Structure Tenofovir Disoproxil Fumarate: TDF is a fumaric acid salt of the bis-isopropoxycarbonyloxymethyl ester derivative of tenofovir. The chemical name of tenofovir DF is 9-[( R )-2 [[bis[[(isopropoxycarbonyl)oxy]- methoxy]phosphinyl]methoxy]propyl]adenine fumarate (1:1). It has a molecular formula of C 19 H 30 N 5 O 10 P ∙ C 4 H 4 O 4 and a molecular weight of 635.52.
It has the following structural formula: Tenofovir disoproxil fumarate is a white to off-white crystalline powder with a solubility of 13.4 mg/mL in water at 25 °C. The partition coefficient (log p) for tenofovir disoproxil is 1.25 and the pKa is 3.75. All dosages are expressed in terms of TDF except where otherwise noted.
TRUVADA tablets are for oral administration, and are available in the following strengths: Film-coated tablet containing 200 mg of FTC and 300 mg of TDF (which is equivalent to 245 mg of tenofovir disoproxil) as active ingredients Film-coated tablet containing 167 mg of FTC and 250 mg of TDF (which is equivalent to 204 mg of tenofovir disoproxil) as active ingredients Film-coated tablet containing 133 mg of FTC and 200 mg of TDF (which is equivalent to 163 mg of tenofovir disoproxil) as active ingredients Film-coated tablet containing 100 mg of FTC and 150 mg of TDF (which is equivalent to 123 mg of tenofovir disoproxil) as active ingredients All strengths of TRUVADA tablets also include the following inactive ingredients: croscarmellose sodium, lactose monohydrate, magnesium stearate, microcrystalline cellulose, and pregelatinized starch (gluten free).
The 200 mg/300 mg strength tablets are coated with Opadry II Blue Y-30-10701, which contains FD&C Blue #2 aluminum lake, hypromellose 2910, lactose monohydrate, titanium dioxide, and triacetin. The 167 mg/250 mg, 133 mg/200 mg, and 100 mg/150 mg strength tablets are coated with Opadry II Blue, which contains FD&C Blue #2 aluminum lake, hypromellose 2910, lactose monohydrate, titanium dioxide, and triacetin. Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Important Information for Uninfected Individuals Taking TRUVADA for HIV-1 PrEP Advise HIV-uninfected individuals about the following [see Warnings and Precautions (5.2) ] : The need to confirm that they are HIV-negative before starting to take TRUVADA to reduce the risk of acquiring HIV-1. That HIV-1 resistance substitutions may emerge in individuals with undetected HIV-1 infection who are taking TRUVADA, because TRUVADA alone does not constitute a complete regimen for HIV-1 treatment.
The importance of taking TRUVADA on a regular dosing schedule and strict adherence to the recommended dosing schedule to reduce the risk of acquiring HIV-1. Uninfected individuals who miss doses are at greater risk of acquiring HIV-1 than those who do not miss doses. That TRUVADA does not prevent other sexually acquired infections and should only be used as part of a complete prevention strategy including other prevention measures.
To use condoms consistently and correctly to lower the chances of sexual contact with any body fluids such as semen, vaginal secretions, or blood. The importance of knowing their HIV-1 status and the HIV-1 status of their partner(s). The importance of virologic suppression in their partner(s) with HIV-1.
The need to get tested regularly for HIV-1 (at least every 3 months, or more frequently for some individuals such as adolescents) and to ask their partner(s) to get tested as well. To report any symptoms of acute HIV-1 infection (flu-like symptoms) to their healthcare provider immediately. That the signs and symptoms of acute infection include fever, headache, fatigue, arthralgia, vomiting, myalgia, diarrhea, pharyngitis, rash, night sweats, and adenopathy (cervical and inguinal).
To get tested for other sexually transmitted infections, such as syphilis, chlamydia, and gonorrhea, that may facilitate HIV-1 transmission. To assess their sexual risk behavior and get support to help reduce sexual risk behavior. Severe Acute Exacerbation of Hepatitis B in Patients Infected with HBV Inform individuals that severe acute exacerbations of hepatitis B have been reported in patients who are infected with HBV and have discontinued TRUVADA [see Warnings and Precautions (5.1) ] .
Advise HBV-infected individuals to not discontinue TRUVADA without first informing their healthcare provider. New Onset or Worsening Renal Impairment Inform HIV-1 infected patients and uninfected individuals that renal impairment, including cases of acute renal failure and Fanconi syndrome, has been reported in association with the use of TDF, a component of TRUVADA. Advise patients to avoid TRUVADA with concurrent or recent use of a nephrotoxic agent (e.g., high-dose or multiple NSAIDs) [see Warnings and Precautions (5.3) ] .
The dosing interval of TRUVADA may need adjustment in HIV-1 infected patients with renal impairment. TRUVADA for HIV-1 PrEP should not be used in HIV-1 uninfected individuals if estimated creatinine clearance is less than 60 mL/min. If a decrease in estimated creatinine clearance is observed in uninfected individuals while using TRUVADA for HIV-1 PrEP, evaluate potential causes and re-assess potential risks and benefits of continued use [see Dosage and Administration (2.6) ] .
Immune Reconstitution Syndrome Inform HIV-1 infected patients that in some patients with advanced HIV infection (AIDS), signs and symptoms of inflammation from previous infections may occur soon after anti-HIV treatment is started. It is believed that these symptoms are due to an improvement in the body's immune response, enabling the body to fight infections that may have been present with no obvious symptoms. Advise patients to inform their healthcare provider immediately of any symptoms of infection [see Warnings and Precautions (5.4) ].
Bone Loss and Mineralization Defects Inform patients that decreases in bone mineral density have been observe…
💬 Medication Guide ▾
This Medication Guide has been approved by the U.S. Food and Drug Administration. Revised: 04/2024 Medication Guide TRUVADA ® (tru-VAH-dah) (emtricitabine and tenofovir disoproxil fumarate) tablets Read this Medication Guide before you start taking TRUVADA and each time you get a refill.
There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment. This Medication Guide provides information about two different ways that TRUVADA may be used.
See the section " What is TRUVADA? " for detailed information about how TRUVADA may be used. What is the most important information I should know about TRUVADA? TRUVADA can cause serious side effects, including: Worsening of hepatitis B virus infection (HBV).
Your healthcare provider will test you for HBV before start or when you start treatment with TRUVADA. If you have HBV infection and take TRUVADA, your HBV may get worse (flare-up) if you stop taking TRUVADA. A "flare-up" is when your HBV infection suddenly returns in a worse way than before.
Do not run out of TRUVADA. Refill your prescription or talk to your healthcare provider before your TRUVADA is all gone. Do not stop taking TRUVADA without first talking to your healthcare provider.
If you stop taking TRUVADA, your healthcare provider will need to check your health often and do blood tests regularly for several months to check your HBV infection, or give you a medicine to treat hepatitis B. Tell your healthcare provider about any new or unusual symptoms you may have after you stop taking TRUVADA. For more information about side effects, see the section " What are the possible side effects of TRUVADA? ".
Other important information for people who take TRUVADA to help reduce their risk of getting human immunodeficiency virus-1 (HIV-1) infection, also called pre-exposure prophylaxis or "PrEP": Before taking TRUVADA to reduce your risk of getting HIV-1: You must be HIV-1 negative to start TRUVADA. You must get tested to make sure that you do not already have HIV-1 infection. Do not take TRUVADA for HIV-1 PrEP unless you are confirmed to be HIV-1 negative.
Some HIV-1 tests can miss HIV-1 infection in a person who has recently become infected. If you have flu-like symptoms, you could have recently become infected with HIV-1. Tell your healthcare provider if you had a flu-like illness within the last month before starting TRUVADA or at any time while taking TRUVADA.
Symptoms of new HIV-1 infection include: tiredness fever joint or muscle aches headache sore throat vomiting or diarrhea rash night sweats enlarged lymph nodes in the neck or groin While you are taking TRUVADA for HIV-1 PrEP: TRUVADA does not prevent other sexually transmitted infections (STIs). Practice safer sex by using a latex or polyurethane condom to reduce the risk of getting STIs. You must stay HIV-negative to keep taking TRUVADA for HIV-1 PrEP.
Know your HIV-1 status and the HIV-1 status of your partners. Ask your partners with HIV-1 if they are taking anti-HIV-1 medicines and have an undetectable viral load. An undetectable viral load is when the amount of virus in the blood is too low to be measured in a lab test.
To maintain an undetectable viral load, your partners must keep taking HIV-1 medicines every day. Your risk of getting HIV-1 is lower if your partners with HIV-1 are taking effective treatment. Get tested for HIV-1 at least every 3 months or when your healthcare provider tells you.
Get tested for other STIs such as syphilis, chlamydia, and gonorrhea. These infections make it easier for HIV-1 to infect you. If you think you were exposed to HIV-1, tell your healthcare provider right away.
They may want to do more tests to be sure you are still HIV-1 negative. Get information and support to help reduce sexual risk behaviors. Do not miss any doses of TRUVADA.
Missing doses increases your risk of getting HIV-1 infection. If you do become HIV-1 positive, you need more…