
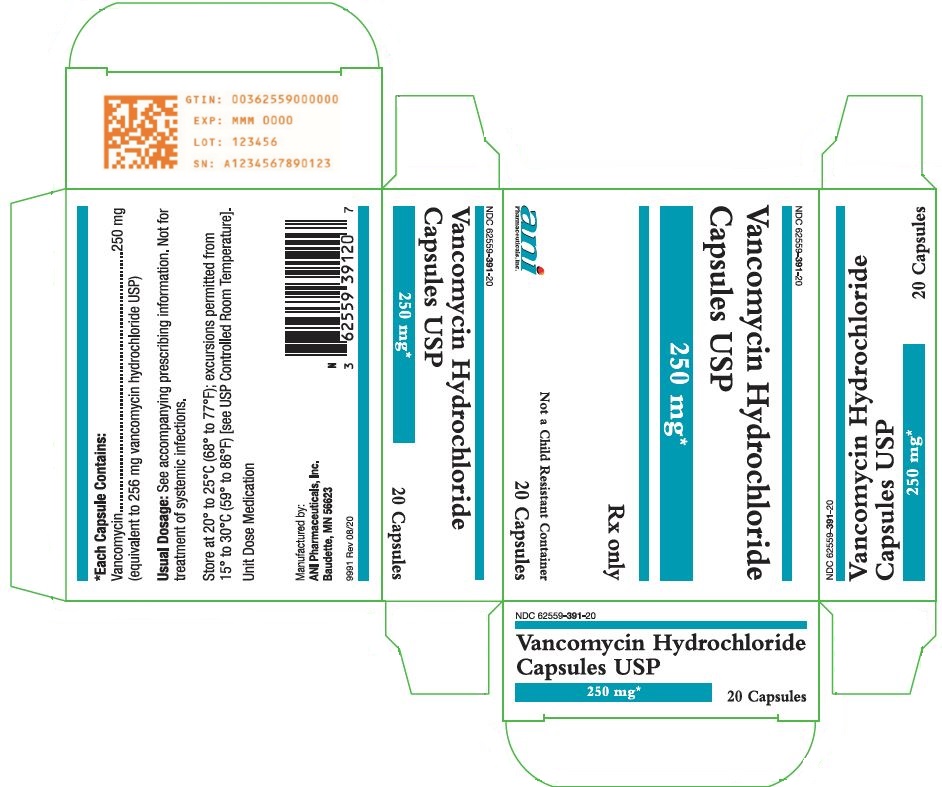
vancomycin hydrochloride 250 mg Capsule, 50-count
Other active recalls for Vancomycin Hydrochloride (different manufacturers) — 2 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Glycopeptide Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Vancomycin is used to treat colitis (inflammation of the intestine caused by certain bacteria) that may occur after taking an antibiotic. Vancomycin is in a class of medications called glycopeptide antibiotics. It works by killing bacteria in the intestines. Vancomycin will not kill bacteria in any other part of the body when taken by mouth. Antibiotics such as vancomycin will not work for colds, flu, or other viral infections. Taking antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- It depends on what you're being treated for. If you have a serious infection like a bloodstream infection, heart valve infection, or bone infection, the oral form of vancomycin sim...
- Why do I need an IV antibiotic — can't I just take a pill?
- The two biggest things to watch for are changes in your hearing and changes in your urination. If you notice ringing in your ears, muffled hearing, or dizziness, let your doctor kn...
- What should I watch out for while taking vancomycin?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Vancomycin Hydrochloride — tap one for details:
Vancomycin Hydrochloride may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 30IQX730WE
Polyethylene glycol 6000 is a synthetic polymer made from ethylene glycol units. It acts as a binder, filler, and solubilizer in medicines to help hold ingredients together, add bulk, and improve how well active drugs dissolve and absorb.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.704 | $135.21 / 50 capsules |
| Medicaid paysCMS SDUD · 12 mo | $2.35 | $117.62 / 50 capsules |
| Medicare drug plans payPart D · Q2 2026 | $1.89 | $94.28 / 50 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Vancomycin Hydrochloride 250 mg 00121-1033-20 | PAI | 20 capsules | $2.704 | AB | Availability likely | — |
| vancomycin hydrochloride 250 mg 23155-0859-25 | Heritage | 50 capsules | $2.704 | AB | Availability likely | — |
| Vancomycin Hydrochloride 250 mg 42494-0451-20 | Cameron | 20 capsules | $2.704 | AB | Availability likely | — |
| vancomycin hydrochloride 250 mgthis 62559-0391-50 | ANI | 50 capsules | $2.704 | AB | Availability likely | — |
| vancomycin hydrochloride 250 mg 64380-0730-02 | Strides | 20 capsules | $2.704 | AB | Availability likely | — |
| Vancocin 250 mg 62559-0311-20 | ANI | 20 capsules | — | AB | FDA listed | — |
| Vancomycin Hydrochloride 250 mg 72162-2306-04 | Bryant | 50 capsules | — | AB | FDA listed | — |
| vancomycin hydrochloride 250 mg 80425-0514-01 | Advanced | 20 capsules | — | AB | FDA listed | — |
| vancomycin hydrochloride 250 mg 23155-0968-25 | Heritage | 50 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 62559-0391-20 | 2 BLISTER PACK in 1 CARTON (62559-391-20) / 10 CAPSULE in 1 BLISTER PACK | $2.70 / ea | $54.08 | 2015-10-26 | Active |
| 62559-0391-50 You're viewing this | 50 CAPSULE in 1 BOTTLE (62559-391-50) | $2.70 / ea | $135.21 | 2016-12-20 | Active |
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($2.70 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 79% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 62559-0391-50?
What is the difference between NDC 62559-0391-50 and NDC 62559-0391-20?
What NDC number is used to bill for this package of vancomycin hydrochloride 250 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Vancomycin Hydrochloride Capsules are indicated for the treatment of Clostridioides difficile -associated diarrhea. Vancomycin Hydrochloride Capsules are also used for the treatment of enterocolitis caused by Staphylococcus aureus (including methicillin-resistant strains) in adult and pediatric patients less than 18 years of age. Limitations of Use • Parenteral administration of vancomycin is not effective for the above infections; therefore, Vancomycin Hydrochloride Capsules must be given orally for these infections. • Orally administered Vancomycin Hydrochloride Capsules are not effective for other types of infections.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Vancomycin Hydrochloride Capsules and other antibacterial drugs, Vancomycin Hydrochloride Capsules should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Vancomycin Hydrochloride Capsules are a glycopeptide antibacterial indicated in adult and pediatric patients (less than 18 years of age) for the treatment of: ( 1 ) • Clostridioides difficile-associated diarrhea • Enterocolitis caused by Staphylococcus aureus (including methicillin-resistant strains) Limitations of Use: ( 1 ) ( 5.1 ) • Parenteral administration of vancomycin is not effective for the above infections; therefore, Vancomycin Hydrochloride Capsules must be given orally for these infections. • Orally administered Vancomycin Hydrochloride Capsules are not effective for other types of infections.
To reduce the development of drug-resistant bacteria and maintain the effectiveness of Vancomycin Hydrochloride Capsules and other antibacterial drugs, Vancomycin Hydrochloride Capsules should be used only to treat or prevent infections that are proven or strongly suspected to be caused by bacteria. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • C. difficile- associated diarrhea: • Adult Patients (18 years of age or greater): 125 mg orally 4 times daily for 10 days. ( 2.1 ) • Pediatric Patients (less than 18 years of age): 40 mg/kg in 3 or 4 divided doses for 7 to 10 days. The total daily dosage should not exceed 2 g.
( 2.2 ) • Staphylococcal enterocolitis: • Adult Patients (18 years of age or greater): 500 mg to 2 g orally in 3 or 4 divided doses for 7 to 10 days. ( 2.1 ) • Pediatric Patients (less than 18 years of age): 40 mg/kg in 3 or 4 divided doses for 7 to 10 days. The total daily dosage should not exceed 2 g.
( 2.2 )
2.1Adults Vancomycin Hydrochloride Capsules are used in treating C. difficile -associated diarrhea and staphylococcal enterocolitis. • C. difficile- associated diarrhea: The recommended dose is 125 mg administered orally 4 times daily for 10 days. • Staphylococcal enterocolitis: Total daily dosage is 500 mg to 2 g administered orally in 3 or 4 divided doses for 7 to 10 days.
2.2Pediatric Patients (less than 18 years of age) For both C. difficile -associated diarrhea and staphylococcal enterocolitis, the usual daily dosage is 40 mg/kg in 3 or 4 divided doses for 7 to 10 days. The total daily dosage should not exceed 2 g.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Vancomycin Hydrochloride Capsules USP, 125 mg (equivalent to vancomycin) have an opaque blue cap and opaque brown body imprinted with “3125” on the cap and “VANCOCIN HCL 125 MG” on the body in white ink. Vancomycin Hydrochloride Capsules USP, 250 mg (equivalent to vancomycin) have an opaque blue cap and opaque lavender body imprinted with “3126” on the cap and “VANCOCIN HCL 250 MG” on the body in white ink. 125 mg capsules and 250 mg capsules ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Vancomycin Hydrochloride Capsules are contraindicated in patients with known hypersensitivity to vancomycin. Hypersensitivity to vancomycin ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Vancomycin Hydrochloride Capsules must be given orally for treatment of staphylococcal enterocolitis and C. difficile -associated diarrhea. Orally administered Vancomycin Hydrochloride Capsules is not effective for other types of infections. ( 5.1 ) • Clinically significant serum concentrations have been reported in some patients who have taken multiple oral doses of Vancomycin Hydrochloride Capsules for active C. difficile -associated diarrhea.
Monitoring of serum concentrations may be appropriate in some instances. ( 5.2 ) • Nephrotoxicity has occurred following oral Vancomycin Hydrochloride Capsule therapy and can occur either during or after completion of therapy. The risk is increased in geriatric patients.
( 5.3 ) Monitor renal function. • Ototoxicity has occurred in patients receiving Vancomycin Hydrochloride Capsules. ( 5.4 ) Assessment of auditory function may be appropriate in some instances. • Severe Dermatologic Reactions: Discontinue Vancomycin Hydrochloride Capsules at the first appearance of skin rashes, mucosal lesions, or blisters ( 5.5 ). • Prescribing Vancomycin Hydrochloride Capsules in the absence of a proven or strongly suspected bacterial infection is unlikely to provide benefit to the patient and increases the risk of the development of drug resistant bacteria.
( 5.6 )
5.1Oral Use Only Vancomycin Hydrochloride Capsules for the treatment of colitis are for oral use only and are not systemically absorbed. Vancomycin Hydrochloride Capsules must be given orally for treatment of staphylococcal enterocolitis and Clostridioides difficile -associated diarrhea. Orally administered Vancomycin Hydrochloride Capsules are not effective for other types of infections.
Parenteral administration of vancomycin is not effective for treatment of staphylococcal enterocolitis and C. difficile -associated diarrhea. If parenteral vancomycin therapy is desired, use an intravenous preparation of vancomycin and consult the package insert accompanying that preparation.
5.2Potential for Systemic Absorption Clinically significant serum concentrations have been reported in some patients who have taken multiple oral doses of Vancomycin Hydrochloride Capsules for active C. difficile -associated diarrhea. Some patients with inflammatory disorders of the intestinal mucosa also may have significant systemic absorption of vancomycin. These patients may be at risk for the development of adverse reactions associated with higher doses of Vancomycin Hydrochloride Capsules; therefore, monitoring of serum concentrations of vancomycin may be appropriate in some instances, e.g., in patients with renal insufficiency and/or colitis or in those receiving concomitant therapy with an aminoglycoside antibiotic.
5.3Nephrotoxicity Nephrotoxicity (e.g., reports of renal failure, renal impairment, blood creatinine increased) has occurred following oral Vancomycin Hydrochloride Capsules therapy in randomized controlled clinical studies, and can occur either during or after completion of therapy. The risk of nephrotoxicity is increased in patients >65 years of age [see Adverse Reactions ( 6.1 ) and Use in Specific Populations ( 8.5 )] . In patients >65 years of age, including those with normal renal function prior to treatment, renal function should be monitored during and following treatment with Vancomycin Hydrochloride Capsules to detect potential vancomycin induced nephrotoxicity.
5.4Ototoxicity Ototoxicity has occurred in patients receiving vancomycin. It may be transient or permanent. It has been reported mostly in patients who have been given excessive intravenous doses, who have an underlying hearing loss, or who are receiving concomitant therapy with another ototoxic agent, such as an aminoglycoside. Serial tests of auditory function may be helpful in order to minimize the risk of ototoxicity [see Adverse Reactions ( 6.2 )]
5.5Severe Dermatologic Reactions Severe dermatologic reactions such as toxic epidermal necroly…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (≥ 10%) were nausea (17%), abdominal pain (15%), and hypokalemia (13%). ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact ANI Pharmaceuticals, Inc. at 1-855-204-1431 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. The data described below reflect exposure to vancomycin in 260 adult subjects in two Phase 3 clinical trials for the treatment of diarrhea associated with C. difficile . In both trials, subjects received vancomycin 125 mg orally four times daily.
The mean duration of treatment was 9.4 days. The median age of patients was 67, ranging between 19 and 96 years of age. Patients were predominantly Caucasian (93%) and 52% were male.
Adverse reactions occurring in ≥ 5% of vancomycin-treated subjects are shown in Table 1. The most common adverse reactions associated with vancomycin (≥ 10%) were nausea, abdominal pain, and hypokalemia. Table 1: Common ( ≥ 5%) Adverse Reactions a for Vancomycin Reported in Clinical Trials for Treatment of Diarrhea Associated with C. difficile a Adverse reaction rates were derived from the incidence of treatment-emergent adverse events.
System/Organ Class Adverse Reaction Vancomycin % (N=260) Gastrointestinal disorders Nausea Abdominal pain Vomiting Diarrhea Flatulence 17 15 9 9 8 General disorders and administration site conditions Pyrexia Edema peripheral Fatigue 9 6 5 Infections and infestations Urinary tract infection 8 Metabolism and nutrition disorders Hypokalemia 13 Musculoskeletal and connective tissue disorders Back pain 6 Nervous system disorders Headache 7 Nephrotoxicity (e.g., reports of renal failure, renal impairment, blood creatinine increased) occurred in 5% of subjects treated with vancomycin.
Nephrotoxicity following vancomycin typically first occurred within one week after completion of treatment (median day of onset was Day 16). Nephrotoxicity following vancomycin occurred in 6% of subjects >65 years of age and 3% of subjects ≤65 years of age [see Warnings and Precautions ( 5.3 )] . The incidences of hypokalemia, urinary tract infection, peripheral edema, insomnia, constipation, anemia, depression, vomiting, and hypotension were higher among subjects >65 years of age than in subjects ≤65 years of age [see Use in Specific Populations ( 8.5 )] .
Discontinuation of study drug due to adverse events occurred in 7% of subjects treated with vancomycin. The most common adverse events leading to discontinuation of vancomycin were C. difficile colitis (<1%), nausea (<1%), and vomiting (<1%).
6.2Postmarketing Experience The following adverse reactions have been identified during post-approval use of vancomycin. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. Ototoxicity : Cases of hearing loss associated with intravenously administered vancomycin have been reported.
Most of these patients had kidney dysfunction or a preexisting hearing loss or were receiving concomitant treatment with an ototoxic drug [see Warnings and Precautions ( 5.4 )] . Vertigo, dizziness, and tinnitus have been reported. Skin and Subcutaneous Tissue Disorders: Severe dermatologic reactions such as toxic epidermal necrolysis (TEN), Stevens-Johnson syndrome (SJS), drug reaction with eosinophilia and systemic symptoms (DRESS), acute generalized exanthematous pustulosis (AGEP), and linear IgA bullous dermatosis (LABD) [see Warnings and Precautions ( 5.5 )] , rashes (including exfoliative dermatitis).
Hematopoietic : Reversible neutropenia, usually starting 1 week or more after onset of intravenous therapy with van…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS No drug interaction studies have been conducted.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Geriatrics: In patients >65 years of age, including those with normal renal function prior to treatment, renal function should be monitored during and following treatment with Vancomycin Hydrochloride Capsules to detect potential vancomycin induced nephrotoxicity. ( 5.3 ) ( 6.1 ) ( 8.5 ) ( 14.1 )
8.1Pregnancy Risk Summary Systemic absorption of vancomycin is low following oral administration of Vancomycin Hydrochloride Capsules; however, absorption may vary depending on various factors [see Clinical Pharmacology ( 12.3 )]. There are no available data on vancomycin use in pregnant women to assess a risk of major birth defects or miscarriage. Available published data on intravenous vancomycin use in pregnancy during the second and third trimesters have not shown an association with adverse maternal or fetal outcomes (see Data) .
Vancomycin did not show adverse developmental effects when administered intravenously to pregnant rats and rabbits during organogenesis at doses less than or equal to the recommended maximum human dose (see Data) . Data Human Data There are no available data on first trimester use of vancomycin in pregnant women to assess a risk of major birth defects or miscarriage. A published study evaluated hearing loss and nephrotoxicity in infants of 10 pregnant intravenous drug users treated with intravenous vancomycin for suspected or documented methicillin-resistant Staphylococcal aureus in the second or third trimester.
The comparison groups were 10 uninfected non-intravenous drug-dependent patients who received no treatment and 10 uninfected untreated intravenous drug-dependent patients. No infant in the vancomycin exposed group had abnormal sensorineural hearing at 3 months of age or nephrotoxicity. A published prospective study assessed outcomes in 55 pregnant women with a positive Group B streptococcus culture and a high-risk penicillin allergy with resistance to clindamycin or unknown sensitivity who were administered intravenous vancomycin at the time of delivery.
Vancomycin dosing ranged from the standard dose of 1 g intravenously every 12 hours to a dose of 20 mg/kg intravenously every 8 hours (maximum individual dose 2 g). No major adverse reactions were recorded either in the mothers or their newborns. None of the newborns had sensorineural hearing loss.
Neonatal renal function was not examined, but all of the newborns were discharged in good condition. Animal Data Vancomycin did not cause fetal malformation when administered intravenously during organogenesis to pregnant rats (gestation days 6 to 15) and rabbits (gestation days 6 to 18) at the equivalent recommended maximum human dose of 200 mg/kg/day to rats or 120 mg/kg/day to rabbits. No effects on fetal weight or development were seen in rats at the highest dose tested or in rabbits given 80 mg/kg/day (approximately 1 and 0.8 times the recommended maximum human dose based on body surface area).
Maternal toxicity was observed in rats (at doses 120 mg/kg and above) and rabbits (at 80 mg/kg and above).
8.2Lactation Risk Summary There are no data on the presence of vancomycin in human milk, the effects on the breastfed infant, or the effect on milk production following oral administration. Systemic absorption of vancomycin is low following oral administration of Vancomycin Hydrochloride Capsules [see Clinical Pharmacology ( 12.3 )] ; therefore, it is unlikely to result in clinically relevant exposure in breastfeeding infants. The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for Vancomycin Hydrochloride Capsules and any potential adverse effects on the breastfed infant from Vancomycin Hydrochloride Capsules or from the underlying maternal condition.
8.4Pediatric Use Vancomycin Hydrochloride Capsules are indicated in pediatric patients less than 18 years of age for the treatment of C. difficile -associated diarrhea and enterocolitis caused by S. aureus (in…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Systemic absorption of vancomycin is low following oral administration of Vancomycin Hydrochloride Capsules; however, absorption may vary depending on various factors [see Clinical Pharmacology ( 12.3 )]. There are no available data on vancomycin use in pregnant women to assess a risk of major birth defects or miscarriage. Available published data on intravenous vancomycin use in pregnancy during the second and third trimesters have not shown an association with adverse maternal or fetal outcomes (see Data) .
Vancomycin did not show adverse developmental effects when administered intravenously to pregnant rats and rabbits during organogenesis at doses less than or equal to the recommended maximum human dose (see Data) . Data Human Data There are no available data on first trimester use of vancomycin in pregnant women to assess a risk of major birth defects or miscarriage. A published study evaluated hearing loss and nephrotoxicity in infants of 10 pregnant intravenous drug users treated with intravenous vancomycin for suspected or documented methicillin-resistant Staphylococcal aureus in the second or third trimester.
The comparison groups were 10 uninfected non-intravenous drug-dependent patients who received no treatment and 10 uninfected untreated intravenous drug-dependent patients. No infant in the vancomycin exposed group had abnormal sensorineural hearing at 3 months of age or nephrotoxicity. A published prospective study assessed outcomes in 55 pregnant women with a positive Group B streptococcus culture and a high-risk penicillin allergy with resistance to clindamycin or unknown sensitivity who were administered intravenous vancomycin at the time of delivery.
Vancomycin dosing ranged from the standard dose of 1 g intravenously every 12 hours to a dose of 20 mg/kg intravenously every 8 hours (maximum individual dose 2 g). No major adverse reactions were recorded either in the mothers or their newborns. None of the newborns had sensorineural hearing loss.
Neonatal renal function was not examined, but all of the newborns were discharged in good condition. Animal Data Vancomycin did not cause fetal malformation when administered intravenously during organogenesis to pregnant rats (gestation days 6 to 15) and rabbits (gestation days 6 to 18) at the equivalent recommended maximum human dose of 200 mg/kg/day to rats or 120 mg/kg/day to rabbits. No effects on fetal weight or development were seen in rats at the highest dose tested or in rabbits given 80 mg/kg/day (approximately 1 and 0.8 times the recommended maximum human dose based on body surface area).
Maternal toxicity was observed in rats (at doses 120 mg/kg and above) and rabbits (at 80 mg/kg and above).
🧒 Pediatric Use ▾
8.4Pediatric Use Vancomycin Hydrochloride Capsules are indicated in pediatric patients less than 18 years of age for the treatment of C. difficile -associated diarrhea and enterocolitis caused by S. aureus (including methicillin-resistant strains) [see Indications and Usage ( 1 ) and Dosage and Administration ( 2.2 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use In clinical trials, 54% of vancomycin-treated subjects were >65 years of age. Of these, 40% were between the ages of >65 and 75, and 60% were >75 years of age. Clinical studies with vancomycin in diarrhea associated with Clostridioides difficile have demonstrated that geriatric subjects are at increased risk of developing nephrotoxicity following treatment with oral vancomycin, which may occur during or after completion of therapy.
In patients >65 years of age, including those with normal renal function prior to treatment, renal function should be monitored during and following treatment with vancomycin to detect potential vancomycin induced nephrotoxicity [see Warnings and Precautions ( 5.3 ), Adverse Reactions ( 6.1 ), and Clinical Studies ( 14.1 )] . Patients >65 years of age may take longer to respond to therapy compared to patients ≤65 years of age [see Clinical Studies ( 14.1 )] . Clinicians should be aware of the importance of appropriate duration of vancomycin treatment in patients >65 years of age and not discontinue or switch to alternative treatment prematurely.
🆘 Overdosage ▾
10 OVERDOSAGE Supportive care is advised, with maintenance of glomerular filtration. Vancomycin is poorly removed by dialysis. Hemofiltration and hemoperfusion with polysulfone resin have been reported to result in increased vancomycin clearance.
To obtain current information about the treatment of overdose, contact a certified Poison Control Center (1-800-222-1222 or www.poison.org). In managing overdosage, consider the possibility of multiple drug overdoses, interaction among drugs, and unusual drug kinetics.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Vancomycin is an antibacterial drug [see Microbiology ( 12.4 )] .
12.3Pharmacokinetics Vancomycin is poorly absorbed after oral administration. During multiple dosing of 250 mg every 8 hours for 7 doses, fecal concentrations of vancomycin in volunteers exceeded 100 mg/kg in the majority of samples. No blood concentrations were detected and urinary recovery did not exceed 0.76%.
In anephric subjects with no inflammatory bowel disease who received vancomycin oral solution 2 g for 16 days, blood concentrations of vancomycin were less than or equal to 0.66 mcg/mL in 2 of 5 subjects. No measurable blood concentrations were attained in the other 3 subjects. Following doses of 2 g daily, concentrations of drug were >3100 mg/kg in the feces and <1 mcg/mL in the serum of subjects with normal renal function who had C. difficile -associated diarrhea.
After multiple-dose oral administration of vancomycin, measurable serum concentrations may occur in patients with active C. difficile -associated diarrhea, and, in the presence of renal impairment, the possibility of accumulation exists. It should be noted that the total systemic and renal clearances of vancomycin are reduced in the elderly [see Use in Specific Populations ( 8.5 )] .
12.4Microbiology Mechanism of Action The bactericidal action of vancomycin against Staphylococcus aureus and the vegetative cells of Clostridioides difficile results primarily from inhibition of cell-wall biosynthesis. In addition, vancomycin alters bacterial-cell-membrane permeability and RNA synthesis. Resistance Staphylococcus aureus S. aureus isolates with vancomycin minimal inhibitory concentrations (MICs) as high as 1024 mcg/mL have been reported.
The exact mechanism of this resistance is not clear but is believed to be due to cell wall thickening and potentially the transfer of genetic material. Clostridioides difficile Isolates of C. difficile generally have vancomycin MICs of <1 mcg/mL, however vancomycin MICs ranging from 4 mcg/mL to 16 mcg/mL have been reported. The mechanism which mediates C. difficile's decreased susceptibility to vancomycin has not been fully elucidated.
Vancomycin has been shown to be active against most isolates of the following microorganisms, both in vitro and in clinical infections [see Indications and Usage ( 1 )] . Gram-positive bacteria Staphylococcus aureus (including methicillin-resistant isolates ) associated with enterocolitis. Anaerobic gram-positive bacteria Clostridioides difficile isolates associated with C. difficile associated diarrhea.
🧬 Mechanism of Action ▾
12.1Mechanism of Action Vancomycin is an antibacterial drug [see Microbiology ( 12.4 )] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Vancomycin Hydrochloride Capsules USP are available in: The 125 mg (equivalent to vancomycin) capsules have an opaque blue cap and opaque brown body imprinted with “3125” on the cap and “VANCOCIN HCL 125 MG” on the body in white ink. NDC 62559-390-20: Carton containing 2 blister packs. Each blister pack contains 10 capsules for a total of 20 capsules per carton.
NDC 62559-390-50: Bottle of 50 capsules. The 250 mg (equivalent to vancomycin) capsules have an opaque blue cap and opaque lavender body imprinted with “3126” on the cap and “VANCOCIN HCL 250 MG” on the body in white ink. NDC 62559-391-20: Carton containing 2 blister packs.
Each blister pack contains 10 capsules for a total of 20 capsules per carton. NDC 62559-391-50: Bottle of 50 capsules. Store at 20° to 25°C (68° to 77°F); excursions permitted from 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Vancomycin Hydrochloride Capsules USP for oral administration contain chromatographically purified vancomycin hydrochloride, a tricyclic glycopeptide antibiotic derived from Amycolatopsis orientalis (formerly Nocardia orientalis ), which has the chemical formula C 66 H 75 Cl 2 N 9 O 24 •HCl. The molecular weight of vancomycin hydrochloride is 1485.73; 500 mg of the base is equivalent to 0.34 mmol. Each capsule contains 125 mg vancomycin (equivalent to 128 mg vancomycin hydrochloride) or 250 mg vancomycin (equivalent to 256 mg vancomycin hydrochloride).
The capsules also contain FD&C Blue No. 2, gelatin, iron oxide, polyethylene glycol, titanium dioxide, and other inactive ingredients. Vancomycin hydrochloride has the structural formula: chemical structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Severe Dermatologic Reactions Advise patients about the signs and symptoms of serious skin manifestations. Instruct patients to stop taking Vancomycin Hydrochloride Capsules immediately and promptly seek medical attention at the first signs or symptoms of skin rash, mucosal lesions or blisters [see Warnings and Precautions ( 5.5 )]. Antibacterial Resistance Patients should be counseled that antibacterial drugs including Vancomycin Hydrochloride Capsules should only be used to treat bacterial infections.
They do not treat viral infections (e.g., the common cold). When Vancomycin Hydrochloride Capsules are prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed. Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by Vancomycin Hydrochloride Capsules or other antibacterial drugs in the future.
Manufactured by: ANI Pharmaceuticals, Inc. Baudette, MN 56623 ani