
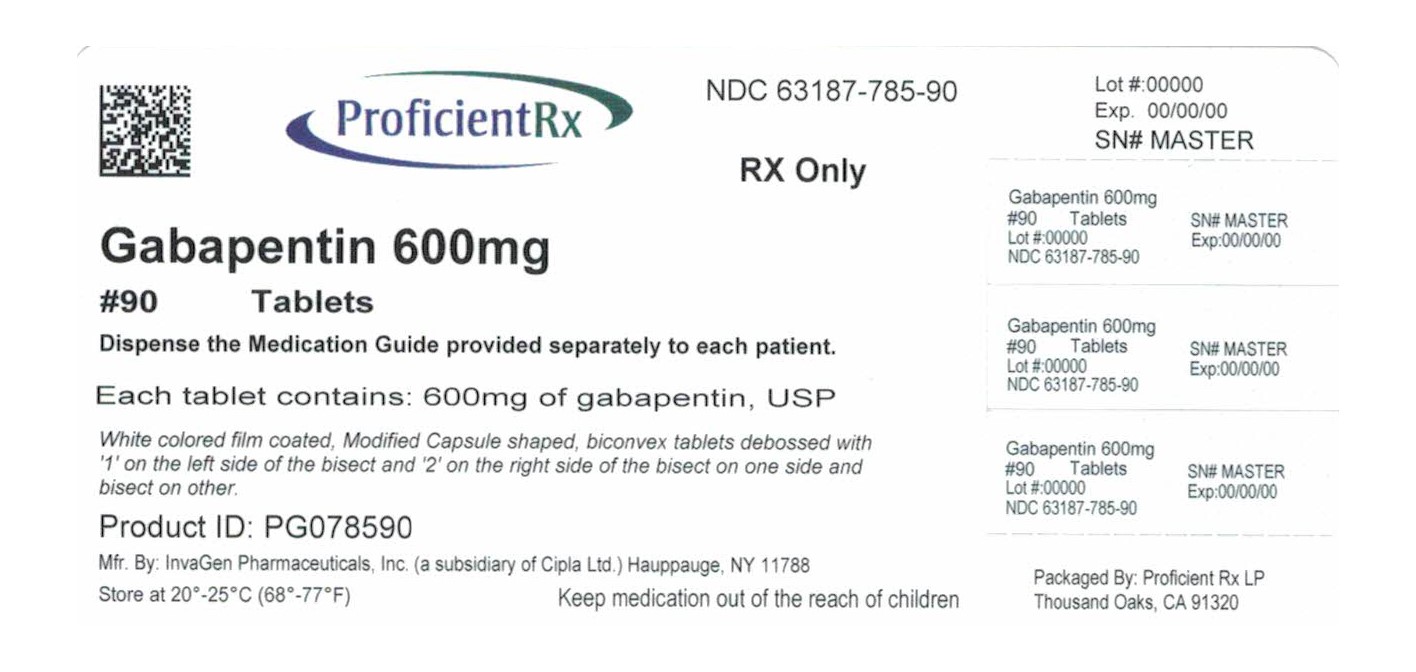
Gabapentin 600 mg Tablet, 100-count — NDC 63187-785-00 (Billing 63187-0785-00)
This is a package of 100 tablets of Gabapentin 600 mg Tablet from Proficient Rx LP, marketed since Jul 2016 and currently FDA-listed. It is the main listing for this product, which comes in 5 package sizes.
Other active recalls for Gabapentin (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 041805
- GCN: 94624
- GPI-14 (Medi-Span): 72600030000330
- HICL (First Databank): 008831
- AHFS class code: 28:08.92.00
- RxCUI (RxNorm): 310433
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Gabapentinoids class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Gabapentin capsules, tablets, and oral solution are used along with other medications to help control certain types of seizures in people who have epilepsy. Gabapentin capsules, tablets, and oral solution are also used to relieve the pain of postherpetic neuralgia (PHN; the burning, stabbing pain or aches that may last for months or years after an attack of shingles). Gabapentin extended-release tablets (Horizant) are used to treat restless legs syndrome (RLS; a condition that causes discomfort in the legs and a strong urge to move the legs, especially at night and when sitting or lying down)....
Read the full MedlinePlus article ↗- It's used for nerve pain after shingles (postherpetic neuralgia). Many gabapentin products are also used as add-on treatment for partial seizures in epilepsy. Horizant is also used...
- Dizziness and sleepiness are the most common side effects. Don't drive or use heavy machinery until you know how it affects you, because you may not judge your own impairment well.
- Talk to your prescriber first. Stopping seizure medicines suddenly can increase seizures. Gralise should be changed or stopped gradually over at least a week.
- Tell me about any opioid or sedating medicine, because together they can slow breathing dangerously. If you use an antacid like Maalox, take gabapentin at least 2 hours after it.
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Gabapentin — tap one for details:
Gabapentin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1683 | $16.83 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 63187-0785-00 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 2016-12-01 | — | Active |
| 63187-0785-30 63187-785-30 | 30 TABLET in 1 BOTTLE | 2016-12-01 | — | Active |
| 63187-0785-60 63187-785-60 | 60 TABLET in 1 BOTTLE | 2016-12-01 | — | Active |
| 63187-0785-72 63187-785-72 | 120 TABLET in 1 BOTTLE | 2016-12-01 | — | Active |
| 63187-0785-90 63187-785-90 | 90 TABLET in 1 BOTTLE | 2016-12-01 | — | Active |
You're viewing one of 5 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 63187-0785-30?
What NDC number is used to bill for this package of Gabapentin 600 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Gabapentin 600 mg 00904-6823-61 | Major | 1 tablet | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 16571-0226-01 | Rising | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 16714-0330-01 | NorthStar | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 31722-0166-01 | Camber | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 50228-0177-01 | ScieGen | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 50268-0325-15 | AvPAK | 1 tablet | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 60687-0507-01 | American | 1 tablet | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 64380-0727-01 | Strides | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 65862-0523-01 | Aurobindo | 100 tablets | $0.064 | — | Availability likely | — |
| Gabapentin 600 mg 67877-0428-01 | Ascend | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 68001-0411-00 | BluePoint | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 68094-0589-50 | Precision | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 68382-0204-01 | Zydus | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 68462-0126-01 | Glenmark | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 69367-0346-05 | Westminster | 500 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 70010-0227-01 | Granules | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 71093-0111-04 | ACI | 100 tablets | $0.064 | AB1 | Discontinued | — |
| Gabapentin 600 mg 76282-0405-01 | Exelan | 100 tablets | $0.064 | — | Availability likely | — |
| Gabapentin 600 mg 76282-0706-05 | Exelan | 500 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 82009-0071-05 | QUALLENT | 500 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 83301-0001-01 | Mullan | 100 tablets | $0.064 | AB1 | Availability likely | — |
| Gabapentin 600 mg 68094-0069-61 | Precision | 10 tablets | $0.064 | AB1 | Availability likely | — |
| gabapentin 600 mg 62756-0202-01 | Sun | 100 tablets | $0.068 | — | FDA listed | — |
| Gabapentin 600 mg 51224-0021-50 | TAGI | 100 tablets | $0.098 | AB1 | Discontinued | — |
| Gabapentin 600 mg 31722-0092-90 | Camber | 90 tablets | $1.025 | AB2 | Availability likely | — |
| Gabapentin 600 mg 42806-0657-09 | Epic | 90 tablets | $1.025 | AB2 | Availability likely | — |
| Gralise 600 mg 52427-0806-90 | Almatica | 90 tablets | $10.153 | AB2 | Availability likely | — |
| Neurontin 600 mg 00071-0513-24 | Parke-Davis | 100 tablets | $14.084 | AB1 | Discontinued | — |
| Neurontin 600 mg 58151-0284-01 | Viatris | 100 tablets | $14.119 | AB1 | Availability likely | — |
| Gabapentin 600 mg 42385-0979-01 | Laurus | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 50090-6854-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 50090-6855-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 50090-7268-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 50090-7269-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 50090-7714-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 50090-7715-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 55154-3357-00 | Cardinal | 1 tablet | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 55154-8189-00 | Cardinal | 1 tablet | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 55289-0959-30 | PD-Rx | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 58118-0166-08 | Clinical | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 60760-0066-60 | St. | 60 tablets | — | AB1 | Discontinued | — |
| Gabapentin 600 mg 60760-0743-90 | St. | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 60760-0987-90 | St. | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 63187-0057-00 | Proficient | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mgthis 63187-0785-00 | Proficient | 100 tablets | — | — | FDA listed | — |
| Gabapentin 600 mg 63629-3063-00 | Bryant | 45 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 63629-7307-01 | Bryant | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 63629-8491-01 | Bryant | 500 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 63629-8492-01 | Bryant | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 65841-0705-01 | Zydus | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 67046-1535-03 | Coupler | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 68071-3445-03 | NuCare | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 68071-3783-09 | NuCare | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 68788-8476-01 | Preferred | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 68788-8488-01 | Preferred | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 69097-0812-02 | Cipla | 30 tablets | — | — | FDA listed | — |
| Gabapentin 600 mg 70518-2098-00 | REMEDYREPACK | 30 tablets | — | AB1 | Discontinued | — |
| Gabapentin 600 mg 70518-2356-00 | REMEDYREPACK | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 70518-2616-03 | REMEDYREPACK | 30 tablets | — | AB1 | Discontinued | — |
| Gabapentin 600 mg 70518-2842-00 | REMEDYREPACK | 28 tablets | — | AB1 | Discontinued | — |
| Gabapentin 600 mg 70518-4532-00 | REMEDYREPACK | 1 tablet | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71205-0457-30 | Proficient | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71205-0533-30 | Proficient | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71205-0931-00 | Proficient | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-1026-01 | Bryant | 90 tablets | — | AB1 | Discontinued | — |
| Gabapentin 600 mg 71335-1132-00 | Bryant | 28 tablets | — | AB1 | Discontinued | — |
| Gabapentin 600 mg 71335-1200-00 | Bryant | 28 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-1287-00 | Bryant | 28 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-2048-01 | Bryant | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-2281-01 | Bryant | 500 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-2701-00 | Bryant | 28 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-2719-01 | Bryant | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-3060-00 | Bryant | 28 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71335-3143-01 | Bryant | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71610-0044-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| gabapentin 600 mg 71610-0069-45 | Aphena | 45 tablets | — | — | FDA listed | — |
| Gabapentin 600 mg 71610-0621-15 | Aphena | 15 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71610-0767-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 71610-0777-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 72162-1530-01 | Bryant | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 72162-2141-01 | Bryant | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 72189-0313-60 | Directrx | 60 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 72189-0471-30 | Direct_Rx | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 72789-0127-30 | PD-Rx | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 72865-0255-05 | XLCare | 500 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 72888-0131-00 | Advagen | 1000 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 76420-0235-12 | Asclemed | 120 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 76420-0836-01 | Asclemed | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 77771-0177-05 | Radha | 500 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 80425-0097-01 | Advanced | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 80425-0201-01 | Advanced | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 82619-0145-01 | Creekwood | 100 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 82804-0015-30 | Proficient | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 82804-0193-30 | Proficient | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 82804-0210-90 | Proficient | 90 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 83008-0063-60 | Quality | 60 tablets | — | AB1 | Discontinued | — |
| Gabapentin 600 mg 87441-0036-01 | Unit | 30 tablets | — | AB1 | FDA listed | — |
| gabapentin 600 mg 50228-0524-05 | ScieGen | 500 tablets | — | AB2 | FDA listed | — |
| gabapentin 600 mg 68382-0607-05 | Zydus | 500 tablets | — | AB2 | FDA listed | — |
| gabapentin 600 mg 70771-1862-04 | Zydus | 100 tablets | — | AB2 | FDA listed | — |
| Gabapentin 600 mg 85534-0009-00 | HAWAII | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 67046-1086-03 | Coupler | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 67046-1233-03 | Coupler | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 85509-1166-03 | PHOENIX | 30 tablets | — | AB1 | FDA listed | — |
| Gabapentin 600 mg 58118-2126-08 | Clinical | 30 tablets | — | AB1 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII RFW2ET671P
Hydroxypropyl cellulose is a plant-derived thickening agent made from cellulose. It acts as a binder to hold tablet ingredients together and as a film-former to coat tablets or control how fast the medicine releases.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Gabapentin is indicated for: • Postherpetic neuralgia in adults ( 1 ) • Adjunctive therapy in the treatment of partial onset seizures, with and without secondary generalization, in adults and pediatric patients 3 years and older with epilepsy ( 1 ) Gabapentin Tablets, USP is indicated for: • Management of postherpetic neuralgia in adults • Adjunctive therapy in the treatment of partial onset seizures, with and without secondary generalization, in adults and pediatric patients 3 years and older with epilepsy
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Postherpetic Neuralgia ( 2.1 ) • Dose can be titrated up as needed to a dose of 1800 mg/day • Day 1: Single 300 mg dose • Day 2: 600 mg/day (i.e., 300 mg two times a day) • Day 3: 900 mg/day (i.e., 300 mg three times a day) • Epilepsy with Partial Onset Seizures ( 2.2 ) • Patients 12 years of age and older: starting dose is 300 mg three times daily; may be titrated up to 600 mg three times daily • Patients 3 to 11 years of age: starting dose range is 10 to 15 mg/kg/day, given in three divided doses; recommended dose in patients 3 to 4 years of age is 40 mg/kg/day, given in three divided doses; the recommended dose in patients 5 to 11 years of age is 25 to 35 mg/kg/day, given in three divided doses.
The recommended dose is reached by upward titration over a period of approximately 3 days • Dose should be adjusted in patients with reduced renal function ( 2.3 , 2.4 )
2.1Dosage for Postherpetic Neuralgia In adults with postherpetic neuralgia, gabapentin may be initiated on Day 1 as a single 300 mg dose, on Day 2 as 600 mg/day (300 mg two times a day), and on Day 3 as 900 mg/day (300 mg three times a day). The dose can subsequently be titrated up as needed for pain relief to a dose of 1800 mg/day (600 mg three times a day). In clinical studies, efficacy was demonstrated over a range of doses from 1800 mg/day to 3600 mg/day with comparable effects across the dose range; however, in these clinical studies, the additional benefit of using doses greater than 1800 mg/day was not demonstrated.
2.2Dosage for Epilepsy with Partial Onset Seizures Patients 12 years of age and above The starting dose is 300 mg three times a day. The recommended maintenance dose of gabapentin tablets is 300 mg to 600 mg three times a day. Dosages up to 2400 mg/day have been well tolerated in long-term clinical studies.
Doses of 3600 mg/day have also been administered to a small number of patients for a relatively short duration, and have been well tolerated. Administer gabapentin tablets three times a day using 600 mg or 800 mg tablets. The maximum time between doses should not exceed 12 hours.
Pediatric Patients Age 3 to 11 years The starting dose range is 10 mg/kg/day to 15 mg/kg/day, given in three divided doses, and the recommended maintenance dose reached by upward titration over a period of approximately 3 days. The recommended maintenance dose of gabapentin in patients 3 to 4 years of age is 40 mg/kg/day, given in three divided doses. The recommended maintenance dose of gabapentin in patients 5 to 11 years of age is 25 mg/kg/day to 35 mg/kg/day, given in three divided doses.
Gabapentin may be administered as the oral solution, capsule, or tablet, or using combinations of these formulations. Dosages up to 50 mg/kg/day have been well tolerated in a long-term clinical study. The maximum time interval between doses should not exceed 12 hours.
2.3Dosage Adjustment in Patients with Renal Impairment Dosage adjustment in patients 12 years of age and older with renal impairment or undergoing hemodialysis is recommended, as follows (see dosing recommendations above for effective doses in each indication): Creatinine clearance (CLCr) is difficult to measure in outpatients. In patients with stable renal function, creatinine clearance can be reasonably well estimated using the equation of Cockcroft and Gault: The use of gabapentin in patients less than 12 years of age with compromised renal function has not been studied. image image
2.4Dosage in Elderly Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and dose should be adjusted based on creatinine clearance values in these patients.
2.5Administration Information Administer gabapentin orally with or without food. Inform patients that, should they divide the scored 600 mg or 800 mg gabapentin tablet in order to administer a half-tablet, they should take the unused half-tablet as the next dose. Half-tablets not used w… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • Tablets: 600 mg, and 800 mg ( 3 ) Gabapentin Tablets, USP 600 mg : White colored film coated, Modified Capsule shaped, biconvex tablets debossed with '1' on the left side of the bisect and '2' on the right side of the bisect on one side and bisect on other. Gabapentin Tablets, USP 800 mg: White colored film coated, Modified Capsule shaped, biconvex tablets de-bossed with '1' on the left side of the bisect and '3' on the right side of the bisect on one side and bisect on other.
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Known hypersensitivity to gabapentin or its ingredients ( 4 ) Gabapentin Tablets, USP are contraindicated in patients who have demonstrated hypersensitivity to the drug or its ingredients.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Drug Reaction with Eosinophilia and Systemic Symptoms (Multiorgan hypersensitivity): discontinue gabapentin if an alternative etiology cannot be established ( 5.1 ) • Anaphylaxis and Angioedema: discontinue gabapentin and evaluate patient immediately ( 5.2 ) • Driving impairment: warn patients not to drive until they have gained sufficient experience with gabapentin to assess whether it will impair their ability to drive ( 5.3 ) • Somnolence/Sedation and Dizziness: gabapentin may impair the patient's ability to operate complex machinery ( 5.4 ) • Increased seizure frequency may occur in patients with seizure disorders if gabapentin is abruptly discontinued ( 5.5 ) • Suicidal Behavior and Ideation: monitor for suicidal thoughts and behavior ( 5.6 ) • Neuropsychiatric Adverse Reactions in Children 3 to 12 Years of Age: monitor for such events ( 5.7 )
5.1Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS), also known as multiorgan hypersensitivity, has occurred with gabapentin. Some of these reactions have been fatal or life-threatening. DRESS typically, although not exclusively, presents with fever, rash, and/or lymphadenopathy, in association with other organ system involvement, such as hepatitis, nephritis, hematological abnormalities, myocarditis, or myositis sometimes resembling an acute viral infection.
Eosinophilia is often present. This disorder is variable in its expression, and other organ systems not noted here may be involved. It is important to note that early manifestations of hypersensitivity, such as fever or lymphadenopathy, may be present even though rash is not evident.
If such signs or symptoms are present, the patient should be evaluated immediately. Gabapentin should be discontinued if an alternative etiology for the signs or symptoms cannot be established.
5.2Anaphylaxis and Angioedema Gabapentin can cause anaphylaxis and angioedema after the first dose or at any time during treatment. Signs and symptoms in reported cases have included difficulty breathing, swelling of the lips, throat, and tongue, and hypotension requiring emergency treatment. Patients should be instructed to discontinue gabapentin and seek immediate medical care should they experience signs or symptoms of anaphylaxis or angioedema.
5.3Effects on Driving and Operating Heavy Machinery Patients taking gabapentin should not drive until they have gained sufficient experience to assess whether gabapentin impairs their ability to drive. Driving performance studies conducted with a prodrug of gabapentin (gabapentin enacarbil tablet, extended release) indicate that gabapentin may cause significant driving impairment. Prescribers and patients should be aware that patients' ability to assess their own driving competence, as well as their ability to assess the degree of somnolence caused by gabapentin, can be imperfect.
The duration of driving impairment after starting therapy with gabapentin is unknown. Whether the impairment is related to somnolence [see Warnings and Precautions ( 5.4 )] or other effects of gabapentin is unknown. Moreover, because gabapentin causes somnolence and dizziness [see Warnings and Precautions ( 5.4 )] , patients should be advised not to operate complex machinery until they have gained sufficient experience on gabapentin to assess whether gabapentin impairs their ability to perform such tasks.
5.4Somnolence/Sedation and Dizziness During the controlled epilepsy trials in patients older than 12 years of age receiving doses of gabapentin up to 1800 mg daily, somnolence, dizziness, and ataxia were reported at a greater rate in patients receiving gabapentin compared to placebo: i.e., 19% in drug versus 9% in placebo for somnolence, 17% in drug versus 7% in placebo for dizziness, and 13% in drug versus 6% in placebo for ataxia. In these trials somnolence, ataxia and fatigue were common adverse reac… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (incidence ≥8% and at least twice that for placebo) were: • Postherpetic neuralgia: dizziness, somnolence, and peripheral edema ( 6.1 ) • Epilepsy in patients >12 years of age: somnolence, dizziness, ataxia, fatigue, and nystagmus ( 6.1 ) • Epilepsy in patients 3 to 12 years of age: viral infection, fever, nausea and/or vomiting, somnolence, and hostility ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Cipla Ltd. at 1-866-604-3268 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
The following serious adverse reactions are discussed in greater detail in other sections: • Drug Reaction with Eosinophilia and Systematic Symptoms (DRESS)/Multiorgan Hypersensitivity [see Warnings and Precautions ( 5.1 )] • Anaphylaxis and Angioedema [see Warnings and Precautions ( 5.2 )] • Somnolence/Sedation and Dizziness [see Warnings and Precautions ( 5.4 )] • Withdrawal Precipitated Seizure, Status Epilepticus [see Warnings and Precautions ( 5.5 )] • Suicidal Behavior and Ideation [see Warnings and Precautions ( 5.6 )] • Neuropsychiatric Adverse Reactions (Pediatric Patient 3 to 12 Years of Age) [see Warnings and Precautions ( 5.7 )] • Sudden and Unexplained Death in Patient with Epilepsy [see Warnings and Precautions ( 5.9 )]
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Postherpetic Neuralgia The most common adverse reactions associated with the use of gabapentin in adults, not seen at an equivalent frequency among placebo-treated patients, were dizziness, somnolence, and peripheral edema. In the 2 controlled trials in postherpetic neuralgia, 16% of the 336 patients who received gabapentin and 9% of the 227 patients who received placebo discontinued treatment because of an adverse reaction.
The adverse reactions that most frequently led to withdrawal in gabapentin-treated patients were dizziness, somnolence, and nausea. Table 3 lists adverse reactions that occurred in at least 1% of gabapentin-treated patients with postherpetic neuralgia participating in placebo-controlled trials and that were numerically more frequent in the gabapentin group than in the placebo group. Table 3.
Adverse Reactions in Pooled Placebo-Controlled Trials in Postherpetic Neuralgia a Reported as blurred vision GabapentinN=336 % Placebo N=227 % Body as a Whole Asthenia 6 5 Infection 5 4 Accidental injury 3 1 Digestive System Diarrhea 6 3 Dry mouth 5 1 Constipation 4 2 Nausea 4 3 Vomiting 3 2 Metabolic and Nutritional Disorders Peripheral edema 8 2 Weight gain 2 0 Hyperglycemia 1 0 Nervous System Dizziness 28 8 Somnolence 21 5 Ataxia 3 0 Thinking abnormal 3 0 Abnormal gait 2 0 Incoordination 2 0 Respiratory System Pharyngitis 1 0 Special Senses Amblyopia a 3 1 Conjunctivitis 1 0 Diplopia 1 0 Otitis media 1 0 Other reactions in more than 1% of patients but equally or more frequent in the placebo group included pain, tremor, neuralgia, back pain, dyspepsia, dyspnea, and flu syndrome.
There were no clinically important differences between men and women in the types and incidence of adverse reactions. Because there were few patients whose race was reported as other than white, there are insufficient data to support a statement regarding the distribution of adverse reactions by race. Epilepsy with Partial Onset Seizures (Adjunctive Therapy) The most common adverse reactions with gabapentin in combination with other antiepileptic drugs in patients >12 years of age, not seen at an equivalent frequency among placebo-treated patients, were somnolence, dizziness, ataxia, fatigue, and nystagmus.
The most common adverse reactions with gabapentin in combination with other antiepileptic drugs in pediatric patients 3 to 12 years of age, not seen at an equal frequency among placebo-tre… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Morphine increases gabapentin concentrations; dose adjustment may be needed ( 5.4 , 7.2 )
7.1Other Antiepileptic Drugs Gabapentin is not appreciably metabolized nor does it interfere with the metabolism of commonly coadministered antiepileptic drugs [see Clinical Pharmacology ( 12.3 )] .
7.2Opioids Hydrocodone Coadministration of gabapentin with hydrocodone decreases hydrocodone exposure [see Clinical Pharmacology ( 12.3 )] . The potential for alteration in hydrocodone exposure and effect should be considered when gabapentin is started or discontinued in a patient taking hydrocodone. Morphine When gabapentin is administered with morphine, patients should be observed for signs of central nervous system (CNS) depression, such as somnolence, sedation and respiratory depression [see Clinical Pharmacology ( 12.3 )].
7.3Maalox®(aluminum hydroxide, magnesium hydroxide) The mean bioavailability of gabapentin was reduced by about 20% with concomitant use of an antacid (Maalox ® ) containing magnesium and aluminum hydroxides. It is recommended that gabapentin be taken at least 2 hours following Maalox administration [see Clinical Pharmacology ( 12.3 )] .
7.4Drug/Laboratory Test Interactions Because false positive readings were reported with the Ames N-Multistix SG ® dipstick test for urinary protein when gabapentin was added to other antiepileptic drugs, the more specific sulfosalicylic acid precipitation procedure is recommended to determine the presence of urine protein.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Pregnancy: based on animal data, may cause fetal harm. ( 8.1 ) • Pediatric Use: effectiveness as adjunctive therapy in treatment of partial seizures in pediatric patients below the age of 3 years has not been established ( 8.4 )
8.1Pregnancy Pregnancy Category C : There are no adequate and well-controlled studies in pregnant women. In nonclinical studies in mice, rats, and rabbits, gabapentin was developmentally toxic when administered to pregnant animals at doses similar to or lower than those used clinically. Gabapentin should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
When pregnant mice received oral doses of gabapentin (500 mg, 1000 mg, or 3000 mg/kg/day) during the period of organogenesis, embryo-fetal toxicity (increased incidences of skeletal variations) was observed at the two highest doses. The no-effect dose for embryo-fetal developmental toxicity in mice was 500 mg/kg/day or approximately ½ of the maximum recommended human dose (MRHD) of 3600 mg/kg on a body surface area (mg/m 2 ) basis. In studies in which rats received oral doses of gabapentin (500 to 2000 mg/kg/day), during pregnancy, adverse effect on offspring development (increased incidences of hydroureter and/or hydronephrosis) were observed at all doses.
The lowest effect dose for developmental toxicity in rats is approximately equal to the MRHD on a mg/m 2 basis. When pregnant rabbits were treated with gabapentin during the period of organogenesis, an increase in embryo-fetal mortality was observed at all doses tested (60 mg, 300 mg, or 1500 mg/kg). The lowest effect dose for embryo-fetal developmental toxicity in rabbits is less than the MRHD on a mg/m 2 basis.
In a published study, gabapentin (400 mg/kg/day) was administered by intraperitoneal injection to neonatal mice during the first postnatal week, a period of synaptogenesis in rodents (corresponding to the last trimester of pregnancy in humans). Gabapentin caused a marked decrease in neuronal synapse formation in brains of intact mice and abnormal neuronal synapse formation in a mouse model of synaptic repair. Gabapentin has been shown in vitro to interfere with activity of the α2δ subunit of voltage-activated calcium channels, a receptor involved in neuronal synaptogenesis.
The clinical significance of these findings is unknown. To provide information regarding the effects of in utero exposure to gabapentin, physicians are advised to recommend that pregnant patients taking gabapentin enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves.
Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/ .
8.3Nursing Mothers Gabapentin is secreted into human milk following oral administration. A nursed infant could be exposed to a maximum dose of approximately 1 mg/kg/day of gabapentin. Because the effect on the nursing infant is unknown, gabapentin should be used in women who are nursing only if the benefits clearly outweigh the risks.
8.4Pediatric Use Safety and effectiveness of gabapentin in the management of postherpetic neuralgia in pediatric patients have not been established. Effectiveness as adjunctive therapy in the treatment of partial seizures in pediatric patients below the age of 3 years has not been established [see Clinical Studies ( 14.2 )] .
8.5Geriatric Use The total number of patients treated with gabapentin in controlled clinical trials in patients with postherpetic neuralgia was 336, of which 102 (30%) were 65 to 74 years of age, and 168 (50%) were 75 years of age and older. There was a larger treatment effect in patients 75 years of age and older compared with younger patients who received the same dosage. Since gabapentin is almost exclusively eliminated by renal excretion, the larger treatment effect observed in patients ≥75 years… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Category C : There are no adequate and well-controlled studies in pregnant women. In nonclinical studies in mice, rats, and rabbits, gabapentin was developmentally toxic when administered to pregnant animals at doses similar to or lower than those used clinically. Gabapentin should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
When pregnant mice received oral doses of gabapentin (500 mg, 1000 mg, or 3000 mg/kg/day) during the period of organogenesis, embryo-fetal toxicity (increased incidences of skeletal variations) was observed at the two highest doses. The no-effect dose for embryo-fetal developmental toxicity in mice was 500 mg/kg/day or approximately ½ of the maximum recommended human dose (MRHD) of 3600 mg/kg on a body surface area (mg/m 2 ) basis. In studies in which rats received oral doses of gabapentin (500 to 2000 mg/kg/day), during pregnancy, adverse effect on offspring development (increased incidences of hydroureter and/or hydronephrosis) were observed at all doses.
The lowest effect dose for developmental toxicity in rats is approximately equal to the MRHD on a mg/m 2 basis. When pregnant rabbits were treated with gabapentin during the period of organogenesis, an increase in embryo-fetal mortality was observed at all doses tested (60 mg, 300 mg, or 1500 mg/kg). The lowest effect dose for embryo-fetal developmental toxicity in rabbits is less than the MRHD on a mg/m 2 basis.
In a published study, gabapentin (400 mg/kg/day) was administered by intraperitoneal injection to neonatal mice during the first postnatal week, a period of synaptogenesis in rodents (corresponding to the last trimester of pregnancy in humans). Gabapentin caused a marked decrease in neuronal synapse formation in brains of intact mice and abnormal neuronal synapse formation in a mouse model of synaptic repair. Gabapentin has been shown in vitro to interfere with activity of the α2δ subunit of voltage-activated calcium channels, a receptor involved in neuronal synaptogenesis.
The clinical significance of these findings is unknown. To provide information regarding the effects of in utero exposure to gabapentin, physicians are advised to recommend that pregnant patients taking gabapentin enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll free number 1-888-233-2334, and must be done by patients themselves.
Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/ .
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness of gabapentin in the management of postherpetic neuralgia in pediatric patients have not been established. Effectiveness as adjunctive therapy in the treatment of partial seizures in pediatric patients below the age of 3 years has not been established [see Clinical Studies ( 14.2 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use The total number of patients treated with gabapentin in controlled clinical trials in patients with postherpetic neuralgia was 336, of which 102 (30%) were 65 to 74 years of age, and 168 (50%) were 75 years of age and older. There was a larger treatment effect in patients 75 years of age and older compared with younger patients who received the same dosage. Since gabapentin is almost exclusively eliminated by renal excretion, the larger treatment effect observed in patients ≥75 years may be a consequence of increased gabapentin exposure for a given dose that results from an age-related decrease in renal function.
However, other factors cannot be excluded. The types and incidence of adverse reactions were similar across age groups except for peripheral edema and ataxia, which tended to increase in incidence with age. Clinical studies of gabapentin in epilepsy did not include sufficient numbers of subjects aged 65 and over to determine whether they responded differently from younger subjects.
Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy. This drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function.
Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, and dose should be adjusted based on creatinine clearance values in these patients [see Dosage and Administration ( 2.4 ), Adverse Reactions ( 6 ), and Clinical Pharmacology ( 12.3 )] .
🆘 Overdosage ▾
10 OVERDOSAGE A lethal dose of gabapentin was not identified in mice and rats receiving single oral doses as high as 8000 mg/kg. Signs of acute toxicity in animals included ataxia, labored breathing, ptosis, sedation, hypoactivity, or excitation. Acute oral overdoses of gabapentin up to 49 grams have been reported.
In these cases, double vision, slurred speech, drowsiness, lethargy, and diarrhea were observed. All patients recovered with supportive care. Coma, resolving with dialysis, has been reported in patients with chronic renal failure who were treated with gabapentin.
Gabapentin can be removed by hemodialysis. Although hemodialysis has not been performed in the few overdose cases reported, it may be indicated by the patient's clinical state or in patients with significant renal impairment. If overexposure occurs, call your poison control center at 1-800-222-1222.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The precise mechanisms by which gabapentin produces its analgesic and antiepileptic actions are unknown. Gabapentin is structurally related to the neurotransmitter gamma-aminobutyric acid (GABA) but has no effect on GABA binding, uptake, or degradation. In vitro studies have shown that gabapentin binds with high-affinity to the α2δ subunit of voltage-activated calcium channels; however, the relationship of this binding to the therapeutic effects of gabapentin is unknown.
12.3Pharmacokinetics All pharmacological actions following gabapentin administration are due to the activity of the parent compound; gabapentin is not appreciably metabolized in humans. Oral Bioavailability Gabapentin bioavailability is not dose proportional; i.e., as dose is increased, bioavailability decreases. Bioavailability of gabapentin is approximately 60%, 47%, 34%, 33%, and 27% following 900 mg, 1200 mg, 2400 mg, 3600 mg, and 4800 mg/day given in 3 divided doses, respectively.
Food has only a slight effect on the rate and extent of absorption of gabapentin (14% increase in AUC and Cmax). Distribution Less than 3% of gabapentin circulates bound to plasma protein. The apparent volume of distribution of gabapentin after 150 mg intravenous administration is 58±6 L (mean ±SD).
In patients with epilepsy, steady-state predose (Cmin) concentrations of gabapentin in cerebrospinal fluid were approximately 20% of the corresponding plasma concentrations. Elimination Gabapentin is eliminated from the systemic circulation by renal excretion as unchanged drug. Gabapentin is not appreciably metabolized in humans.
Gabapentin elimination half-life is 5 to 7 hours and is unaltered by dose or following multiple dosing. Gabapentin elimination rate constant, plasma clearance, and renal clearance are directly proportional to creatinine clearance. In elderly patients, and in patients with impaired renal function, gabapentin plasma clearance is reduced.
Gabapentin can be removed from plasma by hemodialysis. Specific Populations Age The effect of age was studied in subjects 20 to 80 years of age. Apparent oral clearance (CL/F) of gabapentin decreased as age increased, from about 225 mL/min in those under 30 years of age to about 125 mL/min in those over 70 years of age.
Renal clearance (CLr) and CLr adjusted for body surface area also declined with age; however, the decline in the renal clearance of gabapentin with age can largely be explained by the decline in renal function. [see Dosage and Administration ( 2.4 ) and Use in Specific Populations ( 8.5 )] . Gender Although no formal study has been conducted to compare the pharmacokinetics of gabapentin in men and women, it appears that the pharmacokinetic parameters for males and females are similar and there are no significant gender differences.
Race Pharmacokinetic differences due to race have not been studied. Because gabapentin is primarily renally excreted and there are no important racial differences in creatinine clearance, pharmacokinetic differences due to race are not expected. Pediatric Gabapentin pharmacokinetics were determined in 48 pediatric subjects between the ages of 1 month and 12 years following a dose of approximately 10 mg/kg.
Peak plasma concentrations were similar across the entire age group and occurred 2 to 3 hours postdose. In general, pediatric subjects between 1 month and <5 years of age achieved approximately 30% lower exposure (AUC) than that observed in those 5 years of age and older. Accordingly, oral clearance normalized per body weight was higher in the younger children.
Apparent oral clearance of gabapentin was directly proportional to creatinine clearance. Gabapentin elimination half-life averaged 4.7 hours and was similar across the age groups studied. A population pharmacokinetic analysis was performed in 253 pediatric subjects between 1 month and 13 years of age.
Patients received 10 to 65 mg/kg/day given three times a day. Apparent ora… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The precise mechanisms by which gabapentin produces its analgesic and antiepileptic actions are unknown. Gabapentin is structurally related to the neurotransmitter gamma-aminobutyric acid (GABA) but has no effect on GABA binding, uptake, or degradation. In vitro studies have shown that gabapentin binds with high-affinity to the α2δ subunit of voltage-activated calcium channels; however, the relationship of this binding to the therapeutic effects of gabapentin is unknown.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Gabapentin Tablets, USP are supplied as follows: Gabapentin Tablets, USP 600 mg : White colored film coated, Modified Capsule shaped, biconvex tablets de-bossed with '1' on the left side of the bisect and '2' on the right side of the bisect on one side and bisect on other. Bottles of 30's count: (NDC 63187-785-30) Bottles of 60's count: (NDC 63187-785-60) Bottles of 90's count: (NDC 63187-785-90) Bottles of 100's count: (NDC 63187-785-00) Bottles of 120's count: (NDC 63187-785-72) Store at 20°C to 25°C (68° to 77°F). [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION The active ingredient in gabapentin tablets is gabapentin USP, which has the chemical name 1-(aminomethyl) cyclohexaneacetic acid. The molecular formula of gabapentin USP is C 9 H 17 NO 2 and the molecular weight is 171.24. The structural formula of gabapentin is: Gabapentin, USP is a white to off-white crystalline solid with a pK a1 of 3.7 and a pK a2 of 10.7.
It is freely soluble in water and both basic and acidic aqueous solutions. The log of the partition coefficient (n-octanol/0.05M phosphate buffer) at pH 7.4 is –1.25. Gabapentin tablets, USP are white colored film coated, modified capsule shaped biconvex tablets containing 600 mg and 800 mg of gabapentin, USP.
The inactive ingredients are mannitol, Hydroxypropyl Cellulose, Crospovidone, Talc, Magnesium stearate and Aquarius® BP18114 Cool Vanilla. image
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Administration Information Inform patients that gabapentin is taken orally with or without food. Inform patients that, should they divide the scored 600 mg or 800 mg tablet in order to administer a half-tablet, they should take the unused half-tablet as the next dose.
Advise patients to discard half-tablets not used within 28 days of dividing the scored tablet. Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS)/Multiorgan Hypersensitivity Prior to initiation of treatment with gabapentin, instruct patients that a rash or other signs or symptoms of hypersensitivity (such as fever or lymphadenopathy) may herald a serious medical event and that the patient should report any such occurrence to a physician immediately [see Warnings and Precautions ( 5.1 )] . Anaphylaxis and Angioedema Advise patients to discontinue gabapentin and seek medical care if they develop signs or symptoms of anaphylaxis or angioedema [see Warnings and Precautions ( 5.2 )].
Dizziness and Somnolence and Effects on Driving and Operating Heavy Machinery Advise patients that gabapentin may cause dizziness, somnolence, and other symptoms and signs of CNS depression. Other drugs with sedative properties may increase these symptoms. Accordingly, although patients' ability to determine their level of impairment can be unreliable, advise them neither to drive a car nor to operate other complex machinery until they have gained sufficient experience on gabapentin to gauge whether or not it affects their mental and/or motor performance adversely.
Inform patients that it is not known how long this effect lasts [see Warnings and Precautions ( 5.3 ) and Warnings and Precautions ( 5.4 )]. Suicidal Thinking and Behavior Counsel the patient, their caregivers, and families that AEDs, including gabapentin, may increase the risk of suicidal thoughts and behavior. Advise patients of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm.
Instruct patients to report behaviors of concern immediately to healthcare providers [see Warnings and Precautions ( 5.6 )] . Use in Pregnancy Instruct patients to notify their physician if they become pregnant or intend to become pregnant during therapy, and to notify their physician if they are breast feeding or intend to breast feed during therapy [see Use in Specific Populations ( 8.1 ) and ( 8.3 )]. Encourage patients to enroll in the NAAED Pregnancy Registry if they become pregnant.
This registry is collecting information about the safety of antiepileptic drugs during pregnancy. To enroll, patients can call the toll free number 1-888-233-2334 [ see Use in Specific Populations ( 8.1 )]. Revised: 07/2016
💬 Medication Guide ▾
MEDICATION GUIDE Gabapentin Tablets, USP (gab-ah-PEN-tin) Read the Medication Guide before you start taking gabapentin tablets and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about gabapentin tablets? Do not stop taking gabapentin tablets without first talking to your healthcare provider. Stopping gabapentin tablets suddenly can cause serious problems.
Gabapentin tablets can cause serious side effects including: 1. Suicidal Thoughts. Like other antiepileptic drugs, gabapentin tablets may cause suicidal thoughts or actions in a very small number of people, about 1 in 500.
Call a healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: • thoughts about suicide or dying • attempts to commit suicide • new or worse depression • new or worse anxiety • feeling agitated or restless • panic attacks • trouble sleeping (insomnia) • new or worse irritability • acting aggressive, being angry, or violent • acting on dangerous impulses • an extreme increase in activity and talking (mania) • other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions? • Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. • Keep all follow-up visits with your healthcare provider as scheduled.
Call your healthcare provider between visits as needed, especially if you are worried about symptoms. Do not stop taking gabapentin tablets without first talking to a healthcare provider. • Stopping gabapentin tablets suddenly can cause serious problems. Stopping a seizure medicine suddenly in a patient who has epilepsy can cause seizures that will not stop (status epilepticus). • Suicidal thoughts or actions can be caused by things other than medicines.
If you have suicidal thoughts or actions, your healthcare provider may check for other causes. 2. Changes in behavior and thinking - Using gabapentin tablets in children 3 to 12 years of age can cause emotional changes, aggressive behavior, problems with concentration, restlessness, changes in school performance, and hyperactivity.
3. Gabapentin tablets may cause serious or life-threatening allergic reactions that may affect your skin or other parts of your body such as your liver or blood cells. This may cause you to be hospitalized or to stop gabapentin tablets.
You may or may not have a rash with an allergic reaction caused by gabapentin tablets. Call a healthcare provider right away if you have any of the following symptoms: • skin rash • hives • difficulty breathing • fever • swollen glands that do not go away • swelling of your face, lips, throat, or tongue • yellowing of your skin or of the whites of the eyes • unusual bruising or bleeding • severe fatigue or weakness • unexpected muscle pain • frequent infections These symptoms may be the first signs of a serious reaction.
A healthcare provider should examine you to decide if you should continue taking gabapentin tablets. What are gabapentin tablets? Gabapentin tablets are a prescription medicine used to treat: • Pain from damaged nerves (postherpetic pain) that follows healing of shingles (a painful rash that comes after a herpes zoster infection) in adults. • Partial seizures when taken together with other medicines in adults and children 3 years of age and older with seizures.
Who should not take gabapentin tablets? Do not take gabapentin tablets if you are allergic to gabapentin or any of the other ingredients in gabapentin tablets. See the end of this Medication Guide for a complete list of ingredients in gabapentin tablets.
What should I tell my healthcare provider before taking gabapentin tablets? Before taking gabapentin tablets, tell your healthcare provider if you: • have or have had kidney problems or are on hemod… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
8.3Nursing Mothers Gabapentin is secreted into human milk following oral administration. A nursed infant could be exposed to a maximum dose of approximately 1 mg/kg/day of gabapentin. Because the effect on the nursing infant is unknown, gabapentin should be used in women who are nursing only if the benefits clearly outweigh the risks.
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics All pharmacological actions following gabapentin administration are due to the activity of the parent compound; gabapentin is not appreciably metabolized in humans. Oral Bioavailability Gabapentin bioavailability is not dose proportional; i.e., as dose is increased, bioavailability decreases. Bioavailability of gabapentin is approximately 60%, 47%, 34%, 33%, and 27% following 900 mg, 1200 mg, 2400 mg, 3600 mg, and 4800 mg/day given in 3 divided doses, respectively.
Food has only a slight effect on the rate and extent of absorption of gabapentin (14% increase in AUC and Cmax). Distribution Less than 3% of gabapentin circulates bound to plasma protein. The apparent volume of distribution of gabapentin after 150 mg intravenous administration is 58±6 L (mean ±SD).
In patients with epilepsy, steady-state predose (Cmin) concentrations of gabapentin in cerebrospinal fluid were approximately 20% of the corresponding plasma concentrations. Elimination Gabapentin is eliminated from the systemic circulation by renal excretion as unchanged drug. Gabapentin is not appreciably metabolized in humans.
Gabapentin elimination half-life is 5 to 7 hours and is unaltered by dose or following multiple dosing. Gabapentin elimination rate constant, plasma clearance, and renal clearance are directly proportional to creatinine clearance. In elderly patients, and in patients with impaired renal function, gabapentin plasma clearance is reduced.
Gabapentin can be removed from plasma by hemodialysis. Specific Populations Age The effect of age was studied in subjects 20 to 80 years of age. Apparent oral clearance (CL/F) of gabapentin decreased as age increased, from about 225 mL/min in those under 30 years of age to about 125 mL/min in those over 70 years of age.
Renal clearance (CLr) and CLr adjusted for body surface area also declined with age; however, the decline in the renal clearance of gabapentin with age can largely be explained by the decline in renal function. [see Dosage and Administration ( 2.4 ) and Use in Specific Populations ( 8.5 )] . Gender Although no formal study has been conducted to compare the pharmacokinetics of gabapentin in men and women, it appears that the pharmacokinetic parameters for males and females are similar and there are no significant gender differences.
Race Pharmacokinetic differences due to race have not been studied. Because gabapentin is primarily renally excreted and there are no important racial differences in creatinine clearance, pharmacokinetic differences due to race are not expected. Pediatric Gabapentin pharmacokinetics were determined in 48 pediatric subjects between the ages of 1 month and 12 years following a dose of approximately 10 mg/kg.
Peak plasma concentrations were similar across the entire age group and occurred 2 to 3 hours postdose. In general, pediatric subjects between 1 month and <5 years of age achieved approximately 30% lower exposure (AUC) than that observed in those 5 years of age and older. Accordingly, oral clearance normalized per body weight was higher in the younger children.
Apparent oral clearance of gabapentin was directly proportional to creatinine clearance. Gabapentin elimination half-life averaged 4.7 hours and was similar across the age groups studied. A population pharmacokinetic analysis was performed in 253 pediatric subjects between 1 month and 13 years of age.
Patients received 10 to 65 mg/kg/day given three times a day. Apparent oral clearance (CL/F) was directly proportional to creatinine clearance and this relationship was similar following a single dose and at steady state. Higher oral clearance values were observed in children <5 years of age compared to those observed in children 5 years of age and older, when normalized per body weight.
The clearance was highly variable in infants <1 year of age. The normalized CL/F values observed in pediatric patients 5 years of age and older were consistent with values observed in adults after a single dos… [Excerpted — this section continues on DailyMed.]
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Postherpetic Neuralgia Gabapentin was evaluated for the management of postherpetic neuralgia (PHN) in two randomized, double-blind, placebo-controlled, multicenter studies. The intent-to-treat (ITT) population consisted of a total of 563 patients with pain for more than 3 months after healing of the herpes zoster skin rash (Table 6). Table 6.
Controlled PHN Studies: Duration, Dosages, and Number of Patients a Given in 3 divided doses (TID) Study Study Duration Gabapentin (mg/day) a Target Dose Patients Receiving Gabapentin Patients Receiving Placebo 1 8 weeks 3600 113 116 2 7 weeks 1800, 2400 223 111 Total 336 227 Patients initiated treatment with titration to a maximum of 900 mg/day gabapentin over 3 days. Dosages were then to be titrated in 600 to 1200 mg/day increments at 3- to 7-day intervals to the target dose over 3 to 4 weeks. Patients recorded their pain in a daily diary using an 11-point numeric pain rating scale ranging from 0 (no pain) to 10 (worst possible pain).
A mean pain score during baseline of at least 4 was required for randomization. Analyses were conducted using the ITT population (all randomized patients who received at least one dose of study medication). Both studies demonstrated efficacy compared to placebo at all doses tested.
The reduction in weekly mean pain scores was seen by Week 1 in both studies, and were maintained to the end of treatment. Comparable treatment effects were observed in all active treatment arms. Pharmacokinetic/pharmacodynamic modeling provided confirmatory evidence of efficacy across all doses.
Figures 1 and 2 show pain intensity scores over time for Studies 1 and 2. Figure 1. Weekly Mean Pain Scores (Observed Cases in ITT Population): Study 1 Figure 2.
Weekly Mean Pain Scores (Observed cases in ITT Population): Study 2 The proportion of responders (those patients reporting at least 50% improvement in endpoint pain score compared with baseline) was calculated for each study (Figure 3). Figure 3. Proportion of Responders (patients with ≥50% reduction in pain score) at Endpoint: Controlled PHN Studies image image image
14.2Epilepsy for Partial Onset Seizures (Adjunctive Therapy) The effectiveness of gabapentin as adjunctive therapy (added to other antiepileptic drugs) was established in multicenter placebo-controlled, double-blind, parallel-group clinical trials in adult and pediatric patients (3 years and older) with refractory partial seizures. Evidence of effectiveness was obtained in three trials conducted in 705 patients (age 12 years and above) and one trial conducted in 247 pediatric patients (3 to 12 years of age). The patients enrolled had a history of at least 4 partial seizures per month in spite of receiving one or more antiepileptic drugs at therapeutic levels and were observed on their established antiepileptic drug regimen during a 12-week baseline period (6 weeks in the study of pediatric patients).
In patients continuing to have at least 2 (or 4 in some studies) seizures per month, gabapentin or placebo was then added on to the existing therapy during a 12-week treatment period. Effectiveness was assessed primarily on the basis of the percent of patients with a 50% or greater reduction in seizure frequency from baseline to treatment (the "responder rate") and a derived measure called response ratio, a measure of change defined as (T - B)/(T + B), in which B is the patient's baseline seizure frequency and T is the patient's seizure frequency during treatment.
Response ratio is distributed within the range -1 to +1. A zero value indicates no change while complete elimination of seizures would give a value of -1; increased seizure rates would give positive values. A response ratio of -0.33 corresponds to a 50% reduction in seizure frequency.
The results given below are for all partial seizures in the intent-to-treat (all patients who received any doses of treatment) population in each study, unless otherwise indicated. One study compared ga… [Excerpted — this section continues on DailyMed.]
🔒 Drug Abuse and Dependence ▾
9 DRUG ABUSE AND DEPENDENCE
9.1Controlled Substance Gabapentin is not a scheduled drug.
9.2Abuse Gabapentin does not exhibit affinity for benzodiazepine, opiate (mu, delta or kappa), or cannabinoid 1 receptor sites. A small number of postmarketing cases report gabapentin misuse and abuse. These individuals were taking higher than recommended doses of gabapentin for unapproved uses.
Most of the individuals described in these reports had a history of poly-substance abuse or used gabapentin to relieve symptoms of withdrawal from other substances. When prescribing gabapentin carefully evaluate patients for a history of drug abuse and observe them for signs and symptoms of gabapentin misuse or abuse (e.g., development of tolerance, self-dose escalation, and drug-seeking behavior).
9.3Dependence There are rare postmarketing reports of individuals experiencing withdrawal symptoms shortly after discontinuing higher than recommended doses of gabapentin used to treat illnesses for which the drug is not approved. Such symptoms included agitation, disorientation and confusion after suddenly discontinuing gabapentin that resolved after restarting gabapentin. Most of these individuals had a history of poly-substance abuse or used gabapentin to relieve symptoms of withdrawal from other substances.
The dependence and abuse potential of gabapentin has not been evaluated in human studies.
🔒 Controlled Substance ▾
9.1Controlled Substance Gabapentin is not a scheduled drug.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Gabapentin was administered orally to mice and rats in 2-year carcinogenicity studies. No evidence of drug-related carcinogenicity was observed in mice treated at doses up to 2000 mg/kg/day. At 2000 mg/kg, the plasma gabapentin exposure (AUC) in mice is approximately 2 times that in humans at the MRHD of 3600 mg/day.
In rats, increases in the incidence of pancreatic acinar cell adenoma and carcinoma were found in male rats receiving the highest dose (2000 mg/kg), but not at doses of 250 or 1000 mg/kg/day. At 1000 mg/kg, the plasma gabapentin exposure (AUC) in rats is approximately 5 times that in humans at the MRHD. Studies designed to investigate the mechanism of gabapentin-induced pancreatic carcinogenesis in rats indicate that gabapentin stimulates DNA synthesis in rat pancreatic acinar cells in vitro and, thus, may be acting as a tumor promoter by enhancing mitogenic activity.
It is not known whether gabapentin has the ability to increase cell proliferation in other cell types or in other species, including humans. Gabapentin did not demonstrate mutagenic or genotoxic potential in three in vitro and four in vivo assays. It was negative in the Ames test and the in vitro HGPRT forward mutation assay in Chinese hamster lung cells; it did not produce significant increases in chromosomal aberrations in the in vitro Chinese hamster lung cell assay; it was negative in the in vivo chromosomal aberration assay and in the in vivo micronucleus test in Chinese hamster bone marrow; it was negative in the in vivo mouse micronucleus assay; and it did not induce unscheduled DNA synthesis in hepatocytes from rats given gabapentin.
No adverse effects on fertility or reproduction were observed in rats at doses up to 2000 mg/kg. At 2000 mg/kg, the plasma gabapentin exposure (AUC) in rats is approximately 8 times that in humans at the MRHD.
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES • Warnings and Precautions: Anaphylaxis and Angioedema: discontinue gabapentin and evaluate patient immediately ( 5.2 ) 9/2015
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 63187-785-90 Rx ONLY Gabapentin Tablets, USP 600mg PHARMACIST: Dispense the Medication Guide provided separately to each patient. 90 Tablets Cipla 63187-785-90
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |