
Lovastatin 10 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the HMG-CoA Reductase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Lovastatin's main job is to lower your LDL — the 'bad' cholesterol — by reducing how much your liver makes on its own. Over time, that helps slow the buildup of fatty deposits in y...
- What exactly is lovastatin supposed to do for me?
- Take it with a meal — your evening meal is ideal for once-daily dosing. Studies show the body absorbs lovastatin much better when there's food in your stomach. One important heads-...
- Should I take lovastatin with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Lovastatin — tap one for details:
Lovastatin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII REK4960K2U
Butylated hydroxyanisole is a synthetic preservative that prevents oils and fats in medicines from spoiling or becoming rancid. It keeps the medicine stable and extends its shelf life.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1433 | $4.30 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lovastatin 10 mg 00093-0926-06 | Teva | 60 tablets | $0.037 | AB | Availability likely | — |
| Lovastatin 10 mg 61442-0141-01 | Carlsbad | 100 tablets | $0.037 | AB | Availability likely | — |
| Lovastatin 10 mg 68001-0314-00 | BluePoint | 100 tablets | $0.037 | AB | Availability likely | — |
| Lovastatin 10 mg 68180-0467-01 | Lupin | 100 tablets | $0.037 | AB | Availability likely | — |
| Lovastatin 10 mg 50090-3268-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 50090-3396-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 51407-0251-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 51655-0686-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 51655-0873-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 63187-0194-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 63187-0814-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mgthis 63629-1018-02 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 63629-1178-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 63629-1191-01 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 63629-3583-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 66267-0506-30 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 68071-3622-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 68071-4955-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 68788-7056-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 71205-0992-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Lovastatin 10 mg 72162-1739-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 63629-1018-00 | 1000 TABLET in 1 BOTTLE (63629-1018-0) | 2021-10-21 | Active |
| 63629-1018-01 | 100 TABLET in 1 BOTTLE (63629-1018-1) | 2021-10-21 | Active |
| 63629-1018-02 You're viewing this | 30 TABLET in 1 BOTTLE (63629-1018-2) | 2021-10-21 | Active |
| 63629-1018-03 | 300 TABLET in 1 BOTTLE (63629-1018-3) | 2021-10-21 | Active |
| 63629-1018-04 | 120 TABLET in 1 BOTTLE (63629-1018-4) | 2019-12-16 | Active |
| 63629-1018-05 | 500 TABLET in 1 BOTTLE (63629-1018-5) | 2019-12-10 | Active |
| 63629-1018-06 | 60 TABLET in 1 BOTTLE (63629-1018-6) | 2021-10-21 | Active |
| 63629-1018-08 | 800 TABLET in 1 BOTTLE (63629-1018-8) | 2021-10-21 | Active |
| 63629-1018-09 | 90 TABLET in 1 BOTTLE (63629-1018-9) | 2021-10-21 | Active |
You're viewing the smallest of 9 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 63629-1018-02?
What is the difference between NDC 63629-1018-02 and NDC 63629-1018-06?
What NDC number is used to bill for this package of Lovastatin 10 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Therapy with lovastatin should be a component of multiple risk factor intervention in those individuals with dyslipidemia at risk for atherosclerotic vascular disease. Lovastatin should be used in addition to a diet restricted in saturated fat and cholesterol as part of a treatment strategy to lower total-C and LDL-C to target levels when the response to diet and other nonpharmacological measures alone has been inadequate to reduce risk. Primary Prevention of Coronary Heart Disease In individuals without symptomatic cardiovascular disease, average to moderately elevated total-C and LDL-C, and below average HDL-C, lovastatin is indicated to reduce the risk of: Myocardial infarction Unstable angina Coronary revascularization procedures (See CLINICAL PHARMACOLOGY , Clinical Studies .) Coronary Heart Disease Lovastatin is indicated to slow the progression of coronary atherosclerosis in patients with coronary heart disease as part of a treatment strategy to lower total-C and LDL-C to target levels.
Hypercholesterolemia Therapy with lipid-altering agents should be a component of multiple risk factor intervention in those individuals at significantly increased risk for artherosclerotic vascular disease due to hypercholesterolemia. Lovastatin is indicated as an adjunct to diet for the reduction of elevated total-C and LDL-C levels in patients with primary hypercholesterolemia (Types IIa and IIb 2 ), when the response to diet restricted in saturated fat and cholesterol and to other nonpharmacological measures alone has been inadequate.
Adolescent Patients with Heterozygous Familial Hypercholesterolemia Lovastatin is indicated as an adjunct to diet to reduce total-C, LDL-C and apolipoprotein B levels in adolescent boys and girls who are at least one year post-menarche, 10 to 17 years of age, with heFH if after an adequate trial of diet therapy the following findings are present: LDL-C remains >189 mg/dL or LDL-C remains >160 mg/dL and: there is a positive family history of premature cardiovascular disease or two or more other CVD risk factors are present in the adolescent patient General Recommendations Prior to initiating therapy with lovastatin, secondary causes for hypercholesterolemia (e.g., poorly controlled diabetes mellitus, hypothyroidism, nephrotic syndrome, dysproteinemias, obstructive liver disease, other drug therapy, alcoholism) should be excluded, and a lipid profile performed to measure total-C, HDL-C, and TG.
For patients with TG less than 400 mg/dL (<4.5 mmol/L), LDL-C can be estimated using the following equation: LDL-C = total-C - [0.2 × (TG) + HDL-C] For TG levels >400 mg/dL (>4.5 mmol/L), this equation is less accurate and LDL-C concentrations should be determined by ultracentrifugation. In hypertriglyceridemic patients, LDL-C may be low or normal despite elevated total-C. In such cases, lovastatin is not indicated.
The National Cholesterol Education Program (NCEP) Treatment Guidelines are summarized below: † CHD, coronary heart disease †† Some authorities recommend use of LDL-lowering drugs in this category if an LDL-C level of <100 mg/dL cannot be achieved by therapeutic lifestyle changes. Others prefer use of drugs that primarily modify triglycerides and HDL-C, e.g., nicotinic acid or fibrate. Clinical judgment also may call for deferring drug therapy in this subcategory. ††† Almost all people with 0-1 risk factor have a 10-year risk <10%; thus, 10-year risk assessment in people with 0-1 risk factor is not necessary.
NCEP Treatment Guidelines: LDL-C Goals and Cutpoints for Therapeutic Lifestyle Changes and Drug Therapy in Different Risk Categories Risk Category LDL Goal (mg/dL) LDL Level at Which to Initiate Therapeutic Lifestyle Changes (mg/dL) LDL Level at Which to Consider Drug Therapy (mg/dL) CHD † or CHD risk equivalents (10-year risk >20%) <100 ≥100 ≥130 (100-129: drug optional) †† 2+ Risk factors (10 year risk ≤20%) <130 ≥130 10-year risk 10-20%: ≥130 10-year risk <10%: ≥160 0-1 Risk…
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The patient should be placed on a standard cholesterol-lowering diet before receiving lovastatin and should continue on this diet during treatment with lovastatin (see NCEP Treatment Guidelines for details on dietary therapy). Lovastatin should be given with meals. Adult Patients The usual recommended starting dose is 20 mg once a day given with the evening meal.
The recommended dosing range is 10 to 80 mg/day in single or two divided doses; the maximum recommended dose is 80 mg/day. Doses should be individualized according to the recommended goal of therapy (see NCEP Guidelines and CLINICAL PHARMACOLOGY ). Patients requiring reductions in LDL-C of 20% or more to achieve their goal (see INDICATIONS AND USAGE ) should be started on 20 mg/day of lovastatin.
A starting dose of 10 mg may be considered for patients requiring smaller reductions. Adjustments should be made at intervals of 4 weeks or more. Cholesterol levels should be monitored periodically and consideration should be given to reducing the dosage of lovastatin if cholesterol levels fall significantly below the targeted range.
⛔ Contraindications ▾
CONTRAINDICATIONS Hypersensitivity to any component of this medication. Active liver disease or unexplained persistent elevations of serum transaminases (see WARNINGS ). Concomitant administration with strong CYP3A4 inhibitors (e.g., itraconazole, ketoconazole, posaconazole, voriconazole, HIV protease inhibitors, boceprevir, telaprevir, erythromycin, clarithromycin, telithromycin ,nefazodone, and cobicistat-containing products) (see WARNINGS , Myopathy/Rhabdomyolysis ) .
Pregnancy and lactation. ( see PRECAUTIONS, Pregnancy and Nursing Mothers ). Atherosclerosis is a chronic process and the discontinuation of lipid-lowering drugs during pregnancy should have little impact on the outcome of long-term therapy of primary hypercholesterolemia.
Moreover, cholesterol and other products of the cholesterol biosynthesis pathway are essential components for fetal development, including synthesis of steroids and cell membranes. Because of the ability of inhibitors of HMG-CoA reductase such as lovastatin to decrease the synthesis of cholesterol and possibly other products of the cholesterol biosynthesis pathway, lovastatin is contraindicated during pregnancy and in nursing mothers. Lovastatin should be administered to women of childbearing age only when such patients are highly unlikely to conceive.
If the patient becomes pregnant while taking this drug, lovastatin should be discontinued immediately and the patient should be apprised of the potential hazard to the fetus (see PRECAUTIONS , Pregnancy ).
⚠️ Warnings ▾
WARNINGS Myopathy/Rhabdomyolysis Lovastatin, like other inhibitors of HMG-CoA reductase, occasionally causes myopathy manifested as muscle pain, tenderness or weakness with creatine kinase (CK) above 10 times the upper limit of normal (ULN). Myopathy sometimes takes the form of rhabdomyolysis with or without acute renal failure secondary to myoglobinuria, and rare fatalities have occurred. The risk of myopathy is increased by high levels of HMG-CoA reductase inhibitory activity in plasma.
The risk of myopathy/rhabdomyolysis is dose related. In a clinical study (EXCEL) in which patients were carefully monitored and some interacting drugs were excluded, there was one case of myopathy among 4933 patients randomized to lovastatin 20 to 40 mg daily for 48 weeks, and 4 among 1649 patients randomized to 80 mg daily. All patients starting therapy with lovastatin, or whose dose of lovastatin is being increased, should be advised of the risk of myopathy and told to report promptly any unexplained muscle pain, tenderness or weakness particularly if accompanied by malaise or fever or if muscle signs and symptoms persist after discontinuing Lovastatin.
Lovastatin therapy should be discontinued immediately if myopathy is diagnosed or suspected. In most cases, muscle symptoms and CK increases resolved when treatment was promptly discontinued. Periodic CK determinations may be considered in patients starting therapy with lovastatin or whose dose is being increased, but there is no assurance that such monitoring will prevent myopathy.
Many of the patients who have developed rhabdomyolysis on therapy with lovastatin have had complicated medical histories, including renal insufficiency usually as a consequence of long-standing diabetes mellitus. Such patients merit closer monitoring. Lovastatin therapy should be discontinued if markedly elevated CPK levels occur or myopathy is diagnosed or suspected.
Lovatsatin therapy should also be temporarily withheld in any patient experiencing an acute or serious condition predisposing to the development of renal failure secondary to rhabdomyolysis, e.g., sepsis; hypotension; major surgery; trauma; severe metabolic, endocrine, or electrolyte disorders; or uncontrolled epilepsy. The risk of myopathy/rhabdomyolysis is increased by concomitant use of lovastatin with the following: Strong inhibitors of CYP3A4: Lovastatin, like several other inhibitors of HMG-CoA reductase, is a substrate of cytochrome P450 3A4 (CYP3A4).
Certain drugs which inhibit this metabolic pathway can raise the plasma levels of lovastatin and may increase the risk of myopathy. These include itraconazole, ketoconazole, and posaconazole, voriconazole, the macrolide antibiotics erythromycin and clarithromycin, the ketolide antibiotic telithromycin, HIV protease inhibitors, boceprevir, telaprevir, the antidepressant nefazodone, or cobicistat-containing products. Combination of these drugs with lovastatin is contraindicated.
If short-term treatment with strong CYP3A4 inhibitors is unavoidable, therapy with lovastatin should be suspended during the course of treatment (see CONTRAINDICATIONS ; PRECAUTIONS , Drug Interactions ). Gemfibrozil: The combined use of lovastatin with gemfibrozil should be avoided. Other lipid-lowering drugs (other fibrates or ≥ 1 g/day of niacin): Caution should be used when prescribing other fibrates or lipid-lowering doses (≥1 g/day) of niacin with lovastatin, as these agents can cause myopathy when given alone.
The benefit of further alterations in lipid levels by the combined use of lovastatin with other fibrates or niacin should be carefully weighed against the potential risks of these combinations. Cyclosporine: The use of lovastatin with cyclosporine should be avoided. Danazol, diltiazem, dronedarone or verapamil with higher doses of lovastatin: The dose of lovastatin should not exceed 20 mg daily in patients receiving concomitant medication with danazol, diltiazem, dronedarone, or verapamil.
The benefits of the…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS ____________________________________ 3 Manson, J.M., Freyssinges, C., Ducrocq, M.B., Stephenson, W.P., Postmarketing Surveillance of Lovastatin and Simvastatin Exposure During Pregnancy. Reproductive Toxicology . 10(6):439-446.
1996. Phase III Clinical Studies In Phase III controlled clinical studies involving 613 patients treated with lovastatin, the adverse experience profile was similar to that shown below for the 8,245-patient EXCEL study (see Expanded Clinical Evaluation of Lovastatin [EXCEL] Study ). Persistent increases of serum transaminases have been noted (see WARNINGS , Liver Dysfunction ).
About 11% of patients had elevations of CK levels of at least twice the normal value on one or more occasions. The corresponding values for the control agent cholestyramine was 9 percent. This was attributable to the noncardiac fraction of CK.
Large increases in CK have sometimes been reported (see WARNINGS , Myopathy/Rhabdomyolysis ). Expanded Clinical Evaluation of Lovastatin (EXCEL) Study Lovastatin was compared to placebo in 8,245 patients with hypercholesterolemia (total-C 240-300 mg/dL [6.2-7.8 mmol/L]) in the randomized, double-blind, parallel, 48-week EXCEL study. Clinical adverse experiences reported as possibly, probably or definitely drug-related in ≥1% in any treatment group are shown in the table below.
For no event was the incidence on drug and placebo statistically different. Placebo (N=1663) % Lovastatin 20 mg q.p.m. (N=1642) % Lovastatin 40 mg q.p.m.
(N=1645) % Lovastatin 20 mg b.i.d. (N=1646) % Lovastatin 40 mg b.i.d. (N=1649) % Body As a Whole Asthenia 1.4 1.7 1.4 1.5
1.2Gastrointestinal Abdominal pain 1.6 2.0 2.0 2.2
2.5Constipation 1.9 2.0 3.2 3.2
3.5Diarrhea 2.3 2.6 2.4 2.2
2.6Dyspepsia 1.9 1.3 1.3 1.0
1.6Flatulence 4.2 3.7 4.3 3.9
4.5Nausea 2.5 1.9 2.5 2.2
2.2Musculoskeletal Muscle cramps 0.5 0.6 0.8 1.1
1.0Myalgia 1.7 2.6 1.8 2.2
3.0Nervous System/Psychiatric Dizziness 0.7 0.7 1.2 0.5
0.5Headache 2.7 2.6 2.8 2.1
3.2Skin Rash 0.7 0.8 1.0 1.2
1.3Special Senses Blurred vision 0.8 1.1 0.9 0.9
1.2Other clinical adverse experiences reported as possibly, probably or definitely drug-related in 0.5 to 1.0 percent of patients in any drug-treated group are listed below. In all these cases the incidence on drug and placebo was not statistically different. Body as a Whole: chest pain; Gastrointestinal: acid regurgitation, dry mouth, vomiting; Musculoskeletal: leg pain, shoulder pain, arthralgia; Nervous System/Psychiatric: insomnia, paresthesia; Skin: alopecia, pruritus; Special Senses: eye irritation.
In the EXCEL study (see CLINICAL PHARMACOLOGY , Clinical Studies ), 4.6% of the patients treated up to 48 weeks were discontinued due to clinical or laboratory adverse experiences which were rated by the investigator as possibly, probably or definitely related to therapy with lovastatin. The value for the placebo group was 2.5%. Air Force/Texas Coronary Atherosclerosis Prevention Study (AFCAPS/TexCAPS) In AFCAPS/TexCAPS (see CLINICAL PHARMACOLOGY , Clinical Studies ) involving 6,605 participants treated with 20 to 40 mg/day of lovastatin (n=3,304) or placebo (n=3,301), the safety and tolerability profile of the group treated with lovastatin was comparable to that of the group treated with placebo during a median of 5.1 years of follow-up.
The adverse experiences reported in AFCAPS/TexCAPS were similar to those reported in EXCEL (see ADVERSE REACTIONS , Expanded Clinical Evaluation of Lovastatin (EXCEL) Study ). Concomitant Therapy In controlled clinical studies in which lovastatin was administered concomitantly with cholestyramine, no adverse reactions peculiar to this concomitant treatment were observed. The adverse reactions that occurred were limited to those reported previously with lovastatin or cholestyramine.
Other lipid-lowering agents were not administered concomitantly with lovastatin during controlled clinical studies. Preliminary data suggests that the addition of gemfibrozil to…
🔄 Drug Interactions ▾
Drug Interactions CYP3A4 Interactions Lovastatin is metabolized by CYP3A4 but has no CYP3A4 inhibitory activity; therefore it is not expected to affect the plasma concentrations of other drugs metabolized by CYP3A4. Strong inhibitors of CYP3A4 (e.g., itraconazole, ketoconazole, posaconazole, voriconazole, clarithromycin, telithromycin, HIV protease inhibitors, boceprevir, telaprevir, nefazodone, erythromycin, and cobicistat-containing products), and grapefruit juice increase the risk of myopathy by reducing the elimination of lovastatin.
(See CONTRAINDICATIONS , WARNINGS, Myopathy/Rhabdomyolysis , and CLINICAL PHARMACOLOGY, Pharmacokinetics .)
🤰 Pregnancy ▾
Pregnancy Pregnancy Category X See CONTRAINDICATIONS . Safety in pregnant women has not been established. Lovastatin has been shown to produce skeletal malformations in offspring of pregnant mice and rats dosed during gestation at 80 mg/kg/day (affected mouse fetuses/total: 8/307 compared to 4/289 in the control group; affected rat fetuses/total: 6/324 compared to 2/308 in the control group).
Female rats dosed before mating through gestation at 80 mg/kg/day also had fetuses with skeletal malformations (affected fetuses/total: 1/152 compared to 0/171 in the control group). The 80 mg/kg/day dose in mice is 7 times the human dose based on body surface area and in rats results in 5 times the human exposure based on AUC. In pregnant rats given doses of 2, 20, or 200 mg/kg/day and treated through lactation, the following effects were observed: neonatal mortality (4.1%, 3.5%, and 46%, respectively, compared to 0.6% in the control group), decreased pup body weights throughout lactation (up to 5%, 8%, and 38%, respectively, below control), supernumerary ribs in dead pups (affected fetuses/total: 0/7, 1/17, and11/79, respectively, compared to 0/5 in the control group), delays in ossification in dead pups (affected fetuses/total: 0/7, 0/17, and 1/79, respectively, compared to 0/5 in the control group) and delays in pup development (delays in the appearance of an auditory startle response at 200 mg/kg/day and free-fall righting reflexes at 20 and 200 mg/kg/day).
Direct dosing of neonatal rats by subcutaneous injection with 10 mg/kg/day of the open hydroxyacid form of lovastatin resulted in delayed passive avoidance learning in female rats (mean of 8.3 trials to criterion, compared to 7.3 and 6.4 in untreated and vehicle-treated controls; no effects on retention 1 week later) at exposures 4 times the human systemic exposure at 80 mg/day based on AUC. No effect was seen in male rats. No evidence of malformations was observed when pregnant rabbits were given 5 mg/kg/day (doses equivalent to a human dose of 80 mg/day based on body surface area) or a maternally toxic dose of 15 mg/kg/day (3 times the human dose of 80 mg/day based on body surface area).
Rare clinical reports of congenital anomalies following intrauterine exposure to HMG-CoA reductase inhibitors have been received. However, in an analysis† of greater than 200 prospectively followed pregnancies exposed during the first trimester to lovastatin or another closely related HMG-CoA reductase inhibitor, the incidence of congenital anomalies was comparable to that seen in the general population. This number of pregnancies was sufficient to exclude a 3-fold or greater increase in congenital anomalies over the background incidence.
Maternal treatment with lovastatin may reduce the fetal levels of mevalonate, which is a precursor of cholesterol biosynthesis. Atherosclerosis is a chronic process, and ordinarily discontinuation of lipid-lowering drugs during pregnancy should have little impact on the long-term risk associated with primary hypercholesterolemia. For these reasons, lovastatin should not be used in women who are pregnant, or can become pregnant (see CONTRAINDICATIONS ).
Lovastatin should be administered to women of childbearing potential only when such patients are highly unlikely to conceive and have been informed of the potential hazards. Treatment should be immediately discontinued as soon as pregnancy is recognized.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in patients 10 to 17 years of age with heFH have been evaluated in controlled clinical trials of 48 weeks duration in adolescent boys and controlled clinical trials of 24 weeks duration in girls who were at least 1 year post-menarche. Patients treated with lovastatin had an adverse experience profile generally similar to that of patients treated with placebo. Doses greater than 40 mg have not been studied in this population.
In these limited controlled studies, there was no detectable effect on growth or sexual maturation in the adolescent boys or on menstrual cycle length in girls. See CLINICAL PHARMACOLOGY , Clinical Studies in Adolescent Patients ; ADVERSE REACTIONS , Adolescent Patients ; and DOSAGE AND ADMINISTRATION , Adolescent Patients (10 to 17 years of age) with Heterozygous Familial Hypercholesterolemia . Adolescent females should be counseled on appropriate contraceptive methods while on lovastatin therapy (see CONTRAINDICATIONS and PRECAUTIONS , Pregnancy ).
Lovastatin has not been studied in pre-pubertal patients or patients younger than 10 years of age.
🧓 Geriatric Use ▾
Geriatric Use A pharmacokinetic study with lovastatin showed the mean plasma level of HMG-CoA reductase inhibitory activity to be approximately 45% higher in elderly patients between 70 to 78 years of age compared with patients between 18 to 30 years of age; however, clinical study experience in the elderly indicates that dosage adjustment based on this age-related pharmacokinetic difference is not needed. In the two large clinical studies conducted with lovastatin (EXCEL and AFCAPS/TexCAPS), 21% (3094/14850) of patients were ≥65 years of age.
Lipid-lowering efficacy with lovastatin was at least as great in elderly patients compared with younger patients, and there were no overall differences in safety over the 20 to 80 mg/day dosage range (see CLINICAL PHARMACOLOGY ). Because advanced age (≥65 years) is a predisposing factor for myopathy, including rhabdomyolysis, Lovastatin should be prescribed with caution in the elderly.
🆘 Overdosage ▾
OVERDOSAGE After oral administration of lovastatin to mice, the median lethal dose observed was >15 g/m 2 . Five healthy human volunteers have received up to 200 mg of lovastatin as a single dose without clinically significant adverse experiences. A few cases of accidental overdosage have been reported; no patients had any specific symptoms, and all patients recovered without sequelae.
The maximum dose taken was 5 to 6 g. Until further experience is obtained, no specific treatment of overdosage with lovastatin can be recommended. The dialyzability of lovastatin and its metabolites in man is not known at present.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The involvement of low-density lipoprotein cholesterol (LDL-C) in atherogenesis has been well-documented in clinical and pathological studies, as well as in many animal experiments. Epidemiological and clinical studies have established that high LDL-C and low high-density lipoprotein cholesterol (HDL-C) are both associated with coronary heart disease. However, the risk of developing coronary heart disease is continuous and graded over the range of cholesterol levels and many coronary events do occur in patients with total cholesterol (total-C) and LDL-C in the lower end of this range.
Lovastatin has been shown to reduce both normal and elevated LDL-C concentrations. LDL is formed from very low-density lipoprotein (VLDL) and is catabolized predominantly by the high affinity LDL receptor. The mechanism of the LDL-lowering effect of lovastatin may involve both reduction of VLDL-C concentration, and induction of the LDL receptor, leading to reduced production and/or increased catabolism of LDL-C.
Apolipoprotein B also falls during treatment with lovastatin. Lovastatin is a specific inhibitor of HMG-CoA reductase, the enzyme which catalyzes the conversion of HMG-CoA to mevalonate. The conversion of HMG-CoA to mevalonate is an early step in the biosynthetic pathway for cholesterol.
Pharmacokinetics Lovastatin is a lactone, which is readily hydrolyzed in vivo to the corresponding β-hydroxyacid, a strong. inhibitor of HMG-CoA reductase. Inhibition of HMG-CoA reductase is the basis for an assay in pharmacokinetic studies of the β-hydroxyacid metabolites (active inhibitors) and, following base hydrolysis, active plus latent inhibitors (total inhibitors) in plasma following administration of lovastatin. Following an oral dose of 14 C-labeled lovastatin in man, 10% of the dose was excreted in urine and 83% in feces.
The latter represents absorbed drug equivalents excreted in bile, as well as any unabsorbed drug. Plasma concentrations of total radioactivity (lovastatin plus 14 C-metabolites) peaked at 2 hours and declined rapidly to about 10% of peak by 24 hours postdose. Absorption of lovastatin, estimated relative to an intravenous reference dose, in each of four animal species tested, averaged about 30% of an oral dose.
In animal studies, after oral dosing, lovastatin had high selectivity for the liver, where it achieved substantially higher concentrations than in non-target tissues. Lovastatin undergoes extensive first-pass extraction in the liver, its primary site of action, with subsequent excretion of drug equivalents in the bile. As a consequence of extensive hepatic extraction of lovastatin, the availability of drug to the general circulation is low and variable.
In a single dose study in four hypercholesterolemic patients, it was estimated that less than 5% of an oral dose of lovastatin reaches the general circulation as active inhibitors. Following administration of lovastatin tablets the coefficient of variation, based on between-subject variability, was approximately 40% for the area under the curve (AUC) of total inhibitory activity in the general circulation. Both lovastatin and its β-hydroxyacid metabolite are highly bound (>95%) to human plasma proteins.
Animal studies demonstrated that lovastatin crosses the blood-brain and placental barriers. The major active metabolites present in human plasma are the β-hydroxyacid of lovastatin, its 6'-hydroxy derivative, and two additional metabolites. Peak plasma concentrations of both active and total inhibitors were attained within 2 to 4 hours of dose administration.
While the recommended therapeutic dose range is 10 to 80 mg/day, linearity of inhibitory activity in the general circulation was established by a single dose study employing lovastatin tablet dosages from 60 to as high as 120 mg. With a once-a-day dosing regimen, plasma concentrations of total inhibitors over a dosing interval achieved a steady state between the second and third days of therapy a…
📦 How Supplied / Storage and Handling ▾
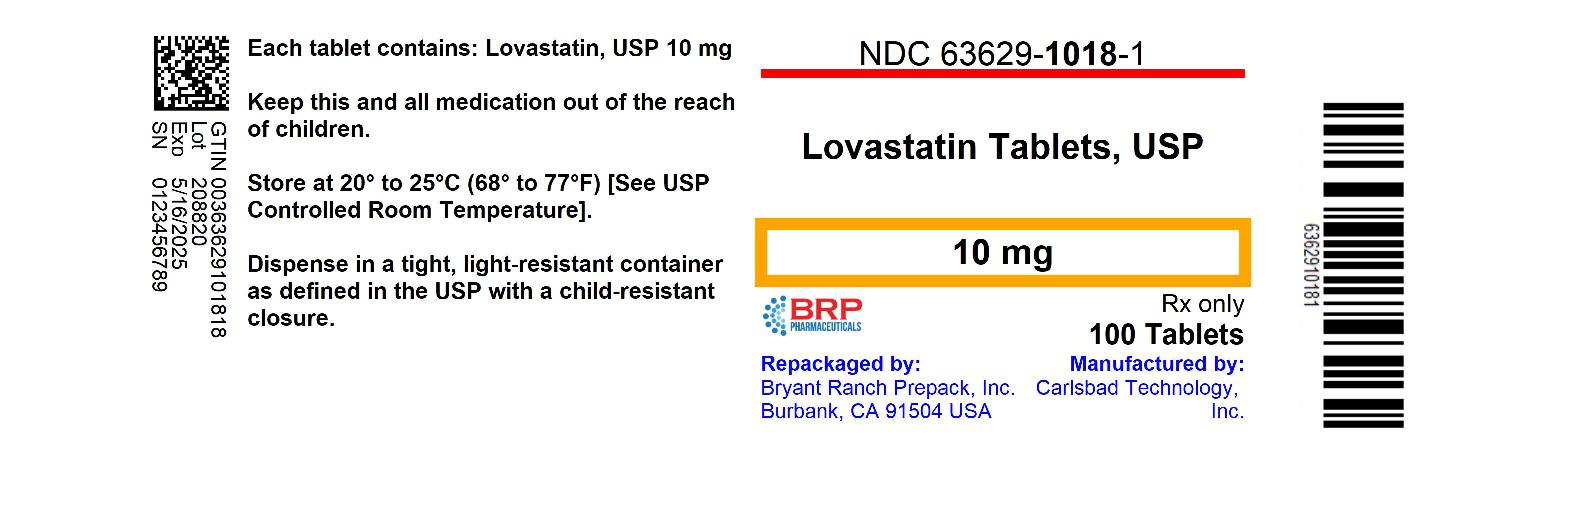
HOW SUPPLIED Lovastatin Tablets USP (white to off white round, unscored tablets) containing 10mg of lovastatin and engraved with “CTI 141". NDC: 63629-1018-1: 100 Tablets in a BOTTLE NDC: 63629-1018-2: 30 Tablets in a BOTTLE NDC: 63629-1018-3: 300 Tablets in a BOTTLE NDC: 63629-1018-4: 120 Tablets in a BOTTLE NDC: 63629-1018-5: 500 Tablets in a BOTTLE NDC: 63629-1018-6: 60 Tablets in a BOTTLE NDC: 63629-1018-8: 800 Tablets in a BOTTLE NDC: 63629-1018-9: 90 Tablets in a BOTTLE NDC: 63629-1018-0: 1000 Tablets in a BOTTLE Storage Store at 20º to 25º C (68º to 77º F). [See USP Controlled Room Temperature.] Lovastatin Tablets must be protected from light and stored in a well-closed, light-resistant and child proof container.
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
DESCRIPTION Lovastatin is a cholesterol lowering agent isolated from a strain of Aspergillus terreus. After oral ingestion, lovastatin, which is an inactive lactone, is hydrolyzed to the corresponding β-hydroxyacid form. This is a principal metabolite and an inhibitor of 3-hydroxy-3-methylglutaryl-coenzyme A (HMG-CoA) reductase.
This enzyme catalyzes the conversion of HMG-CoA to mevalonate, which is an early and rate limiting step in the biosynthesis of cholesterol. Lovastatin is [1 S -[1α( R *), 3α, 7β, 8β(2 S *,4 S *),8aβ]]-1,2,3, 7,8,8a-hexahydro-3,7-dimethyl-8-[2-(tetrahydro-4-hydroxy-6-oxo-2 H -pyran-2-yl)ethyl]-1-naphthalenyl 2-methylbutanoate. The empirical formula of lovastatin is C 24 H 36 O 5 and its molecular weight is 404.55.
Its structural formula is: Lovastatin is a white, nonhygroscopic crystalline powder that is insoluble in water and sparingly soluble in ethanol, methanol, and acetonitrile. Lovastatin tablets are supplied as 10 mg, 20 mg and 40 mg tablets for oral administration. In addition to the active ingredient lovastatin, each tablet contains the following inactive ingredients: lactose monohydrate, magnesium stearate, microcrystalline cellulose, poloxamer, pregelatinized starch, sodium starch glycolate, butylated hydroxyanisole and talc.
Butylated hydroxyanisole (BHA) is added as a preservative.
💬 Information for Patients ▾
Information for Patients Patients should be advised about substances they should not take concomitantly with lovastatin and be advised to report promptly unexplained muscle pain, tenderness, or weakness particularly if accompanied by malaise or fever or if muscle signs and symptoms persist after discountinuing Lovastatin (see list below and WARNINGS , Myopathy/Rhabdomyolysis ) . Patients should also be advised to inform other physicians prescribing a new medication that they are taking lovastatin. It is recommended that liver enzymes be checked before starting therapy, and if signs or symptoms of liver injury occur.
All patients treated with Lovastatin should be advised to report promptly any symptoms that may indicate liver injury, including fatigue, anorexia, right upper abdominal discomfort, dark urine or jaundice.