
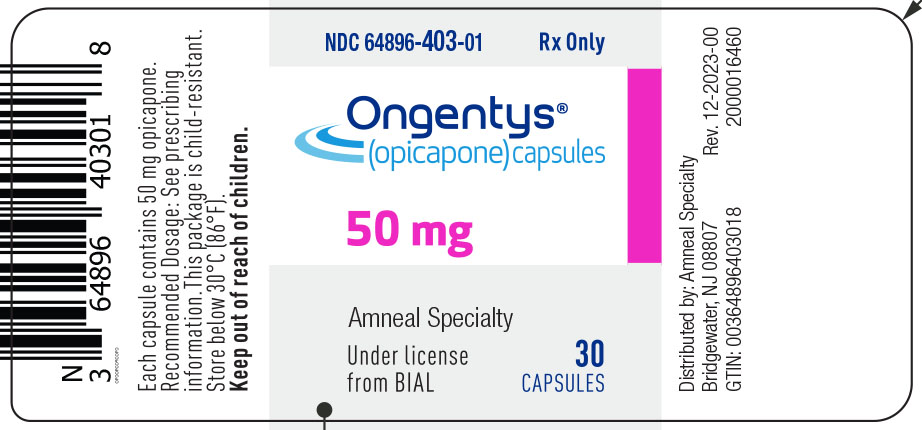
ONGENTYS opicapone 50 mg Capsule, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Catechol-O-Methyltransferase Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Opicapone is used along with levodopa and carbidopa (Sinemet, Rytary) to treat the end-of-dose 'wearing-off' symptoms of Parkinson's disease. Opicapone is an inhibitor of catechol-O-methyltransferase (COMT). Opicapone helps the levodopa and carbidopa work better by allowing more of it to reach the brain, where it has its effects.
Read the full MedlinePlus article ↗- Great question. Levodopa is still the main treatment, but for many people with Parkinson's it starts to wear off between doses — that's what's called an 'off' episode. Ongentys blo...
- What exactly does Ongentys do — why is my doctor adding it to my levodopa?
- Ongentys is taken once at bedtime, and food really does interfere with how well your body absorbs it — a meal can reduce absorption quite significantly. To get the full benefit, yo...
- Why do I have to take it at bedtime and avoid eating around that time?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Opicapone — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII PN2ZH5LOQY
A synthetic red dye approved by the FDA for use in foods, medicines, and cosmetics. It serves as a colorant to make tablets, capsules, and liquids visually distinctive for product identification.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII J2B2A4N98G
Lactose is a natural sugar derived from milk. In medications, it serves as a filler and binder to add bulk and help hold tablet or capsule ingredients together during manufacturing.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
8 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $24.760 | $742.81 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | $24.03 | $721.01 / 30 capsules |
| Medicare drug plans payPart D · Q2 2026 | $23.41 | $702.42 / 30 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ongentys 50 mgthis 64896-0403-01 | Amneal | 30 capsules | $24.760 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9745290 ↗ | Method of use | U-3869 | Oct 10, 2027 |
| US 9745290 ↗ | Method of use | U-3869 | Oct 10, 2027 |
| US 9630955 ↗ | Drug substance | U-3869 | Dec 12, 2032 |
| US 9630955 ↗ | Drug substance | U-3869 | Dec 12, 2032 |
| US 9550759 ↗ | Method of use | U-3870 | Jul 26, 2026 |
| US 9550759 ↗ | Method of use | U-3870 | Jul 26, 2026 |
| US 9550759 ↗ | Method of use | U-3871 | Jul 26, 2026 |
| US 9550759 ↗ | Method of use | U-3872 | Jul 26, 2026 |
| US 9550759 ↗ | Method of use | U-3871 | Jul 26, 2026 |
| US 9550759 ↗ | Method of use | U-3872 | Jul 26, 2026 |
| US 8524746 ↗ | Method of use | U-3869 | Jul 14, 2029 |
| US 8524746 ↗ | Method of use | U-3869 | Jul 14, 2029 |
| US 8168793 ↗ | Drug substance | U-3869 | Oct 10, 2027 |
| US 8168793 ↗ | Drug substance | U-3869 | Oct 10, 2027 |
| US 10583130 ↗ | Method of use | U-3869 | Mar 31, 2030 |
| US 10583130 ↗ | Method of use | U-3869 | Mar 31, 2030 |
| US 12129247 ↗ | Method of use | U-4038 | Jan 11, 2032 |
| US 12129247 ↗ | Method of use | U-4038 | Jan 11, 2032 |
| US 8907099 ↗ | Drug substance | — | May 12, 2027 |
| US 10071085 ↗ | Drug product | — | Mar 31, 2030 |
| US 10071085 ↗ | Drug product | — | Mar 31, 2030 |
| US 8907099 ↗ | Drug substance | — | May 12, 2027 |
Is there a generic version of ONGENTYS 50 MG CAPSULE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 64896-0403-01 You're viewing this | 30 CAPSULE in 1 BOTTLE (64896-403-01) | $24.76 / ea | $742.81 | 2024-04-05 | Active |
| 64896-0403-02 | 7 CAPSULE in 1 BOTTLE (64896-403-02) | — | — | 2024-04-05 | Active |
| 64896-0403-03 | 30 CAPSULE in 1 BOTTLE (64896-403-03) | — | — | 2024-04-05 | Active |
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in NDC 64896-0403-01?
What is the difference between NDC 64896-0403-01 and NDC 64896-0403-02?
What NDC number is used to bill for this package of ONGENTYS opicapone 50 mg Capsule?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ONGENTYS is indicated as adjunctive treatment to levodopa/carbidopa in patients with Parkinson’s disease (PD) experiencing “off” episodes. ONGENTYS is a catechol-O-methyltransferase (COMT) inhibitor indicated as adjunctive treatment to levodopa/carbidopa in patients with Parkinson’s disease (PD) experiencing “off” episodes. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION The recommended dosage is 50 mg administered orally once daily at bedtime. ( 2.1 ) Patients should not eat food for 1 hour before and for at least 1 hour after intake of ONGENTYS. ( 2.1 ) The recommended dosage in patients with moderate hepatic impairment is 25 mg orally once daily at bedtime; avoid use in patients with severe hepatic impairment. ( 2.2 )
2.1Dosing and Administration Information The recommended dosage of ONGENTYS is 50 mg administered orally once daily at bedtime. Patients should not eat food for 1 hour before and for at least 1 hour after intake of ONGENTYS [see Clinical Pharmacology ( 12.3 )].
2.2Dosage Recommendations for Patients with Hepatic Impairment In patients with moderate hepatic impairment (Child-Pugh B), the recommended dose of ONGENTYS is 25 mg orally once daily at bedtime [see Use in Specific Populations ( 8.7 ), Clinical Pharmacology ( 12.3 )]. Avoid use of ONGENTYS in patients with severe (Child-Pugh C) hepatic impairment [ see Use in Specific Populations ( 8.7 ) , Clinical Pharmacology ( 12.3 ) ].
2.3D iscontinuation and Missed Dose When discontinuing ONGENTYS, monitor patients and consider adjustment of other dopaminergic therapies as needed. If a dose of ONGENTYS is missed, the next dose should be taken at the scheduled time the next day.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS ONGENTYS capsules are available in the following strengths: 50 mg capsules with a dark blue opaque cap and dark pink opaque body; axially printed with “OPC” over “50” in white ink, on both the cap and body. 25 mg capsules with a light blue opaque cap and light pink opaque body; axially printed with “OPC” over “25” in blue ink, on both the cap and body. Capsules: 25 mg and 50 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ONGENTYS is contraindicated in patients with: Concomitant use of non-selective monoamine oxidase (MAO) inhibitors [ see Drug Interactions ( 7.1 ) ] . Pheochromocytoma, paraganglioma, or other catecholamine secreting neoplasms. Concomitant use of non-selective monoamine oxidase (MAO) inhibitors. ( 4 ) History of pheochromocytoma, paraganglioma, or other catecholamine secreting neoplasms. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Cardiovascular Effects with Concomitant Use of Drugs Metabolized by Catechol-O-Methyltransferase (COMT): May cause arrhythmias, increased heart rate, and excessive changes in blood pressure. Monitor patients when treated concomitantly with products metabolized by COMT. ( 4 , 5.1 ) Falling Asleep During Activities of Daily Living: Advise patients prior to treatment.
( 5.2 ) Hypotension/Syncope: If occurs, consider discontinuing ONGENTYS or adjusting dosage of other medications that can lower blood pressure. ( 5.3 ) Dyskinesia: May cause or exacerbate dyskinesia; consider levodopa or dopaminergic medication dose reduction. ( 5.4 ) Hallucinations and Psychosis: Consider stopping ONGENTYS if occurs.
( 5.5 ) Impulse Control/Compulsive Disorders: Consider stopping ONGENTYS if occurs. ( 5.6 ) Withdrawal-Emergent Hyperpyrexia and Confusion: When discontinuing ONGENTYS, monitor patients and consider adjustment of other dopaminergic therapies as needed. ( 5.7 )
5.1Cardiovascular Effects with Concomitant Use of Drugs Metabol ized by Catechol-O-Methyltransferase (COMT) Possible arrhythmias, increased heart rate, and excessive changes in blood pressure may occur with concomitant use of ONGENTYS and drugs metabolized by COMT (e.g., isoproterenol, epinephrine, norepinephrine, dopamine, and dobutamine), regardless of the route of administration (including inhalation). Monitor patients treated concomitantly with ONGENTYS and drugs metabolized by COMT [see Contraindications ( 4 ), Drug Interactions ( 7.1 , 7.2 )] .
5.2Falling Asleep During Activities of Daily Living and Somnolence Patients treated with dopaminergic medications and medications that increase levodopa exposure, including ONGENTYS, have reported falling asleep while engaged in activities of daily living, including the operation of motor vehicles, which sometimes has resulted in accidents. Patients may not perceive warning signs, such as excessive drowsiness, or they may report feeling alert immediately prior to the event. Before initiating treatment with ONGENTYS, advise patients of the potential to develop drowsiness and specifically ask about factors that may increase the risk for somnolence with dopaminergic therapy, such as concomitant sedating medications or the presence of a sleep disorder.
If a patient develops daytime sleepiness or episodes of falling asleep during activities that require full attention (e.g., driving a motor vehicle, conversations, eating), consider discontinuing ONGENTYS or adjusting other dopaminergic or sedating medications. If a decision is made to continue ONGENTYS, patients should be advised not to drive and to avoid other potentially dangerous activities.
5.3Hypotension/Syncope In Study 1 and Study 2 [see Clinical Studies ( 14 )] , hypotension (orthostatic and non-orthostatic), syncope, and presyncope occurred in 5% of patients treated with ONGENTYS 50 mg compared to 1% of patients who received placebo. Monitor patients for hypotension (orthostatic and non-orthostatic) and advise patients about the risk for syncope and presyncope. If these adverse reactions occur, consider discontinuing ONGENTYS or adjusting the dosage of other medications that can lower blood pressure.
5.4Dyskinesia ONGENTYS potentiates the effects of levodopa [see Clinical Pharmacology ( 12.3 )] and may cause dyskinesia or exacerbate pre-existing dyskinesia. In controlled clinical trials (Study 1 and Study 2) [see Clinical Studies ( 14 )], dyskinesia occurred in 20% of patients treated with ONGENTYS 50 mg compared to 6% of patients who received placebo. Dyskinesia was also the most common adverse reaction leading to discontinuation of ONGENTYS [see Adverse Reactions ( 6.1 )].
Reducing the patient’s daily levodopa dosage or the dosage of another dopaminergic drug may mitigate dyskinesia that occurs during treatment with ONGENTYS.
5.5Hallucinations and Psychosis In Study 1 and Study 2, hallucinations (hallucinations, auditory hallucinations, visual ha…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are discussed in more detail in other sections of the labeling: Cardiovascular Effects with Concomitant Use of Drugs Metabolized by Catechol-O-Methyltransferase (COMT) [see Warnings and Precautions ( 5.1 )] Falling Asleep During Activities of Daily Living and Somnolence [see Warnings and Precautions ( 5.2 )] Hypotension/Syncope [see Warnings and Precautions ( 5.3 )] Dyskinesia [see Warnings and Precautions ( 5.4 )] Hallucinations and Psychosis [see Warnings and Precautions ( 5.5 )] Impulse Control/Compulsive Disorders [see Warnings and Precautions ( 5.6 )] Withdrawal-Emergent Hyperpyrexia and Confusion [see Warnings and Precautions ( 5.7 )] Most common adverse reactions (≥4% and > placebo): dyskinesia, constipation, blood creatine kinase increased, hypotension/syncope, and weight decreased.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Amneal Pharmaceuticals at 1-877-835-5472 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The safety of ONGENTYS was evaluated in 265 patients with Parkinson’s disease (PD) in two 14-15 week placebo- and active-controlled (Study 1) or placebo-controlled (Study 2) studies [see Clinical Studies ( 14 )] . All patients were taking a stable dose of levodopa and a DOPA decarboxylase inhibitor, alone or in combination with other PD medications.
In Study 1 and Study 2, the mean age of patients was 63.6 years, 59% of patients were male, and 89% of patients were Caucasian. At baseline, the mean duration of PD was 7.6 years. Adverse Reactions Leading to Discontinuation of Treatment In Study 1 and Study 2, a total of 8% of ONGENTYS 50 mg-treated patients and 6% of patients who received placebo discontinued due to adverse events.
The most common adverse reaction leading to discontinuation was dyskinesia, reported in 3% of ONGENTYS 50 mg-treated patients and 0.4% of patients who received placebo. Common Adverse Reactions Adverse reactions that occurred in the pooled studies at an incidence of at least 2% and greater than placebo are presented in Table 1. The most common adverse reactions (incidence at least 4% and greater than placebo) were dyskinesia, constipation, blood creatine kinase increased, hypotension/syncope, and weight decreased.
Table 1 : Adverse Reactions with an Incidence of at Least 2 % in Patients Treated with ONGENTYS and Greater than on Placebo, in Pooled Study 1 and Study 2 Adverse Reactions ONGENTYS 50 mg N=265 % Placebo N=257 % Nervous system disorders Dyskinesia Dizziness 20 3 6 1 Gastrointestinal disorders Constipation Dry mouth 6 3 2 1 Psychiatric disorders Hallucination 1 Insomnia 3 3 1 2 Investigations Blood creatine kinase increased Weight decreased 5 4 2 0 Vascular disorders Hypotension/syncope 2 Hypertension 5 3 1 2 1 Includes hallucinations, hallucinations visual, hallucinations auditory, and hallucinations mixed 2 Includes hypotension, orthostatic hypotension, syncope, and presyncope
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of ONGENTYS. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish causal relationship to drug exposure. Injury, poisoning and procedural complications: Fall Psychiatric disorder : Confusional state
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS
7.1Non-Selective Monoamine Oxidase (MAO) Inhibitors Both ONGENTYS and non-selective MAO inhibitors (e.g., phenelzine, isocarboxazid, and tranylcypromine) inhibit catecholamine metabolism, leading to increased levels of catecholamines. Concomitant use may increase the risk of possible arrhythmias, increased heart rate, and excessive changes in blood pressure. Concomitant use of ONGENTYS with non-selective MAO inhibitors is contraindicated [see Contraindications ( 4 )] .
Selective MAO-B inhibitors can be used concomitantly with ONGENTYS.
7.2Effect of ONGENTYS on Other Drugs Drugs Metabolized by Catechol-O-Methyltransferase (COMT) Concomitant use of ONGENTYS with drugs metabolized by COMT may affect the pharmacokinetics of those drugs, which may increase the risk of possible arrhythmias, increased heart rate, and excessive changes in blood pressure [see Warnings and Precautions ( 5.1 )] . Drugs known to be metabolized by COMT should be administered with caution. Monitor for changes in heart rate, rhythm, and blood pressure in patients concomitantly treated with ONGENTYS and drugs metabolized by COMT [see Warnings and Precautions ( 5.1 )] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm ( 8.1 ) Avoid use in patients with end-stage renal disease. ( 8.6 )
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with use of ONGENTYS in pregnant women. In animal studies, oral administration of opicapone during pregnancy resulted in adverse effects on embryofetal development (increased incidence of fetal abnormalities) at clinically relevant plasma exposures in one of two species tested. In addition, opicapone is always given concomitantly with levodopa/carbidopa, which is known to cause developmental toxicity in rabbits ( s ee Data ).
The background risk of major birth defects and miscarriage in the U.S. general population is 2-4% and 15-20% of clinically recognized pregnancies, respectively. The background risk for major birth defects and miscarriage in patients with Parkinson’s disease is unknown. Data Animal Data Oral administration of opicapone (0, 150, 375, or 1000 mg/kg/day) to pregnant rats throughout gestation resulted in no adverse effects on embryofetal development.
Plasma exposure (AUC) at the highest dose tested (1000 mg/kg/day) was approximately 40 times that in humans at the recommended human dose (50 mg/day). In pregnant rabbits, oral administration of opicapone (0, 100, 175, or 225 mg/kg/day) during the period of organogenesis resulted in increased incidence of structural abnormalities at all doses tested; maternal toxicity was observed at all but the lowest dose tested. A no-effect dose for adverse effects on embryofetal development was not identified.
Plasma exposure (AUC) at the low-effect dose (100 mg/kg/day) was less than that in humans at the RHD. Oral administration of opicapone (0, 150, 375, or 1000 mg/kg/day) throughout gestation and lactation resulted in no adverse effects on pre- and postnatal development; however, effects on neurobehavioral development in the offspring were not rigorously assessed. Plasma exposure (AUC) at the highest dose tested (1000 mg/kg/day) was approximately 40 times that in humans at the RHD.
Opicapone is always given concomitantly with levodopa/carbidopa, which is known to cause visceral and skeletal malformations in rabbits. The developmental toxicity of opicapone in combination with levodopa/carbidopa was not assessed in animals.
8.2Lactation Risk Summary There are no data on the presence of opicapone in human milk, the effects on the breastfed infant, or the effects on milk production. In lactating rats, oral administration of opicapone resulted in levels of opicapone or metabolites in milk similar to those in maternal plasma . The developmental and health benefits of breastfeeding should be considered along with the mother’s clinical need for ONGENTYS and any potential adverse effects on the breastfed infant from ONGENTYS or from the underlying maternal condition.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
8.5Geriatric Use No dose adjustment is required for elderly patients. Of the total number of patients who received ONGENTYS 50 mg in Study 1 and Study 2, 52% of patients were 65 years and older. No overall differences in safety and effectiveness were observed between these patients and younger patients, but greater sensitivity to adverse reactions of some older individuals cannot be ruled out.
8.6Renal Impairment The renal route of elimination plays a minor role in the clearance of opicapone [see Clinical Pharmacology ( 12.3 )]. Avoid use of ONGENTYS in patients with end-stage renal disease (ESRD) (CLcr <15 mL/min). No dosage adjustment is required for patients with mild, moderate, or severe renal impairment.
However, because of a potential for increased exposure, monitor patients with severe renal impairment for adverse reactions and discontinue ONGENTYS if tolerability issues arise. 8. 7 Hepatic Impairment Opicapone exposure is increased in patients with hepatic impairment [see Clinical…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no adequate data on the developmental risk associated with use of ONGENTYS in pregnant women. In animal studies, oral administration of opicapone during pregnancy resulted in adverse effects on embryofetal development (increased incidence of fetal abnormalities) at clinically relevant plasma exposures in one of two species tested. In addition, opicapone is always given concomitantly with levodopa/carbidopa, which is known to cause developmental toxicity in rabbits ( s ee Data ).
The background risk of major birth defects and miscarriage in the U.S. general population is 2-4% and 15-20% of clinically recognized pregnancies, respectively. The background risk for major birth defects and miscarriage in patients with Parkinson’s disease is unknown. Data Animal Data Oral administration of opicapone (0, 150, 375, or 1000 mg/kg/day) to pregnant rats throughout gestation resulted in no adverse effects on embryofetal development.
Plasma exposure (AUC) at the highest dose tested (1000 mg/kg/day) was approximately 40 times that in humans at the recommended human dose (50 mg/day). In pregnant rabbits, oral administration of opicapone (0, 100, 175, or 225 mg/kg/day) during the period of organogenesis resulted in increased incidence of structural abnormalities at all doses tested; maternal toxicity was observed at all but the lowest dose tested. A no-effect dose for adverse effects on embryofetal development was not identified.
Plasma exposure (AUC) at the low-effect dose (100 mg/kg/day) was less than that in humans at the RHD. Oral administration of opicapone (0, 150, 375, or 1000 mg/kg/day) throughout gestation and lactation resulted in no adverse effects on pre- and postnatal development; however, effects on neurobehavioral development in the offspring were not rigorously assessed. Plasma exposure (AUC) at the highest dose tested (1000 mg/kg/day) was approximately 40 times that in humans at the RHD.
Opicapone is always given concomitantly with levodopa/carbidopa, which is known to cause visceral and skeletal malformations in rabbits. The developmental toxicity of opicapone in combination with levodopa/carbidopa was not assessed in animals.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use No dose adjustment is required for elderly patients. Of the total number of patients who received ONGENTYS 50 mg in Study 1 and Study 2, 52% of patients were 65 years and older. No overall differences in safety and effectiveness were observed between these patients and younger patients, but greater sensitivity to adverse reactions of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE No specific antidotes for ONGENTYS are known. As a general measure, removal of ONGENTYS by gastric lavage and/or inactivation by administering activated charcoal should be considered. In managing overdose, provide supportive care, including close medical supervision and monitoring, and consider the possibility of multiple drug involvement. If an over-exposure occurs, call your poison control center at 1-800-222-1222 or www.poison.org.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Opicapone is a selective and reversible inhibitor of catechol-O-methyltransferase (COMT). COMT catalyzes the transfer of the methyl group of S-adenosyl-L-methionine to the phenolic group of substrates that contain a catechol structure. Physiological substrates of COMT include DOPA, catecholamines (dopamine, norepinephrine, and epinephrine), and their hydroxylated metabolites.
When decarboxylation of levodopa is prevented by carbidopa, COMT becomes the major metabolizing enzyme for levodopa, catalyzing its metabolism to 3-methoxy-4-hydroxy-L-phenylalanine (3-OMD).
12.2Pharmacodynamics COMT Activity Once-daily administration of ONGENTYS 50 mg caused inhibition of COMT activity in erythrocytes; the maximal inhibition seen was 84% and was maintained >65% over a 24-hour dosing interval in patients with Parkinson’s disease. Following termination of treatment, COMT inhibition slowly returns to baseline levels, with >35% inhibition still observed 5 days after the last dose. Effects on Levodopa Peak (C max ) and overall levodopa exposure (AUC) increased by 43-44% and 62-94%, respectively, in PD patients following once-daily administration of ONGENTYS at bedtime with levodopa/carbidopa administered every three or every four hours, as compared to after administration of levodopa/carbidopa alone.
C ardiac Electrophysiology At a dose 16 times the recommended dosage, ONGENTYS does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Opicapone demonstrates dose-proportional pharmacokinetics over a 25 mg (0.5 times the recommended dosage) to 50 mg dose range. The pharmacokinetics of opicapone are similar in both PD patients and healthy subjects. Absorption After single-dose administration of ONGENTYS 50 mg, the median (range) plasma T max value was 2.0 (1.0-4.0) hours.
Effect of Food Following a moderate fat/moderate calorie meal, the mean peak plasma concentration (C max ) for opicapone decreased 62%, the mean overall plasma exposure (AUC) decreased 31%, and the T max was delayed by 4 hours. In Study 1, ONGENTYS was administered without regard to food. In Study 2, ONGENTYS administration and food consumption were separated by 1 hour [see Dosage and Administration ( 2.1 ), Clinical Studies ( 14 )].
Distribution Opicapone is highly bound to plasma proteins (>99%), which is independent of concentration. Elimination The mean elimination half-life of opicapone is 1 to 2 hours. Metabolism Sulphation is the primary metabolic pathway of opicapone, based on clinical studies and in vitro assessments.
Other metabolic pathways include glucuronidation, methylation (by COMT), reduction, and glutathione conjugation. Excretion After administration of a single dose of radiolabeled opicapone 100 mg (2 times the recommended dosage) to healthy subjects, approximately 70% of the dose was recovered in feces (22% as unchanged), 20% in expired air, and 5% in urine (<1% as unchanged). Specific Populations No clinically significant differences in the pharmacokinetics of opicapone were observed based on age (i.e., 18 to 40 years of age and ≥ 65 years of age), sex, or race/ethnicity (i.e., Japanese, Caucasian, Asian, and Black).
Renal Impairment Based on population pharmacokinetic analyses, no clinically significant differences in the pharmacokinetics of opicapone were observed in patients with mild or moderate renal impairment (CLcr 30-89 mL/min using the Cockcroft-Gault equation) relative to those with normal renal function (CLcr >90 mL/min). Patients with severe renal impairment or ESRD (CLcr <30 mL/min) have not been studied [see Use in Specific Populations ( 8.6 )] . Hepatic Impairment The single-dose pharmacokinetics of opicapone was evaluated in subjects with mild (Child-Pugh: A) and moderate (Child-Pugh: B) hepatic impairment.
In subjects with mild hepatic impairment, the mean overall opicapone plasma exposure (AUC) increased by 35%, which is not expected to be clinically signifi…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Opicapone is a selective and reversible inhibitor of catechol-O-methyltransferase (COMT). COMT catalyzes the transfer of the methyl group of S-adenosyl-L-methionine to the phenolic group of substrates that contain a catechol structure. Physiological substrates of COMT include DOPA, catecholamines (dopamine, norepinephrine, and epinephrine), and their hydroxylated metabolites.
When decarboxylation of levodopa is prevented by carbidopa, COMT becomes the major metabolizing enzyme for levodopa, catalyzing its metabolism to 3-methoxy-4-hydroxy-L-phenylalanine (3-OMD).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied ONGENTYS (opicapone) capsules are available as: • 50 mg hard gelatin capsules, Size 1; dark blue opaque cap and dark pink opaque body; axially printed with “OPC” over “50” in white ink, on both the cap and body - Bottle of 30 with child-resistant closure: NDC 64896-403-01 • 25 mg hard gelatin capsules, Size 1; light blue opaque cap and light pink opaque body; axially printed with “OPC” over “25” in blue ink, on both the cap and body - Bottle of 30 with child-resistant closure: NDC 64896-402-01
16.2Storage and Handling Store at a temperature below 30°C (86°F).
16.1How Supplied ONGENTYS (opicapone) capsules are available as: • 50 mg hard gelatin capsules, Size 1; dark blue opaque cap and dark pink opaque body; axially printed with “OPC” over “50” in white ink, on both the cap and body - Bottle of 30 with child-resistant closure: NDC 64896-403-01 • 25 mg hard gelatin capsules, Size 1; light blue opaque cap and light pink opaque body; axially printed with “OPC” over “25” in blue ink, on both the cap and body - Bottle of 30 with child-resistant closure: NDC 64896-402-01
📦 Storage and Handling ▾
16.2Storage and Handling Store at a temperature below 30°C (86°F).
📋 Description ▾
11 DESCRIPTION ONGENTYS contains opicapone, a peripheral, selective and reversible catechol-O-methyltransferase (COMT) inhibitor. The chemical name of opicapone is 2,5-dichloro-3-(5-(3,4-dihydroxy-5-nitrophenyl)-1,2,4-oxadiazol-3-yl)-4,6-dimethylpyridine-1-oxide with the following structure: The opicapone molecular formula is C15H10Cl2N4O6; and its molecular weight is 413.17. Opicapone is a yellow powder/crystalline solid with limited aqueous solubility.
ONGENTYS capsules are intended for oral administration. Each capsule contains 25 mg or 50 mg of opicapone. ONGENTYS also contains the following inactive ingredients: lactose, magnesium stearate, pregelatinized starch, and sodium starch glycolate.
The capsule shells contain: FD&C Blue#2, FD&C Red#3, gelatin, and titanium dioxide. ONGENTYS contains opicapone, a peripheral, selective and reversible catechol-O-methyltransferase (COMT) inhibitor. The chemical name of opicapone is 2,5-dichloro-3-(5-(3,4-dihydroxy-5-nitrophenyl)-1,2,4-oxadiazol-3-yl)-4,6-dimethylpyridine-1-oxide with the following structure:
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Patient Information ). Administration Instruct patients and/or caregivers that ONGENTYS capsules should be taken at bedtime. Inform patients to not eat food for 1 hour before and for at least 1 hour after intake of ONGENTYS [see Dosage and Administration ( 2.1 )] .
Concomitant Medications Certain medications can cause an interaction with ONGENTYS. Advise patients and/or caregivers to inform their healthcare provider of all the medicines the patient is taking, including over-the-counter medicines, dietary supplements, and herbal products [see Warnings and Precautions ( 5.1 ) and Drug Interactions ( 7 )] . Falling Asleep During Activities of Daily Living Advise patients and/or caregivers that somnolence has been reported with ONGENTYS.
Patients treated with dopaminergic medications have reported falling asleep while engaged in activities of daily living. These adverse reactions may affect some patients’ ability to drive and operate machinery safely [see Warnings and Precautions ( 5.2 )] . Hypotension/Syncope Advise patients that ONGENTYS may cause hypotension or syncope [see Warnings and Precautions ( 5.3 )].
Dyskinesia Advise patients that ONGENTYS may cause dyskinesia or exacerbate pre-existing dyskinesia [see Warnings and Precautions ( 5.4 )]. Hallucinations and Psychosis Advise patients that ONGENTYS may cause hallucinations, delusions, or aggressive behavior and they should report any of these adverse reactions to their healthcare provider [see Warnings and Precautions ( 5.5 )]. Impulse Control /Compulsive Disorders Inform patients of the potential for experiencing intense urges to gamble, increased sexual urges, intense urges to spend money, binge eating, and other intense urges and the inability to control these urges while taking ONGENTYS and one or more medications that increase central dopaminergic tone that are generally used for the treatment of PD.
Advise patients that they should report any of these adverse reactions to their healthcare provider [see Warnings and Precautions ( 5.6 )] . Withdrawal-Emergent Hyperpyrexia and Confusion Advise patients to contact their healthcare provider before stopping ONGENTYS. Tell patients to inform their healthcare provider if they develop symptoms such as fever, confusion, or severe muscle stiffness after stopping ONGENTYS [see Warnings and Precautions ( 5.7 )] .
For further information on ONGENTYS, call 1-877-835-5472 or visit www.ongentys.com Distributed by: Amneal Specialty, a division of Amneal Pharmaceuticals LLC Bridgewater, NJ 08807 Rev. 10-2025-02 Under license from BIAL-Portela & C a , S.A. ONGENTYS is a registered trademark of BIAL-Portela & C a , S.A.