
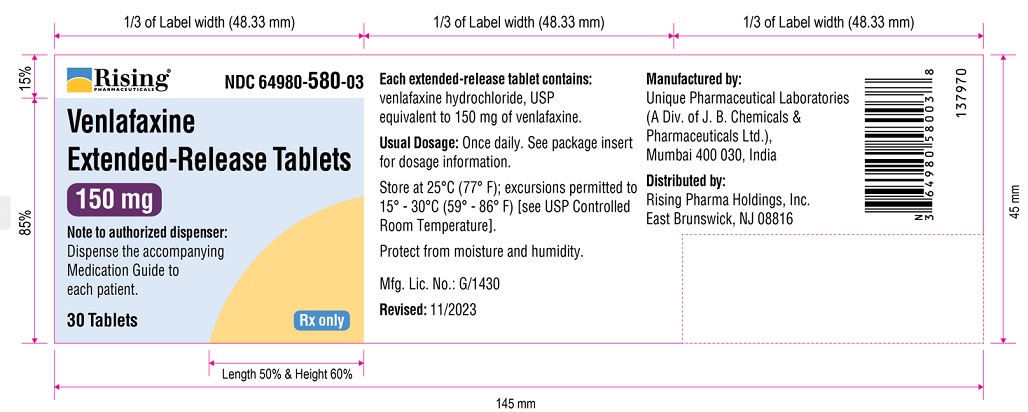
Venlafaxine Hydrochloride 150 mg Tablet, Extended Release, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Serotonin and Norepinephrine Reuptake Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Venlafaxine treats major depressive disorder in all its forms. Depending on which formulation you're prescribed, it can also treat generalized anxiety disorder, social anxiety diso...
- Most people don't feel a full benefit right away — it typically takes several weeks before you notice a meaningful improvement in mood or anxiety. Blood levels stabilize within abo...
- How long does it take for venlafaxine to start working?
- The most common side effects are nausea, dry mouth, sweating, drowsiness or insomnia, dizziness, and decreased appetite — and many of these tend to improve after the first couple o...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Venlafaxine — tap one for details:
Venlafaxine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3J2P07GVB6
Cellulose acetate is a plant-derived polymer made by chemically modifying cellulose fibers. In medications, it serves as a film-coating material for tablets and capsules to protect the drug, control release, and improve appearance.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 0WZ8WG20P6
Hypromellose 2910 is a plant-based cellulose derivative that acts as a thickener, binder, and film-coating agent. It helps control how quickly the medicine dissolves and protects the tablet or capsule from moisture and light.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 4R4HFI6D95
Polyethylene glycol 4000 is a synthetic polymer derived from petroleum. It serves as a binder, filler, and lubricant in solid dosage forms, and helps control how quickly the medicine dissolves.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.233 | $21.00 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.6842 | $61.58 / 90 tablets |
| Medicare drug plans payPart D · Q2 2026 | $2.73 | $245.32 / 90 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Venlafaxine 150 mg 27241-0223-30 | Ajanta | 30 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine Hydrochloride 150 mg 31722-0125-30 | Camber | 30 tablets | $0.233 | AB | Availability likely | — |
| venlafaxine hydrochloride, extended release 150 mg 42799-0962-01 | Edenbridge | 30 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine 150 mg 43598-0943-30 | Dr. | 30 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine Hydrochloride 150 mgthis 64980-0580-09 | Rising | 90 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine 150 mg 67877-0728-30 | Ascend | 30 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine Hydrochloride 150 mg 68001-0498-04 | BluePoint | 30 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine Hydrochloride 150 mg 69367-0417-09 | Westminster | 90 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine 150 mg 72241-0076-04 | Modavar | 90 tablets | $0.233 | AB | Availability likely | — |
| Venlafaxine Hydrochloride 150 mg 47335-0758-08 | Sun | 100 tablets | — | — | FDA listed | — |
| Venlafaxine 150 mg 70518-4500-00 | REMEDYREPACK | 90 tablets | — | AB | FDA listed | — |
| Venlafaxine 150 mg 70710-1350-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Venlafaxine 150 mg 70771-1651-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Venlafaxine 150 mg 71209-0088-01 | Cadila | 30 tablets | — | AB | FDA listed | — |
| Venlafaxine Hydrochloride 150 mg 72865-0199-30 | XLCare | 30 tablets | — | AB | FDA listed | — |
| Venlafaxine Hydrochloride 150 mg 75834-0218-00 | Nivagen | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 64980-0580-03 | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE (64980-580-03) | $0.2333 / ea | $7.00 | 2022-11-28 | Active |
| 64980-0580-09 You're viewing this | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE (64980-580-09) | $0.2333 / ea | $21.00 | 2022-11-28 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.2333 NADAC).
This pack accounts for about 15% of this product's recent Medicaid fills; most go to the 30 tablets pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 64980-0580-09?
What is the difference between NDC 64980-0580-09 and NDC 64980-0580-03?
What NDC number is used to bill for this package of Venlafaxine Hydrochloride 150 mg Tablet, Extended Release?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: SUICIDALITY AND ANTIDEPRESSANT DRUGS Antidepressants increased the risk compared to placebo of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults in short-term studies of Major Depressive Disorder (MDD) and other psychiatric disorders. Anyone considering the use of venlafaxine extended-release tablets or any other antidepressant in a child, adolescent, or young adult must balance this risk with the clinical need. Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction in risk with antidepressants compared to placebo in adults aged 65 and older.
Depression and certain other psychiatric disorders are themselves associated with increases in the risk of suicide. Patients of all ages who are started on antidepressant therapy should be monitored appropriately and observed closely for clinical worsening, suicidality, or unusual changes in behavior. Families and caregivers should be advised of the need for close observation and communication with the prescriber.
Venlafaxine extended-release tablets are not approved for use in pediatric patients. [ See Warnings and Precautions ( 5.1 ) and Patient Counseling Information ( 17.1 ) ] WARNING: Suicidality and Antidepressants See full prescribing information for complete boxed warning. Increased risk of suicidal thinking and behavior in children, adolescents and young adults taking antidepressants for major depressive disorder (MDD) and other psychiatric disorders. Venlafaxine Extended-Release Tablets are not approved for use in pediatric patients.
( 5.1 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Venlafaxine extended-release tablets are a selective serotonin and norepinephrine reuptake inhibitor (SNRI) indicated for: Major Depressive Disorder (MDD) ( 1.1 ) Social Anxiety Disorder (SAD) ( 1.2 )
1.1Major Depressive Disorder Venlafaxine extended-release tablets are indicated for the treatment of major depressive disorder (MDD). Efficacy of venlafaxine in MDD was shown in both short-term trials and a longer-term trial in MDD [ see Clinical Studies ( 14.1 ) ]. A major depressive episode (DSM-IV) implies a prominent and relatively persistent (nearly every day for at least 2 weeks) depressed mood or the loss of interest or pleasure in nearly all activities, representing a change from previous functioning, and includes the presence of at least five of the following nine symptoms during the same two-week period: depressed mood, markedly diminished interest or pleasure in usual activities, significant change in weight and/or appetite, insomnia or hypersomnia, psychomotor agitation or retardation, increased fatigue, feelings of guilt or worthlessness, slowed thinking or impaired concentration, a suicide attempt or suicidal ideation.
1.2Social Anxiety Disorder Venlafaxine extended-release tablets are indicated for the treatment of Social Anxiety Disorder (SAD), also known as Social Phobia, as defined in DSM-IV. Social Anxiety Disorder (DSM-IV) is characterized by a marked and persistent fear of 1 or more social or performance situations in which the person is exposed to unfamiliar people or to possible scrutiny by others. Exposure to the feared situation almost invariably provokes anxiety, which may approach the intensity of a panic attack.
The feared situations are avoided or endured with intense anxiety or distress. The avoidance, anxious anticipation, or distress in the feared situation(s) interferes significantly with the person's normal routine, occupational or academic functioning, or social activities or relationships, or there is a marked distress about having the phobias. Lesser degrees of performance anxiety or shyness generally do not require psychopharmacological treatment.
Efficacy of venlafaxine extended-release tablets in the treatment of SAD was established in short-term SAD trials [ see Clinical Studies ( 14.2 ) ].
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Venlafaxine extended-release tablets should be administered in a single dose with food either in the morning or in the evening at approximately the same time each day. Each tablet should be swallowed whole with fluid and not divided, crushed, chewed, or placed in water. Initial Treatment ( 2.1 ) Indication Starting Dose Dose Increase Maximum Dose Major Depressive Disorder 75 mg/day (in some patients, 37.5 mg/day for 4-7 days) 75 mg/day increments at intervals of 4 days or longer 225 mg/day Social Anxiety Disorder 75 mg/day No benefit at higher doses 75 mg/day Venlafaxine extended-release tablets should be taken as a single daily dose with food in either the morning or evening at the same time each day.
( 2 ) Discontinuation: Gradual; individualized as necessary. ( 2.4 )
2.1Initial Treatment Major Depressive Disorder For most patients, the recommended starting dose for venlafaxine extended-release tablets is 75 mg/day, administered in a single dose. In the clinical trials establishing the efficacy of venlafaxine hydrochloride extended-release capsules in moderately depressed outpatients, the initial dose of venlafaxine was 75 mg/day. For some patients, it may be desirable to start at 37.5 mg/day for 4 to 7 days to allow new patients to adjust to the medication before increasing to 75 mg/day.
While the relationship between dose and antidepressant response for venlafaxine hydrochloride extended-release capsules has not been adequately explored, patients not responding to the initial 75 mg/day dose may benefit from dose increases to a maximum of approximately 225 mg/day. Dose increases should be in increments of up to 75 mg/day, as needed, and should be made at intervals of not less than 4 days, since steady state plasma levels of venlafaxine and its major metabolites are achieved in most patients by day 4.
In the clinical trials establishing efficacy, upward titration was permitted at intervals of 2 weeks or more; the average doses were about 140 to 180 mg/day [ see Clinical Studies ( 14 ) ]. It should be noted that, while the maximum recommended dose for moderately depressed outpatients is also 225 mg/day for venlafaxine hydrochloride immediate-release tablets, more severely depressed inpatients in one study of the development program for that product responded to a mean dose of 350 mg/day (range of 150 to 375 mg/day).
Whether or not higher doses of venlafaxine extended-release tablets are needed for more severely depressed patients is unknown; however, the experience with venlafaxine hydrochloride extended-release capsule doses higher than 225 mg/day is very limited . Social Anxiety Disorder (Social Phobia) The recommended dose is 75 mg/day, administered in a single dose. There was no evidence that higher doses confer any additional benefit .
2.2Maintenance Treatment There is no body of evidence available from controlled trials to indicate how long patients with major depressive disorder should be treated with venlafaxine extended-release tablets. It is generally agreed that acute episodes of major depressive disorder require several months or longer of sustained pharmacological therapy beyond response to the acute episode. In one study, in which patients responding during 8 weeks of acute treatment with venlafaxine hydrochloride extended-release capsules were assigned randomly to placebo or to the same dose of venlafaxine hydrochloride extended-release capsules (75, 150, or 225 mg per day, qAM) during 26 weeks of maintenance treatment as they had received during the acute stabilization phase, longer-term efficacy was demonstrated.
A second longer-term study has demonstrated the efficacy of venlafaxine hydrochloride immediate-release tablets in maintaining a response in patients with recurrent major depressive disorder who had responded and continued to be improved during an initial 26 weeks of treatment and were then randomly assigned to placebo or venlafaxine hydrochloride immediate-release table…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Venlafaxine extended-release tablets are available as: 37.5 mg tablets (White to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V1’ with black ink on any side) 75 mg tablets (White to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V2’ with black ink on any side) 150 mg tablets (White to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V3’ with black ink on any side) 225 mg tablets (White to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V4’ with black ink on any side) 37.5 mg, 75 mg, 150 mg, and 225 mg tablets ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Serotonin Syndrome and MAOIs: Do not use MAOI’s intended to treat psychiatric disorders with venlafaxine extended-release tablets or within 7 days of stopping treatment with venlafaxine extended-release tablets. Do not use venlafaxine extended-release tablets within 14 days of stopping an MAOI intended to treat psychiatric disorders. In addition, do not start venlafaxine extended-release tablets in a patient who is being treated with linezolid or intravenous methylene blue.
( 4.1 )
4.1Monoamine Oxidase Inhibitors (MAOIs) The use of MAOI’s intended to treat psychiatric disorders with venlafaxine extended-release tablets or within 7 days of stopping treatment with venlafaxine extended-release tablets is contraindicated because of an increased risk of serotonin syndrome. The use of venlafaxine extended-release tablets within 14 days of stopping an MAOI intended to treat psychiatric disorders is also contraindicated [ see Dosage and Administration ( 2.6 ), and Warnings and Precautions ( 5.2 ) ]. Starting venlafaxine extended-release tablets in a patient who is being treated with MAOIs such as linezolid or intravenous methylene blue is also contraindicated because of an increased risk of serotonin syndrome [ see Dosage and Administration ( 2.7 ) and Warnings and Precautions ( 5.2 ) ].
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Serotonin Syndrome : Serotonin syndrome has been reported with SSRIs and SNRIs, including venlafaxine extended-release tablets, both when taken alone, but especially when co-administered with other serotonergic agents. If such symptoms occur, discontinue venlafaxine extended-release tablets and serotonergic agents and initiate supportive treatment. If concomitant use of venlafaxine extended-release tablets and serotonergic agents with other serotonergic drugs is clinically warranted, patients should be made aware of a potential increased risk for serotonin syndrome, particularly during treatment initiation and dose increases.
( 5.2 ) Suicidality: Monitor for clinical worsening and suicide risk. ( 5.1 ) Sustained hypertension may occur. Blood pressure monitoring recommended.
( 5.3 ) Angle Closure Glaucoma: Angle closure glaucoma has occurred in patients with untreated anatomically narrow angles treated with antidepressants. ( 5.4 ) Abrupt discontinuation or dose reduction: Discontinuation symptoms may occur (generally self-limiting; serious symptoms possible). Dose reduction recommended to be gradual.
( 5.5 ) Activation of Mania/Hypomania has occurred. ( 5.10 ) Symptomatic hyponatremia may occur. ( 5.11 ) Seizures have been reported.
Use with caution in patients with seizure history. ( 5.12 ) Abnormal bleeding (most commonly ecchymosis) has been reported. ( 5.13 ) Serum cholesterol: Clinically relevant cholesterol increases may occur.
Cholesterol measurements should be considered during long-term therapy. ( 5.14 ) Interstitial lung disease and eosinophilic pneumonia have been reported. ( 5.15 ) Sexual Dysfunction: Venlafaxine extended-release tablets may cause symptoms of sexual dysfunction.
( 5.18 )
5.1Clinical Worsening and Suicide Risk Patients with major depressive disorder (MDD), both adult and pediatric, may experience worsening of their depression and/or the emergence of suicidal ideation and behavior (suicidality) or unusual changes in behavior, whether or not they are taking antidepressant medications, and this risk may persist until significant remission occurs. Suicide is a known risk of depression and certain other psychiatric disorders, and these disorders themselves are the strongest predictors of suicide.
There has been a long standing concern, however, that antidepressants may have a role in inducing worsening of depression and the emergence of suicidality in certain patients during the early phases of treatment. Pooled analyses of short-term placebo-controlled trials of antidepressant drugs (SSRIs and others) showed that these drugs increase the risk of suicidal thinking and behavior (suicidality) in children, adolescents, and young adults (ages 18-24) with major depressive disorder (MDD) and other psychiatric disorders.
Short-term studies did not show an increase in the risk of suicidality with antidepressants compared to placebo in adults beyond age 24; there was a reduction with antidepressants compared to placebo in adults aged 65 and older. The pooled analyses of placebo-controlled trials in children and adolescents with MDD, obsessive compulsive disorder (OCD), or other psychiatric disorders included a total of 24 short-term trials of 9 antidepressant drugs in over 4400 patients. The pooled analyses of placebo-controlled trials in adults with MDD or other psychiatric disorders included a total of 295 short-term trials (median duration of 2 months) of 11 antidepressant drugs in over 77,000 patients.
There was considerable variation in risk of suicidality among drugs, but a tendency toward an increase in the younger patients for almost all drugs studied. There were differences in absolute risk of suicidality across the different indications, with the highest incidence in MDD. The risk differences (drug vs placebo), however, were relatively stable within age strata and across indications.
These risk differences (drug-placebo difference in the number of cases of suicidality per 100…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Major Depressive Disorder - Adverse events in short-term studies that occurred in at least 5% of the patients receiving venlafaxine extended-release capsules and at a rate at least twice that of the placebo group were abnormal ejaculation, gastrointestinal complaints (nausea, dry mouth, and anorexia), CNS complaints (dizziness, somnolence, and abnormal dreams), and sweating. Social Anxiety Disorder - Adverse events in short-term studies that occurred in at least 5% of the patients receiving venlafaxine extended-release capsules and at a rate at least twice that of the placebo group were asthenia, gastrointestinal complaints (anorexia, dry mouth, nausea), CNS complaints (anxiety, insomnia, libido decreased, nervousness, somnolence, dizziness), abnormalities of sexual function (abnormal ejaculation, orgasmic dysfunction, impotence), yawn, sweating, and abnormal vision.
TO REPORT SUSPECTED ADVERSE REACTIONS, CONTACT RISING PHARMA HOLDINGS, INC. AT 1-844-874-7464 OR FDA AT 1-800-FDA-1088 OR WWW.FDA.GOV/MEDWATCH .
6.1Clinical Studies Experience Data Sources The information included in subsection "Adverse Findings Observed in Short-Term, Placebo-Controlled Studies with Venlafaxine Hydrochloride Extended-Release Capsules" is based on data from a pool of three 8- and 12-week controlled clinical trials in major depressive disorder (includes two U.S. trials and one European trial), and on data up to 12 weeks from a pool of two controlled clinical trials in Social Anxiety Disorder. Information on additional adverse reactions associated with venlafaxine hydrochloride extended-release capsules in the entire development program for the formulation and with venlafaxine hydrochloride immediate-release tablets is included in the subsection "Other Adverse Reactions Observed During the Premarketing Evaluation of Venlafaxine Hydrochloride Immediate-Release Tablets and Venlafaxine Hydrochloride Extended-Release Capsules" [ see also Warnings and Precautions ( 5 ) ].
Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Findings Observed in Short-Term, Placebo-Controlled Studies with Venlafaxine Hydrochloride Extended-Release Capsules Adverse Reactions Associated with Discontinuation of Treatment Major Depressive Disorder : Approximately 11% of the 357 patients who received venlafaxine hydrochloride extended-release capsules in placebo-controlled clinical trials for major depressive disorder discontinued treatment due to an adverse reaction, compared with 6% of the 285 placebo-treated patients in those studies.
Adverse reactions that led to treatment discontinuation in a least 2% of drug-treated patients were nausea, dizziness, and somnolence. Social Anxiety Disorder : Approximately 17% of the 277 patients who received venlafaxine hydrochloride extended-release capsules in placebo-controlled clinical trials for Social Anxiety Disorder discontinued treatment due to an adverse reaction, compared with 5% of the 274 placebo-treated patients in those studies. Adverse reactions that led to treatment discontinuation in a least 2% of drug-treated patients were nausea, insomnia, impotence, headache, dizziness, and somnolence.
Adverse Reactions Occurring at an Incidence of 5% or More Major Depressive Disorder : Note in particular the following adverse reactions that occurred in at least 5% of the patients receiving venlafaxine hydrochloride extended-release capsules and at a rate at least twice that of the placebo group for all placebo-controlled trials for the major depressive disorder indication (see Table 6): Abnormal ejaculation, gastrointestinal complaints (nausea, dry mouth, and anorexia), CNS complaints (dizziness, somnolence, and abnormal dreams), and sweating.
In the two U.S. placebo-controlled trials, the following…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS MAOI's: concomitant use contraindicated ( 4 ). Avoid MAOI's 14 days before starting venlafaxine and 7 days after stopping venlafaxine ( 5.2 ). Cimetidine: Caution in patients with pre-existing hypertension, in elderly patients and patients with hepatic dysfunction.
( 7.2 ) Haloperidol: Increase in Haloperidol AUC and C max . ( 7.4 ) Ketoconazole: Increase in venlafaxine and O-desmethylvenlafaxine AUC and C max . Caution when using venlafaxine with substances that inhibit both CYP2D6 and CYP3A4.
( 7.7 ) Metoprolol: Possibly reduced blood-pressure lowering effect despite increased metoprolol plasma levels. Caution should be exercised with co-administration of venlafaxine and metoprolol. ( 7.8 ) CNS-active drugs: Caution when using venlafaxine with such drugs.
( 7.10 ) Serotonergic drugs (e.g., triptans, SSRIs, other SNRIs, linezolid, lithium, tramadol, or St. John's Wort): Potential for serotonin syndrome. Careful patient observation advised.
( 7.10 ) Tryptophan supplements: Concomitant use not recommended. ( 7.10 )
7.1Alcohol A single dose of ethanol (0.5 g/kg) had no effect on the pharmacokinetics of venlafaxine or O-desmethylvenlafaxine (ODV) when venlafaxine was administered at 150 mg/day in 15 healthy male subjects. Additionally, administration of venlafaxine in a stable regimen did not exaggerate the psychomotor and psychometric effects induced by ethanol in these same subjects when they were not receiving venlafaxine.
7.2Cimetidine Concomitant administration of cimetidine and venlafaxine in a steady-state study for both drugs resulted in inhibition of first-pass metabolism of venlafaxine in 18 healthy subjects. The oral clearance of venlafaxine was reduced by about 43%, and the exposure (AUC) and maximum concentration (C max ) of the drug were increased by about 60%. However, coadministration of cimetidine had no apparent effect on the pharmacokinetics of ODV, which is present in much greater quantity in the circulation than venlafaxine.
The overall pharmacological activity of venlafaxine plus ODV is expected to increase only slightly, and no dosage adjustment should be necessary for most normal adults. However, for patients with pre-existing hypertension, and for elderly patients or patients with hepatic dysfunction, the interaction associated with the concomitant use of venlafaxine and cimetidine is not known and potentially could be more pronounced. Therefore, caution is advised with such patients.
7.3Diazepam Under steady-state conditions for venlafaxine administered at 150 mg/day, a single 10 mg dose of diazepam did not appear to affect the pharmacokinetics of either venlafaxine or ODV in 18 healthy male subjects. Venlafaxine also did not have any effect on the pharmacokinetics of diazepam or its active metabolite, desmethyldiazepam, or affect the psychomotor and psychometric effects induced by diazepam.
7.4Haloperidol Venlafaxine administered under steady-state conditions at 150 mg/day in 24 healthy subjects decreased total oral-dose clearance (Cl/F) of a single 2 mg dose of haloperidol by 42%, which resulted in a 70% increase in haloperidol AUC. In addition, the haloperidol C max increased 88% when coadministered with venlafaxine, but the haloperidol elimination half-life (t 1/2 ) was unchanged. The mechanism explaining this finding is unknown.
7.5Lithium The steady-state pharmacokinetics of venlafaxine administered at 150 mg/day were not affected when a single 600 mg oral dose of lithium was administered to 12 healthy male subjects. ODV also was unaffected. Venlafaxine had no effect on the pharmacokinetics of lithium (see also CNS-Active Drugs, below).
7.6Drugs Highly Bound to Plasma Proteins Venlafaxine is not highly bound to plasma proteins; therefore, administration of venlafaxine extended-release tablets to a patient taking another drug that is highly protein bound should not cause increased free concentrations of the other drug.
7.7 Drugs that Inhibit Cytochrome P450 Isoenzymes CYP2D…
🔄 Drug / Laboratory Test Interactions ▾
7.14Drug-Laboratory Test Interactions False-positive urine immunoassay screening tests for phencyclidine (PCP) and amphetamine have been reported in patients taking venlafaxine. This is due to lack of specificity of the screening tests. False positive test results may be expected for several days following discontinuation of venlafaxine therapy.
Confirmatory tests, such as gas chromatography/mass spectrometry, will distinguish venlafaxine from PCP and amphetamine.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Use during pregnancy only if clearly needed. Neonates exposed to venlafaxine in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding. Benefits and risk of venlafaxine use in the third trimester should be carefully considered.
( 2.3 ; 8.1 ) Nursing: Potential for serious adverse reactions in the infant. Discontinue nursing or drug, considering the importance of the drug to the mother. ( 8.3 ) Pediatric use: Not approved for use in pediatric patients.
When considering use in a child or adolescent, balance potential risks with clinical need. ( 8.4 ) Hepatic impairment: Reduction of total daily dose by 50% recommended in patients with mild to moderate impairment. In patients with cirrhosis, further reduction may be necessary and dosing individualization may be desirable.
( 2.3 ; 8.6 ) Renal impairment: Reduction of daily dose by 25%-50% recommended. Dosing individualization may be necessary. ( 2.3 ; 8.7 ) Hemodialysis: Reduction of daily dose by 50%.
( 2.3 ; 8.7 )
8.1Pregnancy Based on data from published observational studies, exposure to SNRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions ( 5.13 ) and Clinical Considerations ]. Teratogenic Effects Venlafaxine did not cause malformations in offspring of rats or rabbits given doses up to 2.5 times (rat) or 4 times (rabbit) the maximum recommended human daily dose on a mg/m 2 basis. However, in rats, there was a decrease in pup weight, an increase in stillborn pups, and an increase in pup deaths during the first 5 days of lactation, when dosing began during pregnancy and continued until weaning.
The cause of these deaths is not known. These effects occurred at 2.5 times (mg/m 2 ) the maximum human daily dose. The no effect dose for rat pup mortality was 0.25 times the human dose on a mg/m 2 basis.
There are no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Non-Teratogenic Effects Neonates exposed to venlafaxine hydrochloride extended-release capsules, other SNRIs (Serotonin and Norepinephrine Reuptake Inhibitors), or SSRIs (Selective Serotonin Reuptake Inhibitors), late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding.
Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and SNRIs or, possibly, a drug discontinuation syndrome.
It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome [ see Warnings and Precautions (5.2) ]. When treating a pregnant woman with venlafaxine extended-release tablets during the third trimester, the physician should carefully consider the potential risks and benefits of treatment. Maternal Adverse Reactions Exposure to Venlafaxine Extended Release Tablets in mid to late pregnancy may increase the risk of preeclampsia, and exposure to Venlafaxine Extended Release Tablets in the month before delivery may be associated with an increased risk of postpartum hemorrhage [ see Warnings and Precautions ( 5.13 ) ].
8.2Labor and Delivery The effect of venlafaxine on labor and delivery in humans is unknown.
8.3Nursing Mothers Venlafaxine and ODV have been reported to be excreted in human milk. Because of the potential for serious adverse reactions in nursing infants from venlafaxine extended-release tablets, a decision should be made whether to d…
🤰 Pregnancy ▾
8.1Pregnancy Based on data from published observational studies, exposure to SNRIs, particularly in the month before delivery, has been associated with a less than 2-fold increase in the risk of postpartum hemorrhage [see Warnings and Precautions ( 5.13 ) and Clinical Considerations ]. Teratogenic Effects Venlafaxine did not cause malformations in offspring of rats or rabbits given doses up to 2.5 times (rat) or 4 times (rabbit) the maximum recommended human daily dose on a mg/m 2 basis. However, in rats, there was a decrease in pup weight, an increase in stillborn pups, and an increase in pup deaths during the first 5 days of lactation, when dosing began during pregnancy and continued until weaning.
The cause of these deaths is not known. These effects occurred at 2.5 times (mg/m 2 ) the maximum human daily dose. The no effect dose for rat pup mortality was 0.25 times the human dose on a mg/m 2 basis.
There are no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed. Non-Teratogenic Effects Neonates exposed to venlafaxine hydrochloride extended-release capsules, other SNRIs (Serotonin and Norepinephrine Reuptake Inhibitors), or SSRIs (Selective Serotonin Reuptake Inhibitors), late in the third trimester have developed complications requiring prolonged hospitalization, respiratory support, and tube feeding.
Such complications can arise immediately upon delivery. Reported clinical findings have included respiratory distress, cyanosis, apnea, seizures, temperature instability, feeding difficulty, vomiting, hypoglycemia, hypotonia, hypertonia, hyperreflexia, tremor, jitteriness, irritability, and constant crying. These features are consistent with either a direct toxic effect of SSRIs and SNRIs or, possibly, a drug discontinuation syndrome.
It should be noted that, in some cases, the clinical picture is consistent with serotonin syndrome [ see Warnings and Precautions (5.2) ]. When treating a pregnant woman with venlafaxine extended-release tablets during the third trimester, the physician should carefully consider the potential risks and benefits of treatment. Maternal Adverse Reactions Exposure to Venlafaxine Extended Release Tablets in mid to late pregnancy may increase the risk of preeclampsia, and exposure to Venlafaxine Extended Release Tablets in the month before delivery may be associated with an increased risk of postpartum hemorrhage [ see Warnings and Precautions ( 5.13 ) ].
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in the pediatric population have not been established [ see BOXED WARNING and Warnings and Precautions ( 5.1 ) ]. Two placebo-controlled trials in 766 pediatric patients with MDD and two placebo-controlled trials in another disorder in 793 pediatric patients have been conducted with venlafaxine hydrochloride extended-release capsules, and the data were not sufficient to support a claim for use in pediatric patients. Anyone considering the use of venlafaxine extended-release tablets in a child or adolescent must balance the potential risks with the clinical need.
Although no studies have been designed to primarily assess impact of venlafaxine hydrochloride extended-release capsules on the growth, development, and maturation of children and adolescents, the studies that have been done suggest that venlafaxine extended-release tablets may adversely affect weight and height [ see Warnings and Precautions ( 5.7 , 5.8 , and 5.9 ) ]. Should the decision be made to treat a pediatric patient with venlafaxine extended-release tablets, regular monitoring of weight and height is recommended during treatment, particularly if it is to be continued long term.
The safety of venlafaxine extended-release tablets treatment for pediatric patients has not been systematically assessed for chronic treatment longer than six months in duration. In the studies conducted in pediatric patients (ages 6 - 17), the occurrence of blood pressure and cholesterol increases considered to be clinically relevant in pediatric patients was similar to that observed in adult patients. Consequently, the precautions for adults apply to pediatric patients [ see Warnings and Precautions ( 5.3 and 5.14 ) ].
🧓 Geriatric Use ▾
8.5Geriatric Use Approximately 4% (14/357) and 2% (6/277) of patients treated with venlafaxine hydrochloride extended-release capsules in placebo-controlled premarketing major depressive disorder and Social Anxiety Disorder trials, respectively, were 65 years of age or over. Of 2,897 patients treated with venlafaxine hydrochloride immediate-release tablets in premarketing phase major depressive disorder studies, 12% (357) were 65 years of age or over. No overall differences in effectiveness or safety were observed between geriatric patients and younger patients, and other reported clinical experience generally has not identified differences in response between the elderly and younger patients.
However, greater sensitivity of some older individuals cannot be ruled out. SSRIs and SNRIs, including venlafaxine hydrochloride extended-release capsules have been associated with cases of clinically significant hyponatremia in elderly patients, who may be at greater risk for this adverse reaction [ see Warnings and Precautions ( 5.11 ) ]. The pharmacokinetics of venlafaxine and ODV are not substantially altered in the elderly [ see Clinical Pharmacology ( 12.3 ) ].
No dose adjustment is recommended for the elderly on the basis of age alone, although other clinical circumstances, some of which may be more common in the elderly, such as renal or hepatic impairment, may warrant a dose reduction [ see Dosage and Administration ( 2.3 )].
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Human Experience Among the patients included in the premarketing evaluation of venlafaxine hydrochloride extended-release capsules, there were 2 reports of acute overdosage with venlafaxine hydrochloride extended-release capsules in major depressive disorder trials, either alone or in combination with other drugs. One patient took a combination of 6 g of venlafaxine hydrochloride extended-release capsules and 2.5 mg of lorazepam. This patient was hospitalized, treated symptomatically, and recovered without any untoward effects.
The other patient took 2.85 g of venlafaxine hydrochloride extended-release capsules. This patient reported paresthesia of all four limbs but recovered without sequelae. There were no reports of acute overdose with venlafaxine hydrochloride extended-release capsules in Social Anxiety Disorder trials.
Among the patients included in the premarketing evaluation with venlafaxine hydrochloride immediate-release tablets, there were 14 reports of acute overdose with venlafaxine, either alone or in combination with other drugs and/or alcohol. The majority of the reports involved ingestion in which the total dose of venlafaxine taken was estimated to be no more than several-fold higher than the usual therapeutic dose. The 3 patients who took the highest doses were estimated to have ingested approximately 6.75 g, 2.75 g, and 2.5 g.
The resultant peak plasma levels of venlafaxine for the latter 2 patients were 6.24 and 2.35 mcg/mL, respectively, and the peak plasma levels of O-desmethylvenlafaxine were 3.37 and 1.30 mcg/mL, respectively. Plasma venlafaxine levels were not obtained for the patient who ingested 6.75 g of venlafaxine. All 14 patients recovered without sequelae.
Most patients reported no symptoms. Among the remaining patients, somnolence was the most commonly reported symptom. The patient who ingested 2.75 g of venlafaxine was observed to have 2 generalized convulsions and a prolongation of QTc to 500 msec, compared with 405 msec at baseline.
Mild sinus tachycardia was reported in 2 of the other patients. In postmarketing experience, overdose with venlafaxine has occurred predominantly in combination with alcohol and/or other drugs. The most commonly reported reactions in overdosage include tachycardia, changes in level of consciousness (ranging from somnolence to coma), mydriasis, seizures, and vomiting.
Electrocardiogram changes (e.g., prolongation of QT interval, bundle branch block, QRS prolongation), ventricular tachycardia, bradycardia, hypotension, rhabdomyolysis, vertigo, liver necrosis, serotonin syndrome, and death have been reported. Published retrospective studies report that venlafaxine overdosage may be associated with an increased risk of fatal outcomes compared to that observed with SSRI antidepressant products, but lower than that for tricyclic antidepressants. Epidemiological studies have shown that venlafaxine-treated patients have a higher pre-existing burden of suicide risk factors than SSRI-treated patients.
The extent to which the finding of an increased risk of fatal outcomes can be attributed to the toxicity of venlafaxine in overdosage as opposed to some characteristic(s) of venlafaxine-treated patients is not clear. Prescriptions for venlafaxine extended-release tablets should be written for the smallest quantity of tablets consistent with good patient management, in order to reduce the risk of overdose.
10.2Management of Overdosage Treatment should consist of those general measures employed in the management of overdosage with any antidepressant. Ensure an adequate airway, oxygenation, and ventilation. Monitor cardiac rhythm and vital signs.
General supportive and symptomatic measures are also recommended. Induction of emesis is not recommended. Gastric lavage with a large bore orogastric tube with appropriate airway protection, if needed, may be indicated if performed soon after ingestion or in symptomatic patients.
Activated charcoal should be administ…
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The mechanism of the antidepressant action of venlafaxine in humans is believed to be associated with its potentiation of neurotransmitter activity in the CNS. Preclinical studies have shown that venlafaxine and its active metabolite, O-desmethylvenlafaxine (ODV), are potent inhibitors of neuronal serotonin and norepinephrine reuptake and weak inhibitors of dopamine reuptake.
12.2Pharmacodynamics Venlafaxine and its active metabolite, O-desmethylvenlafaxine (ODV) have no significant affinity for muscarinic cholinergic, H 1 -histaminergic, or α 1 -adrenergic receptors in vitro . Pharmacologic activity at these receptors is hypothesized to be associated with the various anticholinergic, sedative, and cardiovascular effects seen with other psychotropic drugs. Venlafaxine and ODV do not possess monoamine oxidase (MAO) inhibitory activity.
12.3Pharmacokinetics Steady-state concentrations of venlafaxine and O-desmethylvenlafaxine (ODV) in plasma are attained within 3 days of oral multiple dose therapy. Venlafaxine and ODV exhibited linear kinetics over the dose range of 75 to 450 mg/day. The mean ± SD apparent elimination half-life for venlafaxine and ODV after administration of 75 mg venlafaxine extended-release tablets under fed conditions were 10.7±3.2 hours and 12.5±3.0 hours respectively.
Venlafaxine and ODV are minimally bound at therapeutic concentrations to plasma proteins (27% and 30%, respectively). Absorption and Distribution Venlafaxine is well absorbed and extensively metabolized in the liver. ODV is the only major active metabolite.
On the basis of mass balance studies, at least 92% of a single oral dose of venlafaxine is absorbed. The absolute bioavailability of venlafaxine is about 45%. Administration of 75 mg venlafaxine extended-release tablets under fed conditions resulted in mean ± SD venlafaxine C max of 26.9 ± 13.4 ng/mL and AUC of 1536.3 ± 496.8 ng∙hr/mL.
T max was 6.3 ± 2.3 hours. ODV mean ± SD C max , AUC, T max after administration of 75 mg venlafaxine extended-release tablets under fed conditions were 97.9 ± 29.4 ng/mL, 2926.0 ± 746.1 ng∙hr/mL, and 11.6 ± 2.9 hours, respectively. Administration of venlafaxine hydrochloride extended-release capsules (150 mg q24 hours) generally resulted in lower C max (150 ng/mL for venlafaxine and 260 ng/mL for ODV) and later T max (5.5 hours for venlafaxine and 9 hours for ODV) than for immediate release venlafaxine tablets (C max 's for immediate release 75 mg q12 hours were 225 ng/mL for venlafaxine and 290 ng/mL for ODV; T max 's were 2 hours for venlafaxine and 3 hours for ODV).
When equal daily doses of venlafaxine were administered as either an immediate release tablet or the extended-release form of venlafaxine, the exposure to both venlafaxine and ODV would be similar for the two treatments. Venlafaxine extended-release tablets would, therefore, provide a slower rate of absorption, but the same extent of absorption compared with the immediate-release tablet. Food did not affect the pharmacokinetic parameters AUC, C max , and T max of venlafaxine or its active metabolite, ODV, after administration of venlafaxine extended-release tablets.
Time of administration (AM vs PM) would not affect the pharmacokinetics of venlafaxine and ODV. Equal doses of venlafaxine hydrochloride extended-release tablets are bioequivalent to Effexor XR* capsules when administered under fed conditions. Metabolism and Excretion Following absorption, venlafaxine undergoes extensive presystemic metabolism in the liver, primarily to ODV, but also to N-desmethylvenlafaxine, N,O-didesmethylvenlafaxine, and other minor metabolites.
In vitro studies indicate that the formation of ODV is catalyzed by CYP2D6; this has been confirmed in a clinical study showing that patients with low CYP2D6 levels ("poor metabolizers") had increased levels of venlafaxine and reduced levels of ODV compared to people with normal CYP2D6 ("extensive metabolizers"). The d…
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of the antidepressant action of venlafaxine in humans is believed to be associated with its potentiation of neurotransmitter activity in the CNS. Preclinical studies have shown that venlafaxine and its active metabolite, O-desmethylvenlafaxine (ODV), are potent inhibitors of neuronal serotonin and norepinephrine reuptake and weak inhibitors of dopamine reuptake.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Venlafaxine extended-release tablets 37.5 mg are white to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V1’ with black ink on any side. They are supplied as follows: Unit of Use Bottles of 30 Tablets NDC 64980-578-03 Unit of Use Bottles of 90 Tablets NDC 64980-578-09 Venlafaxine extended-release tablets 75 mg are white to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V2’ with black ink on any side.
They are supplied as follows: Unit of Use Bottles of 30 Tablets NDC 64980-579-03 Unit of Use Bottles of 90 Tablets NDC 64980-579-09 Venlafaxine extended-release tablets 150 mg are white to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V3’ with black ink on any side. They are supplied as follows: Unit of Use Bottles of 30 Tablets NDC 64980-580-03 Unit of Use Bottles of 90 Tablets NDC 64980-580-09 Venlafaxine extended-release tablets 225 mg are white to off white, beveled edge, round biconvex, film coated tablets with release port on one side and imprinted ‘V4’ with black ink on any side.
They are supplied as follows: Unit of Use Bottles of 30 Tablets NDC 64980-581-03 Unit of Use Bottles of 90 Tablets NDC 64980-581-09 Store at 25°C (77° F); excursions permitted to 15° - 30°C (59° - 86° F) [see USP Controlled Room Temperature]. Protect from moisture and humidity.
📋 Description ▾
11 DESCRIPTION Venlafaxine extended-release tablets are extended-release tablets for oral administration that contain venlafaxine hydrochloride USP, a structurally novel antidepressant. Venlafaxine hydrochloride is a selective serotonin and norepinephrine reuptake inhibitor (SNRI). It is designated 1-[(1 RS )-2-Dimethylamino)-1-(4-methoxyphenyl)ethyl] cyclohexanol hydrochloride or (±)-1-[α-[(dimethylamino)methyl]-p-methoxybenzyl] cyclohexanol hydrochloride and has the empirical formula of C 17 H 27 NO 2 HCl.
Its molecular weight is 313.9. The structural formula is shown below. Venlafaxine hydrochloride is a white or almost white powder freely soluble in methanol and water; soluble in anhydrous ethanol and slightly soluble or practically insoluble in acetone.
Its octanol:water (0.2 M sodium chloride) partition coefficient is 0.43. Venlafaxine extended-release tablets are formulated as extended-release tablet for once-a-day oral administration. Venlafaxine extended-release tablets use osmotic pressure to deliver venlafaxine hydrochloride at a controlled rate over approximately 24 hours.
The system, which resembles a conventional tablet in appearance, comprises an osmotically active core surrounded by a semipermeable membrane. The unitary tablet core is composed of the drug and excipients (including the osmotically active components). There is a precision-laser drilled orifice in the semipermeable membrane on the side of the tablet.
In an aqueous environment, such as the gastrointestinal tract, water permeates through the membrane into the tablet core, causing the drug to dissolve and the osmotic components to expand. This expansion pushes the drug out through the orifice. The semipermeable membrane controls the rate at which water permeates into the tablet core, which in turn controls the rate of drug delivery.
The controlled rate of drug delivery into the gastrointestinal lumen is thus independent of pH or gastrointestinal motility. The function of venlafaxine extended-release tablets depends on the existence of an osmotic gradient between the contents of the core and the fluid in the gastrointestinal tract. Since the osmotic gradient remains constant, drug delivery remains essentially constant.
The biologically inert components of the tablet remain intact during gastrointestinal transit and are eliminated in the feces as an insoluble shell. Each extended-release tablet contains venlafaxine hydrochloride, USP equivalent to 37.5 mg, 75 mg, 150 mg, or 225 mg venlafaxine. Inactive ingredients consist of cellulose acetate, colloidal silicon dioxide, lactose monohydrate, magnesium stearate, mannitol, microcrystalline cellulose, opacode black ink (S-1-277001) (ferrosoferric oxide, propylene glycol and shellac), opadry white 03L580003 (hypromellose, propylene glycol, titanium dioxide and triacetin), polyethylene glycol, povidone. venlafaxine-struct
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Prescribers or other health professionals should inform patients, their families, and their caregivers about the benefits and risks associated with treatment with venlafaxine extended-release tablets and should counsel them in its appropriate use. A patient Medication Guide about "Antidepressant Medicines, Depression and Other Serious Mental Illness, and Suicidal Thoughts or Actions" is available for venlafaxine extended-release tablets.
The prescriber or health professional should instruct patients, their families, and their caregivers to read the Medication Guide and should assist them in understanding its contents. Patients should be given the opportunity to discuss the contents of the Medication Guide and to obtain answers to any questions they may have. The complete text of the Medication Guide is reprinted at the end of this document.
Patients should be advised of the following issues and asked to alert their prescriber if these occur while taking venlafaxine extended-release tablets.
17.1Clinical Worsening and Suicide Risk Patients, their families, and their caregivers should be encouraged to be alert to the emergence of anxiety, agitation, panic attacks, insomnia, irritability, hostility, aggressiveness, impulsivity, akathisia (psychomotor restlessness), hypomania, mania, other unusual changes in behavior, worsening of depression, and suicidal ideation, especially early during antidepressant treatment and when the dose is adjusted up or down. Families and caregivers of patients should be advised to look for the emergence of such symptoms on a day-to-day basis, since changes may be abrupt.
Such symptoms should be reported to the patient's prescriber or health professional, especially if they are severe, abrupt in onset, or were not part of the patient's presenting symptoms. Symptoms such as these may be associated with an increased risk for suicidal thinking and behavior and indicate a need for very close monitoring and possibly changes in the medication.
17.2Interference with Cognitive and Motor Performance Clinical studies were performed to examine the effects of venlafaxine on behavioral performance of healthy individuals. The results revealed no clinically significant impairment of psychomotor, cognitive, or complex behavior performance. However, since any psychoactive drug may impair judgment, thinking, or motor skills, patients should be cautioned about operating hazardous machinery, including automobiles, until they are reasonably certain that venlafaxine therapy does not adversely affect their ability to engage in such activities.
17.3Concomitant Medication Patients should be advised to inform their physicians if they are taking, or plan to take, any prescription or over-the-counter drugs, including herbal preparations and nutritional supplements, since there is a potential for interactions. Patients should be cautioned about the risk of serotonin syndrome with the concomitant use of venlafaxine extended-release tablets and triptans, tricyclic antidepressants, opioids, lithium, amphetamines, tryptophan, buspirone, and St. John’s Wort supplements or other serotonergic agents [ see Warnings and Precautions ( 5.2 ) and Drug Interactions ( 7.10 ) ].
Patients should be cautioned about the concomitant use of venlafaxine extended-release tablets and NSAID's, aspirin, warfarin, or other drugs that affect coagulation since combined use of psychotropic drugs that interfere with serotonin reuptake and these agents has been associated with an increased risk of bleeding [see Warnings and Precautions ( 5.13 ) and Drug Interactions ( 7.11 ) ].
17.4Alcohol Although venlafaxine has not been shown to increase the impairment of mental and motor skills caused by alcohol, patients should be advised to avoid alcohol while taking venlafaxine.
17.5 Allergic Reactions Patients should be advised to notify their physician…
💬 Medication Guide ▾
Medication Guide Antidepressant Medicines, Depression and Other Serious Mental Illnesses, and Suicidal Thoughts or Actions Read the Medication Guide that comes with your or your family member's antidepressant medicine. This Medication Guide is only about the risk of suicidal thoughts and actions with antidepressant medicines. T alk to your, or your family member's, healthcare provider about: all risks and benefits of treatment with antidepressant medicines all treatment choices for depression or other serious mental illness Who should not take venlafaxine extended-release tablets? take a monoamine oxidase inhibitor (MAOI).
Ask your healthcare provider or pharmacist if you are not sure if you take an MAOI, including the antibiotic linezolid. Do not take an MAOI within 7 days of stopping venlafaxine extended-release tablets unless directed to do so by your physician. Do not start venlafaxine extended-release tablets if you stopped taking an MAOI in the last 2 weeks unless directed to do so by your physician.
What is the most important information I should know about antidepressant medicines, depression and other serious mental illnesses, and suicidal thoughts or actions? 1. Antidepressant medicines may increase suicidal thoughts or actions in some children, teenagers, and young adults within the first few months of treatment.
2. Depression and other serious mental illnesses are the most important causes of suicidal thoughts and actions. Some people may have a particularly high risk of having suicidal thoughts or actions.
These include people who have (or have a family history of) bipolar illness (also called manic-depressive illness) or suicidal thoughts or actions. 3. How can I watch for and try to prevent suicidal thoughts and actions in myself or a family member?
Pay close attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. This is very important when an antidepressant medicine is started or when the dose is changed. Call the healthcare provider right away to report new or sudden changes in mood, behavior, thoughts, or feelings.
Keep all follow-up visits with the healthcare provider as scheduled. Call the healthcare provider between visits as needed, especially if you have concerns about symptoms. Call a healthcare provider right away if you or your family member has any of the following symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling very agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood Visual Problems: Eye pain, change in vision, swelling or redness around eye What else do I need to know about antidepressant medicines?
Never stop an antidepressant medicine without first talking to a healthcare provider. Stopping an antidepressant medicine suddenly can cause other symptoms. Visual Problems.
Only some people are at risk for these problems. You may want to undergo an eye examination to see if you are at risk and receive preventative treatment if you are. Antidepressants are medicines used to treat depression and other illnesses.
It is important to discuss all the risks of treating depression and also the risks of not treating it. Patients and their families or other caregivers should discuss all treatment choices with the healthcare provider, not just the use of antidepressants. Antidepressant medicines have other side effects.
Talk to the healthcare provider about the side effects of the medicine prescribed for you or your family member. Antidepressant medicines can interact with other medicines. Know all of the medicines that you or your family member takes.
Keep a list of all medicines to show the healthcare provider. Do not start new medicines without first…