
Chlorthalidone 50 mg Tablet, 100-count — NDC 64980-600-01 (Billing 64980-0600-01)
This is a package of 100 tablets of Chlorthalidone 50 mg Tablet from Rising Pharma Holdings, Inc., marketed since Oct 2024 and currently FDA-listed; retail pharmacies pay about $0.1218 per tablet (NADAC). It is this product's only package size.
Other active recalls for Chlorthalidone (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 008214
- GCN: 34984
- GPI-14 (Medi-Span): 37600025000310
- HICL (First Databank): 003662
- AHFS class code: 24:36.24.00
- RxCUI (RxNorm): 197499
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Thiazide-like Diuretic class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Chlorthalidone, a is used to treat high blood pressure and fluid retention. Chlorthalidone is in a class of medications called diuretics ('water pills'). It causes the kidneys to get rid of unneeded water and salt from the body into the urine. High blood pressure is a common condition, and when not treated it can cause damage to the brain, heart, blood vessels, kidneys, and other parts of the body. Damage to these organs may cause heart disease, a heart attack, heart failure, stroke, kidney failure, loss of vision, and other problems. In addition to taking medication, making lifestyle changes...
Read the full MedlinePlus article ↗- Chlorthalidone is a water pill — it helps your kidneys remove extra salt and fluid from your body. That lowers the pressure inside your blood vessels, which is why it's used for hi...
- What exactly is chlorthalidone supposed to do for me?
- Take it in the morning with food — that's the standard recommendation. Taking it in the morning means the increased urination it causes happens during the day while you're awake, r...
- Should I take it in the morning or at night, and does it matter if I eat?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Chlorthalidone — tap one for details:
Chlorthalidone may be associated with lower levels of 8 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.122 | $12.18 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2219 | $22.19 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.2420 | $24.20 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 64980-0600-01 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 2024-10-23 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Chlorthalidone 50 mg 00378-0213-01 | Mylan | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 16714-0129-01 | Northstar | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 27241-0217-01 | Ajanta | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 29300-0334-01 | Unichem | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 43598-0167-01 | Dr. | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 43598-0720-01 | Dr. | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 62135-0506-30 | Chartwell | 30 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone Chlorthalidone 50 mg 62332-0677-31 | Alembic | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 64980-0304-01 | Rising | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mgthis 64980-0600-01 | Rising | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 67877-0697-01 | Ascend | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 68382-0971-01 | Zydus | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 70756-0020-11 | Lifestar | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 75834-0110-01 | Nivagen | 100 tablets | $0.122 | AB | Availability likely | — |
| Chlorthalidone 50 mg 51224-0118-50 | TAGI | 100 tablets | $0.152 | AB | FDA listed | +25% |
| Chlorthalidone 50 mg 59746-0761-01 | JUBILANT | 100 tablets | $0.152 | AB | FDA listed | +25% |
| Chlorthalidone Chlorthalidone 50 mg 46708-0677-31 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 50090-5183-01 | A-S | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 51655-0477-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 51655-0961-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 57664-0649-18 | Sun | 1000 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 60290-0005-01 | Umedica | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 63629-2465-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 63629-4446-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 63629-8762-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 63629-9298-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 65162-0250-03 | Amneal | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 67046-1495-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 67046-1499-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 70771-1370-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 71335-2580-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 71335-2956-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 71335-3089-01 | Bryant | 90 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 71610-0021-09 | Aphena | 9000 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 72162-2010-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 72162-2134-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 72789-0359-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 33342-0426-07 | Macleods | 30 tablets | — | AB | FDA listed | — |
| Chlorthalidone 50 mg 83980-0062-01 | Ipca | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
7 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Diuretics such as chlorthalidone are indicated in the management of hypertension either as the sole therapeutic agent or to enhance the effect of other antihypertensive drugs in the more severe forms of hypertension. Chlorthalidone is indicated as adjunctive therapy in edema associated with congestive heart failure, hepatic cirrhosis, and corticosteroid and estrogen therapy. Chlorthalidone has also been found useful in edema due to various forms of renal dysfunction, such as nephrotic syndrome, acute glomerulonephritis, and chronic renal failure.
Usage in Pregnancy: The routine use of diuretics in an otherwise healthy woman is inappropriate and exposes mother and fetus to unnecessary hazard. Diuretics do not prevent development of toxemia of pregnancy, and there is no satisfactory evidence that they are useful in the treatment of developed toxemia. Edema during pregnancy may arise from pathological causes or from the physiologic and mechanical consequences of pregnancy.
Chlorthalidone is indicated in pregnancy when edema is due to pathologic causes, just as it is in the absence of pregnancy (however, see PRECAUTIONS , below). Dependent edema in pregnancy, resulting from restriction of venous return by the expanded uterus, is properly treated through elevation of the lower extremities and use of support hose; use of diuretics to lower intravascular volume in this case is illogical and unnecessary. There is hypervolemia during normal pregnancy that is harmful to neither the fetus nor the mother (in the absence of cardiovascular disease), but that is associated with edema, including generalized edema, in the majority of pregnant women.
If this edema produces discomfort, increased recumbency will often provide relief. In rare instances, this edema may cause extreme discomfort that is not relieved by rest. In these cases, a short course of diuretics may provide relief and be appropriate.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Therapy should be initiated with the lowest possible dose. This dose should be titrated according to individual patient response to gain maximal therapeutic benefit while maintaining lowest dosage possible. A single dose given in the morning with food is recommended; divided daily doses are unnecessary.
Hypertension: Initiation : Therapy, in most patients, should be initiated with a single daily dose of 25 mg. If the response is insufficient after a suitable trial, the dosage may be increased to a single daily dose of 50 mg. If additional control is required, the dosage of chlorthalidone may be increased to 100 mg once daily or a second antihypertensive drug (step 2 therapy) may be added.
Dosage above 100 mg daily usually does not increase effectiveness. Increases in serum uric acid and decreases in serum potassium are dose-related over the 25 to 100 mg/day range. Maintenance : Maintenance doses may be lower than initial doses and should be adjusted according to individual patient response.
Effectiveness is well sustained during continued use. Edema: Initiation : Adults, initially 50 to 100 mg daily, or 100 mg on alternate days. Some patients may require 150 to 200 mg at these intervals or up to 200 mg daily.
Dosages above this level, however, do not usually produce a greater response. Maintenance : Maintenance doses may often be lower than initial doses and should be adjusted according to individual patient response. Effectiveness is well sustained during continued use.
⛔ Contraindications ▾
CONTRAINDICATIONS Anuria. Known hypersensitivity to chlorthalidone or other sulfonamide-derived drugs.
⚠️ Warnings ▾
WARNINGS Chlorthalidone should be used with caution in severe renal disease. In patients with renal disease, chlorthalidone or related drugs may precipitate azotemia. Cumulative effects of the drug may develop in patients with impaired renal function.
Chlorthalidone should be used with caution in patients with impaired hepatic function or progressive liver disease, since minor alterations of fluid and electrolyte balance may precipitate hepatic coma. Sensitivity reactions may occur in patients with a history of allergy or bronchial asthma. The possibility of exacerbation or activation of systemic lupus erythematosus has been reported with thiazide diuretics, which are structurally related to chlorthalidone.
However, systemic lupus erythematosus has not been reported following chlorthalidone administration.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse reactions have been observed, but there is not enough systematic collection of data to support an estimate of their frequency. Gastrointestinal System Reactions : anorexia, gastric irritation nausea, vomiting cramping diarrhea constipation jaundice (intrahepatic cholestatic jaundice) pancreatitis Central Nervous System Reactions : dizziness vertigo paresthesias headache xanthopsia Hematologic Reactions : leukopenia agranulocytosis thrombocytopenia aplastic anemia Dermatologic-Hypersensitivity Reactions : purpura photosensitivity rash urticaria necrotizing angiitis (vasculitis) (cutaneous vasculitis) Lyell's syndrome (toxic epidermal necrolysis) Cardiovascular Reactions : orthostatic hypotension may occur and may be aggravated by alcohol, barbiturates, or narcotics.
Other Adverse Reactions : hyperglycemia glycosuria hyperuricemia muscle spasm weakness restlessness impotence Whenever adverse reactions are moderate or severe, chlorthalidone dosage should be reduced or therapy withdrawn.
🆘 Overdosage ▾
OVERDOSAGE Symptoms of acute overdosage include nausea, weakness, dizziness, and disturbances of electrolyte balance. The oral LD 50 of the drug in the mouse and the rat is more than 25,000 mg/kg body weight. The minimum lethal dose (MLD) in humans has not been established.
There is no specific antidote, but gastric lavage is recommended, followed by supportive treatment. Where necessary, this may include intravenous dextrose-saline with potassium, administered with caution.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Chlorthalidone is an oral diuretic with prolonged action (48–72 hours) and low toxicity. The major portion of the drug is excreted unchanged by the kidneys. The diuretic effect of the drug occurs in approximately 2.6 hours and continues for up to 72 hours.
The mean half-life following a 50 to 200 mg dose is 40 hours. In the first order of absorption, the elimination half-life is 53 hours following a 50 mg dose, and 60 hours following a 100 mg dose. Approximately 75 percent of the drug is bound to plasma proteins, 58 percent of the drug being bound to albumin.
This is caused by an increased affinity of the drug to erythrocyte carbonic anhydrase. Nonrenal routes of elimination have yet to be clarified. Data are not available regarding percentage of dose as unchanged drug and metabolites, concentration of the drug in body fluids, degree of uptake by a particular organ or in the fetus, or passage across the blood-brain barrier.
The drug produces copious diuresis with greatly increased excretion of sodium and chloride. At maximal therapeutic dosage, chlorthalidone is approximately equal in its diuretic effect to comparable maximal therapeutic doses of benzothiadiazine diuretics. The site of action appears to be the cortical diluting segment of the ascending limb of Henle's loop of the nephron.
📦 How Supplied / Storage and Handling ▾
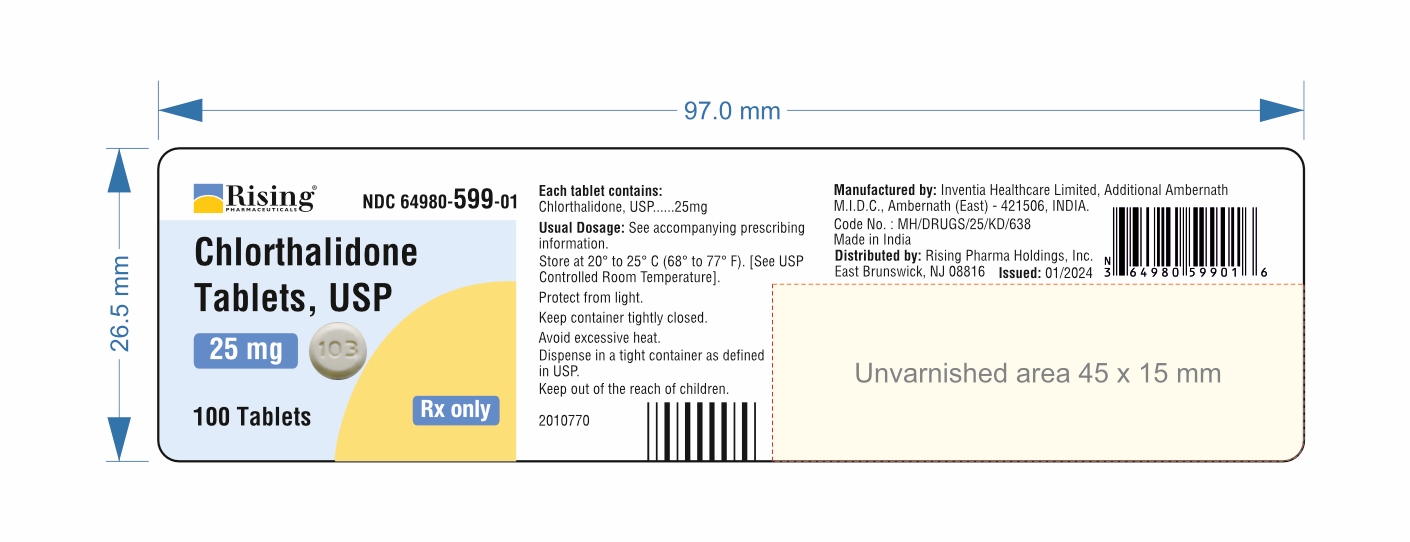
HOW SUPPLIED Chlorthalidone Tablets, USP are available containing 25 mg or 50 mg of Chlorthalidone, USP. The 25 mg tablets are light-yellow colored, round shaped, uncoated, flat, bevelled edge tablets, debossed with '103'on one side of the tablet and blank on the other side. They are available as follows: NDC 64980-599-01 Bottles of 100 with child-resistant closure NDC 64980-599-10 Bottles of 1000 with child-resistant closure The 50 mg tablets are light-green colored, round shaped, uncoated, flat, bevelled edge scored tablets, debossed with '1' to the left and '3'to the right of the score on one side of the tablet and blank on the other side.
They are available as follows: NDC 64980-600-01 Bottles of 100 with child-resistant closure Store at 20 to 25° C (68 to 77° F). [See USP Controlled Room Temperature]. Protect from light. Keep container tightly closed.
Avoid excessive heat. Dispense in a tight container as defined in the USP. Keep out of the reach of children.
This product should be dispensed in a container with a child-resistant cap. Manufactured by: Inventia Healthcare Limited, F1-F1/1-F75/1, Additional Ambernath M.I.D.C., Ambernath (East), Thane 421 506 Maharashtra State, INDIA Code No.: MH/DRUGS/25/KD/638 Made in India Distributed by: Rising Pharma Holdings, Inc. East Brunswick, NJ 08816 Revised: 11/2024
📋 Description ▾
DESCRIPTION Chlorthalidone USP is an oral antihypertensive/diuretic. It is a monosulfamyl diuretic that differs chemically from thiazide diuretics in that a double-ring system is incorporated in its structure. It is 2-chloro-5(1-hydroxy-3-oxo-1-isoindolinyl) benzenesulfonamide, with the following structural formula: Chlorthalidone, USP is practically insoluble in water, in ether, and in chloroform; soluble in methanol; slightly soluble in alcohol.
Chlorthalidone tablets are available containing either 25 mg or 50 mg of chlorthalidone USP and the following inactive ingredients: colloidal silicon dioxide, corn starch, crospovidone, ferric oxide yellow, magnesium stearate, microcrystalline cellulose. The 50 mg tablet also contains FD&C Blue #1. structure
⚠️ Precautions ▾
PRECAUTIONS General: Hypokalemia may develop with chlorthalidone as with any other diuretic, especially with brisk diuresis when severe cirrhosis is present or during concomitant use of corticosteroids or ACTH. Interference with adequate oral electrolyte intake will also contribute to hypokalemia. Digitalis therapy may exaggerate metabolic effects of hypokalemia especially with reference to myocardial activity.
Any chloride deficit is generally mild and usually does not require specific treatment except under extraordinary circumstances (as in liver disease or renal disease). Dilutional hyponatremia may occur in edematous patients in hot weather, appropriate therapy is water restriction, rather than administration of salt except in rare instances when the hyponatremia is life threatening. In actual salt depletion, appropriate replacement is the therapy of choice.
Hyperuricemia may occur or frank gout may be precipitated in certain patients receiving chlorthalidone. Thiazide-like diuretics have been shown to increase the urinary excretion of magnesium; this may result in hypomagnesemia. The antihypertensive effects of the drug may be enhanced in the post-sympathectomy patient.
If progressive renal impairment becomes evident, as indicated by a rising nonprotein nitrogen or blood urea nitrogen, a careful reappraisal of therapy is necessary with consideration given to withholding or discontinuing diuretic therapy. Calcium excretion is decreased by thiazide-like drugs. Pathological changes in the parathyroid gland with hypercalcemia and hypophosphatemia have been observed in few patients on thiazide therapy.
The common complications of hyperparathyroidism such as renal lithiasis, bone resorption and peptic ulceration have not been seen. Information for Patients: Patients should inform their physician if they have: 1) had an allergic reaction to chlorthalidone or other diuretics or have asthma, 2) kidney disease, 3) liver disease, 4) gout, 5) systemic lupus erythematosus, or 6) been taking other drugs such as cortisone, digitalis, lithium carbonate, or drugs for diabetes. Patients should be cautioned to contact their physician if they experience any of the following symptoms of potassium loss: excess thirst, tiredness, drowsiness, restlessness, muscle pains or cramps, nausea, vomiting, or increased heart rate or pulse.
Patients should also be cautioned that taking alcohol can increase the chance of dizziness occurring. Laboratory Tests: Periodic determination of serum electrolytes to detect possible electrolyte imbalance should be performed at appropriate intervals. All patients receiving chlorthalidone should be observed for clinical signs of fluid or electrolyte imbalance: namely, hyponatremia, hypochloremic alkalosis, and hypokalemia.
Serum and urine electrolyte determinations are particularly important when the patient is vomiting excessively or receiving parenteral fluids. Drug Interactions: Chlorthalidone may add to or potentiate the action of other antihypertensive drugs. Potentiation occurs with ganglionic peripheral adrenergic blocking drugs.
Medication such as digitalis may also influence serum electrolytes. Warning signs, irrespective of cause, are: Dryness of mouth, thirst, weakness, lethargy, drowsiness, restlessness, muscle pains or cramps, muscular fatigue, hypotension, oliguria, tachycardia, and gastrointestinal disturbances such as nausea and vomiting. Insulin requirements in diabetic patients may be increased, decreased, or unchanged.
Higher dosage of oral hypoglycemic agents may be required. Latent diabetes mellitus may become manifest during chlorthalidone administration. Chlorthalidone and related drugs may increase the responsiveness to tubocurarine.
Chlorthalidone and related drugs may decrease arterial responsiveness to norepinephrine. This diminution is not sufficient to preclude effectiveness of the pressor agent for therapeutic use. Drug/Laboratory Test Interactions: Chlorthalidone and related drugs may de… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL label-01 label-02 label-03