
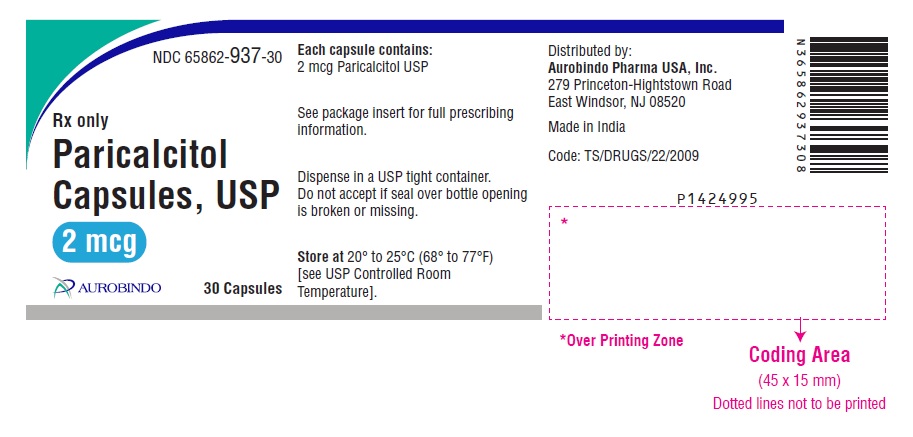
Paricalcitol 2 ug Capsule, Liquid Filled, 30-count — NDC 65862-937-30 (Billing 65862-0937-30)
This is a package of 30 capsules of Paricalcitol 2 ug Capsule, Liquid Filled from Aurobindo Pharma Limited, marketed since Aug 2021 and currently FDA-listed; retail pharmacies pay about $2.59 per capsule (NADAC). It is the main listing for this product, which comes in 2 package sizes.
NDC database record
One package, one record: these facts belong to NDC 65862-937-30 alone.
- Record
- FDA NDC Directory package listing · Drug for further processing
- Code segments
- 65862 labeler · 937 product · 30 package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 6586293730 8
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 059182
- GCN: 24723
- GPI-14 (Medi-Span): 30905070000120
- HICL (First Databank): 018250
- AHFS class code: 88:16.00.00
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
Clinical
- It treats and prevents secondary hyperparathyroidism, which is high PTH caused by chronic kidney disease. It works like vitamin D to bring PTH down. Capsules and injection are used...
- Capsules are swallowed, either daily or three times a week depending on your plan. You can take them with or without food. The injection is given during dialysis through your acces...
- Diarrhea, nausea, vomiting, dizziness, high blood pressure and swelling are among the most common. Mention anything that bothers you or does not go away.
- Watch for tiredness, trouble thinking clearly, poor appetite, nausea, vomiting, constipation, increased thirst or urination, and weight loss. Call your doctor if these appear or wo...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Paricalcitol — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $2.589 | $77.66 / 30 capsules |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.56 | $46.86 / 30 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 4, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 65862-0937-30 You're viewing this Main listing | 30 CAPSULE, LIQUID FILLED in 1 BOTTLE | $2.59 / ea | $77.66 | 2016-01-14 | — | Active |
| 65862-0937-39 65862-937-39 | 3000 CAPSULE, LIQUID FILLED in 1 BAG | — | — | — | — | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 65862-0937-39?
What NDC number is used to bill for this package of Paricalcitol 2 ug Capsule, Liquid Filled?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Paricalcitol 2 ug 49483-0688-03 | TIME | 30 capsules | $2.589 | AB | Availability likely | — |
| Paricalcitol 2 ugthis 65862-0937-30 | Aurobindo | 30 capsules | $2.589 | — | Availability likely | — |
| Paricalcitol 2 ug 69452-0146-13 | Bionpharma | 30 capsules | $2.589 | AB | Availability likely | — |
| Zemplar 2 ug 00074-9037-30 | AbbVie | 30 capsules | — | — | FDA listed | — |
| Paricalcitol 2 ug 25000-0014-03 | MARKSANS | 30 capsules | — | AB | FDA listed | — |
| Paricalcitol 2 ug 55111-0664-01 | Dr. | 100 capsules | — | AB | FDA listed | — |
| Paricalcitol 2 ug 63629-2453-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Paricalcitol 2 ug 65162-0823-03 | Amneal | 30 capsules | — | AB | FDA listed | — |
| Paricalcitol 2 ug 72162-1916-03 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Paricalcitol 2 ug 11014-0336-01 | Catalent | 30000 capsules | — | — | FDA listed | — |
| Paricalcitol 2 ug 10888-8103-01 | Patheon | 15000 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII 1P9D0Z171K
BHT is a synthetic antioxidant that prevents fats and oils in medicines from breaking down and becoming rancid. It helps keep the product stable and effective during storage.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII PDC6A3C0OX
Glycerin is a clear, thick liquid derived from plant oils or fats. It acts as a humectant to retain moisture, a sweetener, and a solvent in medications.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII C9H2L21V7U
A fat derived from coconut or palm oil containing shorter fatty acid chains. It serves as a solvent and carrier to help dissolve or suspend active ingredients, improving absorption and stability in liquid formulations.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Aurobindo Pharma Limited labeler code 65862
- nitrofurantoin (monohydrate/macrocrystals) 25 mg; 75 mg Capsule NDC 65862-929-01
- Sevelamer Carbonate 800 mg Powder, For Suspension NDC 65862-930-90
- Sevelamer Carbonate 2400 mg Powder, For Suspension NDC 65862-931-90
- Aurovela 24 Fe Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 65862-934-58
- Aurovela 1.5/30 Norethindrone Acetate and Ethinyl Estradiol 1.5 mg; 30 ug Tablet NDC 65862-935-54
- Paricalcitol 1 ug Capsule, Liquid Filled NDC 65862-936-30
- Paricalcitol 4 ug Capsule, Liquid Filled NDC 65862-938-30
- Aurovela 1/20 Norethindrone Acetate and Ethinyl Estradiol 1 mg; 20 ug Tablet NDC 65862-939-54
- Aurovela Fe 1/20 Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 65862-940-58
- AUROVELA Fe Norethindrone Acetate and Ethinyl Estradiol and Ferrous Fumarate Kit NDC 65862-941-58
- LEVALBUTEROL 1.25 mg/.5mL Solution, Concentrate NDC 65862-942-03
- Levalbuterol .31 mg/3mL Solution NDC 65862-943-24
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full FDA label FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Paricalcitol is a vitamin D analog indicated in adults and pediatric patients 10 years and older for the prevention and treatment of secondary hyperparathyroidism associated with: Chronic kidney disease (CKD) Stages 3 and 4 (1.1) . CKD Stage 5 in patients on hemodialysis or peritoneal dialysis (1.2) .
1.1Chronic Kidney Disease Stages 3 and 4 Paricalcitol capsules are indicated in adults and pediatric patients 10 years of age and older for the prevention and treatment of secondary hyperparathyroidism associated with Chronic Kidney Disease (CKD) Stages 3 and 4.
1.2Chronic Kidney Disease Stage 5 Paricalcitol capsules are indicated in adults and pediatric patients 10 years of age and older for the prevention and treatment of secondary hyperparathyroidism associated with CKD Stage 5 in patients on hemodialysis (HD) or peritoneal dialysis (PD).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Initial Dosage: CKD Stages 3 and 4 ( 2.1 , 2.3 ) Adult: Baseline iPTH ≤ 500 pg/mL 1 mcg orally daily or 2 mcg three times a week* Adult: Baseline iPTH > 500 pg/mL 2 mcg orally daily or 4 mcg three times a week* Pediatric: Ages 10 to 16 years 1 mcg orally three times a week* Dose Titration: CKD Stages 3 and 4 ( 2.1 , 2.3 ) Adult: iPTH same, increased or decreased by < 30% relative to baseline Increase dose by 1 mcg daily or 2 mcg three times a week* Adult: iPTH decreased by ≥ 30% and ≤ 60% relative to baseline Maintain dose Adult: iPTH decreased by > 60% or iPTH < 60 pg/mL relative to baseline Decrease dose by 1 mcg daily or 2 mcg three times a week* Pediatric: Ages 10 to 16 years Increase each dose by 1 mcg three times a week every 4 weeks or decrease each dose by 1 mcg three times a week at any time based on iPTH, serum calcium and phosphorus levels.* * Not more frequently than every other day when dosing three times a week.
Initial Dosage: CKD Stage 5 ( 2.2 , 2.3 ) Adult Dose (micrograms) = baseline iPTH (pg/mL) divided by 80. Administer dose orally three times a week.* Pediatric: Ages 10 to 16 years Dose (micrograms) = baseline iPTH (pg/mL) divided by 120. Administer dose orally three times a week.* Dose Titration: CKD Stage 5 ( 2.2 , 2.3 ) Adult Dose in micrograms is based on most recent iPTH (pg/mL) divided by 80 with adjustments based on serum calcium and phosphorous levels.
Dose three times a week.* Pediatric: Ages 10 to 16 years Increase each dose by 1 mcg three times a week every 4 weeks or decrease each dose by 2 mcg three times a week at any time based on iPTH, serum calcium and phosphorus levels.* * Not more frequently than every other day. CKD Stage 5: To avoid hypercalcemia only treat patients after their baseline serum calcium has been reduced to 9.5 mg/dL or lower ( 2.2 ).
2.1Chronic Kidney Disease Stages 3 and 4 in Adults Administer paricalcitol capsules orally once daily or three times a week [see Clinical Studies (14.1) ]. When dosing three times weekly, do not administer more frequently than every other day. Initial Dose Table 1.
Recommended Paricalcitol Capsules Starting Dose Based upon Baseline iPTH Level * To be administered not more often than every other day Baseline iPTH Level Daily Dose Three Times a Week Dose* Less than or equal to 500 pg/mL 1 mcg 2 mcg More than 500 pg/mL 2 mcg 4 mcg Dose Titration Table 2. Recommended Paricalcitol Capsules Dose Titration Base upon iPTH Level * To be administered not more often than every other day Dose Adjustment at 2 to 4 Week Intervals iPTH Level Relative to Baseline Paricalcitol Capsule Dose Daily Dosage Three Times a Week Dosage* The same, increased or decreased by less than 30% Increase dose by 1 mcg 2 mcg Decreased by more than or equal to 30% and less than or equal to 60% Maintain dose - - Decreased by more than 60% or iPTH less than 60 pg/mL Decrease dose by 1 mcg 2 mcg If a patient is taking the lowest dose, 1 mcg, on the daily regimen and a dose reduction is needed, the dose can be decreased to 1 mcg three times a week.
If a further dose reduction is required, the drug should be withheld as needed and restarted at a lower dosing frequency.
2.2Chronic Kidney Disease Stage 5 in Adults Initial Dose Administer the dose of paricalcitol capsules orally three times a week, no more frequently than every other day based upon the following formula: Dose (micrograms) = baseline iPTH (pg/mL) divided by 80 Treat patients only after their baseline serum calcium has been adjusted to 9.5 mg/dL or lower to minimize the risk of hypercalcemia [see Clinical Pharmacology (12.2) and Clinical Studies (14.2) ] . Dose Titration Individualize the dose of paricalcitol capsules based on iPTH, serum calcium and phosphorus levels.
Titrate paricalcitol capsules dose based on the following formula: Dose (micrograms) = most recent iPTH level (pg/mL) divided by 80 If serum calcium is elevated, the dose should be decreased by 2 to 4 micrograms. As iPTH approa… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Paricalcitol capsules, USP are available as 1 mcg, 2 mcg, and 4 mcg soft gelatin capsules. 1 mcg: gray colored opaque, oval shaped soft gelatin capsule imprinted as “1” with black edible ink containing clear colorless to pale yellow colored oily liquid. 2 mcg: orange brown colored opaque, oval shaped soft gelatin capsule imprinted as “P2” with black edible ink containing clear colorless to pale yellow colored oily liquid.
4 mcg: gold colored opaque, oval shaped soft gelatin capsule imprinted as “P4” with black edible ink containing clear colorless to pale yellow colored oily liquid. Capsules: 1 mcg, 2 mcg, and 4 mcg (3) .
⛔ Contraindications ▾
4 CONTRAINDICATIONS Paricalcitol capsules should not be given to patients with evidence of hypercalcemia or vitamin D toxicity [see Warnings and Precautions (5.1) ] . Evidence of hypercalcemia (4). Evidence of vitamin D toxicity (4).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Excessive administration of vitamin D compounds, including paricalcitol capsules, can cause over suppression of PTH, hypercalcemia, hypercalciuria, hyperphosphatemia, and adynamic bone disease. Hypercalcemia: Excessive administration of paricalcitol capsules can cause over suppression of PTH, hypercalcemia, hypercalciuria, hyperphosphatemia, and adynamic bone disease. Prescription-based doses of vitamin D and its derivatives should be withheld during paricalcitol treatment (5.1) .
Digitalis toxicity: Potentiated by hypercalcemia of any cause. Use caution when paricalcitol capsules are prescribed concomitantly with digitalis compounds (5.2) . Laboratory tests: Monitor serum calcium, serum phosphorus, and serum or plasma iPTH during initial dosing or following any dose adjustment.
Paricalcitol capsules may increase serum creatinine and therefore decrease the estimated GFR (eGFR) (5.3) . Aluminum overload and toxicity: Avoid excessive use of aluminum containing compounds (5.4) .
5.1Hypercalcemia Progressive hypercalcemia due to overdosage of vitamin D and its metabolites may be so severe as to require emergency attention [see Overdosage (10) ] . Acute hypercalcemia may exacerbate tendencies for cardiac arrhythmias and seizures and may potentiate the action of digitalis. Chronic hypercalcemia can lead to generalized vascular calcification and other soft-tissue calcification.
Concomitant administration of high doses of calcium-containing preparations or thiazide diuretics with paricalcitol may increase the risk of hypercalcemia. High intake of calcium and phosphate concomitant with vitamin D compounds may lead to serum abnormalities requiring more frequent patient monitoring and individualized dose titration. Patients also should be informed about the symptoms of elevated calcium, which include feeling tired, difficulty thinking clearly, loss of appetite, nausea, vomiting, constipation, increased thirst, increased urination and weight loss.
Prescription-based doses of vitamin D and its derivatives should be withheld during paricalcitol treatment to avoid hypercalcemia.
5.2Digitalis Toxicity Digitalis toxicity is potentiated by hypercalcemia of any cause. Use caution when paricalcitol capsules are prescribed concomitantly with digitalis compounds.
5.3Laboratory Tests During the initial dosing or following any dose adjustment of medication, serum calcium, serum phosphorus, and serum or plasma iPTH should be monitored at least every two weeks for 3 months, then monthly for 3 months, and every 3 months thereafter. In pre-dialysis patients, paricalcitol capsules may increase serum creatinine and therefore decrease the estimated GFR (eGFR). Similar effects have also been seen with calcitriol.
5.4Aluminum Overload and Toxicity Aluminum-containing preparations (e.g., antacids, phosphate binders) should not be administered chronically with paricalcitol, as increased blood levels of aluminum and aluminum bone toxicity may occur.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. The most common adverse reactions (> 5% and more frequent than placebo) include diarrhea, nasopharyngitis, dizziness, vomiting, hypertension, hypersensitivity, nausea, and edema (6). To report SUSPECTED ADVERSE REACTIONS, contact Aurobindo Pharma USA, Inc. at 1-800-850-2876 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience CKD Stages 3 and 4 Adults The safety of paricalcitol capsules has been evaluated in three 24-week (approximately six-month), double-blind, placebo-controlled, multicenter clinical studies involving 220 CKD Stages 3 and 4 patients. Six percent (6%) of paricalcitol capsules treated patients and 4% of placebo treated patients discontinued from clinical studies due to an adverse event. Adverse events occurring in the paricalcitol capsules group at a frequency of 2% or greater and more frequently than in the placebo group are presented in Table 3: Table 3.
Adverse Reactions by Body System Occurring in ≥ 2% of Subjects in the Paricalcitol-Treated Group of Three, Double-Blind, Placebo-Controlled CKD Stages 3 and 4 Studies Number (%) of Subjects Adverse Event a Paricalcitol Capsules (n = 107) Placebo (n = 113) Overall 88 (82%) 86 (76%) Ear and Labyrinth Disorders Vertigo 5 (5%) 0 (0%) Gastrointestinal Disorders Abdominal Discomfort 4 (4%) 1 (1%) Constipation 4 (4%) 4 (4%) Diarrhea 7 (7%) 5 (4%) Nausea 6 (6%) 4 (4%) Vomiting 5 (5%) 5 (4%) General Disorders and Administration Site Conditions Chest Pain 3 (3%) 1 (1%) Edema 6 (6%) 5 (4%) Pain 4 (4%) 4 (4%) Immune System Disorders Hypersensitivity 6 (6%) 2 (2%) Infections and Infestations Fungal Infection 3 (3%) 0 (0%) Gastroenteritis 3 (3%) 3 (3%) Infection 3 (3%) 3 (3%) Sinusitis 3 (3%) 1 (1%) Urinary Tract Infection 3 (3%) 1 (1%) Viral Infection 8 (7%) 8 (7%) Metabolism and Nutrition Disorders Dehydration 3 (3%) 1 (1%) Musculoskeletal and Connective Tissue Disorders Arthritis 5 (5%) 0 (0%) Back Pain 3 (3%) 1 (1%) Muscle Spasms 3 (3%) 0 (0%) Nervous System Disorders Dizziness 5 (5%) 5 (4%) Headache 5 (5%) 5 (4%) Syncope 3 (3%) 1 (1%) Psychiatric Disorders Depression 3 (3%) 0 (0%) Respiratory, Thoracic and Mediastinal Disorders Cough 3 (3%) 2 (2%) Oropharyngeal Pain 4 (4%) 0 (0%) Skin and Subcutaneous Tissue Disorders Pruritus 3 (3%) 3 (3%) Rash 4 (4%) 1 (1%) Skin Ulcer 3 (3%) 0 (0%) Vascular Disorders Hypertension 7 (7%) 4 (4%) Hypotension 5 (5%) 3 (3%) a.
Includes only events more common in the paricalcitol treatment group. Additional Adverse Reactions The following additional adverse reactions occurred in <2% of the paricalcitol-treated patients in the above double-blind, placebo-controlled clinical trial. Gastrointestinal Disorders: Dry mouth Investigations: Hepatic enzyme abnormal Nervous System Disorders: Dysgeusia Skin and Subcutaneous Tissue Disorders: Urticaria Pediatric patients 10 to 16 years of age The safety of paricalcitol capsules has been evaluated in one multicenter clinical study involving CKD Stages 3 and 4 patients ages 10 to 16 years.
A 12-week double-blind, placebo-controlled phase was followed by an open-label phase during which all patients received paricalcitol capsules. During the 12-week blinded phase, a total of 18 patients received paricalcitol capsules and 18 patients received placebo. Adverse events occurring more frequently in the paricalcitol capsules group than in the placebo group are presented in Table 4.
Table 4. Adverse Reactions by Body System Occurring in the Double-Blind, Placebo-Controlled, CKD Stages 3 and 4 Study in Patients Ages 10 to 16 Years Number (%) of Subjects Adverse Event a Paricalcitol Capsules (n = 18) Placebo (n = 18) Overall 7 (39%) 16 (89%) Gastrointestinal Disorders Nausea 1 (6%) 0 (0%) Infections an… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 6 shows the clinically significant drug interactions with paricalcitol capsules. Table 6: Clinically Significant Drug Interactions with Paricalcitol CYP3A Inhibitors Clinical Impact Paricalcitol is partially metabolized by CYP3A. Hence, exposure of paricalcitol will increase upon coadministration with strong CYP3A inhibitors such as but not limited to: boceprevir, clarithromycin, conivaptan, grapefruit juice, indinavir, itraconazole, ketoconazole, lopinavir/ritonavir, mibefradil, nefazodone, nelfinavir, posaconazole, ritonavir, saquinavir, telaprevir, telithromycin, voriconazole.
Intervention Dose adjustment of paricalcitol capsules may be necessary. Monitor closely for iPTH and serum calcium concentrations, if a patient initiates or discontinues therapy with a strong CYP3A4 inhibitor. Cholestyramine Clinical Impact Drugs that impair intestinal absorption of fat-soluble vitamins, such as cholestyramine, may interfere with the absorption of paricalcitol.
Intervention Recommend to take paricalcitol capsules at least 1 hour before or 4 to 6 hours after taking cholestyramine (or at as great an interval as possible) to avoid impeding absorption of paricalcitol. Mineral Oil Clinical Impact Mineral oil or other substances that may affect absorption of fat may influence the absorption of paricalcitol. Intervention Recommend to take paricalcitol capsules at least 1 hour before or 4 to 6 hours after taking mineral oil (or at as great an interval as possible) to avoid affecting absorption of paricalcitol.
Strong CYP3A inhibitors (e.g., ketoconazole) will increase the exposure of paricalcitol. Use with caution (7) . Cholestyramine, Mineral Oil: Intestinal absorption of paricalcitol may be reduced if administered simultaneously with cholestyramine or mineral oil.
Take paricalcitol capsules at least 1 hour before or 4 to 6 hours after taking cholestyramine or mineral oil (7).
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding not recommended (8.2) .
8.1Pregnancy Risk Summary Limited data with paricalcitol capsules in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with chronic kidney disease in pregnancy [see Clinical Considerations] . In animal reproduction studies, slightly increased embryofetal loss was observed in pregnant rats and rabbits administered paricalcitol intravenously during the period of organogenesis at doses 2 and 0.5 times, respectively, the maximum recommended human dose (MRHD).
Adverse reproductive outcomes were observed at doses that caused maternal toxicity [see Data] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Chronic kidney disease in pregnancy increases the maternal risk for hypertension, spontaneous abortion, preterm labor, and preeclampsia. Chronic kidney disease increases the fetal risk for intrauterine growth restriction (IUGR), prematurity, polyhydramnios, still birth, and low birth weight.
Data Animal Data Pregnant rats and rabbits were treated with paricalcitol by once-daily intravenous (IV) injection during the period of organogenesis (in rats, from gestation day (GD) 6 to 17; in rabbits, from GD 6 to 18). Rats were dosed at 0, 0.3, 1.0 or 3.0 mcg/kg/day and rabbits at 0, 0.03, 0.1 or 0.3 mcg/kg/day, representing up to 2 or 0.5 times, respectively, the maximum recommended human dose (MRHD) of 0.24 mcg/kg, based on body surface area (mg/m 2 ). Slightly decreased fetal viability was observed in both studies at the highest doses representing 2 and 0.5 times, respectively, the MRHD in the presence of maternal toxicity (decreased body weight and food consumption).
Pregnant rats were administered paricalcitol by IV injection three times per week at doses of 0, 0.3, 3.0 or 20.0 mcg/kg/day throughout gestation, parturition and lactation (GD 6 to lactation day (LD) 20) representing exposures up to 13 times the MHRD. A small increase in stillbirths and pup deaths from parturition to LD 4 were observed at the high dose when compared to the control group (9.2% versus 3.3% in controls) at 13 times the MRHD, which occurred at a maternally toxic dose known to cause hypercalcemia in rats.
Surviving pups were not adversely affected; body weight gains, developmental landmarks, reflex ontogeny, learning indices, and locomotor activity were all within normal parameters. F1 reproductive capacity was unaffected.
8.2Lactation Risk Summary There is no information available on the presence of paricalcitol in human milk, the effects of the drug on the breastfed infant or the effects of the drug on milk production. Studies in rats have shown that paricalcitol and/or its metabolites are present in the milk of lactating rats; however, due to specifies-specific differences in lactation physiology, animal data may not reliably predict drug levels in human milk [see Data] . Because of the potential for serious adverse reactions, including hypercalcemia in a breastfed infant, advise patients that breastfeeding is not recommended during treatment with paricalcitol.
Data Following a single oral administration of 20 mcg/kg of radioactive [ 3 H] paricalcitol to lactating rats, the concentrations of total radioactivity was determined. Lower levels of total radioactivity were present in the milk compared to that in the plasma of the dams indicating that low levels of [ 3 H] paricalcitol and/or its metabolites are secreted into milk. Exposure of the pups to [ 3 H] paricalcitol through mi… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited data with paricalcitol capsules in pregnant women are insufficient to inform a drug-associated risk for major birth defects and miscarriage. There are risks to the mother and fetus associated with chronic kidney disease in pregnancy [see Clinical Considerations] . In animal reproduction studies, slightly increased embryofetal loss was observed in pregnant rats and rabbits administered paricalcitol intravenously during the period of organogenesis at doses 2 and 0.5 times, respectively, the maximum recommended human dose (MRHD).
Adverse reproductive outcomes were observed at doses that caused maternal toxicity [see Data] . The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Chronic kidney disease in pregnancy increases the maternal risk for hypertension, spontaneous abortion, preterm labor, and preeclampsia. Chronic kidney disease increases the fetal risk for intrauterine growth restriction (IUGR), prematurity, polyhydramnios, still birth, and low birth weight.
Data Animal Data Pregnant rats and rabbits were treated with paricalcitol by once-daily intravenous (IV) injection during the period of organogenesis (in rats, from gestation day (GD) 6 to 17; in rabbits, from GD 6 to 18). Rats were dosed at 0, 0.3, 1.0 or 3.0 mcg/kg/day and rabbits at 0, 0.03, 0.1 or 0.3 mcg/kg/day, representing up to 2 or 0.5 times, respectively, the maximum recommended human dose (MRHD) of 0.24 mcg/kg, based on body surface area (mg/m 2 ). Slightly decreased fetal viability was observed in both studies at the highest doses representing 2 and 0.5 times, respectively, the MRHD in the presence of maternal toxicity (decreased body weight and food consumption).
Pregnant rats were administered paricalcitol by IV injection three times per week at doses of 0, 0.3, 3.0 or 20.0 mcg/kg/day throughout gestation, parturition and lactation (GD 6 to lactation day (LD) 20) representing exposures up to 13 times the MHRD. A small increase in stillbirths and pup deaths from parturition to LD 4 were observed at the high dose when compared to the control group (9.2% versus 3.3% in controls) at 13 times the MRHD, which occurred at a maternally toxic dose known to cause hypercalcemia in rats.
Surviving pups were not adversely affected; body weight gains, developmental landmarks, reflex ontogeny, learning indices, and locomotor activity were all within normal parameters. F1 reproductive capacity was unaffected.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of paricalcitol capsules have been established in pediatric patients 10 to 16 years of age for the prevention and treatment of secondary hyperparathyroidism associated with Stage 3, 4, and 5 CKD. Use of paricalcitol capsules in this age group is supported by evidence from adequate and well controlled studies in adults with CKD, a 12-week double-blind placebo-controlled randomized multicenter study in 36 pediatric patients 10 to 16 years of age with CKD Stages 3 and 4, and safety data from a 12-week open-label single-arm multicenter study in 13 pediatric patients 10 to 16 years of age with CKD Stage 5 receiving peritoneal dialysis or hemodialysis.
The pharmacokinetics of paricalcitol in Stage 5 CKD pediatric patients appear to be similar to those observed in Stage 3 and 4 pediatric patients [see Clinical Pharmacology (12.3) and Clinical Studies (14.1) ] . Adverse reactions reported in these pediatric studies are consistent with the known safety profile of paricalcitol capsules and with what has been reported in adult clinical studies [see Adverse Reactions (6.1) ] . Safety and effectiveness of paricalcitol capsules in pediatric patients under the age of 10 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the total number (n = 220) of CKD Stages 3 and 4 patients in clinical studies of paricalcitol capsules, 49% were age 65 and over, while 17% were age 75 and over. Of the total number (n = 88) of CKD Stage 5 patients in the pivotal study of paricalcitol capsules, 28% were age 65 and over, while 6% were age 75 and over. No overall differences in safety and effectiveness were observed between these patients and younger patients, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Excessive administration of paricalcitol capsules can cause hypercalcemia, hypercalciuria, and hyperphosphatemia, and over suppression of PTH [see Warnings and Precautions (5.1) ]. Treatment of Overdosage The treatment of acute overdosage of paricalcitol capsules should consist of general supportive measures. If drug ingestion is discovered within a relatively short time, induction of emesis or gastric lavage may be of benefit in preventing further absorption.
If the drug has passed through the stomach, the administration of mineral oil may promote its fecal elimination. Serial serum electrolyte determinations (especially calcium), rate of urinary calcium excretion, and assessment of electrocardiographic abnormalities due to hypercalcemia should be obtained. Such monitoring is critical in patients receiving digitalis.
Discontinuation of supplemental calcium and institution of a low-calcium diet are also indicated in accidental overdosage. Due to the relatively short duration of the pharmacological action of paricalcitol, further measures are probably unnecessary. If persistent and markedly elevated serum calcium levels occur, there are a variety of therapeutic alternatives that may be considered depending on the patient's underlying condition.
These include the use of drugs such as phosphates and corticosteroids, as well as measures to induce an appropriate forced diuresis. Paricalcitol is not significantly removed by dialysis.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY Secondary hyperparathyroidism is characterized by an elevation in parathyroid hormone (PTH) associated with inadequate levels of active vitamin D hormone. The source of vitamin D in the body is from synthesis in the skin as vitamin D 3 and from dietary intake as either vitamin D 2 or D 3 . Both vitamin D 2 and D 3 require two sequential hydroxylations in the liver and the kidney to bind to and to activate the vitamin D receptor (VDR).
The endogenous VDR activator, calcitriol [1,25(OH) 2 D 3 ], is a hormone that binds to VDRs that are present in the parathyroid gland, intestine, kidney, and bone to maintain parathyroid function and calcium and phosphorus homeostasis, and to VDRs found in many other tissues, including prostate, endothelium and immune cells. VDR activation is essential for the proper formation and maintenance of normal bone. In the diseased kidney, the activation of vitamin D is diminished, resulting in a rise of PTH, subsequently leading to secondary hyperparathyroidism and disturbances in the calcium and phosphorus homeostasis.
Decreased levels of 1,25(OH) 2 D 3 have been observed in early stages of chronic kidney disease. The decreased levels of 1,25(OH) 2 D 3 and resultant elevated PTH levels, both of which often precede abnormalities in serum calcium and phosphorus, affect bone turnover rate and may result in renal osteodystrophy.
12.1Mechanism of Action Paricalcitol is a synthetic, biologically active vitamin D 2 analog of calcitriol. Preclinical and in vitro studies have demonstrated that paricalcitol's biological actions are mediated through binding of the VDR, which results in the selective activation of vitamin D responsive pathways. Vitamin D and paricalcitol have been shown to reduce parathyroid hormone levels by inhibiting PTH synthesis and secretion.
12.2Pharmacodynamics Paricalcitol decreases serum intact parathyroid hormone (iPTH) and increases serum calcium and serum phosphorous in both HD and PD patients. This observed relationship was quantified using a mathematical model for HD and PD patient populations separately. Computer-based simulations of 100 trials in HD or PD patients (N = 100) using these relationships predict slightly lower efficacy (at least two consecutive ≥ 30% reductions from baseline iPTH) with lower hypercalcemia rates (at least two consecutive serum calcium ≥ 10.5 mg/dL) for lower iPTH-based dosing regimens.
Further lowering of hypercalcemia rates was predicted if the treatment with paricalcitol is initiated in patients with lower serum calcium levels at screening. Based on these simulations, a dosing regimen of iPTH/80 with a screening serum calcium ≤ 9.5 mg/dL, approximately 76.5% (95% CI: 75.6% to 77.3%) of HD patients are predicted to achieve at least two consecutive weekly ≥ 30% reductions from baseline iPTH over a duration of 12 weeks. The predicted incidence of hypercalcemia is 0.8% (95% CI: 0.7% to 1%).
In PD patients, with this dosing regimen, approximately 83.3% (95% CI: 82.6% to 84%) of patients are predicted to achieve at least two consecutive weekly ≥ 30% reductions from baseline iPTH. The predicted incidence of hypercalcemia is 12.4% (95% CI: 11.7% to 13%) [see Clinical Studies (14.2) and Dosage and Administration (2.2) ] .
12.3Pharmacokinetics Absorption The mean absolute bioavailability of paricalcitol capsules under low-fat fed condition ranged from 72% to 86% in healthy adult volunteers, CKD Stage 5 patients on HD, and CKD Stage 5 patients on PD. A food effect study in healthy adult volunteers indicated that the C max and AUC 0-∞ were unchanged when paricalcitol was administered with a high fat meal compared to fasting. Food delayed T max by about 2 hours.
The AUC 0-∞ of paricalcitol increased proportionally over the dose range of 0.06 to 0.48 mcg/kg in healthy adult volunteers. Distribution Paricalcitol is extensively bound to plasma proteins (≥ 99.8%). The mean apparent volume of distribution following a 0.24 mcg/kg dose of pari… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Paricalcitol is a synthetic, biologically active vitamin D 2 analog of calcitriol. Preclinical and in vitro studies have demonstrated that paricalcitol's biological actions are mediated through binding of the VDR, which results in the selective activation of vitamin D responsive pathways. Vitamin D and paricalcitol have been shown to reduce parathyroid hormone levels by inhibiting PTH synthesis and secretion.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Paricalcitol capsules are available as 1 mcg, 2 mcg, and 4 mcg capsules. Paricalcitol Capsules USP, 1 mcg are gray colored opaque, oval shaped soft gelatin capsule imprinted as “1” with black edible ink containing clear colorless to pale yellow colored oily liquid. Bottles of 30 NDC 65862-936-30 Paricalcitol Capsules USP, 2 mcg are orange brown colored opaque, oval shaped soft gelatin capsule imprinted as “P2” with black edible ink containing clear colorless to pale yellow colored oily liquid.
Bottles of 30 NDC 65862-937-30 Paricalcitol Capsules USP, 4 mcg are gold colored opaque, oval shaped soft gelatin capsule imprinted as “P4” with black edible ink containing clear colorless to pale yellow colored oily liquid. Bottles of 30 NDC 65862-938-30 Storage Store paricalcitol capsules, USP at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
📋 Description ▾
11 DESCRIPTION Paricalcitol, USP, the active ingredient in paricalcitol capsules, USP is a synthetically manufactured, metabolically active vitamin D analog of calcitriol with modifications to the side chain (D 2 ) and the A (19-nor) ring. Paricalcitol is available as soft gelatin capsules for oral administration containing 1 microgram, 2 micrograms or 4 micrograms of paricalcitol USP. Each capsule contains alcohol (ethanol 96% v/v), butylated hydroxytoluene, gelatin, glycerin, medium chain triglycerides, and titanium dioxide.
In addition, 1 mcg capsules contain black iron oxide, 2 mcg capsules contain red iron oxide, and yellow iron oxide, and 4 mcg capsules contain yellow iron oxide. The medium chain triglycerides are fractionated from coconut oil or palm kernel oil. The capsules are imprinted with Opacode WB black which containing black iron oxide, hypromellose, and propylene glycol.
Paricalcitol USP is a white to almost white powder with the molecular formula of C 27 H 44 O 3 , which corresponds to a molecular weight of 416.64. Paricalcitol is chemically designated as 19-nor-1α,3β,25-trihydroxy-9,10-secoergosta-5(Z),7(E),22(E)-triene and has the following structural formula: Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise patients of the following: The most common adverse reactions with use of paricalcitol capsules include diarrhea, hypertension, nausea, nasopharyngitis, dizziness, and vomiting. Patients should adhere to instructions regarding diet and phosphorus restriction. Patients should contact a health care provider if they develop symptoms of elevated calcium, (e.g., feeling tired, difficulty thinking clearly, loss of appetite, nausea, vomiting, constipation, increased thirst, increased urination and weight loss).
Patients should return to the physician's office for routine monitoring. More frequent monitoring is necessary during the initiation of therapy, following dose changes or when potentially interacting medications are started or discontinued. Patients should inform their physician of all medications, including prescription and nonprescription drugs, supplements, and herbal preparations they are taking and any change to their medical condition.
Patients should also inform their physician that they are taking paricalcitol capsules if a new medication is prescribed. Breastfeeding is not recommended during treatment with paricalcitol capsules [see Use in Specific Populations (8.2) ] . Distributed by: Aurobindo Pharma USA, Inc.
279 Princeton-Hightstown Road East Windsor, NJ 08520 Manufactured by: Aurobindo Pharma Limited Hyderabad-500 032, India Revised: 12/2023
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Absorption The mean absolute bioavailability of paricalcitol capsules under low-fat fed condition ranged from 72% to 86% in healthy adult volunteers, CKD Stage 5 patients on HD, and CKD Stage 5 patients on PD. A food effect study in healthy adult volunteers indicated that the C max and AUC 0-∞ were unchanged when paricalcitol was administered with a high fat meal compared to fasting. Food delayed T max by about 2 hours.
The AUC 0-∞ of paricalcitol increased proportionally over the dose range of 0.06 to 0.48 mcg/kg in healthy adult volunteers. Distribution Paricalcitol is extensively bound to plasma proteins (≥ 99.8%). The mean apparent volume of distribution following a 0.24 mcg/kg dose of paricalcitol in healthy adult volunteers was 34 L.
The mean apparent volume of distribution following a 4 mcg dose of paricalcitol in CKD Stage 3 and a 3 mcg dose in CKD Stage 4 patients is between 44 and 46 L. Metabolism After oral administration of a 0.48 mcg/kg dose of 3 H-paricalcitol, parent drug was extensively metabolized, with only about 2% of the dose eliminated unchanged in the feces, and no parent drug was found in the urine. Several metabolites were detected in both the urine and feces.
Most of the systemic exposure was from the parent drug. Two minor metabolites, relative to paricalcitol, were detected in human plasma. One metabolite was identified as 24(R)-hydroxy paricalcitol, while the other metabolite was unidentified.
The 24(R)-hydroxy paricalcitol is less active than paricalcitol in an in vivo rat model of PTH suppression. In vitro data suggest that paricalcitol is metabolized by multiple hepatic and non-hepatic enzymes, including mitochondrial CYP24, as well as CYP3A4 and UGT1A4. The identified metabolites include the product of 24(R)-hydroxylation, 24,26- and 24,28-dihydroxylation and direct glucuronidation.
Elimination Paricalcitol is eliminated primarily via hepatobiliary excretion; approximately 70% of the radiolabeled dose is recovered in the feces and 18% is recovered in the urine. While the mean elimination half-life of paricalcitol is 4 to 6 hours in healthy adult volunteers, the mean elimination half-life of paricalcitol in CKD Stages 3, 4, and 5 (on HD and PD) patients ranged from 14 to 20 hours. Table 7.
Paricalcitol Capsule Pharmacokinetic Parameters (mean ± SD) in CKD Stages 3, 4, and 5 Adult Patients Pharmacokinetic Parameters (units) CKD Stage 3 n = 15* CKD Stage 4 n = 14* CKD Stage 5 HD** n = 14 CKD Stage 5 PD** n = 8 C max (ng/mL) 0.11 ± 0.04 0.06 ± 0.01 0.575 ± 0.17 0.413 ±
0.06AUC 0-∞ (ng . h/mL) 2.42 ± 0.61 2.13 ± 0.73 11.67 ± 3.23 13.41 ±
5.48CL/F (L/h) 1.77 ± 0.5 1.52 ± 0.36 1.82 ± 0.75 1.76 ±
0.77V/F (L) 43.7 ± 14.4 46.4 ± 12.4 38 ± 16.4 48.7 ± 15.6 t 1/2 16.8 ± 2.65 19.7 ± 7.2 13.9 ± 5.1 17.7 ±
9.6HD: hemodialysis; PD: peritoneal dialysis. * Four mcg paricalcitol capsules were given to CKD Stage 3 patients; three mcg paricalcitol capsules were given to CKD Stage 4 patients. ** CKD Stage 5 HD and PD patients received a 0.24 mcg/kg dose of paricalcitol as capsules. Specific Populations Geriatric The pharmacokinetics of paricalcitol has not been investigated in geriatric patients greater than 65 years [see Use in Specific Populations (8.5) ]. Pediatric Paricalcitol C max, AUC, and t 1/2 values were similar between Stage 3 and Stage 4 CKD pediatric patients 10 to 16 years of age.
Population pharmacokinetic analysis shows that the pharmacokinetics of paricalcitol in Stage 5 CKD pediatric patients appear to be similar to those observed in Stage 3 and Stage 4 pediatric patients. Table 8. Paricalcitol Capsules Pharmacokinetic Parameters (mean ± SD) in CKD Stages 3 and 4 Patients 10 to 16 Years of Age Pharmacokinetic Parameter (units) CKD Stage 3 n = 6 CKD Stage 4 N = 5 C max (ng/mL) 0.12 ± 0.06 0.13 ±
0.05AUC ∞ (ng•h/mL) 2.63 ± 0.76 3.2 ±
0.99CL/F (L/h) 1.23 ± 0.38 1.02 ±
0.35V/F (L) 27.78 ± 18.60 24.36 ± 5.92 t 1/2 (h) 15.0 ± 6.1 17.5 ± 5.9 * Three 1 mcg paricalcitol capsules… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Paricalcitol decreases serum intact parathyroid hormone (iPTH) and increases serum calcium and serum phosphorous in both HD and PD patients. This observed relationship was quantified using a mathematical model for HD and PD patient populations separately. Computer-based simulations of 100 trials in HD or PD patients (N = 100) using these relationships predict slightly lower efficacy (at least two consecutive ≥ 30% reductions from baseline iPTH) with lower hypercalcemia rates (at least two consecutive serum calcium ≥ 10.5 mg/dL) for lower iPTH-based dosing regimens.
Further lowering of hypercalcemia rates was predicted if the treatment with paricalcitol is initiated in patients with lower serum calcium levels at screening. Based on these simulations, a dosing regimen of iPTH/80 with a screening serum calcium ≤ 9.5 mg/dL, approximately 76.5% (95% CI: 75.6% to 77.3%) of HD patients are predicted to achieve at least two consecutive weekly ≥ 30% reductions from baseline iPTH over a duration of 12 weeks. The predicted incidence of hypercalcemia is 0.8% (95% CI: 0.7% to 1%).
In PD patients, with this dosing regimen, approximately 83.3% (95% CI: 82.6% to 84%) of patients are predicted to achieve at least two consecutive weekly ≥ 30% reductions from baseline iPTH. The predicted incidence of hypercalcemia is 12.4% (95% CI: 11.7% to 13%) [see Clinical Studies (14.2) and Dosage and Administration (2.2) ] .
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Chronic Kidney Disease Stages 3 and 4 Adults The safety and efficacy of paricalcitol capsules were evaluated in three, 24-week, double blind, placebo-controlled, randomized, multicenter, Phase 3 clinical studies in CKD Stages 3 and 4 patients. Two studies used an identical three times a week dosing design, and one study used a daily dosing design. A total of 107 patients received paricalcitol capsules and 113 patients received placebo.
The mean age of the patients was 63 years, 68% were male, 71% were Caucasian, and 26% were African-American. The average baseline iPTH was 274 pg/mL (range: 145 to 856 pg/mL). The average duration of CKD prior to study entry was 5.7 years.
At study entry 22% were receiving calcium based phosphate binders and/or calcium supplements. Baseline 25-hydroxyvitamin D levels were not measured. The initial dose of paricalcitol capsules was based on baseline iPTH.
If iPTH was ≤ 500 pg/mL, paricalcitol capsules were administered 1 mcg daily or 2 mcg three times a week, not more than every other day. If iPTH was > 500 pg/mL, paricalcitol capsules were administered 2 mcg daily or 4 mcg three times a week, not more than every other day. The dose was increased by 1 mcg daily or 2 mcg three times a week every 2 to 4 weeks until iPTH levels were reduced by at least 30% from baseline.
The overall average weekly dose of paricalcitol capsules was 9.6 mcg/week in the daily regimen and 9.5 mcg/week in the three times a week regimen. In the clinical studies, doses were titrated for any of the following reasons: if iPTH fell to < 60 pg/mL, or decreased > 60% from baseline, the dose was reduced or temporarily withheld; if iPTH decreased < 30% from baseline and serum calcium was ≤ 10.3 mg/dL and serum phosphorus was ≤ 5.5 mg/dL, the dose was increased; and if iPTH decreased between 30 to 60% from baseline and serum calcium and phosphorus were ≤ 10.3 mg/dL and ≤ 5.5 mg/dL, respectively, the dose was maintained.
Additionally, if serum calcium was between 10.4 to 11 mg/dL, the dose was reduced irrespective of iPTH, and the dose was withheld if serum calcium was > 11 mg/dL. If serum phosphorus was > 5.5 mg/dL, dietary counseling was provided, and phosphate binders could have been initiated or increased. If the elevation persisted, the paricalcitol capsules dose was decreased.
Seventy-seven percent (77%) of the paricalcitol capsules treated patients and 82% of the placebo treated patients completed the 24-week treatment. The primary efficacy endpoint of at least two consecutive ≥ 30% reductions from baseline iPTH was achieved by 91% of paricalcitol capsules treated patients and 13% of the placebo treated patients (p < 0.001). The proportion of paricalcitol capsules treated patients achieving two consecutive ≥ 30% reductions was similar between the daily and the three times a week regimens (daily: 30/33, 91%; three times a week: 62/68, 91%).
The incidence of hypercalcemia (defined as two consecutive serum calcium values > 10.5 mg/dL), and hyperphosphatemia in paricalcitol capsules treated patients was similar to placebo. There were no treatment related adverse events associated with hypercalcemia or hyperphosphatemia in the paricalcitol capsules group. No increases in urinary calcium or phosphorous were detected in paricalcitol capsules treated patients compared to placebo.
The pattern of change in the mean values for serum iPTH during the studies is shown in Figure 1. The mean changes from baseline to final treatment visit in serum iPTH, calcium, phosphorus, and bone-specific alkaline phosphatase are shown in Table 9. Table 9.
Mean Changes from Baseline to Final Treatment Visit in Serum iPTH, Bone Specific Alkaline Phosphatase, Calcium, Phosphorus, and Calcium x Phosphorus Product in Three Combined Double-Blind, Placebo-Controlled, Phase 3, CKD Stages 3 and 4 Studies Paricalcitol Capsules Placebo iPTH (pg/mL) n = 104 n = 110 Mean Baseline Value 266 279 Mean Final Treatment Value 162 315 Mean Change fr… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 104-week carcinogenicity study in CD-1 mice, an increased incidence of uterine leiomyoma and leiomyosarcoma was observed at subcutaneous doses of 1, 3, 10 mcg/kg given three times weekly (2 to 15 times the AUC at a human dose of 14 mcg, equivalent to 0.24 mcg/kg based on AUC). The incidence rate of uterine leiomyoma was significantly different than the control group at the highest dose of 10 mcg/kg. In a 104-week carcinogenicity study in rats, there was an increased incidence of benign adrenal pheochromocytoma at subcutaneous doses of 0.15, 0.5, 1.5 mcg/kg (< 1 to 7 times the exposure following a human dose of 14 mcg, equivalent to 0.24 mcg/kg based on AUC).
The increased incidence of pheochromocytomas in rats may be related to the alteration of calcium homeostasis by paricalcitol. Paricalcitol did not exhibit genetic toxicity in vitro with or without metabolic activation in the microbial mutagenesis assay (Ames Assay), mouse lymphoma mutagenesis assay (L5178Y), or a human lymphocyte cell chromosomal aberration assay. There was also no evidence of genetic toxicity in an in vivo mouse micronucleus assay.
Paricalcitol had no effect on fertility (male or female) in rats at intravenous doses up to 20 mcg/kg/dose (equivalent to 13 times a human dose of 14 mcg based on surface area, mcg/m 2 ).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a 104-week carcinogenicity study in CD-1 mice, an increased incidence of uterine leiomyoma and leiomyosarcoma was observed at subcutaneous doses of 1, 3, 10 mcg/kg given three times weekly (2 to 15 times the AUC at a human dose of 14 mcg, equivalent to 0.24 mcg/kg based on AUC). The incidence rate of uterine leiomyoma was significantly different than the control group at the highest dose of 10 mcg/kg. In a 104-week carcinogenicity study in rats, there was an increased incidence of benign adrenal pheochromocytoma at subcutaneous doses of 0.15, 0.5, 1.5 mcg/kg (< 1 to 7 times the exposure following a human dose of 14 mcg, equivalent to 0.24 mcg/kg based on AUC).
The increased incidence of pheochromocytomas in rats may be related to the alteration of calcium homeostasis by paricalcitol. Paricalcitol did not exhibit genetic toxicity in vitro with or without metabolic activation in the microbial mutagenesis assay (Ames Assay), mouse lymphoma mutagenesis assay (L5178Y), or a human lymphocyte cell chromosomal aberration assay. There was also no evidence of genetic toxicity in an in vivo mouse micronucleus assay.
Paricalcitol had no effect on fertility (male or female) in rats at intravenous doses up to 20 mcg/kg/dose (equivalent to 13 times a human dose of 14 mcg based on surface area, mcg/m 2 ).
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1 mcg (30 Capsules Bottle) NDC 65862-936-30 Rx only Paricalcitol Capsules, USP 1 mcg AUROBINDO 30 Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 1 mcg (30 Capsules Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2 mcg (30 Capsules Bottle) NDC 65862-937-30 Rx only Paricalcitol Capsules, USP 2 mcg AUROBINDO 30 Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 2 mcg (30 Capsules Bottle)
PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4 mcg (30 Capsules Bottle) NDC 65862-938-30 Rx only Paricalcitol Capsules, USP 4 mcg AUROBINDO 30 Capsules PACKAGE LABEL-PRINCIPAL DISPLAY PANEL - 4 mcg (30 Capsules Bottle)
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What "drug for further processing" means
FDA lists this package under the "drug for further processing" marketing category: Aurobindo Pharma Limited supplies it to other companies for further processing or repackaging (blister cards that are later repackaged or co-packaged are a common example). The units themselves are a finished dosage form — which is why pricing or Medicaid data can still appear — but this exact package code may not be the presentation a retail pharmacy dispenses.
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | ✓ Available |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |