
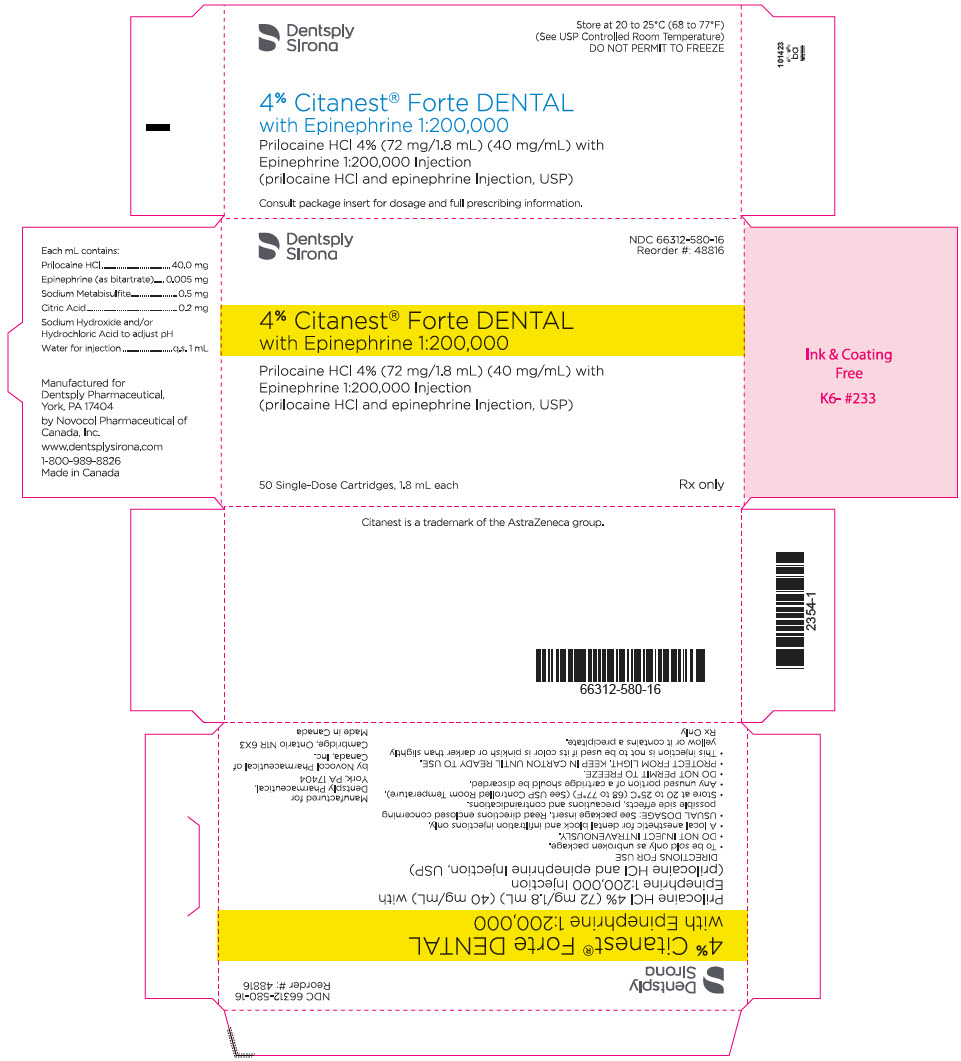
Citanest Forte DENTAL prilocaine hcl and epinephrine 40 mg/mL; .005 mg/mL Injection, Solution, 50 cartridges
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the alpha-Adrenergic Agonist class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
0.2 mg / 1 mL
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
0.5 mg / 1 mL
UNII 4VON5FNS3C
Sodium metabisulfite is a preservative derived from sulfur compounds. It prevents microbial growth and oxidation in medicines, helping extend shelf life and maintain product stability.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Citanest Forte DENTAL 40 mg/mL; .005 mg/mL 51004-5801-06 | Novocol | 50 cartridges | — | AP | FDA listed | — |
| Citanest Forte DENTAL 40 mg/mL; .005 mg/mLthis 66312-0580-16 | Dentsply | 50 cartridges | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 66312-0580-16 You're viewing this | 50 CARTRIDGE in 1 CARTON (66312-580-16) / 1.8 mL in 1 CARTRIDGE | 2017-12-04 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Citanest Forte is indicated for the production of local anesthesia in dentistry by nerve block or infiltration techniques. Only accepted procedures for these techniques as described in standard textbooks are recommended.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The dosage of Citanest Forte varies and depends on the physical status of the patient, the area of the oral cavity to be anesthetized, the vascularity of the oral tissues, and the technique of anesthesia. The least volume of injection that results in effective local anesthesia should be administered. For specific techniques and procedures of local anesthesia in the oral cavity, refer to standard textbooks.
Inferior Alveolar Block There are no practical clinical differences between prilocaine with and without epinephrine when used for inferior alveolar blocks. Maxillary Infiltration 4% Citanest Plain (without epinephrine) is recommended for use in maxillary infiltration anesthesia for procedures in which the painful aspects can be completed within 15 minutes after the injection. 4% Citanest Plain is therefore especially suited to short procedures in the maxillary anterior teeth.
For long procedures, or those involving maxillary posterior teeth where soft tissue numbness is not troublesome to the patient, Citanest Forte is recommended. For most routine procedures, initial dosages of 1 to 2 mL of Citanest Forte will usually provide adequate infiltration or major nerve block anesthesia. The maximum recommended dose that should ever be administered within a two hour period in normal healthy adults should be calculated based upon the patient's weight as follows: Weight Maximum recommended dose <150 lb (<70 kg) 4 mg/lb (8mg/kg) ≥ 150 lb (≥ 70 kg) 600 mg (15 mL) or 8 cartridges In children under 10 years of age it is rarely necessary to administer more than one-half cartridge (40 mg) of Citanest Forte per procedure to achieve local anesthesia for a procedure involving a single tooth.
In maxillary infiltration, this amount will often suffice to the treatment of two or even three teeth. In the mandibular block, however, satisfactory anesthesia achieved with this amount of drug will allow treatment of the teeth in an entire quadrant. ASPIRATION PRIOR TO INJECTION IS RECOMMENDED, since it reduces the possibility of intravascular injection, thereby keeping the incidence of side effects and anesthetic failure to a minimum.
NOTE: Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration whenever the solution and container permit. Solutions that are discolored and/or contain particulate matter should not be used. Any unused portion of a cartridge should be discarded.
Maximum Recommended Dosages In patients weighing <150 lb (70 kg), no more than 4 mg/lb (8 mg/kg) should be administered. In patients weighing ≥150 lb, no more than 600 mg (8 cartridges) of prilocaine HCl should be administered as a single injection. Children It is difficult to recommend a maximum dose of any drug for children since this varies as a function of age and weight.
For children of less than ten years who have a normal lean body mass and normal body development, the maximum dose may be determined by the application of one of the standard pediatric drug formulas (e.g., Clark's rule). For example, in a child of five years weighing 50 lb, the dose of prilocaine HCl should not exceed 150 to 200 mg (6.6 to 8.8 mg/kg or 3 to 4 mg/lb of body weight) when calculated according to Clark's rule.
⛔ Contraindications ▾
CONTRAINDICATIONS Prilocaine is contraindicated in patients with a known history of hypersensitivity to local anesthetics of the amide type and in those rare patients with congenital or idiopathic methemoglobinemia.
⚠️ Warnings ▾
WARNINGS DENTAL PRACTITIONERS WHO EMPLOY LOCAL ANESTHETIC AGENTS SHOULD BE WELL VERSED IN DIAGNOSIS AND MANAGEMENT OF EMERGENCIES THAT MAY ARISE FROM THEIR USE. RESUSCITATIVE EQUIPMENT, OXYGEN AND OTHER RESUSCITATIVE DRUGS SHOULD BE AVAILABLE FOR IMMEDIATE USE. Methemoglobinemia Cases of methemoglobinemia have been reported in association with local anesthetic use.
Although all patients are at risk for methemoglobinemia, patients with glucose-6-phosphate dehydrogenase deficiency, congenital or idiopathic methemoglobinemia, cardiac or pulmonary compromise, infants under 6 months of age, and concurrent exposure to oxidizing agents or their metabolites are more susceptible to developing clinical manifestations of the condition. If local anesthetics must be used in these patients, close monitoring for symptoms and signs of methemoglobinemia is recommended. Signs of methemoglobinemia may occur immediately or may be delayed some hours after exposure, and are characterized by a cyanotic skin discoloration and/or abnormal coloration of the blood.
Methemoglobin levels may continue to rise; therefore, immediate treatment is required to avert more serious central nervous system and cardiovascular adverse effects, including seizures, coma, arrhythmias, and death. Discontinue CITANEST FORTE and any other oxidizing agents. Depending on the severity of the signs and symptoms, patients may respond to supportive care, i.e., oxygen therapy, hydration.
A more severe clinical presentation may require treatment with methylene blue exchange transfusion, or hyperbaric oxygen. To minimize the likelihood of intravascular injection, aspiration should be performed before the local anesthetic solution is injected. If blood is aspirated, the needle must be repositioned until no return of blood can be elicited by aspiration.
Note, however, that the absence of blood in the syringe does not assure that intravascular injection will be avoided. Citanest Forte contains sodium metabisulfite, a sulfite that may cause allergic-type reactions including anaphylactic symptoms and life-threatening or less severe asthmatic episodes in certain susceptible people. The overall prevalence of sulfite sensitivity in the general population is unknown and probably low.
Sulfite sensitivity is seen more frequently in asthmatic than non-asthmatic people.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Swelling and persistent paresthesia of the lips and oral tissues may occur. Persistent paresthesia lasting weeks to months, and in rare instances paresthesia lasting greater than one year have been reported. Adverse experiences following the administration of prilocaine are similar in nature to those observed with other amide local anesthetic agents.
These adverse experiences are, in general, dose-related and may result from high plasma levels caused by excessive dosage, rapid absorption or unintentional intravascular injection, or may result from a hypersensitivity, idiosyncrasy or diminished tolerance on the part of the patient. Serious adverse experiences are generally systemic in nature. The following types are those most commonly reported: Central Nervous System CNS manifestations are excitatory and/or depressant and may be characterized by lightheadedness, nervousness, apprehension, euphoria, confusion, dizziness, drowsiness, tinnitus, blurred or double vision, vomiting, sensations of heat, cold or numbness, twitching, tremors, convulsions, unconsciousness, respiratory depression, and arrest.
The excitatory manifestations may be very brief or may not occur at all, in which case the first manifestation of toxicity may be drowsiness merging into unconsciousness and respiratory arrest. Drowsiness following the administration of prilocaine is usually an early sign of a high blood level of the drug and may occur as a consequence of rapid absorption. Cardiovascular System Cardiovascular manifestations are usually depressant and are characterized by bradycardia, hypotension, and cardiovascular collapse, which may lead to cardiac arrest.
Signs and symptoms of depressed cardiovascular function may commonly result from a vasovagal reaction, particularly if the patient is in an upright position. Less commonly, they may result from a direct effect of the drug. Failure to recognize the premonitory signs such as sweating, a feeling of faintness, and changes in pulse or sensorium may result in progressive cerebral hypoxia and seizure or serious cardiovascular catastrophe.
Management consists of placing the patient in the recumbent position and ventilation with oxygen. Supportive treatment of circulatory depression may require the administration of intravenous fluids, and, when appropriate, a vasopressor (e.g., ephedrine) as directed by the clinical situation. Allergic Allergic reactions are characterized by cutaneous lesions, urticaria, edema or anaphylactoid reactions.
Allergic reactions as a result of sensitivity to prilocaine are extremely rare and, if they occur, should be managed by conventional means. The detection of sensitivity by skin testing is of doubtful value. Neurologic The incidences of adverse reactions (e.g., persistent neurologic deficit) associated with the use of local anesthetics may be related to the technique employed, the total dose of local anesthetic administered, the particular drug used, the route of administration, and the physical condition of the patient.
🔄 Drug Interactions ▾
Clinically Significant Drug Interactions Patients who are administered local anesthetics are at increased risk of developing methemoglobinemia when concurrently exposed to the following drugs, which could include other local anesthetics: EXAMPLES OF DRUGS ASSOCIATED WITH METHEMOGLOBINEMIA: Class Examples Nitrates/Nitrites nitric oxide, nitroglycerin, nitroprusside, nitrous oxide Local anesthetics articaine, benzocaine, bupivacaine, lidocaine, mepivacaine, prilocaine, procaine, ropivacaine, tetracaine Antineoplastic Agents cyclophosphamide, flutamide, hydroxyurea, ifosfamide, rasburicase Antibiotics dapsone, nitrofurantoin, para-aminosalicylic acid, sulfonamides Antimalarials chloroquine, primaquine Anticonvulsants phenobarbital, phenytoin, sodium valproate Other drugs acetaminophen, metoclopramide, quinine, sulfasalazine The administration of local anesthetic injections containing epinephrine or norepinephrine to patients receiving monoamine oxidase inhibitors, tricyclic antidepressants or phenothiazines may produce severe, prolonged hypotension or hypertension.
Concurrent use of these agents should generally be avoided. In situations when concurrent therapy is necessary, careful patient monitoring is essential. Concurrent administration of vasopressor drugs and ergot-type oxytocic drugs may cause severe, persistent hypertension or cerebrovascular accidents.
🔄 Drug / Laboratory Test Interactions ▾
Drug/Laboratory Test Interactions The intramuscular injection of prilocaine may result in an increase in creatine phosphokinase levels. Thus, the use of this enzyme determination, without isoenzyme separation, as a diagnostic test for the presence of acute myocardial infarction may be compromised by the intramuscular injection of prilocaine.
🤰 Pregnancy ▾
Use in Pregnancy Teratogenic Effects Pregnancy Category B Reproduction studies have been performed in rats at doses up to 30 times the human dose and revealed no evidence of impaired fertility or harm to the fetus due to prilocaine. There are, however, no adequate and well-controlled studies in pregnant women. Animal reproduction studies are not always predictive of human response.
General consideration should be given to this fact before administering prilocaine to women of childbearing potential, especially during early pregnancy when maximum organogenesis takes place.
🧒 Pediatric Use ▾
Pediatric Use Dosages in children should be reduced, commensurate with age, body weight, and physical condition. (See DOSAGE AND ADMINISTRATION .)
🆘 Overdosage ▾
OVERDOSAGE Acute emergencies from local anesthetics are generally related to high plasma levels encountered during therapeutic use of local anesthetics (see ADVERSE REACTIONS , WARNINGS , and PRECAUTIONS ). Management of Local Anesthetic Emergencies The first consideration is prevention, best accomplished by careful and constant monitoring of cardiovascular and respiratory vital signs and the patient's state of consciousness after each local anesthetic injection. At the first sign of change, oxygen should be administered.
The first step in the management of convulsions consists of immediate attention to the maintenance of a patent airway and assisted or controlled ventilation with oxygen and a delivery system capable of permitting immediate positive airway pressure by mask. Immediately after the institution of these ventilatory measures, the adequacy of the circulation should be evaluated, keeping in mind that drugs used to treat convulsions sometimes depress the circulation when administered intravenously. Should convulsions persist despite adequate respiratory support, and if the status of the circulation permits, small increments of an ultra-short acting barbiturate (such as thiopental or thiamylal) or a benzodiazepine (such as diazepam) may be administered intravenously.
The clinician should be familiar, prior to use of local anesthetics, with these anticonvulsant drugs. Supportive treatment of circulatory depression may require administration of intravenous fluids and, when appropriate, a vasopressor as directed by the clinical situation (e.g., ephedrine). If not treated immediately, both convulsions and cardiovascular depression can result in hypoxia, acidosis, bradycardia, arrhythmias and cardiac arrest.
If cardiac arrest should occur, standard cardiopulmonary resuscitative measures should be instituted. Endotracheal intubation, employing drugs and techniques familiar to the clinician, may be indicated, after initial administration of oxygen by mask, if difficulty is encountered in the maintenance of a patent airway or if prolonged ventilatory support (assisted or controlled) is indicated. Dialysis is of negligible value in the treatment of acute overdosage with prilocaine.
The development of methemoglobinemia is generally dose related but may occur at any dose in susceptible individuals. While methemoglobin values of less than 20% do not generally produce any clinical symptoms, the appearance of cyanosis at 2 to 4 hours following administration should be evaluated in terms of the general health status of the patient. Methemoglobinemia can be reversed when indicated by intravenous administration of methylene blue at a dosage of 1 to 2 mg/kg given over a five minute period.
The subcutaneous LD 50 of prilocaine HCl in female mice is 550 (359 to 905) mg/kg.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Prilocaine stabilizes the neuronal membrane by inhibiting the ionic fluxes required for the initiation and conduction of impulses, thereby effecting local anesthetic action. Onset and Duration of Action When used for infiltration injection in dental patients, the time of onset of anesthesia averages less than 2 minutes with an average duration of soft tissue anesthesia of approximately 2¼ hours. When used for inferior alveolar nerve block, the time of onset averages less than three minutes with an average duration of soft tissue anesthesia of approximately 3 hours.
Hemodynamics Excessive blood levels may cause changes in cardiac output, total peripheral resistance, and mean arterial pressure. These changes may be attributable to a direct depressant effect of the local anesthetic agent on various components of the cardiovascular system and/or the beta-adrenergic receptor stimulating action of epinephrine. Pharmacokinetics and Metabolism Information derived from diverse formulations, concentrations and usages reveals that prilocaine is completely absorbed following parenteral administration, its rate of absorption depending, for example, upon such factors as the site of administration and the presence or absence of a vasoconstrictor agent.
Prilocaine is metabolized in both the liver and the kidney and excreted via the kidney. It is not metabolized by plasma esterases. Hydrolysis of prilocaine by amidases yields ortho-toluidine and n-proylalanine.
Both of these compounds may undergo ring hydroxylation. O-toluidine has been found to produce methemoglobin, both in vitro and in vivo (see ADVERSE REACTIONS ). Because prilocaine is metabolized in both the liver and kidneys, hepatic and renal dysfunction may alter prilocaine kinetics.
As with other local anesthetic agents, the plasma binding of prilocaine may be dependent on drug concentration. At 0.5 to 1.0 mg/mL it is 55% protein bound. Prilocaine crosses the blood-brain and placental barriers, presumably by passive diffusion.
Factors such as acidosis and the use of CNS stimulants and depressants affect the CNS levels of prilocaine required to produce overt systemic effects. In the rhesus monkey, arterial blood levels of 20 mg/mL have been shown to be the threshold for convulsive activity.
🧬 Mechanism of Action ▾
Mechanism of Action Prilocaine stabilizes the neuronal membrane by inhibiting the ionic fluxes required for the initiation and conduction of impulses, thereby effecting local anesthetic action.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Citanest Forte (NDC 66312-580-16) is dispensed in 1.8 mL single-dose cartridges, packed 50 per box. Sterilization, Storage and Technical Procedures: Cartridges should not be autoclaved, because solutions of epinephrine and the closures employed in cartridges cannot withstand autoclaving temperatures and pressures. If chemical disinfection of anesthetic cartridges is desired, either 91% isopropyl alcohol or 70% ethyl alcohol is recommended.
Many commercially available brands of rubbing alcohol, as well as solutions of ethyl alcohol not of U.S.P. grade, contain denaturants that are injurious to rubber and, therefore, are not to be used. It is recommended that chemical disinfection be accomplished by wiping the cartridge cap thoroughly with a pledget of cotton that has been moistened with the recommended alcohol just prior to use. IMMERSION IS NOT RECOMMENDED.
Certain metallic ions (mercury, zinc, copper, etc.) have been related to swelling and edema after local anesthesia in dentistry. Therefore, chemical disinfectants containing or releasing those ions are not recommended. Antirust tablets usually contain metal ions.
Accordingly, aluminum sealed cartridges should not be kept in such solutions. Quaternary ammonium salts, such as benzalkonium chloride, are electrolytically incompatible with aluminum. Cartridges are sealed with aluminum caps and therefore should not be immersed in any solution containing these salts.
To avoid leakage of solutions during injection, be sure to penetrate the center of the rubber diaphragm when loading the syringe. An off-center penetration produces an oval shaped puncture that allows leakage around the needle. Other causes of leakage and breakage include badly worn syringes, aspirating syringes with bent harpoons, the use of syringes not designed to take 1.8 mL cartridges, and inadvertent freezing.
Cracking of glass cartridges is most often the result of an attempt to use a cartridge with an extruded plunger. An extruded plunger loses its lubrication and can be forced back into the cartridge only with difficulty. Cartridges with extruded plungers should be discarded.
Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Solutions containing epinephrine should be protected from light.
📦 Storage and Handling ▾
Sterilization, Storage and Technical Procedures: Cartridges should not be autoclaved, because solutions of epinephrine and the closures employed in cartridges cannot withstand autoclaving temperatures and pressures. If chemical disinfection of anesthetic cartridges is desired, either 91% isopropyl alcohol or 70% ethyl alcohol is recommended. Many commercially available brands of rubbing alcohol, as well as solutions of ethyl alcohol not of U.S.P. grade, contain denaturants that are injurious to rubber and, therefore, are not to be used.
It is recommended that chemical disinfection be accomplished by wiping the cartridge cap thoroughly with a pledget of cotton that has been moistened with the recommended alcohol just prior to use. IMMERSION IS NOT RECOMMENDED. Certain metallic ions (mercury, zinc, copper, etc.) have been related to swelling and edema after local anesthesia in dentistry.
Therefore, chemical disinfectants containing or releasing those ions are not recommended. Antirust tablets usually contain metal ions. Accordingly, aluminum sealed cartridges should not be kept in such solutions.
Quaternary ammonium salts, such as benzalkonium chloride, are electrolytically incompatible with aluminum. Cartridges are sealed with aluminum caps and therefore should not be immersed in any solution containing these salts. To avoid leakage of solutions during injection, be sure to penetrate the center of the rubber diaphragm when loading the syringe.
An off-center penetration produces an oval shaped puncture that allows leakage around the needle. Other causes of leakage and breakage include badly worn syringes, aspirating syringes with bent harpoons, the use of syringes not designed to take 1.8 mL cartridges, and inadvertent freezing. Cracking of glass cartridges is most often the result of an attempt to use a cartridge with an extruded plunger.
An extruded plunger loses its lubrication and can be forced back into the cartridge only with difficulty. Cartridges with extruded plungers should be discarded. Store at 20° to 25°C (68° to 77°F); excursions permitted between 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
Solutions containing epinephrine should be protected from light.
📋 Description ▾
DESCRIPTION 4% Citanest ® Forte DENTAL with Epinephrine 1:200,000 (Citanest Forte), Prilocaine HCl 4% (72 mg/1.8 mL) (40 mg/mL) with Epinephrine 1:200,000 Injection, is a sterile, non-pyrogenic isotonic solution that contains a local anesthetic agent with epinephrine (as bitartrate) and is administered parenterally by injection. See INDICATIONS AND USAGE for specific uses. The quantitative composition is shown in Table 1.
Citanest Forte contains prilocaine HCl, which is chemically designated as propanamide, N-(2-methyl-phenyl) -2- (propylamino)-, monohydrochloride and has the following structural formula: C 13 H 20 N 2 O ∙ HCl molecular wt = 256.77 and epinephrine, which is (-) -3, 4-Dihydroxy- ∝ -[(methylamino) methyl] benzyl alcohol and has the following structural formula: C 9 H 13 NO 3 molecular wt = 183.21 Parenteral drug products should be inspected visually for particulate matter and discoloration prior to administration. The specific quantitative composition is shown in Table 1.
Table 1. COMPOSITION Product Identification Formula (mg/mL) Prilocaine HCl Epinephrine (as bitartrate) Citric Acid Sodium Metabisulfite pH Note: Sodium hydroxide and/or hydrochloric acid may be used to adjust the pH of Citanest Forte. 4% Citanest ® Forte DENTAL with Epinephrine 1:200,000 (Prilocaine HCl 4% (72 mg/1.8 mL) (40 mg/mL) with Epinephrine 1:200,000 Injection) 40.0 0.005 0.2 0.5 3.3 to
5.5 Chemical Structure Chemical Structure
💬 Information for Patients ▾
Information for Patients Inform patients that use of local anesthetics may cause methemoglobinemia, a serious condition that must be treated promptly. Advise patients or caregivers to seek immediate medical attention if they or someone in their care experience the following signs or symptoms: pale, gray, or blue colored skin (cyanosis); headache; rapid heart rate; shortness of breath; lightheadedness; or fatigue. The patient should be informed of the possibility of temporary loss of sensation and muscle function following infiltration or nerve block injections.
The patient should be advised to exert caution to avoid inadvertent trauma to the lips, tongue, cheek mucosae or soft palate when these structures are anesthetized. The ingestion of food should therefore be postponed until normal function returns. The patient should be advised to consult the dentist if anesthesia persists, or if a rash develops.