
Orfadin Nitisinone 10 mg Capsule, 60-count — NDC 66658-110-60 (Billing 66658-0110-60)
This is a package of 60 capsules of Orfadin Nitisinone 10 mg Capsule from SWEDISH ORPHAN BIOVITRUM AB (PUBL), marketed since Jul 2016 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 66658-110-60 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 66658 labeler · 110 product · 60 package
- Package marketed since
- Jul 1, 2016
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 60 EA per package
- Barcode (UPC-A, from the NDC)
- 3 6665811060 8
- Medicaid fills, this package
- 31 prescriptions in the last four reported quarters
- FDA record last changed
- Oct 1, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 049855
- GCN: 15664
- GPI-14 (Medi-Span): 30904045000130
- HICL (First Databank): 023253
- AHFS class code: 44:08.00.00
- RxCUI (RxNorm): 351173
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the 4-Hydroxyphenyl-Pyruvate Dioxygenase Inhibitor class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Nitisinone is used to treat hereditary tyrosinemia type 1 (HT-1; rare genetic disorder where body cannot break down amino acid tyrosine causing build-up that can harm kidneys and liver) and reduction of urine homogentisic acid (HGA) in patients with alkaptonuria (AKU; rare genetic disorder where body can't breakdown aminoacids tyrosine and phenylalanine leading to builld up of HGA causing deposits in connective tissue causing severe arthritis symptoms). Nitisinone is in a class of medications called hydroxyphenyl-pyruvate dioxygenase inhibitors. It works by by helping the body eliminate the to...
Read the full MedlinePlus article ↗- Nitisinone works by blocking a step in the breakdown of tyrosine — an amino acid found in many protein-rich foods. This means tyrosine can build up in your blood while you're on th...
- Why do I have to follow a special diet while taking nitisinone?
- High tyrosine levels can irritate and damage the surface of your eyes. Call your doctor right away if you notice eye pain, increased sensitivity to light, redness, swelling, or any...
- What eye problems should I watch out for, and when should I call my doctor?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with nitisinone — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $272.64 | $16,358.27 / 60 capsules |
| Medicare drug plans payPart D · Q2 2026 | $267.76 | $16,065.57 / 60 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 66658-0110-60 You're viewing this Main listing | 1 BOTTLE, PLASTIC in 1 CARTON / 60 CAPSULE in 1 BOTTLE, PLASTIC | 2016-07-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nitisinone 10 mg 00254-3022-02 | Par | 60 capsules | — | AB | FDA listed | — |
| Nitisinone 10 mg 63629-2233-01 | Bryant | 60 capsules | — | AB | FDA listed | — |
| Orfadin 10 mgthis 66658-0110-60 | SWEDISH | 60 capsules | — | AB | FDA listed | — |
| Nitisinone 10 mg 70505-0210-60 | Analog | 60 capsules | — | AB | FDA listed | — |
| Nitisinone 10 mg 71863-0121-60 | Eton | 60 capsules | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Nitisinone inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from SWEDISH ORPHAN BIOVITRUM AB (PUBL) labeler code 66658
- Orfadin Nitisinone 2 mg Capsule NDC 66658-102-60
- Orfadin Nitisinone 5 mg Capsule NDC 66658-105-60
- KEPIVANCE palifermin 5.16 mg/1.2mL Injection, Powder, Lyophilized, For Solution NDC 66658-113-03
- Orfadin Nitisinone 20 mg Capsule NDC 66658-120-60
- ORFADIN nitisinone 4 mg/mL Suspension NDC 66658-204-90
- Synagis palivizumab 50 mg/.5mL Injection, Solution NDC 66658-230-01
- Synagis palivizumab 100 mg/mL Injection, Solution NDC 66658-231-01
- Kineret anakinra 100 mg/.67mL Injection, Solution NDC 66658-234-07
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ORFADIN ® is indicated for the treatment of adult and pediatric patients with hereditary tyrosinemia type 1 (HT-1) in combination with dietary restriction of tyrosine and phenylalanine. ORFADIN is a hydroxy-phenylpyruvate dioxygenase inhibitor indicated for the treatment of adult and pediatric patients with hereditary tyrosinemia type 1 (HT-1) in combination with dietary restriction of tyrosine and phenylalanine. ( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Recommended Dosage ( 2.1 ) : The recommended starting dosage is 0.5 mg/kg orally twice daily. In patients 5 years of age and older who have undetectable serum and urine succinylacetone concentrations after a minimum of 4 weeks on a stable dosage of nitisinone, the total daily dose may be given once daily. Titrate the dosage based on biochemical and/or clinical response, as described in the full prescribing information.
The maximum total daily dosage is 2 mg/kg orally. Preparation and Administration Instructions ( 2.2 ) : For instructions on preparing, measuring and administering the oral suspension, see the full prescribing information. Maintain dietary restriction of tyrosine and phenylalanine Take ORFADIN capsules at least one hour before, or two hours after a meal For patients who have difficulties swallowing capsules and who are intolerant to the oral suspension, the capsules may be opened and the contents suspended in a small amount of water, formula or apple sauce immediately before use.
Take ORFADIN oral suspension without regard to meals.
2.1Dosage Starting Dosage The recommended starting dosage of ORFADIN is 0.5 mg/kg administered orally twice daily. Maintenance Regimen In patients 5 years of age and older who have undetectable serum and urine succinylacetone concentrations after a minimum of 4 weeks on a stable dosage of nitisinone, the total daily dose of ORFADIN may be given once daily (e.g., 1 to 2 mg/kg once daily) [see Clinical Pharmacology ( 12.2 )] . Dosage Titration Titrate the dosage in each individual patient based on biochemical and/or clinical response.
Monitor plasma and/or urine succinylacetone concentrations, liver function parameters and alpha-fetoprotein levels. If succinylacetone is still detectable in blood or urine 4 weeks after the start of nitisinone treatment, increase the nitisinone dosage to 0.75 mg/kg twice daily. A maximum total daily dosage of 2 mg/kg may be needed based on the evaluation of all biochemical parameters.
If the biochemical response is satisfactory (undetectable blood and/or urine succinylacetone), the dosage should be adjusted only according to body weight gain and not according to plasma tyrosine levels. During initiation of therapy, when switching from twice daily to once daily dosing, or if there is a deterioration in the patient's condition, it may be necessary to follow all available biochemical parameters more closely (i.e. plasma and/or urine succinylacetone, urine 5-aminolevulinate (ALA) and erythrocyte porphobilinogen (PBG)-synthase activity).
Maintain plasma tyrosine levels below 500 micromol/L by dietary restriction of tyrosine and phenylalanine intake [see Warnings and Precautions ( 5.1 )] . In patients who develop plasma tyrosine levels above 500 micromol/L, assess dietary tyrosine and phenylalanine intake. Do not adjust the ORFADIN dosage in order to lower the plasma tyrosine concentration.
2.2Preparation and Administration Instructions Preparation of the Oral Suspension The oral suspension will be dispensed with an oral syringe of appropriate size and a bottle adaptor provided by a pharmacist or other healthcare provider. Preparing a Bottle Without the Adapter Already Inserted: Store the bottle in the refrigerator prior to first use. Remove the bottle from the refrigerator.
Calculate 60 days from when the bottle is removed from the refrigerator. Write this date as the “Discard after” date on the bottle label. Allow the bottle to warm to room temperature (30 to 60 minutes).
Shake the bottle vigorously for at least 20 seconds until the solid cake at the bottom of the bottle is completely dispersed. Check that there are no particles left at the bottom of the bottle. Foam will form in the bottle.
Insert the bottle adapter. Preparing a Bottle With the Adapter Inserted: Shake the bottle vigorously for at least 5 seconds. Check that there are no particles left at the bottom of the bottle.
Foam will form in the bottle. Measuring and Admin… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: 2 mg, 5 mg, 10 mg and 20 mg white capsules imprinted with “NTBC” followed by “2 mg”, “5 mg”, “10 mg” or ”20 mg”, indicating the actual amount of nitisinone in each capsule. Oral suspension: 4 mg/mL, a white, slightly viscous opaque suspension. Capsules: 2 mg, 5 mg, 10 mg, 20 mg. ( 3 ) Oral suspension: 4 mg/mL ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Elevated Plasma Tyrosine Levels, Ocular Symptoms, Developmental Delay and Hyperkeratotic Plaques : Inadequate restriction of tyrosine and phenylalanine intake can lead to elevations in plasma tyrosine, which at levels above 500 micromol/L can result in symptoms, intellectual disability and developmental delay or painful hyperkeratotic plaques on the soles and palms; do not adjust ORFADIN dosage in order to lower the plasma tyrosine concentration. Obtain slit-lamp examination prior to treatment, regularly during treatment; Reexamine patients if symptoms develop or tyrosine levels are > 500 micromol/L.
Assess plasma tyrosine levels in patients with an abrupt change in neurologic status. ( 5.1 ) Leukopenia and Severe Thrombocytopenia : Monitor platelet and white blood cell counts. ( 5.2 ) Risk of Adverse Reactions Due to Glycerol Content of ORFADIN Oral Suspension : Doses of 20 mL of ORFADIN oral suspension may cause headache, upset stomach and diarrhea due to the glycerol content.
Consider switching patients to ORFADIN capsules. ( 5.3 )
5.1Elevated Plasma Tyrosine Levels, Ocular Symptoms, Developmental Delay and Hyperkeratotic Plaques Nitisinone is an inhibitor of 4-hydroxyphenyl-pyruvate dioxygenase, an enzyme in the tyrosine metabolic pathway [see Clinical Pharmacology ( 12.1 )] . Therefore, treatment with ORFADIN may cause an increase in plasma tyrosine levels in patients with HT-1. Maintain concomitant reduction in dietary tyrosine and phenylalanine while on ORFADIN treatment.
Do not adjust ORFADIN dosage in order to lower the plasma tyrosine concentration. Maintain plasma tyrosine levels below 500 micromol/L. Inadequate restriction of tyrosine and phenylalanine intake can lead to elevations in plasma tyrosine levels and levels greater than 500 micromol/L may lead to the following: Ocular signs and symptoms including corneal ulcers, corneal opacities, keratitis, conjunctivitis, eye pain, and photophobia have been reported in patients treated with ORFADIN [see Adverse Reactions ( 6.1 )] .
In a clinical study in a non HT-1 population without dietary restriction and reported tyrosine levels >500 micromol/L both symptomatic and asymptomatic keratopathies have been observed. Therefore, perform a baseline ophthalmologic examination including slit-lamp examination prior to initiating ORFADIN treatment and regularly thereafter. Patients who develop photophobia, eye pain, or signs of inflammation such as redness, swelling, or burning of the eyes or tyrosine levels are > 500 micromol/L during treatment with ORFADIN should undergo slit-lamp reexamination and immediate measurement of the plasma tyrosine concentration.
Variable degrees of intellectual disability and developmental delay. In patients treated with ORFADIN who exhibit an abrupt change in neurologic status, perform a clinical laboratory assessment including plasma tyrosine levels. Painful hyperkeratotic plaques on the soles and palms In patients with HT-1 treated with dietary restrictions and ORFADIN who develop elevated plasma tyrosine levels, assess dietary tyrosine and phenylalanine intake.
5.2Leukopenia and Severe Thrombocytopenia In clinical trials, patients treated with ORFADIN and dietary restriction developed transient leukopenia (3%), thrombocytopenia (3%), or both (1.5%) [see Adverse Reactions ( 6.1 )] . No patients developed infections or bleeding as a result of the episodes of leukopenia and thrombocytopenia. Monitor platelet and white blood cell counts during ORFADIN therapy.
5.3Risk of Adverse Reactions Due to Glycerol Content of ORFADIN Oral Suspension Oral doses of glycerol of 10 grams or more have been reported to cause headache, upset stomach and diarrhea. ORFADIN oral suspension contains 500 mg/mL of glycerol. Patients receiving more than 20 mL of ORFADIN oral suspension (10 grams glycerol) as a single dose are at increased risk of these adverse reactions.
Consider switching patients who are unable to tolerate the oral suspensi… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions (>1%) are elevated tyrosine levels, thrombocytopenia, leukopenia, conjunctivitis, corneal opacity, keratitis, photophobia, eye pain, blepharitis, cataracts, granulocytopenia, epistaxis, pruritus, exfoliative dermatitis, dry skin, maculopapular rash and alopecia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Swedish Orphan Biovitrum at 1-866-773-5274 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. ORFADIN was studied in one open-label, uncontrolled study of 207 patients with HT-1, ages 0 to 22 years at enrollment (median age 9 months), who were diagnosed with HT-1 by the presence of succinylacetone in the urine or plasma.
The starting dose of ORFADIN was 0.3 to 0.5 mg/kg twice daily, and the dose was increased in some patients to 1 mg/kg twice daily based on weight, biochemical, and enzyme markers. The recommended starting dosage of ORFADIN is 0.5 mg/kg twice daily [see Dosage and Administration ( 2.1 )] . Median duration of treatment was 22 months (range 0.1 to 80 months).
The most serious adverse reactions reported during ORFADIN treatment were thrombocytopenia, leukopenia, porphyria, and ocular/visual complaints associated with elevated tyrosine levels [see Warnings and Precautions ( 5.1 , 5.2 )] . Fourteen patients experienced ocular/visual events. The duration of the symptoms varied from 5 days to 2 years.
Six patients had thrombocytopenia, three of which had platelet counts 30,000/microL or lower. In 4 patients with thrombocytopenia, platelet counts gradually returned to normal (duration up to 47 days) without change in ORFADIN dose. No patients developed infections or bleeding as a result of the episodes of leukopenia and thrombocytopenia.
Patients with HT- 1 are at increased risk of developing porphyric crises, hepatic neoplasms, and liver failure requiring liver transplantation. These complications of HT-1 were observed in patients treated with nitisinone for a median of 22 months during the clinical trial (liver transplantation 13%, liver failure 7%, malignant hepatic neoplasms 5%, benign hepatic neoplasms 3%, porphyria 1%). The most common adverse reactions reported in the clinical trial are summarized in Table 1 .
TABLE 1 *reported in at least 1% of patients Most Common Adverse Reactions in Patients with HT-1 Treated with Nitisinone* Elevated tyrosine levels Leukopenia Thrombocytopenia Conjunctivitis Corneal opacity Keratitis Photophobia Eye pain Blepharitis Cataracts Granulocytopenia Epistaxis Pruritus Exfoliative dermatitis Dry skin Maculopapular rash Alopecia >10% 3% 3% 2% 2% 2% 2% 1% 1% 1% 1% 1% 1% 1% 1% 1% 1% Adverse reactions reported in less than 1% of the patients, included death, seizure, brain tumor, encephalopathy, hyperkinesia, cyanosis, abdominal pain, diarrhea, enanthema, gastrointestinal hemorrhage, melena, elevated hepatic enzymes, liver enlargement, hypoglycemia, septicemia, and bronchitis.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Nitisinone is a moderate CYP2C9 inhibitor, a weak CYP2E1 inducer and an inhibitor of OAT1/OAT3. Table 2 includes drugs with clinically important drug interactions when administered concomitantly with ORFADIN and instructions for preventing or managing them. Table 2: Clinically Relevant Interactions Affecting Co-Administered Drugs Sensitive CYP2C9 Substrates (e.g., celecoxib, tolbutamide) or CYP2C9 Substrates with a Narrow Therapeutic Index (e.g., phenytoin, warfarin) Clinical Impact Increased exposure of the co-administered drugs metabolized by CYP2C9. [see Clinical Pharmacology ( 12.3 )] Intervention Reduce the dosage of the co-administered drugs metabolized by CYP2C9 drug by half.
Additional dosage adjustments may be needed to maintain therapeutic drug concentrations for narrow therapeutic index drugs. See prescribing information for those drugs. OAT1/OAT3 Substrates (e.g., adefovir, ganciclovir, methotrexate) Clinical Impact Increased exposure of the interacting drug [see Clinical Pharmacology ( 12.3 )] Intervention Monitor for potential adverse reactions related to the co-administered drug.
CYP2C9 Substrates : Increased systemic exposure of these co-administered drugs; reduce the dosage. Additional dosage adjustments may be needed to maintain therapeutic drug concentrations for narrow therapeutic index drugs. ( 7 ) OAT1/OAT3 Substrates : Increased systemic exposure of these co-administered drugs; monitor for potential adverse reactions.
( 7 )
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Limited available data with nitisinone use in pregnant women are not sufficient to determine a drug-associated risk of adverse developmental outcomes. Animal reproduction studies have been conducted for nitisinone. In these studies, nitisinone was administered to mice and rabbits during organogenesis with oral doses of nitisinone up to 20 and 8 times respectively, the recommended initial dose of 1 mg/kg/day.
In mice, nitisinone caused incomplete skeletal ossification of fetal bones and decreased pup survival at doses 0.4 times the recommended initial dose, and increased gestational length at doses 4 times the recommended initial dose. In rabbits, nitisinone caused maternal toxicity and incomplete skeletal ossification of fetal bones at doses 1.6 times the recommended initial dose [see Data ] . The background risk of major birth defects and miscarriage for the indicated population are unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproduction studies have been performed in mice at oral doses of about 0.4, 4 and 20 times the recommended initial dose (1 mg/kg/day) and in rabbits at oral doses of about 1.6, 4 and 8 times the recommended initial dose based on the body surface area. In mice, nitisinone has been shown to cause incomplete skeletal ossification of fetal bones at 0.4, 4 and 20 times the recommended initial dose, increased gestational length at 4 and 20 times the recommended initial dose, and decreased pup survival at 0.4 times the recommended initial dose based on the body surface area.
In rabbits, nitisinone caused incomplete skeletal ossification of fetal bones at 1.6, 4 and 8 times the recommended initial dose based on the body surface area.
8.2Lactation Risk Summary There are no data on the presence of nitisinone in human milk, the effects on the breastfed infant, or the effects on milk production. Data suggest that nitisinone is present in rat milk due to findings of ocular toxicity and lower body weight seen in drug naive nursing rat pups. The development and health benefits of breastfeeding should be considered along with the mother's clinical need for ORFADIN and any potential adverse effects on the breastfed infant from ORFADIN or from the underlying maternal condition.
8.4Pediatric Use The safety and effectiveness of ORFADIN have been established in pediatric patients for the treatment of HT-1 in combination with dietary restriction of tyrosine and phenylalanine. Use of ORFADIN in pediatric patients is supported by evidence from one open-label, uncontrolled clinical study conducted in 207 patients with HT-1 ages 0 to 22 years (median age 9 months) [see Clinical Studies ( 14 )] .
8.5Geriatric Use Clinical studies of nitisinone did not include any subjects aged 65 and over. No pharmacokinetic studies of nitisinone have been performed in geriatric patients. In general, dose selection for an elderly patient should be cautious reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and concomitant disease or other drug therapy in this patient population.
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data with nitisinone use in pregnant women are not sufficient to determine a drug-associated risk of adverse developmental outcomes. Animal reproduction studies have been conducted for nitisinone. In these studies, nitisinone was administered to mice and rabbits during organogenesis with oral doses of nitisinone up to 20 and 8 times respectively, the recommended initial dose of 1 mg/kg/day.
In mice, nitisinone caused incomplete skeletal ossification of fetal bones and decreased pup survival at doses 0.4 times the recommended initial dose, and increased gestational length at doses 4 times the recommended initial dose. In rabbits, nitisinone caused maternal toxicity and incomplete skeletal ossification of fetal bones at doses 1.6 times the recommended initial dose [see Data ] . The background risk of major birth defects and miscarriage for the indicated population are unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Animal Data Reproduction studies have been performed in mice at oral doses of about 0.4, 4 and 20 times the recommended initial dose (1 mg/kg/day) and in rabbits at oral doses of about 1.6, 4 and 8 times the recommended initial dose based on the body surface area. In mice, nitisinone has been shown to cause incomplete skeletal ossification of fetal bones at 0.4, 4 and 20 times the recommended initial dose, increased gestational length at 4 and 20 times the recommended initial dose, and decreased pup survival at 0.4 times the recommended initial dose based on the body surface area.
In rabbits, nitisinone caused incomplete skeletal ossification of fetal bones at 1.6, 4 and 8 times the recommended initial dose based on the body surface area.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of ORFADIN have been established in pediatric patients for the treatment of HT-1 in combination with dietary restriction of tyrosine and phenylalanine. Use of ORFADIN in pediatric patients is supported by evidence from one open-label, uncontrolled clinical study conducted in 207 patients with HT-1 ages 0 to 22 years (median age 9 months) [see Clinical Studies ( 14 )] .
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of nitisinone did not include any subjects aged 65 and over. No pharmacokinetic studies of nitisinone have been performed in geriatric patients. In general, dose selection for an elderly patient should be cautious reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and concomitant disease or other drug therapy in this patient population.
🆘 Overdosage ▾
10 OVERDOSAGE Accidental ingestion of ORFADIN by individuals eating normal diets not restricted in tyrosine and phenylalanine will result in elevated tyrosine levels. In healthy subjects given a single 1 mg/kg dose of nitisinone, the plasma tyrosine level reached a maximum of 1200 micromol/L at 48 to 120 hours after dosing. After a washout period of 14 days, the mean value of plasma tyrosine was still 808 micromol/L.
Fasted follow-up samples obtained from volunteers several weeks later showed tyrosine values back to normal. There were no reports of changes in vital signs or laboratory data of any clinical significance. One patient reported sensitivity to sunlight.
Hyper-tyrosinemia has been reported with ORFADIN treatment [see Warnings and Precautions ( 5.1 )] .
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Nitisinone is a competitive inhibitor of 4-hydroxyphenyl-pyruvate dioxygenase, an enzyme upstream of fumarylacetoacetate hydrolase (FAH) in the tyrosine catabolic pathway. By inhibiting the normal catabolism of tyrosine in patients with HT-1, nitisinone prevents the accumulation of the catabolic intermediates maleylacetoacetate and fumarylacetoacetate. In patients with HT-1, these catabolic intermediates are converted to the toxic metabolites succinylacetone and succinylacetoacetate, which are responsible for the observed liver and kidney toxicity.
Succinylacetone can also inhibit the porphyrin synthesis pathway leading to the accumulation of 5-aminolevulinate, a neurotoxin responsible for the porphyric crises characteristic of HT-1.
12.2Pharmacodynamics In a clinical study, patients with HT-1 were diagnosed by the presence of succinylacetone in urine or plasma and treated with ORFADIN [see Clinical Studies ( 14 )] . In all 186 patients whose urine succinylacetone was measured, the urinary succinylacetone concentration decreased to less than 1 mmol/mol creatinine, the lower limit of quantitation. The median time to normalization of urine succinylacetone was 0.3 months.
The probability of recurrence of abnormal values of urine succinylacetone was 1% at a nitisinone concentration of 37 micromol/L (95% confidence interval: 23, 51 micromol/L). In 87% (150/172) of patients whose plasma succinylacetone was measured, the plasma succinylacetone concentration decreased to less than 0.1 micromol/L, the lower limit of quantitation. The median time to normalization of plasma succinylacetone was 3.9 months.
In another study, comparing two dosing regimens, succinylacetone was measured in urine and/or blood in 16 patients with HT-1 aged 5 years to 24 years. All study patients were on a stable ORFADIN daily dosage (0.4 mg/kg/day to 1 mg/kg/day) during both study dosing regimens. After at least 4 weeks of twice daily dosing with ORFADIN, both the urine and/or blood succinylacetone concentrations were below the limit of quantitation for the assay.
Patients were then switched to once daily dosing with the same total daily dosage of ORFADIN and blood and/or urine succinylacetone concentrations remained undetectable when measured following at least 4 weeks of treatment with once daily dosing. Nitisinone inhibits catabolism of the amino acid tyrosine and can result in elevated plasma levels of tyrosine. Therefore, treatment with nitisinone requires restriction of the dietary intake of tyrosine and phenylalanine to prevent the toxicity associated with elevated plasma levels of tyrosine [see Warnings and Precautions ( 5.1 )].
12.3Pharmacokinetics The single-dose pharmacokinetics of nitisinone have been studied for both ORFADIN capsules and ORFADIN oral suspension in healthy adult subjects and the multiple-dose pharmacokinetics have been studied for ORFADIN capsules in healthy subjects. Absorption The pharmacokinetic characteristics following single oral administration of ORFADIN 30 mg under fasting conditions are shown in Table 3 . Compared to ORFADIN capsule, the median T max occurred about 3 hours earlier with ORFADIN oral suspension.
The multiple-dose characteristics of ORFADIN 80 mg once daily are shown in Table 4 . Steady-state (SS) was reached within 14 days dosing in all subjects. TABLE 3 Nitisinone Arithmetic Mean (CV%) Pharmacokinetic Parameters in Healthy Subjects Following a Single Oral 30 mg Dose of ORFADIN Under Fasting Conditions Treatment C max (micromol/L) [range] t max * (h) [range] AUC 0-72h (micromol·h/L) [range] * presented as median [range] ORFADIN capsule (n=12) 10.5 (26) 3.5 406 (13) [0.8 to 8.0] ORFADIN oral suspension (n=12) 10.1 (34) 0.4 350 (17) [0.2 to 4.0] TABLE 4 Nitisinone Arithmetic Mean (CV%) Pharmacokinetic Parameters in Healthy Subjects Following Repeated Once Daily Administration of 80 mg ORFADIN Under Fasting Conditions.
Treatment C max,ss (micromol/L) [CV%] C mi… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Nitisinone is a competitive inhibitor of 4-hydroxyphenyl-pyruvate dioxygenase, an enzyme upstream of fumarylacetoacetate hydrolase (FAH) in the tyrosine catabolic pathway. By inhibiting the normal catabolism of tyrosine in patients with HT-1, nitisinone prevents the accumulation of the catabolic intermediates maleylacetoacetate and fumarylacetoacetate. In patients with HT-1, these catabolic intermediates are converted to the toxic metabolites succinylacetone and succinylacetoacetate, which are responsible for the observed liver and kidney toxicity.
Succinylacetone can also inhibit the porphyrin synthesis pathway leading to the accumulation of 5-aminolevulinate, a neurotoxin responsible for the porphyric crises characteristic of HT-1.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Capsules: White capsules marked in black with "NTBC" and identified as 2 mg, 5 mg, 10 mg or 20 mg strengths of nitisinone. The capsules are packed in a high density (HD) polyethylene container with a tamper-resistant low density (LD) polyethylene snap-on cap. Each bottle contains 60 capsules.
2 mg white capsules imprinted "NTBC 2 mg" in black ink, NDC 66658-102-60 5 mg white capsules imprinted "NTBC 5 mg" in black ink, NDC 66658-105-60 10 mg white capsules imprinted "NTBC 10 mg" in black ink, NDC 66658-110-60 20 mg white capsules imprinted "NTBC 20 mg" in black ink, NDC 66658-120-60 Store refrigerated at 2° to 8°C (36° to 46°F). Alternatively, patients/caregivers may store ORFADIN capsules at room temperature up to 25°C (77°F) for up to 45 days. If not used within 45 days, discard ORFADIN capsules.
Oral suspension: White, slightly viscous opaque suspension. 1 mL contains 4 mg of nitisinone. The suspension is provided in a 100 mL brown bottle (type III glass) with a white child resistant HDPE screw cap with sealing and tamper evidence.
Each bottle contains 90 mL oral suspension. Oral suspension 4 mg/mL, NDC 66658-204-90 Store refrigerated at 2°C to 8°C (36°F to 46°F) prior to first use. Do not freeze.
Store upright. After first opening, store the product at room temperature (up to 25°C (77°F)) for up to 60 days. If not used within 60 days, discard unused portion.
The discard after date should be noted on the bottle
📋 Description ▾
11 DESCRIPTION ORFADIN contains nitisinone, which is a hydroxyphenyl-pyruvate dioxygenase inhibitor indicated as an adjunct to dietary restriction of tyrosine and phenylalanine in the treatment of hereditary tyrosinemia type 1 (HT-1). Nitisinone occurs as white to yellowish-white, crystalline powder. It is practically insoluble in water, soluble in 2M sodium hydroxide and in methanol, and sparingly soluble in alcohol.
Chemically, nitisinone is 2-(2-nitro-4-trifluoromethylbenzoyl) cyclohexane-1,3-dione, and the structural formula is: Figure 1. The molecular formula is C 14 H 10 F 3 NO 5 with a relative mass of 329.23 Capsules: Hard, white-opaque capsule, marked as 2 mg, 5 mg, 10 mg or 20 mg strengths of nitisinone, intended for oral administration. Each capsule contains 2 mg, 5 mg, 10 mg or 20 mg nitisinone, plus pre-gelatinized starch.
The capsule shell is gelatin and titanium dioxide and the imprint is an iron oxide. Oral suspension: 4 mg/mL, a white, slightly viscous opaque suspension. The inactive ingredients are hydroxypropyl methylcellulose, glycerol, polysorbate 80, sodium benzoate, citric acid monohydrate, trisodium citrate dihydrate, strawberry aroma (artificial) and purified water.
Glycerol: Each mL contains 500 mg. Sodium: Each mL contains 0.7 mg (0.03 mEq). Figure 1
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Instructions for Use ). Preparation and Administration Instructions [see Dosage and Administration ( 2.2 )] Preparation of the Oral Suspension The oral suspension will be dispensed with an oral syringe of appropriate size and a bottle adaptor provided by a pharmacist or other healthcare provider. Preparing a Bottle Without the Adapter Already Inserted: Store the bottle in the refrigerator prior to first use.
Remove the bottle from the refrigerator. Calculate 60 days from when the bottle is removed from the refrigerator. Write this date as the “Discard after” date on the bottle label.
Allow the bottle to warm to room temperature (30 to 60 minutes). Shake the bottle vigorously for at least 20 seconds until the solid cake at the bottom of the bottle is completely dispersed. Check that there are no particles left at the bottom of the bottle.
Foam will form in the bottle. Insert the bottle adapter. Preparing a Bottle With the Adapter Inserted: Shake the bottle vigorously for at least 5 seconds.
Check that there are no particles left at the bottom of the bottle. Foam will form in the bottle. Measuring and Administering the Dose Once the bottle is prepared with the adapter: Use the oral syringe to measure the dose.
Keep the bottle upright and insert the oral syringe into the adapter. Carefully turn the bottle upside down with the oral syringe in place. Wait for the foam to rise to the top of the bottle.
Pull back on the syringe plunger to withdraw the dose. Leave the syringe in the adapter and turn the bottle upright. Remove the syringe from the adapter by gently twisting it out of the bottle.
Dispense the dose into the patient's mouth. Do not remove the bottle adapter. Store the bottle at room temperature (not above 25°C).
Administration of ORFADIN Capsules and Oral Suspension Maintain dietary restriction of tyrosine and phenylalanine when taking ORFADIN. Capsules: Take at least one hour before, or two hours after a meal. For patients who have difficulty swallowing the capsules and for which the oral suspension is not suitable [see Warnings and Precautions ( 5.3 ]) , the capsules may be opened and the contents suspended in a small amount of water, formula or apple sauce immediately before use.
Or, the oral suspension may be used instead. Oral suspension: Take without regard to meals. Elevated Plasma Tyrosine Levels, Ocular Symptoms, Developmental Delay and Hyperkeratotic Plaques Inform patients that inadequate restriction may be associated with ocular signs and symptoms, intellectual disability and developmental delay, and painful hyperkeratotic plaques on the soles and palms.
Advise patients and caregivers of the need to maintain dietary restriction of tyrosine and phenylalanine and to report any unexplained ocular, neurologic, or other symptoms promptly to their healthcare provider [see Warnings and Precautions ( 5.1 )]. Risk of Adverse Reactions Due to Glycerol Content of ORFADIN Oral Suspension Advise patients receiving doses of greater than 20 mL of ORFADIN oral suspension that they may experience headache, upset stomach and diarrhea due to the glycerol component of the formulation and if they develop symptoms to report these to their healthcare provider [see Warnings and Precautions ( 5.3 )].
Manufactured by: Apotek Produktion & Laboratorier AB, Sweden Marketed by: Sobi, Inc 77 Fourth Avenue, 3 rd Floor, Waltham, MA 02451-7559
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The single-dose pharmacokinetics of nitisinone have been studied for both ORFADIN capsules and ORFADIN oral suspension in healthy adult subjects and the multiple-dose pharmacokinetics have been studied for ORFADIN capsules in healthy subjects. Absorption The pharmacokinetic characteristics following single oral administration of ORFADIN 30 mg under fasting conditions are shown in Table 3 . Compared to ORFADIN capsule, the median T max occurred about 3 hours earlier with ORFADIN oral suspension.
The multiple-dose characteristics of ORFADIN 80 mg once daily are shown in Table 4 . Steady-state (SS) was reached within 14 days dosing in all subjects. TABLE 3 Nitisinone Arithmetic Mean (CV%) Pharmacokinetic Parameters in Healthy Subjects Following a Single Oral 30 mg Dose of ORFADIN Under Fasting Conditions Treatment C max (micromol/L) [range] t max * (h) [range] AUC 0-72h (micromol·h/L) [range] * presented as median [range] ORFADIN capsule (n=12) 10.5 (26) 3.5 406 (13) [0.8 to 8.0] ORFADIN oral suspension (n=12) 10.1 (34) 0.4 350 (17) [0.2 to 4.0] TABLE 4 Nitisinone Arithmetic Mean (CV%) Pharmacokinetic Parameters in Healthy Subjects Following Repeated Once Daily Administration of 80 mg ORFADIN Under Fasting Conditions.
Treatment C max,ss (micromol/L) [CV%] C min,ss (micromol/L) [range] t max,ss * (h) [range] AUC 0-24h,ss (micromol·h/L) [range] * presented as median [range] ORFADIN capsule (n=18) 120 (23) 73(24) 4.0 2204(18) [0.0 to 16.0] Food Effect: No food effect study was conducted with ORFADIN capsules. For ORFADIN oral suspension, a high calorie (800 to 1000 calories) and high fat meal (approximately 50% of total caloric content) did not affect nitisinone total exposure (AUC 72h ), but decreased the C max by approximately 20% [see Dosage and Administration ( 2.2 )] .
Distribution In vitro binding of nitisinone to human plasma proteins is greater than 95% at 50 micromolar concentration. Elimination The mean terminal plasma half-life of single dose nitisinone in healthy male subjects is 54 hours. The mean (CV%)apparent plasma clearance in 18 healthy adults following multiple once daily doses of ORFADIN 80 mg is 113 (16) mL/h.
Metabolism: In vitro studies have shown that nitisinone is relatively stable in human liver microsomes with minor metabolism possibly mediated by CYP3A4 enzyme. Excretion: Renal elimination of nitisinone is of minor importance, since the mean of the fraction of dose excreted as unchanged nitisinone in the urine (fe(%)) was 3.0% (n=3) following multiple oral doses of 80 mg daily in healthy subjects. The estimated mean (CV%) renal clearance of nitisinone was 0.003 L/h (25%).
Drug Interaction Studies Nitisinone does not inhibit CYP2D6. Nitisinone is a moderate inhibitor of CYP2C9, and a weak inducer of CYP2E1 ( Table 5 ). Nitisinone is an inhibitor of OAT1/3 ( Table 5 ).
Table 5. Percent Change in AUC 0-∞ and C max for Co-administered Drugs in the Presence of ORFADIN in 18 Healthy Subjects ↑ = Increased; ↓ = Decreased a The interacting drug was administered alone on Day 1 and together with ORFADIN on Day 17. b Multiple doses of 80 mg ORFADIN were administered daily alone from Day 3 to Day 16. c 16 subjects in Period 2 received ORFADIN and tolbutamide while 18 subjects in Period 1 received ORFADIN alone. Co-administered Drug a Dose of Co-administered Drug (Route of Administration) Effect of Nitisinone on the Pharmacokinetics of Co-administered Drug b AUC 0-∞ C max CYP2C9 Substrate Tolbutamide c 500 mg (oral) 131% ↑ 16% ↑ CYP2E1 Substrate Chlorzoxazone 250 mg (oral) 27% ↓ 18% ↓ OAT1/3 Substrate Furosemide 20 mg (intravenous) 72% ↑ 12% ↑ In Vitro Studies Where Drug Interaction Potential Was Not Further Evaluated Clinically In vitro studies showed that nitisinone does not inhibit CYP1A2, 2C19, or 3A4.
Nitisinone does not induce CYP1A2, 2B6 or 3A4/5. Nitisinone does not inhibit P-gp, BCRP, OATP1B1, OATP1B3 and OCT2-mediated transports at therapeutically relevant concentrations.
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics In a clinical study, patients with HT-1 were diagnosed by the presence of succinylacetone in urine or plasma and treated with ORFADIN [see Clinical Studies ( 14 )] . In all 186 patients whose urine succinylacetone was measured, the urinary succinylacetone concentration decreased to less than 1 mmol/mol creatinine, the lower limit of quantitation. The median time to normalization of urine succinylacetone was 0.3 months.
The probability of recurrence of abnormal values of urine succinylacetone was 1% at a nitisinone concentration of 37 micromol/L (95% confidence interval: 23, 51 micromol/L). In 87% (150/172) of patients whose plasma succinylacetone was measured, the plasma succinylacetone concentration decreased to less than 0.1 micromol/L, the lower limit of quantitation. The median time to normalization of plasma succinylacetone was 3.9 months.
In another study, comparing two dosing regimens, succinylacetone was measured in urine and/or blood in 16 patients with HT-1 aged 5 years to 24 years. All study patients were on a stable ORFADIN daily dosage (0.4 mg/kg/day to 1 mg/kg/day) during both study dosing regimens. After at least 4 weeks of twice daily dosing with ORFADIN, both the urine and/or blood succinylacetone concentrations were below the limit of quantitation for the assay.
Patients were then switched to once daily dosing with the same total daily dosage of ORFADIN and blood and/or urine succinylacetone concentrations remained undetectable when measured following at least 4 weeks of treatment with once daily dosing. Nitisinone inhibits catabolism of the amino acid tyrosine and can result in elevated plasma levels of tyrosine. Therefore, treatment with nitisinone requires restriction of the dietary intake of tyrosine and phenylalanine to prevent the toxicity associated with elevated plasma levels of tyrosine [see Warnings and Precautions ( 5.1 )].
🔬 Clinical Studies ▾
14 CLINICAL STUDIES The efficacy and safety of ORFADIN in patients with HT-1 was evaluated in one open-label, uncontrolled study of 207 patients with HT-1, ages 0 to 22 years at enrollment (median age 9 months). Patients were diagnosed with HT-1 by the presence of succinylacetone in the urine or plasma. All patients were treated with ORFADIN at a starting dose of 0.3 to 0.5 mg/kg twice daily, and the dose was increased in some patients to 1 mg/kg twice daily based on weight, liver and kidney function tests, platelet count, serum amino acids, urinary phenolic acid, plasma and urine succinylacetone, erythrocyte PBG-synthase, and urine 5-ALA.
The median duration of treatment was 22 months (range less than 1 month to 80 months). Efficacy was assessed by comparison of survival and incidence of liver transplant to historical controls. For patients presenting with HT-1 younger than 2 months of age who were treated with dietary restriction and nitisinone, 2- and 4-year survival probabilities were 88% and 88%, respectively.
Data from historical controls showed that patients presenting with HT-1 at younger than 2 months of age and treated with dietary restriction alone had 2- and 4-year survival probabilities of 29% and 29%, respectively. For patients presenting with HT-1 between 2 months and 6 months of age who were treated with dietary restriction and nitisinone, 2- and 4-year survival probabilities were 94% and 94%, respectively. Data for historical controls showed that patients presenting with HT-1 between 2 months and 6 months of age treated with dietary restriction alone had 2- and 4-year survival probabilities of 74% and 60%, respectively.
The effects of nitisinone on urine and plasma succinylacetone, porphyrin metabolism, and urinary alpha-1-microglobulin were also assessed in this clinical study. Porphyria-like crisis were reported in 3 patients (0.3% of cases per year) during the clinical study. This compares to an incidence of 5 to 20% of cases per year expected as part of the natural history of the disorder.
An assessment of porphyria-like crises was performed because these events are commonly reported in patients with HT-1 who are not treated with nitisinone. Urinary alpha-1-microglobulin, a proposed marker of proximal tubular dysfunction, was measured in 100 patients at baseline. The overall median pretreatment level was 4.3 grams/mol creatinine.
After one year of treatment in a subgroup of patients (N=100), overall median alpha-1-microglobulin decreased by 1.5 grams/mol creatinine. In patients 24 months of age and younger in whom multiple values were available (N=65), median alpha-1-microglobulin levels decreased from 5.0 to 3.0 grams/mol creatinine (reference value for age less than or equal to 12 grams/mol creatinine). In patients older than 24 months in whom multiple values were available (N=35), median alpha-1-microglobulin levels decreased from 2.8 to 2.0 grams/mol creatinine (reference for age less than or equal to 6 grams/mol creatinine).
The long term effect of nitisinone on hepatic function was not assessed.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of nitisinone was assessed in a 26-week oral (gavage) carcinogenicity study in Tg.rasH2 mice. There were no drug-related neoplastic findings in male or female Tg.rasH2 mice at doses up to 100 mg/kg/ day nitisinone (approximately 8.1 times the recommended initial dose of 1 mg/kg/day on a body surface area basis). Nitisinone was not genotoxic in the Ames test and the in vivo mouse liver unscheduled DNA synthesis (UDS) test.
Nitisinone was mutagenic in the mouse lymphoma cell (L5178Y/TK +/- ) forward mutation test and in an in vivo mouse bone marrow micronucleus test. In a single dose-group study in rats given 100 mg/kg (16.2 times the recommended initial dose of 1 mg/kg/day on a body surface area basis), reduced litter size, decreased pup weight at birth, and decreased survival of pups after birth was demonstrated.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility The carcinogenic potential of nitisinone was assessed in a 26-week oral (gavage) carcinogenicity study in Tg.rasH2 mice. There were no drug-related neoplastic findings in male or female Tg.rasH2 mice at doses up to 100 mg/kg/ day nitisinone (approximately 8.1 times the recommended initial dose of 1 mg/kg/day on a body surface area basis). Nitisinone was not genotoxic in the Ames test and the in vivo mouse liver unscheduled DNA synthesis (UDS) test.
Nitisinone was mutagenic in the mouse lymphoma cell (L5178Y/TK +/- ) forward mutation test and in an in vivo mouse bone marrow micronucleus test. In a single dose-group study in rats given 100 mg/kg (16.2 times the recommended initial dose of 1 mg/kg/day on a body surface area basis), reduced litter size, decreased pup weight at birth, and decreased survival of pups after birth was demonstrated.
📖 Instructions for Use ▾
Instructions for Use ORFADIN (OR-fuh-din) (nitisinone) oral suspension 4 mg/mL Read this Instructions for Use before you start taking ORFADIN oral suspension and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or your treatment.
Important information about measuring ORFADIN oral suspension: Use the oral syringe provided with your ORFADIN oral suspension to make sure you measure the right amount. You will be provided with: 1 bottle of ORFADIN oral suspension 1 oral syringe 1 adapter (The adapter may or may not be inserted in your bottle of ORFADIN oral suspension when you receive it.) Figure A If the adapter is not inserted in your bottle of ORFADIN oral suspension when you receive it, follow the instructions in “ How to prepare a bottle of ORFADIN oral suspension if the adapter is not inserted .” If the adapter is inserted in your bottle of ORFADIN oral suspension when you receive it, follow the instructions in “ How to prepare a dose of ORFADIN oral suspension after the adapter is inserted .” How to prepare a bottle of ORFADIN oral suspension if the adapter is not inserted: See “ How should I store ORFADIN oral suspension? ” for instructions on how to store ORFADIN oral suspension if the adapter is not inserted.
1. Remove the ORFADIN oral suspension bottle from the refrigerator 30 minutes to 1 hour before using it to allow it to reach room temperature. ORFADIN oral suspension should be thrown away (discarded) 60 days after it is removed from the refrigerator and the adapter is inserted in the bottle.
Write the discard date on the bottle label. 2. Shake the bottle well for at least 20 seconds until the solid cake of particles at the bottom of the bottle is dissolved (See Figure B ).
Check that there are no particles left at the bottom of the bottle. Foam will form in the bottle. Figure B 3.
Remove the child resistant screw cap by pushing it down firmly and turning it counter-clockwise (See Figure C ). Figure C 4. Place the open bottle upright on a flat surface.
Push the ribbed end of the adapter firmly into the neck of the bottle as far as it will go (See Figure D ). Replace the child resistant screw cap on the bottle. Do not remove the adapter from the bottle after it is inserted.
Figure D 5. Follow the instructions in “ How to prepare a dose of ORFADIN oral suspension after the adapter is inserted .” How to prepare a dose of ORFADIN oral suspension after the adapter is inserted See “ How should I store ORFADIN oral suspension? ” for instructions on how to store ORFADIN oral suspension after the adapter is inserted. 1.
Shake the ORFADIN oral suspension bottle well for at least 5 seconds (See Figure E ). Check that there are no particles left at the bottom of the bottle. Foam will form in the bottle.
Figure E 2. Remove the child resistant screw cap right away by pushing it down firmly and turning it counter-clockwise (See Figure F ). Figure F 3.
Hold the oral syringe in one hand. With your other hand, fully push down (depress) the plunger (See Figure G ). Figure G 4.
Keeping the bottle in an upright position, insert the oral syringe firmly into the adapter (See Figure H ). Figure H 5. Carefully turn the bottle upside down with the oral syringe in place (See Figure I ).
Wait until you can see that the foam is at the top of the bottle to avoid withdrawing bubbles into the syringe. Figure I 6. Pull back slowly on the oral syringe plunger until the top edge of the black ring is at the line marking the dose prescribed by your healthcare provider (See Figure J ).
Figure J shows a dose of 1 mL as an example. If you see air bubbles in the oral syringe, fully push in the plunger so that the oral suspension flows back into the bottle. Then, withdraw your prescribed dose of oral suspension.
Figure J 7. Leave the oral syringe in the adapter and turn the bottle to an upright position. Place the bottle onto a flat surface.… [Excerpted — this section continues on DailyMed.]
📄 Recent Major Changes ▾
Warnings and Precautions ( 5.1 ) 05/2019
📄 Package Label / Principal Display Panel ▾
Principal Display Panel - 2 mg Carton Label 60 capsules NDC 66658-102-60 Orfadin ® Capsules (Nitisinone) 2 mg For Oral Use sobi Principal Display Panel - 2 mg Carton Label
Principal Display Panel - Bottle Label For Oral Use Rx only See Package Insert Store refrigerated 2-8 °C (36-46 °F) Manufactured by: Apotek Produktion & Laboratorier AB, Sweden Orfadin ® Capsules (Nitisinone) 2 mg sobi NDC 66658-102-60 60 capsules Marketed by: Sobi, Inc 890 Winter Street Waltham, MA 02451 Principal Display Panel - Bottle Label
Principal Display Panel - 5 mg Carton Label 60 capsules NDC 66658-105-60 Orfadin ® Capsules (Nitisinone) 5 mg For Oral Use sobi Principal Display Panel - 5 mg Carton Label
Principal Display Panel - Bottle Label For Oral Use Rx only See Package Insert Store refrigerated 2-8 °C (36-46 °F) Manufactured by: Apotek Produktion & Laboratorier AB, Sweden Orfadin ® Capsules (Nitisinone) 5 mg sobi NDC 66658-105-60 60 capsules Marketed by: Sobi, Inc 890 Winter Street Waltham, MA 02451 Principal Display Panel - Bottle Label
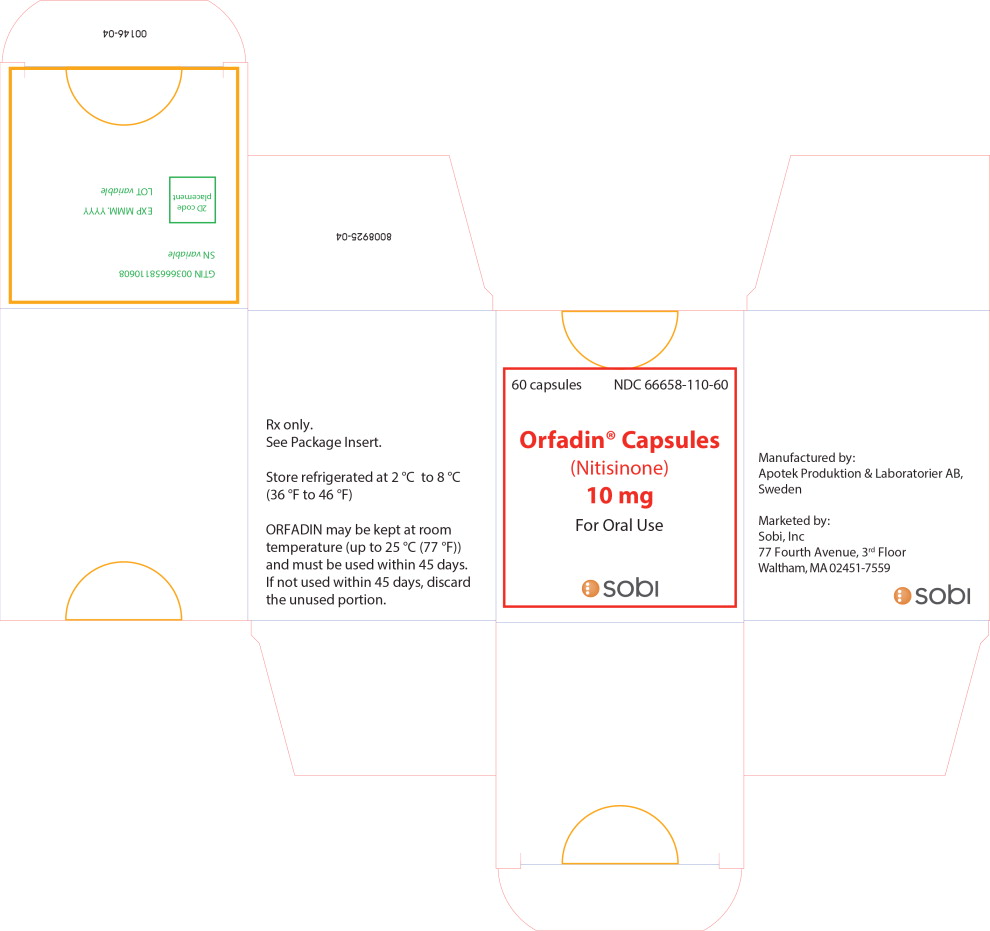
Principal Display Panel - 10 mg Carton Label 60 capsules NDC 66658-110-60 Orfadin ® Capsules (Nitisinone) 10 mg For Oral Use sobi Principal Display Panel - 10 mg Carton Label
Principal Display Panel - Bottle Label For Oral Use Rx only See Package Insert Store refrigerated 2-8 °C (36-46 °F) Manufactured by: Apotek Produktion & Laboratorier AB, Sweden Orfadin ® Capsules (Nitisinone) 10 mg sobi NDC 66658-110-60 60 capsules Marketed by: Sobi, Inc 890 Winter Street Waltham, MA 02451 Principal Display Panel - Bottle Label
Principal Display Panel - 20 mg Carton Label 60 capsules NDC 66658-120-60 Orfadin ® Capsules (Nitisinone) 20 mg For Oral Use sobi Principal Display Panel - 20 mg Carton Label
Principal Display Panel - Bottle Label For Oral Use Rx only See Package Insert Store refrigerated 2-8 °C (36-46 °F) Manufactured by: Apotek Produktion & Laboratorier AB, Sweden Orfadin ® Capsules (Nitisinone) 20 mg sobi NDC 66658-110-60 60 capsules Marketed by: Sobi, Inc 890 Winter Street Waltham, MA 02451 Principal Display Panel - Bottle Label
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |