
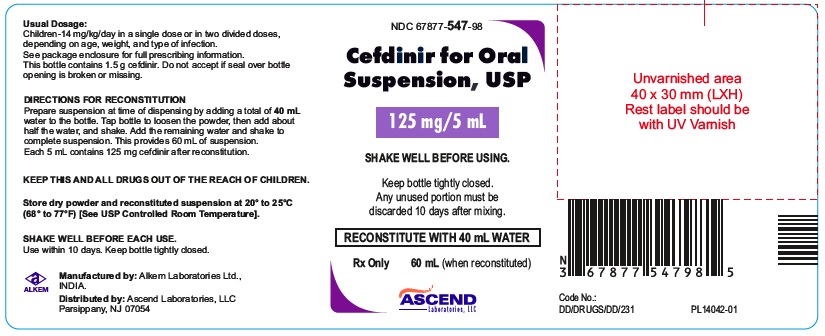
cefdinir 250 mg/5mL Powder, For Suspension, 100 mL
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Cephalosporin Antibacterial class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Cefdinir is used to treat certain infections caused by bacteria. Cefdinir is in a class of medications called cephalosporin antibiotics. It works by killing bacteria. Antibiotics such as cefdinir will not work for colds, flu, or other viral infections. Using antibiotics when they are not needed increases your risk of getting an infection later that resists antibiotic treatment.
Read the full MedlinePlus article ↗- Cefdinir treats a range of common bacterial infections — strep throat, sinus infections, ear infections (mainly in kids), pneumonia, bronchitis flare-ups, and uncomplicated skin in...
- What kinds of infections does cefdinir treat?
- It depends — and this is really important to tell your doctor upfront. Cefdinir is in the cephalosporin family, which is related to penicillin. Up to about 1 in 10 people with a pe...
- Can I take cefdinir if I'm allergic to penicillin?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Cefdinir — tap one for details:
Cefdinir may be associated with lower levels of 7 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII RS7A450LGA
A sodium salt derived from citric acid that helps regulate acidity and maintain pH balance in the medicine. It also works as a binding agent to hold tablet ingredients together.
-
UNII E89I1637KE
Guar gum is a natural thickener made from guar bean seeds. It's used in medicines as a binder and thickening agent to hold ingredients together and create the right texture and consistency.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII OJ245FE5EU
Sodium benzoate is a salt derived from benzoic acid, a preservative. It's added to medicines to prevent growth of bacteria, fungi, and other microorganisms that could spoil the product.
-
UNII 4J2TY8Y81V
A natural flavoring derived from strawberries that gives the medicine its strawberry taste and smell. It helps make the medicine more pleasant to take, especially for children.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.114 | $11.35 / 100 ml |
| Medicaid paysCMS SDUD · 12 mo | $0.2275 | $22.75 / 100 ml |
| Medicare drug plans payPart D · Q2 2026 | $0.2002 | $20.02 / 100 ml |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Cefdinir 250 mg/5mL 65862-0219-01 | Aurobindo | 1 bottle | $0.114 | AB | Availability likely | — |
| cefdinir 250 mg/5mLthis 67877-0548-88 | Ascend | 100 ml | $0.114 | AB | Availability likely | — |
| Cefdinir 250 mg/5mL 00093-4137-64 | Teva | 60 ml | $0.119 | AB | Availability likely | +5% |
| Cefdinir 250 mg/5mL 68180-0723-04 | Lupin | 60 ml | $0.119 | AB | Availability likely | +5% |
| Cefdinir 250 mg/5mL 50090-2735-00 | A-S | 1 bottle | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 50090-3723-00 | A-S | 100 ml | — | AB | FDA listed | — |
| cefdinir 250 mg/5mL 50090-5811-00 | A-S | 60 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 50090-6171-00 | A-S | 60 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 63187-0616-00 | Proficient | 100 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 68071-3403-01 | NuCare | 100 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 68071-5106-06 | NuCare | 60 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 68788-4106-01 | Preferred | 100 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 68788-8655-01 | Preferred | 100 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 71205-0380-00 | Proficient | 100 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 71205-0405-00 | Proficient | 1 bottle | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 72189-0043-32 | DIRECT | 5 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 72189-0186-32 | DIRECT | 60 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 72189-0259-32 | DIRECT | 100 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 76420-0328-01 | Asclemed | 100 ml | — | AB | FDA listed | — |
| Cefdinir 250 mg/5mL 68788-7844-01 | Preferred | 1 bottle | — | AB | Discontinued | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
💊 Medicaid utilization by pack size
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 67877-0548-88 You're viewing this | 100 mL in 1 BOTTLE (67877-548-88) | $0.1135 / mL | $11.35 | 2021-02-20 | Active |
| 67877-0548-98 | 60 mL in 1 BOTTLE (67877-548-98) | $0.1195 / mL | $7.17 | 2021-02-20 | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack has the lowest per-mL cost of the 2 priced pack sizes ($0.1135 NADAC).
This pack accounts for about 32% of this product's recent Medicaid fills; most go to the 6 ml pack. See all packs ↓
Pack size FAQ
What quantity is in NDC 67877-0548-88?
What is the difference between NDC 67877-0548-88 and NDC 67877-0548-98?
What NDC number is used to bill for this package of cefdinir 250 mg/5mL Powder, For Suspension?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS & USAGE To reduce the development of drug-resistant bacteria and maintain the effectiveness of cefdinir and other antibacterial drugs, cefdinir should be used only to treat or prevent infections that are proven or strongly suspected to be caused by susceptible bacteria. When culture and susceptibility information are available, they should be considered in selecting or modifying antibacterial therapy. In the absence of such data, local epidemiology and susceptibility patterns may contribute to the empiric selection of therapy.
Cefdinir for oral suspension is indicated for the treatment of patients with mild to moderate infections caused by susceptible strains of the designated microorganisms in the conditions listed below. Adults and Adolescents Community-Acquired Pneumonia caused by Haemophilus influenzae (including β-lactamase producing strains), Haemophilus parainfluenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains) (see CLINICAL STUDIES ).
Acute Exacerbations of Chronic Bronchitis caused by Haemophilus influenzae (including β-lactamase producing strains), Haemophilus parainfluenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains). Acute Maxillary Sinusitis caused by Haemophilus influenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains).
NOTE: For information on use in pediatric patients, see Pediatric Use and DOSAGE AND ADMINISTRATION . Pharyngitis/Tonsillitis caused by Streptococcus pyogenes (see CLINICAL STUDIES ). NOTE: Cefdinir is effective in the eradication of S. pyogenes from the oropharynx.
Cefdinir has not, however, been studied for the prevention of rheumatic fever following S. pyogenes pharyngitis/tonsillitis. Only intramuscular penicillin has been demonstrated to be effective for the prevention of rheumatic fever. Uncomplicated Skin and Skin Structure Infections caused by Staphylococcus aureus (including β-lactamase producing strains) and Streptococcus pyogenes .
Pediatric Patients Acute Bacterial Otitis Media caused by Haemophilus influenzae (including β-lactamase producing strains), Streptococcus pneumoniae (penicillin-susceptible strains only), and Moraxella catarrhalis (including β-lactamase producing strains).Pharyngitis/Tonsillitis caused by Streptococcus pyogenes (see CLINICAL STUDIES ). NOTE: Cefdinir is effective in the eradication of S. pyogenes from the oropharynx. Cefdinir has not, however, been studied for the prevention of rheumatic fever following S. pyogenes pharyngitis/tonsillitis.
Only intramuscular penicillin has been demonstrated to be effective for the prevention of rheumatic fever. Uncomplicated Skin and Skin Structure Infections caused by Staphylococcus aureus (including β-lactamase producing strains) and Streptococcus pyogenes .
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION (see INDICATIONS AND USAGE for Indicated Pathogens) Powder for Oral Suspension The recommended dosage and duration of treatment for infections in pediatric patients are described in the following chart; the total daily dose for all infections is 14 mg/kg, up to a maximum dose of 600 mg per day. Once-daily dosing for 10 days is as effective as BID. dosing. Once-daily dosing has not been studied in skin infections; therefore, cefdinir for oral suspension should be administered twice daily in this infection.
Cefdinir for oral suspension may be administered without regard to meals. Pediatric Patients (Age 6 Months Through 12 Years) Type of Infection Dosage Duration Acute Bacterial Otitis Media 7 mg/kg q12h or 14 mg/kg q24h 5 to 10 days 10 days Acute Maxillary Sinusitis 7 mg/kg q12h or 14 mg/kg q24h 10 days 10 days Pharyngitis/Tonsillitis 7 mg/kg q12h or 14 mg/kg q24h 5 to 10 days 10 days Uncomplicated Skin and Skin Structure Infections 7 mg/kg q12h 10 days CEFDINIR FOR ORAL SUSPENSION PEDIATRIC DOSAGE CHART Weight 125 mg/5 mL 250 mg/5 mL 9 kg/20 lbs 2.5 mL q12h or 5 mL q24h Use 125 mg/5 mL product 18 kg/40 lbs 5 mL q12h or 10 mL q24h 2.5 mL q12h or 5 mL q24h 27 kg/60 lbs 7.5 mL q12h or 15 mL q24h 3.75 mL q12h or 7.5 mL q24h 36 kg/80 lbs 10 mL q12h or 20 mL q24h 5 mL q12h or 10 mL q24h ≥43 kg* /95 lbs 12 mL q12h or 24 mL q24h 6 mL q12h or 12 mL q24h * Pediatric patients who weigh ≥ 4 3 kg should receive the maximum daily dose of 600 mg.
Patients with Renal Insufficiency For adult patients with creatinine clearance < 30 mL/min, the dose of cefdinir should be 300 mg given once daily. Creatinine clearance is difficult to measure in outpatients. However, the following formula may be used to estimate creatinine clearance (CLcr) in adult patients.
For estimates to be valid, serum creatinine levels should reflect steady-state levels of renal function. Males: CLcr = (weight) (140 – age) (72) (serum creatinine) Females: CLcr = 0.85 x above value where creatinine clearance is in mL/min, age is in years, weight is in kilograms, and serum creatinine is in mg/dL .1 The following formula may be used to estimate creatinine clearance in pediatric patients: CLcr = K x body length or height serum creatinine where K=0.55 for pediatric patients older than 1 year 2 and 0.45 for infants (up to 1 year).
3 In the above equation, creatinine clearance is in mL/min/1.73 m 2 , body length or height is in centimeters, and serum creatinine is in mg/dL. For pediatric patients with a creatinine clearance of < 30 mL/min/1.73 m 2 , the dose of cefdinir should be 7 mg/kg (up to 300 mg) given once daily Patients on Hemodialysis Hemodialysis removes cefdinir from the body. In patients maintained on chronic hemodialysis, the recommended initial dosage regimen is a 300- mg or 7- mg/kg dose every other day.
At the conclusion of each hemodialysis session, 300 mg (or 7 mg/kg) should be given. Subsequent doses (300 mg or 7 mg/kg) are then administered every other day. Directions for Mixing Cefdinir for Oral Suspension Final Concentration Final Volume(mL) Amount of Water Directions 125 mg/5 mL 60 100 40 mL 64 mL Tap bottle to loosen powder, then add water in 2 portions.
Shake well after each aliquot. 250 mg/5 mL 60 100 40 mL 64 mL Tap bottle to loosen powder, then add water in 2 portions. Shake well after each aliquot.
After mixing, the suspension can be stored at controlled room temperature (20 ° to 25 ° C/68 ° to 77 ° F). The container should be kept tightly closed, and the suspension should be shaken well before each administration. The suspension may be used for 10 days, after which any unused portion must be discarded.
⛔ Contraindications ▾
CONTRAINDICATIONS Cefdinir is contraindicated in patients with known allergy to the cephalosporin class of antibiotics.
⚠️ Warnings ▾
WARNINGS BEFORE THERAPY WITH CEFDINIR IS INSTITUTED, CAREFUL INQUIRY SHOULD BE MADE TO DETERMINE WHETHER THE PATIENT HAS HAD PREVIOUS HYPERSENSITIVITY REACTIONS TO CEFDINIR, OTHER CEPHALOSPORINS, PENICILLINS, OR OTHER DRUGS. IF CEFDINIR IS TO BE GIVEN TO PENICILLIN SENSITIVE PATIENTS, CAUTION SHOULD BE EXERCISED BECAUSE CROSSHYPERSENSITIVITY AMONG β-LACTAM ANTIBIOTICS HAS BEEN CLEARLY DOCUMENTED AND MAY OCCUR IN UP TO 10% OF PATIENTS WITH A HISTORY OF PENICILLIN ALLERGY. IF AN ALLERGIC REACTION TO CEFDINIR OCCURS, THE DRUG SHOULD BE DISCONTINUED.
SERIOUS ACUTE HYPERSENSITIVITY REACTIONS MAY REQUIRE TREATMENT WITH EPINEPHRINE AND OTHER EMERGENCY MEASURES, INCLUDING OXYGEN, INTRAVENOUS FLUIDS, INTRAVENOUS ANTIHISTAMINES, CORTICOSTEROIDS, PRESSOR AMINES, AND AIRWAY MANAGEMENT, AS CLINICALLY INDICATED. Clostridium difficile associated diarrhea (CDAD) has been reported with use of nearly all antibacterial agents, including cefdinir, and may range in severity from mild diarrhea to fatal colitis. Treatment with antibacterial agents alters the normal flora of the colon leading to overgrowth of C. difficile .
C. difficile produces toxins A and B which contribute to the development of CDAD. Hypertoxin producing strains of C. difficile cause increased morbidity and mortality, as these infections can be refractory to antimicrobial therapy and may require colectomy. CDAD must be considered in all patients who present with diarrhea following antibacterial use.
Careful medical history is necessary since CDAD has been reported to occur over two months after the administration of antibacterial agents. If CDAD is suspected or confirmed, ongoing antibacterial use not directed against C. difficile may need to be discontinued. Appropriate fluid and electrolyte management, protein supplementation, antibacterial treatment of C. difficile , and surgical evaluation should be instituted as clinically indicated.
🤒 Adverse Reactions ▾
ADVERSE EVENTS Clinical Trials-Cefdinir for Oral Suspension (Pediatric Patients) In clinical trials, 2289 pediatric patients (1783 U.S. and 506 non-U.S.) were treated with the recommended dose of cefdinir suspension (14 mg/kg/day). Most adverse events were mild and self-limiting. No deaths or permanent disabilities were attributed to cefdinir.
Forty of 2289 (2%) patients discontinued medication due to adverse events considered by the investigators to be possibly, probably, or definitely associated with cefdinir therapy. Discontinuations were primarily for gastrointestinal disturbances, usually diarrhea. Five of 2289 (0.2%) patients were discontinued due to rash thought related to cefdinir administration.
In the U.S., the following adverse events were thought by investigators to be possibly, probably, or definitely related to cefdinir suspension in multiple-dose clinical trials (N = 1783 cefdinir-treated patients): ADVERSE EVENTS ASSOCIATED WITH CEFDINIR SUSPENSION U.S. TRIALS IN PEDIATRIC PATIENTS (N = 1783)* Incidence ≥ 1% Diarrhea Rash Vomiting 8% 3% 1% Incidence < 1% but > 0.1% Cutaneous moniliasis Abdominal pain Leukopenia† Vaginal moniliasis Vaginitis Abnormal stools Dyspepsia Hyperkinesia Increased AST† Maculopapular rash Nausea 0.9% 0.8% 0.3% 0.3% of girls 0.3% of girls 0.2% 0.2% 0.2% 0.2% 0.2% 0.2% * 977 males, 806 females † Laboratory changes were occasionally reported as adverse events.
NOTE: In both cefdinir- and control-treated patients, rates of diarrhea and rash were higher in the youngest pediatric patients. The incidence of diarrhea in cefdinir-treated patients ≤ 2 years of age was 17% (95/557) compared with 4% (51/1226) in those >2 years old. The incidence of rash (primarily diaper rash in the younger patients) was 8% (43/557) in patients ≤ 2 years of age compared with 1% (8/1226) in those >2 years old.
The following laboratory value changes of possible clinical significance, irrespective of relationship to therapy with cefdinir, were seen during clinical trials conducted in the U.S.: LABORATORY VALUE CHANGES OF POSSIBLE CLINICAL SIGNIFICANCE OBSERVED WITH CEFDINIR SUSPENSION U.S. TRIALS IN PEDIATRIC PATIENTS (N = 1783) Incidence ≥1% ↑Lymphocytes, ↓Lymphocytes ↑Alkaline phosphatase ↓Bicarbonate* ↑Eosinophils ↑Lactate dehydrogenase ↑Platelets ↑PMNs, ↓PMNs ↑Urine protein 2%, 0.8% 1% 1% 1% 1% 1% 1%, 1% 1% Incidence < 1% but > 0.1% ↑Phosphorus, ↓Phosphorus ↑Urine pH ↓White blood cells, ↑White blood cells ↓Calcium* ↓Hemoglobin ↑Urine leukocytes ↑Monocytes ↑AST ↑Potassium* ↑Urine specific gravity, ↓Urine specific gravity ↓Hematocrit* 0.9%, 0.4% 0.8% 0.7%, 0.3% 0.5% 0.5% 0.5% 0.4% 0.3% 0.3% 0.3%, 0.1% 0.2% * N = 1387 for these parameters Postmarketing Experience The following adverse experiences and altered laboratory tests, regardless of their relationship to cefdinir, have been reported during extensive postmarketing experience, beginning with approval in Japan in 1991: shock, anaphylaxis with rare cases of fatality, facial and laryngeal edema, feeling of suffocation, serum sickness-like reactions, conjunctivitis, stomatitis, Stevens-Johnson syndrome, toxic epidermal necrolysis, exfoliative dermatitis, erythema multiforme, erythema nodosum, acute hepatitis, cholestasis, fulminant hepatitis, hepatic failure, jaundice, increased amylase, acute enterocolitis, bloody diarrhea, hemorrhagic colitis, melena, pseudomembranous colitis, pancytopenia, granulocytopenia, leukopenia, thrombocytopenia, idiopathic thrombocytopenic purpura, haemolytic anemia, acute respiratory failure, asthmatic attack, drug-induced pneumonia, eosinophilic pneumonia, idiopathic interstitial pneumonia, fever, acute renal failure, nephropathy, bleeding tendency, coagulation disorder, disseminated intravascular coagulation, upper GI bleed, peptic ulcer, ileus, loss of consciousness, allergic vasculitis, possible cefdinir-diclofenac interaction, cardiac failure, chest pain, myocardial infarction, hypertension, involuntary movements, and rhabdomyolysis.…
🔄 Drug Interactions ▾
DRUG INTERACTIONS Antacids (aluminum- or magnesium-containing) Concomitant administration of 300- mg cefdinir capsules with 30 mL Maalox ® TC suspension reduces the rate (C max ) and extent (AUC) of absorption by approximately 40%. Time to reach Cmax is also prolonged by 1 hour. There are no significant effects on cefdinir pharmacokinetics if the antacid is administered 2 hours before or 2 hours after cefdinir.
If antacids are required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the antacid Probenecid As with other β-lactam antibiotics, probenecid inhibits the renal excretion of cefdinir, resulting in an approximate doubling in AUC, a 54% increase in peak cefdinir plasma levels, and a 50% prolongation in the apparent elimination t 1/2 . Iron Supplements and Foods Fortified With Iron Concomitant administration of cefdinir with a therapeutic iron supplement containing 60 mg of elemental iron (as FeSO 4 ) or vitamins supplemented with 10 mg of elemental iron reduced extent of absorption by 80% and 31%, respectively.
If iron supplements are required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the supplement. The effect of foods highly fortified with elemental iron (primarily iron-fortified breakfast cereals) on cefdinir absorption has not been studied. Concomitantly administered iron-fortified infant formula (2.2 mg elemental iron/6 oz) has no significant effect on cefdinir pharmacokinetics.
Therefore, cefdinir for oral suspension can be administered with iron-fortified infant formula. There have been reports of reddish stools in patients receiving cefdinir. In many cases, patients were also receiving iron-containing products.
The reddish color is due to the formation of a nonabsorbable complex between cefdinir or its breakdown products and iron in the gastrointestinal tract.
🔄 Drug / Laboratory Test Interactions ▾
DRUG & OR LABORATORY TEST INTERACTIONS A false-positive reaction for ketones in the urine may occur with tests using nitroprusside, but not with those using nitroferricyanide. The administration of cefdinir may result in a false-positive reaction for glucose in urine using Clinitest ® , Benedict’s solution, or Fehling’s solution. It is recommended that glucose tests based on enzymatic glucose oxidase reactions (such as Clinistix ® or Tes-Tape ® ) be used.
Cephalosporins are known to occasionally induce a positive direct Coombs’ test.
🤰 Pregnancy ▾
PREGNANCY Teratogenic Effects Pregnancy Category B Cefdinir was not teratogenic in rats at oral doses up to 1000 mg/kg/day (70 times the human dose based on mg/kg/day, 11 times based on mg/m 2 /day) or in rabbits at oral doses up to 10 mg/kg/day (0.7 times the human dose based on mg/kg/day, 0.23 times based on mg/m 2 /day). Maternal toxicity (decreased body weight gain) was observed in rabbits at the maximum tolerated dose of 10 mg/kg/day without adverse effects on offspring. Decreased body weight occurred in rat fetuses at ≥ 100 mg/kg/day, and in rat offspring at ≥ 32 mg/kg/day.
No effects were observed on maternal reproductive parameters or offspring survival, development, behavior, or reproductive function. There are, however, no adequate and well-controlled studies in pregnant women. Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
PEDIATRIC USE Safety and efficacy in neonates and infants less than 6 months of age have not been established. Use of cefdinir for the treatment of acute maxillary sinusitis in pediatric patients (age 6 months through 12 years) is supported by evidence from adequate and well-controlled studies in adults and adolescents, the similar pathophysiology of acute sinusitis in adult and pediatric patients, and comparative pharmacokinetic data in the pediatric population.
🧓 Geriatric Use ▾
GERIATRIC USE Efficacy is comparable in geriatric patients and younger adults. While cefdinir has been well-tolerated in all age groups, in clinical trials geriatric patients experienced a lower rate of adverse events, including diarrhea, than younger adults. Dose adjustment in elderly patients is not necessary unless renal function is markedly compromised (see DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE Information on cefdinir overdosage in humans is not available. In acute rodent toxicity studies, a single oral 5600- mg/kg dose produced no adverse effects. Toxic signs and symptoms following overdosage with other β-lactam antibiotics have included nausea, vomiting, epigastric distress, diarrhea, and convulsions.
Hemodialysis removes cefdinir from the body. This may be useful in the event of a serious toxic reaction from overdosage, particularly if renal function is compromised.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Pharmacokinetics and Drug Metabolism Absorption Oral Bioavailability Maximal plasma cefdinir concentrations occur 2 to 4 hours postdose following capsule or suspension administration. Plasma cefdinir concentrations increase with dose, but the increases are less than dose-proportional from 300 mg (7 mg/kg) to 600 mg (14 mg/kg). Following administration of suspension to healthy adults, cefdinir bioavailability is 120% relative to capsules.
Estimated bioavailability of cefdinir capsules is 21% following administration of a 300 mg capsule dose, and 16% following administration of a 600 mg capsule dose. Estimated absolute bioavailability of cefdinir suspension is 25%. Cefdinir oral suspension of 250 mg/5 mL strength was shown to be bioequivalent to the 125 mg/5 mL strength in healthy adults under fasting conditions.
Effect of Food The C max and AUC of cefdinir from the capsules are reduced by 16% and 10%, respectively, when given with a high-fat meal. In adults given the 250 mg/5 mL oral suspension with a high-fat meal, the Cmax and AUC of cefdinir are reduced by 44% and 33%, respectively. The magnitude of these reductions is not likely to be clinically significant because the safety and efficacy studies of oral suspension in pediatric patients were conducted without regard to food intake.
Therefore, cefdinir may be taken without regard to food. Cefdinir Suspension Cefdinir plasma concentrations and pharmacokinetic parameter values following administration of single 7- and 14- mg/kg oral doses of cefdinir to pediatric subjects (age 6 months to 12 years) are presented in the following table: Mean (±SD) Plasma Cefdinir Pharmacokinetic Parameter Values Following Administration of Suspension to Pediatric Subjects Dose Cmax(mcg /mL) tmax(hr) AUC(mcg .hr/mL) 7 mg /kg 2.30 (0 .6 5) 2.2(0 .6 ) 8 .31(2.50 ) 14 mg /kg 3.8 6 (0 .6 2) 1.8 (0 .4 ) 13.4 (2.6 4 ) Multiple Dosing Cefdinir does not accumulate in plasma following once- or twice-daily administration to subjects with normal renal function.
Distribution The mean volume of distribution (Vd area ) of cefdinir in adult subjects is
0.35L/kg (±0.29); in pediatric subjects (age 6 months to 12 years), cefdinir Vd area is
0.67L/kg (±0.38). Cefdinir is 60% to 70% bound to plasma proteins in both adult and pediatric subjects; binding is independent of concentration. Skin Blister In adult subjects, median (range) maximal blister fluid cefdinir concentrations of 0.65 (0.33 to 1.1) and 1.1 (0.49 to 1.9) mcg/mL were observed 4 to 5 hours following administration of 300- and 600- mg doses, respectively.
Mean (±SD) blister C max and AUC (0-∞) values were 48% (±13) and 91% (±18) of corresponding plasma values. Tonsil Tissue In adult patients undergoing elective tonsillectomy, respective median tonsil tissue cefdinir concentrations 4 hours after administration of single 300- and 600- mg doses were 0.25 (0.22 to 0.46) and 0.36 (0.22 to 0.80) mcg/g. Mean tonsil tissue concentrations were 24% (±8) of corresponding plasma concentrations.
Sinus Tissue In adult patients undergoing elective maxillary and ethmoid sinus surgery, respective median sinus tissue cefdinir concentrations 4 hours after administration of single 300- and 600- mg doses were < 0.12 (< 0.12 to 0.46) and 0.21 (< 0.12 to 2.0) mcg/g. Mean sinus tissue concentrations were 16% (±20) of corresponding plasma concentrations. Lung Tissue In adult patients undergoing diagnostic bronchoscopy, respective median bronchial mucosa cefdinir concentrations 4 hours after administration of single 300- and 600- mg doses were 0.78 (< 0.06 to 1.33) and 1.14 (< 0.06 to 1.92) mcg/mL, and were 31% (±18) of corresponding plasma concentrations.
Respective median epithelial lining fluid concentrations were 0.29 (< 0.3 to 4.73) and 0.49 (< 0.3 to 0.59) mcg/mL, and were 35% (±83) of corresponding plasma concentrations. Middle Ear Fluid In 14 pediatric patients with acute bacterial otitis media, respective median middle ear fluid cefdinir concent…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Cefdinir for Oral Suspension USP is a off white to yellow free flowing powder filled in HDPE bottle that, when reconstituted as directed, contains 125 mg cefdinir/5 mL or 250 mg cefdinir/5 mL. The reconstituted suspensions have a off white to yellow colour and strawberry flavor. The powder is available as follows: Cefdinir for Oral Suspension USP 125 mg/5 mL 60 mL bottle: NDC 67877-547-98 100 mL bottle: NDC 67877-547-88 Cefdinir for Oral Suspension USP 250 mg/5 mL 60 mL bottle: NDC 67877-548-98 100 mL bottle: NDC 67877-548-88 Store unsuspended powder at 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Once reconstituted, the oral suspension can be stored at controlled room temperature for 10 days.
📋 Description ▾
DESCRIPTION Cefdinir for Oral Suspension USP contains the active ingredient cefdinir, an extended-spectrum, semisynthetic cephalosporin, for oral administration. Chemically, cefdinir is [6R-[6α, 7β (Z)]]-7-[[(2-amino-4-thiazolyl)(hydroxyimino)acetyl]amino]-3-ethenyl-8-oxo-5-thia-1-azabicyclo[4.2.0]oct-2-ene-2-carboxylic acid. Cefdinir is a white to slightly brownish-yellow solid. It is slightly soluble in dilute hydrochloric acid and sparingly soluble in
0.1M pH 7.0 phosphate buffer. The empirical formula is C 14 H 13 N 5 O 5 S 2 and the molecular weight is 395.42. Cefdinir has the structural formula shown below: Cefdinir for Oral Suspension USP, after reconstitution, contains 125 mg cefdinir per 5 mL or 250 mg cefdinir per 5 mL and the following inactive ingredients: sucrose, sodium benzoate, xanthan gum, guar gum, colloidal silicone dioxide, magnesium stearate, sodium citrate anhydrous, citric acid anhydrous and strawberry flavoring. cefdinir-structure
💬 Information for Patients ▾
INFORMATION FOR PATIENTS Patients should be counseled that antibacterial drugs including cefdinir should only be used to treat bacterial infections. They do not treat viral infections (e.g., the common cold). When cefdinir is prescribed to treat a bacterial infection, patients should be told that although it is common to feel better early in the course of therapy, the medication should be taken exactly as directed.
Skipping doses or not completing the full course of therapy may (1) decrease the effectiveness of the immediate treatment and (2) increase the likelihood that bacteria will develop resistance and will not be treatable by cefdinir or other antibacterial drugs in the future. Antacids containing magnesium or aluminum interfere with the absorption of cefdinir. If this type of antacid is required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the antacid.
Iron supplements, including multivitamins that contain iron, interfere with the absorption of cefdinir. If iron supplements are required during cefdinir therapy, cefdinir should be taken at least 2 hours before or after the supplement. Iron-fortified infant formula does not significantly interfere with the absorption of cefdinir.
Therefore, cefdinir for oral suspension can be administered with iron-fortified infant formula. Diabetic patients and caregivers should be aware that the oral suspension contains 2.86 g of sucrose per teaspoon. Diarrhea is a common problem caused by antibiotics which usually ends when the antibiotic is discontinued.
Sometimes after starting treatment with antibiotics, patients can develop watery and bloody stools (with or without stomach cramps and fever) even as late as two or more months after having taken the last dose of the antibiotic. If this occurs, patients should contact their physician as soon as possible.