
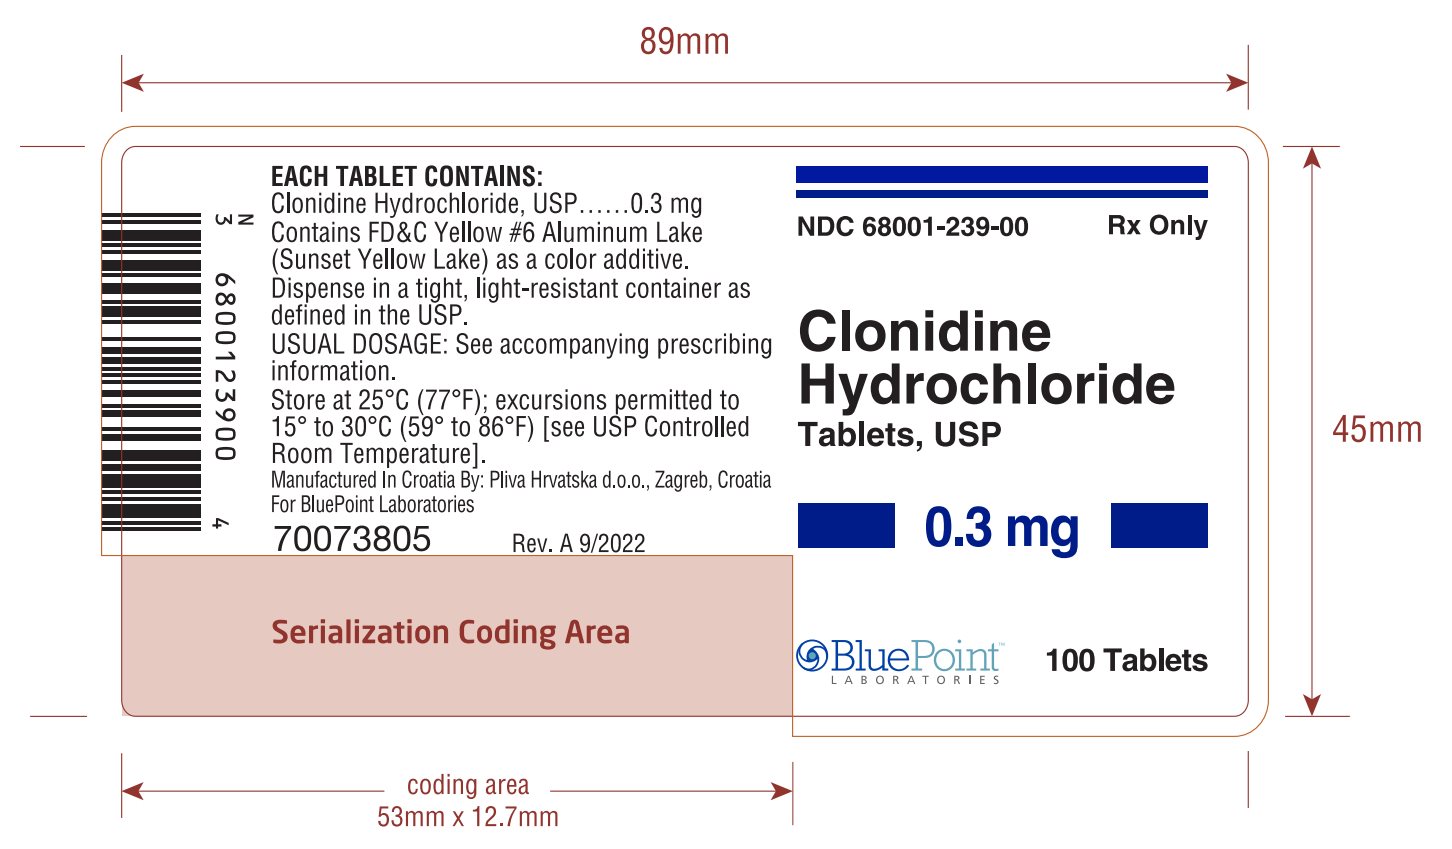
Clonidine Hydrochloride .3 mg Tablet, 100-count — NDC 68001-239-00 (Billing 68001-0239-00)
This is a package of 100 tablets of Clonidine Hydrochloride .3 mg Tablet from BluePoint Laboratories, marketed since Jan 1995 and currently FDA-listed; retail pharmacies pay about $0.0408 per tablet (NADAC). It is this product's only package size.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 000348
- GCN: 01392
- GPI-14 (Medi-Span): 36201010100315
- HICL (First Databank): 000113
- AHFS class code: 24:24.00.00
- RxCUI (RxNorm): 884173
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Central alpha-2 Adrenergic Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It depends on the product. Tablets, oral solutions, Nexiclon XR and patches lower high blood pressure. Certain extended-release products treat ADHD. The epidural injection is used...
- No. Stopping suddenly can cause rebound high blood pressure, with headache, a racing heart, nervousness and anxiety. Your doctor will lower the dose gradually.
- Sleepiness is common. Don't drive or use heavy equipment until you know how it affects you. Avoid alcohol, and ask me before combining it with other sedating medicines.
- No. Extended-release clonidine tablets should be swallowed whole, not crushed, chewed or broken. They can be taken with or without food.
Patient education
Supplement & herbal interactions
Clonidine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.041 | $4.08 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2293 | $22.93 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.0688 | $6.88 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68001-0239-00 You're viewing this Main listing | 100 TABLET in 1 BOTTLE | 1995-01-03 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Clonidine Hydrochloride .3 mg 00228-2129-10 | Actavis | 100 tablets | $0.041 | AB | Availability likely | — |
| clonidine hydrochloride .3 mg 29300-0137-01 | Unichem | 100 tablets | $0.041 | AB | Availability likely | — |
| Clonidine Hydrochloride .3 mg 43547-0567-10 | Solco | 100 tablets | $0.041 | AB | Availability likely | — |
| clonidine hydrochloride .3 mg 50268-0194-15 | AvPAK | 50 tablets | $0.041 | AB | Availability likely | — |
| Clonidine hydrochloride .3 mg 52817-0182-00 | TruPharma, | 1000 tablets | $0.041 | — | Availability likely | — |
| Clonidine Hydrochloride .3 mg 58657-0649-01 | Method | 100 tablets | $0.041 | AB | Availability likely | — |
| Clonidine Hydrochloride .3 mg 59651-0234-01 | Aurobindo | 100 tablets | $0.041 | AB | Availability likely | — |
| Clonidine Hydrochloride .3 mgthis 68001-0239-00 | BluePoint | 100 tablets | $0.041 | AB | Availability likely | — |
| clonidine hydrochloride .3 mg 43063-0924-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Clonidine Hydrochloride .3 mg 43353-0316-09 | Aphena | 9000 tablets | — | AB | FDA listed | — |
| clonidine hydrochloride .3 mg 46708-0308-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| clonidine hydrochloride .3 mg 50090-1910-00 | A-S | 100 tablets | — | AB | FDA listed | — |
| clonidine hydrochloride .3 mg 51655-0339-25 | Northwind | 60 tablets | — | AB | FDA listed | — |
| Clonidine hydrochloride .3 mg 51655-0451-25 | Northwind | 60 tablets | — | — | FDA listed | — |
| clonidine hydrochloride .3 mg 62332-0056-10 | Alembic | 100 tablets | — | AB | FDA listed | — |
| Clonidine Hydrochloride .3 mg 63629-2318-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Clonidine Hydrochloride .3 mg 63629-2319-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| clonidine hydrochloride .3 mg 66267-0464-90 | NuCare | 90 tablets | — | AB | FDA listed | — |
| clonidine hydrochloride .3 mg 68788-8163-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| clonidine hydrochloride .3 mg 70518-2203-01 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Clonidine Hydrochloride .3 mg 70518-4379-00 | REMEDYREPACK | 60 tablets | — | AB | FDA listed | — |
| clonidine hydrochloride .3 mg 71335-0915-01 | Bryant | 60 tablets | — | AB | Discontinued | — |
| Clonidine hydrochloride .3 mg 71335-1624-01 | Bryant | 60 tablets | — | — | Discontinued | — |
| Clonidine Hydrochloride .3 mg 71335-2889-01 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Clonidine Hydrochloride .3 mg 71335-9682-01 | Bryant | 60 tablets | — | AB | FDA listed | — |
| Clonidine hydrochloride .3 mg 71610-0449-09 | Aphena | 9000 tablets | — | — | FDA listed | — |
| Clonidine Hydrochloride .3 mg 72162-1681-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Clonidine Hydrochloride .3 mg 72162-2611-05 | Bryant | 500 tablets | — | AB | FDA listed | — |
| Clonidine hydrochloride .3 mg 76420-0286-01 | Asclemed | 100 tablets | — | — | FDA listed | — |
| clonidine hydrochloride .3 mg 87063-0183-01 | ASCLEMED | 100 tablets | — | AB | FDA listed | — |
| Clonidine Hydrochloride .3 mg 00615-2574-39 | NCS | 30 tablets | — | AB | Discontinued | — |
| clonidine hydrochloride .3 mg 67046-0646-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Clonidine hydrochloride tablets are indicated in the treatment of hypertension. Clonidine hydrochloride tablets may be employed alone or concomitantly with other antihypertensive agents.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Adults: The dose of clonidine hydrochloride tablets must be adjusted according to the patient’s individual blood pressure response. The following is a general guide to its administration. Initial Dose: 0.1 mg tablet twice daily (morning and bedtime).
Elderly patients may benefit from a lower initial dose. Maintenance Dose: Further increments of 0.1 mg per day may be made at weekly intervals if necessary until the desired response is achieved. Taking the larger portion of the oral daily dose at bedtime may minimize transient adjustment effects of dry mouth and drowsiness.
The therapeutic doses most commonly employed have ranged from 0.2 mg to 0.6 mg per day given in divided doses. Studies have indicated that 2.4 mg is the maximum effective daily dose, but doses as high as this have rarely been employed. Renal Impairment: Patients with renal impairment may benefit from a lower initial dose.
Patients should be carefully monitored. Since only a minimal amount of clonidine is removed during routine hemodialysis, there is no need to give supplemental clonidine following dialysis. For questions regarding this product, call Teva at 1-888-838-2872.
⛔ Contraindications ▾
CONTRAINDICATIONS Clonidine hydrochloride tablets should not be used in patients with known hypersensitivity to clonidine (see PRECAUTIONS ).
⚠️ Warnings ▾
WARNINGS Withdrawal Patients should be instructed not to discontinue therapy without consulting their physician. Sudden cessation of clonidine treatment has, in some cases, resulted in symptoms such as nervousness, agitation, headache, and tremor accompanied or followed by a rapid rise in blood pressure and elevated catecholamine concentrations in the plasma. The likelihood of such reactions to discontinuation of clonidine therapy appears to be greater after administration of higher doses or continuation of concomitant beta-blocker treatment and special caution is therefore advised in these situations.
Rare instances of hypertensive encephalopathy, cerebrovascular accidents and death have been reported after clonidine withdrawal. When discontinuing therapy with clonidine hydrochloride tablets, the physician should reduce the dose gradually over 2 to 4 days to avoid withdrawal symptomatology. An excessive rise in blood pressure following discontinuation of clonidine hydrochloride tablets therapy can be reversed by administration of oral clonidine hydrochloride or by intravenous phentolamine.
If therapy is to be discontinued in patients receiving a beta-blocker and clonidine concurrently, the beta-blocker should be withdrawn several days before the gradual discontinuation of clonidine hydrochloride tablets. Because children commonly have gastrointestinal illnesses that lead to vomiting, they may be particularly susceptible to hypertensive episodes resulting from abrupt inability to take medication.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Most adverse effects are mild and tend to diminish with continued therapy. The most frequent (which appear to be dose-related) are dry mouth, occurring in about 40 of 100 patients; drowsiness, about 33 in 100; dizziness, about 16 in 100; constipation and sedation, each about 10 in 100. The following less frequent adverse experiences have also been reported in patients receiving clonidine hydrochloride tablets, but in many cases patients were receiving concomitant medication and a causal relationship has not been established.
Body as a Whole: Fatigue, fever, headache, pallor, weakness, and withdrawal syndrome. Also reported were a weakly positive Coombs’ test and increased sensitivity to alcohol. Cardiovascular: Bradycardia, congestive heart failure, electrocardiographic abnormalities (i.e., sinus node arrest, junctional bradycardia, high degree AV block and arrhythmias), orthostatic symptoms, palpitations, Raynaud’s phenomenon, syncope, and tachycardia.
Cases of sinus bradycardia and atrioventricular block have been reported, both with and without the use of concomitant digitalis. Central Nervous System: Agitation, anxiety, delirium, delusional perception, hallucinations (including visual and auditory), insomnia, mental depression, nervousness, other behavioral changes, paresthesia, restlessness, sleep disorder, and vivid dreams or nightmares. Dermatological: Alopecia, angioneurotic edema, hives, pruritus, rash, and urticaria.
Gastrointestinal: Abdominal pain, anorexia, constipation, hepatitis, malaise, mild transient abnormalities in liver function tests, nausea, parotitis, pseudo-obstruction (including colonic pseudo-obstruction), salivary gland pain, and vomiting. Genitourinary: Decreased sexual activity, difficulty in micturition, erectile dysfunction, loss of libido, nocturia, and urinary retention. Hematologic: Thrombocytopenia.
Metabolic: Gynecomastia, transient elevation of blood glucose or serum creatine phosphokinase, and weight gain. Musculoskeletal: Leg cramps and muscle or joint pain. Oro-otolaryngeal: Dryness of the nasal mucosa.
Ophthalmological: Accommodation disorder, blurred vision, burning of the eyes, decreased lacrimation, and dryness of eyes. To report SUSPECTED ADVERSE EVENTS, contact Teva at 1-888-838-2872 or FDA at 1-800-FDA-1088 or http://www.fda.gov/medwatch for voluntary reporting of adverse reactions.
🔄 Drug Interactions ▾
Drug Interactions Clonidine may potentiate the CNS-depressive effects of alcohol, barbiturates or other sedating drugs. If a patient receiving clonidine hydrochloride is also taking tricyclic antidepressants, the hypotensive effect of clonidine may be reduced, necessitating an increase in the clonidine dose. If a patient receiving clonidine is also taking neuroleptics, orthostatic regulation disturbances (e.g., orthostatic hypotension, dizziness, fatigue) may be induced or exacerbated.
Monitor heart rate in patients receiving clonidine concomitantly with agents known to affect sinus node function or AV nodal conduction, e.g., digitalis, calcium channel blockers, and beta-blockers. Sinus bradycardia resulting in hospitalization and pacemaker insertion has been reported in association with the use of clonidine concomitantly with diltiazem or verapamil. Amitriptyline in combination with clonidine enhances the manifestation of corneal lesions in rats (see Toxicology ).
Based on observations in patients in a state of alcoholic delirium it has been suggested that high intravenous doses of clonidine may increase the arrhythmogenic potential (QT-prolongation, ventricular fibrillation) of high intravenous doses of haloperidol. Causal relationship and relevance for clonidine oral tablets have not been established. Toxicology In several studies with oral clonidine hydrochloride, a dose-dependent increase in the incidence and severity of spontaneous retinal degeneration was seen in albino rats treated for six months or longer.
Tissue distribution studies in dogs and monkeys showed a concentration of clonidine in the choroid. In view of the retinal degeneration seen in rats, eye examinations were performed during clinical trials in 908 patients before, and periodically after, the start of clonidine therapy. In 353 of these 908 patients, the eye examinations were carried out over periods of 24 months or longer.
Except for some dryness of the eyes, no drug-related abnormal ophthalmological findings were recorded and, according to specialized tests such as electroretinography and macular dazzle, retinal function was unchanged. In combination with amitriptyline, clonidine hydrochloride administration led to the development of corneal lesions in rats within 5 days.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Reproduction studies performed in rabbits at doses up to approximately 3 times the oral maximum recommended daily human dose (MRDHD) of clonidine hydrochloride tablets produced no evidence of a teratogenic or embryotoxic potential in rabbits. In rats, however, doses as low as 1/3 the oral MRDHD (1/15 the MRDHD on a mg/m 2 basis) of clonidine were associated with increased resorptions in a study in which dams were treated continuously from 2 months prior to mating. Increased resorptions were not associated with treatment at the same time or at higher dose levels (up to 3 times the oral MRDHD) when the dams were treated on gestation days 6 to 15.
Increases in resorption were observed at much higher dose levels (40 times the oral MRDHD on a mg/kg basis; 4 to 8 times the MRDHD on a mg/m 2 basis) in mice and rats treated on gestation days 1 to 14 (lowest dose employed in the study was 500 mcg/kg). No adequate, well-controlled studies have been conducted in pregnant women. Clonidine crosses the placental barrier (see CLINICAL PHARMACOLOGY, Pharmacokinetics ).
Because animal reproduction studies are not always predictive of human response, this drug should be used during pregnancy only if clearly needed.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established in adequate and well-controlled trials (see WARNINGS, Withdrawal ).
🆘 Overdosage ▾
OVERDOSAGE Hypertension may develop early and may be followed by hypotension, bradycardia, respiratory depression, hypothermia, drowsiness, decreased or absent reflexes, weakness, irritability and miosis. The frequency of CNS depression may be higher in children than adults. Large overdoses may result in reversible cardiac conduction defects or dysrhythmias, apnea, coma and seizures.
Signs and symptoms of overdose generally occur within 30 minutes to two hours after exposure. As little as 0.1 mg of clonidine has produced signs of toxicity in children. There is no specific antidote for clonidine overdosage.
Clonidine overdosage may result in the rapid development of CNS depression; therefore, induction of vomiting with ipecac syrup is not recommended. Gastric lavage may be indicated following recent and/or large ingestions. Administration of activated charcoal and/or a cathartic may be beneficial.
Supportive care may include atropine sulfate for bradycardia, intravenous fluids and/or vasopressor agents for hypotension and vasodilators for hypertension. Naloxone may be a useful adjunct for the management of clonidine-induced respiratory depression, hypotension and/or coma; blood pressure should be monitored since the administration of naloxone has occasionally resulted in paradoxical hypertension. Tolazoline administration has yielded inconsistent results and is not recommended as first-line therapy.
Dialysis is not likely to significantly enhance the elimination of clonidine. The largest overdose reported to date involved a 28-year old male who ingested 100 mg of clonidine hydrochloride powder. This patient developed hypertension followed by hypotension, bradycardia, apnea, hallucinations, semicoma, and premature ventricular contractions.
The patient fully recovered after intensive treatment. Plasma clonidine levels were 60 ng/mL after 1 hour, 190 ng/mL after 1.5 hours, 370 ng/mL after 2 hours, and 120 ng/mL after 5.5 and 6.5 hours. In mice and rats, the oral LD 50 of clonidine is 206 and 465 mg/kg, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Clonidine stimulates alpha-adrenoreceptors in the brain stem. This action results in reduced sympathetic outflow from the central nervous system and in decreases in peripheral resistance, renal vascular resistance, heart rate, and blood pressure. Clonidine hydrochloride tablets act relatively rapidly.
The patient’s blood pressure declines within 30 to 60 minutes after an oral dose, the maximum decrease occurring within 2 to 4 hours. Renal blood flow and glomerular filtration rate remain essentially unchanged. Normal postural reflexes are intact; therefore, orthostatic symptoms are mild and infrequent.
Acute studies with clonidine hydrochloride in humans have demonstrated a moderate reduction (15% to 20%) of cardiac output in the supine position with no change in the peripheral resistance: at a 45 degree tilt there is a smaller reduction in cardiac output and a decrease of peripheral resistance. During long term therapy, cardiac output tends to return to control values, while peripheral resistance remains decreased. Slowing of the pulse rate has been observed in most patients given clonidine, but the drug does not alter normal hemodynamic response to exercise.
Tolerance to the antihypertensive effect may develop in some patients, necessitating a reevaluation of therapy. Other studies in patients have provided evidence of a reduction in plasma renin activity and in the excretion of aldosterone and catecholamines. The exact relationship of these pharmacologic actions to the antihypertensive effect of clonidine has not been fully elucidated.
Clonidine acutely stimulates growth hormone release in both children and adults, but does not produce a chronic elevation of growth hormone with long-term use. Pharmacokinetics The pharmacokinetics of clonidine is dose-proportional in the range of 100 mcg to 600 mcg. The absolute bioavailability of clonidine on oral administration is 70% to 80%.
Peak plasma clonidine levels are attained in approximately 1 to 3 hours. Following intravenous administration, clonidine displays biphasic disposition with a distribution half-life of about 20 minutes and an elimination half-life ranging from 12 to 16 hours. The half-life increases up to 41 hours in patients with severe impairment of renal function.
Clonidine crosses the placental barrier. It has been shown to cross the blood-brain barrier in rats. Following oral administration about 40% to 60% of the absorbed dose is recovered in the urine as unchanged drug in 24 hours.
About 50% of the absorbed dose is metabolized in the liver. Neither food nor the race of the patient influences the pharmacokinetics of clonidine. The antihypertensive effect is reached at plasma concentrations between about 0.2 and 2.0 ng/mL in patients with normal excretory function.
A further rise in the plasma levels will not enhance the antihypertensive effect.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Clonidine hydrochloride tablets, USP are supplied as follows: 0.1 mg — Each orange, round tablet imprinted with and 127 on one side and bisect on the other side contains 0.1 mg of clonidine hydrochloride, USP and is supplied in bottles of 100 (NDC 68001-237-00) and 500 (NDC 68001-237-03). 0.2 mg — Each orange, round tablet imprinted with on one side and 128 and bisect on the other side contains 0.2 mg of clonidine hydrochloride, USP and is supplied in bottles of 100 (NDC 68001-238-00) and 500 (NDC 68001-238-03).
0.3mg — Each orange, round tablet imprinted with on one side and 129 and bisect on the other side contains 0.3 mg of clonidine hydrochloride, USP and is supplied in bottles of 100 (NDC 68001-239-00). Dispense in a tight, light-resistant container as defined in the USP. Store at 25°C (77ºF); excursions permitted to 15º to 30ºC (59º to 86ºF) [see USP Controlled Room Temperature].
Manufactured In Croatia By: Pliva Hrvatska d.o.o. Zagreb, Croatia For BluePoint Laboratories Rev. A 9/2022 18ddb7fd-figure-02 18ddb7fd-figure-03 18ddb7fd-figure-04
📋 Description ▾
DESCRIPTION Clonidine hydrochloride, USP is a centrally acting alpha-agonist hypotensive agent available as tablets for oral administration in three dosage strengths: 0.1 mg, 0.2 mg, and 0.3 mg. The 0.1 mg tablet is equivalent to 0.087 mg of the free base. The following inactive ingredients are contained in these products: corn starch, D&C Yellow #10 Aluminum Lake, FD&C Yellow #6 Aluminum Lake (Sunset Yellow Lake), lactose monohydrate, magnesium stearate, and sodium starch glycolate.
Clonidine hydrochloride, USP is an imidazoline derivative and exists as a mesomeric compound. The chemical name is 2-(2,6-dichlorophenylamino)-2-imidazoline hydrochloride. The following is the structural formula: Clonidine hydrochloride, USP is an odorless, bitter, white, crystalline substance soluble in water and alcohol.
18ddb7fd-figure-01
💬 Information for Patients ▾
Information for Patients Patients should be cautioned against interruption of clonidine hydrochloride tablets therapy without their physician’s advice. Since patients may experience a possible sedative effect, dizziness, or accommodation disorder with use of clonidine, caution patients about engaging in activities such as driving a vehicle or operating appliances or machinery. Also, inform patients that this sedative effect may be increased by concomitant use of alcohol, barbiturates, or other sedating drugs.
Patients who wear contact lenses should be cautioned that treatment with clonidine hydrochloride tablets may cause dryness of eyes.
⚠️ Precautions ▾
PRECAUTIONS General In patients who have developed localized contact sensitization to transdermal clonidine, continuation of transdermal clonidine or substitution of oral clonidine hydrochloride therapy may be associated with the development of a generalized skin rash. In patients who develop an allergic reaction to transdermal clonidine, substitution of oral clonidine hydrochloride may also elicit an allergic reaction (including generalized rash, urticaria, or angioedema). The sympatholytic action of clonidine may worsen sinus node dysfunction and atrioventricular (AV) block, especially in patients taking other sympatholytic drugs.
There are postmarketing reports of patients with conduction abnormalities and/or taking other sympatholytic drugs who developed severe bradycardia requiring IV atropine, IV isoproterenol and temporary cardiac pacing while taking clonidine. In hypertension caused by pheochromocytoma, no therapeutic effect of clonidine hydrochloride tablets can be expected. Perioperative Use Administration of clonidine hydrochloride tablets should be continued to within 4 hours of surgery and resumed as soon as possible thereafter.
Blood pressure should be carefully monitored during surgery and additional measures to control blood pressure should be available if required. Information for Patients Patients should be cautioned against interruption of clonidine hydrochloride tablets therapy without their physician’s advice. Since patients may experience a possible sedative effect, dizziness, or accommodation disorder with use of clonidine, caution patients about engaging in activities such as driving a vehicle or operating appliances or machinery.
Also, inform patients that this sedative effect may be increased by concomitant use of alcohol, barbiturates, or other sedating drugs. Patients who wear contact lenses should be cautioned that treatment with clonidine hydrochloride tablets may cause dryness of eyes. Drug Interactions Clonidine may potentiate the CNS-depressive effects of alcohol, barbiturates or other sedating drugs.
If a patient receiving clonidine hydrochloride is also taking tricyclic antidepressants, the hypotensive effect of clonidine may be reduced, necessitating an increase in the clonidine dose. If a patient receiving clonidine is also taking neuroleptics, orthostatic regulation disturbances (e.g., orthostatic hypotension, dizziness, fatigue) may be induced or exacerbated. Monitor heart rate in patients receiving clonidine concomitantly with agents known to affect sinus node function or AV nodal conduction, e.g., digitalis, calcium channel blockers, and beta-blockers.
Sinus bradycardia resulting in hospitalization and pacemaker insertion has been reported in association with the use of clonidine concomitantly with diltiazem or verapamil. Amitriptyline in combination with clonidine enhances the manifestation of corneal lesions in rats (see Toxicology ). Based on observations in patients in a state of alcoholic delirium it has been suggested that high intravenous doses of clonidine may increase the arrhythmogenic potential (QT-prolongation, ventricular fibrillation) of high intravenous doses of haloperidol.
Causal relationship and relevance for clonidine oral tablets have not been established. Toxicology In several studies with oral clonidine hydrochloride, a dose-dependent increase in the incidence and severity of spontaneous retinal degeneration was seen in albino rats treated for six months or longer. Tissue distribution studies in dogs and monkeys showed a concentration of clonidine in the choroid.
In view of the retinal degeneration seen in rats, eye examinations were performed during clinical trials in 908 patients before, and periodically after, the start of clonidine therapy. In 353 of these 908 patients, the eye examinations were carried out over periods of 24 months or longer. Except for some dryness of the eyes, no drug-related abnormal ophthalmological findings were recorded and, according to… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers As clonidine hydrochloride is excreted in human milk, caution should be exercised when clonidine hydrochloride tablets are administered to a nursing woman.
🧬 Pharmacokinetics ▾
Pharmacokinetics The pharmacokinetics of clonidine is dose-proportional in the range of 100 mcg to 600 mcg. The absolute bioavailability of clonidine on oral administration is 70% to 80%. Peak plasma clonidine levels are attained in approximately 1 to 3 hours.
Following intravenous administration, clonidine displays biphasic disposition with a distribution half-life of about 20 minutes and an elimination half-life ranging from 12 to 16 hours. The half-life increases up to 41 hours in patients with severe impairment of renal function. Clonidine crosses the placental barrier.
It has been shown to cross the blood-brain barrier in rats. Following oral administration about 40% to 60% of the absorbed dose is recovered in the urine as unchanged drug in 24 hours. About 50% of the absorbed dose is metabolized in the liver.
Neither food nor the race of the patient influences the pharmacokinetics of clonidine. The antihypertensive effect is reached at plasma concentrations between about 0.2 and 2.0 ng/mL in patients with normal excretory function. A further rise in the plasma levels will not enhance the antihypertensive effect.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Chronic dietary administration of clonidine was not carcinogenic to rats (132 weeks) or mice (78 weeks) dosed, respectively, at up to 46 or 70 times the maximum recommended daily human dose as mg/kg (9 or 6 times the MRDHD on a mg/m 2 basis). There was no evidence of genotoxicity in the Ames test for mutagenicity or mouse micronucleus test for clastogenicity. Fertility of male or female rats was unaffected by clonidine doses as high as 150 mcg/kg (approximately 3 times MRDHD).
In a separate experiment, fertility of female rats appeared to be affected at dose levels of 500 mcg/kg to 2000 mcg/kg (10 to 40 times the oral MRDHD on a mg/kg basis; 2 to 8 times the MRDHD on a mg/m 2 basis).
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 68001-237-00 Rx Only Clonidine Hydrochloride Tablets, USP 0.1 mg 100 Tablets BluePoint 0.1mg 100s
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 68001-238-00 Rx Only Clonidine Hydrochloride Tablets, USP 0.2 mg 100 Tablets BluePoint 0.2mg 100s
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 68001-239-00 Rx Only Clonidine Hydrochloride Tablets, USP 0.3 mg 100 Tablets BluePoint 0.3mg 100s