
Tacrolimus 1 mg Capsule, 30-count
Other active recalls for Tacrolimus (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Calcineurin Inhibitor Immunosuppressant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Tacrolimus (Astagraf XL, Envarsus XR, Prograf) is used along with other medications to prevent rejection (attack of a transplanted organ by the immune system of a person receiving the organ) in people who have received a kidney transplant. Tacrolimus (Prograf) is also used along with other medications to prevent rejection in people who have received a liver, lung, or heart transplant. Tacrolimus is in a class of medications called immunosupressants. It works by decreasing the activity of the immune system to prevent it from attacking the transplanted organ.
Read the full MedlinePlus article ↗- That's a great question, and it's one of the most important things to understand. Your body's immune system doesn't just stop trying to attack the new organ once you leave the hosp...
- Why do I have to take tacrolimus even when I feel completely fine?
- It actually does matter — but the key is being consistent, not choosing one over the other. Food can change how much tacrolimus your body absorbs, so if you always take it the same...
- Does it matter if I take tacrolimus with food or on an empty stomach?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Tacrolimus — tap one for details:
Tacrolimus may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 5138Q19F1X
Ammonia is a colorless gas made from nitrogen and hydrogen. It's used in medicines as a pH buffer to maintain the correct acidity level and help keep the product stable.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3779 | $11.34 / 30 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Tacrolimus 1 mg 00378-2046-01 | Mylan | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 00781-2103-01 | Sandoz | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 00904-7097-61 | Major | 100 capsules | $0.152 | AB | Availability likely | — |
| tacrolimus 1 mg 16714-0099-01 | NORTHSTAR | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 51079-0818-20 | MylanInstitutional | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 55111-0526-01 | Dr. | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 59746-0799-01 | Jubilant | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 67877-0279-01 | Ascend | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 68084-0450-01 | American | 100 capsules | $0.152 | AB | Availability likely | — |
| tacrolimus 1 mg 68462-0686-01 | Glenmark | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 70377-0015-11 | Biocon | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 82009-0054-01 | Quallent | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 85972-0102-01 | Stellon | 100 capsules | $0.152 | AB | Availability likely | — |
| Tacrolimus 1 mg 16729-0042-01 | Accord | 100 capsules | $0.161 | BX | Availability likely | — |
| Prograf 1 mg 00469-0617-73 | Astellas | 100 capsules | $7.315 | AB | Availability likely | — |
| Tacrolimus 1 mg 43353-0317-09 | Aphena | 9000 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 43817-0422-01 | Panacea | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 48433-0093-20 | Safecor | 100 capsules | — | AB | FDA listed | — |
| tacrolimus 1 mg 50090-5581-00 | A-S | 90 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 50090-5596-00 | A-S | 90 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 54288-0135-01 | BPI | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 55154-4080-08 | Cardinal | 2000 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 55154-4168-00 | Cardinal | 10 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 60429-0378-01 | Golden | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 63629-8723-01 | Bryant | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 63629-9325-01 | Bryant | 60 capsules | — | BX | FDA listed | — |
| Tacrolimus 1 mg 64380-0721-01 | Strides | 100 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 65897-0010-02 | Hangzhou | 100 capsules | — | — | FDA listed | — |
| Tacrolimus 1 mgthis 68254-5005-05 | CONCORD | 30 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 72189-0536-30 | Direct_Rx | 30 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 82804-0032-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Tacrolimus 1 mg 82983-0401-10 | Ajenat | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 68254-5005-01 | 100 CAPSULE in 1 BOTTLE (68254-5005-1) | 2020-11-23 | Active |
| 68254-5005-05 You're viewing this | 30 CAPSULE in 1 BOTTLE (68254-5005-5) | 2020-11-23 | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 68254-5005-05?
What is the difference between NDC 68254-5005-05 and NDC 68254-5005-01?
What NDC number is used to bill for this package of Tacrolimus 1 mg Capsule?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: MALIGNANCIES AND SERIOUS INFECTIONS Increased risk for developing serious infections and malignancies with Tacrolimus or other immunosuppressants that may lead to hospitalization or death. ( 5.1 , 5.2 ) WARNING: MALIGNANCIES AND SERIOUS INFECTIONS See full prescribing information for complete boxed warning. Increased risk for developing serious infections and malignancies with Tacrolimus or other immunosuppressants that may lead to hospitalization or death.
( 5.1 , 5.2 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Tacrolimus capsules are a calcineurin-inhibitor immunosuppressant indicated for the prophylaxis of organ rejection in adult patients receiving allogeneic liver, kidney or heart transplants, and pediatric patients receiving allogeneic liver transplants in combination with other immunosuppressants. ( 1.1 )
1.1Prophylaxis of Organ Rejection in Kidney, Liver or Heart Transplant Tacrolimus capsules are indicated for the prophylaxis of organ rejection, in adult patients receiving allogeneic kidney transplant [see Clinical Studies (14.1)] , liver transplant [see Clinical Studies (14.2)] , heart transplant [see Clinical Studies (14.3)] , and pediatric patients receiving allogeneic liver transplant [see Clinical Studies (14.2)] in combination with other immunosuppressants. Additional pediatric use information is approved for Astellas Pharma US, Inc.'s Prograf (tacrolimus) products.
However, due to Astellas Pharma US, Inc.'s marketing exclusivity rights, this drug product is not labeled with that information.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Intravenous (IV) use recommended for patients who cannot tolerate oral formulations (capsules). ( 2.1 , 2.2 ) Administer capsules consistently with or without food. ( 2.1 ) Therapeutic drug monitoring is recommended.
( 2.1 , 2.6 ) Avoid eating grapefruit or drinking grapefruit juice. ( 2.1 ) See dosage adjustments for African-American patients ( 2.2 ), hepatic and renal impaired. ( 2.4 , 2.5 ) For complete dosing information, see the full prescribing information.
ADULT Patient Population Initial Oral Dosage (formulation) Whole Blood Trough Concentration Range Kidney Transplant With azathioprine 0.2 mg/kg/day capsules, divided in two doses, every 12 hours Month 1-3: 7-20 ng/mL Month 4-12: 5-15 ng/mL With MMF/IL-2 receptor antagonist 0.1 mg/kg/day capsules, divided in two doses, every 12 hours Month 1-12: 4-11 ng/mL Liver Transplant With corticosteroids only 0.1-0.15 mg/kg/day capsules, divided in two doses, every 12 hours Month 1-12: 5-20 ng/mL Heart Transplant With azathioprine or MMF 0.075 mg/kg/day capsules, divided in two doses, every 12 hours Month 1-3: 10-20 ng/mL Month ≥ 4: 5-15 ng/mL MMF= Mycophenolate mofetil PEDIATRIC Patient Population Initial Oral Dosage (formulation) Whole Blood Trough Concentration Range Liver Transplant 0.15-0.2 mg/kg/day capsules divided in two doses, every 12 hours Month 1-12: 5-20 ng/mL
2.1Important Administration Instructions Tacrolimus capsules should not be used without supervision by a physician with experience in immunosuppressive therapy. Tacrolimus capsules are not interchangeable or substitutable for other tacrolimus extended-release products. This is because rate of absorption following the administration of an extended-release tacrolimus product is not equivalent to that of an immediate-release tacrolimus drug product.
Under- or overexposure to tacrolimus may result in graft rejection or other serious adverse reactions. Changes between tacrolimus immediate-release and extended release dosage forms must occur under physician supervision [see Warnings and Precautions (5.3) ] . Intravenous Formulation - Administration Precautions due to Risk of Anaphylaxis Intravenous use is recommended for patients who cannot tolerate oral formulations, and conversion from intravenous to oral tacrolimus is recommended as soon as oral therapy can be tolerated to minimize the risk of anaphylactic reactions that occurred with injectables containing castor oil derivatives [see Warnings and Precautions (5.9) ] .
Patients receiving Tacrolimus injection should be under continuous observation for at least the first 30 minutes following the start of the infusion and at frequent intervals thereafter. If signs or symptoms of anaphylaxis occur, the infusion should be stopped. An aqueous solution of epinephrine should be available at the bedside as well as a source of oxygen.
Oral Formulation (Capsules) If patients are able to initiate oral therapy, the recommended starting doses should be initiated. Tacrolimus capsules may be taken with or without food. However, since the presence of food affects the bioavailability of Tacrolimus, if taken with food, it should be taken consistently the same way each time [ see ClinicalPharmacology (12.3) ].
General Administration Instructions Patients should not eat grapefruit or drink grapefruit juice in combination with Tacrolimus [ see Drug Interactions (7.2) ]. Tacrolimus should not be used simultaneously with cyclosporine. Tacrolimus or cyclosporine should be discontinued at least 24 hours before initiating the other.
In the presence of elevated Tacrolimus or cyclosporine concentrations, dosing with the other drug usually should be further delayed. Therapeutic drug monitoring (TDM) is recommended for all patients receiving tacrolimus capsules [ see Dosage and Administration (2.6) ].
2.2Dosage Recommendations for Adult Kidney, Liver or Heart Transplant Patients - Capsules and Injection Capsules If patients are able to tolerate oral therapy, the re…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Tacrolimus capsules USP, are available in 0.5 mg, 1 mg, and 5 mg strengths. Tacrolimus capsules USP, 0.5mg: Opaque light yellow color, size "4" hard gelatin capsules imprinted with "C5" "0.5mg" on cap with black ink, containing white to off white granular powder. Tacrolimus capsules USP, 1mg: Opaque white color, size "4" hard gelatin capsules imprinted with "C6" "1 mg" on cap with black ink, containing white to off white granular powder.
Tacrolimus capsules USP, 5mg: Opaque grayish red color, size "4" hard gelatin capsules imprinted with "C7'' "5mg" on cap with black ink, containing white to off white granular powder. Capsules: 0.5 mg, 1 mg and 5 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Hypersensitivity to tacrolimus or HCO-60 (polyoxyl 60 hydrogenated castor oil). ( 4 ) Tacrolimus capsules are contraindicated in patients with a hypersensitivity to tacrolimus. Tacrolimus injection is contraindicated in patients with a hypersensitivity to HCO-60 (polyoxyl 60 hydrogenated castor oil). Hypersensitivity symptoms reported include dyspnea, rash, pruritus, and acute respiratory distress syndrome [see Adverse Reactions (6) ] .
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Not Interchangeable with Extended-Release Tacrolimus Products- Medication Errors: Instruct patients or caregivers to recognize the appearance of Tacrolimus capsules. ( 5.3 ) New Onset Diabetes After Transplant: Monitor blood glucose. ( 5.4 ) Nephrotoxicity (acute and/or chronic): Reduce the dose; use caution with other nephrotoxic drugs.
( 5.5 ) Neurotoxicity: Including risk of Posterior Reversible Encephalopathy Syndrome (PRES); monitor for neurologic abnormalities; reduce or discontinue tacrolimus capsules. ( 5.6 ) Hyperkalemia: Monitor serum potassium levels. Consider carefully before using with other agents also associated with hyperkalemia.
( 5.7 ) Hypertension: May require antihypertensive therapy. Monitor relevant drug-drug interactions. ( 5.8 ) Anaphylactic Reactions with IV formulation: Observe patients receiving tacrolimus injection for signs and symptoms of anaphylaxis.
( 5.9 ) Not recommended for use with sirolimus: Not recommended in liver and heart transplant due to increased risk of serious adverse reactions. ( 5.10 ) Myocardial Hypertrophy: Consider dose reduction/discontinuation. ( 5.13 ) Immunizations: Avoid live vaccines.
( 5.14 ) Pure Red Cell Aplasia: Consider discontinuation of tacrolimus. ( 5.15 ) Thrombotic Microangiopathy, Including Hemolytic Uremic Syndrome and Thrombotic Thrombocytopenic Purpura: May occur, especially in patients with infections and certain concomitant medications. ( 5.16 )
5.1Lymphoma and Other Malignancies Patients receiving immunosuppressants, including tacrolimus, are at increased risk of developing lymphomas and other malignancies, particularly of the skin . The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent. As usual for patients with increased risk for skin cancer, examine patients for skin changes; exposure to sunlight and UV light should be limited by wearing protective clothing and using a broad-spectrum sunscreen with a high protection factor.
Post-transplant lymphoproliferative disorder (PTLD) has been reported in immunosuppressed organ transplant recipients. The majority of PTLD events appear related to Epstein-Barr Virus (EBV) infection. The risk of PTLD appears greatest in those individuals who are EBV seronegative, a population which includes many young children.
Monitor EBV serology during treatment.
5.2Serious Infections Patients receiving immunosuppressants, including tacrolimus, are at increased risk of developing bacterial, viral, fungal, and protozoal infections, including opportunistic infections. These infections may lead to serious, including fatal, outcomes. Serious viral infections reported include: Polyomavirus-associated nephropathy (PVAN), mostly due to BK virus infection JC virus-associated progressive multifocal leukoencephalopathy (PML) Cytomegalovirus infections: CMV seronegative transplant patients who receive an organ from a CMV seropositive donor disease are at higher risk of developing CMV viremia and CMV disease.
Monitor for the development of infection and adjust the immunosuppressive regimen to balance the risk of rejection with the risk of infection [see Adverse Reactions (6.1 , 6.2 )].
5.3Not Interchangeable with Extended-Release Tacrolimus Products - Medication Errors Medication errors, including substitution and dispensing errors, between tacrolimus immediate-release products and tacrolimus extended-release products were reported outside the U.S. This led to serious adverse reactions, including graft rejection, or other adverse reactions due to under- or over exposure to tacrolimus. Tacrolimus is not interchangeable or substitutable for tacrolimus extended-release products.
Changes between tacrolimus immediate-release and extended-release dosage forms must occur under physician supervision. Instruct patients and caregivers to recognize the appearance of tacrolimus dosage forms [see Dosage Forms and Strengths (3) ] and to confirm with t…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (≥ 15%) were abnormal renal function, hypertension, diabetes mellitus, fever, CMV infection, tremor, hyperglycemia, leukopenia, infection, anemia, bronchitis, pericardial effusion, urinary tract infection, constipation, diarrhea, headache, abdominal pain, insomnia, paresthesia, peripheral edema, nausea, hyperkalemia, hypomagnesemia, and hyperlipemia. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Concord Biotech Limited at Telephone: 1-855-407-0586 or FDA at 1-800-FDA-1088 or www.fda.g ov/medwatch.
The following serious and otherwise important adverse drug reactions are discussed in greater detail in other sections of labeling: Lymphoma and Other Malignancies [see Warnings and Precautions (5.1) ] Serious Infections [ see Warnings and Precautions (5.2) ] New Onset Diabetes After Transplant [see Warnings and Precautions (5.4) ] Nephrotoxicity [see Warnings and Precautions (5.5) ] Neurotoxicity [see Warnings and Precautions (5.6) ] Hyperkalemia [see Warnings and Precautions (5.7) ] Hypertension [see Warnings and Precautions (5.8) ] Anaphylactic Reactions with Tacrolimus Injection [see Warnings and Precautions (5.9) ] Myocardial Hypertrophy [see Warnings and Precautions (5.13) ] Pure Red Cell Aplasia [see Warnings and Precautions (5.15) ] Thrombotic Microangiopathy, Including Hemolytic Uremic Syndrome and Thrombotic Thrombocytopenic Purpura [see Warnings and Precautions ( 5.16 )]
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. In addition, the clinical trials were not designed to establish comparative differences across study arms with regards to the adverse reactions discussed below. Kidney Transplantation The incidence of adverse reactions was determined in three randomized kidney transplant trials.
One of the trials used azathioprine (AZA) and corticosteroids and two of the trials used mycophenolate mofetil (MMF) and corticosteroids concomitantly for maintenance immunosuppression. Tacrolimus-based immunosuppression in conjunction with azathioprine and corticosteroids following kidney transplantation was assessed in a trial where 205 patients received tacrolimus-based immunosuppression and 207 patients received cyclosporine-based immunosuppression. The trial population had a mean age of 43 years (mean±SD was 43±13 years on tacrolimus and 44±12 years on cyclosporine arm), the distribution was 61% male, and the composition was White (58%), African- American (25%), Hispanic (12%), and Other (5%).
The 12-month post-transplant information from this trial is presented below. The most common adverse reactions (≥30%) observed in tacrolimus-treated kidney transplant patients are: infection, tremor, hypertension, abnormal renal function, constipation, diarrhea, headache, abdominal pain, insomnia, nausea, hypomagnesemia, urinary tract infection, hypophosphatemia, peripheral edema, asthenia, pain, hyperlipidemia, hyperkalemia, and anemia. Based on reported adverse reaction terms related to decreased renal function, nephrotoxicity was reported in approximately 52% of kidney transplantation patients.
Adverse reactions that occurred in ≥15% of kidney transplant patients treated with tacrolimus in conjunction with azathioprine are presented below: Table 4. Kidney Transplantation: Adverse Reactions Occurring in ≥ 15% of Patients Treated with Tacrolimus in Conjunction with Azathioprine (AZA) Tacrolimus/AZA (N = 205) Cyclosporine/AZA (N = 207) Nervous System Tremor 54% 34% Headache 44% 38% Insomnia 32% 30% Paresthesia 23% 16% Dizziness 19% 16% Gastrointestinal Diarrhea 44% 41% Nausea 38% 36% Constipation 35% 43% Vomiting 29% 23% Dyspepsia 28% 20% Cardiovascular Hypertension 50% 52% Chest Pain 19% 13% Urogenital Creatinine Increased 45% 42% Uri…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Mycophenolic Acid Products: Can increase MPA exposure after crossover from cyclosporine to tacrolimus; monitor for MPA-related adverse reactions and adjust MMF or MPA dose as needed. ( 7.1 ) Nelfinavir and Grapefruit Juice: Increased tacrolimus concentrations via CYP3A inhibition; avoid concomitant use. ( 7.2 ) CYP3A Inhibitors: Increased tacrolimus concentrations; monitor concentrations and adjust tacrolimus dose as needed.
( 5.11 , 7.2 ) CYP3A4 Inducers: Decreased tacrolimus concentrations; monitor concentrations and adjust tacrolimus dose as needed. ( 5.11 , 7.2 ) Therapeutic drug monitoring and dose reduction for tacrolimus should be considered when tacrolimus is co-administered with cannabidiol ( 5.17 , 7.3 ).
7.1Mycophenolic Acid When tacrolimus is prescribed with a given dose of a mycophenolic acid (MPA) product, exposure to MPA is higher with tacrolimus co-administration than with cyclosporine co-administration with MPA, because cyclosporine interrupts the enterohepatic recirculation of MPA while tacrolimus does not. Monitor for MPA-associated adverse reactions and reduce the dose of concomitantly administered mycophenolic acid products as needed.
7.2Effects of Other Drugs on Tacrolimus Table 15 displays the effects of other drugs on Tacrolimus. Table 15. Effects of Other Drugs/Substances on Tacrolimus 1 1.
Tacrolimus dosage adjustment recommendation based on observed effect of coadministered drug on tacrolimus exposures [see Clinical Pharmacology (12.3) ] , literature reports of altered tacrolimus exposures, or the other drug's known CYP3A inhibitor/inducer status. 2. High dose or double strength grapefruit juice is a strong CYP3A inhibitor; low dose or single strength grapefruit juice is a moderate CYP3A inhibitor.
3. Strong CYP3A inhibitor/inducer, based on reported effect on exposures to tacrolimus along with supporting in vitro CYP3A inhibitor/inducer data, or based on drug- drug interaction studies with midazolam (sensitive CYP3A probe substrate). Drug/Substance Class or Name Drug Interaction Effect Recommendations Grapefruit or grapefruit juice 2 May increase tacrolimus whole blood trough concentrations and increase the risk of serious adverse reactions (e.g., neurotoxicity, QT prolongation) [see Warnings and Precautions (5.6 , 5.11 , 5.12 )].
Avoid grapefruit or grapefruit juice. Strong CYP3A Inducers 3 : Antimycobacterials (e.g., rifampin, rifabutin), anticonvulsants (e.g., phenytoin, carbamazepine and phenobarbital), St John's Wort May decrease tacrolimus whole blood trough concentrations and increase the risk of rejection [see Warnings and Precautions (5.11 )]. Increase tacrolimus dose and monitor tacrolimus whole blood trough concentrations [ see Dosage and Administration (2.2 , 2.6 ) and Clinical Pharmacology (12.3) ].
Strong CYP3A Inhibitors 3 : Protease inhibitors (e.g, nelfinavir, telaprevir, boceprevir, ritonavir), azole antifungals (e.g., voriconazole, posaconazole, itraconazole, ketoconazole), antibiotics (e.g., clarithromycin, troleandomycin, chloramphenicol), nefazodone, letermovir, Schisandra sphenanthera extracts May increase tacrolimus whole blood trough concentrations and increase the risk of serious adverse reactions (e.g., neurotoxicity, QT prolongation). A rapid, sharp rise in tacrolimus levels may occur early, despite an immediate reduction of tacrolimus dose [see Warnings and Precautions (5.6 , 5.11 , 5.12 )].
Reduce tacrolimus dose (for voriconazole and posaconazole, give one-third of the original dose) and adjust dose based on tacrolimus whole blood trough concentrations [ see Dosage and Administration (2.2 , 2.6 ) and Clinical Pharmacology (12.3) ]. Early and frequent monitoring of tacrolimus whole blood trough levels should start within 1-3 days and continue monitoring as necessary [see Warnings and Precautions (5.11)] . Mild or Moderate CYP3A Inhibitors: Clotrimazole, antibiotics (e.g., erythromycin, fluconazole), calcium channel blockers (e.g., verapamil, diltia…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Can cause fetal harm. Advise pregnant women of the potential risk to the fetus. ( 8.1 , 8.3 ) Additional pediatric use information is approved for Astellas Pharma US, Inc.'s Prograf (tacrolimus) products. However, due to Astellas Pharma US, Inc.'s marketing exclusivity rights, this drug product is not labeled with that information.
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy registry that monitors pregnancy outcomes in women exposed to tacrolimus during pregnancy. The Transplantation Pregnancy Registry International (TPRI) is a voluntary pregnancy exposure registry that monitors outcomes of pregnancy in female transplant recipients and those fathered by male transplant recipients exposed to immunosuppressants including tacrolimus. Healthcare providers are encouraged to advise their patients to register by contacting the Transplantation Pregnancy Registry International at 1-877-955-6877 or https://www.transplantpregnancyregistry.org/ .
Risk Summary Tacrolimus can cause fetal harm when administered to a pregnant woman. Data from postmarketing surveillance and TPRI suggest that infants exposed to tacrolimus in utero are at a risk of prematurity, birth defects/congenital anomalies, low birth weight, and fetal distress [see Human Data]. Advise pregnant women of the potential risk to the fetus.
Administration of oral tacrolimus to pregnant rabbits and rats throughout the period of organogenesis was associated with maternal toxicity/lethality, and an increased incidence of abortion, malformation and embryofetal death at clinically relevant doses (0.5 to 6.9 times the recommended clinical dose range [0.2 to 0.075 mg/kg/day], on a mg/m 2 basis). Administration of oral tacrolimus to pregnant rats after organogenesis and throughout lactation produced maternal toxicity, effects on parturition, reduced pup viability and reduced pup weight at clinically relevant doses (0.8 to 6.9 times the recommended clinical dose range, on a mg/m 2 basis).
Administration of oral tacrolimus to rats prior to mating, and throughout gestation and lactation produced maternal toxicity/lethality, marked effects on parturition, embryofetal loss, malformations, and reduced pup viability at clinically relevant doses (0.8 to 6.9 times the recommended clinical dose range, on a mg/m 2 basis). Interventricular septal defects, hydronephrosis, craniofacial malformations and skeletal effects were observed in offspring that died [see Animal Data] . The background risk of major birth defects and miscarriage in the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Disease-Associated Maternal and/or Embryo-Fetal Risk Risks during pregnancy are increased in organ transplant recipients. The risk of premature delivery following transplantation is increased.
Pre-existing hypertension and diabetes confer additional risk to the pregnancy of an organ transplant recipient. Pre-gestational and gestational diabetes are associated with birth defects/congenital anomalies, hypertension, low birth weight and fetal death. Cholestasis of pregnancy (COP) was reported in 7% of liver or liver-kidney (LK) transplant recipients, compared with approximately 1% of pregnancies in the general population.
However, COP symptoms resolved postpartum and no long-term effects on the offspring were reported. Maternal Adverse Reactions Tacrolimus may increase hyperglycemia in pregnant women with diabetes (including gestational diabetes). Monitor maternal blood glucose levels regularly [see Warnings and Precautions (5.4) ].
Tacrolimus may exacerbate hypertension in pregnant women and increase pre-eclampsia. Monitor and control blood pressure [see Warnings and Precautions (5.7 , 5.8 )]. Fetal/Neonatal Adverse Reactions Renal dysfunction, transient neonatal hyperkalemia…
🆘 Overdosage ▾
10 OVERDOSAGE Limited overdosage experience is available. Acute overdosages of up to 30 times the intended dose have been reported. Almost all cases have been asymptomatic and all patients recovered with no sequelae.
Acute overdosage was sometimes followed by adverse reactions consistent with those reported with the use of tacrolimus [see Adverse Reactions (6.1, 6.2)], including tremors, abnormal renal function, hypertension, and peripheral edema; in one case of acute overdosage, transient urticaria and lethargy were observed. Based on the poor aqueous solubility and extensive erythrocyte and plasma protein binding, it is anticipated that tacrolimus is not dialyzable to any significant extent; there is no experience with charcoal hemoperfusion.
The oral use of activated charcoal has been reported in treating acute overdoses, but experience has not been sufficient to warrant recommending its use. General supportive measures and treatment of specific symptoms should be followed in all cases of overdosage.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Tacrolimus binds to an intracellular protein, FKBP-12. A complex of tacrolimus-FKBP-12, calcium, calmodulin, and calcineurin (a ubiquitous mammalian intracellular enzyme) is then formed, after which the phosphatase activity of calcineurin is inhibited. Such inhibition prevents the dephosphorylation and translocation of various factors such as the nuclear factor of activated T-cells (NF-AT), and nuclear factor kappa-light-chain enhancer of activated B-cells (NF-κB).
Tacrolimus inhibits the expression and/or production of several cytokines that include interleukin (IL)-1 beta, IL-2, IL-3, IL-4, IL-5, IL-6, IL-8, IL-10, gamma interferon, tumor necrosis factor-alpha, and granulocyte macrophage colony stimulating factor. Tacrolimus also inhibits IL-2 receptor expression and nitric oxide release, induces apoptosis and production of transforming growth factor beta that can lead to immunosuppressive activity. The net result is the inhibition of T-lymphocyte activation and proliferation, as well as T-helper-cell-dependent B-cell response (i.e., immunosuppression).
12.3Pharmacokinetics Tacrolimus activity is primarily due to the parent drug. The pharmacokinetic parameters (mean ± S.D.) of tacrolimus have been determined following intravenous (IV) and/or oral (PO) administration in healthy volunteers, and in kidney transplant, liver transplant, and heart transplant patients (Table 17). Table 17.
Pharmacokinetics Parameters (mean ± S.D.) of Tacrolimus in Healthy Volunteers and Patients 1. Not applicable 2. AUC 0-inf 3.
Not available 4. AUC 0-t 5. Determined after the first dose 6.
Median [range] 7. AUC 0-12 Population N Route (Dose) Parameters C max (ng/mL) T max (hr) AUC (ng•hr/mL) t 1/2 (hr) CL (L/hr/kg) V (L/kg) Healthy Volunteers 8 IV (0.025 mg/kg/4 hr) 1 1 652 2 ± 156 34.2 ± 7.7 0.040 ± 0.009 1.91 ± 0.31 30 PO (5 mg) (capsules) 28.8 ± 8.9 1.5 ± 0.7 266 2 ± 95 32.3 ± 8.8 3 3 Kidney Transplant Patients 26 IV (0.02 mg/kg/12 hr) 1 1 294 2 ± 262 18.8 ± 16.7 0.083 ± 0.050 1.41 ±
0.66PO (0.2 mg/kg/day) 19.2 ± 10.3 3.0 203 2 ± 42 3 3 3 PO (0.3 mg/kg/day) 24.2 ± 15.8 1.5 288 2 ± 93 3 3 3 Liver Transplant Patients 17 IV (0.05 mg/kg/12 hr) 1 1 3300 2 ± 2130 11.7 ± 3.9 0.053 ± 0.017 0.85 ± .30 PO (0.3 mg/kg/day) 68.5 ± 30.0 2.3 ± 1.5 519 2 ± 179 3 3 3 Heart Transplant Patients 11 IV (0.01 mg/kg/day as a continuous infusion) 1 1 954 4 ± 334 23.6 ± 9.22 0.051 ± 0.015 3 11 PO (0.075 mg/kg/day) 5 14.7 ± 7.79 2.1 [0.5- 6.0] 6 82.7 7 ± 63.2 1 3 3 14 PO (0.15 mg/kg/day) 5 24.5 ± 13.7 1.5 [0.4- 4.0] 6 142 7 ± 116 1 3 3 Due to intersubject variability in tacrolimus pharmacokinetics, individualization of the dosing regimen is necessary for optimal therapy [see Dosage and Administration (2.6) ] .
Pharmacokinetic data indicate that whole blood concentrations rather than plasma concentrations serve as the more appropriate sampling compartment to describe tacrolimus pharmacokinetics. Absorption Absorption of tacrolimus from the gastrointestinal tract after oral administration is incomplete and variable. The absolute bioavailability of tacrolimus was 17±10% in adult kidney transplant patients (N=26), 22±6% in adult liver transplant patients (N=17), 23±9% in adult heart transplant patients (N=11) and 18±5% in healthy volunteers (N=16).
A single dose trial conducted in 32 healthy volunteers established the bioequivalence of the 1 mg and 5 mg capsules. Another single dose trial in 32 healthy volunteers established the bioequivalence of the 0.5 mg and 1 mg capsules. Tacrolimus maximum blood concentrations (C max ) and area under the curve (AUC) appeared to increase in a dose-proportional fashion in 18 fasted healthy volunteers receiving a single oral dose of 3, 7, and 10 mg.
In 18 kidney transplant patients, tacrolimus trough concentrations from 3 to 30 ng/mL measured at 10-12 hours post-dose (C min ) correlated well with the AUC (correlation coefficient 0.93). In 24 liver transplant patients over a concentration…
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
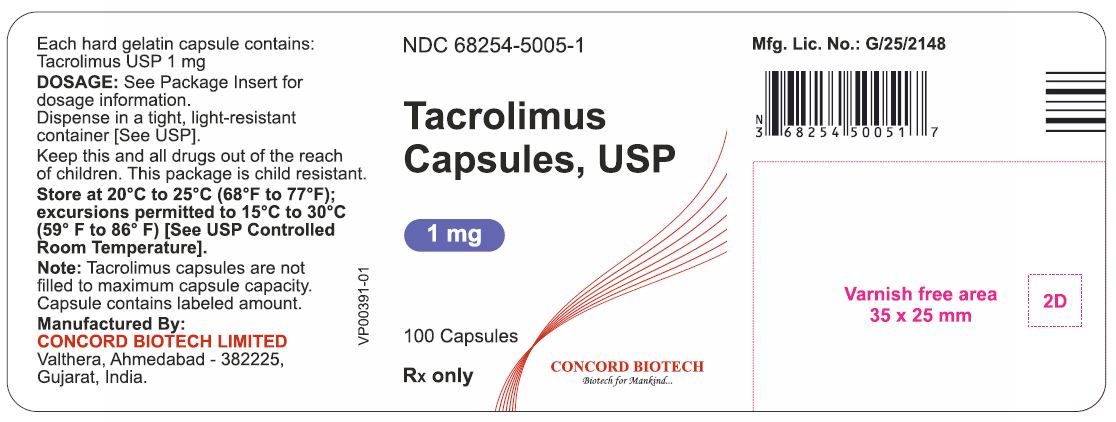
16.1Tacrolimus Capsules, USP Strength 0.5 mg (containing the equivalent of 0.5 mg anhydrous tacrolimus USP) 1 mg (containing the equivalent of 1 mg anhydrous tacrolimus USP) 5 mg (containing the equivalent of 5 mg anhydrous tacrolimus USP) Shape/color capsule/light yellow capsule /white capsule /grayish red Imprint on capsule cap "C5" "0.5mg" on cap "C6" "1mg" on cap "C7" "5mg" on cap 30 count bottle NDC 68254-5004-5 NDC 68254-5005-5 NDC 68254-5006-5 100 count bottle NDC 68254-5004-1 NDC 68254-5005-1 NDC 68254-5006-1 Note: Tacrolimus capsules USP are not filled to maximum capsule capacity.
Capsule contains labeled amount. Store and Dispense Store at 20°C to 25°C (68°F to 77°F); excursions permitted 15°C to 30°C (59°F to 86°F) [See USP Controlled Room Temperature].
16.4Handling and Disposal Tacrolimus can cause fetal harm. Tacrolimus capsules should not be opened or crushed. Wearing disposable gloves is recommended during dilution of the injection in the hospital and when wiping any spills.
Avoid inhalation or direct contact with skin or mucous membranes of the powder contained in tacrolimus capsules. If such contact occurs, wash the skin thoroughly with soap and water; if ocular contact occurs, rinse eyes with water. In case a spill occurs, wipe the surface with a wet paper towel.
Follow applicable special handling and disposal procedures 1 .
📋 Description ▾
11 DESCRIPTION Tacrolimus, previously known as FK506, is the active ingredient in Tacrolimus capsules USP. Tacrolimus is a calcineurin-inhibitor immunosuppressant produced by Streptomyces tsukubaensis . Chemically, tacrolimus is designated as [3 S -[3 R *[ E (1 S *,3 S *,4 S *)],4 S *,5 R *,8 S *,9 E ,12 R *,14 R *,15 S *,16 R *,18 S *,19 S *,26a R *]]-5,6,8,11,12,13,14,15,16,17,18,19,24,25,26,26a-hexadecahydro-5,19-dihydroxy-3-[2-(4-hydroxy-3-methoxycyclohexyl)-1-methylethenyl]-14,16-dimethoxy-4,10,12,18-tetramethyl-8-(2-propenyl)-15,19-epoxy-3H-pyrido[2,1- c ][1,4]oxaazacyclotricosine-1,7,20,21(4H,23H)-tetrone, monohydrate.
The chemical structure of tacrolimus is: Tacrolimus has an empirical formula of C 44 H 69 NO 12 •H 2 O and a formula weight of 822.03. Tacrolimus appears as white crystals or crystalline powder. It is practically insoluble in water, freely soluble in ethanol, and very soluble in methanol and chloroform.
Tacrolimus is available for oral administration as capsules (tacrolimus capsules USP) containing the equivalent of 0.5 mg, 1 mg or 5 mg of anhydrous tacrolimus USP. In addition, each capsule contains the following inactive ingredients: croscarmellose sodium, hypromellose, anhydrous lactose and magnesium stearate. The tacrolimus capsule shell for 0.5 mg strength consists of gelatin, titanium dioxide and yellow iron oxide.
The tacrolimus capsule shell for 1 mg strength consists of gelatin and titanium dioxide. The tacrolimus capsule shell for 5 mg strength consists of red iron oxide, gelatin, and titanium dioxide. Tacrolimus Capsules USP, 0.5 mg, 1 mg and 5 mg are printed with edible black ink.
The black ink is comprised of shellac, propylene glycol, strong ammonia solution, black iron oxide and potassium hydroxide. Tacrolimus Capsules, USP meets USP Dissolution Test 8. image
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information and Instructions for Use).
17.1Administration Advise the patient or caregiver to: Inspect their tacrolimus medicine when they receive a new prescription and before taking it. If the appearance of the capsule is not the same as usual, or if dosage instructions have changed, advise patients to contact their healthcare provider as soon as possible to make sure that they have the right medicine. Other tacrolimus products cannot be substituted for tacrolimus.
Take tacrolimus at the same 12-hour intervals every day to achieve consistent blood concentrations. Take tacrolimus consistently either with or without food because the presence and composition of food decreases the bioavailability of tacrolimus. Not to eat grapefruit or drink grapefruit juice in combination with tacrolimus [see Drug Interactions (7.2) ].
17.2Development of Lymphoma and Other Malignancies Inform patients they are at increased risk of developing lymphomas and other malignancies, particularly of the skin, due to immunosuppression. Advise patients to limit exposure to sunlight and ultraviolet (UV) light by wearing protective clothing and using a broad spectrum sunscreen with a high protection factor [see Warnings and Precautions (5.1) ] .
17.3Increased Risk of Infection Inform patients they are at increased risk of developing a variety of infections, including opportunistic infections, due to immunosuppression and to contact their physician if they develop any symptoms of infection such as fever, sweats or chills, cough or flu-like symptoms, muscle aches, or warm, red, painful areas on the skin [see Warnings and Precautions (5.2) ] .
17.4New Onset Diabetes After Transplant Inform patients that tacrolimus capsules can cause diabetes mellitus and should be advised to contact their physician if they develop frequent urination, increased thirst, or hunger [see Warnings and Precautions (5.4) ] .
17.5Nephrotoxicity Inform patients that Tacrolimus can have toxic effects on the kidney that should be monitored. Advise patients to attend all visits and complete all blood tests ordered by their medical team [ see Warnings and Precautions (5.5) ].
17.6Neurotoxicity Inform patients that they are at risk of developing adverse neurologic reactions including seizure, altered mental status, and tremor. Advise patients to contact their physician should they develop vision changes, delirium, or tremors [see Warnings and Precautions (5.6) ] .
17.7Hyperkalemia Inform patients that Tacrolimus can cause hyperkalemia. Monitoring of potassium levels may be necessary, especially with concomitant use of other drugs known to cause hyperkalemia [ see Warnings and Precautions (5.7) ].
17.8Hypertension Inform patients that tacrolimus capsules can cause high blood pressure which may require treatment with antihypertensive therapy. Advise patients to monitor their blood pressure [see Warnings and Precautions (5.8) ] .
17.9Thrombotic Microangiopathy Inform patients that tacrolimus capsules can cause blood clotting problems. The risk of this occurring increases when patients take tacrolimus capsules and sirolimus or everolimus concomitantly, or when patients develop certain infections. Advise them to seek medical attention promptly if they develop fever, petequiae or bruises, fatigue, confusion, jaundice, oliguria. [see Warnings and Precautions (5.16) ]
17.10Drug Interactions Instruct patients to tell their healthcare providers when they start or stop taking any medicines, including prescription medicines and nonprescription medicines, natural or herbal remedies, nutritional supplements, and vitamins. Advise patients to avoid grapefruit and grapefruit juice [see Drug Interactions (7) ].
17.11Pregnancy, Lactation and Infertility Inform women of childbearing potential that tacrolimus can harm the fetus. Instruct male and female patients to discuss with their healthcare provi…
💬 Patient Medication Information ▾
PATIENT INFORMATION Tacrolimus Capsules, for oral use (ta kroe′ li mus) Read this Patient Information before you start taking tacrolimus capsules and each time you get a refill. There may be new information. This information does not take the place of talking with your healthcare provider about your medical condition or your treatment.
What is the most important information I should know about Tacrolimus Capsules? Tacrolimus Capsules can cause serious side effects, including: Increased risk of cancer. People who take tacrolimus have an increased risk of getting some kinds of cancer, including skin and lymph gland cancer (lymphoma).
Increased risk of infection. Tacrolimus is a medicine that affects your immune system. Tacrolimus can lower the ability of your immune system to fight infections.
Serious infections can happen in people receiving tacrolimus that can cause death. Call your healthcare provider right away if you have any symptoms of an infection, including: fever sweats or chills cough or flu-like symptoms muscle aches warm, red, or painful areas on your skin What are Tacrolimus Capsules? Tacrolimus Capsules are a prescription medicine used with other medicines to help prevent organ rejection in people who have had a kidney, liver or heart transplant.
Tacrolimus capsules are a types of tacrolimus immediate-release drug and it is not the same as tacrolimus extended-release tablets or tacrolimus extended-release capsules. Your healthcare provider should decide what medicine is right for you. Who should not take Tacrolimus Capsules?
Do not take Tacrolimus Capsules if you: are allergic to tacrolimus or any of the ingredients in Tacrolimus Capsules. See the end of this leaflet for a complete list of ingredients in Tacrolimus Capsules. What should I tell my healthcare provider before taking Tacrolimus Capsules?
Before taking Tacrolimus Capsules, tell your healthcare provider about all of your medical conditions, including if you: plan to receive any vaccines. People taking Tacrolimus Capsules should not receive live vaccines. have or have had liver, kidney, or heart problems. are pregnant or plan to become pregnant. Tacrolimus Capsules can harm your unborn baby.
If you are able to become pregnant, you should use effective birth control before and during treatment with tacrolimus capsules. Talk to your healthcare provider before starting treatment with tacrolimus capsules about birth control methods that may be right for you. Males who have female partners who are able to become pregnant should also use effective birth control before and during treatment with tacrolimus capsules.
Talk to your healthcare provider before starting treatment with tacrolimus capsules about birth control methods that may be right for you. There is a pregnancy registry for females who become pregnant and males who have fathered a pregnancy during treatment with tacrolimus capsules. The purpose of this registry is to collect information about the health of you and your baby.
To enroll in this voluntary registry, call 1-877-955-6877 or go to https://www.transplantpregnancyregistry.org/. are breastfeeding or plan to breastfeed. Tacrolimus passes into your breast milk. You and your healthcare provider should decide if you will breastfeed while taking tacrolimus capsules. plan to have children.
Tacrolimus capsules may affect the ability to have children in females and males (fertility problems). Tell your healthcare provider about all the medicines you take, and when you start a new medicine or stop taking a medicine, including prescription and over-the-counter medicines, vitamins, natural, herbal, or nutritional supplements. Especially tell your healthcare provider if you take: sirolimus (RAPAMUNE): You should not take tacrolimus if you take sirolimus cyclosporine (GENGRAF, NEORAL, and SANDIMMUNE) medicines called aminoglycosides that are used to treat bacterial infections ganciclovir (CYTOVENE IV, VALCYTE) amphotericin B (ABELCET, AMBISOME) cisplatin a…