
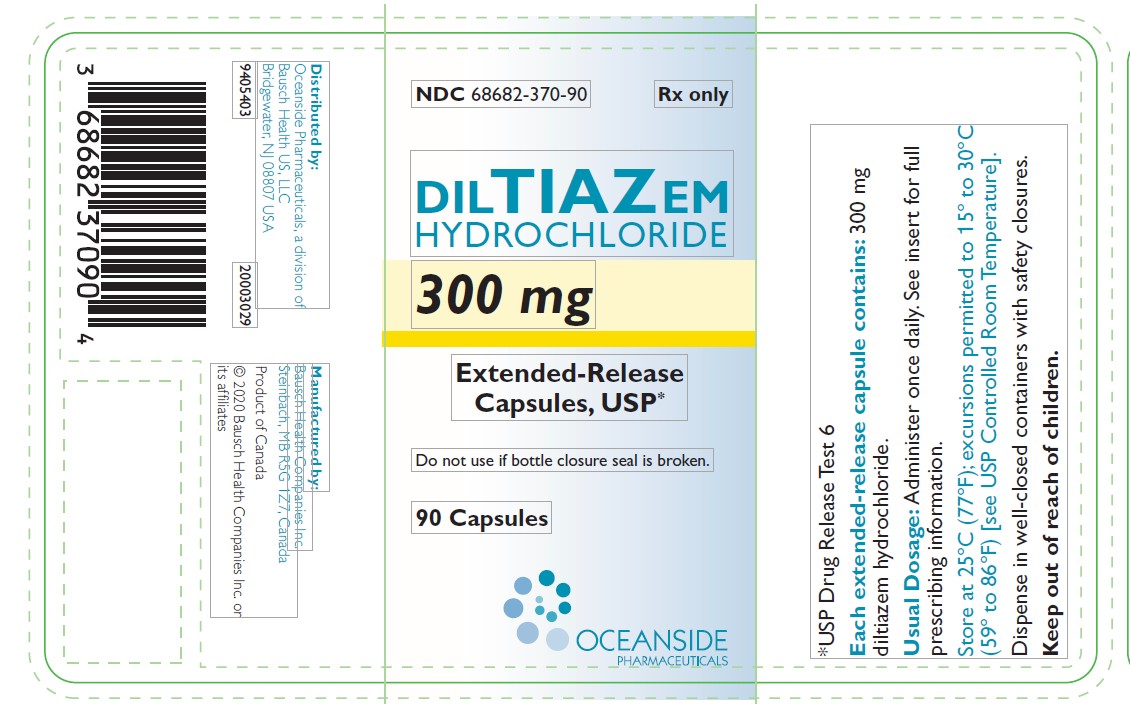
Diltiazem Hydrochloride EXTENDED RELEASE 300 mg Capsule, Extended Release, 90-count — NDC 68682-370-90 (Billing 68682-0370-90)
This is a package of 90 capsules of Diltiazem Hydrochloride EXTENDED RELEASE 300 mg Capsule, Extended Release from Oceanside Pharmaceuticals, marketed since Aug 2014 and currently FDA-listed; retail pharmacies pay about $0.5155 per capsule (NADAC). It is this product's only package size.
Other active recalls for Diltiazem Hydrochloride (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 024539
- GCN: 02333
- GPI-14 (Medi-Span): 34000010117050
- HICL (First Databank): 000182
- AHFS class code: 24:04.04.24
- RxCUI (RxNorm): 830795
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Calcium Channel Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Diltiazem is used to treat high blood pressure and to control angina (chest pain). Diltiazem is in a class of medications called calcium-channel blockers. It works by relaxing the blood vessels so the heart does not have to pump as hard. It also increases the supply of blood and oxygen to the heart. High blood pressure is a common condition, and when not treated it can cause damage to the brain, heart, blood vessels, kidneys, and other parts of the body. Damage to these organs may cause heart disease, a heart attack, heart failure, stroke, kidney failure, loss of vision, and other problems. In...
Read the full MedlinePlus article ↗- The pills and capsules you take by mouth are used for high blood pressure and for chronic stable angina, which is chest pain from the heart's workload. Some capsule brands, such as...
- Usually it's taken once a day, and you should swallow it whole. Don't open, chew or crush the capsules. Some products, like DILT-XR, are best taken in the morning on an empty stoma...
- How should I take my extended-release capsule or tablet?
- The most common ones are a stuffy or runny nose, headache, sore throat, constipation, cough, and swelling in the legs or ankles. Most are mild. Call your doctor if you faint, feel...
Patient education
Supplement & herbal interactions
Diltiazem may be associated with lower levels of 2 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.516 | $46.40 / 90 capsules |
| Medicaid paysCMS SDUD · 12 mo | $0.7063 | $63.57 / 90 capsules |
| Medicare drug plans payPart D · Q2 2026 | $0.3502 | $31.52 / 90 capsules |
Where does this data come from?
- CMS NADAC weekly file · file of Feb 21, 2024
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 68682-0370-90 You're viewing this Main listing | 90 CAPSULE, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2014-08-20 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diltiazem Hydrochloride 300 mg 68682-0998-98 | OCEANSIDE | 90 capsules | $0.287 | AB3 | FDA listed | save 44% |
| Diltiazem Hydrochloride 300 mg 00904-7220-61 | Major | 1 capsule | $0.302 | AB3 | Availability likely | save 41% |
| Diltiazem Hydrochloride Extended-Release 300 mg 10370-0832-05 | Endo | 500 capsules | $0.302 | AB3 | Discontinued | save 41% |
| Diltiazem Hydrochloride 300 mg 24979-0029-02 | Upsher-Smith | 500 capsules | $0.302 | AB3 | Availability likely | save 41% |
| Diltiazem Hydrochloride Extended-Release 300 mg 60687-0228-01 | American | 1 capsule | $0.302 | AB3 | Availability likely | save 41% |
| Cartia XT 300 mg 62037-0600-05 | Actavis | 500 capsules | $0.302 | AB3 | Availability likely | save 41% |
| Diltiazem hydrochloride 300 mg 63304-0721-05 | Sun | 500 capsules | $0.309 | — | FDA listed | save 40% |
| Diltiazem Hydrochloride 300 mg 47335-0672-13 | Sun | 500 capsules | $0.516 | — | FDA listed | — |
| Diltiazem Hydrochloride EXTENDED RELEASE 300 mgthis 68682-0370-90 | Oceanside | 90 capsules | $0.516 | AB4 | FDA listed | — |
| Cardizem CD 300 mg 00187-0798-30 | Bausch | 30 capsules | — | AB3 | FDA listed | — |
| Tiazac Extended Release 300 mg 00187-2615-30 | Bausch | 30 capsules | — | AB4 | FDA listed | — |
| Diltiazem Hydrochloride 300 mg 33342-0524-02 | Macleods | 6 capsules | — | AB3 | FDA listed | — |
| Diltiazem Hydrochloride 300 mg 46708-0728-30 | Alembic | 30 capsules | — | AB3 | FDA listed | — |
| Diltiazem Hydrochloride 300 mg 47335-0678-13 | Sun | 500 capsules | — | — | FDA listed | — |
| diltiazem hydrochloride 300 mg 50742-0251-05 | Ingenus | 500 capsules | — | AB3 | FDA listed | — |
| Diltiazem Hydrochloride 300 mg 51407-0476-90 | Golden | 90 capsules | — | AB3 | FDA listed | — |
| Diltiazem Hydrochloride 300 mg 62332-0728-30 | Alembic | 30 capsules | — | AB3 | FDA listed | — |
| Diltiazem Hydrochloride Extended-Release 300 mg 63629-2159-01 | Bryant | 30 capsules | — | AB3 | FDA listed | — |
| diltiazem hydrochloride 300 mg 68382-0598-01 | Zydus | 100 capsules | — | AB3 | FDA listed | — |
| Tiadylt Er 300 mg 68382-0748-01 | Zydus | 100 capsules | — | AB4 | FDA listed | — |
| diltiazem hydrochloride 300 mg 70771-1033-01 | Zydus | 100 capsules | — | AB3 | FDA listed | — |
| Tiadylt Er 300 mg 70771-1038-00 | Zydus | 1000 capsules | — | AB4 | FDA listed | — |
| Cartia Xt 300 mg 72189-0344-90 | DirectRx | 90 capsules | — | AB3 | FDA listed | — |
| Diltiazem HCL ER 300 mg 72189-0409-90 | Direct_Rx | 90 capsules | — | AB3 | FDA listed | — |
| diltiazem hydrochloride 300 mg 84677-0042-90 | Golden | 90 capsules | — | AB3 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Feb 21, 2024
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 767IP0Y5NH
A synthetic red colorant used to give medicines their color. It helps patients identify their medication and makes the product visually appealing.
-
UNII P2OM2Q86BI
A synthetic polymer made from two types of plastic-like chemicals bonded together. It forms a protective coating on tablets or capsules to control how quickly the medicine dissolves and releases in your digestive system.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII 3P3ONR6O1S
A synthetic green dye approved by the FDA for use in medicines and foods. It serves as a colorant to make the pill or liquid visually distinctive and help with product identification.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII FZ989GH94E
Povidone is a synthetic polymer made from a plastic-like material. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in your stomach so the medicine can be absorbed.
-
UNII 274KW0O50M
Sucrose stearate is a compound made from sugar and stearic acid (a fatty substance). It works as an emulsifier and surfactant to help mix oils and water-based ingredients together in the medicine.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hypertension Diltiazem hydrochloride extended-release capsules are indicated for the treatment of hypertension. They may be used alone or in combination with other antihypertensive medications. Chronic Stable Angina Diltiazem hydrochloride extended-release capsules are indicated for the treatment of chronic stable angina.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Hypertension: Dosage needs to be adjusted by titration to individual patient needs. When used as monotherapy, usual starting doses are 120 to 240 mg once daily. Maximum antihypertensive effect is usually observed by 14 days of chronic therapy; therefore, dosage adjustments should be scheduled accordingly.
The usual dosage range studied in clinical trials was 120 to 540 mg once daily. Current clinical experience with 540 mg dose is limited; however, the dose may be increased to 540 mg once daily. Angina: Dosages for the treatment of angina should be adjusted to each patient’s needs, starting with a dose of 120 mg to 180 mg once daily.
Individual patients may respond to higher doses of up to 540 mg once daily. When necessary, titration should be carried out over 7 to 14 days. Concomitant Use with Other Cardiovascular Agents: 1.
Sublingual Nitroglycerin (NTG): May be taken as required to abort acute anginal attacks during diltiazem hydrochloride therapy. 2. Prophylactic Nitrate Therapy: Diltiazem hydrochloride may be safely coadministered with short- and long-acting nitrates.
3. Beta-blockers: (see WARNINGS and PRECAUTIONS ) . 4.
Antihypertensives: Diltiazem hydrochloride has an additive antihypertensive effect when used with other antihypertensive agents. Therefore, the dosage of diltiazem hydrochloride or the concomitant antihypertensives may need to be adjusted when adding one to the other. Hypertensive or anginal patients who are treated with other formulations of diltiazem can safely be switched to diltiazem hydrochloride extended-release capsules at the nearest equivalent total daily dose.
Subsequent titration to higher or lower doses may, however, be necessary and should be initiated as clinically indicated. Sprinkling the Capsule Contents on Food: Diltiazem hydrochloride extended-release capsules may also be administered by carefully opening the capsule and sprinkling the capsule contents on a spoonful of applesauce. The applesauce should be swallowed immediately without chewing and followed with a glass of cool water to ensure complete swallowing of the capsule contents.
The applesauce should not be hot, and it should be soft enough to be swallowed without chewing. Any capsule contents/applesauce mixture should be used immediately and not stored for future use. Subdividing the contents of a diltiazem hydrochloride extended-release capsule is not recommended.
⛔ Contraindications ▾
CONTRAINDICATIONS Diltiazem is contraindicated in: • Patients with sick sinus syndrome except in the presence of a functioning ventricular pacemaker • Patients with second- or third-degree AV block except in the presence of a functioning ventricular pacemaker • Patients with severe hypotension (less than 90 mm Hg systolic) • Patients who have demonstrated hypersensitivity to the drug • Patients with acute myocardial infarction and pulmonary congestion documented by x-ray on admission.
⚠️ Warnings ▾
WARNINGS 1. Cardiac Conduction: Diltiazem hydrochloride prolongs AV node refractory periods without significantly prolonging sinus node recovery time, except in patients with sick sinus syndrome. This effect may rarely result in abnormally slow heart rates (particularly in patients with sick sinus syndrome) or second- or third-degree AV block (13 of 3007 patients or 0.43%).
Concomitant use of diltiazem with beta-blockers or digitalis may result in additive effects on cardiac conduction. A patient with Prinzmetal’s angina developed periods of asystole (2 to 5 seconds) after a single dose of 60 mg of diltiazem. 2.
Congestive Heart Failure: Although diltiazem has a negative inotropic effect in isolated animal tissue preparations, hemodynamic studies in humans with normal ventricular function have not shown a reduction in cardiac index nor consistent negative effects on contractility (dP/dt). An acute study of oral diltiazem in patients with impaired ventricular function (ejection fraction 24% ± 6%) showed improvement in indices of ventricular function without significant decrease in contractile function (dP/dt). Worsening of congestive heart failure has been reported in patients with preexisting impairment of ventricular function.
Experience with the use of diltiazem hydrochloride in combination with beta-blockers in patients with impaired ventricular function is limited. Caution should be exercised when using this combination. 3.
Hypotension: Decreases in blood pressure associated with diltiazem hydrochloride therapy may occasionally result in symptomatic hypotension. 4. Acute Hepatic Injury: Mild elevations of transaminases with and without concomitant elevation in alkaline phosphatase and bilirubin have been observed in clinical studies.
Such elevations were usually transient and frequently resolved even with continued diltiazem treatment. In rare instances, significant elevations in enzymes such as alkaline phosphatase, LDH, SGOT, and SGPT, and other phenomena consistent with acute hepatic injury have been noted. These reactions tended to occur early after therapy initiation (1 to 8 weeks) and have been reversible upon discontinuation of drug therapy.
The relationship to diltiazem hydrochloride is uncertain in some cases but probable in some (see PRECAUTIONS ) .
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Serious adverse reactions have been rare in studies with diltiazem hydrochloride extended-release capsules, as well as with other diltiazem formulations. It should be recognized that patients with impaired ventricular function and cardiac conduction abnormalities have usually been excluded from these studies. A total of 256 hypertensives were treated for between 4 and 8 weeks; a total of 207 patients with chronic stable angina were treated for 3 weeks with doses of diltiazem hydrochloride extended-release capsules ranging from 120 to 540 mg once daily.
Two patients experienced first-degree AV block at the 540 mg dose. The following table presents the most common adverse reactions, whether or not drug-related, reported in placebo-controlled trials in patients receiving diltiazem hydrochloride extended-release capsules up to 360 mg and up to 540 mg with rates in placebo patients shown for comparison. MOST COMMON ADVERSE EVENTS IN DOUBLE-BLIND PLACEBO-CONTROLLED HYPERTENSION TRIALS Adverse events occurring in treated patients at 2% or more than placebo-treated patients.
Placebo Diltiazem hydrochloride extended-release capsules Adverse Events (COSTART Term) n=57 # pts (%) Up to 360 mg n=149 # pts (%) 480 - 540 mg n=48 # pts (%) edema, peripheral 1 (2) 8 (5) 7 (15) dizziness 4 (7) 6 (4) 2 (4) vasodilation 1 (2) 5 (3) 1 (2) dyspepsia 0 (0) 7 (5) 0 (0) pharyngitis 2 (4) 3 (2) 3 (6) rash 0 (0) 3 (2) 0 (0) infection 2 (4) 2 (1) 3 (6) diarrhea 0 (0) 2 (1) 1 (2) palpitations 0 (0) 2 (1) 1 (2) nervousness 0 (0) 3 (2) 0 (0) MOST COMMON ADVERSE EVENTS IN DOUBLE-BLIND PLACEBO-CONTROLLED ANGINA TRIALS Adverse events occurring in treated patients at 2% or more than placebo-treated patients.
Placebo Diltiazem hydrochloride extended-release capsules Adverse Events (COSTART Term) n=50 # pts (%) Up to 360 mg n=158 # pts (%) 540 mg n=49 # pts (%) headache 1 (2) 13 (8) 4 (8) edema, peripheral 1 (2) 3 (2) 5 (10) pain 1 (2) 10 (6) 3 (6) dizziness 0 (0) 5 (3) 5 (10) asthenia 0 (0) 1 (1) 2 (4) dyspepsia 0 (0) 2 (1) 3 (6) dyspnea 0 (0) 1 (1) 3 (6) bronchitis 0 (0) 1 (1) 2 (4) AV block 0 (0) 0 (0) 2 (4) infection 0 (0) 2 (1) 1 (2) flu syndrome 0 (0) 0 (0) 1 (2) cough increase 0 (0) 2 (1) 1 (2) extrasystoles 0 (0) 0 (0) 1 (2) gout 0 (0) 2 (1) 1 (2) myalgia 0 (0) 0 (0) 1 (2) impotence 0 (0) 0 (0) 1 (2) conjunctivitis 0 (0) 0 (0) 1 (2) rash 0 (0) 2 (1) 1 (2) abdominal enlargement 0 (0) 0 (0) 1 (2) In addition, the following events have been reported infrequently (less than 2%) in clinical trials with other diltiazem products: Cardiovascular: Angina, arrhythmia, AV block (second- or third-degree), bundle branch block, congestive heart failure, ECG abnormalities, hypotension, palpitations, syncope, tachycardia, ventricular extrasystoles.
Nervous System: Abnormal dreams, amnesia, depression, gait abnormality, hallucinations, insomnia, nervousness, paresthesia, personality change, somnolence, tinnitus, tremor. Gastrointestinal: Anorexia, constipation, diarrhea, dry mouth, dysgeusia, mild elevations of SGOT, SGPT, LDH, and alkaline phosphatase (see WARNINGS , Acute Hepatic Injury ) , nausea, thirst, vomiting, weight increase. Dermatological: Petechiae, photosensitivity, pruritus.
Other: Albuminuria, allergic reaction, amblyopia, asthenia, CPK increase, crystalluria, dyspnea, edema, epistaxis, eye irritation, headache, hyperglycemia, hyperuricemia, impotence, muscle cramps, nasal congestion, neck rigidity, nocturia, osteoarticular pain, pain, polyuria, rhinitis, sexual difficulties, gynecomastia. In addition, the following postmarketing events have been reported infrequently in patients receiving diltiazem hydrochloride: acute generalized exanthematous pustulosis, alopecia, erythema multiforme, exfoliative dermatitis, Stevens-Johnson syndrome, toxic epidermal necrolysis, extrapyramidal symptoms, gingival hyperplasia, hemolytic anemia, increased bleeding time, photosensitivity (including lichenoid keratosis and hyperpigmentation at sun-exposed ski… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Due to the potential for additive effects, caution and careful titration are warranted in patients receiving diltiazem hydrochloride concomitantly with other agents known to affect cardiac contractility and/or conduction (see WARNINGS ) . Pharmacologic studies indicate that there may be additive effects in prolonging AV conduction when using beta-blockers or digitalis concomitantly with diltiazem hydrochloride extended-release capsules (see WARNINGS ) . Diltiazem is both a substrate and an inhibitor of the Pg-p and cytochrome P450 3A4 enzyme system which may affect exposure to diltiazem and concomitant drugs metabolized by those pathways.
Patients with renal and/or hepatic impairment may be particularly at risk of exposure changes. Anesthetics: The depression of cardiac contractility, conductivity, and automaticity as well as the vascular dilation associated with anesthetics may be potentiated by calcium channel blockers. When used concomitantly, anesthetics and calcium channel blockers should be titrated carefully.
Benzodiazepines: Studies showed that diltiazem increased the AUC of midazolam and triazolam by 3- to 4-fold and the C max by 2-fold, compared to placebo. The elimination half-life of midazolam and triazolam also increased (1.5- to 2.5-fold) during coadministration with diltiazem. These pharmacokinetic effects seen during diltiazem coadministration can result in increased clinical effects (e.g., prolonged sedation) of both midazolam and triazolam.
Beta-blockers: Controlled and uncontrolled domestic studies suggest that concomitant use of diltiazem hydrochloride and beta-blockers is usually well tolerated, but available data are not sufficient to predict the effects of concomitant treatment in patients with left ventricular dysfunction or cardiac conduction abnormalities. Administration of diltiazem hydrochloride concomitantly with propranolol in five normal volunteers resulted in increased propranolol levels in all subjects and bioavailability of propranolol was increased approximately 50%.
In vitro, propranolol appears to be displaced from its binding sites by diltiazem. If combination therapy is initiated or withdrawn in conjunction with propranolol, an adjustment in the propranolol dose may be warranted (see WARNINGS ) . Buspirone: In nine healthy subjects, diltiazem significantly increased the mean buspirone AUC 5.5-fold and C max 4.1-fold compared to placebo.
The T ½ and T max of buspirone were not significantly affected by diltiazem. Enhanced effects and increased toxicity of buspirone may be possible during concomitant administration with diltiazem. Subsequent dose adjustments may be necessary during coadministration, and should be based on clinical assessment.
Carbamazepine: Concomitant administration of diltiazem with carbamazepine has been reported to result in elevated serum levels of carbamazepine (40% to 72% increase), resulting in toxicity in some cases. Patients receiving these drugs concurrently should be monitored for a potential drug interaction. Cimetidine: A study in six healthy volunteers has shown a significant increase in peak diltiazem plasma levels (58%) and AUC (53%) after a 1-week course of cimetidine 1200 mg/day and a single dose of diltiazem 60 mg.
Ranitidine produced smaller, nonsignificant increases. The effect may be mediated by cimetidine’s known inhibition of hepatic cytochrome P450, the enzyme system responsible for the first-pass metabolism of diltiazem. Patients currently receiving diltiazem therapy should be carefully monitored for a change in pharmacological effect when initiating and discontinuing therapy with cimetidine.
An adjustment in the diltiazem dose may be warranted. Clonidine: Sinus bradycardia resulting in hospitalization and pacemaker insertion has been reported in association with the use of clonidine concurrently with diltiazem. Monitor heart rate in patients receiving concomitant diltiazem and clonidine.
Cyclosporine: A pharmacokinetic interacti… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy Reproduction studies have been conducted in mice, rats, and rabbits. Administration of doses ranging from 4 to 6 times (depending on species) the upper limit of the optimum dosage range in clinical trials (480 mg/day or 8 mg/kg/day for a 60-kg patient) resulted in embryo and fetal lethality. These studies revealed, in one species or another, a propensity to cause abnormalities of the skeleton, heart, retina, and tongue.
Also observed were reductions in early individual pup weights and pup survival, prolonged delivery and increased incidence of stillbirths. There are no well-controlled studies in pregnant women; therefore, use diltiazem hydrochloride in pregnant women only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in children have not been established.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of diltiazem did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE The oral LD 50S in mice and rats range from 415 to 740 mg/kg and from 560 to 810 mg/kg, respectively. The intravenous LD 50S in these species were 60 and 38 mg/kg, respectively. The oral LD 50 in dogs is considered to be in excess of 50 mg/kg, while lethality was seen in monkeys at 360 mg/kg.
The toxic dose in man is not known. Due to extensive metabolism, blood levels after a standard dose of diltiazem can vary over tenfold, limiting the usefulness of blood levels in overdose cases. There have been 29 reports of diltiazem overdose in doses ranging from less than 1 g to 10.8 g.
Sixteen of these reports involved multiple drug ingestions. Twenty-two reports indicated patients had recovered from diltiazem overdose ranging from less than 1 g to 10.8 g. There were seven reports with a fatal outcome; although the amount of diltiazem ingested was unknown, multiple drug ingestions were confirmed in six of the seven reports.
Events observed following diltiazem overdose included bradycardia, hypotension, heart block, and cardiac failure. Most reports of overdose described some supportive medical measure and/or drug treatment. Bradycardia frequently responded favorably to atropine as did heart block, although cardiac pacing was also frequently utilized to treat heart block.
Fluids and vasopressors were used to maintain blood pressure, and in cases of cardiac failure, inotropic agents were administered. In addition, some patients received treatment with ventilatory support, activated charcoal, and/or intravenous calcium. Evidence of the effectiveness of intravenous calcium administration to reverse the pharmacological effects of diltiazem overdose was conflicting.
In the event of overdose or exaggerated response, appropriate supportive measures should be employed in addition to gastrointestinal decontamination. Diltiazem does not appear to be removed by peritoneal or hemodialysis. Based on the known pharmacological effects of diltiazem and/or reported clinical experiences, the following measures may be considered: Bradycardia: Administer atropine (0.60 to 1.0 mg).
If there is no response to vagal blockage, administer isoproterenol cautiously. High-Degree AV Block: Treat as for bradycardia above. Fixed high-degree AV block should be treated with cardiac pacing.
Cardiac Failure: Administer inotropic agents (isoproterenol, dopamine, or dobutamine) and diuretics. Hypotension: Vasopressors (e.g., dopamine or norepinephrine). Actual treatment and dosage should depend on the severity of the clinical situation and the judgment and experience of the treating physician.
In a few reported cases, overdose with calcium channel blockers has been associated with hypotension and bradycardia, initially refractory to atropine but becoming more responsive to this treatment when the patients received large doses (close to 1 gram/hour for more than 24 hours) of calcium chloride. Due to extensive metabolism, plasma concentrations after a standard dose of diltiazem can vary over tenfold, which significantly limits their value in evaluation cases of overdosage. Charcoal hemoperfusion has been used successfully as an adjunct therapy to hasten drug elimination.
Overdoses with as much as 10.8 g of oral diltiazem have been successfully treated using appropriate supportive care.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The therapeutic effects of diltiazem hydrochloride are believed to be related to its ability to inhibit the cellular influx of calcium ions during membrane depolarization of cardiac and vascular smooth muscle. Mechanisms of Action Hypertension: Diltiazem produces its antihypertensive effect primarily by relaxation of vascular smooth muscle and the resultant decrease in peripheral vascular resistance. The magnitude of blood pressure reduction is related to the degree of hypertension: thus hypertensive individuals experience an antihypertensive effect, whereas there is only a modest fall in blood pressure in normotensives.
Angina: Diltiazem hydrochloride has been shown to produce increases in exercise tolerance, probably due to its ability to reduce myocardial oxygen demand. This is accomplished via reductions in heart rate and systemic blood pressure at submaximal and maximal workloads. Diltiazem has been shown to be a potent dilator of coronary arteries, both epicardial and subendocardial.
Spontaneous and ergonovine-induced coronary artery spasms are inhibited by diltiazem. In animal models, diltiazem interferes with the slow inward (depolarizing) current in excitable tissue. It causes excitation-contraction uncoupling in various myocardial tissues without changes in the configuration of the action potential.
Diltiazem produces relaxation of the coronary vascular smooth muscle and dilation of both large and small coronary vascular smooth muscle and dilation of both large and small coronary arteries at drug levels which cause little or no negative inotropic effect. The resultant increases in coronary blood flow (epicardial and subendocardial) occur in ischemic and nonischemic models and are accompanied by dose-dependent decreases in systemic blood pressure and decreases in peripheral resistance. Hemodynamic and Electrophysiologic Effects Like other calcium channel antagonists, diltiazem decreases sinoatrial and atrioventricular conduction in isolated tissues and has a negative inotropic effect in isolated preparations.
In the intact animal, prolongation of the AH interval can be seen at higher doses. In man, diltiazem prevents spontaneous and ergonovine-provoked coronary artery spasm. It causes a decrease in peripheral vascular resistance and a modest fall in blood pressure in normotensive individuals and, in exercise tolerance studies in patients with ischemic heart disease, reduces the heart rate-blood pressure product for any given workload.
Studies to date, primarily in patients with good ventricular function, have not revealed evidence of a negative inotropic effect; cardiac output, ejection fraction, and left ventricular end-diastolic pressure have not been affected. Such data have no predictive value with respect to effects in patients with poor ventricular function, and increased heart failure has been reported in patients with preexisting impairment of ventricular function. There are as yet few data on the interaction of diltiazem and beta-blockers in patients with poor ventricular function.
Resting heart rate is usually slightly reduced by diltiazem. Diltiazem hydrochloride extended-release capsules produce antihypertensive effects both in the supine and standing positions. Postural hypotension is infrequently noted upon suddenly assuming an upright position.
No reflex tachycardia is associated with the chronic antihypertensive effects. Diltiazem hydrochloride decreases vascular resistance, increases cardiac output (by increasing stroke volume), and produces a slight decrease or no change in heart rate. During dynamic exercise, increases in diastolic pressure are inhibited while maximum achievable systolic pressure is usually reduced.
Chronic therapy with diltiazem hydrochloride produces no change or an increase in plasma catecholamines. No increased activity of the renin-angiotensin-aldosterone axis has been observed. Diltiazem hydrochloride reduces the renal and peripheral effects of angiotensi… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
Mechanisms of Action Hypertension: Diltiazem produces its antihypertensive effect primarily by relaxation of vascular smooth muscle and the resultant decrease in peripheral vascular resistance. The magnitude of blood pressure reduction is related to the degree of hypertension: thus hypertensive individuals experience an antihypertensive effect, whereas there is only a modest fall in blood pressure in normotensives. Angina: Diltiazem hydrochloride has been shown to produce increases in exercise tolerance, probably due to its ability to reduce myocardial oxygen demand.
This is accomplished via reductions in heart rate and systemic blood pressure at submaximal and maximal workloads. Diltiazem has been shown to be a potent dilator of coronary arteries, both epicardial and subendocardial. Spontaneous and ergonovine-induced coronary artery spasms are inhibited by diltiazem.
In animal models, diltiazem interferes with the slow inward (depolarizing) current in excitable tissue. It causes excitation-contraction uncoupling in various myocardial tissues without changes in the configuration of the action potential. Diltiazem produces relaxation of the coronary vascular smooth muscle and dilation of both large and small coronary vascular smooth muscle and dilation of both large and small coronary arteries at drug levels which cause little or no negative inotropic effect.
The resultant increases in coronary blood flow (epicardial and subendocardial) occur in ischemic and nonischemic models and are accompanied by dose-dependent decreases in systemic blood pressure and decreases in peripheral resistance. Hemodynamic and Electrophysiologic Effects Like other calcium channel antagonists, diltiazem decreases sinoatrial and atrioventricular conduction in isolated tissues and has a negative inotropic effect in isolated preparations. In the intact animal, prolongation of the AH interval can be seen at higher doses.
In man, diltiazem prevents spontaneous and ergonovine-provoked coronary artery spasm. It causes a decrease in peripheral vascular resistance and a modest fall in blood pressure in normotensive individuals and, in exercise tolerance studies in patients with ischemic heart disease, reduces the heart rate-blood pressure product for any given workload. Studies to date, primarily in patients with good ventricular function, have not revealed evidence of a negative inotropic effect; cardiac output, ejection fraction, and left ventricular end-diastolic pressure have not been affected.
Such data have no predictive value with respect to effects in patients with poor ventricular function, and increased heart failure has been reported in patients with preexisting impairment of ventricular function. There are as yet few data on the interaction of diltiazem and beta-blockers in patients with poor ventricular function. Resting heart rate is usually slightly reduced by diltiazem.
Diltiazem hydrochloride extended-release capsules produce antihypertensive effects both in the supine and standing positions. Postural hypotension is infrequently noted upon suddenly assuming an upright position. No reflex tachycardia is associated with the chronic antihypertensive effects.
Diltiazem hydrochloride decreases vascular resistance, increases cardiac output (by increasing stroke volume), and produces a slight decrease or no change in heart rate. During dynamic exercise, increases in diastolic pressure are inhibited while maximum achievable systolic pressure is usually reduced. Chronic therapy with diltiazem hydrochloride produces no change or an increase in plasma catecholamines.
No increased activity of the renin-angiotensin-aldosterone axis has been observed. Diltiazem hydrochloride reduces the renal and peripheral effects of angiotensin II. Hypertensive animal models respond to diltiazem with reductions in blood pressure and increased urinary output and natriuresis without a change in urinary sodium/potassium ratio.
In man, transient natriuresis and kaliuresis ha… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Diltiazem hydrochloride extended-release capsules, USP Strength Description Quantity NDC# 120 mg #3 lavender/lavender capsule imprinted: 120 90 68682-367-90 180 mg #2 white/blue-green capsule imprinted: 180 90 68682-368-90 240 mg #1 blue-green/lavender capsule imprinted: 240 90 68682-369-90 300 mg #0 white/lavender capsule imprinted: 300 90 68682-370-90 360 mg #0 blue-green/blue-green capsule imprinted: 360 90 68682-371-90 420 mg #00 white/white capsule imprinted: 420 90 68682-372-90 Storage Conditions: Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature].
Avoid excessive humidity.
📦 Storage and Handling ▾
Storage Conditions: Store at 25°C (77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Avoid excessive humidity.
📋 Description ▾
DESCRIPTION Diltiazem hydrochloride is a calcium ion cellular influx inhibitor (slow channel blocker). Chemically, diltiazem hydrochloride is 1,5-Benzothiazepin-4(5 H )-one, 3-(acetyloxy)-5-[2-(dimethylamino)ethyl]-2, 3-dihydro-2-(4-methoxyphenyl)-, monohydrochloride, (+)- cis -. The chemical structure is: Diltiazem hydrochloride is a white to off-white crystalline powder with a bitter taste.
It is soluble in water, methanol and chloroform and has a molecular weight of 450.98. Diltiazem hydrochloride extended-release capsules contain diltiazem hydrochloride in extended-release beads at doses of 120, 180, 240, 300, 360 and 420 mg. Diltiazem hydrochloride extended-release capsules, USP also contain: black iron oxide, D&C Red No.
28, ethyl acrylate and methyl methacrylate copolymer dispersion, FD&C Blue No. 1, FD&C Green No. 3, FD&C Red No.
40, gelatin, hypromellose, magnesium stearate, microcrystalline cellulose, polysorbate, povidone, simethicone, sucrose stearate, talc, and titanium dioxide. USP Drug Release Test 6 For oral administration. Chemical Structure
⚠️ Precautions ▾
PRECAUTIONS General Diltiazem hydrochloride is extensively metabolized by the liver and excreted by the kidneys and in bile. As with any drug given over prolonged periods, laboratory parameters of renal and hepatic function should be monitored at regular intervals. The drug should be used with caution in patients with impaired renal or hepatic function.
In subacute and chronic dog and rat studies designed to produce toxicity, high doses of diltiazem were associated with hepatic damage. In special subacute hepatic studies, oral doses of 125 mg/kg and higher in rats were associated with histological changes in the liver which were reversible when the drug was discontinued. In dogs, doses of 20 mg/kg were also associated with hepatic changes; however, these changes were reversible with continued dosing.
Dermatological events (see ADVERSE REACTIONS ) may be transient and may disappear despite continued use of diltiazem hydrochloride. However, skin eruptions progressing to erythema multiforme and/or exfoliative dermatitis have also been infrequently reported. Should a dermatologic reaction persist, the drug should be discontinued.
Drug Interactions Due to the potential for additive effects, caution and careful titration are warranted in patients receiving diltiazem hydrochloride concomitantly with other agents known to affect cardiac contractility and/or conduction (see WARNINGS ) . Pharmacologic studies indicate that there may be additive effects in prolonging AV conduction when using beta-blockers or digitalis concomitantly with diltiazem hydrochloride extended-release capsules (see WARNINGS ) . Diltiazem is both a substrate and an inhibitor of the Pg-p and cytochrome P450 3A4 enzyme system which may affect exposure to diltiazem and concomitant drugs metabolized by those pathways.
Patients with renal and/or hepatic impairment may be particularly at risk of exposure changes. Anesthetics: The depression of cardiac contractility, conductivity, and automaticity as well as the vascular dilation associated with anesthetics may be potentiated by calcium channel blockers. When used concomitantly, anesthetics and calcium channel blockers should be titrated carefully.
Benzodiazepines: Studies showed that diltiazem increased the AUC of midazolam and triazolam by 3- to 4-fold and the C max by 2-fold, compared to placebo. The elimination half-life of midazolam and triazolam also increased (1.5- to 2.5-fold) during coadministration with diltiazem. These pharmacokinetic effects seen during diltiazem coadministration can result in increased clinical effects (e.g., prolonged sedation) of both midazolam and triazolam.
Beta-blockers: Controlled and uncontrolled domestic studies suggest that concomitant use of diltiazem hydrochloride and beta-blockers is usually well tolerated, but available data are not sufficient to predict the effects of concomitant treatment in patients with left ventricular dysfunction or cardiac conduction abnormalities. Administration of diltiazem hydrochloride concomitantly with propranolol in five normal volunteers resulted in increased propranolol levels in all subjects and bioavailability of propranolol was increased approximately 50%.
In vitro, propranolol appears to be displaced from its binding sites by diltiazem. If combination therapy is initiated or withdrawn in conjunction with propranolol, an adjustment in the propranolol dose may be warranted (see WARNINGS ) . Buspirone: In nine healthy subjects, diltiazem significantly increased the mean buspirone AUC 5.5-fold and C max 4.1-fold compared to placebo.
The T ½ and T max of buspirone were not significantly affected by diltiazem. Enhanced effects and increased toxicity of buspirone may be possible during concomitant administration with diltiazem. Subsequent dose adjustments may be necessary during coadministration, and should be based on clinical assessment.
Carbamazepine: Concomitant administration of diltiazem with carbamazepine has been reported to result in eleva… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Diltiazem is excreted in human milk. One report suggests that concentrations in breast milk may approximate serum levels. If use of diltiazem hydrochloride extended-release capsules is deemed essential, an alternative method of infant feeding should be instituted.
🧬 Pharmacokinetics ▾
Pharmacokinetics and Metabolism Diltiazem is well absorbed from the gastrointestinal tract but undergoes substantial hepatic first-pass effect. The absolute bioavailability of an oral dose of an immediate-release formulation (compared to intravenous administration) is approximately 40%. Only 2% to 4% of unchanged diltiazem appears in the urine.
The plasma elimination half-life of diltiazem is approximately 3.0 to 4.5 hours. Drugs which induce or inhibit hepatic microsomal enzymes may alter diltiazem disposition. Therapeutic blood levels of diltiazem appear to be in the range of 40 to 200 ng/mL.
There is a departure from linearity when dose strengths are increased; the half-life is slightly increased with dose. The two primary metabolites of diltiazem are desacetyldiltiazem and desmethyldiltiazem. The desacetyl metabolite is approximately 25% to 50% as potent a coronary vasodilator as diltiazem and is present in plasma at concentrations of 10% to 20% of parent diltiazem.
However, recent studies employing sensitive and specific analytical methods have confirmed the existence of several sequential metabolic pathways of diltiazem. As many as nine diltiazem metabolites have been identified in the urine of humans. Total radioactivity measurements following single intravenous dose administration in healthy volunteers suggest the presence of other unidentified metabolites.
These metabolites are more slowly excreted (with a half-life of total radioactivity of approximately 20 hours) and attain concentrations in excess of diltiazem. In vitro binding studies show diltiazem hydrochloride is 70% to 80% bound to plasma proteins. Competitive in vitro ligand binding studies have also shown diltiazem hydrochloride binding is not altered by therapeutic concentrations of digoxin, hydrochlorothiazide, phenylbutazone, propranolol, salicylic acid, or warfarin.
A study that compared patients with normal hepatic function to patients with cirrhosis who received immediate-release diltiazem found an increase in diltiazem elimination half-life and a 69% increase in bioavailability in the hepatically impaired patients. Patients with severely impaired renal function (creatinine clearance <50 mL/min) who received immediate-release diltiazem had modestly increased diltiazem concentrations compared to patients with normal renal function.
🧬 Pharmacodynamics ▾
Pharmacodynamics Hypertension: In short-term, double-blind, placebo-controlled clinical trials diltiazem hydrochloride extended-release capsules demonstrated a dose-related antihypertensive response among patients with mild to moderate hypertension. In one parallel-group study of 198 patients diltiazem hydrochloride extended-release capsules were given for four weeks. The changes in diastolic blood pressure measured at trough (24 hours after the dose) for placebo, 90 mg, 180 mg, 360 mg and 540 mg were -5.4, -6.3, -6.2, -8.2, and -11.8 mm Hg, respectively.
Supine diastolic blood pressure as well as standing diastolic and systolic blood pressures also showed statistically significant linear dose response effects. In another clinical trial that followed a dose-escalation design, diltiazem hydrochloride extended-release capsules also reduced blood pressure in a linear dose-related manner. Supine diastolic blood pressure measured following two-week intervals of treatment was reduced by -3.7 mm Hg with 120 mg/day versus -2.0 mm Hg with placebo, by -7.6 mm Hg after escalation to 240 mg/day versus -2.3 mm Hg with placebo, by -8.1 mm Hg after escalation to 360 mg/day versus -0.9 mm Hg with placebo, and by -10.8 mm Hg after escalation to 480/540 mg/day versus -2.2 mm Hg with placebo.
Angina: In a double-blind, parallel-group, placebo-controlled trial (approximately 50 patients/group, in patients with chronic stable angina), diltiazem hydrochloride extended-release capsules at doses of 120 to 540 mg/day increased exercise tolerance time. At trough, 24 hours after dosing, exercise tolerance times using a Bruce exercise protocol, increased by 14, 26, 41, 33 and 32 seconds over baseline for placebo and the 120 mg, 240 mg, 360 mg, and 540 mg treated patient groups, respectively. At peak, 8 hours after dosing, exercise tolerance times relative to baseline were statistically significantly increased by 13, 38, 64, 55 and 42 seconds for placebo and 120 mg, 240 mg, 360 mg, and 540 mg diltiazem hydrochloride extended-release capsule treated patients, respectively.
Compared to baseline, diltiazem hydrochloride extended-release capsule treated patients experienced statistically significant reductions in anginal attacks and decreased nitroglycerin requirements when compared to placebo treated patients. Pharmacokinetics and Metabolism Diltiazem is well absorbed from the gastrointestinal tract but undergoes substantial hepatic first-pass effect. The absolute bioavailability of an oral dose of an immediate-release formulation (compared to intravenous administration) is approximately 40%.
Only 2% to 4% of unchanged diltiazem appears in the urine. The plasma elimination half-life of diltiazem is approximately 3.0 to 4.5 hours. Drugs which induce or inhibit hepatic microsomal enzymes may alter diltiazem disposition.
Therapeutic blood levels of diltiazem appear to be in the range of 40 to 200 ng/mL. There is a departure from linearity when dose strengths are increased; the half-life is slightly increased with dose. The two primary metabolites of diltiazem are desacetyldiltiazem and desmethyldiltiazem.
The desacetyl metabolite is approximately 25% to 50% as potent a coronary vasodilator as diltiazem and is present in plasma at concentrations of 10% to 20% of parent diltiazem. However, recent studies employing sensitive and specific analytical methods have confirmed the existence of several sequential metabolic pathways of diltiazem. As many as nine diltiazem metabolites have been identified in the urine of humans.
Total radioactivity measurements following single intravenous dose administration in healthy volunteers suggest the presence of other unidentified metabolites. These metabolites are more slowly excreted (with a half-life of total radioactivity of approximately 20 hours) and attain concentrations in excess of diltiazem. In vitro binding studies show diltiazem hydrochloride is 70% to 80% bound to plasma proteins.
Competitive in vitro ligand binding s… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility A 24-month study in rats at oral dosage levels of up to 100 mg/kg/day and a 21-month study in mice at oral dosage levels of up to 30 mg/kg/day showed no evidence of carcinogenicity. There was also no mutagenic response in vitro or in vivo in mammalian cell assays or in vitro in bacteria. No evidence of impaired fertility was observed in a study performed in male and female rats at oral dosages of up to 100 mg/kg/day.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 120 mg Capsule Bottle Label NDC 68682-367-90 Rx only DILTIAZEM HYDROCHLORIDE 120 mg Extended-Release Capsules, USP* Do not use if bottle closure seal is broken. 90 Capsules OCEANSIDE PHARMACEUTICALS 120 mg label
PRINCIPAL DISPLAY PANEL - 180 mg Capsule Bottle Label NDC 68682-368-90 Rx only DILTIAZEM HYDROCHLORIDE 180 mg Extended-Release Capsules, USP* Do not use if bottle closure seal is broken. 90 Capsules OCEANSIDE PHARMACEUTICALS 180 mg label
PRINCIPAL DISPLAY PANEL - 240 mg Capsule Bottle Label NDC 68682-369-90 Rx only DILTIAZEM HYDROCHLORIDE 240 mg Extended-Release Capsules, USP* Do not use if bottle closure seal is broken. 90 Capsules OCEANSIDE PHARMACEUTICALS 240 mg label
PRINCIPAL DISPLAY PANEL - 300 mg Capsule Bottle Label NDC 68682-370-90 Rx only DILTIAZEM HYDROCHLORIDE 300 mg Extended-Release Capsules, USP* Do not use if bottle closure is broken. 90 Capsules OCEANSIDE PHARMACEUTICALS 300 mg label
PRINCIPAL DISPLAY PANEL - 360 mg Capsule Bottle Label NDC 68682-371-90 Rx only DILTIAZEM HYDROCHLORIDE 360 mg Extended-Release Capsules, USP* Do not use if bottle closure seal is broken. 90 Capsules OCEANSIDE PHARMACEUTICALS 360 mg label
PRINCIPAL DISPLAY PANEL - 420 mg Capsule Bottle Label NDC 68682-372-90 Rx only DILTIAZEM HYDROCHLORIDE 420 mg Extended-Release Capsules, USP* Do not use if bottle closure seal is broken. 90 Capsules OCEANSIDE PHARMACEUTICALS 420 mg label