
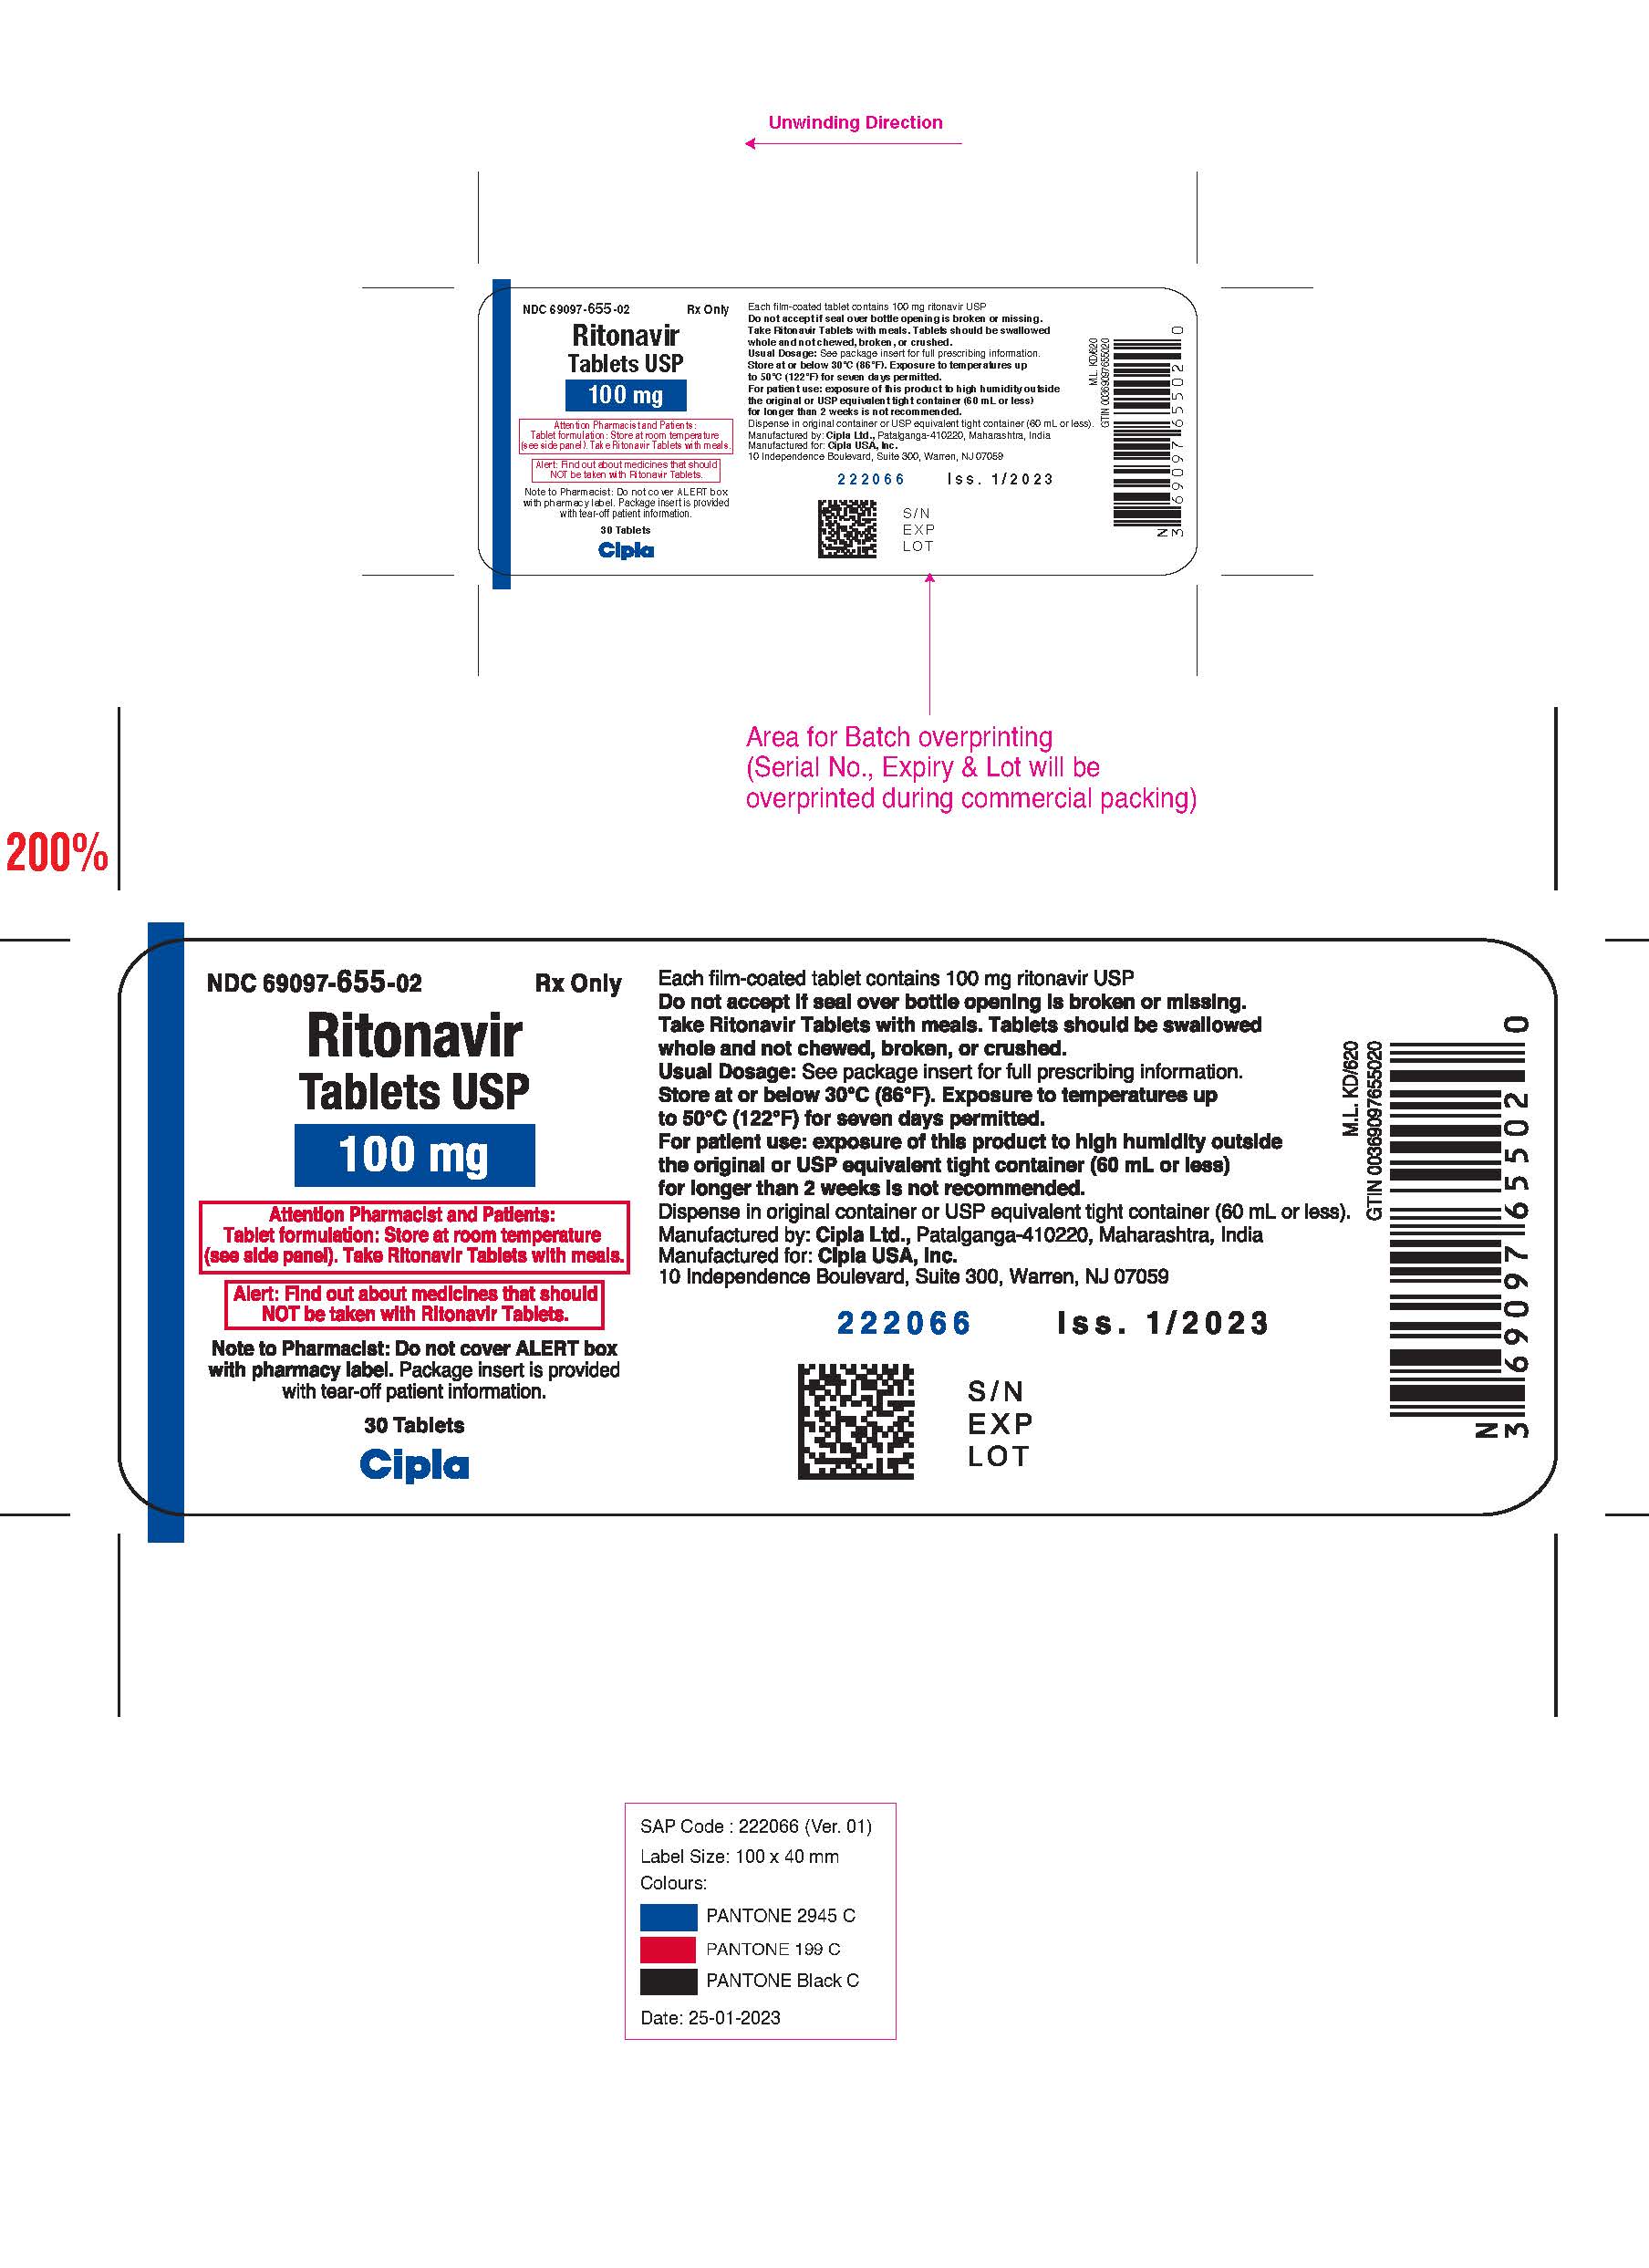
Ritonavir film coated ritonavir 100 mg 100 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Protease Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Ritonavir is used to treat human immunodeficiency virus (HIV) infection. Ritonavir is in a class of medications called protease inhibitors. It works by decreasing the amount of HIV in the blood. Although ritonavir does not cure HIV, it may decrease your chance of developing acquired immunodeficiency syndrome (AIDS) and HIV-related illnesses. Taking these medications and making other lifestyle changes may decrease the risk of transmitting the HIV virus to other people.
Read the full MedlinePlus article ↗- Ritonavir blocks an enzyme called protease that HIV needs to replicate. Without it, the virus can't make mature copies of itself. But ritonavir on its own isn't enough to fully con...
- What exactly does ritonavir do, and why do I have to take it with other HIV medicines?
- You're right — stomach side effects like diarrhea, nausea, vomiting, and abdominal pain are very common, especially when you first start. The good news is these often improve after...
- I've heard ritonavir causes a lot of stomach problems. What should I expect?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII L11K75P92J
A mineral salt made from calcium and phosphate. It acts as a filler and binder in tablets to add bulk and help hold the medicine together in solid form.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII ND2M416302
Isopropyl alcohol is a clear liquid solvent derived from petroleum. In medicines, it dissolves active ingredients and other components, helps the product flow smoothly, and aids in sterilization during manufacturing.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII 6W9PS8B71J
Sorbitan monolaurate is a natural oil-derived emulsifier made from sorbitol and lauric acid. It helps mix oils and water-based ingredients together in the medicine so the formula stays uniform and smooth.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
11 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.607 | $18.20 / 30 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $2.32 | $69.66 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Ritonavir 100 mg 60687-0420-25 | American | 1 tablet | $0.607 | AB | Availability likely | — |
| Ritonavir film coated 100 mgthis 69097-0655-02 | Cipla | 30 tablets | $0.607 | AB | Availability likely | — |
| Norvir 100 mg 00074-2340-30 | AbbVie | 30 tablets | $8.328 | AB | Availability likely | +1273% |
| Ritonavir 100 mg 31722-0597-12 | Camber | 120 tablets | — | AB | FDA listed | — |
| Ritonavir 100 mg 63629-5702-01 | Bryant | 15 tablets | — | AB | FDA listed | — |
| Ritonavir 100 mg 65162-0061-06 | Amneal | 60 tablets | — | — | FDA listed | — |
| Ritonavir 100 mg 65862-0687-01 | Aurobindo | 100 tablets | — | — | FDA listed | — |
| Ritonavir 100 mg 68071-3898-03 | NuCare | 3 tablets | — | AB | FDA listed | — |
| Ritonavir 100 mg 71335-2610-01 | Bryant | 15 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Status |
|---|---|---|---|---|---|
| 69097-0655-02 You're viewing this | 30 TABLET in 1 CONTAINER (69097-655-02) | $0.6067 / ea | $18.20 | 2022-03-23 | Active |
| 69097-0655-08 | 120 TABLET in 1 CONTAINER (69097-655-08) | — | — | 2022-03-23 | Active |
You're viewing the smallest of 2 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 69097-0655-02?
What is the difference between NDC 69097-0655-02 and NDC 69097-0655-08?
What NDC number is used to bill for this package of Ritonavir film coated ritonavir 100 mg 100 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: DRUG-DRUG INTERACTIONS LEADING TO POTENTIALLY SERIOUS AND/OR LIFE THREATENING REACTIONS Co-administration of ritonavir with several classes of drugs including sedative hypnotics, antiarrhythmics, or ergot alkaloid preparations may result in potentially serious and/or life-threatening adverse events due to possible effects of ritonavir on the hepatic metabolism of certain drugs. Review medications taken by patients prior to prescribing ritonavir or when prescribing other medications to patients already taking ritonavir. [see Contraindications 4 , Warnings and Precautions 5.1 ] WARNING: DRUG-DRUG INTERACTIONS LEADING TO POTENTIALLY SERIOUS AND/OR LIFE THREATENING REACTIONS See full prescribing information for complete boxed warning Co-administration of ritonavir with several classes of drugs including sedative hypnotics, antiarrhythmics, or ergot alkaloid preparations may result in potentially serious and/or life-threatening adverse events due to possible effects of ritonavir on the hepatic metabolism of certain drugs.
Review medications taken by patients prior to prescribing ritonavir or when prescribing other medications to patients already taking ritonavir. ( 4 , 5.1 ) .
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Ritonavir tablets are indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection. Ritonavir tablets are HIV protease inhibitor indicated in combination with other antiretroviral agents for the treatment of HIV-1 infection. ( 1 ).
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Adult patients: 600 mg twice-daily with meals. ( 2.3 ) Pediatrics patients: The recommended twice daily dose for children greater than one month of age is based on body surface area and should not exceed 600 mg twice daily with meals. ( 2.4 , 5.2 ) Ritonavir oral solution should not be administered to neonates before a postmenstrual age (first day of the mother's last menstrual period to birth plus the time elapsed after birth) of 44 weeks has been attained.
( 2.4 , 5.2 ) Ritonavir oral powder can only be used for dosing increments of 100 mg. ( 2.4 ) Dose modification for ritonavir is necessary when used with other protease inhibitors. ( 2.6 )
2.1General Administration Recommendations Ritonavir must be used in combination with other antiretroviral agents. Ritonavir is administered orally. Ritonavir tablets should be swallowed whole, and not chewed, broken or crushed.
Take ritonavir with meals. General Dosing Guidelines: Patients who take the 600 mg twice daily soft gel capsule ritonavir dose may experience more gastrointestinal side effects such as nausea, vomiting, abdominal pain or diarrhea when switching from the soft gel capsule to the tablet formulation because of greater maximum plasma concentration (Cmax) achieved with the tablet formulation relative to the soft gel capsule [see Clinical Pharmacology ( 12.3 )] . Patients should also be aware that these adverse events (gastrointestinal or paresthesias) may diminish as therapy is continued.
2.3Dosage Recommendations in Adults Recommended Dosage for Treatment of HIV-1: The recommended dosage of ritonavir is 600 mg twice daily by mouth to be taken with meals. Use of a dose titration schedule may help to reduce treatment-emergent adverse events while maintaining appropriate ritonavir plasma levels. Ritonavir should be started at no less than 300 mg twice daily and increased at 2 to 3 day intervals by 100 mg twice daily.
The maximum dose of 600 mg twice daily should not be exceeded upon completion of the titration [see Dosage and Administration ( 2.6 )] . Pregnant Women: Ritonavir oral solution is not recommended during pregnancy due to its ethanol content. Ritonavir oral solution contains the excipients ethanol (approx.
43% v/v) and propylene glycol (approx. 27% w/v) [see Use in Specific Populations ( 8.1 )] .
2.4Dosage Recommendations in Pediatric Patients Ritonavir must be used in combination with other antiretroviral agents [see Dosage and Administration ( 2 )] . The recommended dosage of ritonavir in pediatric patients older than 1 month is 350 to 400 mg per m 2 twice daily by mouth to be taken with meals and should not exceed 600 mg twice daily. Ritonavir should be started at 250 mg per m 2 twice daily and increased at 2 to 3 day intervals by 50 mg per m 2 twice daily.
If patients do not tolerate 400 mg per m 2 twice daily due to adverse events, the highest tolerated dose may be used for maintenance therapy in combination with other antiretroviral agents, however, alternative therapy should be considered [see Dosage and Administration ( 2.6 )] . Pediatric Dosage Guidelines for Oral Solution Ritonavir oral solution should not be administered to neonates before a postmenstrual age (first day of the mother's last menstrual period to birth plus the time elapsed after birth) of 44 weeks has been attained [see Warnings and Precautions ( 5.2 )] .
Ritonavir oral solution contains the excipients ethanol (approx. 43% v/v) and propylene glycol (approx. 27% w/v).
Special attention should be given to accurate calculation of the dose of ritonavir, transcription of the medication order, dispensing information and dosing instructions to minimize the risk for medication errors, and overdose. This is especially important for young children. Total amounts of ethanol and propylene glycol from all medicines that are to be given to pediatric patients 1 to 6 months of age should be taken into account in order to avoid toxicity from these excipients [see Warnings…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Ritonavir Tablets USP, 100 mg are a white-colored, oval shaped, shallow, film-coated tablet with "54" debossed on one side and "247" debossed on the other side. Tablet: 100 mg ritonavir. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS When co-administering ritonavir with other protease inhibitors, see the full prescribing information for that protease inhibitor including contraindication information. Ritonavir is contraindicated in patients with known hypersensitivity (e.g., toxic epidermal necrolysis (TEN) or Stevens-Johnson syndrome) to ritonavir or any of its ingredients. Ritonavir is contraindicated with drugs that are highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening reactions [see Drug Interactions ( 7.1 ) and Clinical Pharmacology ( 12.3 )] . o Alpha 1- Adrenoreceptor Antagonist: alfuzosin o Antianginal: ranolazine o Antiarrhythmics: amiodarone, dronedarone, flecainide, propafenone, quinidine o Antifungal: voriconazole o Anti-gout: colchicine o Antipsychotics: lurasidone, pimozide o Ergot Derivatives: dihydroergotamine, ergotamine, methylergonovine o GI Motility Agent: cisapride o HMG-CoA Reductase Inhibitors: lovastatin, simvastatin o Microsomal triglyceride transfer protein (MTTP) Inhibitor: lomitapide o PDE5 Inhibitor: sildenafil (Revatio ® ) when used for the treatment of pulmonary arterial hypertension o Sedative/Hypnotics: triazolam, orally administered midazolam Ritonavir is contraindicated with drugs that are potent CYP3A inducers where significantly reduced ritonavir plasma concentrations may be associated with the potential for loss of virologic response and possible resistance and cross-resistance [see Drug Interactions ( 7.2 ) and Clinical Pharmacology ( 12.3 )] . o Anticancer Agents: apalutamide o Herbal Products: St.
John's Wort (hypericum perforatum) Ritonavir is contraindicated in patients with known hypersensitivity to ritonavir (e.g., toxic epidermal necrolysis, Stevens-Johnson syndrome) or any of its ingredients. ( 4 ) Co-administration with drugs highly dependent on CYP3A for clearance and for which elevated plasma concentrations may be associated with serious and/or life-threatening events.( 4 ) Co-administration with drugs that significantly reduce ritonavir. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS The following have been observed in patients receiving ritonavir: The concomitant use of ritonavir and certain other drugs may result in known or potentially significant drug interactions. Consult the full prescribing information prior to and during treatment for potential drug interactions. ( 5.1 , 7.2 ) Toxicity in preterm neonates: Ritonavir oral solution should not be used in preterm neonates in the immediate postnatal period because of possible toxicities.
A safe and effective dose of Ritonavir oral solution in this patient population has not been established. ( 2.4 , 5.2 ) Hepatotoxicity: Fatalities have occurred. Monitor liver function before and during therapy, especially in patients with underlying hepatic disease, including hepatitis B and hepatitis C, or marked transaminase elevations.( 5.3 , 8.6 ) Pancreatitis: Fatalities have occurred; suspend therapy as clinically appropriate.
( 5.4 ) Allergic Reactions/Hypersensitivity: Allergic reactions have been reported and include anaphylaxis, toxic epidermal necrolysis, Stevens-Johnson syndrome, bronchospasm and angioedema. Discontinue treatment if severe reactions develop.( 5.5 , 6.2 ) PR interval prolongation may occur in some patients. Cases of second and third degree heart block have been reported.
Use with caution with patients with preexisting conduction system disease, ischemic heart disease, cardiomyopathy, underlying structural heart disease or when administering with other drugs that may prolong the PR interval. ( 5.6 , 12.3 ) Total cholesterol and triglycerides elevations: Monitor prior to therapy and periodically thereafter.( 5.7 ) Patients may develop new onset or exacerbations of diabetes mellitus, hyperglycemia.( 5.8 ) Patients may develop immune reconstitution syndrome. ( 5.9 ) Patients may develop redistribution/accumulation of body fat.( 5.10 ) Hemophilia: Spontaneous bleeding may occur, and additional factor VIII may be required.( 5.11 )
5.1Risk of Serious Adverse Reactions Due to Drug Interactions Initiation of ritonavir, a CYP3A inhibitor, in patients receiving medications metabolized by CYP3A or initiation of medications metabolized by CYP3A in patients already receiving ritonavir, may increase plasma concentrations of medications metabolized by CYP3A. Initiation of medications that inhibit or induce CYP3A may increase or decrease concentrations of ritonavir, respectively. These interactions may lead to: Clinically significant adverse reactions, potentially leading to severe, life-threatening, or fatal events from greater exposures of concomitant medications.
Clinically significant adverse reactions from greater exposures of ritonavir. Loss of therapeutic effect of ritonavir and possible development of resistance. When co-administering ritonavir with other protease inhibitors, see the full prescribing information for that protease inhibitor including important Warnings and Precautions.
See Table 4 for steps to prevent or manage these possible and known significant drug interactions, including dosing recommendations [see Drug Interactions ( 7 )] . Consider the potential for drug interactions prior to and during ritonavir therapy; review concomitant medications during ritonavir therapy, and monitor for the adverse reactions associated with the concomitant medications [see Contraindications ( 4 ) and Drug Interactions ( 7 )] .
5.2Toxicity in Preterm Neonates Ritonavir oral solution contains the excipients ethanol (approx. 43% v/v) and propylene glycol (approx. 27% w/v).
When administered concomitantly with propylene glycol, ethanol competitively inhibits the metabolism of propylene glycol, which may lead to elevated concentrations. Preterm neonates may be at an increased risk of propylene glycol-associated adverse events due to diminished ability to metabolize propylene glycol, thereby leading to accumulation and potential adverse events. Postmarketing life-threatening cases of cardiac toxicity (including complete AV block, b…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the labeling. Drug Interactions [see Warnings and Precautions ( 5.1 )] Hepatotoxicity [see Warnings and Precautions ( 5.3 )] Pancreatitis [see Warnings and Precautions ( 5.4 )] Allergic Reactions/Hypersensitivity [see Warnings and Precautions ( 5.5 )] When co-administering ritonavir with other protease inhibitors, see the full prescribing information for that protease inhibitor including adverse reactions. The most frequently reported adverse drug reactions among patients receiving ritonavir alone or in combination with other antiretroviral drugs were gastrointestinal (including diarrhea, nausea, vomiting, abdominal pain (upper and lower), neurological disturbances (including paresthesia and oral paresthesia), rash, and fatigue/asthenia.( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Cipla Ltd., India at 1-866-604-3268 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trial Experience Because clinical trials are conducted under widely varying conditions, adverse reactions rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Adverse Reactions in Adults The safety of ritonavir alone and in combination with other antiretroviral agents was studied in 1,755 adult patients. Table 2 lists treatment-emergent Adverse Reactions (with possible or probable relationship to study drug) occurring in greater than or equal to 1% of adult patients receiving ritonavir in combined Phase II/IV studies.
The most frequently reported adverse drug reactions among patients receiving ritonavir alone or in combination with other antiretroviral drugs were gastrointestinal (including diarrhea, nausea, vomiting, abdominal pain (upper and lower)), neurological disturbances (including paresthesia and oral paresthesia), rash, and fatigue/asthenia. Table 2. Treatment-Emergent Adverse Reactions (With Possible or Probable Relationship to Study Drug) Occurring in greater than or equal to 1% of Adult Patients Receiving Ritonavir in Combined Phase II/IV Studies (N = 1,755) Adverse Reactions n % Eye disorders Blurred vision 113
6.4 Gastrointestinal Disorders Abdominal Pain (upper and lower) * 464
26.4 Diarrhea including severe with electrolyte imbalance * 1,192
67.9 Dyspepsia 201
11.5 Flatulence 142
8.1 Gastrointestinal hemorrhage * 41
2.3 Gastroesophageal reflux disease (GERD) 19
1.1 Nausea 1,007
57.4 Vomiting * 559
31.9 General disorders and administration site conditions Fatigue including asthenia * 811
46.2 Hepatobiliary Disorders Blood bilirubin increased (including jaundice) * 25
1.4 Hepatitis (including increased AST, ALT, GGT) * 153
8.7 Immune system disorders Hypersensitivity including urticaria and face edema * 114
8.2 Metabolism and nutrition disorders Edema and peripheral edema* 110
6.3 Gout* 24
1.4 Hypercholesterolemia * 52
3.0 Hypertriglyceridemia * 158
9.0 Lipodystrophy acquired * 51
2.9 Musculoskeletal and connective tissue disorders Arthralgia and back pain * 326
18.6 Myopathy/creatine phosphokinase increased * 66
3.8 Myalgia 156
8.9 Nervous system disorders Dizziness* 274
15.6 Dysgeusia * 285
16.2 Paresthesia (including oral paresthesia) * 889
50.7 Peripheral neuropathy 178
10.1 Syncope * 58
3.3 Psychiatric disorders Confusion* 52
3.0 Disturbance in attention 44
2.5 Renal and urinary disorders Increased urination * 74
4.2 Respiratory, thoracic and mediastinal disorders Coughing* 380
21.7 Oropharyngeal Pain * 279
15.9 Skin and subcutaneous tissue disorders Acne* 67
3.8 Pruritus * 214
12.2 Rash (includes erythematous and maculopapular)* 475
27.1 Vascular Disorders Flushing, feeling hot* 232
13.2 Hypertension* 58
3.3 Hypotension including orthostatic hypotension* 30
1.7Peripheral Coldness * 21 1.2 *Represents a medical concept including several similar MedDRA PTs Laboratory Abnormalities in Adults Table 3 sh…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS When co-administering ritonavir with other protease inhibitors (atazanavir, darunavir, fosamprenavir, saquinavir, and tipranavir), see the full prescribing information for that protease inhibitor including important information for drug interactions. Co-administration of ritonavir can alter the concentrations of other drugs. The potential for drug-drug interactions must be considered prior to and during therapy. ( 4 , 5.1 , 7 , 12.3 )
7.1Potential for Ritonavir to Affect Other Drugs Ritonavir is an inhibitor of cytochrome P450 3A (CYP3A) and may increase plasma concentrations of agents that are primarily metabolized by CYP3A. Agents that are extensively metabolized by CYP3A and have high first pass metabolism appear to be the most susceptible to large increases in AUC (greater than 3-fold) when co-administered with ritonavir. Thus, co-administration of ritonavir with drugs highly dependent on CYP3A for clearance and for which elevated plasma concentrations are associated with serious and/or life-threatening events is contraindicated.
Co-administration with other CYP3A substrates may require a dose adjustment or additional monitoring as shown in Table 4. Ritonavir also inhibits CYP2D6 to a lesser extent. Co-administration of substrates of CYP2D6 with ritonavir could result in increases (up to 2-fold) in the AUC of the other agent, possibly requiring a proportional dosage reduction.
Ritonavir also appears to induce CYP3A, CYP1A2, CYP2C9, CYP2C19, and CYP2B6 as well as other enzymes, including glucuronosyl transferase. These examples are a guide and not considered a comprehensive list of all possible drugs that may interact with ritonavir. The healthcare provider should consult appropriate references for comprehensive information.
7.2Established and Other Potentially Significant Drug Interactions Table 4 provides a list of established or potentially clinically significant drug interactions. Alteration in dose or regimen may be recommended based on drug interaction studies or predicted interaction [see Contraindications ( 4 ), Warnings and Precautions ( 5.1 ), and Clinical Pharmacology ( 12.3 )] for magnitude of interaction. Table 4.
Established and Other Potentially Significant Drug Interactions Concomitant Drug Class: Drug Name Effect on Concentration of Ritonavir or Concomitant Drug Clinical Comment HIV-Antiviral Agents HIV-1 Protease Inhibitor: atazanavir darunavir fosamprenavir ↑ amprenavir ↑ atazanavir ↑ darunavir See the complete prescribing information for fosamprenavir, atazanavir, darunavir for details on co-administration with ritonavir. HIV-1 Protease Inhibitor: indinavir ↑ indinavir Appropriate doses for this combination, with respect to efficacy and safety, have not been established.
HIV-1 Protease Inhibitor: saquinavir ↑ saquinavir See the complete prescribing information for saquinavir for details on co-administration of saquinavir and ritonavir. Saquinavir/ritonavir in combination with rifampin is not recommended due to the risk of severe hepatotoxicity (presenting as increased hepatic transaminases) if the three drugs are given together. HIV-1 Protease Inhibitor: tipranavir ↑ tipranavir See the complete prescribing information for tipranavir for details on co-administration of tipranavir and ritonavir.
Non-Nucleoside Reverse Transcriptase Inhibitor: delavirdine ↑ ritonavir Appropriate doses of this combination with respect to safety and efficacy have not been established. HIV-1 CCR5-antagonist: maraviroc ↑ maraviroc See the complete prescribing information for maraviroc for details on co-administration of maraviroc and ritonavir-containing protease inhibitors. Integrase Inhibitor: raltegravir ↓ raltegravir The effects of ritonavir on raltegravir with ritonavir dosage regimens greater than 100 mg twice daily have not been evaluated, however raltegravir concentrations may be decreased with ritonavir co-administration.
Other Agents Alpha 1-Adrenoreceptor Antagonist: alfuzosin ↑ alfuzosin Contra…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS When co-administering ritonavir with other protease inhibitors, see the full prescribing information for the co-administered protease inhibitor including important information for use in special populations. Lactation: Women infected with HIV should be instructed not to breastfeed due to the potential for HIV transmission.( 8.2 ).
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ritonavir during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Prospective pregnancy data from the Antiretroviral Pregnancy Registry (APR) are not sufficient to adequately assess the risk of birth defects or miscarriage.
Available data from the APR show no difference in the rate of overall birth defects for ritonavir compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) [see Data ]. In animal reproduction studies, no evidence of adverse developmental outcomes was observed with oral administration of ritonavir to pregnant rats and rabbits. During organogenesis in the rat and rabbit, systemic exposure (AUC) was approximately 1/3 lower than human exposure at the recommended daily dose.
In the rat pre- and post-natal developmental study, maternal systemic exposure to ritonavir was approximately 1/2 of the exposure in humans at the recommended daily dose, based on a body surface area conversion factor [see Data ]. Ritonavir oral solution is not recommended during pregnancy because there is no known safe level of ethanol exposure during pregnancy [see Clinical Considerations, Dosage and Administration ( 2.3 ) and Warnings and Precautions ( 5.2 )] . The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Dose Adjustments During Pregnancy and the Postpartum Period Ritonavir oral solution contains approx.
43% ethanol (v/v) and approx. 27% (w/v) propylene glycol and is not recommended during pregnancy because there is no known safe level of ethanol exposure during pregnancy [see Dosage and Administration ( 2.3 ) and Warnings and Precautions ( 5.2 )] . Data Human Data Based on prospective reports to the APR of approximately 6,100 live births following exposure to ritonavir-containing regimens (including over 2,800 live births exposed in the first trimester and over 3,200 live births exposed in the second and third trimesters), there was no difference in the rate of overall birth defects for ritonavir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 2.3% (95% CI: 1.7% to 2.9%) following first-trimester exposure to ritonavir-containing regimens and 2.9% (95% CI: 2.3% to 3.5%) following second and third trimester exposure to ritonavir-containing regimens. While placental transfer of ritonavir and fetal ritonavir concentrations are generally low, detectable levels have been observed in cord blood samples and neonate hair. Animal Data Ritonavir was administered orally to pregnant rats (at 0, 15, 35, and 75 mg/kg/day) and rabbits (at 0, 25, 50, and 110 mg/kg/day) during organogenesis (on gestation days 6 through 17 and 6 through 19, respectively).
No evidence of teratogenicity due to ritonavir was observed in rats and rabbits at doses producing systemic exposures (AUC) equivalent to approximately 1/3 lower than human exposure at the recommended daily dose. Developmental toxicity observed in rats (early resorptions,…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to ritonavir during pregnancy. Healthcare providers are encouraged to register patients by calling the Antiretroviral Pregnancy Registry (APR) at 1-800-258-4263. Risk Summary Prospective pregnancy data from the Antiretroviral Pregnancy Registry (APR) are not sufficient to adequately assess the risk of birth defects or miscarriage.
Available data from the APR show no difference in the rate of overall birth defects for ritonavir compared to the background rate for major birth defects of 2.7% in the U.S. reference population of the Metropolitan Atlanta Congenital Defects Program (MACDP) [see Data ]. In animal reproduction studies, no evidence of adverse developmental outcomes was observed with oral administration of ritonavir to pregnant rats and rabbits. During organogenesis in the rat and rabbit, systemic exposure (AUC) was approximately 1/3 lower than human exposure at the recommended daily dose.
In the rat pre- and post-natal developmental study, maternal systemic exposure to ritonavir was approximately 1/2 of the exposure in humans at the recommended daily dose, based on a body surface area conversion factor [see Data ]. Ritonavir oral solution is not recommended during pregnancy because there is no known safe level of ethanol exposure during pregnancy [see Clinical Considerations, Dosage and Administration ( 2.3 ) and Warnings and Precautions ( 5.2 )] . The background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Clinical Considerations Dose Adjustments During Pregnancy and the Postpartum Period Ritonavir oral solution contains approx.
43% ethanol (v/v) and approx. 27% (w/v) propylene glycol and is not recommended during pregnancy because there is no known safe level of ethanol exposure during pregnancy [see Dosage and Administration ( 2.3 ) and Warnings and Precautions ( 5.2 )] . Data Human Data Based on prospective reports to the APR of approximately 6,100 live births following exposure to ritonavir-containing regimens (including over 2,800 live births exposed in the first trimester and over 3,200 live births exposed in the second and third trimesters), there was no difference in the rate of overall birth defects for ritonavir compared with the background birth defect rate of 2.7% in the U.S. reference population of the MACDP.
The prevalence of birth defects in live births was 2.3% (95% CI: 1.7% to 2.9%) following first-trimester exposure to ritonavir-containing regimens and 2.9% (95% CI: 2.3% to 3.5%) following second and third trimester exposure to ritonavir-containing regimens. While placental transfer of ritonavir and fetal ritonavir concentrations are generally low, detectable levels have been observed in cord blood samples and neonate hair. Animal Data Ritonavir was administered orally to pregnant rats (at 0, 15, 35, and 75 mg/kg/day) and rabbits (at 0, 25, 50, and 110 mg/kg/day) during organogenesis (on gestation days 6 through 17 and 6 through 19, respectively).
No evidence of teratogenicity due to ritonavir was observed in rats and rabbits at doses producing systemic exposures (AUC) equivalent to approximately 1/3 lower than human exposure at the recommended daily dose. Developmental toxicity observed in rats (early resorptions, decreased fetal body weight and ossification delays and developmental variations) occurred at a maternally toxic dose, at an exposure equivalent to approximately 1/3 lower than human exposure at the recommended daily dose. A slight increase in the incidence of cryptorchidism was also noted in rats (at a maternally toxic dose) at an exposure approximately 1/5 l…
🧒 Pediatric Use ▾
8.4Pediatric Use In HIV-infected patients age greater than 1 month to 21 years, the antiviral activity and adverse event profile seen during clinical trials and through postmarketing experience were similar to that for adult patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of ritonavir did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Acute Overdosage - Human Overdose Experience Human experience of acute overdose with ritonavir is limited. One patient in clinical trials took ritonavir 1,500 mg per day for two days. The patient reported paresthesias which resolved after the dose was decreased.
A post-marketing case of renal failure with eosinophilia has been reported with ritonavir overdose. The approximate lethal dose was found to be greater than 20 times the related human dose in rats and 10 times the related human dose in mice. Management of Overdosage Ritonavir oral solution contains approx.
43% ethanol (v/v) and approx. 27% (w/v) propylene glycol. Ingestion of the product over the recommended dose by a young child could result in significant toxicity and could potentially be lethal.
Treatment of overdose with ritonavir consists of general supportive measures including monitoring of vital signs and observation of the clinical status of the patient. There is no specific antidote for overdose with ritonavir. If indicated, elimination of unabsorbed drug should be achieved by gastric lavage; usual precautions should be observed to maintain the airway.
Administration of activated charcoal may also be used to aid in removal of unabsorbed drug. Since ritonavir is extensively metabolized by the liver and is highly protein bound, dialysis is unlikely to be beneficial in significant removal of the drug. However, dialysis can remove both ethanol and propylene glycol in the case of overdose with ritonavir oral solution.
A Certified Poison Control Center should be consulted for up-to-date information on the management of overdose with ritonavir.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Ritonavir is an antiretroviral drug [see Microbiology ( 12.4 )] .
12.2Pharmacodynamics Cardiac Electrophysiology QTcF interval was evaluated in a randomized, placebo and active (moxifloxacin 400 mg once-daily) controlled crossover study in 45 healthy adults, with 10 measurements over 12 hours on Day 3. The maximum mean (95% upper confidence bound) time-matched difference in QTcF from placebo after baseline correction was 5.5 (7.6) milliseconds (msec) for 400 mg twice-daily ritonavir. Ritonavir 400 mg twice daily resulted in Day 3 ritonavir exposure that was approximately 1.5 fold higher than observed with ritonavir 600 mg twice-daily dose at steady state.
PR interval prolongation was also noted in subjects receiving ritonavir in the same study on Day 3. The maximum mean (95% confidence interval) difference from placebo in the PR interval after baseline correction was 22 (25) msec for 400 mg twice-daily ritonavir [see Warnings and Precautions ( 5.6 )] .
12.3Pharmacokinetics The pharmacokinetics of ritonavir have been studied in healthy volunteers and HIV-infected patients (CD4 greater than or equal to 50 cells per µL). See Table 5 for ritonavir pharmacokinetic characteristics. Absorption The absolute bioavailability of ritonavir has not been determined.
After a 600 mg dose of oral solution, peak concentrations of ritonavir were achieved approximately 2 hours and 4 hours after dosing under fasting and non-fasting (514 KCal; 9% fat, 12% protein, and 79% carbohydrate) conditions, respectively. Ritonavir tablets are not bioequivalent to ritonavir capsules. Under moderate fat conditions (857 kcal; 31% fat, 13% protein, 56% carbohydrates), when a single 100 mg ritonavir dose was administered as a tablet compared with a capsule, AUC(0-∞) met equivalence criteria but mean Cmax was increased by 26% (92.8% confidence intervals: ↑15 to ↑39%).
No information is available comparing ritonavir tablets to ritonavir capsules under fasting conditions. After administration of a single 100 mg dose under fed conditions (617 Kcal, 29% calories from fat), ritonavir oral powder demonstrated comparable bioavailability to the oral solution. Effect of Food on Oral Absorption The bioavailability of ritonavir tablet, oral solution, and oral powder is decreased under fed conditions as compared to fasted conditions.
Following the administration of a 100 mg tablet dose of ritonavir, Cmax and AUCinf of ritonavir were decreased by 21 to 23% under moderate fat (857 Kcal, 30% from fat) or high fat conditions (917 Kcal, 60% calories from fat) relative to fasting conditions. Following the administration of a 600 mg dose ritonavir oral solution, Cmax and AUCinf of ritonavir were decreased by 23% and 7%, respectively, under nonfasting conditions (514 Kcal, 10% from fat) relative to fasting conditions. Dilution of the oral solution, within one hour of administration, with 240 mL of chocolate milk, Advera® or Ensure® did not significantly affect the extent and rate of ritonavir absorption.
Following the administration of a 100 mg dose of ritonavir oral powder, Cmax and AUCinf of ritonavir were decreased by 23 to 49% under moderate fat (617 Kcal, 29% calories from fat) or high fat conditions (917 Kcal, 60% calories from fat) relative to fasting conditions. Metabolism Nearly all of the plasma radioactivity after a single oral 600 mg dose of 14C-ritonavir oral solution (n = 5) was attributed to unchanged ritonavir. Five ritonavir metabolites have been identified in human urine and feces.
The isopropylthiazole oxidation metabolite (M-2) is the major metabolite and has antiviral activity similar to that of parent drug; however, the concentrations of this metabolite in plasma are low. In vitro studies utilizing human liver microsomes have demonstrated that cytochrome P450 3A (CYP3A) is the major isoform involved in ritonavir metabolism, although CYP2D6 also contributes to the formation of M–2. Elimination In a study of five…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Ritonavir is an antiretroviral drug [see Microbiology ( 12.4 )] .
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Ritonavir Tablets USP 100 mg tablet is supplied as a white-colored, oval shaped, shallow, film coated tablet with "54" debossed on one side and "247" debossed on the other side . NDC 69097-655-02: Bottle of 30 Tablets NDC 69097-655-08: Bottle of 120 Tablets Recommended Storage Store at or below 30°C (86°F). Exposure to temperatures up to 50°C (122°F) for seven days permitted.
For patient use: exposure of this product to high humidity outside the original or USP equivalent tight container (60 mL or less) for longer than 2 weeks is not recommended. Dispense in original container or USP equivalent tight container (60 mL or less).
📋 Description ▾
11 DESCRIPTION Ritonavir is an inhibitor of HIV protease with activity against the Human Immunodeficiency Virus (HIV). Ritonavir is chemically designated as 2,4,7,12-Tetraazatridecan-13-oic acid, 10-hydroxy-2-methyl-5-(1-methylethyl)-1-[2-(1-methylethyl)-4-thiazolyl]-3,6-dioxo-8,11-bis(phenylmethyl)-5-thiazolylmethyl ester, [5S-(5R*,8R*,10R*,11R*)]. Its molecular formula is C 37 H 48 N 6 O 5 S 2 , and its molecular weight is 720.94.
Ritonavir has the following structural formula: Ritonavir USP is a white to almost white powder. It is freely soluble in methanol and in methylene chloride, very slightly soluble in acetonitrile, practically insoluble in water. Ritonavir Tablets USP are available for oral administration containing 100 mg ritonavir USP and the following inactive ingredients: anhydrous dibasic calcium phosphate, colloidal silicon dioxide, copovidone, hypromellose, isopropyl alcohol, polysorbate 80, polyethylene glycol, purified water, sodium stearyl fumarate, sorbitan monolaurate, and titanium dioxide.
Image
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Patient Information) General Administration Information [see Dosage and Administration ( 2 )]: Advise patients and caregivers to pay special attention to accurate preparation and administration of their dose to minimize the risk of accidental overdose or underdose of ritonavir. Advise caregivers to inform their healthcare provider if their child's weight changes in order to make sure that the child's ritonavir dose is adjusted as needed.
Advise patients to take ritonavir with meals. For adult patients taking ritonavir tablets, the maximum dose of 600 mg twice daily by mouth with meals should not be exceeded. Advise patients to remain under the care of a physician while using ritonavir and to take ritonavir and other concomitant antiretroviral therapy every day as prescribed.
Ritonavir must always be used in combination with other antiretroviral drugs. Advise patients not to alter the dose or discontinue therapy without consulting with their healthcare provider. If a dose of ritonavir is missed patients should take the dose as soon as possible and then return to their normal schedule.
However, if a dose is skipped the patient should not double the next dose. Continued ritonavir therapy at a dose of 600 mg twice daily following loss of viral suppression may increase the likelihood of cross-resistance to other protease inhibitors. Ritonavir is not a cure for HIV-1 infection and patients may continue to experience illnesses associated with HIV-1 infection, including opportunistic infections.
Patients should remain under the care of a physician when using ritonavir. Drug Interactions Ritonavir may interact with some drugs; therefore, patients should be advised to report to their doctor the use of any other prescription, non-prescription medication or herbal products, particularly St. John's Wort.
Instruct patients receiving combined hormonal contraception to use an effective alternative contraceptive method or an additional barrier method during therapy with ritonavir because hormonal levels may decrease [ see Drug Interactions ( 7.2 ), Use in Specific Populations ( 8.3 ) ]. Hepatotoxicity Pre-existing liver disease including Hepatitis B or C can worsen with use of ritonavir. This can be seen as worsening of transaminase elevations or hepatic decompensation.
Advise patients that their liver function tests will need to be monitored closely especially during the first several months of ritonavir treatment and that they should notify their healthcare provider if they develop the signs and symptoms of worsening liver disease including loss of appetite, abdominal pain, jaundice, and itchy skin [see Warnings and Precautions ( 5.3 )] . Pancreatitis Pancreatitis, including some fatalities, has been observed in patients receiving ritonavir therapy. Advise patients to notify their healthcare provider of signs and symptoms (nausea, vomiting, and abdominal pain) that might be suggestive of pancreatitis [see Warnings and Precautions ( 5.4 )] .
Allergic Reactions/Hypersensitivity Skin rashes ranging in severity from mild to Stevens-Johnson syndrome have been reported in patients receiving ritonavir. Advise patients to contact their healthcare provider if they develop a rash while taking ritonavir [see Warnings and Precautions ( 5.5 )] . PR Interval Prolongation Ritonavir may produce changes in the electrocardiogram (e.g., PR prolongation).
Advise patients to consult their healthcare provider if they experience symptoms such as dizziness, lightheadedness, abnormal heart rhythm or loss of consciousness [see Warnings and Precautions ( 5.6 )] . Lipid Disorders Advise patients that treatment with ritonavir therapy can result in substantial increases in the concentration of total cholesterol and triglycerides (see 5.7 )] . Diabetes Mellitus/Hyperglycemia Advise patients that new onset of diabetes or exacerbation of pre-existing diabetes mellitus, and hyperg…