
Bisoprolol Fumarate 5 mg Tablet, Film Coated, 100-count — NDC 70095-020-02 (Billing 70095-0020-02)
This is a package of 100 tablets of Bisoprolol Fumarate 5 mg Tablet, Film Coated from Sun Pharmaceutical Industries Limited, marketed since Mar 2024 and currently FDA-listed; retail pharmacies pay about $0.1142 per tablet (NADAC). It is the main listing for this product, which comes in 2 package sizes.
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 017956
- GCN: 63821
- GPI-14 (Medi-Span): 33200022100310
- HICL (First Databank): 007396
- AHFS class code: 12:16.08.08
- RxCUI (RxNorm): 854901
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- Bisoprolol is used to lower high blood pressure (hypertension). It works by slowing your heart rate and reducing the force of each heartbeat, which takes pressure off your arteries...
- Please don't stop it suddenly without talking to your doctor first. Even if you feel great, stopping bisoprolol abruptly — especially if you have any underlying heart disease — can...
- Can I stop taking bisoprolol if I feel fine?
- Beta-blockers like bisoprolol generally aren't recommended if you have asthma or COPD because they can cause airway tightening (bronchospasm). That said, bisoprolol is more heart-s...
Patient education
Supplement & herbal interactions
Bisoprolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.114 | $11.42 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.2872 | $28.72 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $0.3944 | $39.44 / 100 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Sep 30, 2026
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 70095-0020-01 70095-020-01 | 30 TABLET, FILM COATED in 1 BOTTLE, UNIT-DOSE | $0.1142 / ea | $3.43 | 2024-03-10 | — | Active |
| 70095-0020-02 You're viewing this Main listing | 100 TABLET, FILM COATED in 1 BOTTLE | $0.1142 / ea | $11.42 | 2024-03-10 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.1142 NADAC).
In Medicaid, this is the most-dispensed pack of this product — about 100% of fills over the last four reported quarters. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 70095-0020-01?
What NDC number is used to bill for this package of Bisoprolol Fumarate 5 mg Tablet, Film Coated?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bisoprolol Fumarate 5 mg 16714-0529-01 | NorthStar | 30 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 29300-0126-01 | Unichem | 100 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol fumarate 5 mg 43547-0616-03 | Solco | 30 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 50268-0127-15 | AvPAK | 1 tablet | $0.114 | AB | Availability likely | — |
| Bisoprolol 5 mg 52817-0270-10 | TruPharma, | 100 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 60687-0679-21 | American | 30 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 62332-0603-30 | Alembic | 30 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 64980-0709-01 | Rising | 100 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 65862-0086-01 | Aurobindo | 100 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mgthis 70095-0020-02 | Sun | 100 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 70954-0455-10 | Novitium | 30 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 72578-0111-01 | Viona | 100 tablets | $0.114 | AB | Availability likely | — |
| Bisoprolol 5 mg 42571-0470-01 | Micro | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 46708-0603-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 51407-0645-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 63187-0871-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 63629-5173-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 68788-8671-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol fumarate 5 mg 69339-0236-01 | Natco | 100 tablets | — | — | FDA listed | — |
| Bisoprolol Fumarate 5 mg 70771-1726-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol 5 mg 71335-1678-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 71335-2178-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol 5 mg 72162-2177-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 72789-0392-82 | PD-Rx | 500 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 72888-0092-00 | Advagen | 1000 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 82638-0107-01 | Harman | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Sep 30, 2026
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Bisoprolol fumarate is indicated in the management of hypertension. It may be used alone or in combination with other antihypertensive agents.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The dose of bisoprolol fumarate must be individualized to the needs of the patient. The usual starting dose is 5 mg once daily. In some patients, 2.5 mg may be an appropriate starting dose (see Bronchospastic Disease in WARNINGS ).
If the antihypertensive effect of 5 mg is inadequate, the dose may be increased to 10 mg and then, if necessary, to 20 mg once daily. Patients with Renal or Hepatic Impairment In patients with hepatic impairment (hepatitis or cirrhosis) or renal dysfunction (creatinine clearance less than 40 mL/min), the initial daily dose should be 2.5 mg and caution should be used in dose-titration. Since limited data suggest that bisoprolol fumarate is not dialyzable, drug replacement is not necessary in patients undergoing dialysis.
Geriatric Patients It is not necessary to adjust the dose in the elderly, unless there is also significant renal or hepatic dysfunction (see above and Geriatric Use in PRECAUTIONS). Pediatric Patients There is no pediatric experience with bisoprolol fumarate.
⛔ Contraindications ▾
CONTRAINDICATIONS Bisoprolol fumarate is contraindicated in patients with cardiogenic shock, overt cardiac failure, second or third degree AV block, and marked sinus bradycardia.
⚠️ Warnings ▾
WARNINGS Cardiac Failure Sympathetic stimulation is a vital component supporting circulatory function in the setting of congestive heart failure, and beta-blockade may result in further depression of myocardial contractility and precipitate more severe failure. In general, beta-blocking agents should be avoided in patients with overt congestive failure. However, in some patients with compensated cardiac failure it may be necessary to utilize them.
In such a situation, they must be used cautiously. In Patients Without a History of Cardiac Failure Continued depression of the myocardium with beta-blockers can, in some patients, precipitate cardiac failure. At the first signs or symptoms of heart failure, discontinuation of bisoprolol fumarate should be considered.
In some cases, beta-blocker therapy can be continued while heart failure is treated with other drugs. Abrupt Cessation of Therapy Exacerbation of angina pectoris, and, in some instances, myocardial infarction or ventricular arrhythmia, has been observed in patients with coronary artery disease following abrupt cessation of therapy with beta-blockers. Such patients should, therefore, be cautioned against interruption or discontinuation of therapy without the physician’s advice.
Even in patients without overt coronary artery disease, it may be advisable to taper therapy with bisoprolol fumarate over approximately one week with the patient under careful observation. If withdrawal symptoms occur, bisoprolol fumarate therapy should be reinstituted, at least temporarily. Peripheral Vascular Disease Beta-blockers can precipitate or aggravate symptoms of arterial insufficiency in patients with peripheral vascular disease.
Caution should be exercised in such individuals. Bronchospastic Disease PATIENTS WITH BRONCHOSPASTIC DISEASE SHOULD, IN GENERAL, NOT RECEIVE BETA-BLOCKERS. Because of its relative beta1-selectivity, however, bisoprolol fumarate may be used with caution in patients with bronchospastic disease who do not respond to, or who cannot tolerate other antihypertensive treatment.
Since beta1-selectivity is not absolute, the lowest possible dose of bisoprolol fumarate should be used, with therapy starting at 2.5 mg. A beta2 agonist (bronchodilator) should be made available. Major Surgery Chronically administered beta-blocking therapy should not be routinely withdrawn prior to major surgery; however, the impaired ability of the heart to respond to reflex adrenergic stimuli may augment the risk of general anesthesia and surgical procedures.
Diabetes and Hypoglycemia Beta-blockers may mask some of the manifestations of hypoglycemia, particularly tachycardia. Nonselective beta-blockers may potentiate insulin-induced hypoglycemia and delay recovery of serum glucose levels. Because of its beta1-selectivity, this is less likely with bisoprolol fumarate.
However, patients subject to spontaneous hypoglycemia, or diabetic patients receiving insulin or oral hypoglycemic agents, should be cautioned about these possibilities and bisoprolol fumarate should be used with caution. Thyrotoxicosis Beta-adrenergic blockade may mask clinical signs of hyperthyroidism, such as tachycardia. Abrupt withdrawal of beta-blockade may be followed by an exacerbation of the symptoms of hyperthyroidism or may precipitate thyroid storm.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Safety data are available in more than 30,000 patients or volunteers. Frequency estimates and rates of withdrawal of therapy for adverse events were derived from two U.S. placebo-controlled studies. In Study A, doses of 5, 10, and 20 mg bisoprolol fumarate were administered for 4 weeks.
In Study B, doses of 2.5, 10, and 40 mg of bisoprolol fumarate were administered for 12 weeks. A total of 273 patients were treated with 5 to 20 mg of bisoprolol fumarate; 132 received placebo. Withdrawal of therapy for adverse events was 3.3% for patients receiving bisoprolol fumarate and 6.8% for patients on placebo.
Withdrawals were less than 1% for either bradycardia or fatigue/lack of energy. The following table presents adverse experiences, whether or not considered drug related, reported in at least 1% of patients in these studies, for all patients studied in placebo-controlled clinical trials (2.5 to 40 mg), as well as for a subgroup that was treated with doses within the recommended dosage range (5 to 20 mg). Of the adverse events listed in the table, bradycardia, diarrhea, asthenia, fatigue, and sinusitis appear to be dose related.
Body System/Adverse Experience All Adverse Experiences (% a ) Bisoprolol fumarate Placebo (n = 132) % 5 to 20 mg (n = 273) % 2.5 to 40 mg (n = 404) % Skin increased sweating 1.5 0.7
1.0Musculoskeletal arthralgia 2.3 2.2
2.7Central Nervous System dizziness 3.8 2.9 3.5 headache 11.4 8.8 10.9 hypoaesthesia 0.8 1.1
1.5Autonomic Nervous System dry mouth 1.5 0.7
1.3Heart Rate/Rhythm bradycardia 0 0.4
0.5Psychiatric vivid dreams 0 0 0 insomnia 2.3 1.5 2.5 depression 0.8 0
0.2Gastrointestinal diarrhea 1.5 2.6 3.5 nausea 1.5 1.5 2.2 vomiting 0 1.1
1.5Respiratory bronchospasm 0 0 0 cough 4.5 2.6 2.5 dyspnea 0.8 1.1 1.5 pharyngitis 2.3 2.2 2.2 rhinitis 3.0 2.9 4.0 sinusitis 1.5 2.2
2.2URI 3.8 4.8
5.0Body as a Whole asthenia 0 0.4 1.5 chest pain 0.8 1.1 1.5 fatigue 1.5 6.6 8.2 edema (peripheral) 3.8 3.7 3.0 a percentage of patients with event The following is a comprehensive list of adverse experiences reported with bisoprolol fumarate in worldwide studies, or in postmarketing experience (in italics): Central Nervous System Dizziness, unsteadiness, vertigo, syncope, headache, paresthesia, hypoesthesia, hyperesthesia, somnolence, sleep disturbances, anxiety/restlessness, decreased concentration/memory Autonomic Nervous System Dry mouth Cardiovascular Bradycardia, palpitations and other rhythm disturbances, cold extremities, claudication, hypotension, orthostatic hypotension, chest pain, congestive heart failure, dyspnea on exertion Psychiatric Vivid dreams, insomnia, depression.
Gastrointestinal Gastric/epigastric/abdominal pain, gastritis, dyspepsia, nausea, vomiting, diarrhea, constipation, peptic ulcer Musculoskeletal Muscle/joint pain, arthralgia, back/neck pain, muscle cramps, twitching/tremor. Skin Rash, acne, eczema, psoriasis, skin irritation, pruritus, flushing, sweating, alopecia, dermatitis, angioedema, exfoliative dermatitis, cutaneous vasculitis Special Senses Visual disturbances, ocular pain/pressure, abnormal lacrimation, tinnitus, decreased hearing, earache, taste abnormalities.
Metabolic Gout Respiratory Asthma/bronchospasm, bronchitis, coughing, dyspnea, pharyngitis, rhinitis, sinusitis, URI. Genitourinary Decreased libido/impotence, Peyronie’s disease, cystitis, renal colic, polyuria. Hematologic Purpura.
General Fatigue, asthenia, chest pain, malaise, edema, weight gain, angioedema. In addition, a variety of adverse effects have been reported with other beta-adrenergic blocking agents and should be considered potential adverse effects of bisoprolol fumarate: Central Nervous System Reversible mental depression progressing to catatonia, hallucinations, an acute reversible syndrome characterized by disorientation to time and place, emotional lability, slightly clouded sensorium. Allergic Fever, combined with aching and sore throat, laryngospasm, respiratory distress.
Hematolog… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
Drug Interactions Bisoprolol fumarate should not be combined with other beta-blocking agents. Patients receiving catecholamine-depleting drugs, such as reserpine or guanethidine, should be closely monitored, because the added beta-adrenergic blocking action of bisoprolol fumarate may produce excessive reduction of sympathetic activity. In patients receiving concurrent therapy with clonidine, if therapy is to be discontinued, it is suggested that bisoprolol fumarate be discontinued for several days before the withdrawal of clonidine.
Bisoprolol fumarate should be used with care when myocardial depressants or inhibitors of AV conduction, such as certain calcium antagonists (particularly of the phenylalkylamine [verapamil] and benzothiazepine [diltiazem] classes), or antiarrhythmic agents, such as disopyramide, are used concurrently. Both digitalis glycosides and beta-blockers slow atrioventricular conduction and decrease heart rate. Concomitant use can increase the risk of bradycardia.
Concurrent use of rifampin increases the metabolic clearance of bisoprolol fumarate, resulting in a shortened elimination half-life of bisoprolol fumarate. However, initial dose modification is generally not necessary. Pharmacokinetic studies document no clinically relevant interactions with other agents given concomitantly, including thiazide diuretics and cimetidine.
There was no effect of bisoprolol fumarate on prothrombin time in patients on stable doses of warfarin. Risk of Anaphylactic Reaction: While taking beta-blockers, patients with a history of severe anaphylactic reaction to a variety of allergens may be more reactive to repeated challenge, either accidental, diagnostic, or therapeutic. Such patients may be unresponsive to the usual doses of epinephrine used to treat allergic reactions.
🤰 Pregnancy ▾
Pregnancy In rats, bisoprolol fumarate was not teratogenic at doses up to 150 mg/kg/day which is 375 and 77 times the MRHD on the basis of body weight and body surface area, respectively. Bisoprolol fumarate was fetotoxic (increased late resorptions) at 50 mg/kg/day and maternotoxic (decreased food intake and body weight gain) at 150 mg/kg/day. The fetotoxicity in rats occurred at 125 times the MRHD on a body weight basis and 26 times the MRHD on the basis of body surface area.
The maternotoxicity occurred at 375 times the MRHD on a body weight basis and 77 times the MRHD on the basis of body surface area. In rabbits, bisoprolol fumarate was not teratogenic at doses up to 12.5 mg/kg/day, which is 31 and 12 times the MRHD based on body weight and body surface area, respectively, but was embryolethal (increased early resorptions) at 12.5 mg/kg/day. There are no adequate and well-controlled studies in pregnant women.
Bisoprolol fumarate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Bisoprolol fumarate has been used in elderly patients with hypertension. Response rates and mean decreases in systolic and diastolic blood pressure were similar to the decreases in younger patients in the U.S. clinical studies. Although no dose response study was conducted in elderly patients, there was a tendency for older patients to be maintained on higher doses of bisoprolol fumarate.
Observed reductions in heart rate were slightly greater in the elderly than in the young and tended to increase with increasing dose. In general, no disparity in adverse experience reports or dropouts for safety reasons was observed between older and younger patients. Dose adjustment based on age is not necessary.
🆘 Overdosage ▾
OVERDOSAGE The most common signs expected with overdosage of a beta-blocker are bradycardia, hypotension, congestive heart failure, bronchospasm, and hypoglycemia. To date, a few cases of overdose (maximum: 2000 mg) with bisoprolol fumarate have been reported. Bradycardia and/or hypotension were noted.
Sympathomimetic agents were given in some cases, and all patients recovered. In general, if overdose occurs, bisoprolol fumarate therapy should be stopped and supportive and symptomatic treatment should be provided. Limited data suggest that bisoprolol fumarate is not dialyzable.
Based on the expected pharmacologic actions and recommendations for other beta-blockers, the following general measures should be considered when clinically warranted: Bradycardia Administer IV atropine. If the response is inadequate, isoproterenol or another agent with positive chronotropic properties may be given cautiously. Under some circumstances, transvenous pacemaker insertion may be necessary.
Hypotension IV fluids and vasopressors should be administered. Intravenous glucagon may be useful. Heart Block (second or third degree) Patients should be carefully monitored and treated with isoproterenol infusion or transvenous cardiac pacemaker insertion, as appropriate.
Congestive Heart Failure Initiate conventional therapy (i.e., digitalis, diuretics, inotropic agents, vasodilating agents). Bronchospasm Administer bronchodilator therapy such as isoproterenol and/or aminophylline. Hypoglycemia Administer IV glucose.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Bisoprolol fumarate is a beta 1 -selective (cardioselective) adrenoceptor blocking agent without significant membrane stabilizing activity or intrinsic sympathomimetic activity in its therapeutic dosage range. Cardioselectivity is not absolute, however, and at higher doses (≥ 20 mg) bisoprolol fumarate also inhibits beta 2 -adrenoceptors, chiefly located in the bronchial and vascular musculature; to retain selectivity it is therefore important to use the lowest effective dose. Pharmacokinetics and Metabolism The absolute bioavailability after a 10 mg oral dose of bisoprolol fumarate is about 80%.
Absorption is not affected by the presence of food. The first pass metabolism of bisoprolol fumarate is about 20%. Binding to serum proteins is approximately 30%.
Peak plasma concentrations occur within 2-4 hours of dosing with 5 to 20 mg, and mean peak values range from 16 ng/mL at 5 mg to 70 ng/mL at 20 mg. Once daily dosing with bisoprolol fumarate results in less than twofold intersubject variation in peak plasma levels. The plasma elimination half-life is 9-12 hours and is slightly longer in elderly patients, in part because of decreased renal function in that population.
Steady state is attained within 5 days of once daily dosing. In both young and elderly populations, plasma accumulation is low; the accumulation factor ranges from 1.1 to 1.3, and is what would be expected from the first order kinetics and once daily dosing. Plasma concentrations are proportional to the administered dose in the range of 5 to 20 mg.
Pharmacokinetic characteristics of the two enantiomers are similar. Bisoprolol fumarate is eliminated equally by renal and non-renal pathways with about 50% of the dose appearing unchanged in the urine and the remainder appearing in the form of inactive metabolites. In humans, the known metabolites are labile or have no known pharmacologic activity.
Less than 2% of the dose is excreted in the feces. Bisoprolol fumarate is not metabolized by cytochrome P450 II D6 (debrisoquin hydroxylase). In subjects with creatinine clearance less than 40 mL/min, the plasma half-life is increased approximately threefold compared to healthy subjects.
In patients with cirrhosis of the liver, the elimination of bisoprolol fumarate is more variable in rate and significantly slower than that in healthy subjects, with plasma half-life ranging from 8.3 to 21.7 hours. Pharmacodynamics The most prominent effect of bisoprolol fumarate is the negative chronotropic effect, resulting in a reduction in resting and exercise heart rate. There is a fall in resting and exercise cardiac output with little observed change in stroke volume, and only a small increase in right atrial pressure, or pulmonary capillary wedge pressure at rest or during exercise.
Findings in short-term clinical hemodynamics studies with bisoprolol fumarate are similar to those observed with other beta-blocking agents. The mechanism of action of its antihypertensive effects has not been completely established. Factors which may be involved include: 1.
Decreased cardiac output, 2. Inhibition of renin release by the kidneys, 3. Diminution of tonic sympathetic outflow from the vasomotor centers in the brain.
In normal volunteers, bisoprolol fumarate therapy resulted in a reduction of exercise- and isoproterenol-induced tachycardia. The maximal effect occurred within 1-4 hours post-dosing. Effects persisted for 24 hours at doses equal to or greater than 5 mg.
Electrophysiology studies in man have demonstrated that bisoprolol fumarate significantly decreases heart rate, increases sinus node recovery time, prolongs AV node refractory periods, and, with rapid atrial stimulation, prolongs AV nodal conduction. Beta 1 -selectivity of bisoprolol fumarate has been demonstrated in both animal and human studies. No effects at therapeutic doses on beta 2 -adrenoceptor density have been observed.
Pulmonary function studies have been conducted in healthy volunteers, asthmati… [Excerpted — this section continues on DailyMed.]
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Bisoprolol fumarate is supplied as 5 mg and 10 mg tablets. The 5 mg tablet is pinkish purple to purple colored, round, biconvex, film-coated tablets, debossed with “H14” on one side and functional scoring on other side. Tablets shall be free from physical defects.
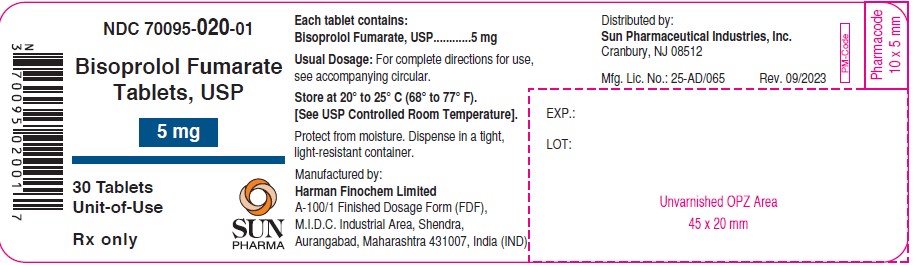
Bottles of 30 Unit-of-use: NDC 70095-020-01 Bottles of 100: NDC 70095-020-02 The 10 mg tablet is white to off white colored, round, biconvex, film-coated tablets, debossed with “H16” on one side and plain on other side. Tablets shall be free from physical defects. Bottles of 30 Unit-of-use: NDC 70095-019-01 Bottles of 100: NDC 70095-019-02 Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature].
Protect from moisture. Dispense in tight, light-resistant containers. To report SUSPECTED ADVERSE REACTIONS, contact Sun Pharmaceutical Industries, Inc. at +1 855 963 5151 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
Manufactured by: Harman Finochem Limited A-100/1 Finished Dosage Form (FDF), M.I.D.C. Industrial Area, Shendra, Ch. Sambhajinagar, Maharashtra 431154, India (IND) Distributed by: Sun Pharmaceutical Industries, Inc.
Cranbury, NJ 08512 Revised: 10/2024
📋 Description ▾
DESCRIPTION Bisoprolol fumarate, USP is a synthetic, beta 1 -selective (cardioselective) adrenoceptor blocking agent. The chemical name for bisoprolol fumarate is (±)-1-[4-[[2-(1-Methylethoxy)ethoxy]methyl]phenoxy]-3-[(1-methylethyl)amino]-2-propanol (E)-2-butenedioate (2:1) (salt). It possesses an asymmetric carbon atom in its structure and is provided as a racemic mixture.
The S(-) enantiomer is responsible for most of the beta-blocking activity. Its molecular formula is (C 18 H 31 NO 4 ) 2 •C 4 H 4 O 4 and its structure is: Bisoprolol fumarate has a molecular weight of 766.97. It is a white crystalline powder which is approximately equally hydrophilic and lipophilic, and is readily soluble in water, methanol, ethanol, and chloroform.
Bisoprolol fumarate tablets, USP are available as 5 and 10 mg tablets for oral administration. Inactive ingredients include microcrystalline cellulose, butylated hydroxy anisole, dibasic calcium phosphate anhydrous, crospovidone, colloidal silicon dioxide, magnesium stearate, hypromellose, hydroxypropyl cellulose and titanium dioxide. The 5 mg tablets also contain talc, FD&C red#40 and FD&C blue #2.
FDA approved dissolution test specifications differ from USP. spl-structure
💬 Information for Patients ▾
Information for Patients Patients, especially those with coronary artery disease, should be warned about discontinuing use of bisoprolol fumarate without a physician’s supervision. Patients should also be advised to consult a physician if any difficulty in breathing occurs, or if they develop signs or symptoms of congestive heart failure or excessive bradycardia. Patients subject to spontaneous hypoglycemia, or diabetic patients receiving insulin or oral hypoglycemic agents, should be cautioned that beta-blockers may mask some of the manifestations of hypoglycemia, particularly tachycardia, and bisoprolol fumarate should be used with caution.
Patients should know how they react to this medicine before they operate automobiles and machinery or engage in other tasks requiring alertness.
⚠️ Precautions ▾
PRECAUTIONS Impaired Renal or Hepatic Function Use caution in adjusting the dose of bisoprolol fumarate in patients with renal or hepatic impairment (see CLINICAL PHARMACOLOGY and DOSAGE AND ADMINISTRATION ). Drug Interactions Bisoprolol fumarate should not be combined with other beta-blocking agents. Patients receiving catecholamine-depleting drugs, such as reserpine or guanethidine, should be closely monitored, because the added beta-adrenergic blocking action of bisoprolol fumarate may produce excessive reduction of sympathetic activity.
In patients receiving concurrent therapy with clonidine, if therapy is to be discontinued, it is suggested that bisoprolol fumarate be discontinued for several days before the withdrawal of clonidine. Bisoprolol fumarate should be used with care when myocardial depressants or inhibitors of AV conduction, such as certain calcium antagonists (particularly of the phenylalkylamine [verapamil] and benzothiazepine [diltiazem] classes), or antiarrhythmic agents, such as disopyramide, are used concurrently. Both digitalis glycosides and beta-blockers slow atrioventricular conduction and decrease heart rate.
Concomitant use can increase the risk of bradycardia. Concurrent use of rifampin increases the metabolic clearance of bisoprolol fumarate, resulting in a shortened elimination half-life of bisoprolol fumarate. However, initial dose modification is generally not necessary.
Pharmacokinetic studies document no clinically relevant interactions with other agents given concomitantly, including thiazide diuretics and cimetidine. There was no effect of bisoprolol fumarate on prothrombin time in patients on stable doses of warfarin. Risk of Anaphylactic Reaction: While taking beta-blockers, patients with a history of severe anaphylactic reaction to a variety of allergens may be more reactive to repeated challenge, either accidental, diagnostic, or therapeutic.
Such patients may be unresponsive to the usual doses of epinephrine used to treat allergic reactions. Information for Patients Patients, especially those with coronary artery disease, should be warned about discontinuing use of bisoprolol fumarate without a physician’s supervision. Patients should also be advised to consult a physician if any difficulty in breathing occurs, or if they develop signs or symptoms of congestive heart failure or excessive bradycardia.
Patients subject to spontaneous hypoglycemia, or diabetic patients receiving insulin or oral hypoglycemic agents, should be cautioned that beta-blockers may mask some of the manifestations of hypoglycemia, particularly tachycardia, and bisoprolol fumarate should be used with caution. Patients should know how they react to this medicine before they operate automobiles and machinery or engage in other tasks requiring alertness. Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term studies were conducted with oral bisoprolol fumarate administered in the feed of mice (20 and 24 months) and rats (26 months).
No evidence of carcinogenic potential was seen in mice dosed up to 250 mg/kg/day or rats dosed up to 125 mg/kg/day. On a body weight basis, these doses are 625 and 312 times, respectively, the maximum recommended human dose (MRHD) of 20 mg, (or 0.4 mg/kg/day based on a 50 kg individual); on a body surface area basis, these doses are 59 times (mice) and 64 times (rats) the MRHD. The mutagenic potential of bisoprolol fumarate was evaluated in the microbial mutagenicity (Ames) test, the point mutation and chromosome aberration assays in Chinese hamster V79 cells, the unscheduled DNA synthesis test, the micronucleus test in mice, and the cytogenetics assay in rats.
There was no evidence of mutagenic potential in these in vitro and in vivo assays. Reproduction studies in rats did not show any impairment of fertility at doses up to 150 mg/kg/day of bisoprolol fumarate, or 375 and 77 times the MRHD on the basis of body weight and body surface area, respectively. Pregnancy In rats, bisopro… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Small amounts of bisoprolol fumarate (< 2% of the dose) have been detected in the milk of lactating rats. It is not known whether this drug is excreted in human milk. Because many drugs are excreted in human milk caution should be exercised when bisoprolol fumarate is administered to nursing women.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term studies were conducted with oral bisoprolol fumarate administered in the feed of mice (20 and 24 months) and rats (26 months). No evidence of carcinogenic potential was seen in mice dosed up to 250 mg/kg/day or rats dosed up to 125 mg/kg/day. On a body weight basis, these doses are 625 and 312 times, respectively, the maximum recommended human dose (MRHD) of 20 mg, (or 0.4 mg/kg/day based on a 50 kg individual); on a body surface area basis, these doses are 59 times (mice) and 64 times (rats) the MRHD.
The mutagenic potential of bisoprolol fumarate was evaluated in the microbial mutagenicity (Ames) test, the point mutation and chromosome aberration assays in Chinese hamster V79 cells, the unscheduled DNA synthesis test, the micronucleus test in mice, and the cytogenetics assay in rats. There was no evidence of mutagenic potential in these in vitro and in vivo assays. Reproduction studies in rats did not show any impairment of fertility at doses up to 150 mg/kg/day of bisoprolol fumarate, or 375 and 77 times the MRHD on the basis of body weight and body surface area, respectively.
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 5 mg NDC 70095-020-01 Bisoprolol Fumarate Tablets, USP 5 mg 30 Tablets Unit-of-Use Rx only SUN PHARMA bisoprolol-5mg
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL - 10 mg NDC 70095-019-01 Bisoprolol Fumarate Tablets, USP 10 mg 30 Tablets Unit-of-Use Rx only SUN PHARMA bisoprolol-10mg