
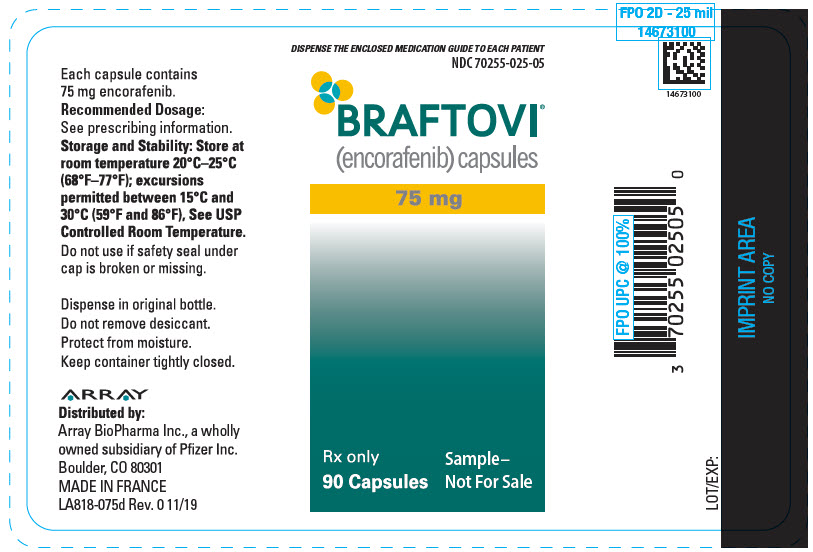
BRAFTOVI Encorafenib 75 mg Capsule, 90-count — NDC 70255-025-05 (Billing 70255-0025-05)
This is a package of 90 capsules of BRAFTOVI Encorafenib 75 mg Capsule from Array BioPharma Inc., marketed since Jun 2018 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 70255-025-05 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70255 labeler · 025 product · 05 package
- Package marketed since
- Aug 3, 2020
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2027
- Barcode (UPC)
- 0370255025067, 0370255025029
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 078574
- GCN: 44925
- GPI-14 (Medi-Span): 21532040000130
- HICL (First Databank): 045039
- AHFS class code: 10:00.00.00
- RxCUI (RxNorm): 2049119
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the B-Raf serine-threonine kinase (BRAF) inhibitors class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats melanoma, colorectal cancer and non-small cell lung cancer that carry a BRAF V600E mutation (V600K too in melanoma). A test confirms the mutation first. You take it toget...
- Take the capsules by mouth once a day, with or without food. If you miss a dose, skip it if your next dose is within 12 hours. If you vomit after taking it, don't take extra. Just...
- Common ones are tiredness, nausea, vomiting, belly pain, diarrhea or constipation, joint pain and rash. Tell your care team if these get hard to handle, since the dose can be adjus...
- Call about any bleeding, vision changes, new shortness of breath or swelling, fainting or a racing heartbeat, or new skin growths. Regular skin, eye, heart and blood checks are par...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Encorafenib — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $120.77 | $10,869.30 / 90 capsules |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 7, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70255-0025-01 70255-025-01 Main listing | 2 BOTTLE in 1 CARTON / 90 CAPSULE in 1 BOTTLE | 2018-06-27 | — | Active |
| 70255-0025-03 70255-025-03 | 2 BOTTLE in 1 CARTON / 60 CAPSULE in 1 BOTTLE | 2018-06-27 | — | Active |
| 70255-0025-05 You're viewing this | 90 CAPSULE in 1 BOTTLE | 2020-08-03 | — | Active |
| 70255-0025-06 70255-025-06 | 60 CAPSULE in 1 BOTTLE | 2020-08-03 | — | Active |
This pack shows little to no recent Medicaid volume — a different pack size carries most fills. See all packs ↓
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 70255-0025-06?
What NDC number is used to bill for this package of BRAFTOVI Encorafenib 75 mg Capsule?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Braftovi 75 mgthis 70255-0025-05 | Array | 90 capsules | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9314464 ↗ | Method of use | U-2336 | Jul 4, 2031 |
| US 8541575 ↗ | Drug substance | U-2335 | Feb 26, 2030 |
| US 10005761 ↗ | Method of use | U-2335 | Aug 27, 2030 |
| US 9314464 ↗ | Method of use | U-2336 | Jul 4, 2031 |
| US 9763941 ↗ | Method of use | U-2335 | Nov 21, 2032 |
| US 9850230 ↗ | Method of use | U-2334 | Aug 27, 2030 |
| US 8541575 ↗ | Drug substance | U-2335 | Feb 26, 2030 |
| US 9850230 ↗ | Method of use | U-2334 | Aug 27, 2030 |
| US 9763941 ↗ | Method of use | U-2335 | Nov 21, 2032 |
| US 9850229 ↗ | Method of use | U-2337 | Aug 27, 2030 |
| US 10258622 ↗ | Method of use | U-4439 | Nov 21, 2032 |
| US 9314464 ↗ | Method of use | U-4440 | Jul 4, 2031 |
| US 10005761 ↗ | Method of use | U-4440 | Aug 27, 2030 |
| US 9850230 ↗ | Method of use | U-4440 | Aug 27, 2030 |
| US 9474754 ↗ | Method of use | U-4440 | Aug 5, 2033 |
| US 8541575 ↗ | Drug substance | U-4440 | Feb 26, 2030 |
| US 8541575 ↗ | Drug substance | U-2803 | Feb 26, 2030 |
| US 8541575 ↗ | Drug substance | U-2802 | Feb 26, 2030 |
| US 9314464 ↗ | Method of use | U-2802 | Jul 4, 2031 |
| US 9314464 ↗ | Method of use | U-2803 | Jul 4, 2031 |
| US 9850230 ↗ | Method of use | U-2802 | Aug 27, 2030 |
| US 9850230 ↗ | Method of use | U-2803 | Aug 27, 2030 |
| US 10005761 ↗ | Method of use | U-2802 | Aug 27, 2030 |
| US 10005761 ↗ | Method of use | U-2803 | Aug 27, 2030 |
| US 10258622 ↗ | Method of use | U-2802 | Nov 21, 2032 |
| US 9474754 ↗ | Method of use | U-2802 | Aug 5, 2033 |
| US 9314464 ↗ | Method of use | U-3738 | Jul 4, 2031 |
| US 10005761 ↗ | Method of use | U-3738 | Aug 27, 2030 |
| US 9850230 ↗ | Method of use | U-3738 | Aug 27, 2030 |
| US 8541575 ↗ | Drug substance | U-3738 | Feb 26, 2030 |
| US 10005761 ↗ | Method of use | U-2335 | Aug 27, 2030 |
| US 9850229 ↗ | Method of use | U-2337 | Aug 27, 2030 |
| US 10258622 ↗ | Method of use | U-4051 | Nov 21, 2032 |
| US 9314464 ↗ | Method of use | U-4051 | Jul 4, 2031 |
| US 8541575 ↗ | Drug substance | U-4051 | Feb 26, 2030 |
| US 9474754 ↗ | Method of use | U-4051 | Aug 5, 2033 |
| US 9850230 ↗ | Method of use | U-4051 | Aug 27, 2030 |
| US 10005761 ↗ | Method of use | U-4051 | Aug 27, 2030 |
| US 8946250 ↗ | Drug substance | — | Jul 23, 2029 |
| US 8946250 ↗ | Drug substance | — | Jul 23, 2029 |
| US 9593099 ↗ | Drug substance | — | Aug 27, 2030 |
| US 9387208 ↗ | Drug product | — | Nov 21, 2032 |
| US 9593099 ↗ | Drug substance | — | Aug 27, 2030 |
| US 9593100 ↗ | Drug product | — | Aug 27, 2030 |
| US RE49556 ↗ | Drug substance | — | Feb 27, 2030 |
| US 9387208 ↗ | Drug product | — | Nov 21, 2032 |
| US 9593100 ↗ | Drug product | — | Aug 27, 2030 |
| Code | What it grants | Expires |
|---|---|---|
| I-928 | New indication (3-year) | Oct 11, 2026 |
| I-957 | New indication (3-year) | Dec 20, 2027 |
| ODE-445 | Orphan Drug Exclusivity (7-year) | Oct 11, 2030 |
| I-928 | New indication (3-year) | Oct 11, 2026 |
| I-957 | New indication (3-year) | Dec 20, 2027 |
| ODE-445 | Orphan Drug Exclusivity (7-year) | Oct 11, 2030 |
Is there a generic version of BRAFTOVI 75 MG CAPSULE?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 6, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Encorafenib inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D9C330MD8B
Copovidone is a synthetic polymer made by combining two types of plastic-like molecules. It acts as a binder and film-former to help hold tablet ingredients together and improve how the medicine dissolves in your body.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII AB6MNQ6J6L
Succinic acid is an organic acid derived from natural sources or chemical synthesis. In medications, it functions as a buffer to help maintain the proper pH level and may also serve as a preservative or flavor enhancer in formulations.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
14 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 6, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Array BioPharma Inc. labeler code 70255
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE BRAFTOVI is a kinase inhibitor indicated: Melanoma • in combination with binimetinib, for the treatment of patients with unresectable or metastatic melanoma with a BRAF V600E or V600K mutation, as detected by an FDA-authorized test. ( 1.1 , 2.1 ) Colorectal Cancer (CRC) • in combination with cetuximab and fluorouracil-based chemotherapy, for the treatment of adult patients with metastatic colorectal cancer (mCRC) with a BRAF V600E mutation, as detected by an FDA‑authorized test. ( 1.2 , 2.1 ) • in combination with cetuximab, for the treatment of adult patients with mCRC with a BRAF V600E mutation, as detected by an FDA-authorized test, after prior therapy.
( 1.2 , 2.1 ) Non-Small Cell Lung Cancer (NSCLC) • in combination with binimetinib, for the treatment of adult patients with metastatic non–small cell lung cancer (NSCLC) with a BRAF V600E mutation, as detected by an FDA-authorized test. ( 1.3 , 2.1 ) Limitations of Use BRAFTOVI is not indicated for treatment of patients with wild-type BRAF melanoma, wild-type BRAF CRC, or wild-type BRAF NSCLC. ( 1.4 , 5.2 )
1.1BRAF V600E or V600K Mutation–Positive Unresectable or Metastatic Melanoma BRAFTOVI is indicated, in combination with binimetinib, for the treatment of patients with unresectable or metastatic melanoma with a BRAF V600E or V600K mutation, as detected by an FDA-authorized test [see Dosage and Administration (2.1) ] .
1.2BRAF V600E Mutation-Positive Metastatic Colorectal Cancer (mCRC) • BRAFTOVI is indicated, in combination with cetuximab and fluorouracil-based chemotherapy , for the treatment of adult patients with metastatic colorectal cancer (mCRC) with a BRAF V600E mutation, as detected by an FDA- authorized test [see Dosage and Administration (2.1) ]. • BRAFTOVI is indicated, in combination with cetuximab, for the treatment of adult patients with mCRC with a BRAF V600E mutation, as detected by an FDA- authorized test, after prior therapy [see Dosage and Administration (2.1) ].
1.3BRAF V600E Mutation-Positive Metastatic Non-Small Cell Lung Cancer (NSCLC) BRAFTOVI is indicated, in combination with binimetinib, for the treatment of adult patients with metastatic non-small cell lung cancer (NSCLC) with a BRAF V600E mutation, as detected by an FDA-authorized test [see Dosage and Administration (2.1) ] .
1.4Limitations of Use BRAFTOVI is not indicated for treatment of patients with wild-type BRAF melanoma, wild-type BRAF CRC, or wild-type BRAF NSCLC [see Warnings and Precautions (5.2)] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Melanoma • Confirm the presence of BRAF V600E or V600K mutation in tumor specimens prior to the initiation of BRAFTOVI. ( 2.1 ) • The recommended dose is 450 mg orally once daily in combination with binimetinib. ( 2.2 ) CRC • Confirm the presence of BRAF V600E mutation in plasma or tumor specimens prior to the initiation of BRAFTOVI.
( 2.1 ) • The recommended dose is 300 mg orally once daily in combination with o biweekly cetuximab and mFOLFOX6 (fluorouracil, leucovorin and oxaliplatin) or cetuximab and FOLFIRI (fluorouracil, leucovorin and irinotecan) ( 2.3 ) o weekly cetuximab ( 2.3 ) NSCLC • Confirm the presence of BRAF V600E mutation in tumor or plasma specimens prior to initiating BRAFTOVI. ( 2.1 ) • The recommended dose is 450 mg orally once daily in combination with binimetinib. ( 2.2 ) Take BRAFTOVI with or without food.
( 2.4 )
2.1Patient Selection BRAF V600E or V600K Mutation-Positive Unresectable or Metastatic Melanoma Confirm the presence of a BRAF V600E or V600K mutation in tumor specimens prior to initiating BRAFTOVI [see Warnings and Precautions (5.2) , Clinical Studies (14.1) ] . Information on FDA-authorized tests for the detection of BRAF V600E and V600K mutations in melanoma is available at: http://www.fda.gov/CompanionDiagnostics . BRAF V600E Mutation-Positive Metastatic Colorectal Cancer (CRC) Confirm the presence of a BRAF V600E mutation in plasma or tumor tissue prior to initiating BRAFTOVI [see Warnings and Precautions (5.2) , Clinical Studies (14.2 , 14.3) ].
If no mutation is detected in a plasma specimen, test tumor tissue. Information on FDA- authorized tests for the detection of BRAF V600E mutations in CRC is available at: http://www.fda.gov/CompanionDiagnostics . BRAF V600E Mutation-Positive Metastatic Non‑Small Cell Lung Cancer (NSCLC) Confirm the presence of a BRAF V600E mutation in tumor or plasma specimens prior to initiating BRAFTOVI [see Warnings and Precautions (5.2) , Clinical Studies (14.3) ] .
If no mutation is detected in a plasma specimen, test tumor tissue. Information on FDA- authorized tests for the detection of BRAF V600E mutations in NSCLC is available at: http://www.fda.gov/CompanionDiagnostics .
2.2Recommended Dosage for BRAF V600E or V600K Mutation-Positive Unresectable or Metastatic Melanoma and for BRAF V600E Mutation-Positive Metastatic Non-Small Cell Lung Cancer (NSCLC) The recommended dosage of BRAFTOVI is 450 mg (six 75 mg capsules) orally once daily in combination with binimetinib until disease progression or unacceptable toxicity. Refer to the binimetinib prescribing information for recommended binimetinib dosing information.
2.3Recommended Dosage for BRAF V600E Mutation-Positive Metastatic Colorectal Cancer (CRC) The recommended dosage of BRAFTOVI is 300 mg (four 75 mg capsules) orally once daily until disease progression or unacceptable toxicity in combination with: • biweekly cetuximab and mFOLFOX6 (fluorouracil, leucovorin and oxaliplatin) or biweekly cetuximab and FOLFIRI (fluorouracil, leucovorin and irinotecan) [see Clinical Studies (14.2) ] • weekly cetuximab [see Clinical Studies (14.2) ].
2.4Administration BRAFTOVI may be taken with or without food [see Clinical Pharmacology (12.3) ] . Do not take a missed dose of BRAFTOVI within 12 hours of the next dose of BRAFTOVI. Do not take an additional dose if vomiting occurs after BRAFTOVI administration but continue with the next scheduled dose.
2.5Dosage Modifications for Adverse Reactions BRAF V600E or V600K Mutation-Positive Unresectable or Metastatic Melanoma or BRAF V600E Mutation-Positive Metastatic NSCLC If binimetinib is withheld, reduce BRAFTOVI to a maximum dose of 300 mg (four 75 mg capsules) once daily until binimetinib is resumed [see Warnings and Precautions (5.9) ] . Dose reductions for adverse reactions associated with BRAFTOVI are presented in Table 1. Table 1: Recommended Dose Reductions for BRAFTOVI for Adverse Reactions – Melanoma or NSCLC Action Recommended Dose F… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Capsules: 75 mg, hard gelatin, stylized "A" on beige cap and "LGX 75mg" on white body. Capsules: 75 mg. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS None. None. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • New Primary Malignancies, cutaneous and noncutaneous : Can occur. Monitor for malignancies and perform dermatologic evaluations prior to, while on therapy, and following discontinuation of treatment. ( 5.1 ) • Tumor Promotion in BRAF Wild-Type Tumors : Increased cell proliferation can occur with BRAF inhibitors.
( 5.2 ) • Cardiomyopathy : Assess left ventricular ejection fraction (LVEF) before initiating treatment with BRAFTOVI and binimetinib, and after one month of treatment, then every 2 to 3 months thereafter. The safety of BRAFTOVI in combination with binimetinib has not been established in patients with LVEF below 50%. ( 5.3 ) • Hepatotoxicity : Monitor liver function tests before and during treatment with BRAFTOVI and binimetinib and as clinically indicated.
( 5.4 ) • Hemorrhage : Major hemorrhagic events can occur in patients receiving BRAFTOVI and binimetinib. ( 5.5 ) • Uveitis : Perform ophthalmologic evaluation at regular intervals and for any visual disturbances. ( 5.6 ) • QT Prolongation : Monitor electrolytes before and during treatment.
Correct electrolyte abnormalities and control for cardiac risk factors for QT prolongation. Withhold BRAFTOVI for QTc of 500 ms or greater. ( 5.7 ) • Embryo-Fetal Toxicity : Can cause fetal harm.
Advise females with reproductive potential of potential risk to the fetus and to use effective nonhormonal method of contraception. ( 5.8 , 8.1 , 8.3 ) • Risks Associated with BRAFTOVI as a Single Agent : If binimetinib is temporarily interrupted or permanently discontinued, reduce the dose of BRAFTOVI as recommended. ( 5.9 ) • Risks Associated with Combination Treatment : BRAFTOVI is indicated for use as part of a regimen in combination with binimetinib or cetuximab.
( 5.10 )
5.1New Primary Malignancies New primary malignancies, cutaneous and noncutaneous, have been observed in patients treated with BRAF inhibitors and can occur with BRAFTOVI. Cutaneous Malignancies In COLUMBUS, cutaneous squamous cell carcinoma (cuSCC), including keratoacanthoma (KA), occurred in 2.6%, and basal cell carcinoma occurred in 1.6% of patients who received BRAFTOVI in combination with binimetinib. Median time to first occurrence of cuSCC/KA was 5.8 months (range 1 to 9 months) [see Adverse Reactions (6.1) ] .
For patients who received BRAFTOVI as a single agent, cuSCC/KA was reported in 8%, basal cell carcinoma in 1%, and a new primary melanoma in 5% of patients. In BEACON CRC, cuSCC/KA occurred in 1.4% of patients with CRC, and a new primary melanoma occurred in 1.4% of patients who received BRAFTOVI in combination with cetuximab. In PHAROS, cuSCC and skin papilloma, each occurred in 2% of patients who received BRAFTOVI in combination with binimetinib.
In BREAKWATER, the following cutaneous malignancies occurred in patients receiving BRAFTOVI in combination with cetuximab and mFOLFOX6: melanocytic nevus in 5.6%, skin papilloma in 3% , basal cell carcinoma in 1.3%, squamous cell carcinoma of skin in 0.9%, keratoacanthoma in 0.4% and malignant melanoma in situ in 0.4%. In patients who received BRAFTOVI in combination with cetuximab and FOLFIRI, skin papilloma occurred in 2.8% and keratoacanthoma in 1.4% of patients. Perform dermatologic evaluations prior to initiating treatment, every 2 months during treatment, and for up to 6 months following discontinuation of treatment.
Manage suspicious skin lesions with excision and dermatopathologic evaluation. Dose modification is not recommended for new primary cutaneous malignancies. Noncutaneous Malignancies Based on its mechanism of action, BRAFTOVI may promote malignancies associated with activation of RAS through mutation or other mechanisms [see Warnings and Precautions (5.2) ] .
Monitor patients receiving BRAFTOVI for signs and symptoms of noncutaneous malignancies. Discontinue BRAFTOVI for RAS mutation-positive noncutaneous malignancies [see Dosage and Administration (2.5) ] .
5.2Tumor Promotion in BRAF Wild-Type Tumors In vitro… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are described elsewhere in the labeling: • New Primary Malignancies [see Warnings and Precautions (5.1) ] • Tumor Promotion in BRAF Wild-Type Tumors [see Warnings and Precautions (5.2) ] • Cardiomyopathy [see Warnings and Precautions (5.3) ] • Hepatotoxicity [see Warnings and Precautions (5.4) ] • Hemorrhage [see Warnings and Precautions (5.5) ] • Uveitis [see Warnings and Precautions (5.6) ] • QT Prolongation [see Warnings and Precautions (5.7) ] • Embryo-Fetal Toxicity [see Warnings and Precautions (5.8) ] • Risks Associated with BRAFTOVI as a Single Agent [see Warnings and Precautions (5.9) ] • Risks Associated with Combination Treatment [see Warnings and Precautions (5.10) ] • Melanoma : Most common adverse reactions (≥25%) for BRAFTOVI, in combination with binimetinib, are fatigue, nausea, vomiting, abdominal pain, and arthralgia.
( 6.1 ) • CRC : Most common adverse reactions (≥25%) for BRAFTOVI, in combination with cetuximab and mFOLFOX6, are peripheral neuropathy, nausea, fatigue, diarrhea, decreased appetite, rash, vomiting, hemorrhage, abdominal pain, arthralgia, pyrexia, and constipation. ( 6.1 ) • Most common adverse reactions (≥25%) for BRAFTOVI, in combination with cetuximab and FOLFIRI are nausea, diarrhea, fatigue, vomiting, alopecia, constipation, abdominal pain, decreased appetite, and rash. ( 6.1 ) • Most common adverse reactions (≥25%) for BRAFTOVI, in combination with cetuximab, are fatigue, nausea, diarrhea, dermatitis acneiform, abdominal pain, decreased appetite, arthralgia, and rash.
( 6.1 ) • NSCLC : Most common adverse reactions (≥25%) for BRAFTOVI, in combination with binimetinib, are fatigue, nausea, diarrhea, musculoskeletal pain, vomiting, abdominal pain, visual impairment, constipation, dyspnea, rash, and cough. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Pfizer Inc. at 1-800-438-1985 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. BRAF V600E or V600K Mutation-Positive Unresectable or Metastatic Melanoma The safety of BRAFTOVI in combination with binimetinib is described in 192 patients with BRAF V600 mutation-positive unresectable or metastatic melanoma who received BRAFTOVI (450 mg once daily) in combination with binimetinib (45 mg twice daily) in a randomized open-label, active-controlled trial (COLUMBUS).
The COLUMBUS trial [see Clinical Studies (14.1) ] excluded patients with a history of Gilbert's syndrome, abnormal left ventricular ejection fraction, prolonged QTc (>480 ms), uncontrolled hypertension, and history or current evidence of retinal vein occlusion. The median duration of exposure was 11.8 months for patients treated with BRAFTOVI in combination with binimetinib and 6.2 months for patients treated with vemurafenib. The most common (≥25%) adverse reactions in patients receiving BRAFTOVI in combination with binimetinib were fatigue, nausea, vomiting, abdominal pain, and arthralgia.
Adverse reactions leading to dose interruptions of BRAFTOVI occurred in 30% of patients receiving BRAFTOVI in combination with binimetinib; the most common were nausea (7%), vomiting (7%), and pyrexia (4%). Adverse reactions leading to dose reductions of BRAFTOVI occurred in 14% of patients receiving BRAFTOVI in combination with binimetinib; the most common were arthralgia (2%), fatigue (2%), and nausea (2%). Five percent (5%) of patients receiving BRAFTOVI in combination with binimetinib experienced an adverse reaction that resulted in permanent discontinuation of BRAFTOVI; the most common were hemorrhage in 2% and headache in 1% of patients.
Table 5 and Table 6 present adverse drug reactions and laboratory abnormalities, respectively, identified in… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Strong or moderate CYP3A4 inhibitors: Avoid coadministration. If unavoidable, reduce BRAFTOVI dosage. ( 2.6 , 7.1 ) • Strong CYP3A4 inducers: Avoid coadministration.
( 7.1 ) • Sensitive CYP3A4 substrates: Avoid coadministration with CYP3A4 substrates (including hormonal contraceptives) for which a decrease in plasma concentration may lead to reduced efficacy of the substrate. ( 7.2 ) • Transporters: Dose reductions of drugs that are substrates of OATP1B1, OATP1B3, or BCRP may be required when used concomitantly with BRAFTOVI. ( 7.2 , 12.3 )
7.1Effect of Other Drugs on BRAFTOVI Strong or Moderate CYP3A4 Inhibitors Coadministration of BRAFTOVI with a strong or moderate CYP3A4 inhibitor increases encorafenib plasma concentrations [see Clinical Pharmacology (12.3) ] and may increase encorafenib adverse reactions. Avoid coadministration of BRAFTOVI with strong or moderate CYP3A4 inhibitors, including grapefruit juice. If coadministration is unavoidable, reduce the BRAFTOVI dose [see Dosage and Administration (2.6) ] .
Strong CYP3A4 Inducers Coadministration of BRAFTOVI with a strong CYP3A4 inducer may decrease encorafenib plasma concentrations [see Clinical Pharmacology (12.3) ] and may decrease encorafenib efficacy. Avoid coadministration of BRAFTOVI with strong CYP3A4 inducers.
7.2Effect of BRAFTOVI on Other Drugs Sensitive CYP3A4 Substrates BRAFTOVI is a strong CYP3A4 inducer at steady-state. Concomitant use of BRAFTOVI may decrease the plasma concentrations of CYP3A4 substrates (including hormonal contraceptives), [see Clinical Pharmacology (12.3) ] , which may reduce the efficacy of these substrates. Avoid the coadministration of BRAFTOVI with CYP3A4 substrates for which a decrease in plasma concentration may lead to reduced efficacy of the substrate.
If the coadministration cannot be avoided, see the CYP3A4 substrate product labeling for recommendations. OATP1B1, OATP1B3, or BCRP Substrates Coadministration of BRAFTOVI with OATP1B1, OATP1B3, or BCRP substrates can result in increased concentrations of the substrates, and may increase toxicity of these agents. When used in combination, monitor patients closely for signs and symptoms of increased exposure and consider adjusting the dose of these substrates [see Clinical Pharmacology (12.3) ].
7.3Drugs That Prolong the QT Interval BRAFTOVI is associated with dose-dependent QTc interval prolongation [see Warnings and Precautions (5.7) , Clinical Pharmacology (12.2) ] . Avoid coadministration of BRAFTOVI with drugs known to prolong the QT/QTc interval.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Lactation : Advise not to breastfeed. ( 8.2 ) • Males of Reproductive Potential : BRAFTOVI may impair fertility. ( 8.3 )
8.1Pregnancy Risk Summary Based on its mechanism of action, BRAFTOVI can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available clinical data on the use of BRAFTOVI during pregnancy. In animal reproduction studies, encorafenib produced embryo-fetal developmental changes in rats and rabbits and was an abortifacient in rabbits at doses greater than or equal to those resulting in exposures approximately 26 (in the rat) and 178 (in the rabbit) times the human exposure at the clinical dose of 450 mg, with no clear findings at lower doses (see Data ) .
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In reproductive toxicity studies, administration of encorafenib to rats during the period of organogenesis resulted in maternal toxicity, decreased fetal weights, and increased incidence of total skeletal variations at a dose of 20 mg/kg/day (approximately 26 times the human exposure based on area under the concentration-time curve [AUC] at the recommended clinical dose of 450 mg once daily).
In pregnant rabbits, administration of encorafenib during the period of organogenesis resulted in maternal toxicity, decreased fetal body weights, increased incidence of total skeletal variations and increased post-implantation loss, including total loss of pregnancy at a dose of 75 mg/kg/day (approximately 178 times the human exposure based on AUC at the recommended clinical dose of 450 mg once daily). While formal placental transfer studies have not been performed, encorafenib exposure in the fetal plasma of both rats and rabbits was up to 1.7% and 0.8%, respectively, of maternal exposure.
8.2Lactation Risk Summary There are no data on the presence of encorafenib or its metabolites in human milk or the effects of encorafenib on the breastfed child, or the effects on milk production. Because of the potential for serious adverse reactions in a breastfed child from BRAFTOVI, advise women not to breastfeed during treatment with BRAFTOVI and for 2 weeks after the last dose.
8.3Females and Males of Reproductive Potential BRAFTOVI can cause fetal harm when administered to a pregnant woman [see Use in Specific Populations (8.1) ] . Pregnancy Testing Verify the pregnancy status of females of reproductive potential prior to initiating BRAFTOVI [see Use in Specific Populations (8.1) ]. Contraception Females Advise females of reproductive potential to use effective contraception during treatment with BRAFTOVI and for 2 weeks after the last dose.
Counsel patients to use a nonhormonal method of contraception since BRAFTOVI has the potential to render hormonal contraceptives ineffective [see Drug Interactions (7.2) ] . Infertility Males Based on findings in male rats at doses approximately 13 times the human exposure at the 450 mg clinical dose, use of BRAFTOVI may impact fertility in males [see Nonclinical Toxicology (13.1) ] .
8.4Pediatric Use The safety and effectiveness of BRAFTOVI have not been established in pediatric patients.
8.5Geriatric Use Of the 690 patients with BRAF mutation-positive melanoma who received BRAFTOVI in combination with binimetinib across multiple clinical trials, 20% were aged 65 to 74 years and 8% were aged 75 years and older [see Clinical Studies (14.1) ] . Of the 232 patients with BRAF V600E mutation-positive metastatic CRC who received BRAFTOVI in combination with cetuximab and mFOLFOX6, 84 (36%) were 65 years of age and over and 16 (7%) were 75 years of age and over [see Clinical Studies (14.2) ] . Of the 71 patients with BRAF V600E mutation-positive metastatic CRC who receiv… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Based on its mechanism of action, BRAFTOVI can cause fetal harm when administered to a pregnant woman [see Clinical Pharmacology (12.1) ] . There are no available clinical data on the use of BRAFTOVI during pregnancy. In animal reproduction studies, encorafenib produced embryo-fetal developmental changes in rats and rabbits and was an abortifacient in rabbits at doses greater than or equal to those resulting in exposures approximately 26 (in the rat) and 178 (in the rabbit) times the human exposure at the clinical dose of 450 mg, with no clear findings at lower doses (see Data ) .
Advise pregnant women and females of reproductive potential of the potential risk to a fetus. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Animal Data In reproductive toxicity studies, administration of encorafenib to rats during the period of organogenesis resulted in maternal toxicity, decreased fetal weights, and increased incidence of total skeletal variations at a dose of 20 mg/kg/day (approximately 26 times the human exposure based on area under the concentration-time curve [AUC] at the recommended clinical dose of 450 mg once daily).
In pregnant rabbits, administration of encorafenib during the period of organogenesis resulted in maternal toxicity, decreased fetal body weights, increased incidence of total skeletal variations and increased post-implantation loss, including total loss of pregnancy at a dose of 75 mg/kg/day (approximately 178 times the human exposure based on AUC at the recommended clinical dose of 450 mg once daily). While formal placental transfer studies have not been performed, encorafenib exposure in the fetal plasma of both rats and rabbits was up to 1.7% and 0.8%, respectively, of maternal exposure.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of BRAFTOVI have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 690 patients with BRAF mutation-positive melanoma who received BRAFTOVI in combination with binimetinib across multiple clinical trials, 20% were aged 65 to 74 years and 8% were aged 75 years and older [see Clinical Studies (14.1) ] . Of the 232 patients with BRAF V600E mutation-positive metastatic CRC who received BRAFTOVI in combination with cetuximab and mFOLFOX6, 84 (36%) were 65 years of age and over and 16 (7%) were 75 years of age and over [see Clinical Studies (14.2) ] . Of the 71 patients with BRAF V600E mutation-positive metastatic CRC who received BRAFTOVI in combination with cetuximab and FOLFIRI, 35 (49%) were 65 years of age and over and 9 (13%) were 75 years of age and over [see Clinical Studies (14.2) ] .
Of the 216 patients with BRAF V600E mutation-positive metastatic CRC who received BRAFTOVI in combination with cetuximab, 62 (29%) were 65 years of age to up to 75 years of age, while 20 (9%) were 75 years of age and over [see Clinical Studies (14.2) ] . Of the 98 patients with BRAF V600E mutation-positive metastatic NSCLC who received BRAFTOVI with binimetinib, 62 (63%) were 65 years of age and over and 20 (20%) were 75 years and over [see Clinical Studies (14.3) ] . No overall differences in the safety or effectiveness of BRAFTOVI plus binimetinib, BRAFTOVI plus cetuximab, or BRAFTOVI plus cetuximab and mFOLFOX6 or FOLFIRI were observed in older patients as compared to younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE Since encorafenib is 86% bound to plasma proteins, hemodialysis is likely to be ineffective in the treatment of overdose with BRAFTOVI.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Encorafenib is a kinase inhibitor that targets BRAF V600E, as well as wild-type BRAF and CRAF in in vitro cell-free assays with IC 50 values of 0.35, 0.47, and 0.3 nM, respectively. Mutations in the BRAF gene, such as BRAF V600E, can result in constitutively activated BRAF kinases that may stimulate tumor cell growth. Encorafenib was also able to bind to other kinases in vitro including JNK1, JNK2, JNK3, LIMK1, LIMK2, MEK4, and STK36 and reduce ligand binding to these kinases at clinically achievable concentrations (≤0.9 µM).
Encorafenib inhibited in vitro growth of tumor cell lines expressing BRAF V600 E, D, and K mutations. In mice implanted with tumor cells expressing BRAF V600E , encorafenib induced tumor regressions associated with RAF/MEK/ERK pathway suppression. Encorafenib and binimetinib target two different kinases in the RAS/RAF/MEK/ERK pathway.
Compared with either drug alone, coadministration of encorafenib and binimetinib resulted in greater anti-proliferative activity in vitro in BRAF mutation-positive cell lines and greater anti-tumor activity with respect to tumor growth inhibition in BRAF V600E mutant human melanoma xenograft studies in mice. Additionally, the combination of encorafenib and binimetinib delayed the emergence of resistance in BRAF V600E mutant human melanoma xenografts in mice compared to either drug alone. In a BRAF V600E mutant NSCLC patient-derived xenograft model in mice, coadministration of encorafenib and binimetinib resulted in greater anti-tumor activity compared to binimetinib alone, with respect to tumor growth inhibition.
Increased tumor growth delay after dosing cessation was also observed with the coadministration compared to either drug alone. In the setting of BRAF-mutant CRC, induction of EGFR-mediated MAPK pathway activation has been identified as a mechanism of resistance to BRAF inhibitors. Combinations of a BRAF inhibitor and agents targeting EGFR have been shown to overcome this resistance mechanism in nonclinical models.
Coadministration of encorafenib and cetuximab had an anti-tumor effect greater than either drug alone, in a mouse model of colorectal cancer with mutated BRAF V600E.
12.2Pharmacodynamics Cardiac Electrophysiology A dedicated study to evaluate the QT prolongation potential of BRAFTOVI has not been conducted. BRAFTOVI is associated with dose-dependent QTc interval prolongation. Based on a central tendency analysis of QTc in a study of adult patients with melanoma who received the recommended dose of BRAFTOVI in combination with binimetinib, the largest mean (90% CI) QTcF change from baseline (ΔQTcF) was 18 (14 to 22) ms [see Warnings and Precautions (5.7) ] .
12.3Pharmacokinetics The pharmacokinetics of encorafenib were studied in healthy subjects and patients with solid tumors, including advanced and unresectable or metastatic cutaneous melanoma harboring a BRAF V600E or V600K mutation, BRAF V600E mutation-positive metastatic CRC. After a single dose, systemic exposure of encorafenib was dose proportional over the dose range of 50 mg to 700 mg (0.1 to 1.6 times the maximum recommended dose of 450 mg). After once-daily dosing, systemic exposure of encorafenib was less than dose proportional over the dose range of 50 mg to 800 mg (0.1 to 1.8 times the maximum recommended dose of 450 mg).
Steady-state was reached within 15 days, with exposure being 50% lower compared to Day 1; intersubject variability (CV%) of AUC ranged from 12% to 69%. Absorption The median T max of encorafenib is 2 hours. At least 86% of the dose is absorbed.
Effect of Food Following administration of a single dose of BRAFTOVI 100 mg (0.2 times the maximum recommended dose of 450 mg) with a high-fat, high-calorie meal (consisting of approximately 150 calories from protein, 350 calories from carbohydrates, and 500 calories from fat) the mean maximum encorafenib concentration (C max ) decreased by 36% and there was no effect on AUC. Distribu… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action Encorafenib is a kinase inhibitor that targets BRAF V600E, as well as wild-type BRAF and CRAF in in vitro cell-free assays with IC 50 values of 0.35, 0.47, and 0.3 nM, respectively. Mutations in the BRAF gene, such as BRAF V600E, can result in constitutively activated BRAF kinases that may stimulate tumor cell growth. Encorafenib was also able to bind to other kinases in vitro including JNK1, JNK2, JNK3, LIMK1, LIMK2, MEK4, and STK36 and reduce ligand binding to these kinases at clinically achievable concentrations (≤0.9 µM).
Encorafenib inhibited in vitro growth of tumor cell lines expressing BRAF V600 E, D, and K mutations. In mice implanted with tumor cells expressing BRAF V600E , encorafenib induced tumor regressions associated with RAF/MEK/ERK pathway suppression. Encorafenib and binimetinib target two different kinases in the RAS/RAF/MEK/ERK pathway.
Compared with either drug alone, coadministration of encorafenib and binimetinib resulted in greater anti-proliferative activity in vitro in BRAF mutation-positive cell lines and greater anti-tumor activity with respect to tumor growth inhibition in BRAF V600E mutant human melanoma xenograft studies in mice. Additionally, the combination of encorafenib and binimetinib delayed the emergence of resistance in BRAF V600E mutant human melanoma xenografts in mice compared to either drug alone. In a BRAF V600E mutant NSCLC patient-derived xenograft model in mice, coadministration of encorafenib and binimetinib resulted in greater anti-tumor activity compared to binimetinib alone, with respect to tumor growth inhibition.
Increased tumor growth delay after dosing cessation was also observed with the coadministration compared to either drug alone. In the setting of BRAF-mutant CRC, induction of EGFR-mediated MAPK pathway activation has been identified as a mechanism of resistance to BRAF inhibitors. Combinations of a BRAF inhibitor and agents targeting EGFR have been shown to overcome this resistance mechanism in nonclinical models.
Coadministration of encorafenib and cetuximab had an anti-tumor effect greater than either drug alone, in a mouse model of colorectal cancer with mutated BRAF V600E.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING BRAFTOVI (encorafenib) is supplied as 75 mg hard gelatin capsules. 75 mg: stylized "A" on beige cap and "LGX 75mg" on white body, available in cartons (NDC 70255-025-01) containing two bottles of 90 capsules each (NDC 70255-025-02) and cartons (NDC 70255-025-03) containing two bottles of 60 capsules each (NDC 70255-025-04). Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature].
Do not use if safety seal under cap is broken or missing. Dispense in original bottle. Do not remove desiccant.
Protect from moisture. Keep container tightly closed.
📦 Storage and Handling ▾
Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [see USP Controlled Room Temperature]. Do not use if safety seal under cap is broken or missing. Dispense in original bottle. Do not remove desiccant. Protect from moisture. Keep container tightly closed.
📋 Description ▾
11 DESCRIPTION Encorafenib is a kinase inhibitor. The chemical name is methyl N -{(2 S )-1-[(4-{3-[5-chloro-2-fluoro-3-(methanesulfonamido)phenyl]-1-(propan-2-yl)-1 H -pyrazol-4-yl}pyrimidin-2-yl)amino]propan-2-yl}carbamate. The molecular formula is C 22 H 27 ClFN 7 O 4 S and the molecular weight is 540 daltons.
The chemical structure of encorafenib is shown below: Encorafenib is a white to almost white powder. In aqueous media, encorafenib is slightly soluble at pH 1, very slightly soluble at pH 2, and insoluble at pH 3 and higher. BRAFTOVI (encorafenib) capsules for oral use contain 75 mg of encorafenib with the following inactive ingredients: copovidone, poloxamer 188, microcrystalline cellulose, succinic acid, crospovidone, colloidal silicon dioxide, magnesium stearate (vegetable origin).
The capsule shell contains gelatin, titanium dioxide, iron oxide red, iron oxide yellow, ferrosoferric oxide, monogramming ink (pharmaceutical glaze, ferrosoferric oxide, propylene glycol). Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-authorized patient labeling (Medication Guide). Inform patients of the following: New Primary Malignancies Advise patients that BRAFTOVI increases the risk of developing new primary cutaneous and noncutaneous malignancies. Advise patients to contact their healthcare provider immediately for change in or development of new skin lesions [see Warnings and Precautions (5.1) ] .
Tumor Promotion in BRAF Wild-Type Tumors Advise patients of the need to confirm BRAF V600E or V600K mutation prior to initiating BRAFTOVI [see Warnings and Precautions (5.2) ] . Cardiomyopathy Advise patients to report any symptoms of heart failure to their healthcare provider [see Warnings and Precautions (5.3) ] . Hepatotoxicity Advise patients that serial testing of serum liver tests (ALT, AST, bilirubin) is recommended during treatment with BRAFTOVI.
Instruct patients to report symptoms of liver dysfunction including jaundice, dark urine, nausea, vomiting, loss of appetite, fatigue, bruising, or bleeding [see Warnings and Precautions (5.4) ] . Hemorrhage Advise patients to notify their healthcare provider immediately with any symptoms suggestive of hemorrhage, such as unusual bleeding [see Warnings and Precautions (5.5) ] . Uveitis Advise patients to contact their healthcare provider if they experience any changes in their vision [see Warnings and Precautions (5.6) ] .
QT Prolongation Advise patients that BRAFTOVI can cause QTc interval prolongation and to inform their physician if they have any QTc interval prolongation symptoms, such as syncope [see Warnings and Precautions (5.7) ] . Embryo-Fetal Toxicity • Advise females with reproductive potential of the potential risk to a fetus. Advise females to contact their healthcare provider if they become pregnant, or if pregnancy is suspected, during treatment with BRAFTOVI [see Warnings and Precautions (5.8) , Use in Specific Populations (8.1) ] . • Advise females of reproductive potential to use effective nonhormonal contraception during treatment with BRAFTOVI and for 2 weeks after the last dose [see Use in Specific Populations (8.3) ] .
Lactation Advise women not to breastfeed during treatment with BRAFTOVI and for 2 weeks after the last dose [see Use in Specific Populations (8.2) ] . Infertility Advise males of reproductive potential that BRAFTOVI may impair fertility [see Use in Specific Populations (8.3) ] . Drug Interactions Coadministration of BRAFTOVI with a strong or moderate CYP3A inhibitor may increase encorafenib concentrations; coadministration of BRAFTOVI with a strong CYP3A inducer may decrease encorafenib concentrations.
Advise patients that they may need to avoid certain medications while taking BRAFTOVI and to inform their healthcare provider of all concomitant medications, including prescription medicines, over-the-counter drugs, vitamins, and herbal products. Advise patients to avoid grapefruit and grapefruit juice while taking BRAFTOVI [see Drug Interactions (7.1) ] . Storage BRAFTOVI is moisture sensitive.
Advise patients to store BRAFTOVI in the original bottle with desiccant and to keep the cap of the bottle tightly closed. Do not remove the desiccants from the bottle.
💬 Medication Guide ▾
MEDICATION GUIDE BRAFTOVI ® (braf-TOE-vee) (encorafenib) capsules Important information: BRAFTOVI is used in combination with other medicines, including binimetinib, cetuximab, or cetuximab and fluorouracil-based chemotherapy. Read the Medication Guide that comes with binimetinib if BRAFTOVI is used with binimetinib. Talk to your healthcare provider about cetuximab, or cetuximab and mFOLFOX6 or FOLFIRI if used with BRAFTOVI.
What is the most important information I should know about BRAFTOVI? BRAFTOVI can cause serious side effects, including: Risk of new skin cancers. BRAFTOVI can cause skin cancers called cutaneous squamous cell carcinoma or basal cell carcinoma.
Talk to your healthcare provider about your risk for these cancers. Check your skin and tell your healthcare provider right away about any skin changes, including a: • new wart • skin sore or reddish bump that bleeds or does not heal • change in size or color of a mole Your healthcare provider should check your skin before treatment with BRAFTOVI, every 2 months during treatment, and for up to 6 months after you stop treatment with BRAFTOVI to look for any new skin cancers. Your healthcare provider should also check for cancers that may not occur on the skin.
Tell your healthcare provider about any new symptoms that develop during treatment with BRAFTOVI. See " What are the possible side effects of BRAFTOVI ? " for more information about side effects. What is BRAFTOVI?
BRAFTOVI is a prescription medicine used: • in combination with a medicine called binimetinib to treat people with a type of skin cancer called melanoma: o that has spread to other parts of the body or cannot be removed by surgery, and o that has a certain type of abnormal " BRAF " gene • in combination with medicines called cetuximab and mFOLFOX6 (fluorouracil, leucovorin and oxaliplatin) or cetuximab and FOLFIRI (fluorouracil, leucovorin, and irinotecan) to treat adults with cancer of the colon or rectum (colorectal cancer): o that has spread to other parts of the body, and o that has a certain type of abnormal " BRAF " gene • in combination with a medicine called cetuximab to treat adults with cancer of the colon or rectum (colorectal cancer) after past treatment: o that has spread to other parts of the body, and o that has a certain type of abnormal " BRAF " gene • in combination with a medicine called binimetinib to treat adults with a type of lung cancer called non‑small‑cell lung cancer (NSCLC): o that has spread to other parts of the body, and o that has a certain type of abnormal " BRAF " gene BRAFTOVI should not be used to treat people with wild-type‑ BRAF melanoma, wild-type‑ BRAF colorectal cancer, or wild-type‑ BRAF NSCLC.
Your healthcare provider will perform a test to make sure that BRAFTOVI is right for you. It is not known if BRAFTOVI is safe and effective in children. Before taking BRAFTOVI, tell your healthcare provider about all of your medical conditions, including if you: • have had bleeding problems • have eye problems • have heart problems, including a condition called long QT syndrome • have been told that you have low blood levels of potassium, calcium, or magnesium • have liver or kidney problems • are pregnant or plan to become pregnant.
BRAFTOVI can harm your unborn baby. Females who are able to become pregnant: o Use effective nonhormonal birth control (contraception) during treatment with BRAFTOVI and for 2 weeks after the last dose of BRAFTOVI. Birth control methods that contain hormones (such as birth control pills, injections or transdermal systems) may not work as well during treatment with BRAFTOVI. o Talk to your healthcare provider about birth control methods that may be right for you during this time. o Your healthcare provider will do a pregnancy test before you start taking BRAFTOVI.
Tell your healthcare provider right away if you become pregnant or think you might be pregnant during treatment with BRAFTOVI. • are breastfeeding or plan to breastfeed. It is not… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics The pharmacokinetics of encorafenib were studied in healthy subjects and patients with solid tumors, including advanced and unresectable or metastatic cutaneous melanoma harboring a BRAF V600E or V600K mutation, BRAF V600E mutation-positive metastatic CRC. After a single dose, systemic exposure of encorafenib was dose proportional over the dose range of 50 mg to 700 mg (0.1 to 1.6 times the maximum recommended dose of 450 mg). After once-daily dosing, systemic exposure of encorafenib was less than dose proportional over the dose range of 50 mg to 800 mg (0.1 to 1.8 times the maximum recommended dose of 450 mg).
Steady-state was reached within 15 days, with exposure being 50% lower compared to Day 1; intersubject variability (CV%) of AUC ranged from 12% to 69%. Absorption The median T max of encorafenib is 2 hours. At least 86% of the dose is absorbed.
Effect of Food Following administration of a single dose of BRAFTOVI 100 mg (0.2 times the maximum recommended dose of 450 mg) with a high-fat, high-calorie meal (consisting of approximately 150 calories from protein, 350 calories from carbohydrates, and 500 calories from fat) the mean maximum encorafenib concentration (C max ) decreased by 36% and there was no effect on AUC. Distribution The geometric mean (CV%) of apparent volume of distribution is 164 L (70%). The protein binding of encorafenib is 86% in vitro.
The blood-to-plasma concentration ratio is 0.58. Elimination The mean (CV%) terminal half-life (t 1/2 ) of encorafenib is 3.5 hours (17%), and the apparent clearance is 14 L/h (54%) at day 1, increasing to 32 L/h (59%) at steady-state at the maximum recommended dose of 450 mg. Metabolism Encorafenib is primarily metabolized by CYP3A4 (83%) and to a lesser extent by CYP2C19 (16%) and CYP2D6 (1%).
Excretion Following a single radiolabeled dose of 100 mg encorafenib, 47% (5% unchanged) of the administered dose was recovered in feces and 47% (2% unchanged) in urine. Specific Populations No clinically significant differences in the pharmacokinetics of encorafenib were observed based on age (19 to 94 years), sex, body weight (34 to 168 kg), mild hepatic impairment (Child-Pugh Class A), and mild or moderate renal impairment (CLcr 30 to <90 mL/min). The effect of race or ethnicity, moderate or severe hepatic impairment (Child-Pugh Class B or C), and severe renal impairment (CLcr <30 mL/min) on encorafenib pharmacokinetics have not been studied.
Drug Interaction Studies Clinical Studies CYP3A4 Inhibitors: Coadministration of posaconazole (strong CYP3A4 inhibitor) or diltiazem (moderate CYP3A4 inhibitor) increased AUC of encorafenib by 183% and 83%, respectively, and increased C max by 68% and 45%, respectively, after a single dose of 50 mg BRAFTOVI (0.1 times the maximum recommended dose of 450 mg). Strong CYP3A4 Inducers: The effect of a strong CYP3A4 inducer on encorafenib exposure has not been studied [see Drug Interactions (7.1) ] . Moderate CYP3A4 Inducers: Repeat dose administration of BRAFTOVI 450 mg once daily and binimetinib 45 mg twice daily with modafinil, a moderate CYP3A4 inducer, decreased encorafenib steady-state AUC by 24% and C max by 20%, compared to BRAFTOVI alone.
Effect of encorafenib on CYP3A4 Substrates: Repeat dose administration of BRAFTOVI 450 mg once daily and binimetinib 45 mg twice daily with a single dose of midazolam 2 mg, a sensitive CYP3A4 substrate, decreased midazolam AUC by 82% and C max by 74% relative to midazolam 2 mg alone. Effect of encorafenib on Other CYP Substrates: There was no clinically significant effect of repeat dose administration of BRAFTOVI 450 mg once daily and binimetinib 45 mg twice daily on the exposure of substrates of CYP1A2, CYP2B6, CYP2C9, CYP2C19, and CYP2D6.
Proton Pump Inhibitors: No clinically significant differences in encorafenib pharmacokinetics were observed when coadministered with rabeprazole. Binimetinib: No clinically significant differences in the pharmacokinetics of binimetinib (UGT1… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics Cardiac Electrophysiology A dedicated study to evaluate the QT prolongation potential of BRAFTOVI has not been conducted. BRAFTOVI is associated with dose-dependent QTc interval prolongation. Based on a central tendency analysis of QTc in a study of adult patients with melanoma who received the recommended dose of BRAFTOVI in combination with binimetinib, the largest mean (90% CI) QTcF change from baseline (ΔQTcF) was 18 (14 to 22) ms [see Warnings and Precautions (5.7) ] .
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1BRAF V600E or V600K Mutation-Positive Unresectable or Metastatic Melanoma BRAFTOVI in combination with binimetinib was evaluated in a randomized, active-controlled, open-label, multicenter trial (COLUMBUS; NCT01909453). Eligible patients were required to have BRAF V600E or V600K mutation-positive unresectable or metastatic melanoma, as detected using the bioMerieux THxID™ BRAF assay. Patients were permitted to have received immunotherapy in the adjuvant setting and one prior line of immunotherapy for unresectable locally advanced or metastatic disease.
Prior use of BRAF inhibitors or MEK inhibitors was prohibited. Randomization was stratified by American Joint Committee on Cancer (AJCC) Stage (IIIB, IIIC, IVM1a or IVM1b, versus IVM1c), Eastern Cooperative Oncology Group (ECOG) performance status (0 versus 1), and prior immunotherapy for unresectable or metastatic disease (yes versus no). Patients were randomized (1:1:1) to receive BRAFTOVI 450 mg once daily in combination with binimetinib 45 mg twice daily (BRAFTOVI in combination with binimetinib), BRAFTOVI 300 mg once daily, or vemurafenib 960 mg twice daily.
Treatment continued until disease progression or unacceptable toxicity. Only the results of the approved dosing (BRAFTOVI 450 mg in combination with binimetinib 45 mg) are described below. The major efficacy outcome measure was progression-free survival (PFS), as assessed by a blinded independent central review, to compare BRAFTOVI in combination with binimetinib with vemurafenib.
Additional efficacy outcome measures included overall survival (OS), as well as objective response rate (ORR) and duration of response (DoR) which were assessed by central review. A total of 577 patients were randomized, 192 to the BRAFTOVI in combination with binimetinib arm, 194 to the BRAFTOVI arm, and 191 to the vemurafenib arm. Of the 383 patients randomized to either the BRAFTOVI in combination with binimetinib or the vemurafenib arms, the median age was 56 years (20 to 89 years), 59% were male, 91% were White, and 72% had baseline ECOG performance status of 0.
Ninety-five percent (95%) had metastatic disease, 65% were Stage IVM1c, and 4% received prior CTLA-4, PD-1, or PD-L1 directed antibodies. Twenty-eight percent (28%) had elevated baseline serum lactate dehydrogenase (LDH), 45% had ≥3 organs with tumor involvement at baseline, and 3% had brain metastases. Based on centralized testing, 100% of patients' tumors tested positive for BRAF mutations; BRAF V600E (88%), BRAF V600K (11%), or both (<1%).
BRAFTOVI in combination with binimetinib demonstrated a statistically significant improvement in PFS compared to vemurafenib. Efficacy results are summarized in Table 15 and Figure 1. Table 15: Efficacy Results for COLUMBUS CI = Confidence interval; CR = Complete response; DoR = Duration of response; HR = Hazard ratio; NE = Not estimable; ORR = Overall response rate; OS = Overall survival; PFS = Progression-free survival; PR = Partial response.
BRAFTOVI with binimetinib N=192 Vemurafenib N=191 Progression-Free Survival Number of events (%) 98 (51) 106 (55) Progressive disease 88 (46) 104 (54) Death 10 (5) 2 (1) Median PFS, months (95% CI) 14.9 (11.0, 18.5) 7.3 (5.6, 8.2) HR (95% CI) Estimated with Cox proportional hazard model adjusted by the following stratification factors: American Joint Committee on Cancer (AJCC) Stage (IIIB, IIIC, IVM1a or IVM1b, versus IVM1c) and Eastern Cooperative Oncology Group (ECOG) performance status (0 versus 1). 0.54 (0.41, 0.71) P -value Log-rank test adjusted by the same stratification factors. <0.0001 Overall Survival Based on a cutoff date of 82.4 months after the date of the PFS analysis.
Number of events (%) 139 (72) 147 (77) Median OS, months (95% CI) 33.6 (24.4, 39.2) 16.9 (14.0, 24.5) HR (95% CI) 0.67 (0.53, 0.84) Overall Response Rate ORR (95% CI) 63% (56%, 70%) 40% (33%, 48%) CR 8% 6% PR 55% 35% Duration of Response Median DoR, months (95% CI) 16.6 (12.2, 20.4) 12.3 (6.9, 16.9… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with encorafenib have not been conducted. Encorafenib was not genotoxic in studies evaluating reverse mutations in bacteria, chromosomal aberrations in mammalian cells, or micronuclei in bone marrow of rats. No dedicated fertility studies were performed with encorafenib in animals.
In a general toxicology study in rats, decreased testes and epididymis weights, tubular degeneration in testes, and oligospermia in epididymides were observed at doses approximately 13 times the human exposure at the 450 mg clinical dose based on AUC. No effects on reproductive organs were observed in either sex in any of the nonhuman primate toxicity studies.
13.2Animal Toxicology and/or Pharmacology Adverse histopathology findings of hyperplasia and hyperkeratosis occurred in the stomach of rats at encorafenib doses of 20 mg/kg/day (approximately 14 times the human exposure at the 450 mg clinical dose based on AUC) or greater, in both 4 and 13-week studies.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenicity studies with encorafenib have not been conducted. Encorafenib was not genotoxic in studies evaluating reverse mutations in bacteria, chromosomal aberrations in mammalian cells, or micronuclei in bone marrow of rats. No dedicated fertility studies were performed with encorafenib in animals.
In a general toxicology study in rats, decreased testes and epididymis weights, tubular degeneration in testes, and oligospermia in epididymides were observed at doses approximately 13 times the human exposure at the 450 mg clinical dose based on AUC. No effects on reproductive organs were observed in either sex in any of the nonhuman primate toxicity studies.
📄 Recent Major Changes ▾
Indications and Usage ( 1.2 ) 2/2026 Dosage and Administration ( 2.1 , 2.3 , 2.5 ) 2/2026 Warnings and Precautions ( 5.1 , 5.4 , 5.5 , 5.6 , 5.7 , 5.10 ) 2/2026
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Label - 025-02 DISPENSE THE ENCLOSED MEDICATION GUIDE TO EACH PATIENT NDC 70255-025-02 BRAFTOVI ® (encorafenib) capsules 75 mg Rx only 90 Capsules PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Label - 025-02
PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Carton DISPENSE THE ENCLOSED MEDICATION GUIDE TO EACH PATIENT NDC 70255-025-01 BRAFTOVI ® (encorafenib) capsules 75 mg Rx only 2 Bottles x 90 Capsules PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Carton
PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Label - 025-06 DISPENSE THE ENCLOSED MEDICATION GUIDE TO EACH PATIENT NDC 70255-025-06 BRAFTOVI ® (encorafenib) capsules 75 mg Rx only 60 Capsules Sample– Not For Sale PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Label - 025-06
PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Label - 025-05 DISPENSE THE ENCLOSED MEDICATION GUIDE TO EACH PATIENT NDC 70255-025-05 BRAFTOVI ® (encorafenib) capsules 75 mg Rx only 90 Capsules Sample– Not For Sale PRINCIPAL DISPLAY PANEL - 75 mg Capsule Bottle Label - 025-05
Medicaid utilization by pack size
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |