
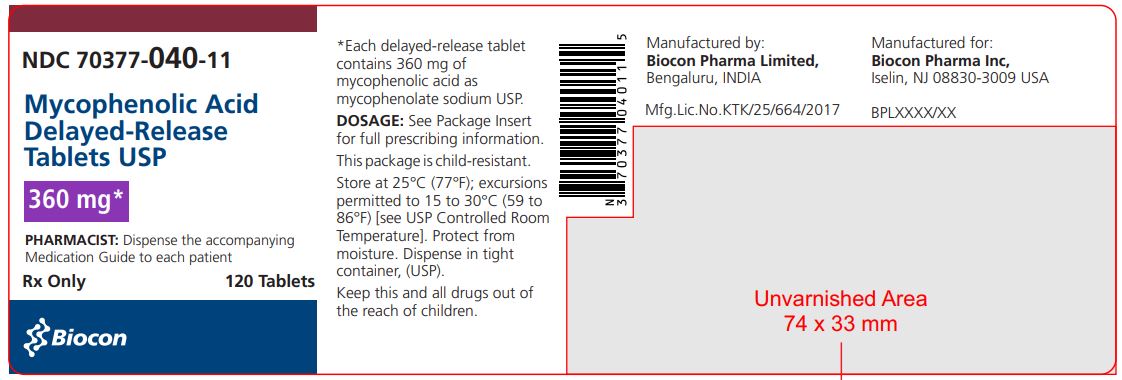
Mycophenolic Acid 360 mg Tablet, Delayed Release, 120-count
Other active recalls for Mycophenolic Acid (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Antimetabolite Immunosuppressant class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Mycophenolate is used to prevent transplant organ rejection (attack of the new organ by the immune system) in people who have received kidney, heart, or liver transplants. Mycophenolate is in a class of medications called immunosuppressive agents. It works by weakening the body's immune system so it will not attack and reject the transplanted organ.
Read the full MedlinePlus article ↗- The enteric coating on the tablet is designed to release the medicine in your intestine, not your stomach. Food doesn't block absorption entirely, but it delays and lowers the peak...
- Why do I have to take this on an empty stomach? What happens if I take it with food?
- Not on your own — and probably not without careful planning. Even though both medicines work the same way, mycophenolic acid delayed-release tablets and MMF are absorbed at differe...
- Can I ever switch to the mycophenolate mofetil (MMF) pill instead?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Mycophenolic Acid — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 40UAA97IT9
Crospovidone is a synthetic polymer derived from povidone. It absorbs liquid quickly and swells, helping tablets and capsules break apart and dissolve faster in your stomach.
-
UNII 1K09F3G675
Ferric oxide red is an inorganic iron compound used as a colorant in medicines. It gives tablets, capsules, or other dosage forms a red or reddish tint for identification and appearance.
-
UNII EX438O2MRT
Ferric oxide yellow is a naturally occurring iron compound used as a colorant in medications. It gives tablets, capsules, and other forms a yellow or golden hue for identification and appearance.
-
UNII 87Y6436BKR
Hypromellose phthalate is a plant-derived polymer that forms a protective coating around pills and capsules. It dissolves in the intestines rather than the stomach, helping deliver the medicine to the right place for absorption.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.227 | $27.18 / 120 tablets |
| Medicaid paysCMS SDUD · 12 mo | $0.8170 | $98.04 / 120 tablets |
| Medicare drug plans payPart D · Q2 2026 | $1.35 | $162.13 / 120 tablets |
| Medicare Part B allowsASP · J7518 | $0.325 / J7518 unit | — |
Where does this data come from?
🧾 Billing & reimbursement
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Mycophenolic Acid 360 mg 00904-6786-04 | Major | 1 tablet | $0.226 | AB | Availability likely | — |
| Mycophenolic Acid 360 mg 16729-0189-29 | Accord | 120 tablets | $0.226 | AB | Availability likely | — |
| mycophenolic acid 360 mg 24979-0161-44 | Upsher-Smith | 120 tablets | $0.226 | — | Availability likely | — |
| Mycophenolic Acid 360 mg 59651-0622-08 | Aurobindo | 120 tablets | $0.226 | AB | Availability likely | — |
| Mycophenolic Acid 360 mg 60505-2966-07 | Apotex | 120 tablets | $0.226 | AB | Availability likely | — |
| Mycophenolic Acid 360 mg 68084-0918-25 | American | 1 tablet | $0.226 | AB | Availability likely | — |
| Mycophenolic Acid 360 mgthis 70377-0040-11 | Biocon | 120 tablets | $0.226 | AB | Availability likely | — |
| Mycophenolic Acid 360 mg 70377-0127-11 | Biocon | 120 tablets | $0.226 | AB | Availability likely | — |
| Mycophenolic Acid 360 mg 72819-0156-08 | Archis | 120 tablets | $0.226 | — | Availability likely | — |
| mycophenolic acid 360 mg 72888-0200-12 | Advagen | 120 tablets | $0.226 | AB | Availability likely | — |
| Mycophenolic Acid 360 mg 70436-0173-23 | Slate | 120 tablets | $0.237 | AB | Availability likely | +5% |
| Myfortic 360 mg 00078-0386-66 | Novartis | 120 tablets | $14.934 | AB | Availability likely | +6494% |
| Mycophenolic Acid 360 mg 00904-7372-04 | Major | 1 tablet | — | AB | FDA listed | — |
| Mycophenolic Acid 360 mg 50090-6492-00 | A-S | 180 tablets | — | AB | FDA listed | — |
| Mycophenolic Acid 360 mg 60429-0017-12 | Golden | 120 tablets | — | AB | FDA listed | — |
| Mycophenolic Acid 360 mg 67877-0427-05 | Ascend | 500 tablets | — | AB | FDA listed | — |
| Mycophenolic Acid 360 mg 67877-0929-05 | Ascend | 500 tablets | — | AB | FDA listed | — |
| mycophenolic acid 360 mg 68254-5002-01 | CONCORD | 120 tablets | — | AB | FDA listed | — |
| Mycophenolic Acid 360 mg 70518-4391-00 | REMEDYREPACK | 1 tablet | — | AB | FDA listed | — |
| mycophenolic acid 360 mg 72789-0246-98 | PD-Rx | 120 tablets | — | — | FDA listed | — |
| Mycophenolic Acid 360 mg 82293-0013-10 | Novugen | 120 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70377-0040-11 You're viewing this | 120 TABLET, DELAYED RELEASE in 1 BOTTLE (70377-040-11) | 2022-05-30 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: EMBRYO-FETAL TOXICITY, MALIGNANCIES, AND SERIOUS INFECTIONS Use during pregnancy is associated with increased risks of pregnancy loss and congenital malformations. Avoid if safer treatment options are available. Females of reproductive potential must be counseled regarding pregnancy prevention and planning [see Warnings and Precautions ( 5.1 ), Use in Specific Populations ( 8.1 , 8.3 )].
Only physicians experienced in immunosuppressive therapy and management of organ transplant patients should prescribe mycophenolic acid delayed-release tablets. Patients receiving mycophenolic acid delayed-release tablets should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources. The physician responsible for maintenance therapy should have complete information requisite for the follow-up of the patient [see Warnings and Precautions ( 5.2 )].
Increased risk of development of lymphoma and other malignancies, particularly of the skin, due to immunosuppression [see Warnings and Precautions ( 5.3 )]. Increased susceptibility to bacterial, viral, fungal, and protozoal infections, including opportunistic infections [see Warnings and Precautions ( 5.4 , 5.5 )]. WARNING: EMBRYO-FETAL TOXICITY, MALIGNANCIES, and SERIOUS INFECTIONS See full prescribing information for complete boxed warning Use during pregnancy is associated with increased risks of pregnancy loss and congenital malformations.
Avoid if safer treatment options are available. Females of reproductive potential must be counseled regarding pregnancy prevention and planning. ( 5.1 , 8.1, 8.3 ) Only physicians experienced in immunosuppressive therapy and management of organ transplant patients should prescribe mycophenolic acid delayed-release tablets.
( 5.2 ) Increased risk of development of lymphoma and other malignancies, particularly of the skin, due to immunosuppression. ( 5.3 ) Increased susceptibility to bacterial, viral, fungal, and protozoal infections, including opportunistic infections. ( 5.4 , 5.5 )
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Mycophenolic acid delayed-release tablets are antimetabolite immunosuppressant indicated for prophylaxis of organ rejection in adult patients receiving kidney transplants and in pediatric patients at least 5 years of age and older who are at least 6 months post kidney transplant. ( 1.1 ) Use in combination with cyclosporine and corticosteroids. ( 1.1 ) Limitations of Use: Mycophenolic acid delayed-release tablets and mycophenolate mofetil tablets and capsules should not be used interchangeably.
( 1.2 )
1.1Prophylaxis of Organ Rejection in Kidney Transplant Mycophenolic acid delayed-release tablets are indicated for the prophylaxis of organ rejection in adult patients receiving a kidney transplant. Mycophenolic acid delayed-release tablets are indicated for the prophylaxis of organ rejection in pediatric patients 5 years of age and older who are at least 6 months post kidney transplant. Mycophenolic acid delayed-release tablets are to be used in combination with cyclosporine and corticosteroids.
1.2Limitations of Use Mycophenolic acid delayed-release tablets and mycophenolate mofetil (MMF) tablets and capsules should not be used interchangeably without physician supervision because the rate of absorption following the administration of these two products is not equivalent.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION In adults: 720 mg by mouth, twice daily (1,440 mg total daily dose) on an empty stomach, 1 hour before or 2 hours after food intake. ( 2.1 ) In children: 5 years of age and older (who are at least 6 months post kidney transplant), 400 mg/m 2 by mouth, twice daily (up to a maximum of 720 mg twice daily). ( 2.2 ) Do not crush, chew, or cut tablet prior to ingestion. ( 2.3 )
2.1Dosage in Adult Kidney Transplant Patients The recommended dose of mycophenolic acid delayed-release tablets is 720 mg administered twice daily (1,440 mg total daily dose).
2.2Dosage in Pediatric Kidney Transplant Patients The recommended dose of mycophenolic acid delayed-release tablets in conversion (at least 6 months post-transplant) pediatric patients age 5 years and older is 400 mg/m 2 body surface area (BSA) administered twice daily (up to a maximum dose of 720 mg administered twice daily).
2.3Administration Mycophenolic acid delayed-release tablets should be taken on an empty stomach, 1 hour before or 2 hours after food intake [see Clinical Pharmacology ( 12.3 )]. Mycophenolic acid delayed-release tablets should not be crushed, chewed, or cut prior to ingesting. The tablets should be swallowed whole in order to maintain the integrity of the enteric coating.
Pediatric patients with a BSA of 1.19 m 2 to 1.58 m 2 may be dosed either with three mycophenolic acid delayed-release tablets 180 mg, or one 180 mg tablet plus one 360 mg tablet twice daily (1,080 mg daily dose). Patients with a BSA of > 1.58 m 2 may be dosed either with four mycophenolic acid delayed-release tablets 180 mg, or two mycophenolic acid delayed-release tablets 360 mg, twice daily (1,440 mg daily dose). Pediatric doses for patients with BSA < 1.19 m 2 cannot be accurately administered using currently available formulations of mycophenolic acid delayed-release tablets.
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Mycophenolic Acid Delayed-Release Tablets, USP are available as 360 mg and 180 mg tablets. Table 1: Description of Mycophenolic Acid Delayed-Release Tablets, USP Dosage Strength 360 mg tablet 180 mg tablet Active ingredient mycophenolic acid as mycophenolate sodium, USP mycophenolic acid as mycophenolate sodium, USP Appearance Pale orange-red, oval shaped, biconvex coated tablets Lime green colored, round shaped bevelled edged, coated tablets Imprint Debossed with “B360” on one side and plain on other side Debossed with “B180” on one side and plain on other side Mycophenolic acid delayed-release are available as 180 mg and 360 mg tablets.
( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Mycophenolic acid delayed-release tablets is contraindicated in patients with a history of hypersensitivity, including anaphylaxis, to mycophenolate sodium, mycophenolic acid (MPA), mycophenolate mofetil, or to any of its excipients. [see Warnings and Precautions ( 5.9 ), Adverse Reactions ( 6.2 )] . History of hypersensitivity, including anaphylaxis, to mycophenolate sodium, mycophenolic acid (MPA), mycophenolate mofetil, or to any of its excipients. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS New or Reactivated Viral Infections: Consider reducing immunosuppression. ( 5.5 ) Blood Dyscrasias, including Pure Red Cell Aplasia (PRCA): Monitor for neutropenia or anemia; consider treatment interruption or dose reduction. ( 5.6 ) Serious GI Tract Complications (gastrointestinal bleeding, perforations and ulcers): Administer with caution to patients with active digestive system disease.
( 5.7 ) Hypersensitivity Reactions: Discontinue Mycophenolic acid delayed-release tablets; treat and monitor until signs and symptoms resolve. ( 5.9 ) Immunizations: Avoid live attenuated vaccines. ( 5.10 ) Patients with Hereditary Deficiency of Hypoxanthine-guanine Phosphoribosyl-transferase (HGPRT): May cause exacerbation of disease symptoms; avoid use.
( 5.11 ) Blood Donation: Avoid during therapy and for 6 weeks thereafter. ( 5.12 ) Semen Donation: Avoid during therapy and for 90 days thereafter. ( 5.13 )
5.1Embryo-Fetal Toxicity Use of mycophenolic acid delayed-release tablets during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of congenital malformations, especially external ear and other facial abnormalities, including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney, and nervous system. Females of reproductive potential must be aware of these risks and must be counseled regarding pregnancy prevention and planning. Avoid use of mycophenolic acid delayed-release tablets during pregnancy if safer treatment options are available [see Use in Specific Populations ( 8.1 , 8.3 )] .
5.2Management of Immunosuppression Only physicians experienced in immunosuppressive therapy and management of organ transplant patients should prescribe mycophenolic acid delayed-release tablets. Patients receiving the drug should be managed in facilities equipped and staffed with adequate laboratory and supportive medical resources. The physicians responsible for maintenance therapy should have complete information requisite for the follow-up of the patient [see Boxed Warning ] .
5.3Lymphoma and Other Malignancies Patients receiving immunosuppressants, including mycophenolic acid delayed-release tablets, are at increased risk of developing lymphomas and other malignancies, particularly of the skin [see Adverse Reactions ( 6 )] . The risk appears to be related to the intensity and duration of immunosuppression rather than to the use of any specific agent. As usual for patients with increased risk for skin cancer, exposure to sunlight and UV light should be limited by wearing protective clothing and using a broad-spectrum sunscreen with a high protection factor.
Post-transplant lymphoproliferative disorder (PTLD) has been reported in immunosuppressed organ transplant recipients. The majority of PTLD events appear related to Epstein-Barr Virus (EBV) infection. The risk of PTLD appears greatest in those individuals who are EBV seronegative, a population which includes many young children.
5.4Serious Infections Patients receiving immunosuppressants, including mycophenolic acid delayed-release tablets, are at increased risk of developing bacterial, viral, fungal, and protozoal infections, and new or reactivated viral infections, including opportunistic infections [see Warnings and Precautions ( 5.5 )] . These infections may lead to serious, including fatal outcomes. Because of the danger of oversuppression of the immune system which can increase susceptibility to infection, combination immunosuppressant therapy should be used with caution.
5.5New or Reactivated Viral Infections Polyomavirus associated nephropathy (PVAN), JC virus-associated progressive multifocal leukoencephalopathy (PML), cytomegalovirus (CMV) infections, reactivation of hepatitis B (HBV) or hepatitis C (HCV), SARS-CoV-2 infection, have been reported in patients treated with immunosuppressants, including MPA derivatives mycophenolic acid delayed-release tablets and MMF. Reduction…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are discussed in greater detail in other sections of the label. Embryo-Fetal Toxicity [see Boxed Warning, Warnings and Precautions ( 5.1 )] Lymphomas and Other Malignancies [see Boxed Warning, Warnings and Precautions ( 5.3 )] Serious Infections [see Boxed Warning, Warnings and Precautions ( 5.4 )] New or Reactivated Viral Infections [see Warnings and Precautions ( 5.5 )] Blood Dyscrasias, Including Pure Red Cell Aplasia [see Warnings and Precautions ( 5.6 )] Serious GI Tract Complications [see Warnings and Precautions ( 5.7 )] Acute Inflammatory Syndrome Associated with Mycophenolate Products [see Warnings and Precautions ( 5.8 )] Hypersensitivity Reactions [see Warnings and Precautions ( 5.9 )] Rare Hereditary Deficiencies [see Warnings and Precautions ( 5.11 )] Most common adverse reactions (≥ 20%): anemia, leukopenia, constipation, nausea, diarrhea, vomiting, dyspepsia, urinary tract infection, CMV infection, insomnia, and postoperative pain.
( 6.2 ) To report SUSPECTED ADVERSE REACTIONS, contact Biocon Pharma Inc., at 1-866-924-6266 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. The data described below derive from two randomized, comparative, active-controlled, double-blind, double-dummy trials in prevention of acute rejection in de novo and converted stable kidney transplant patients. In the de novo trial, patients were administered either mycophenolic acid delayed-release tablets 1.44 grams per day (N = 213) or MMF 2 grams per day (N = 210) within 48 hours post-transplant for 12 months in combination with cyclosporine, USP MODIFIED and corticosteroids.
Forty-one percent of patients also received antibody therapy as induction treatment. In the conversion trial, renal transplant patients who were at least 6 months post-transplant and receiving 2 grams per day MMF in combination with cyclosporine USP MODIFIED, with or without corticosteroids for at least two weeks prior to entry in the trial were randomized to mycophenolic acid delayed-release tablets 1.44 grams per day (N = 159) or MMF 2 grams per day (N = 163) for 12 months. The average age of patients in both studies was 47 years and 48 years ( de novo study and conversion study, respectively), ranging from 22 to 75 years.
Approximately 66% of patients were male; 82% were white, 12% were black, and 6% other races. About 40% of patients were from the United States and 60% from other countries. In the de novo trial, the overall incidence of discontinuation due to adverse reactions was 18% (39/213) and 17% (35/210) in the mycophenolic acid delayed-release tablets and MMF arms, respectively.
The most common adverse reactions leading to discontinuation in the mycophenolic acid delayed-release tablets arm were graft loss (2%), diarrhea (2%), vomiting (1%), renal impairment (1%), CMV infection (1%), and leukopenia (1%). The overall incidence of patients reporting dose reduction at least once during the 0- to 12-month study period was 59% and 60% in the mycophenolic acid delayed-release tablets and MMF arms, respectively. The most frequent reasons for dose reduction in the mycophenolic acid delayed-release tablets arm were adverse reactions (44%), dose reductions according to protocol guidelines (17%), dosing errors (11%) and missing data (2%).
The most common adverse reactions (≥ 20%) associated with the administration of mycophenolic acid delayed-release tablets were anemia, leukopenia, constipation, nausea, diarrhea, vomiting, dyspepsia, urinary tract infection, CMV infection, insomnia, and postoperative pain. The adverse reactions reported in ≥ 10% of patients in the de novo trial are presented in Table 2 below. Table 2: Adverse…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Antacids with Magnesium and Aluminum Hydroxides: Decreases concentrations of MPA; concomitant use is not recommended. ( 7.1 ) Azathioprine: Competition for purine metabolism; concomitant administration is not recommended. ( 7.2 ) Cholestyramine, Bile Acid Sequestrates, Oral Activated Charcoal, and Other Drugs that Interfere with Enterohepatic Recirculation: May decrease MPA concentrations; concomitant use is not recommended.
( 7.3 ) Sevelamer: May decrease MPA concentrations; concomitant use is not recommended. ( 7.4 ) Cyclosporine: May decrease MPA concentrations; exercise caution when switching from cyclosporine to other drugs or from other drugs to cyclosporine. ( 7.5 ) Norfloxacin and Metronidazole: May decrease MPA concentrations; concomitant use with both drugs is not recommended.
( 7.6 ) Rifampin: May decrease MPA concentrations; concomitant use is not recommended unless the benefit outweighs the risk. ( 7.7 ) Hormonal Contraceptives: May reduce the effectiveness of oral contraceptives. Additional barrier contraceptive methods must be used.
( 5.2 , 7.8 ) Acyclovir, Valacyclovir, Ganciclovir, Valganciclovir, and Other Drugs that Undergo Renal Tubular Secretion: May increase concentrations of mycophenolic acid glucuronide (MPAG) and coadministered drug; monitor blood cell counts. ( 7.9 )
7.1Antacids With Magnesium and Aluminum Hydroxides Concomitant use of mycophenolic acid delayed-release tablets and antacids decreased plasma concentrations of mycophenolic acid (MPA). It is recommended that mycophenolic acid delayed-release tablets and antacids not be administered simultaneously [see Clinical Pharmacology ( 12.3 )] .
7.2Azathioprine Given that azathioprine and MMF inhibit purine metabolism, it is recommended that mycophenolic acid delayed-release tablets not be administered concomitantly with azathioprine or MMF.
7.3Cholestyramine, Bile Acid Sequestrates, Oral Activated Charcoal and Other Drugs That Interfere With Enterohepatic Recirculation Drugs that interrupt enterohepatic recirculation may decrease MPA plasma concentrations when coadministered with MMF. Therefore, do not administer mycophenolic acid delayed-release tablets with cholestyramine or other agents that may interfere with enterohepatic recirculation or drugs that may bind bile acids, e.g., bile acid sequestrates or oral activated charcoal, because of the potential to reduce the efficacy of mycophenolic acid delayed-release tablets [see Clinical Pharmacology ( 12.3 )] .
7.4Sevelamer Concomitant administration of sevelamer and MMF may decrease MPA plasma concentrations. Sevelamer and other calcium-free phosphate binders should not be administered simultaneously with mycophenolic acid delayed-release tablets [see Clinical Pharmacology ( 12.3 )] .
7.5Cyclosporine Cyclosporine inhibits the enterohepatic recirculation of MPA, and therefore, MPA plasma concentrations may be decreased when mycophenolic acid delayed-release tablets are coadministered with cyclosporine. Clinicians should be aware that there is also a potential change of MPA plasma concentrations after switching from cyclosporine to other immunosuppressive drugs or from other immunosuppressive drugs to cyclosporine in patients concomitantly receiving mycophenolic acid delayed-release tablets [see Clinical Pharmacology ( 12.3 )] .
7.6Norfloxacin and Metronidazole MPA plasma concentrations may be decreased when MMF is administrated with norfloxacin and metronidazole. Therefore, mycophenolic acid delayed-release tablets are not recommended to be given with the combination of norfloxacin and metronidazole. Although there will be no effect on MPA plasma concentrations when mycophenolic acid delayed-release tablets are concomitantly administered with norfloxacin or metronidazole when given separately [see Clinical Pharmacology ( 12.3 )] .
7.7Rifampin The concomitant administration of MMF and rifampin may decrease MPA plasma concentrations. Therefore, mycophenolic acid delayed-rele…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Male Patients: Sexually active male patients and/or their female partners are recommended to use effective contraception during treatment of the male patient and for at least 90 days after cessation of treatment. ( 8.3 )
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to mycophenolate during pregnancy and those becoming pregnant within 6 weeks of discontinuing mycophenolic acid delayed-release tablets treatment. To report a pregnancy or obtain information about the registry, visit www.mycophenolateREMS.com or call 1-800-617-8191. Risk Summary Following oral or intravenous (IV) administration, MMF is metabolized to mycophenolic acid (MPA), the active ingredient in mycophenolic acid delayed-release tablets and the active form of the drug.
Use of MMF during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of multiple congenital malformations in multiple organ systems (see Human Data). Oral administration of mycophenolate to rats and rabbits during the period of organogenesis produced congenital malformations and pregnancy loss at doses less than the recommended clinical dose (0.05 and 1.1 times exposure at the recommended clinical doses in kidney transplant patients for rats and rabbits, respectively) (see Animal Data) .
Risks and benefits of mycophenolic acid delayed-release tablets should be discussed with the patient. When appropriate, consider alternative immunosuppressants with less potential for embryo-fetal toxicity. The estimated background risk of pregnancy loss and congenital malformations in organ transplant populations is not clear.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data A spectrum of congenital malformations (including multiple malformations in individual newborns) has been reported in 23% to 27% of live births in MMF exposed pregnancies, based on published data from pregnancy registries. Malformations that have been documented include external ear, eye, and other facial abnormalities, including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney, and nervous system.
Based on published data from pregnancy registries, the risk of first trimester pregnancy loss has been reported at 45% to 49% following MMF exposure. Animal Data In animal reproductive toxicology studies, congenital malformations and pregnancy loss occurred when pregnant rats and rabbits received mycophenolate at dose multiples equivalent to and less than the recommended human dose. Oral administration of mycophenolate sodium to pregnant rats from Gestational Day 7 to Day 16 at a dose as low as 1 mg per kg resulted in malformations including anophthalmia, exencephaly, and umbilical hernia.
The systemic exposure at this dose represents 0.05 times the clinical exposure at the human dose of 1,440 mg per day of mycophenolic acid delayed-release tablets. Oral administration of mycophenolate to pregnant rabbits from Gestational Day 7 to Day 19 resulted in embryofetal lethality and malformations, including ectopia cordis, ectopic kidneys, diaphragmatic hernia, and umbilical hernia at doses equal to or greater than 80 mg per kg per day, in the absence of maternal toxicity. This corresponds to about 1.1 times the recommended clinical dose based on BSA.
8.2Lactation Risk Summary There are no data on the presence of mycophenolate in human milk, or the effects on milk production. There are limited data in the National Transplantation Pregnancy Registry on the effects of mycophenolate on a breastfed child (see Data) . Studies in rats treated with MMF have shown mycophenolic acid to be present in milk.
Because available data are limited, it is not possible to exclude potential risks to a breastfeeding infant. The develo…
🤰 Pregnancy ▾
8.1Pregnancy Pregnancy Exposure Registry There is a pregnancy exposure registry that monitors pregnancy outcomes in women exposed to mycophenolate during pregnancy and those becoming pregnant within 6 weeks of discontinuing mycophenolic acid delayed-release tablets treatment. To report a pregnancy or obtain information about the registry, visit www.mycophenolateREMS.com or call 1-800-617-8191. Risk Summary Following oral or intravenous (IV) administration, MMF is metabolized to mycophenolic acid (MPA), the active ingredient in mycophenolic acid delayed-release tablets and the active form of the drug.
Use of MMF during pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of multiple congenital malformations in multiple organ systems (see Human Data). Oral administration of mycophenolate to rats and rabbits during the period of organogenesis produced congenital malformations and pregnancy loss at doses less than the recommended clinical dose (0.05 and 1.1 times exposure at the recommended clinical doses in kidney transplant patients for rats and rabbits, respectively) (see Animal Data) .
Risks and benefits of mycophenolic acid delayed-release tablets should be discussed with the patient. When appropriate, consider alternative immunosuppressants with less potential for embryo-fetal toxicity. The estimated background risk of pregnancy loss and congenital malformations in organ transplant populations is not clear.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Data Human Data A spectrum of congenital malformations (including multiple malformations in individual newborns) has been reported in 23% to 27% of live births in MMF exposed pregnancies, based on published data from pregnancy registries. Malformations that have been documented include external ear, eye, and other facial abnormalities, including cleft lip and palate, and anomalies of the distal limbs, heart, esophagus, kidney, and nervous system.
Based on published data from pregnancy registries, the risk of first trimester pregnancy loss has been reported at 45% to 49% following MMF exposure. Animal Data In animal reproductive toxicology studies, congenital malformations and pregnancy loss occurred when pregnant rats and rabbits received mycophenolate at dose multiples equivalent to and less than the recommended human dose. Oral administration of mycophenolate sodium to pregnant rats from Gestational Day 7 to Day 16 at a dose as low as 1 mg per kg resulted in malformations including anophthalmia, exencephaly, and umbilical hernia.
The systemic exposure at this dose represents 0.05 times the clinical exposure at the human dose of 1,440 mg per day of mycophenolic acid delayed-release tablets. Oral administration of mycophenolate to pregnant rabbits from Gestational Day 7 to Day 19 resulted in embryofetal lethality and malformations, including ectopia cordis, ectopic kidneys, diaphragmatic hernia, and umbilical hernia at doses equal to or greater than 80 mg per kg per day, in the absence of maternal toxicity. This corresponds to about 1.1 times the recommended clinical dose based on BSA.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of mycophenolic acid delayed-release tablets have been established in pediatric kidney transplant patients 5 to 16 years of age who were initiated on mycophenolic acid delayed-release tablets at least 6 months post-transplant. Use of mycophenolic acid delayed-release tablets in this age group is supported by evidence from adequate and well-controlled studies of mycophenolic acid delayed-release tablets in a similar population of adult kidney transplant patients with additional pharmacokinetic data in pediatric kidney transplant patients [see Dosage and Administration ( 2.2 , 2.3 ), Clinical Pharmacology ( 12.3 )] .
Pediatric doses for patients with BSA < 1.19 m 2 cannot be accurately administered using currently available formulations of mycophenolic acid delayed-release tablets. The safety and effectiveness of mycophenolic acid delayed-release tablets in de novo pediatric kidney transplant patients and in pediatric kidney transplant patients below the age of 5 years have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of mycophenolic acid delayed-release tablets did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Of the 372 patients treated with mycophenolic acid delayed-release tablets in the clinical trials, 6% (N = 21) were 65 years of age and older and 0.3% (N = 1) were 75 years of age and older. Other reported clinical experience has not identified differences in responses between the elderly and younger patients.
In general, dose selection for an elderly patient should be cautious, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
10 OVERDOSAGE Signs and Symptoms There have been anecdotal reports of deliberate or accidental overdoses with mycophenolic acid delayed-release tablets, whereas not all patients experienced related adverse reactions. In those overdose cases in which adverse reactions were reported, the reactions fall within the known safety profile of the class. Accordingly, an overdose of mycophenolic acid delayed-release tablets could possibly result in oversuppression of the immune system and may increase the susceptibility to infection, including opportunistic infections, fatal infections and sepsis.
If blood dyscrasias occur (e.g., neutropenia with absolute neutrophil count < 1.5 x 10 3 /mcL or anemia), it may be appropriate to interrupt or discontinue mycophenolic acid delayed-release tablets. Possible signs and symptoms of acute overdose could include the following: hematological abnormalities, such as leukopenia and neutropenia, and gastrointestinal symptoms, such as abdominal pain, diarrhea, nausea and vomiting, and dyspepsia. Treatment and Management General supportive measures and symptomatic treatment should be followed in all cases of overdosage.
Although dialysis may be used to remove the inactive metabolite mycophenolic acid glucuronide (MPAG), it would not be expected to remove clinically significant amounts of the active moiety, mycophenolic acid, due to the 98% plasma protein binding of mycophenolic acid. By interfering with enterohepatic circulation of mycophenolic acid, activated charcoal or bile sequestrates, such as cholestyramine, may reduce the systemic mycophenolic acid exposure.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Mycophenolic acid (MPA), an immunosuppressant, is an uncompetitive and reversible inhibitor of inosine monophosphate dehydrogenase (IMPDH), and therefore inhibits the de novo pathway of guanosine nucleotide synthesis without incorporation to DNA. T- and B-lymphocytes are critically dependent for their proliferation on de novo synthesis of purines, whereas other cell types can utilize salvage pathways. MPA has cytostatic effects on lymphocytes.
Mycophenolate sodium has been shown to prevent the occurrence of acute rejection in rat models of kidney and heart allotransplantation. Mycophenolate sodium also decreases antibody production in mice.
12.3Pharmacokinetics Mycophenolic acid delayed-release tablets exhibit linear and dose-proportional pharmacokinetics over the dose-range (360 mg to 2,160 mg) evaluated. The absolute bioavailability of mycophenolic acid delayed-release tablets in stable renal transplant patients on cyclosporine was 72%. MPA is highly protein bound (> 98% bound to albumin).
The predominant metabolite of MPA is the phenolic glucuronide (MPAG) which is pharmacologically inactive. A minor metabolite AcMPAG which is an acyl glucuronide of MPAG is also formed and has pharmacological activity comparable to MPA. MPAG undergoes renal elimination.
A fraction of MPAG also undergoes biliary excretion, followed by deconjugation by gut flora and subsequent reabsorption as MPA. The mean elimination half-lives of MPA and MPAG ranged between 8 and 16 hours, and 13 and 17 hours, respectively. Absorption In vitro studies demonstrated that the enteric-coated mycophenolic acid delayed-release tablet does not release MPA under acidic conditions (pH < 5) as in the stomach but is highly soluble in neutral pH conditions as in the intestine.
Following mycophenolic acid delayed-release tablets oral administration without food in several pharmacokinetic studies conducted in renal transplant patients, consistent with its enteric-coated formulation, the median delay (T lag ) in the rise of MPA concentration ranged between 0.25 and 1.25 hours and the median time to maximum concentration (T max ) of MPA ranged between 1.5 and 2.75 hours. In comparison, following the administration of MMF, the median T max ranged between 0.5 and 1.0 hours. In stable renal transplant patients on cyclosporine, USP MODIFIED based immunosuppression, gastrointestinal absorption and absolute bioavailability of MPA following the administration of mycophenolic acid delayed-release tablet was 93% and 72%, respectively.
Mycophenolic acid delayed-release tablets pharmacokinetics is dose proportional over the dose range of 360 mg to 2,160 mg. Distribution The mean (± SD) volume of distribution at steady state and elimination phase for MPA is 54 (± 25) L and 112 (± 48) L, respectively. MPA is highly protein bound to albumin, > 98%.
The protein binding of MPAG is 82%. The free MPA concentration may increase under conditions of decreased protein binding (uremia, hepatic failure, and hypoalbuminemia). Metabolism MPA is metabolized principally by glucuronyl transferase to glucuronidated metabolites.
The phenolic glucuronide of MPA, MPAG, is the predominant metabolite of MPA and does not manifest pharmacological activity. The acyl glucuronide is a minor metabolite and has comparable pharmacological activity to MPA. In stable renal transplant patients on cyclosporine, USP MODIFIED based immunosuppression, approximately 28% of the oral mycophenolic acid delayed-release tablets dose was converted to MPAG by presystemic metabolism.
The AUC ratio of MPA:MPAG:acyl glucuronide is approximately 1:24:0.28 at steady state. The mean clearance of MPA was 140 (± 30) mL/min. Elimination The majority of MPA dose administered is eliminated in the urine primarily as MPAG (> 60%) and approximately 3% as unchanged MPA following mycophenolic acid delayed-release tablets administration to stable renal transplant patients.
The mean renal clearanc…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Mycophenolic acid (MPA), an immunosuppressant, is an uncompetitive and reversible inhibitor of inosine monophosphate dehydrogenase (IMPDH), and therefore inhibits the de novo pathway of guanosine nucleotide synthesis without incorporation to DNA. T- and B-lymphocytes are critically dependent for their proliferation on de novo synthesis of purines, whereas other cell types can utilize salvage pathways. MPA has cytostatic effects on lymphocytes.
Mycophenolate sodium has been shown to prevent the occurrence of acute rejection in rat models of kidney and heart allotransplantation. Mycophenolate sodium also decreases antibody production in mice.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Mycophenolic Acid Delayed-Release Tablets, USP are available containing mycophenolate sodium, USP equivalent to 180 mg or 360 mg of mycophenolic acid. 360 mg tablet: Pale orange-red, oval shaped biconvex coated tablets free from physical defects, debossed with “B360” on one side and plain on other side. Bottles of 120 tablets with child-resistant closure…NDC 70377-040-11 180 mg tablet: Lime green, round shaped beveled edged coated tablets free from physical defects, debossed with “B180” on one side and plain on other.
Bottles of 120 tablets with child-resistant closure…NDC 70377-039-11 Storage Store at 25°C (77°F); excursions permitted to 15 to 30°C (59 to 86°F) [see USP Controlled Room Temperature]. Protect from moisture. Dispense in a tight container (USP).
Handling Keep out of reach and sight of children. Mycophenolic acid delayed-release tablets should not be crushed or cut in order to maintain the integrity of the enteric coating [see Dosage and Administration ( 2.3 )] . Teratogenic effects have been observed with mycophenolate sodium [see Warnings and Precautions ( 5.1 )] .
If for any reason the mycophenolic acid delayed-release tablets must be crushed, avoid inhalation of the powder, or direct contact of the powder, with skin or mucous membranes.
📋 Description ▾
11 DESCRIPTION Mycophenolic acid delayed-release tablets, USP are enteric formulation of mycophenolate sodium that delivers the active moiety mycophenolic acid (MPA). Mycophenolic acid is an immunosuppressive agent. As the sodium salt, MPA is chemically designated as (E)-6-(4-hydroxy-6-methoxy-7-methyl-3-oxo-1,3-dihydroisobenzofuran-5-yl)-4-methylhex-4-enoic acid sodium salt.
Its empirical formula is C 17 H 19 O 6 Na. The molecular weight is 342.32 g/mol and the structural formula is: Mycophenolic acid, as the sodium salt (mycophenolate sodium, USP), is a white to off-white, crystalline powder and is highly soluble in aqueous media at physiological pH and practically insoluble in 0.1N hydrochloric acid. Mycophenolic acid is available for oral use as delayed-release tablets containing either 180 mg or 360 mg of mycophenolic acid.
Inactive ingredients include colloidal silicon dioxide, crospovidone, lactose anhydrous, magnesium stearate, maize starch and povidone (K-30). The enteric coating of the tablet consists of FD & C Blue No. 2 Aluminum Lake (180 mg), ferric oxide red (360 mg), ferric oxide yellow, hypromellose phthalate and titanium dioxide.
Contains no ingredient made from a gluten-containing grain (wheat, barley, or rye). Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling ( Medication Guide ). Embryo-Fetal Toxicity Pregnancy loss and malformations Inform pregnant women and females of reproductive potential that use of mycophenolic acid delayed-release tablets in pregnancy is associated with an increased risk of first trimester pregnancy loss and an increased risk of congenital malformations. Advise patients that they must use an acceptable form of contraception [see Warnings and Precautions ( 5.1 ), Use in Specific Populations ( 8.1 , 8.3 )] .
Encourage pregnant women to enroll in the Mycophenolate Pregnancy Registry (1-800-617-8191). This registry monitors pregnancy outcomes in women exposed to mycophenolate [see Use in Specific Populations ( 8.1 )] . Contraception Discuss pregnancy testing, pregnancy prevention and planning with females of reproductive potential [see Use in Specific Populations ( 8.3 )].
Females of reproductive potential must use acceptable form of birth control during the entire mycophenolic acid delayed-release tablets therapy and for 6 weeks after stopping mycophenolic acid delayed-release tablets, unless the patient chooses to avoid heterosexual sexual intercourse completely (abstinence). Mycophenolic acid delayed-release tablets may reduce effectiveness of oral contraceptives. Use of additional barrier contraceptive methods is recommended [see Use in Specific Populations ( 8.3 )].
For patients who are considering pregnancy, discuss appropriate alternative immunosuppressants with less potential for embryo-fetal toxicity. Risks and benefits of mycophenolic acid delayed-release tablets should be discussed with the patient [see Use in Specific Populations ( 8.3 )]. Advise sexually active male patients and/or their partners to use effective contraception during the treatment of the male patient and for at least 90 days after cessation of treatment.
This recommendation is based on findings of animal studies. Development of Lymphoma and Other Malignancies Inform patients they are at increased risk of developing lymphomas and other malignancies, particularly of the skin, due to immunosuppression [see Warnings and Precautions ( 5.3 )] . Advise patients to limit exposure to sunlight and ultraviolet (UV) light by wearing protective clothing and use a broad-spectrum sunscreen with a high protection factor [see Warnings and Precautions ( 5.3 )] .
Increased Risk of Infection Inform patients they are at increased risk of developing a variety of infections, including opportunistic infections, due to immunosuppression and to contact their physician if they develop any symptoms of infection as explained in the Medication Guide [see Warnings and Precautions ( 5.4 , 5.5 )] . Blood Dyscrasias Inform patients they are at increased risk for developing blood dyscrasias (e.g., neutropenia or anemia) and to immediately contact their healthcare provider if they experience any evidence of infection, unexpected bruising, bleeding, or any other manifestation of bone marrow suppression [see Warnings and Precautions ( 5.6 )] .
Gastrointestinal Tract Complications Inform patients that mycophenolic acid delayed-release tablets can cause gastrointestinal tract complications, including bleeding, intestinal perforations, and gastric or duodenal ulcers. Advise the patient to contact their healthcare provider if they have symptoms of gastrointestinal bleeding or sudden onset or persistent abdominal pain [see Warnings and Precautions ( 5.7 )] . Acute Inflammatory Syndrome Inform patients that acute inflammatory reactions have been reported in some patients who received mycophenolate products.
Some reactions were severe, requiring hospitalization. Advise patients to contact their physician if they develop fever, joint stiffness, joint pain or muscle pains [see Warnings and Precautions ( 5.8 )] . Hypersensitivity Reactions Inform patients of the potential risk of hypersensitivity reactions.
Advise patients to stop taki…
💬 Medication Guide ▾
MEDICATION GUIDE Mycophenolic Acid * (mye′′ koe fe nol′ ik as′ id) Delayed-Release Tablets, USP * as Mycophenolate sodium Read the Medication Guide that comes with mycophenolic acid delayed-release tablets before you start taking it and each time you get a refill. There may be new information. This Medication Guide does not take the place of talking with your healthcare provider about your medical condition or treatment.
If you have any questions about mycophenolic acid delayed-release tablets, ask your doctor. What is the most important information I should know about mycophenolic acid delayed-release tablets? Mycophenolic acid delayed-release tablets can cause serious side effects, including: Increased risk of loss of pregnancy (miscarriage) and higher risk of birth defects.
Females who take mycophenolic acid delayed-release tablets during pregnancy, have a higher risk of miscarriage during the first 3 months (first trimester), and a higher risk that their baby will be born with birth defects. Ο If you are a female who can become pregnant: your doctor must talk with you about acceptable birth control methods (contraceptive counseling) while taking mycophenolic acid delayed-release tablets. you should have a pregnancy test immediately before starting mycophenolic acid delayed-release tablets and another pregnancy test 8 to 10 days later.
Pregnancy tests should be repeated during routine follow-up visits with your doctor. Talk to your doctor about the results of all of your pregnancy tests. you must use acceptable birth control during your entire mycophenolic acid delayed-release tablets therapy and for 6 weeks after stopping mycophenolic acid delayed-release tablets, unless at any time you choose to avoid sexual intercourse (abstinence) with a man completely. Mycophenolic acid delayed-release tablets decrease blood levels of the hormones in birth control pills that you take by mouth.
Birth control pills may not work as well while you take mycophenolic acid delayed-release tablets and you could become pregnant. If you decide to take birth control pills while using mycophenolic acid delayed-release tablets, you must also use another form of birth control. Talk to your doctor about other birth control methods that can be used while taking mycophenolic acid delayed-release tablets. Ο If you are a sexually active male whose female partner can become pregnant, use effective contraception while you are taking mycophenolic acid delayed-release tablets and for at least 90 days after stopping mycophenolic acid delayed-release tablets.
If you plan to become pregnant, talk with your doctor. Your doctor will decide if other medicines to prevent rejection may be right for you. If you become pregnant while taking mycophenolic acid delayed-release tablets, do not stop taking mycophenolic acid delayed-release tablets.
Call your doctor right away. You and your doctor may decide that other medicines to prevent rejection may be right for you. You and your doctor should report your pregnancy to Mycophenolate Pregnancy Registry (1-800-617-8191) The purpose of this registry is to gather information about the health of your baby.
Increased risk of getting serious infections. Mycophenolic acid delayed-release tablets weaken the body’s immune system and affects your ability to fight infections. Serious infections can happen with mycophenolic acid delayed-release tablets and can lead to death.
These serious infections can include: Ο Viral infections . Certain viruses can live in your body and cause active infections when your immune system is weak. Viral infections that can happen with mycophenolic acid delayed-release tablets include: Shingles, other herpes infections, and cytomegalovirus (CMV).
CMV can cause serious tissue and blood infections. BK virus. BK virus can affect how your kidney works and cause your transplanted kidney to fail.
Hepatitis B and C viruses. Hepatitis viruses can affect how your liver works. Talk to your doctor about how hepat…