
LANOXIN digoxin 100 ug/mL Injection, Solution, 10 vials — NDC 70515-263-10 (Billing 70515-0263-10)
This is a package of 10 vials of LANOXIN digoxin 100 ug/mL Injection, Solution from Covis Pharma US, Inc, marketed since Oct 2019 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 70515-263-10 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 70515 labeler · 263 product · 10 package
- Package marketed since
- Oct 29, 2019
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 7051526310 9
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 080552
- GCN: 47431
- GPI-14 (Medi-Span): 31200010002005
- HICL (First Databank): 000004
- AHFS class code: 24:04.08.00
- RxCUI (RxNorm): 104208
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Cardiac Glycoside class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats mild to moderate heart failure in adults and helps control the heart rate in chronic atrial fibrillation. It is also used in children with heart failure. It can ease symp...
- Take it exactly as your prescriber directs, at about the same time each day. Tablets can be taken with or after meals, but try to be consistent. Avoid high-bran meals around your d...
- Nausea, vomiting, loss of appetite, diarrhea, dizziness, headache and tiredness are among the more common ones. Call me or your doctor if you notice vision changes like blurred or...
- Many medicines interact with digoxin. Heart rhythm drugs, some antibiotics and antacids are common examples, and St. John’s Wort can lower digoxin levels. Always check with me befo...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Digoxin — tap one for details:
Digoxin may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J1160 | $3.911 / J1160 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 8, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Oct 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 70515-0263-10 You're viewing this Main listing | 10 VIAL in 1 BOX / 1 mL in 1 VIAL | 2019-10-29 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Lanoxin 100 ug/mLthis 70515-0263-10 | Covis | 10 vials | — | AP | FDA listed | — |
| Lanoxin 100 ug/mL 70515-0262-10 | Covis | 10 ampules | — | AP | Discontinued | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
The FDA lists approved generic versions of this medicine, but that does not always mean a pharmacy can get one today. Patent rules, launch agreements, supply and pricing can affect when generics actually arrive.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Digoxin inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3K9958V90M
A liquid solvent derived from fermentation or chemical synthesis. In medicines, alcohol dissolves active ingredients, helps preserve the product, and improves how the body absorbs certain drugs.
-
UNII XF417D3PSL
Anhydrous citric acid is a sour, crystalline powder derived from citric acid with water removed. In medicines, it acts as a buffer to control pH, adds tartness to improve taste, and helps tablets disintegrate.
-
UNII 6DC9Q167V3
Propylene glycol is a clear liquid derived from petroleum or vegetable sources. It acts as a solvent, humectant, and preservative in medicines, helping dissolve active ingredients and maintain product stability.
-
UNII GR686LBA74
Sodium phosphate, dibasic is a salt derived from phosphoric acid. It acts as a buffer to help maintain the medicine's pH balance and may serve as a binder or filler in tablets and capsules.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Covis Pharma US, Inc labeler code 70515
- Duaklir Pressair aclidinium bromide and formoterol fumarate 400 ug; 12 ug Powder, Metered NDC 70515-001-01
- Tudorza Pressair aclidinium bromide 400 ug Powder, Metered NDC 70515-002-01
- LANOXIN digoxin 250 ug/mL Injection, Solution NDC 70515-260-10
- LANOXIN digoxin 250 ug/mL Injection, Solution NDC 70515-261-10
- LANOXIN digoxin 100 ug/mL Injection, Solution NDC 70515-262-10
- Sular nisoldipine 8.5 mg Tablet, Film Coated, Extended Release NDC 70515-500-10
- Sular nisoldipine 17 mg Tablet, Film Coated, Extended Release NDC 70515-501-10
- Sular nisoldipine 34 mg Tablet, Film Coated, Extended Release NDC 70515-503-10
- Zanaflex tizanidine hydrochloride 4 mg Tablet NDC 70515-594-15
- Zanaflex tizanidine hydrochloride 2 mg Capsule NDC 70515-602-15
- Zanaflex tizanidine hydrochloride 4 mg Capsule NDC 70515-604-15
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE LANOXIN is a cardiac glycoside indicated for: Treatment of mild to moderate heart failure in adults. ( 1.1 ) Increasing myocardial contractility in pediatric patients with heart failure. ( 1.2 ) Control of resting ventricular rate in adults with chronic atrial fibrillation. ( 1.3 )
1.1Heart Failure in Adults LANOXIN is indicated for the treatment of mild to moderate heart failure in adults. LANOXIN increases left ventricular ejection fraction and improves heart failure symptoms, as evidenced by improved exercise capacity and decreased heart failure-related hospitalizations and emergency care, while having no effect on mortality. Where possible, LANOXIN should be used in combination with a diuretic and an angiotensin-converting enzyme (ACE) inhibitor.
1.2Heart Failure in Pediatric Patients LANOXIN increases myocardial contractility in pediatric patients with heart failure.
1.3Atrial Fibrillation in Adults LANOXIN is indicated for the control of ventricular response rate in adult patients with chronic atrial fibrillation.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION LANOXIN dose is based on patient-specific factors (age, lean body weight, renal function, etc.). See full prescribing information. Monitor for toxicity and therapeutic effect. ( 2 ) Intravenous administration is preferable to intramuscular. Avoid bolus administration. ( 2 )
2.1Important Dosing and Administration Information In selecting a LANOXIN dosing regimen, it is important to consider factors that affect digoxin blood levels (e.g., body weight, age, renal function, concomitant drugs) since toxic levels of digoxin are only slightly higher than therapeutic levels. Dosing can be either initiated with a loading dose followed by maintenance dosing if rapid titration is desired or initiated with maintenance dosing without a loading dose. Parenteral administration of digoxin should be used only when the need for rapid digitalization is urgent or when the drug cannot be taken orally.
Intramuscular injection can lead to severe pain at the injection site, thus intravenous administration is preferred. If the drug must be administered by the intramuscular route, it should be injected deep into the muscle followed by massage. For adults, no more than 500 mcg of LANOXIN Injection should be injected into a single site.
For pediatric patients, no more than 200 mcg of LANOXIN Injection Pediatric should be injected into a single site. Administer the dose over a period of 5 minutes or longer and avoid bolus administration to prevent systemic and coronary vasoconstriction. Mixing of LANOXIN Injection and Injection Pediatric with other drugs in the same container or simultaneous administration in the same intravenous line is not recommended.
LANOXIN Injection and Injection Pediatric can be administered undiluted or diluted with a 4-fold or greater volume of Sterile Water for Injection, 0.9% Sodium Chloride Injection, or 5% Dextrose Injection. The use of less than a 4-fold volume of diluent could lead to precipitation of the digoxin. Immediate use of the diluted product is recommended.
Consider interruption or reduction in LANOXIN dose prior to electrical cardioversion [see Warnings and Precautions ( 5.4 )]. Discard unused portion of LANOXIN Injection and LANOXIN Injection Pediatric.
2.2Loading Dosing Regimen in Adults and Pediatric Patients Table 1. Recommended LANOXIN Injection Loading Dose mcg = microgram Age Total IV Loading Dose (mcg/kg) Administer half the total loading dose initially, then ¼ the loading dose every 6-8 hours twice Premature 15-25 Full-Term 20-30 1-24 Months 30-50 2-5 Years 25-35 5-10 Years 15-30 Adults and pediatric patients over 10 years 8-12
2.3Maintenance Dosing in Adults and Pediatric Patients Over 10 Years Old The maintenance dose is based on lean body weight, renal function, age, and concomitant products [see Clinical Pharmacology ( 12.3 )] . The recommended starting maintenance doses in adults and pediatric patients over 10 years old with normal renal function are given in Table 2 . Doses may be increased every 2 weeks according to clinical response, serum drug levels, and toxicity.
Table 2. Recommended Starting LANOXIN Injection Maintenance Dosage in Adults and Pediatric Patients Over 10 Years Old mcg = microgram Age Total Intravenous Maintenance Dose, mcg/kg/day (given once daily) Adults and pediatric patients over 10 years 2.4-3.6 Table 3 provides the recommended (once daily) maintenance dose for adults and pediatric patients over 10 years old (to be given once daily) according to lean body weight and renal function. The doses are based on studies in adult patients with heart failure.
Alternatively, the maintenance dose may be estimated by the following formula (peak body stores lost each day through elimination): Total Maintenance Dose = Loading Dose (i.e., Peak Body Stores) x % Daily Loss/100 (% Daily Loss = 14 + Creatinine clearance/5) Reduce the dose of LANOXIN in patients whose lean weight is an abnormally small fraction of their total body mass because of obesity or edema. T… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS LANOXIN Injection: 500 mcg/2 mL (250 mcg/mL) single-dose ampule. LANOXIN Injection: 500 mcg/2 mL (250 mcg/ mL) single-dose vial. LANOXIN Injection Pediatric: 100 mcg/mL single-dose ampule.
LANOXIN Injection Pediatric: 100 mcg/mL single-dose vial. LANOXIN ® Injection: 500 mcg/2 mL (250 mcg/mL) single-dose ampule ( 3 ) LANOXIN ® Injection:500 mcg/2 mL (250 mcg/mL) single-dose vial ( 3 ) LANOXIN ® Injection Pediatric: 100 mcg/mL single-dose ampule ( 3 ) LANOXIN ® Injection Pediatric: 100 mcg/mL single-dose vial ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS LANOXIN is contraindicated in patients with: Ventricular fibrillation [see Warnings and Precautions ( 5.1 )] Known hypersensitivity to digoxin (reactions seen include unexplained rash, swelling of the mouth, lips or throat or a difficulty in breathing). A hypersensitivity reaction to other digitalis preparations usually constitutes a contraindication to digoxin. Ventricular fibrillation.
( 4 ) Known hypersensitivity to digoxin or other forms of digitalis. ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of rapid ventricular response leading to ventricular fibrillation in patients with AV accessory pathway. ( 5.1 ) Risk of advanced or complete heart block in patients with sinus node disease and AV block. ( 5.2 ) Digoxin toxicity: Indicated by nausea, vomiting, visual disturbances, and cardiac arrhythmias.
Advanced age, low body weight, impaired renal function and electrolyte abnormalities predispose to toxicity. ( 5.3 ) Risk of ventricular arrhythmias during electrical cardioversion. ( 5.4 ) Not recommended in patients with acute myocardial infarction ( 5.5 ) Avoid LANOXIN in patients with myocarditis.
( 5.6 )
5.1Ventricular Fibrillation in Patients With Accessory AV Pathway (Wolff-Parkinson-White Syndrome) Patients with Wolff-Parkinson-White syndrome who develop atrial fibrillation are at high risk of ventricular fibrillation. Treatment of these patients with digoxin leads to greater slowing of conduction in the atrioventricular node than in accessory pathways, and the risks of rapid ventricular response leading to ventricular fibrillation are thereby increased.
5.2Sinus Bradycardia and Sino-atrial Block LANOXIN may cause severe sinus bradycardia or sinoatrial block particularly in patients with pre-existing sinus node disease and may cause advanced or complete heart block in patients with pre-existing incomplete AV block. Consider insertion of a pacemaker before treatment with digoxin.
5.3Digoxin Toxicity Signs and symptoms of digoxin toxicity include anorexia, nausea, vomiting, visual changes and cardiac arrhythmias [first-degree, second-degree (Wenckebach), or third-degree heart block (including asystole); atrial tachycardia with block; AV dissociation; accelerated junctional (nodal) rhythm; unifocal or multiform ventricular premature contractions (especially bigeminy or trigeminy); ventricular tachycardia; and ventricular fibrillation]. Toxicity is usually associated with digoxin levels greater than 2 ng/mL although symptoms may also occur at lower levels.
Low body weight, advanced age or impaired renal function, hypokalemia, hypercalcemia, or hypomagnesemia may predispose to digoxin toxicity. Obtain serum digoxin levels in patients with signs or symptoms of digoxin therapy and interrupt or adjust dose if necessary [see Adverse Reactions ( 6 ) and Overdosage ( 10 )]. Assess serum electrolytes and renal function periodically.
The earliest and most frequent manifestation of digoxin toxicity in infants and children is the appearance of cardiac arrhythmias, including sinus bradycardia. In children, the use of digoxin may produce any arrhythmia. The most common are conduction disturbances or supraventricular tachyarrhythmias, such as atrial tachycardia (with or without block) and junctional (nodal) tachycardia.
Ventricular arrhythmias are less common. Sinus bradycardia may be a sign of impending digoxin intoxication, especially in infants, even in the absence of first-degree heart block. Any arrhythmias or alteration in cardiac conduction that develops in a child taking digoxin should initially be assumed to be a consequence of digoxin intoxication.
Given that adult patients with heart failure have some symptoms in common with digoxin toxicity, it may be difficult to distinguish digoxin toxicity from heart failure. Misidentification of their etiology might lead the clinician to continue or increase LANOXIN dosing, when dosing should actually be suspended. When the etiology of these signs and symptoms is not clear, measure serum digoxin levels.
5.4Risk of Ventricular Arrhythmias During Electrical Cardioversion It may be desirable to reduce the dose of or discontinue LANOXIN for 1-2 days prior to electrical cardioversion of atrial fibrillation to avoid the induction of ventricular arrhythmias, but physicians must consider the consequences of increasing the ventricular response if digoxin is decreased or withdrawn. If digitalis toxicity is suspected, elective cardioversion should be delayed. If… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following adverse reactions are included in more detail in the Warnings and Precautions section of the label: Cardiac arrhythmias [see Warnings and Precautions ( 5.1 , 5.2 )] Digoxin Toxicity [see Warnings and Precautions ( 5.3 )] The overall incidence of adverse reactions with digoxin has been reported as 5-20%, with 15-20% of adverse events considered serious. Cardiac toxicity accounts for about one-half, gastrointestinal disturbances for about one-fourth, and CNS and other toxicity for about one-fourth of these adverse events.
( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Covis Pharma at 1-877-411-2510 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. In general, the adverse reactions of LANOXIN are dose-dependent and occur at doses higher than those needed to achieve a therapeutic effect. Hence, adverse reactions are less common when LANOXIN is used within the recommended dose range, is maintained within the therapeutic serum concentration range, and when there is careful attention to concurrent medications and conditions.
In the DIG trial (a trial investigating the effect of digoxin on mortality and morbidity in patients with heart failure), the incidence of hospitalization for suspected digoxin toxicity was 2% in patients taking LANOXIN compared to 0.9% in patients taking placebo [see Clinical Studies ( 14.1 )] . The overall incidence of adverse reactions with digoxin has been reported as 5-20%, with 15-20% of adverse events considered serious. Cardiac toxicity accounts for about one-half, gastrointestinal disturbances for about one-fourth, and CNS and other toxicity for about one-fourth of these adverse events.
Gastrointestinal: In addition to nausea and vomiting, the use of digoxin has been associated with abdominal pain, intestinal ischemia, and hemorrhagic necrosis of the intestines. CNS: Digoxin can cause headache, weakness, dizziness, apathy, confusion, and mental disturbances (such as anxiety, depression, delirium, and hallucination). Other: Gynecomastia has been occasionally observed following the prolonged use of digoxin.
Thrombocytopenia and maculopapular rash and other skin reactions have been rarely observed.
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Digoxin has a narrow therapeutic index, increased monitoring of serum digoxin concentrations and for potential signs and symptoms of clinical toxicity is necessary when initiating, adjusting, or discontinuing drugs that may interact with digoxin. Prescribers should consult the prescribing information of any drug which is co-prescribed with digoxin for potential drug interaction information. PGP Inducers/Inhibitors: Drugs that induce or inhibit PGP have the potential to alter digoxin pharmacokinetics.
( 7.1 ) The potential for drug-drug interactions must be considered prior to and during drug therapy. See full prescribing information. ( 7.2 , 7.3 , 12.3 )
7.1P-Glycoprotein (PGP) Inducers/Inhibitors Digoxin is a substrate of P-glycoprotein, at the level of intestinal absorption, renal tubular section and biliary-intestinal secretion. Therefore, drugs that induce/ inhibit P-glycoprotein have the potential to alter digoxin pharmacokinetics.
7.2Pharmacokinetic Drug Interactions Pharmacokinetic interactions have been observed and reported primarily when digoxin is co-administered by oral route. There are very few studies that have evaluated the drug interaction when digoxin is administered via IV route. The magnitude of digoxin exposure change through IV route is generally lower than that through oral route.
Table below provides available interaction data using digoxin IV formulation (NA means not available). Digoxin concentrations increased greater than 50% Digoxin Serum Concentration Increase Digoxin AUC Increase Recommendations Quinidine NA 54-83% Measure serum digoxin concentrations before initiating concomitant drugs. Reduce digoxin concentrations by decreasing dose by approximately 30-50% or by modifying the dosing frequency and continue monitoring.
Ritonavir NA 86% Digoxin concentrations increased less than 50% Amiodarone 17% 40% Measure serum digoxin concentrations before initiating concomitant drugs. Reduce digoxin concentrations by decreasing the dose by approximately 15-30% or by modifying the dosing frequency and continue monitoring. Propafenone 28% 29% Quinine NA 34-38% Spironolactone NA 44% Verapamil NA 24% Mirabegron 29% 27%
7.3Potentially Significant Pharmacodynamic Drug Interactions Because of considerable variability of pharmacodynamic interactions, the dosage of digoxin should be individualized when patients receive these medications concurrently. Drugs that Affect Renal Function A decline in GFR or tubular secretion, as from ACE inhibitors, angiotensin receptor blockers, nonsteroidal anti-inflammatory drugs [NSAIDs], COX-2 inhibitors may impair the excretion of digoxin. Antiarrthymics Dofetilide Concomitant administration with digoxin was associated with a higher rate of torsades de pointes.
Sotalol Proarrhythmic events were more common in patients receiving sotalol and digoxin than on either alone; it is not clear whether this represents an interaction or is related to the presence of CHF, a known risk factor for proarrhythmia, in patients receiving digoxin. Dronedarone Sudden death was more common in patients receiving digoxin with dronedarone than on either alone; it is not clear whether this represents an interaction or is related to the presence of advanced heart disease, a known risk factor for sudden death in patients receiving digoxin.
Parathyroid Hormone Analog Teriparatide Sporadic case reports have suggested that hypercalcemia may predispose patients to digitalis toxicity. Teriparatide transiently increases serum calcium. Thyroid supplement Thyroid Treatment of hypothyroidism in patients taking digoxin may increase the dose requirements of digoxin.
Sympathomimetics Epinephrine Norepinephrine Dopamine Can increase the risk of cardiac arrhythmias. Neuromuscular Blocking Agents Succinylcholine May cause sudden extrusion of potassium from muscle cells, causing arrhythmias in patients taking digoxin. Supplements Calcium If administered rapidly by intravenous route, can produce serious… [Excerpted — this section continues on DailyMed.]
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pediatric patients: Newborn infants display variability in tolerance to LANOXIN. ( 8.4 ) Geriatric patients: Consider renal function in dosage selection, and carefully monitor for side effects. ( 8.5 ) Renal impairment: LANOXIN is excreted by the kidneys. Consider renal function during dosage selection. ( 8.6 )
8.1Pregnancy Risk Summary Experience with digoxin in pregnant women over several decades, based on published retrospective clinical studies and case reports, has not led to the identification of a drug associated risk of major birth defects, miscarriage or adverse maternal and fetal outcomes. Untreated underlying maternal conditions, such as heart failure and atrial fibrillation, during pregnancy pose a risk to the mother and fetus (see Clinical Consideration) . Animal reproduction studies have not been conducted with digoxin.
The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Pregnant women with heart failure are at increased risk for preterm birth. Clinical classification of heart disease may worsen with pregnancy and lead to maternal or fetal death. Pregnant women with atrial fibrillation are at an increased risk of delivering a low birth weight infant.
Atrial fibrillation may worsen with pregnancy and can lead to maternal or fetal death. Fetal/neonatal adverse reactions Digoxin has been shown to cross the placenta and is found in amniotic fluid. Monitor neonates for signs and symptoms of digoxin toxicity, including vomiting, and cardiac arrhythmias [see Warnings and Precautions (5.3)] .
Dose adjustments during pregnancy and the postpartum period LANOXIN requirements may increase during pregnancy and decrease in the postpartum period. Monitor serum digoxin levels during pregnancy and the postpartum period [see Dosage and Administration (2.5)] . Labor or Delivery Risk of arrhythmias may increase during the labor and delivery.
Monitor patients continuously during labor and delivery [see Warnings and Precautions (5.1 and 5.2)] .
8.2Lactation Risk Summary The digoxin dose received through breastfeeding is up to 4% of the neonatal maintenance dosage, which is unlikely to be clinically relevant. There are no data on the effects of digoxin on the breastfed infant or the effects on milk production. Data Based on data from two lactation studies in a total of 13 breastfed infants, the digoxin concentrations in breast milk were between 0.4 – 1.0 ng/mL following 0.25 mg once daily dose of digoxin in the lactating mother.
Thus, the amount of digoxin ingested daily by the infants is estimated to be between 0.03 to 0.16 mcg/kg/day. This translates to a relative infant dose of digoxin between 1 to 7% of the maternal weight-adjusted dose and about 0.2 to 4% of the neonatal maintenance dose.
8.4Pediatric Use The safety and effectiveness of LANOXIN in the control of ventricular rate in children with atrial fibrillation have not been established. The safety and effectiveness of LANOXIN in the treatment of heart failure in children have not been established in adequate and well-controlled studies. However, in published literature of children with heart failure of various etiologies (e.g., ventricular septal defects, anthracycline toxicity, patent ductus arteriosus), treatment with digoxin has been associated with improvements in hemodynamic parameters and in clinical signs and symptoms.
Newborn infants display considerable variability in their tolerance to digoxin. Premature and immature infants are particularly sensitive to the effects of digoxin, and the dosage of the drug must not only be reduced but must be… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Experience with digoxin in pregnant women over several decades, based on published retrospective clinical studies and case reports, has not led to the identification of a drug associated risk of major birth defects, miscarriage or adverse maternal and fetal outcomes. Untreated underlying maternal conditions, such as heart failure and atrial fibrillation, during pregnancy pose a risk to the mother and fetus (see Clinical Consideration) . Animal reproduction studies have not been conducted with digoxin.
The estimated background risk of major birth defects and miscarriage for the indicated population(s) are unknown. All pregnancies have a background risk of birth defect, loss, or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Pregnant women with heart failure are at increased risk for preterm birth. Clinical classification of heart disease may worsen with pregnancy and lead to maternal or fetal death. Pregnant women with atrial fibrillation are at an increased risk of delivering a low birth weight infant.
Atrial fibrillation may worsen with pregnancy and can lead to maternal or fetal death. Fetal/neonatal adverse reactions Digoxin has been shown to cross the placenta and is found in amniotic fluid. Monitor neonates for signs and symptoms of digoxin toxicity, including vomiting, and cardiac arrhythmias [see Warnings and Precautions (5.3)] .
Dose adjustments during pregnancy and the postpartum period LANOXIN requirements may increase during pregnancy and decrease in the postpartum period. Monitor serum digoxin levels during pregnancy and the postpartum period [see Dosage and Administration (2.5)] . Labor or Delivery Risk of arrhythmias may increase during the labor and delivery.
Monitor patients continuously during labor and delivery [see Warnings and Precautions (5.1 and 5.2)] .
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of LANOXIN in the control of ventricular rate in children with atrial fibrillation have not been established. The safety and effectiveness of LANOXIN in the treatment of heart failure in children have not been established in adequate and well-controlled studies. However, in published literature of children with heart failure of various etiologies (e.g., ventricular septal defects, anthracycline toxicity, patent ductus arteriosus), treatment with digoxin has been associated with improvements in hemodynamic parameters and in clinical signs and symptoms.
Newborn infants display considerable variability in their tolerance to digoxin. Premature and immature infants are particularly sensitive to the effects of digoxin, and the dosage of the drug must not only be reduced but must be individualized according to their degree of maturity.
🧓 Geriatric Use ▾
8.5Geriatric Use The majority of clinical experience gained with digoxin has been in the elderly population. This experience has not identified differences in response or adverse effects between the elderly and younger patients. However, this drug is known to be substantially excreted by the kidney, and the risk of toxic reactions to this drug may be greater in patients with impaired renal function.
Because elderly patients are more likely to have decreased renal function, care should be taken in dose selection, which should be based on renal function, and it may be useful to monitor renal function [see Dosage and Administration ( 2.1 )] .
🆘 Overdosage ▾
10 OVERDOSAGE
10.1Signs and Symptoms in Adults and Children The signs and symptoms of toxicity are generally similar to those previously described [see Adverse Reactions ( 6.1 )] but may be more frequent and can be more severe. Signs and symptoms of digoxin toxicity become more frequent with levels above 2 ng/mL. However, in deciding whether a patient’s symptoms are due to digoxin, the clinical state together with serum electrolyte levels and thyroid function are important factors [see Dosage and Administration ( 2 )] .
Adults: The most common signs and symptoms of digoxin toxicity are nausea, vomiting, anorexia, and fatigue that occur in 30-70% of patients who are overdosed. Extremely high serum concentrations produce hyperkalemia especially in patients with impaired renal function. Almost every type of cardiac arrhythmia has been associated with digoxin overdose and multiple rhythm disturbances in the same patient are common.
Peak cardiac effects occur 3-6 hours following ingestion and may persist for 24 hours or longer. Arrhythmias that are considered more characteristic of digoxin toxicity are new-onset Mobitz type 1 A-V block, accelerated junctional rhythms, non-paroxysmal atrial tachycardia with A-V block, and bi-directional ventricular tachycardia. Cardiac arrest from asystole or ventricular fibrillation is usually fatal.
Digoxin toxicity is related to serum concentration. As digoxin serum levels increase above 1.2 ng/mL, there is a potential for increase in adverse reactions. Furthermore, lower potassium levels increases the risk for adverse reactions.
In adults with heart disease, clinical observations suggest that an overdose of digoxin of 10-15 mg results in death of half of patients. A dose above 25 mg ingested by an adult without heart disease appeared to be uniformly fatal if no Digoxin Immune Fab (DIGIBIND®, DIGIFAB®) was administered. Among the extra-cardiac manifestations, gastrointestinal symptoms (e.g., nausea, vomiting, anorexia) are very common (up to 80% incidence) and precede cardiac manifestations in approximately half of the patients in most literature reports.
Neurologic manifestations (e.g., dizziness, various CNS disturbances), fatigue, and malaise are very common. Visual manifestations may also occur with aberration in color vision (predominance of yellow green) the most frequent. Neurological and visual symptoms may persist after other signs of toxicity have resolved.
In chronic toxicity, nonspecific extra-cardiac symptoms, such as malaise and weakness, may predominate. Children: In pediatric patients, signs and symptoms of toxicity can occur during or shortly after the dose of digoxin. Frequent non-cardiac effects are similar to those observed in adults although nausea and vomiting are not seen frequently in infants and small pediatric patients.
Other reported manifestations of overdose are weight loss in older age groups, failure to thrive in infants, abdominal pain caused by mesenteric artery ischemia, drowsiness, and behavioral disturbances including psychotic episodes. Arrhythmias and combinations of arrhythmias that occur in adult patients can also occur in pediatric patients although sinus tachycardia, supraventricular tachycardia, and rapid atrial fibrillation are seen less frequently in pediatric patients. Pediatric patients are more likely to develop A-V conduction disturbances, or sinus bradycardia.
Any arrhythmia in a child treated with digoxin should be considered related to digoxin until otherwise ruled out. In pediatric patients aged 1-3 years without heart disease, clinical observations suggest that an overdose of digoxin of 6-10 mg would result in death of half of the patients. In the same population, a dose above 10 mg resulted in death if no Digoxin Immune Fab were administered.
10.2Treatment Chronic Overdose If there is suspicion of toxicity, discontinue LANOXIN and place the patient on a cardiac monitor. Correct factors such as electrolyte abnormalities, thyroid dysfunction,… [Excerpted — this section continues on DailyMed.]
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action All of digoxin’s actions are mediated through its effects on Na-K ATPase. This enzyme, the “sodium pump,” is responsible for maintaining the intracellular milieu throughout the body by moving sodium ions out of and potassium ions into cells. By inhibiting Na-K ATPase, digoxin causes increased availability of intracellular calcium in the myocardium and conduction system, with consequent increased inotropy, increased automaticity, and reduced conduction velocity indirectly causes parasympathetic stimulation of the autonomic nervous system, with consequent effects on the sino-atrial (SA) and atrioventricular (AV) nodes reduces catecholamine reuptake at nerve terminals, rendering blood vessels more sensitive to endogenous or exogenous catecholamines increases baroreceptor sensitization, with consequent increased carotid sinus nerve activity and enhanced sympathetic withdrawal for any given increment in mean arterial pressure increases (at higher concentrations) sympathetic outflow from the central nervous system (CNS) to both cardiac and peripheral sympathetic nerves allows (at higher concentrations) progressive efflux of intracellular potassium, with consequent increase in serum potassium levels.
The cardiologic consequences of these direct and indirect effects are an increase in the force and velocity of myocardial systolic contraction (positive inotropic action), a slowing of the heart rate (negative chronotropic effect), decreased conduction velocity through the AV node, and a decrease in the degree of activation of the sympathetic nervous system and renin-angiotensin system (neurohormonal deactivating effect).
12.2Pharmacodynamics The times to onset of pharmacologic effect and to peak effect of preparations of LANOXIN are shown in Table 7 . Table 7. Times to Onset of Pharmacologic Effect and to Peak Effect of Preparations of LANOXIN a Documented for ventricular response rate in atrial fibrillation, inotropic effects and electrocardiographic changes. b Depending upon rate of infusion.
Product Time to Onset of Effect a Time to Peak Effect a LANOXIN Tablets 0.5-2 hours 2-6 hours LANOXIN Injection/IV 5-30 minutes b 1-4 hours Hemodynamic Effects: Short- and long-term therapy with the drug increases cardiac output and lowers pulmonary artery pressure, pulmonary capillary wedge pressure, and systemic vascular resistance in patients with heart failure. These hemodynamic effects are accompanied by an increase in the left ventricular ejection fraction and a decrease in end-systolic and end-diastolic dimensions.
ECG Changes: The use of therapeutic doses of LANOXIN may cause prolongation of the PR interval and depression of the ST segment on the electrocardiogram. LANOXIN may produce false positive ST-T changes on the electrocardiogram during exercise testing. These electrophysiologic effects are not indicative of toxicity.
LANOXIN does not significantly reduce heart rate during exercise.
12.3Pharmacokinetics Note: The following data are from studies performed in adults, unless otherwise stated. Comparisons of the systemic availability and equivalent doses for oral preparations of LANOXIN are shown in Table 6 [see Dosage and Administration ( 2.6 )] . Distribution: Following drug administration, a 6-8 hour tissue distribution phase is observed.
This is followed by a much more gradual decline in the serum concentration of the drug, which is dependent on the elimination of digoxin from the body. The peak height and slope of the early portion (absorption/distribution phases) of the serum concentration-time curve are dependent upon the route of administration and the absorption characteristics of the formulation. Clinical evidence indicates that the early high serum concentrations do not reflect the concentration of digoxin at its site of action, but that with chronic use, the steady-state post-distribution serum concentrations are in equilibrium with tissue concentrations and correlate with… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action All of digoxin’s actions are mediated through its effects on Na-K ATPase. This enzyme, the “sodium pump,” is responsible for maintaining the intracellular milieu throughout the body by moving sodium ions out of and potassium ions into cells. By inhibiting Na-K ATPase, digoxin causes increased availability of intracellular calcium in the myocardium and conduction system, with consequent increased inotropy, increased automaticity, and reduced conduction velocity indirectly causes parasympathetic stimulation of the autonomic nervous system, with consequent effects on the sino-atrial (SA) and atrioventricular (AV) nodes reduces catecholamine reuptake at nerve terminals, rendering blood vessels more sensitive to endogenous or exogenous catecholamines increases baroreceptor sensitization, with consequent increased carotid sinus nerve activity and enhanced sympathetic withdrawal for any given increment in mean arterial pressure increases (at higher concentrations) sympathetic outflow from the central nervous system (CNS) to both cardiac and peripheral sympathetic nerves allows (at higher concentrations) progressive efflux of intracellular potassium, with consequent increase in serum potassium levels.
The cardiologic consequences of these direct and indirect effects are an increase in the force and velocity of myocardial systolic contraction (positive inotropic action), a slowing of the heart rate (negative chronotropic effect), decreased conduction velocity through the AV node, and a decrease in the degree of activation of the sympathetic nervous system and renin-angiotensin system (neurohormonal deactivating effect).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING LANOXIN (digoxin) Injection, 500 mcg/2 mL (250 mcg/mL); box of 10 single-dose ampules (NDC 70515 260 10) LANOXIN (digoxin) Injection, 500 mcg/2 mL (250 mcg/mL); box of 10 single-dose vials (NDC 70515 261 10) LANOXIN (digoxin) Injection Pediatric, 100 mcg/mL; box of 10 single-dose ampules (NDC 70515 262 10) LANOXIN (digoxin) Injection Pediatric, 100 mcg/mL; box of 10 single-dose vials (NDC 70515 263 10) Store at 25 °C (77 °F); excursions permitted to 15 °C to 30 °C (59 °F to 86 °F) [see USP Controlled Room Temperature] and protect from light.
Discard unused portion.
📋 Description ▾
11 DESCRIPTION LANOXIN (digoxin) is one of the cardiac (or digitalis) glycosides, a closely related group of drugs having in common specific effects on the myocardium. These drugs are found in a number of plants. Digoxin is extracted from the leaves of Digitalis lanata .
The term “digitalis” is used to designate the whole group of glycosides. The glycosides are composed of 2 portions: a sugar and a cardenolide (hence “glycosides”). Digoxin is described chemically as (3β,5β,12β)-3-[( O -2,6-dideoxy-β- D-ribo -hexopyranosyl-(1→4)- O -2,6-dideoxy-β- D-ribo -hexopyranosyl-(1→4)-2,6-dideoxy-β- D-ribo -hexopyranosyl)oxy]-12,14-dihydroxy-card-20(22)-enolide.
Its molecular formula is C 41 H 64 O 14 , its molecular weight is 780.95, and its structural formula is: Digoxin exists as odorless white crystals that melt with decomposition above 230°C. The drug is practically insoluble in water and in ether; slightly soluble in diluted (50%) alcohol and in chloroform; and freely soluble in pyridine. LANOXIN Injection and Injection Pediatric are sterile solutions of digoxin for intravenous or intramuscular injection.
The vehicle contains 42.5% (W/V) propylene glycol and 10% alcohol (V/V). The injection is buffered to a pH of 6.8-7.2 with 0.17% dibasic sodium phosphate and 0.08% anhydrous citric acid. Each 2-mL single-dose ampule or vial of LANOXIN Injection contains 500 mcg digoxin (250 mcg/mL).
Dilution is not required. Each 1-mL single-dose ampule or vial of LANOXIN Injection Pediatric contains 100 mcg digoxin (100 mcg/mL). Dilution is not required.
Digoxin Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION •Advise patients to contact their doctor or a health care professional if they experience nausea, vomiting, persistent diarrhea, confusion, weakness, or visual disturbances (including blurred vision, green-yellow color disturbances, halo effect) as these could be signs that the dose of LANOXIN may be too high.•Advise parents or caregivers that the symptoms of having too high LANOXIN doses may be difficult to recognize in infants and pediatric patients. Symptoms such as weight loss, failure to thrive in infants, abdominal pain, and behavioral disturbances may be indications of digoxin toxicity.•Instruct the patient to monitor and record their heart rate and blood pressure daily.
LANOXIN is registered trademark of GlaxoSmithKline. Manufactured for Covis Pharma Zug, 6300 Switzerland 2025, Covis Pharma. All rights reserved.
Covis Logo
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Note: The following data are from studies performed in adults, unless otherwise stated. Comparisons of the systemic availability and equivalent doses for oral preparations of LANOXIN are shown in Table 6 [see Dosage and Administration ( 2.6 )] . Distribution: Following drug administration, a 6-8 hour tissue distribution phase is observed.
This is followed by a much more gradual decline in the serum concentration of the drug, which is dependent on the elimination of digoxin from the body. The peak height and slope of the early portion (absorption/distribution phases) of the serum concentration-time curve are dependent upon the route of administration and the absorption characteristics of the formulation. Clinical evidence indicates that the early high serum concentrations do not reflect the concentration of digoxin at its site of action, but that with chronic use, the steady-state post-distribution serum concentrations are in equilibrium with tissue concentrations and correlate with pharmacologic effects.
In individual patients, these post-distribution serum concentrations may be useful in evaluating therapeutic and toxic effects [see Dosage and Administration ( 2.1 )] . Digoxin is concentrated in tissues and therefore has a large apparent volume of distribution (approximately 475-500 L). Digoxin crosses both the blood-brain barrier and the placenta.
At delivery, the serum digoxin concentration in the newborn is similar to the serum concentration in the mother. Approximately 25% of digoxin in the plasma is bound to protein. Serum digoxin concentrations are not significantly altered by large changes in fat tissue weight, so that its distribution space correlates best with lean (i.e., ideal) body weight, not total body weight.
Metabolism: Only a small percentage (13%) of a dose of digoxin is metabolized in healthy volunteers. The urinary metabolites, which include dihydrodigoxin, digoxigenin bisdigitoxoside, and their glucuronide and sulfate conjugates are polar in nature and are postulated to be formed via hydrolysis, oxidation, and conjugation. The metabolism of digoxin is not dependent upon the cytochrome P-450 system, and digoxin is not known to induce or inhibit the cytochrome P-450 system.
Excretion: Elimination of digoxin follows first-order kinetics (that is, the quantity of digoxin eliminated at any time is proportional to the total body content). Following intravenous administration to healthy volunteers, 50-70% of a digoxin dose is excreted unchanged in the urine. Renal excretion of digoxin is proportional to creatinine clearance and is largely independent of urine flow.
In healthy volunteers with normal renal function, digoxin has a half-life of 1.5-2 days. The half-life in anuric patients is prolonged to 3.5-5 days. Digoxin is not effectively removed from the body by dialysis, exchange transfusion, or during cardiopulmonary bypass because most of the drug is bound to extravascular tissues.
Special Populations: Geriatrics: Because of age-related declines in renal function, elderly patients would be expected to eliminate digoxin more slowly than younger subjects. Elderly patients may also exhibit a lower volume of distribution of digoxin due to age-related loss of lean muscle mass. Thus, the dosage of digoxin should be carefully selected and monitored in elderly patients [see Use in Specific Populations ( 8.5 )] .
Gender: In a study of 184 patients, the clearance of digoxin was 12% lower in female than in male patients. This difference is not likely to be clinically important. Hepatic Impairment: Because only a small percentage (approximately 13%) of a dose of digoxin undergoes metabolism, hepatic impairment would not be expected to significantly alter the pharmacokinetics of digoxin.
In a small study, plasma digoxin concentration profiles in patients with acute hepatitis generally fell within the range of profiles in a group of healthy subjects. No dosage adjustments are recommended for patients… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics The times to onset of pharmacologic effect and to peak effect of preparations of LANOXIN are shown in Table 7 . Table 7. Times to Onset of Pharmacologic Effect and to Peak Effect of Preparations of LANOXIN a Documented for ventricular response rate in atrial fibrillation, inotropic effects and electrocardiographic changes. b Depending upon rate of infusion.
Product Time to Onset of Effect a Time to Peak Effect a LANOXIN Tablets 0.5-2 hours 2-6 hours LANOXIN Injection/IV 5-30 minutes b 1-4 hours Hemodynamic Effects: Short- and long-term therapy with the drug increases cardiac output and lowers pulmonary artery pressure, pulmonary capillary wedge pressure, and systemic vascular resistance in patients with heart failure. These hemodynamic effects are accompanied by an increase in the left ventricular ejection fraction and a decrease in end-systolic and end-diastolic dimensions.
ECG Changes: The use of therapeutic doses of LANOXIN may cause prolongation of the PR interval and depression of the ST segment on the electrocardiogram. LANOXIN may produce false positive ST-T changes on the electrocardiogram during exercise testing. These electrophysiologic effects are not indicative of toxicity.
LANOXIN does not significantly reduce heart rate during exercise.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Chronic Heart Failure Two 12-week, double-blind, placebo-controlled studies enrolled 178 (RADIANCE trial) and 88 (PROVED trial) adult patients with NYHA Class II or III heart failure previously treated with oral digoxin, a diuretic, and an ACE inhibitor (RADIANCE only) and randomized them to placebo or treatment with LANOXIN Tablets. Both trials demonstrated better preservation of exercise capacity in patients randomized to LANOXIN. Continued treatment with LANOXIN reduced the risk of developing worsening heart failure, as evidenced by heart failure-related hospitalizations and emergency care and the need for concomitant heart failure therapy.
DIG Trial of LANOXIN in Patients with Heart Failure The Digitalis Investigation Group (DIG) main trial was a 37-week, multicenter, randomized, double-blind mortality study comparing digoxin to placebo in 6800 adult patients with heart failure and left ventricular ejection fraction less than or equal to 0.45. At randomization, 67% were NYHA class I or II, 71% had heart failure of ischemic etiology, 44% had been receiving digoxin, and most were receiving a concomitant ACE inhibitor (94%) and diuretics (82%). As in the smaller trials described above, patients who had been receiving open-label digoxin were withdrawn from this treatment before randomization.
Randomization to digoxin was again associated with a significant reduction in the incidence of hospitalization, whether scored as number of hospitalizations for heart failure (relative risk 75%), risk of having at least one such hospitalization during the trial (RR 72%), or number of hospitalizations for any cause (RR 94%). On the other hand, randomization to digoxin had no apparent effect on mortality (RR 99%, with confidence limits of 91-107%).
14.2Chronic Atrial Fibrillation Digoxin has also been studied as a means of controlling the ventricular response to chronic atrial fibrillation in adults. Digoxin reduced the resting heart rate, but not the heart rate during exercise. In 3 different randomized, double-blind trials that included a total of 315 adult patients, digoxin was compared to placebo for the conversion of recent-onset atrial fibrillation to sinus rhythm.
Conversion was equally likely, and equally rapid, in the digoxin and placebo groups. In a randomized 120-patient trial comparing digoxin, sotalol, and amiodarone, patients randomized to digoxin had the lowest incidence of conversion to sinus rhythm, and the least satisfactory rate control when conversion did not occur. In at least one study, digoxin was studied as a means of delaying reversion to atrial fibrillation in adult patients with frequent recurrence of this arrhythmia.
This was a randomized, double-blind, 43-patient crossover study. Digoxin increased the mean time between symptomatic recurrent episodes by 54%, but had no effect on the frequency of fibrillatory episodes seen during continuous electrocardiographic monitoring.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Digoxin showed no genotoxic potential in in vitro studies (Ames test and mouse lymphoma). No data are available on the carcinogenic potential of digoxin, nor have studies been conducted to assess its potential to affect fertility.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Digoxin showed no genotoxic potential in in vitro studies (Ames test and mouse lymphoma). No data are available on the carcinogenic potential of digoxin, nor have studies been conducted to assess its potential to affect fertility.
📄 Package Label / Principal Display Panel ▾
PRINCIPAL DISPLAY PANEL - Adult Carton Label - Ampule C O V I S 10 single-dose ampuls 2 mL each NDC 70515-260-10 Discard unused portion LANOXIN ® (digoxin) Injection 500 mcg/2 mL (250 mcg/mL) For intravenous or intramuscular injection. Dilution not required. In a vehicle of 42.5% (W/V) propylene glycol and 10% alcohol (V/V).
Dibasic sodium phosphate 0.17%, citric acid anhydrous 0.08%. See prescribing information for dosage information. Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and protect from light.
Manufactured for Covis Pharma Zug, 6300 Switzerland Made in Germany ©2024, Covis Pharma Rx only Principal Display Panel - Adult Carton Label - Ampule
PRINCIPAL DISPLAY PANEL - Adult Carton Label - Vial C O V I S NDC 70515-261-10 10 single-dose vials 2 mL each Discard unused portion LANOXIN ® (digoxin) Injection 500 mcg/2 mL (250 mcg/mL) For Intravenous or Intramuscular Injection. Dilution not required. Rx only NDC 70515-261-10 LANOXIN ® (digoxin) Injection 500 mcg/2 mL (250 mcg/mL) In a vehicle of 42.5% (W/V) propylene glycol and 10% alcohol (V/V).
Dibasic sodium phosphate 0.17%, citric acid anhydrous 0.08%. See prescribing information for dosage information. Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and protect from light.
Manufactured for Covis Pharma Zug, 6300 Switzerland Made in Germany ©2024, Covis Pharma Principal Display Panel - Adult Carton Label - Vial
PRINCIPAL DISPLAY PANEL - Pediatric Carton Label - Ampule NDC 70515-262-10 10 single-dose ampules 1 mL each – Discard unused portion LANOXIN ® (digoxin) Injection Pediatric 100 mcg/mL For intravenous or intramuscular injection. Dilution not required. In a vehicle of 42.5% (W/V) propylene glycol and 10% alcohol (V/V).
Sodium phosphate 0.17%. Citric acid anhydrous 0.08%. See prescribing information for dosage information.
Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and protect from light. Rx only C O V I S Principal Display Panel - Pediatric Carton Label - Ampule
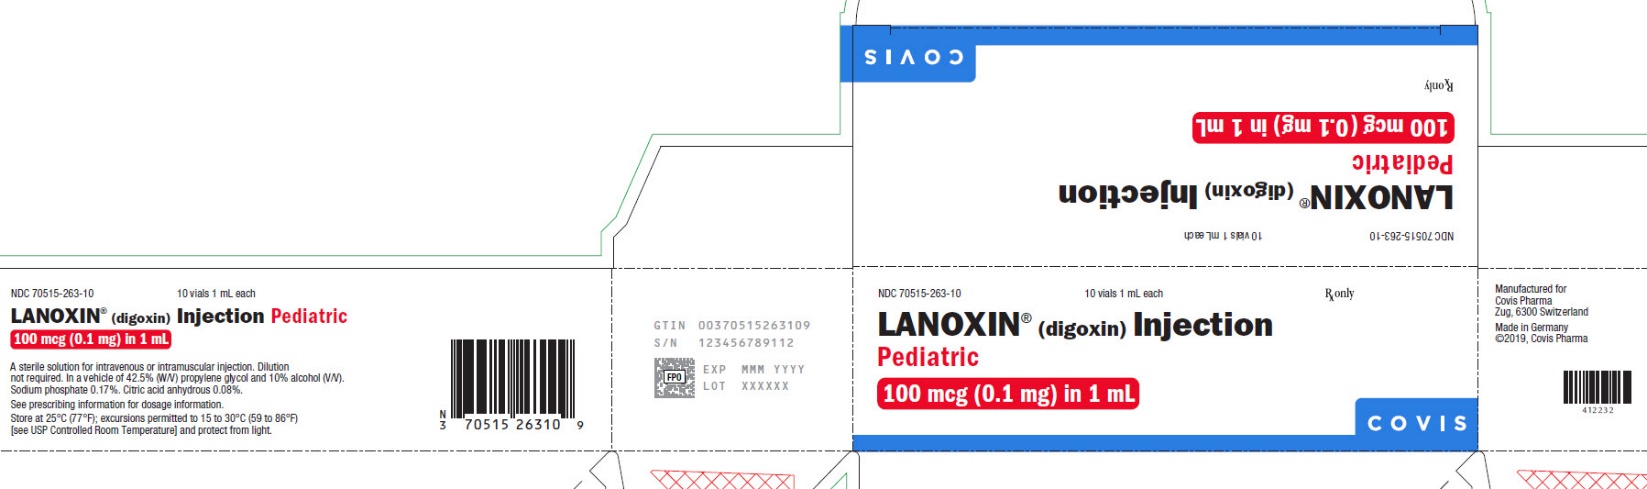
PRINCIPAL DISPLAY PANEL - Pediatric Carton Label - Vial NDC 70515-263-10 10 vials 1 mL each – Discard unused portion Rx only LANOXIN ® (digoxin) Injection Pediatric 100 mcg/mL For Intravenous or Intramuscular Injection. Dilution not required. C O V I S NDC 70515-263-10 10 single-dose vials 1 mL each LANOXIN ® (digoxin) Injection Pediatric 100 mcg/mL In a vehicle of 42.5% (W/V) propylene glycol and 10% alcohol (V/V).
Sodium phosphate 0.17%. Citric acid anhydrous 0.08%. See prescribing information for dosage information.
Store at 25°C (77°F); excursions permitted to 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature] and protect from light. Manufactured for Covis Pharma Zug, 6300 Switzerland Made in Germany ©2024, Covis Pharma Principal Display Panel - Pediatric Carton Label - Vial
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |