
Nebivolol 20 mg Tablet, 90-count — NDC 70756-293-90 (Billing 70756-0293-90)
This is a package of 90 tablets of Nebivolol 20 mg Tablet from Lifestar Pharma LLC, marketed since Nov 2022 and currently FDA-listed; retail pharmacies pay about $0.2135 per tablet (NADAC).
Other active recalls for Nebivolol (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 064945
- GCN: 18703
- HICL (First Databank): 016740
- AHFS class code: 12:16.08.04
- RxCUI (RxNorm): 387013
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Nebivolol is used to treat high blood pressure. Nebivolol is in a class of medications called beta blockers. It works by relaxing blood vessels and slowing heart rate to improve blood flow and decrease blood pressure.
Read the full MedlinePlus article ↗- It treats high blood pressure. Lowering your blood pressure helps reduce your risk of strokes and heart attacks. You can take it alone or with other blood pressure medicines.
- Take it by mouth, usually once a day, with or without food. Follow your prescriber's directions. Your dose may be adjusted over a few weeks.
- Please don't stop suddenly. Stopping a beta blocker abruptly can worsen chest pain or even trigger a heart attack or dangerous heart rhythm. If you need to stop, your prescriber wi...
- The most common are headache and fatigue. Some people also notice dizziness, nausea, diarrhea or trouble sleeping. Call your doctor if you faint, have a very slow heartbeat, wheeze...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Nebivolol — tap one for details:
Nebivolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $0.214 | $19.22 / 90 tablets |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3058 | $27.52 / 90 tablets |
Where does this data come from?
- CMS NADAC weekly file · file of Feb 21, 2024
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Per unit | Per pack | Marketing start | Marketing end | Status |
|---|---|---|---|---|---|---|
| 70756-0293-30 70756-293-30 Main listing | 30 TABLET in 1 BOTTLE | $0.2135 / ea | $6.41 | 2022-11-14 | — | Active |
| 70756-0293-90 You're viewing this | 90 TABLET in 1 BOTTLE | $0.2135 / ea | $19.22 | 2022-11-14 | — | Active |
You're viewing the largest of 2 pack sizes for this product.
This pack effectively ties for the lowest per-ea cost of the 2 priced pack sizes ($0.2135 NADAC).
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 70756-0293-30?
What NDC number is used to bill for this package of Nebivolol 20 mg Tablet?
Prices are the latest CMS NADAC pharmacy acquisition cost per NDC; per-pack figures are per-unit × pack quantity, shown only when the pack is denominated in the same measure NADAC prices.
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Nebivolol 20 mg 00904-7500-04 | Major | 30 tablets | $0.175 | AB | Availability likely | save 18% |
| nebivolol 20 mg 24689-0162-01 | Apnar | 30 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mg 33342-0460-07 | Macleods | 30 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mg 43547-0527-03 | Solco | 30 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mg 59651-0140-30 | Aurobindo | 30 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mg 62559-0278-05 | ANI | 500 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mg 72205-0153-30 | Novadoz | 30 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mg 72241-0035-04 | Modavar | 90 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mg 72603-0873-01 | NorthStar | 30 tablets | $0.175 | AB | Availability likely | save 18% |
| Nebivolol 20 mgthis 70756-0293-90 | Lifestar | 90 tablets | $0.214 | AB | FDA listed | — |
| Bystolic 20 mg 00456-1420-01 | Allergan, | 100 tablets | — | AB | FDA listed | — |
| Nebivolol Hydrochloride 20 mg 29300-0378-05 | Unichem | 500 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 31722-0588-01 | Camber | 100 tablets | — | AB | FDA listed | — |
| nebivolol 20 mg 42291-0874-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 50090-7301-01 | A-S | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 50090-7853-01 | A-S | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 51407-0486-30 | Golden | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 63629-9423-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 67877-0390-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| nebivolol 20 mg 68462-0618-01 | Glenmark | 100 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 71209-0061-01 | Cadila | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 72162-2416-03 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Nebivolol 20 mg 72189-0592-60 | Direct_Rx | 60 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file · file of Feb 21, 2024
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII ZK64F7XSTX
A red synthetic colorant made by combining D&C Red No. 27 dye with aluminum salts. It's used to give tablets, capsules, or other medicines their red or pink color.
-
UNII 4AQJ3LG584
A synthetic blue dye combined with aluminum to create a stable colorant. It's used in medicines and supplements to add blue color or create specific shades for product identification and appearance.
-
UNII 36SFW2JZ0W
Hypromellose 2910 is a plant-based thickening agent derived from cellulose. In medicines, it forms a protective coating on tablets or capsules and controls how quickly the drug dissolves and releases into your body.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
10 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Nebivolol tablets are a beta-adrenergic blocking agent indicated for the treatment of hypertension, to lower blood pressure. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions. ( 1.1 )
1.1Hypertension Nebivolol tablets are indicated for the treatment of hypertension, to lower blood pressure [see Clinical Studies (14.1) ]. Nebivolol tablets may be used alone or in combination with other antihypertensive agents [see Drug Interactions (7) ]. Lowering blood pressure reduces the risk of fatal and nonfatal cardiovascular events, primarily strokes and myocardial infarctions.
These benefits have been seen in controlled trials of antihypertensive drugs from a wide variety of pharmacologic classes, including the class to which this drug principally belongs. There are no controlled trials demonstrating risk reduction with nebivolol tablets. Control of high blood pressure should be part of comprehensive cardiovascular risk management, including, as appropriate, lipid control, diabetes management, antithrombotic therapy, smoking cessation, exercise, and limited sodium intake.
Many patients will require more than one drug to achieve blood pressure goals. For specific advice on goals and management, see published guidelines, such as those of the National High Blood Pressure Education Program's Joint National Committee on Prevention, Detection, Evaluation, and Treatment of High Blood Pressure (JNC). Numerous antihypertensive drugs, from a variety of pharmacologic classes and with different mechanisms of action, have been shown in randomized controlled trials to reduce cardiovascular morbidity and mortality, and it can be concluded that it is blood pressure reduction, and not some other pharmacologic property of the drugs, that is largely responsible for those benefits.
The largest and most consistent cardiovascular outcome benefit has been a reduction in the risk of stroke, but reductions in myocardial infarction and cardiovascular mortality also have been seen regularly. Elevated systolic or diastolic pressure causes increased cardiovascular risk, and the absolute risk increase per mmHg is greater at higher blood pressures, so that even modest reductions of severe hypertension can provide substantial benefit. Relative risk reduction from blood pressure reduction is similar across populations with varying absolute risk, so the absolute benefit is greater in patients who are at higher risk independent of their hypertension (for example, patients with diabetes or hyperlipidemia), and such patients would be expected to benefit from more aggressive treatment to a lower blood pressure goal.
Some antihypertensive drugs have smaller blood pressure effects (as monotherapy) in black patients, and many antihypertensive drugs have additional approved indications and effects (e.g., on angina, heart failure, or diabetic kidney disease). These considerations may guide selection of therapy.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Can be taken with and without food. Individualize to the needs of the patient and monitor during up-titration. ( 2 ) Hypertension: Most patients start at 5 mg once daily. Dose can be increased at 2-week intervals up to 40 mg. ( 2.1 )
2.1Hypertension The dose of nebivolol tablets must be individualized to the needs of the patient. For most patients, the recommended starting dose is 5 mg once daily, with or without food, as monotherapy or in combination with other agents. For patients requiring further reduction in blood pressure, the dose can be increased at 2-week intervals up to 40 mg.
A more frequent dosing regimen is unlikely to be beneficial. Renal Impairment In patients with severe renal impairment (ClCr less than 30 mL/min) the recommended initial dose is 2.5 mg once daily; titrate up slowly if needed. Nebivolol tablets has not been studied in patients receiving dialysis [see Clinical Pharmacology (12.4) ].
Hepatic Impairment In patients with moderate hepatic impairment, the recommended initial dose is 2.5 mg once daily; titrate up slowly if needed. Nebivolol tablets has not been studied in patients with severe hepatic impairment and therefore it is not recommended in that population [ see Clinical Pharmacology (12.4) ].
2.2Subpopulations Geriatric Patients It is not necessary to adjust the dose in the elderly [see use in Specific Populations (8.5) ]. CYP2D6 Polymorphism No dose adjustments are necessary for patients who are CYP2D6 poor metabolizers. The clinical effect and safety profile observed in poor metabolizers were similar to those of extensive metabolizers [see Clinical Pharmacology (12.3) ].
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Nebivolol tablets are available as tablets for oral administration containing nebivolol hydrochloride equivalent to 2.5, 5, 10, and 20 mg of nebivolol. 2.5 mg tablets: Round-shaped, white to off-white tablets and engraved with "L" on one side and "25" on the other side. 5 mg tablets: Round-shaped, white to off-white tablets and engraved with "LS" on one side and "291" on the other side.
10 mg tablets: Round-shaped, pinkish purple colored mottled tablets and engraved with "LS" on one side and "292" on the other side. 20 mg tablets: Round-shaped, light blue colored mottled tablets and engraved with "LS" on one side and "293" on the other side. Tablets: 2.5, 5, 10, 20 mg ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS Nebivolol tablets are contraindicated in the following conditions: Severe bradycardia Heart block greater than first degree Patients with cardiogenic shock Decompensated cardiac failure Sick sinus syndrome (unless a permanent pacemaker is in place) Patients with severe hepatic impairment (Child-Pugh >B) Patients who are hypersensitive to any component of this product. Severe bradycardia ( 4 ) Heart block greater than first degree ( 4 ) Patients with cardiogenic shock ( 4 ) Decompensated cardiac failure ( 4 ) Sick sinus syndrome (unless a permanent pacemaker is in place) ( 4 ) Patients with severe hepatic impairment (Child-Pugh >B) ( 4 ) Hypersensitive to any component of this product ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Acute exacerbation of coronary artery disease upon cessation of therapy: Do not abruptly discontinue. ( 5.1 ) Diabetes: May mask symptoms of hypoglycemia and alter glucose levels; monitor. ( 5.5 )
5.1Abrupt Cessation of Therapy Do not abruptly discontinue nebivolol tablets therapy in patients with coronary artery disease. Severe exacerbation of angina, myocardial infarction and ventricular arrhythmias have been reported in patients with coronary artery disease following the abrupt discontinuation of therapy with β-blockers. Myocardial infarction and ventricular arrhythmias may occur with or without preceding exacerbation of the angina pectoris.
Caution patients without overt coronary artery disease against interruption or abrupt discontinuation of therapy. As with other β-blockers, when discontinuation of nebivolol tablets are planned, carefully observe and advise patients to minimize physical activity. Taper nebivolol tablets over 1 to 2 weeks when possible.
If the angina worsens or acute coronary insufficiency develops, re-start nebivolol tablets promptly, at least temporarily.
5.2Angina and Acute Myocardial Infarction Nebivolol tablets was not studied in patients with angina pectoris or who had a recent MI.
5.3Bronchospastic Diseases In general, patients with bronchospastic diseases should not receive β-blockers.
5.4Anesthesia and Major Surgery Because beta-blocker withdrawal has been associated with an increased risk of MI and chest pain, patients already on beta-blockers should generally continue treatment throughout the perioperative period. If nebivolol tablets are to be continued perioperatively, monitor patients closely when anesthetic agents which depress myocardial function, such as ether, cyclopropane, and trichloroethylene, are used. If β-blocking therapy is withdrawn prior to major surgery, the impaired ability of the heart to respond to reflex adrenergic stimuli may augment the risks of general anesthesia and surgical procedures.
The β-blocking effects of nebivolol tablets can be reversed by β-agonists, e.g., dobutamine or isoproterenol. However, such patients may be subject to protracted severe hypotension. Additionally, difficulty in restarting and maintaining the heartbeat has been reported with β-blockers.
5.5Hypoglycemia Beta-blockers may prevent early warning signs of hypoglycemia, such as tachycardia, and increase the risk for severe or prolonged hypoglycemia at anytime during treatment, especially in patients with diabetes mellitus or children and patients who are fasting (i.e., surgery, not eating regularly, or are vomiting). If severe hypoglycemia occurs, patients should be instructed to seek emergency treatment.
5.6Thyrotoxicosis β-blockers may mask clinical signs of hyperthyroidism, such as tachycardia. Abrupt withdrawal of β-blockers may be followed by an exacerbation of the symptoms of hyperthyroidism or may precipitate a thyroid storm.
5.7Peripheral Vascular Disease β-blockers can precipitate or aggravate symptoms of arterial insufficiency in patients with peripheral vascular disease.
5.8Non-dihydropyridine Calcium Channel Blockers Because of significant negative inotropic and chronotropic effects in patients treated with β-blockers and calcium channel blockers of the verapamil and diltiazem type, monitor the ECG and blood pressure in patients treated concomitantly with these agents.
5.9Use with CYP2D6 Inhibitors Nebivolol exposure increases with inhibition of CYP2D6 [see Drug Interactions (7) ] . The dose of nebivolol tablets may need to be reduced.
5.10Impaired Renal Function Renal clearance of nebivolol is decreased in patients with severe renal impairment. Nebivolol tablets has not been studied in patients receiving dialysis [see Clinical Pharmacology (12.4) and Dosage and Administration (2.1) ] .
5.11Impaired Hepatic Function Metabolism of nebivolol is decreased in patients with moderate hepatic impairment. Nebivolol tablets has not been studied in patien… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS Most common adverse reactions ( 6.1 ): Headache, fatigue To report SUSPECTED ADVERSE REACTIONS, contact Lifestar Pharma LLC at 1-888-995-4337 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Studies Experience Nebivolol tablets has been evaluated for safety in patients with hypertension and in patients with heart failure. The observed adverse reaction profile was consistent with the pharmacology of the drug and the health status of the patients in the clinical trials. Adverse reactions reported for each of these patient populations are provided below.
Excluded are adverse reactions considered too general to be informative and those not reasonably associated with the use of the drug because they were associated with the condition being treated or are very common in the treated population. The data described below reflect worldwide clinical trial exposure to nebivolol tablets in 6545 patients, including 5038 patients treated for hypertension and the remaining 1507 subjects treated for other cardiovascular diseases. Doses ranged from 0.5 mg to 40 mg.
Patients received nebivolol tablets for up to 24 months, with over 1900 patients treated for at least 6 months, and approximately 1300 patients for more than one year. HYPERTENSION : In placebo-controlled clinical trials comparing nebivolol tablets with placebo, discontinuation of therapy due to adverse reactions was reported in 2.8% of patients treated with nebivolol and 2.2% of patients given placebo. The most common adverse reactions that led to discontinuation of nebivolol tablets were headache (0.4%), nausea (0.2%) and bradycardia (0.2%).
Table 1 lists treatment-emergent adverse reactions that were reported in three 12-week, placebo-controlled monotherapy trials involving 1597 hypertensive patients treated with either 5 mg, 10 mg, or 20-40 mg of nebivolol tablets and 205 patients given placebo and for which the rate of occurrence was at least 1% of patients treated with nebivolol and greater than the rate for those treated with placebo in at least one dose group. Table 1. Treatment-Emergent Adverse Reactions with an Incidence (over 6 weeks) ≥ 1% in nebivolol tablets - Treated Patients and at a Higher Frequency than Placebo-Treated Patients System Organ Class – Preferred Term Placebo (n = 205) (%) Nebivolol 5 mg (n = 459) (%) Nebivolol 10 mg (n = 461) (%) Nebivolol 20-40 mg (n = 677) (%) Cardiac Disorders Bradycardia 0 0 0 1 Gastrointestinal Disorders Diarrhea 2 2 2 3 Nausea 0 1 3 2 General Disorders Fatigue 1 2 2 5 Chest pain 0 0 1 1 Peripheral edema 0 1 1 1 Nervous System Disorders Headache 6 9 6 7 Dizziness 2 2 3 4 Psychiatric Disorders Insomnia 0 1 1 1 Respiratory Disorders Dyspnea 0 0 1 1 Skin and subcutaneous Tissue Disorders Rash 0 0 1 1 Listed below are other reported adverse reactions with an incidence of at least 1% in the more than 4300 patients treated with nebivolol tablets in controlled or open-label trials except for those already appearing in Table 1, terms too general to be informative, minor symptoms, or adverse reactions unlikely to be attributable to drug because they are common in the population.
These adverse reactions were in most cases observed at a similar frequency in placebo-treated patients in the controlled studies. Body as a Whole: asthenia. Gastrointestinal System Disorders: abdominal pain Metabolic and Nutritional Disorders: hypercholesterolemia Nervous System Disorders: paraesthesia
6.2Laboratory Abnormalities In controlled monotherapy trials of hypertensive patients, nebivolol tablets was associated with an increase in BUN, uric acid, triglycerides and a decrease in HDL cholesterol and platelet count.
6.3Postmarketing Experience The following adverse reactions have been identified from spontaneous reports of nebivolol tablets received worldwide and have not been listed elsewhere. These adverse reactions have been chosen for inclusion due to a combination of seriousness, frequency of reporting or potential causa… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS CYP2D6 enzyme inhibitors may increase nebivolol levels. ( 7.1 ) Reserpine or clonidine may produce excessive reduction of sympathetic activity. ( 7.2 ) Both digitalis glycosides and β-blockers slow atrioventricular conduction and decrease heart rate.
Concomitant use can increase the risk of bradycardia. ( 7.3 ) Verapamil- or diltiazem-type calcium channel blockers may cause excessive reductions in heart rate, blood pressure, and cardiac contractility. ( 7.4 )
7.1CYP2D6 Inhibitors Use caution when nebivolol tablets are co-administered with CYP2D6 inhibitors (quinidine, propafenone, fluoxetine, paroxetine, etc.) [see Clinical Pharmacology (12.5) ] .
7.2Hypotensive Agents Do not use nebivolol tablets with other β-blockers. Closely monitor patients receiving catecholamine-depleting drugs, such as reserpine or guanethidine, because the added β-blocking action of nebivolol tablets may produce excessive reduction of sympathetic activity. In patients who are receiving nebivolol tablets and clonidine, discontinue nebivolol tablets for several days before the gradual tapering of clonidine.
7.3Digitalis Glycosides Both digitalis glycosides and β-blockers slow atrioventricular conduction and decrease heart rate. Concomitant use can increase the risk of bradycardia.
7.4Calcium Channel Blockers Nebivolol tablets can exacerbate the effects of myocardial depressants or inhibitors of AV conduction, such as certain calcium antagonists (particularly of the phenylalkylamine [verapamil] and benzothiazepine [diltiazem] classes), or antiarrhythmic agents, such as disopyramide.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Breastfeeding is not recommended. ( 8.2 )
8.1Pregnancy Risk Summary Available data regarding use of nebivolol tablets in pregnant women are insufficient to determine whether there are drug-associated risks of adverse developmental outcomes. There are risks to the mother and fetus associated with poorly controlled hypertension in pregnancy. The use of beta blockers during the third trimester of pregnancy may increase the risk of hypotension, bradycardia, hypoglycemia, and respiratory depression in the neonate [see Clinical Considerations].
Oral administration of nebivolol to pregnant rats during organogenesis resulted in embryofetal and perinatal lethality at doses approximately equivalent to the maximum recommended human dose (MRHD). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/Neonatal adverse reactions Neonates of women with hypertension, who are treated with beta-blockers during the third trimester of pregnancy, may be at increased risk for hypotension, bradycardia, hypoglycemia, and respiratory depression. Observe newborns for symptoms of hypotension, bradycardia, hypoglycemia and respiratory depression and manage accordingly. Data Animal Data Nebivolol was shown to increase embryo-fetal and perinatal lethality in rats at approximately 1.2 times the MRHD or 40 mg/day on a mg/m 2 basis.
Decreased pup body weights occurred at 1.25 and 2.5 mg/kg in rats, when exposed during the perinatal period (late gestation, parturition and lactation). At 5 mg/kg and higher doses (1.2 times the MRHD), prolonged gestation, dystocia and reduced maternal care were produced with corresponding increases in late fetal deaths and stillbirths and decreased birth weight, live litter size and pup survival. These events occurred only when nebivolol was given during the perinatal period (late gestation, parturition and lactation).
Insufficient numbers of pups survived at 5 mg/kg to evaluate the offspring for reproductive performance. In studies in which pregnant rats were given nebivolol during organogenesis, reduced fetal body weights were observed at maternally toxic doses of 20 and 40 mg/kg/day (5 and 10 times the MRHD), and small reversible delays in sternal and thoracic ossification associated with the reduced fetal body weights and a small increase in resorption occurred at 40 mg/kg/day (10 times the MRHD). No adverse effects on embryo-fetal viability, sex, weight or morphology were observed in studies in which nebivolol was given to pregnant rabbits at doses as high as 20 mg/kg/day (10 times the MRHD).
8.2Lactation Risk Summary There is no information regarding the presence of nebivolol in human milk, the effects on the breastfed infant, or the effects on milk production. Nebivolol is present in rat milk [see Data]. Because of the potential for β-blockers to produce serious adverse reactions in nursing infants, especially bradycardia, nebivolol tablets are not recommended during nursing.
Data In lactating rats, maximum milk levels of unchanged nebivolol were observed at 4 hours after single and repeat doses of 2.5 mg/kg/day. The daily dose (mg/kg body weight) ingested by a rat pup is 0.3% of the dam dose for unchanged nebivolol.
8.4Pediatric Use Safety and effectiveness in pediatric patients have not bee… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data regarding use of nebivolol tablets in pregnant women are insufficient to determine whether there are drug-associated risks of adverse developmental outcomes. There are risks to the mother and fetus associated with poorly controlled hypertension in pregnancy. The use of beta blockers during the third trimester of pregnancy may increase the risk of hypotension, bradycardia, hypoglycemia, and respiratory depression in the neonate [see Clinical Considerations].
Oral administration of nebivolol to pregnant rats during organogenesis resulted in embryofetal and perinatal lethality at doses approximately equivalent to the maximum recommended human dose (MRHD). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2-4% and 15-20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk Hypertension in pregnancy increases the maternal risk for pre-eclampsia, gestational diabetes, premature delivery, and delivery complications (e.g., need for cesarean section, and post-partum hemorrhage). Hypertension increases the fetal risk for intrauterine growth restriction and intrauterine death. Pregnant women with hypertension should be carefully monitored and managed accordingly.
Fetal/Neonatal adverse reactions Neonates of women with hypertension, who are treated with beta-blockers during the third trimester of pregnancy, may be at increased risk for hypotension, bradycardia, hypoglycemia, and respiratory depression. Observe newborns for symptoms of hypotension, bradycardia, hypoglycemia and respiratory depression and manage accordingly. Data Animal Data Nebivolol was shown to increase embryo-fetal and perinatal lethality in rats at approximately 1.2 times the MRHD or 40 mg/day on a mg/m 2 basis.
Decreased pup body weights occurred at 1.25 and 2.5 mg/kg in rats, when exposed during the perinatal period (late gestation, parturition and lactation). At 5 mg/kg and higher doses (1.2 times the MRHD), prolonged gestation, dystocia and reduced maternal care were produced with corresponding increases in late fetal deaths and stillbirths and decreased birth weight, live litter size and pup survival. These events occurred only when nebivolol was given during the perinatal period (late gestation, parturition and lactation).
Insufficient numbers of pups survived at 5 mg/kg to evaluate the offspring for reproductive performance. In studies in which pregnant rats were given nebivolol during organogenesis, reduced fetal body weights were observed at maternally toxic doses of 20 and 40 mg/kg/day (5 and 10 times the MRHD), and small reversible delays in sternal and thoracic ossification associated with the reduced fetal body weights and a small increase in resorption occurred at 40 mg/kg/day (10 times the MRHD). No adverse effects on embryo-fetal viability, sex, weight or morphology were observed in studies in which nebivolol was given to pregnant rabbits at doses as high as 20 mg/kg/day (10 times the MRHD).
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness in pediatric patients have not been established. Pediatric studies in ages newborn to 18 years old have not been conducted because of incomplete characterization of developmental toxicity and possible adverse effects on long-term fertility [see Nonclinical Toxicology (13.1) ] . Juvenile Animal Toxicity Data Daily oral doses of nebivolol to juvenile rats from post-natal day 14 to post-natal day 27 showed sudden unexplained death at exposures equal to those in human poor metabolizers given a single dose of 10 mg.
No mortality was seen at half the adult human exposure. In surviving rats, cardiomyopathy was seen at exposures greater than or equal to the human exposure. Male rat pups exposed to twice the human exposure showed decreases in total sperm count as well as decreases in the total and percentage of motile sperm.
🧓 Geriatric Use ▾
8.5Geriatric Use Of the 2800 patients in the U.S. sponsored placebo-controlled clinical hypertension studies, 478 patients were 65 years of age or older. No overall differences in efficacy or in the incidence of adverse events were observed between older and younger patients.
🆘 Overdosage ▾
10 OVERDOSAGE In clinical trials and worldwide postmarketing experience there were reports of nebivolol tablets overdose. The most common signs and symptoms associated with nebivolol tablets overdosage are bradycardia and hypotension. Other important adverse reactions reported with nebivolol tablets overdose include cardiac failure, dizziness, hypoglycemia, fatigue and vomiting.
Other adverse reactions associated with β-blocker overdose include bronchospasm and heart block. The largest known ingestion of nebivolol tablets worldwide involved a patient who ingested up to 500 mg of nebivolol tablets along with several 100 mg tablets of acetylsalicylic acid in a suicide attempt. The patient experienced hyperhydrosis, pallor, depressed level of consciousness, hypokinesia, hypotension, sinus bradycardia, hypoglycemia, hypokalemia, respiratory failure and vomiting.
The patient recovered. Because of extensive drug binding to plasma proteins, hemodialysis is not expected to enhance nebivolol clearance. If overdose occurs, provide general supportive and specific symptomatic treatment.
Based on expected pharmacologic actions and recommendations for other β-blockers, consider the following general measures, including stopping nebivolol tablets, when clinically warranted: Bradycardia: Administer IV atropine. If the response is inadequate, isoproterenol or another agent with positive chronotropic properties may be given cautiously. Under some circumstances, transthoracic or transvenous pacemaker placement may be necessary.
Hypotension: Administer IV fluids and vasopressors. Intravenous glucagon may be useful. Heart Block (second or third degree): Monitor and treat with isoproterenol infusion.
Under some circumstances, transthoracic or transvenous pacemaker placement may be necessary. Congestive Heart Failure: Initiate therapy with digitalis glycoside and diuretics. In certain cases, consider the use of inotropic and vasodilating agents.
Bronchospasm: Administer bronchodilator therapy such as a short acting inhaled β2-agonist and/or aminophylline. Hypoglycemia: Administer IV glucose. Repeated doses of IV glucose or possibly glucagon may be required.
Supportive measures should continue until clinical stability is achieved. The half-life of low doses of nebivolol is 12-19 hours. Call the National Poison Control Center (800-222-1222) for the most current information on β-blocker overdose treatment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY Nebivolol is a β-adrenergic receptor blocking agent. In extensive metabolizers (most of the population) and at doses less than or equal to 10 mg, nebivolol is preferentially β 1 selective. In poor metabolizers and at higher doses, nebivolol inhibits both β 1 - and β 2 -adrenergic receptors.
Nebivolol lacks intrinsic sympathomimetic and membrane stabilizing activity at therapeutically relevant concentrations. At clinically relevant doses, nebivolol tablets does not demonstrate α 1 -adrenergic receptor blockade activity. Various metabolites, including glucuronides, contribute to β-blocking activity.
12.1Mechanism of Action The mechanism of action of the antihypertensive response of nebivolol tablets has not been definitively established. Possible factors that may be involved include: (1) decreased heart rate, (2) decreased myocardial contractility, (3) diminution of tonic sympathetic outflow to the periphery from cerebral vasomotor centers, (4) suppression of renin activity and (5) vasodilation and decreased peripheral vascular resistance.
12.3Pharmacokinetics Nebivolol is metabolized by a number of routes, including glucuronidation and hydroxylation by CYP2D6. The active isomer (d-nebivolol) has an effective half-life of about 12 hours in CYP2D6 extensive metabolizers (most people), and 19 hours in poor metabolizers and exposure to d-nebivolol is substantially increased in poor metabolizers. This has less importance than usual, however, because the metabolites, including the hydroxyl metabolite and glucuronides (the predominant circulating metabolites), contribute to β-blocking activity.
Plasma levels of d–nebivolol increase in proportion to dose in EMs and PMs for doses up to 20mg. Exposure to l-nebivolol is higher than to d-nebivolol but l-nebivolol contributes little to the drug's activity as d-nebivolol's beta receptor affinity is > 1000-fold higher than l-nebivolol. For the same dose, PMs attain a 5-fold higher Cmax and 10-fold higher AUC of d-nebivolol than do EMs. d-Nebivolol accumulates about 1.5-fold with repeated once-daily dosing in EMs.
Absorption Absorption of nebivolol tablets are similar to an oral solution. The absolute bioavailability has not been determined. Mean peak plasma nebivolol concentrations occur approximately 1.5 to 4 hours post-dosing in EMs and PMs.
Food does not alter the pharmacokinetics of nebivolol. Under fed conditions, nebivolol glucuronides are slightly reduced. Nebivolol tablets may be administered without regard to meals.
Distribution The in vitro human plasma protein binding of nebivolol is approximately 98%, mostly to albumin, and is independent of nebivolol concentrations. Metabolism Nebivolol is predominantly metabolized via direct glucuronidation of parent and to a lesser extent via Ndealkylation and oxidation via cytochrome P450 2D6. Its stereospecific metabolites contribute to the pharmacologic activity [see Drug Interactions (7) ] .
Elimination After a single oral administration of 14C-nebivolol, 38% of the dose was recovered in urine and 44% in feces for EMs and 67% in urine and 13% in feces for PMs. Essentially all nebivolol was excreted as multiple oxidative metabolites or their corresponding glucuronide conjugates.
12.4Pharmacokinetics in Special Populations Hepatic Disease d-Nebivolol peak plasma concentration increased 3-fold, exposure (AUC) increased 10-fold, and the apparent clearance decreased by 86% in patients with moderate hepatic impairment (Child-Pugh Class B). No formal studies have been performed in patients with severe hepatic impairment and nebivolol should be contraindicated for these patients [see Dosage and Administration (2.1) ] . Renal Disease The apparent clearance of nebivolol was unchanged following a single 5 mg dose of nebivolol tablets in patients with mild renal impairment (ClCr 50 to 80 mL/min, n=7), and it was reduced negligibly in patients with moderate (ClCr 30 to 50 mL/min, n=9), but clearance was reduced by 53% in pati… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The mechanism of action of the antihypertensive response of nebivolol tablets has not been definitively established. Possible factors that may be involved include: (1) decreased heart rate, (2) decreased myocardial contractility, (3) diminution of tonic sympathetic outflow to the periphery from cerebral vasomotor centers, (4) suppression of renin activity and (5) vasodilation and decreased peripheral vascular resistance.
📦 How Supplied / Storage and Handling ▾
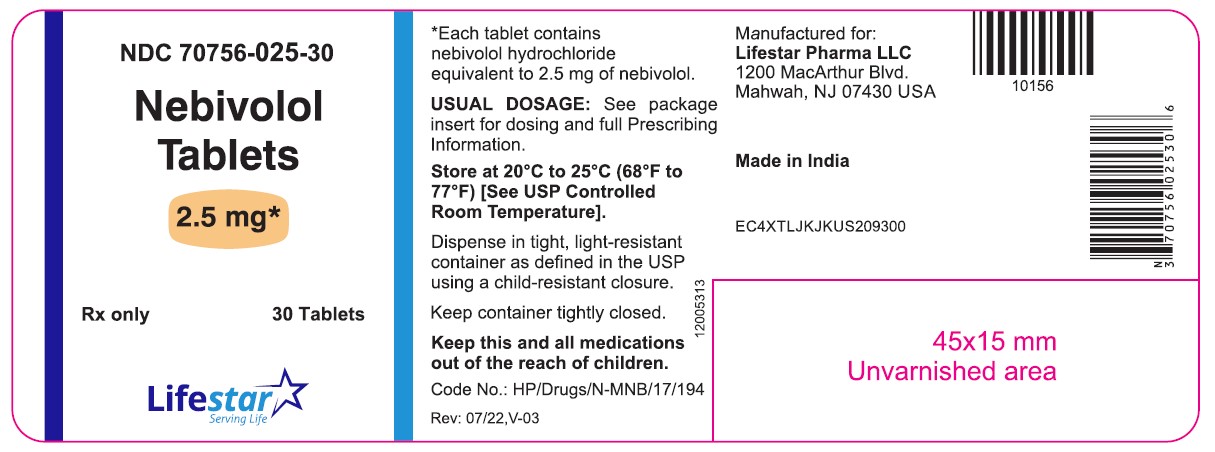
16 HOW SUPPLIED/STORAGE AND HANDLING Nebivolol tablets are available as tablets for oral administration containing nebivolol hydrochloride equivalent to 2.5, 5, 10, and 20 mg of nebivolol. 2.5 mg tablets: Round-shaped, white to off-white tablets and engraved with "L" on one side and "25" on the other side, are supplied in the following package sizes: Bottles of 30's with child-resistant closure (NDC 70756-025-30) 5 mg tablets: Round-shaped, white to off-white tablets and engraved with "LS" on one side and "291" on the other side, are supplied in the following package sizes: Bottles of 30's with child-resistant closure (NDC 70756-291-30) Bottles of 90's with child-resistant closure (NDC 70756-291-90) 10 mg tablets: Round-shaped, pinkish purple colored mottled tablets and engraved with "LS" on one side and "292" on the other side, are supplied in the following package sizes: Bottles of 30's with child-resistant closure (NDC 70756-292-30) Bottles of 90's with child-resistant closure (NDC 70756-292-90) 20 mg tablets: Round-shaped, light blue colored mottled tablets and engraved with "LS" on one side and "293" on the other side, are supplied in the following package sizes: Bottles of 30's with child-resistant closure (NDC 70756-293-30) Bottles of 90's with child-resistant closure (NDC 70756-293-90) Store at 20°C to 25°C (68°F to 77°F) [See USP Controlled Room Temperature].
Dispense in a tight, light-resistant container as defined in the USP using a child-resistant closure.
📋 Description ▾
11 DESCRIPTION The chemical name for the active ingredient in nebivolol tablets are (1RS,1'RS)-1,1'-[(2RS,2'SR)-bis(6-fluoro-3,4-dihydro-2H-1-benzopyran-2-yl)]- 2,2'-iminodiethanol hydrochloride. Nebivolol is a racemate composed of d-Nebivolol and l-Nebivolol with the stereochemical designations of [SRRR]-nebivolol and [RSSS]-nebivolol, respectively. Nebivolol's molecular formula is (C 22 H 25 F 2 NO 4 •HCl) with the following structural formula: SRRR - or d-nebivolol hydrochloride RSSS - or l-nebivolol hydrochloride MW: 441.90 g/mol Nebivolol hydrochloride is a white to off-white crystalline powder that is sparingly soluble in dimethyl formamide and slightly soluble in methanol.
Nebivolol tablets for oral administration contains nebivolol hydrochloride equivalent to 2.5, 5, 10, and 20 mg of nebivolol base. In addition, nebivolol tablets contains the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, pregelatinized starch (maize), and polysorbate 80. In addition, 10 and 20 mg contain D&C RED #27 Aluminum Lake and FD&C BLUE #2 Aluminum Lake.
SRRR - or d-nebivolol hydrochloride RSSS - or l-nebivolol hydrochloride
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION See FDA-approved patient labeling ( Patient Information ). Patient Advice Advise patients to take nebivolol tablets regularly and continuously, as directed. Nebivolol tablets can be taken with or without food.
If a dose is missed, take the next scheduled dose only (without doubling it). Do not interrupt or discontinue nebivolol tablets without consulting the physician. Patients should know how they react to this medicine before they operate automobiles, use machinery, or engage in other tasks requiring alertness.
Advise patients to consult a physician if any difficulty in breathing occurs, or if they develop signs or symptoms of worsening congestive heart failure such as weight gain or increasing shortness of breath, or excessive bradycardia. Caution patients subject to spontaneous hypoglycemia, or diabetic patients receiving insulin or oral hypoglycemic agents, that β-blockers may mask some of the manifestations of hypoglycemia, particularly tachycardia. Inform patients or caregivers that there is a risk of hypoglycemia when nebivolol tablets are given to patients who are fasting or who are vomiting.
Instruct patients or caregivers how to monitor for signs of hypoglycemia [see Warnings and Precautions (5.5)]. Manufactured for: Lifestar Pharma LLC 1200 MacArthur Blvd. Mahwah, NJ 07430 USA Made in India The brands listed are trademarks of their respective owners.
Revised: July 2023, V-04
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Nebivolol is metabolized by a number of routes, including glucuronidation and hydroxylation by CYP2D6. The active isomer (d-nebivolol) has an effective half-life of about 12 hours in CYP2D6 extensive metabolizers (most people), and 19 hours in poor metabolizers and exposure to d-nebivolol is substantially increased in poor metabolizers. This has less importance than usual, however, because the metabolites, including the hydroxyl metabolite and glucuronides (the predominant circulating metabolites), contribute to β-blocking activity.
Plasma levels of d–nebivolol increase in proportion to dose in EMs and PMs for doses up to 20mg. Exposure to l-nebivolol is higher than to d-nebivolol but l-nebivolol contributes little to the drug's activity as d-nebivolol's beta receptor affinity is > 1000-fold higher than l-nebivolol. For the same dose, PMs attain a 5-fold higher Cmax and 10-fold higher AUC of d-nebivolol than do EMs. d-Nebivolol accumulates about 1.5-fold with repeated once-daily dosing in EMs.
Absorption Absorption of nebivolol tablets are similar to an oral solution. The absolute bioavailability has not been determined. Mean peak plasma nebivolol concentrations occur approximately 1.5 to 4 hours post-dosing in EMs and PMs.
Food does not alter the pharmacokinetics of nebivolol. Under fed conditions, nebivolol glucuronides are slightly reduced. Nebivolol tablets may be administered without regard to meals.
Distribution The in vitro human plasma protein binding of nebivolol is approximately 98%, mostly to albumin, and is independent of nebivolol concentrations. Metabolism Nebivolol is predominantly metabolized via direct glucuronidation of parent and to a lesser extent via Ndealkylation and oxidation via cytochrome P450 2D6. Its stereospecific metabolites contribute to the pharmacologic activity [see Drug Interactions (7) ] .
Elimination After a single oral administration of 14C-nebivolol, 38% of the dose was recovered in urine and 44% in feces for EMs and 67% in urine and 13% in feces for PMs. Essentially all nebivolol was excreted as multiple oxidative metabolites or their corresponding glucuronide conjugates.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Hypertension The antihypertensive effectiveness of nebivolol tablets as monotherapy has been demonstrated in three randomized, double-blind, multi-center, placebo-controlled trials at doses ranging from 1.25 to 40 mg for 12 weeks (Studies 1, 2, and 3). A fourth placebo-controlled trial demonstrated additional antihypertensive effects of nebivolol tablets at doses ranging from 5 to 20 mg when administered concomitantly with up to two other antihypertensive agents (ACE inhibitors, angiotensin II receptor antagonists, and thiazide diuretics) in patients with inadequate blood pressure control.
The three monotherapy trials included a total of 2016 patients (1811 nebivolol tablets, 205 placebo) with mild to moderate hypertension who had baseline diastolic blood pressures (DBP) of 95 to 109 mmHg. Patients received either nebivolol tablets or placebo once daily for twelve weeks. Two of these monotherapy trials (Studies 1 and 2) studied 1716 patients in the general hypertensive population with a mean age of 54 years, 55% males, 26% non-Caucasians, 7% diabetics and 6% genotyped as PMs.
The third monotherapy trial (Study 3) studied 300 Black patients with a mean age of 51 years, 45% males, 14% diabetics, and 3% as PMs. Placebo-subtracted blood pressure reductions by dose for each study are presented in Table 2. Most studies showed increasing response to doses above 5 mg.
Table 2. Placebo-Subtracted Least-Square Mean Reductions in Trough Sitting Systolic/Diastolic Blood Pressure (SiSBP/SiDBP mmHg) by Dose in Studies with Once Daily nebivolol tablets Nebivolol dose (mg) 1.25 2.5 5.0 10 20 30-40 Study 1 -6.6*/-5.1* -8.5*/-5.6* -8.1*/-5.5* -9.2*/-6.3* -8.7*/-6.9* -11.7*/-8.3* Study 2 -3.8/-3.2* -3.1/-3.9* -6.3*/-4.5* Study 3 ¶ -1.5/-2.9 -2.6/-4.9* -6.0*/-6.1* -7.2*/-6.1* -6.8*/-5.5* Study 4 ^ -5.7*/-3.3* -3.7*/-3.5* -6.2*/-4.6* * p<0.05 based on pair-wise comparison vs. placebo ¶ Study enrolled only African Americans. ^ Study on top of one or two other antihypertensive medications.
Study 4 enrolled 669 patients with a mean age of 54 years, 55% males, 54% Caucasians, 29% Blacks, 15% Hispanics, 1% Asians, 14% diabetics, and 5% PMs. Nebivolol tablets, 5 mg to 20 mg, administered once daily concomitantly with stable doses of up to two other antihypertensive agents (ACE inhibitors, angiotensin II receptor antagonists, and thiazide diuretics) resulted in significant additional antihypertensive effects over placebo compared to baseline blood pressure. Effectiveness was similar in subgroups analyzed by age and sex.
Effectiveness was established in Blacks, but as monotherapy the magnitude of effect was somewhat less than in Caucasians. The blood pressure lowering effect of nebivolol tablets was seen within two weeks of treatment and was maintained over the 24-hour dosing interval. There are no trials of nebivolol tablets demonstrating reductions in cardiovascular risk in patients with hypertension, but at least one pharmacologically similar drug has demonstrated such benefits.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a two-year study of nebivolol in mice, a statistically significant increase in the incidence of testicular Leydig cell hyperplasia and adenomas was observed at 40 mg/kg/day (5 times the maximally recommended human dose of 40 mg on a mg/m 2 basis). Similar findings were not reported in mice administered doses equal to approximately 0.3 or 1.2 times the maximum recommended human dose. No evidence of a tumorigenic effect was observed in a 24-month study in Wistar rats receiving doses of nebivolol 2.5, 10 and 40 mg/kg/day (equivalent to 0.6, 2.4, and 10 times the maximally recommended human dose).
Co-administration of dihydrotestosterone reduced blood LH levels and prevented the Leydig cell hyperplasia, consistent with an indirect LH-mediated effect of nebivolol in mice and not thought to be clinically relevant in man. A randomized, double-blind, placebo- and active-controlled, parallel-group study in healthy male volunteers was conducted to determine the effects of nebivolol on adrenal function, luteinizing hormone, and testosterone levels. This study demonstrated that 6 weeks of daily dosing with 10 mg of nebivolol had no significant effect on ACTH-stimulated mean serum cortisol AUC 0-120 min , serum LH, or serum total testosterone.
Effects on spermatogenesis were seen in male rats and mice at ≥ 40 mg/kg/day (10 and 5 times the MRHD, respectively). For rats the effects on spermatogenesis were not reversed and may have worsened during a four week recovery period. The effects of nebivolol on sperm in mice, however, were partially reversible.
Mutagenesis: Nebivolol was not genotoxic when tested in a battery of assays (Ames, in vitro mouse lymphoma TK +/- , in vitro human peripheral lymphocyte chromosome aberration, in vivo Drosophila melanogaster sex-linked recessive lethal, and in vivo mouse bone marrow micronucleus tests).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility In a two-year study of nebivolol in mice, a statistically significant increase in the incidence of testicular Leydig cell hyperplasia and adenomas was observed at 40 mg/kg/day (5 times the maximally recommended human dose of 40 mg on a mg/m 2 basis). Similar findings were not reported in mice administered doses equal to approximately 0.3 or 1.2 times the maximum recommended human dose. No evidence of a tumorigenic effect was observed in a 24-month study in Wistar rats receiving doses of nebivolol 2.5, 10 and 40 mg/kg/day (equivalent to 0.6, 2.4, and 10 times the maximally recommended human dose).
Co-administration of dihydrotestosterone reduced blood LH levels and prevented the Leydig cell hyperplasia, consistent with an indirect LH-mediated effect of nebivolol in mice and not thought to be clinically relevant in man. A randomized, double-blind, placebo- and active-controlled, parallel-group study in healthy male volunteers was conducted to determine the effects of nebivolol on adrenal function, luteinizing hormone, and testosterone levels. This study demonstrated that 6 weeks of daily dosing with 10 mg of nebivolol had no significant effect on ACTH-stimulated mean serum cortisol AUC 0-120 min , serum LH, or serum total testosterone.
Effects on spermatogenesis were seen in male rats and mice at ≥ 40 mg/kg/day (10 and 5 times the MRHD, respectively). For rats the effects on spermatogenesis were not reversed and may have worsened during a four week recovery period. The effects of nebivolol on sperm in mice, however, were partially reversible.
Mutagenesis: Nebivolol was not genotoxic when tested in a battery of assays (Ames, in vitro mouse lymphoma TK +/- , in vitro human peripheral lymphocyte chromosome aberration, in vivo Drosophila melanogaster sex-linked recessive lethal, and in vivo mouse bone marrow micronucleus tests).
📄 Recent Major Changes ▾
RECENT MAJOR CHANGES Warnings and Precautions, Hypoglycemia (5.5) 6/2023
📄 Package Label / Principal Display Panel ▾
PACKAGE LABEL.PRINCIPAL DISPLAY PANEL NDC 70756-025-30 Nebivolol Tablets 2.5 mg* Rx only 30 Tablets NDC 70756-291-30 Nebivolol Tablets * 5 mg* Rx only 30 Tablets NDC 70756-291-90 Nebivolol Tablets 5 mg* Rx only 90 Tablets NDC 70756-292-30 Nebivolol Tablets 10 mg * Rx only 30 Tablets NDC 70756-292-90 Nebivolol Tablets 10 mg* Rx only 90 Tablets NDC 70756-293-30 Nebivolol Tablets 20 mg* Rx only 30 Tablets NDC 70756-293-90 20 mg* Nebivolol Tablets Rx only 90 Tablets 2.5mg 5mg 30 5 mg 90 10mg 30 10mg 90 20mg 30 20mg 90