
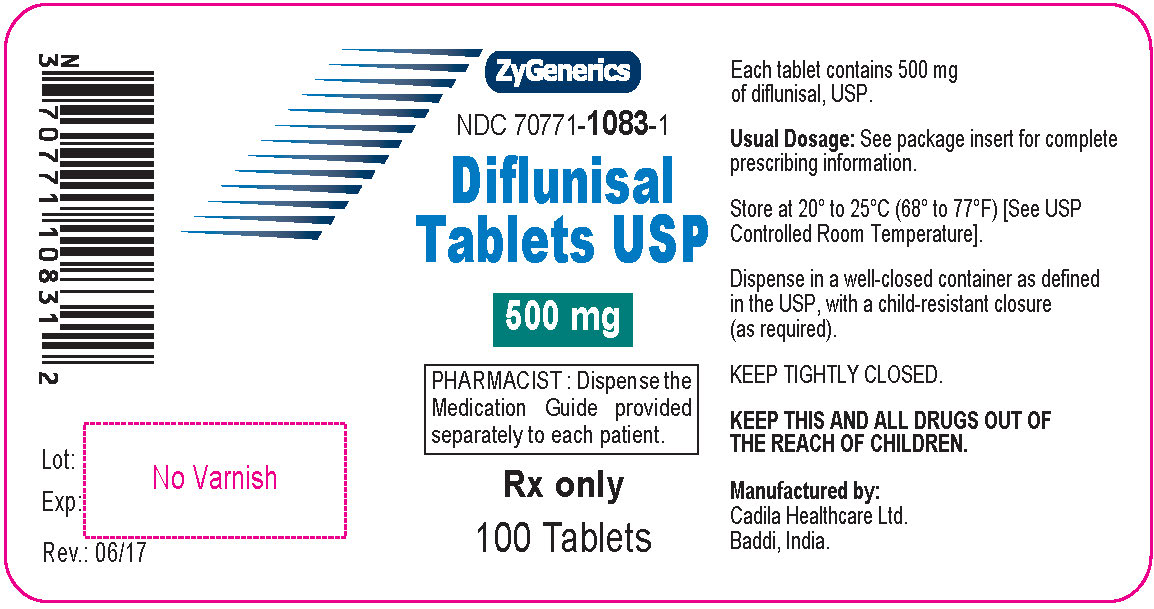
Diflunisal 500 mg Tablet, 1,000-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Nonsteroidal Anti-inflammatory Drug class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Diflunisal is an anti-inflammatory pain reliever — an NSAID — used to treat mild to moderate pain and to help manage the symptoms of osteoarthritis and rheumatoid arthritis. It can...
- Swallow the tablets whole — don't crush or chew them. For pain, you'll usually take a higher first dose to get things working, then a lower dose every 8 to 12 hours after that. For...
- The most common ones are stomach-related — nausea, stomach pain, diarrhea, and sometimes constipation. You might also notice headache, dizziness, or ringing in your ears. Most of t...
- What side effects should I watch out for?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Diflunisal — tap one for details:
Diflunisal may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $1.06 | $1,058.60 / 1000 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Diflunisal 500 mg 00093-9222-01 | Teva | 100 tablets | $1.043 | AB | Availability likely | — |
| diflunisal 500 mg 14539-0673-01 | Heritage | 100 tablets | $1.043 | — | Availability likely | — |
| Diflunisal 500 mg 62135-0456-60 | Chartwell | 60 tablets | $1.043 | — | Availability likely | — |
| Diflunisal 500 mg 68382-0530-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Diflunisal 500 mgthis 70771-1083-00 | Zydus | 1000 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 70771-1083-00 You're viewing this | 1000 TABLET in 1 BOTTLE (70771-1083-0) | 2017-09-14 | Active |
| 70771-1083-01 | 100 TABLET in 1 BOTTLE (70771-1083-1) | 2017-09-14 | Active |
| 70771-1083-03 | 30 TABLET in 1 BOTTLE (70771-1083-3) | 2017-09-14 | Active |
| 70771-1083-05 | 500 TABLET in 1 BOTTLE (70771-1083-5) | 2017-09-14 | Active |
| 70771-1083-06 | 60 TABLET in 1 BOTTLE (70771-1083-6) | 2017-09-14 | Active |
| 70771-1083-08 | 10 BLISTER PACK in 1 CARTON (70771-1083-8) / 10 TABLET in 1 BLISTER PACK | 2017-09-14 | Active |
| 70771-1083-09 | 90 TABLET in 1 BOTTLE (70771-1083-9) | 2017-09-14 | Active |
Pack size FAQ
What quantity is in NDC 70771-1083-00?
What is the difference between NDC 70771-1083-00 and NDC 70771-1083-03?
What NDC number is used to bill for this package of Diflunisal 500 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
Cardiovascular Risk • Nonsteroidal anti-inflammatory drugs (NSAIDs) cause an increased risk of serious cardiovascular thrombotic events, including myocardial infarction and stroke, which can be fatal. This risk may occur early in treatment and may increase with duration of use (see WARNINGS and PRECAUTIONS ). • Diflunisal tablets are contraindicated in the setting of coronary artery bypass graft (CABG) surgery (see CONTRAINDICATIONS and WARNINGS ). Gastrointestinal Risk • NSAIDs cause an increased risk of serious gastrointestinal adverse events including bleeding, ulceration, and perforation of the stomach or intestines, which can be fatal.
These events can occur at any time during use and without warning symptoms. Elderly patients are at greater risk for serious gastrointestinal events (see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Carefully consider the potential benefits and risks of diflunisal tablets and other treatment options before deciding to use diflunisal tablets. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). Diflunisal tablets are indicated for acute or long-term use for symptomatic treatment of the following: 1.
Mild to moderate pain 2. Osteoarthritis 3. Rheumatoid arthritis
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Carefully consider the potential benefits and risks of diflunisal tablets and other treatment options before deciding to use diflunisal tablets. Use the lowest effective dose for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). After observing the response to initial therapy with diflunisal tablets, the dose and frequency should be adjusted to suit an individual patient's needs.
Concentration-dependent pharmacokinetics prevail when diflunisal is administered; a doubling of dosage produces a greater than doubling of drug accumulation. The effect becomes more apparent with repetitive doses. For mild to moderate pain, an initial dose of 1000 mg followed by 500 mg every 12 hours is recommended for most patients.
Following the initial dose, some patients may require 500 mg every 8 hours. A lower dosage may be appropriate depending on such factors as pain severity, patient response, weight, or advanced age; for example, 500 mg initially, followed by 250 mg every 8 to 12 hours. For osteoarthritis and rheumatoid arthritis, the suggested dosage range is 500 mg to 1000 mg daily in two divided doses.
The dosage of diflunisal may be increased or decreased according to patient response. Maintenance doses higher than 1500 mg a day are not recommended. Tablets should be swallowed whole, not crushed or chewed.
⛔ Contraindications ▾
CONTRAINDICATIONS Diflunisal tablets are contraindicated in patients with known hypersensitivity to diflunisal or the excipients (see DESCRIPTION ). Diflunisal tablets should not be given to patients who have experienced asthma, urticaria, or allergic-type reactions after taking aspirin or other NSAIDs. Severe, rarely fatal, anaphylactic/analphylactoid reactions to NSAIDs have been reported in such patients (see WARNINGS , Anaphylactic/Anaphylactoid Reactions and PRECAUTIONS , Preexisting Asthma ).
Diflunisal tablets are contraindicated in the setting of coronary artery bypass graft (CABG) surgery (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Cardiovascular Effects Cardiovascular Thrombotic Events Clinical trials of several COX-2 selective and nonselective NSAIDs of up to three years duration have shown an increased risk of serious cardiovascular (CV) thrombotic events, including myocardial infarction (MI) and stroke, which can be fatal. Based on available data, it is unclear that the risk for CV thrombotic events is similar for all NSAIDs. The relative increase in serious CV thrombotic events over baseline conferred by NSAID use appears to be similar in those with and without known CV disease or risk factors for CV disease.
However, patients with known CV disease or risk factors had a higher absolute incidence of excess serious CV thrombotic events, due to their increased baseline rate. Some observational studies found that this increased risk of serious CV thrombotic events began as early as the first weeks of treatment. The increase in CV thrombotic risk has been observed most consistently at higher doses.
To minimize the potential risk for an adverse CV event in NSAID-treated patients, use the lowest effective dose for the shortest duration possible. Physicians and patients should remain alert for the development of such events, throughout the entire treatment course, even in the absence of previous CV symptoms. Patients should be informed about the symptoms of serious CV events and the steps to take if they occur.
There is no consistent evidence that concurrent use of aspirin mitigates the increased risk of serious CV thrombotic events associated with NSAID use. The concurrent use of aspirin and an NSAID, such as diflunisal, increases the risk of serious gastrointestinal (GI) events (see WARNINGS) . Status Post Coronary Artery Bypass Graft (CABG) Surgery Two large, controlled clinical trials of a COX-2 selective NSAID for the treatment of pain in the first 10–14 days following CABG surgery found an increased incidence of myocardial infarction and stroke.
NSAIDs are contraindicated in the setting of CABG (see CONTRAINDICATIONS) . Post-MI Patients Observational studies conducted in the Danish National Registry have demonstrated that patients treated with NSAIDs in the post-MI period were at increased risk of reinfarction, CV-related death, and all-cause mortality beginning in the first week of treatment. In this same cohort, the incidence of death in the first year post MI was 20 per 100 person years in NSAID-treated patients compared to 12 per 100 person years in non-NSAID exposed patients.
Although the absolute rate of death declined somewhat after the first year post-MI, the increased relative risk of death in NSAID users persisted over at least the next four years of follow-up. Avoid the use of diflunisal tablets in patients with a recent MI unless the benefits are expected to outweigh the risk of recurrent CV thrombotic events. If diflunisal tablets is used in patients with a recent MI, monitor patients for signs of cardiac ischemia.
Hypertension NSAIDs, including diflunisal tablets, can lead to onset of new hypertension or worsening of preexisting hypertension, either of which may contribute to the increased incidence of CV events. Patients taking thiazides or loop diuretics may have impaired response to these therapies when taking NSAIDs. NSAIDs, including diflunisal tablets, should be used with caution in patients with hypertension.
Blood pressure (BP) should be monitored closely during the initiation of NSAID treatment and throughout the course of therapy. Heart Failure and Edema The Coxib and traditional NSAID Trialists' Collaboration meta-analysis of randomized controlled trials demonstrated an approximately two-fold increase in hospitalizations for heart failure in COX-2 selective-treated patients and nonselective NSAID-treated patients compared to placebo-treated patients. In a Danish National Registry study of patients with heart failure, NSAID use increased the risk of MI, hospitalization for heart failure, and death.
Additionally, fluid…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The adverse reactions observed in controlled clinical trials encompass observations in 2,427 patients. Listed below are the adverse reactions reported in the 1,314 of these patients who received treatment in studies of two weeks or longer. Five hundred thirteen patients were treated for at least 24 weeks, 255 patients were treated for at least 48 weeks, and 46 patients were treated for 96 weeks.
In general, the adverse reactions listed below were 2 to 14 times less frequent in the 1,113 patients who received short-term treatment for mild to moderate pain. Incidence Greater Than 1% Gastrointestinal The most frequent types of adverse reactions occurring with diflunisal are gastrointestinal: these include nausea*, vomiting, dyspepsia*, gastrointestinal pain*, diarrhea*, constipation, and flatulence. Psychiatric Somnolence, insomnia.
Central Nervous System Dizziness. Special Senses Tinnitus. Dermatologic Rash*.
Miscellaneous Headache*, fatigue/tiredness. * Incidence between 3% and 9%. Those reactions occurring in 1% to 3% are not marked with an asterisk. Incidence Less Than 1 in 100 The following adverse reactions, occurring less frequently than 1 in 100, were reported in clinical trials or since the drug was marketed.
The probability exists of a causal relationship between diflunisal and these adverse reactions. Dermatologic Erythema multiforme, exfoliative dermatitis, Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), fixed drug reaction (FDE), urticaria, pruritus, sweating, dry mucous membranes, stomatitis, and photosensitivity. Gastrointestinal Peptic ulcer, gastrointestinal bleeding, anorexia, eructation, gastrointestinal perforation, gastritis.
Liver function abnormalities; jaundice, sometimes with fever; cholestasis; hepatitis. Hematologic Thrombocytopenia; agranulocytosis; hemolytic anemia. Genitourinary Dysuria; renal impairment, including renal failure; interstitial nephritis; hematuria; proteinuria.
Psychiatric Nervousness, depression, hallucinations, confusion, disorientation. Central Nervous System Vertigo; light-headedness; paresthesias. Special Senses Transient visual disturbances including blurred vision.
Hypersensitivity Reactions Acute anaphylactic reaction with bronchospasm; angioedema; flushing. Hypersensitivity vasculitis. Hypersensitivity syndrome (see PRECAUTIONS ).
Miscellaneous Asthenia, edema. Causal Relationship Unknown Other reactions have been reported in clinical trials or since the drug was marketed, but occurred under circumstances where a causal relationship could not be established. However, in these rarely reported events, that possibility cannot be excluded.
Therefore, these observations are listed to serve as alerting information to physicians. Respiratory Dyspnea. Cardiovascular Palpitation, syncope.
Musculoskeletal Muscle cramps. Genitourinary Nephrotic syndrome. Special Senses Hearing loss.
Miscellaneous Chest pain. A rare occurrence of fulminant necrotizing fasciitis, particularly in association with Group A β -hemolytic streptococcus, has been described in persons treated with non-steroidal anti-inflammatory agents, including diflunisal, sometimes with fatal outcome (see also PRECAUTIONS, General ). Potential Adverse Effects In addition, a variety of adverse effects not observed with diflunisal in clinical trials or in marketing experience, but reported with other non-steroidal analgesic/anti-inflammatory agents should be considered potential adverse effects of diflunisal.
🔄 Drug Interactions ▾
Drug Interactions ACE-inhibitors and Angiotensin II Anagonists Reports suggest that NSAIDs may diminish the antihypertensive effect of ACE-inhibitors and angiotensin II antagonists. These interactions should be given consideration in patients taking NSAIDs concomitantly with ACE-inhibitors or angiotensin II antagonists. In some patients with compromised renal function, the coadministration of an NSAID and an ACE-inhibitor or an angiotensin II antagonist may result in further deterioration of renal function, including possible acute renal failure, which is usually reversible.
Acetaminophen In normal volunteers, concomitant administration of diflunisal and acetaminophen resulted in an approximate 50% increase in plasma levels of acetaminophen. Acetaminophen had no effect on plasma levels of diflunisal. Since acetaminophen in high doses has been associated with hepatotoxicity, concomitant administration of diflunisal tablets and acetaminophen should be used cautiously, with careful monitoring of patients.
Concomitant administration of diflunisal and acetaminophen in dogs, but not in rats, at approximately 2 times the recommended maximum human therapeutic dose of each (40 to 52 mg/kg/day of diflunisal/acetaminophen), resulted in greater gastrointestinal toxicity than when either drug was administered alone. The clinical significance of these findings has not been established. Antacids Concomitant administration of antacids may reduce plasma levels of diflunisal.
This effect is small with occasional doses of antacids, but may be clinically significant when antacids are used on a continuous schedule. Aspirin When diflunisal is administered with aspirin, its protein binding is reduced, although the clearance of free diflunisal is not altered. The clinical significance of this interaction is not known; however, as with other NSAIDs, concomitant administration of diflunisal tablets and aspirin is not generally recommended because of the potential of increased adverse effects.
In normal volunteers, a small decrease in diflunisal levels was observed when multiple doses of diflunisal and aspirin were administered concomitantly. Cyclosporine Administration of non-steroidal anti-inflammatory drugs concomitantly with cyclosporine has been associated with an increase in cyclosporine-induced toxicity, possibly due to decreased synthesis of renal prostacyclin. NSAIDs should be used with caution in patients taking cyclosporine, and renal function should be carefully monitored.
Diuretics Clinical studies, as well as postmarketing observations, have shown that diflunisal can reduce the natriuretic effect of furosemide and thiazides in some patients. This response has been attributed to inhibition of renal prostaglandin synthesis. In normal volunteers, concomitant administration of diflunisal and hydrochlorothiazide resulted in significantly increased plasma levels of hydrochlorothiazide.
Diflunisal decreased the hyperuricemic effect of hydrochlorothiazide. During concomitant therapy with NSAIDs, the patient should be observed closely for signs of renal failure (see WARNINGS , Renal Effects ), as well as to assure diuretic efficacy. Lithium NSAIDs have produced an elevation of plasma lithium levels and a reduction in renal lithium clearance.
The mean minimum lithium concentration increased 15% and the renal clearance was decreased by approximately 20%. These effects have been attributed to inhibition of renal prostaglandin synthesis by the NSAID. Thus, when NSAIDs and lithium are administered concurrently, subjects should be observed carefully for signs of lithium toxicity.
Methotrexate NSAIDs have been reported to competitively inhibit methotrexate accumulation in rabbit kidney slices. This may indicate that they could enhance the toxicity of methotrexate. Caution should be used when NSAIDs are administered concomitantly with methotrexate.
NSAIDs The administration of diflunisal to normal volunteers receiving indomethacin decreased the renal clear…
🤰 Pregnancy ▾
Pregnancy In late pregnancy, as with other NSAIDs, diflunisal tablets should be avoided because they may cause premature closure of the ductus arteriosus.
Pregnancy Teratogenic Effects Pregnancy category C A dose of 60 mg/kg/day of diflunisal (equivalent to two times the maximum human dose) was maternotoxic, embryotoxic, and teratogenic in rabbits. In three of six studies in rabbits, evidence of teratogenicity was observed at doses ranging from 40 to 50 mg/kg/day. Teratology studies in mice, at doses up to 45 mg/kg/day, and in rats at doses up to 100 mg/kg/day, revealed no harm to the fetus due to diflunisal.
Aspirin and other salicylates have been shown to be teratogenic in a wide variety of species, including the rat and rabbit, at doses ranging from 50 to 400 mg/kg/day (approximately one to eight times the human dose). Animal reproduction studies are not always predictive of human response. There are no adequate and well controlled studies with diflunisal in pregnant women.
Diflunisal tablets should be used in pregnancy only if the potential benefit justifies the potential risk to the fetus. Nonteratogenic Effects Because of the known effects of non-steroidal anti-inflammatory drugs on the fetal cardiovascular system (closure of ductus arteriosus), use during pregnancy (particularly late pregnancy) should be avoided. The known effects of drugs of this class on the human fetus during the third trimester of pregnancy include: constriction of the ductus arteriosus prenatally, tricuspid incompetence, and pulmonary hypertension; non-closure of the ductus arteriosus postnatally which may be resistant to medical management; myocardial degenerative changes, platelet dysfunction with resultant bleeding, intracranial bleeding, renal dysfunction or failure, renal injury/dysgenesis which may result in prolonged or permanent renal failure, oligohydramnios, gastrointestinal bleeding or perforation, and increased risk of necrotizing enterocolitis.
In rats at a dose of one and one-half times the maximum human dose, there was an increase in the average length of gestation. Similar increases in the length of gestation have been observed with aspirin, indomethacin, and phenylbutazone, and may be related to inhibition of prostaglandin synthetase. Labor and Delivery In rat studies with NSAIDs, as with other drugs known to inhibit prostaglandin synthesis, an increased incidence of dystocia, delayed parturition, and decreased pup survival occurred.
The effects of diflunisal tablets on labor and delivery in pregnant women are unknown. Nursing Mothers Diflunisal is excreted in human milk in concentrations of 2 to 7% of those in plasma. Because of the potential for serious adverse reactions in nursing infants from diflunisal, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
Pediatric Use Safety and effectiveness of diflunisal in pediatric patients below the age of 12 have not been established. Use of diflunisal tablets in pediatric patients below the age of 12 is not recommended. The adverse effects observed following diflunisal administration to neonatal animals appear to be species, age, and dose-dependent.
At dose levels approximately 3 times the usual human therapeutic dose, both aspirin (200 to 400 mg/kg/day) and diflunisal (80 mg/kg/day) resulted in death, leukocytosis, weight loss, and bilateral cataracts in neonatal (4 to 5 day-old) beagle puppies after 2 to 10 doses. Administration of an 80 mg/kg/day dose of diflunisal to 25 day-old puppies resulted in lower mortality, and did not produce cataracts. In newborn rats, a 400 mg/kg/day dose of aspirin resulted in increased mortality and some cataracts, whereas the effects of diflunisal administration at doses up to 140 mg/kg/day were limited to a decrease in average body weight gain.
Geriatric Use As with any NSAID, caution should be exercised in treating the elderly (65 years and older) since adv…
🆘 Overdosage ▾
OVERDOSAGE Cases of overdosage have occurred and deaths have been reported. Most patients recovered without evidence of permanent sequelae. The most common signs and symptoms observed with overdosage were drowsiness, vomiting, nausea, diarrhea, hyperventilation, tachycardia, sweating, tinnitus, disorientation, stupor, and coma.
Diminished urine output and cardiorespiratory arrest have also been reported. The lowest dosage of diflunisal at which a death has been reported was 15 grams without the presence of other drugs. In a mixed drug overdose, ingestion of 7.5 grams of diflunisal resulted in death.
In the event of overdosage, the stomach should be emptied by inducing vomiting or by gastric lavage, and the patient carefully observed and given symptomatic and supportive treatment. Because of the high degree of protein binding, hemodialysis may not be effective. The oral LD 50 of the drug is 500 mg/kg and 826 mg/kg in female mice and female rats, respectively.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Action Diflunisal is a non-steroidal drug with analgesic, anti-inflammatory and antipyretic properties. It is a peripherally-acting non-narcotic analgesic drug. Habituation, tolerance, and addiction have not been reported.
Diflunisal is a difluorophenyl derivative of salicylic acid. Chemically, diflunisal differs from aspirin (acetylsalicylic acid) in two respects. The first of these two is the presence of a difluorophenyl substituent at carbon 1.
The second difference is the removal of the O -acetyl group from the carbon 4 position. Diflunisal is not metabolized to salicylic acid, and the fluorine atoms are not displaced from the difluorophenyl ring structure. The precise mechanism of the analgesic and anti-inflammatory actions of diflunisal is not known.
Diflunisal is a prostaglandin synthetase inhibitor. In animals, prostaglandins sensitize afferent nerves and potentiate the action of bradykinin in inducing pain. Since prostaglandins are known to be among the mediators of pain and inflammation, the mode of action of diflunisal may be due to a decrease of prostaglandins in peripheral tissues.
Pharmacokinetics and Metabolism Diflunisal is rapidly and completely absorbed following oral administration with peak plasma concentrations occurring between 2 to 3 hours. The drug is excreted in the urine as two soluble glucuronide conjugates accounting for about 90% of the administered dose. Little or no diflunisal is excreted in the feces.
Diflunisal appears in human milk in concentrations of 2 to 7% of those in plasma. More than 99% of diflunisal in plasma is bound to proteins. As is the case with salicylic acid, concentration-dependent pharmacokinetics prevail when diflunisal is administered; a doubling of dosage produces a greater than doubling of drug accumulation.
The effect becomes more apparent with repetitive doses. Following single doses, peak plasma concentrations of 41 ± 11 mcg/mL (mean ± S.D.) were observed following 250 mg doses, 87 ± 17 mcg/mL were observed following 500 mg and 124 ± 11 mcg/mL following single 1000 mg doses. However, following administration of 250 mg b.i.d., a mean peak level of 56 ± 14 mcg/mL was observed on day 8, while the mean peak level after 500 mg b.i.d. for 11 days was 190 ± 33 mcg/mL.
In contrast to salicylic acid which has a plasma half-life of 2 1/2 hours, the plasma half-life of diflunisal is 3 to 4 times longer (8 to 12 hours), because of a difluorophenyl substituent at carbon 1. Because of its long half-life and nonlinear pharmacokinetics, several days are required for diflunisal plasma levels to reach steady state following multiple doses. For this reason, an initial loading dose is necessary to shorten the time to reach steady-state levels, and 2 to 3 days of observation are necessary for evaluating changes in treatment regimens if a loading dose is not used.
Studies in baboons to determine passage across the blood-brain barrier have shown that only small quantities of diflunisal, under normal or acidotic conditions are transported into the cerebrospinal fluid (CSF). The ratio of blood/CSF concentrations after intravenous doses of 50 mg/kg or oral doses of 100 mg/kg of diflunisal was 100:1. In contrast, oral doses of 500 mg/kg of aspirin resulted in a blood/CSF ratio of 5:1.
Mild to Moderate Pain Diflunisal is a peripherally-acting analgesic agent with a long duration of action. Diflunisal produces significant analgesia within 1 hour and maximum analgesia within 2 to 3 hours. Consistent with its long half-life, clinical effects of diflunisal mirror its pharmacokinetic behavior, which is the basis for recommending a loading dose when instituting therapy.
Patients treated with diflunisal, on the first dose, tend to have a slower onset of pain relief when compared with drugs achieving comparable peak effects. However, diflunisal produces longer lasting responses than the comparative agents. Comparative single dose clinical studies have established the analgesic effica…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Diflunisal Tablets USP, 500 mg are light blue to blue color, capsule shaped, biconvex, coated tablets, debossed with "530" on one side and plain on the other side and are supplied as follows: NDC 70771-1083-3 in bottle of 30 tablets NDC 70771-1083-6 in bottle of 60 tablets NDC 70771-1083-9 in bottle of 90 tablets NDC 70771-1083-1 in bottle of 100 tablets NDC 70771-1083-5 in bottle of 500 tablets NDC 70771-1083-0 in bottle of 1000 tablets NDC 70771-1083-8 in unit-dose blister cartons of 100 (10 X 10) unit-dose tablets Storage Store at 20° to 25°C (68° to 77°F) [See USP Controlled Room Temperature].
Dispense in a tight container (USP). Call your doctor for medical advice about side effects. You may report side effects to FDA at 1-800-FDA-1088.
Manufactured by: Zydus Lifesciences Limited., Baddi-173205, India Rev.: 07/24
📋 Description ▾
DESCRIPTION Diflunisal is 2',4'-difluoro-4-hydroxy-3-biphenylcarboxylic acid. Its structural formula is: C 13 H 8 F 2 O 3 M.W. 250.20 Diflunisal is a stable, white to off-white, crystalline compound with a melting point of 211° to 213°C.
It is practically insoluble in hexane and water. It is soluble in most organic solvents including acetone and ethyl acetate and it is slightly soluble in chloroform, carbon tetrachloride and methylene chloride. Each diflunisal tablet intended for oral administration contains 500 mg of diflunisal.
In addition, each tablet contains the following inactive ingredients: colloidal silicon dioxide, croscarmellose sodium, hypromellose, microcrystalline cellulose, pregelatinised starch and sodium stearyl fumarate. Additionally, each diflunisal tablets contain opadry blue 03B505010 which contains FD&C blue #2, FD&C yellow #6, hypromellose, polyethylene glycol and titanium dioxide. Structure
💬 Information for Patients ▾
INFORMATION FOR PATIENTS Patients should be informed of the following information before initiating therapy with an NSAID and periodically during the course of ongoing therapy. Patients should also be encouraged to read the NSAID Medication Guide that accompanies each prescription dispensed. 1.
Cardiovascular Thrombotic Events Advise patients to be alert for the symptoms of cardiovascular thrombotic events, including chest pain, shortness of breath, weakness, or slurring of speech, and to report any of these symptoms to their health care provider immediately (see WARNINGS ). 2. Diflunisal tablets, like other NSAIDs, can cause GI discomfort and, rarely, serious GI side effects, such as ulcers and bleeding, which may result in hospitalization and even death.
Although serious GI tract ulcerations and bleeding can occur without warning symptoms, patients should be alert for the signs and symptoms of ulcerations and bleeding, and should ask for medical advice when observing any indicative signs or symptoms including epigastric pain, dyspepsia, melena, and hematemesis. Patients should be apprised of the importance of this follow-up (see WARNINGS, Gastrointestinal Effects - Risk of Ulceration, Bleeding, and Perforation ). 3.
Diflunisal tablets, like other NSAIDs, can cause serious skin side effects such as exfoliative dermatitis, SJS, and TEN, which may result in hospitalization and even death. Although serious skin reactions may occur without warning, patients should be alert for the signs and symptoms of skin rash and blisters, fever, or other signs of hypersensitivity such as itching, and should ask for medical advice when observing any indicative signs or symptoms. Patients should be advised to stop the drug immediately if they develop any type of rash and contact their physicians as soon as possible.
4. Heart Failure And Edema Advise patients to be alert for the symptoms of congestive heart failure including shortness of breath, unexplained weight gain, or edema and to contact their healthcare provider if such symptoms occur (see WARNINGS ). 5.
Patients should be informed of the warning signs and symptoms of hepatotoxicity (e.g., nausea, fatigue, lethargy, pruritus, jaundice, right upper quadrant tenderness, and "flu-like" symptoms). If these occur, patients should be instructed to stop therapy and seek immediate medical therapy. 6.
Patients should be informed of the signs of an anaphylactic/anaphylactoid reaction (e.g., difficulty breathing, swelling of the face or throat). If these occur, patients should be instructed to seek immediate emergency help (see WARNINGS ). 7.
In late pregnancy, as with other NSAIDs, diflunisal tablets should be avoided because they may cause premature closure of the ductus arteriosus. Laboratory Tests Because serious GI tract ulcerations and bleeding can occur without warning symptoms, physicians should monitor for signs or symptoms of GI bleeding. Patients on long-term treatment with NSAIDs, should have their CBC and a chemistry profile checked periodically.
If clinical signs and symptoms consistent with liver or renal disease develop, systemic manifestations occur (e.g., eosinophilia, rash, etc.) or if abnormal liver tests persist or worsen, diflunisal tablets should be discontinued. Drug Interactions ACE-inhibitors and Angiotensin II Anagonists Reports suggest that NSAIDs may diminish the antihypertensive effect of ACE-inhibitors and angiotensin II antagonists. These interactions should be given consideration in patients taking NSAIDs concomitantly with ACE-inhibitors or angiotensin II antagonists.
In some patients with compromised renal function, the coadministration of an NSAID and an ACE-inhibitor or an angiotensin II antagonist may result in further deterioration of renal function, including possible acute renal failure, which is usually reversible. Acetaminophen In normal volunteers, concomitant administration of diflunisal and acetaminophen resulted in an approximate 50% increase in plasma…
💬 Medication Guide ▾
Medication Guide for Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) Rx only (See the end of this Medication Guide for a list of prescription NSAID medicines.) What is the most important information I should know about medicines called Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)? Increased risk of a heart attack or stroke that can lead to death. The risk may happen early in treatment and may increase: with increasing doses of NSAIDs with longer use of NSAIDs Do not take NSAIDs right before or after a heart surgery called a "coronary artery bypass graft (CABG)." Avoid taking NSAIDs after a recent heart attack, unless your healthcare provider tells you to.
You may have an increased risk of another heart attack if you take NSAIDs after a recent heart attack. NSAID medicines can cause ulcers and bleeding in the stomach and intestines at any time during treatment. Ulcers and bleeding: can happen without warning symptoms may cause death The chance of a person getting an ulcer or bleeding increases with: taking medicines called "corticosteroids" and "anticoagulants" longer use smoking drinking alcohol older age having poor health NSAID medicines should only be used: exactly as prescribed at the lowest dose possible for your treatment for the shortest time needed What are Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)?
NSAID medicines are used to treat pain and redness, swelling, and heat (inflammation) from medical conditions such as: different types of arthritis menstrual cramps and other types of short-term pain Who should not take a Non-Steroidal Anti-Inflammatory Drug (NSAID)? Do not take an NSAID medicine: if you had an asthma attack, hives, or other allergic reaction with aspirin or any other NSAID medicine right before or after heart bypass surgery Tell your healthcare provider: about all of your medical conditions. about all of the medicines you take.
NSAIDs and some other medicines can interact with each other and cause serious side effects. Keep a list of your medicines to show to your healthcare provider and pharmacist. if you are pregnant. NSAID medicines should not be used by pregnant women late in their pregnancy. if you are breastfeeding.
Talk to your doctor. if you have high blood pressure What are the possible side effects of Non-Steroidal Anti-Inflammatory Drugs (NSAIDs)? Serious Side effects include: Other side effects include: • heart attack • stomach pain • stroke • constipation • high blood pressure • diarrhea • heart failure from body swelling (fluid retention) • gas • kidney problems including kidney failure • heartburn • bleeding and ulcers in the stomach and intestine • nausea • low red blood cells (anemia) • vomiting • life-threatening skin reactions • dizziness • life-threatening allergic reactions • liver problems including liver failure • asthma attacks in people who have asthma Get emergency help right away if you have any of the following symptoms: shortness of breath or trouble breathing chest pain weakness in one part or side of your body slurred speech swelling of the face or throat Stop your NSAID medicine and call your healthcare provider right away if you have any of the following symptoms: nausea more tired or weaker than usual itching your skin or eyes look yellow stomach pain flu-like symptoms vomit blood there is blood in your bowel movement or it is black and sticky like tar unusual weight gain skin rash or blisters with fever swelling of the arms and legs, hands and feet These are not all the side effects with NSAID medicines.
Talk to your healthcare provider or pharmacist for more information about NSAID medicines. Other information about Non-Steroidal Anti-Inflammatory Drugs (NSAIDs) Aspirin is an NSAID medicine but it does not increase the chance of a heart attack. Aspirin can cause bleeding in the brain, stomach, and intestines.
Aspirin can also cause ulcers in the stomach and intestines. Some of these NSAID medicines are sold in lower doses without a prescription (over-the-counter).…