
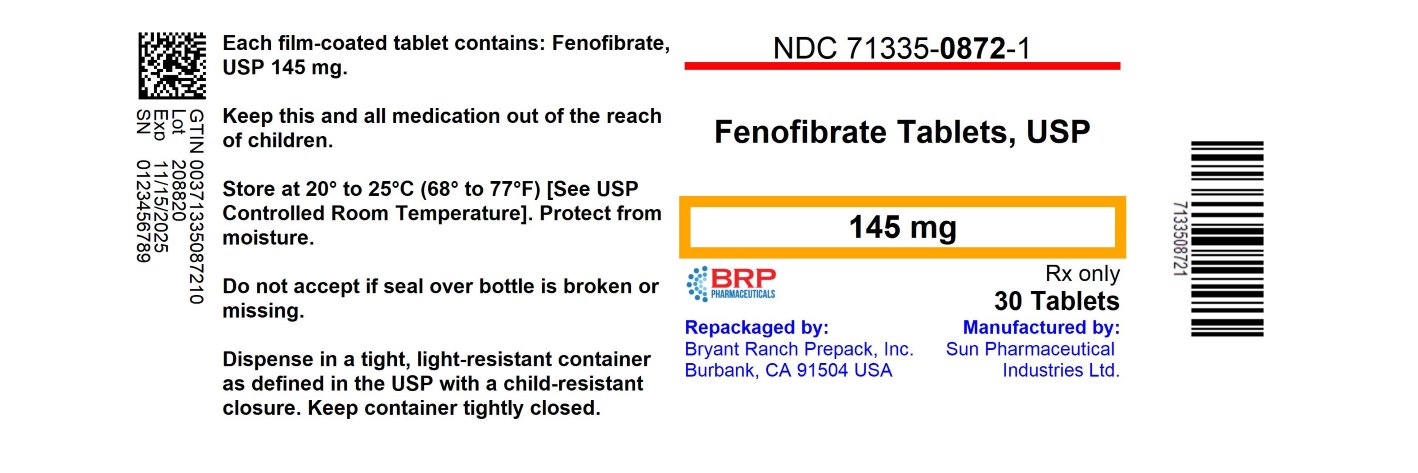
Fenofibrate 145 mg Tablet, Film Coated, 30-count — NDC 71335-0872-1 (Billing 71335-0872-01)
This is a package of 30 tablets of Fenofibrate 145 mg Tablet, Film Coated from Bryant Ranch Prepack, marketed since Jun 2018 and currently FDA-listed. It is the main listing for this product, which comes in 3 package sizes.
Other active recalls for Fenofibrate (different manufacturers) — 2 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
- RxCUI (RxNorm): 477560
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Peroxisome Proliferator-activated Receptor alpha Agonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Fenofibrate is used to reduce the amount of cholesterol (a fat-like substance that can build up in blood vessels leading to heart attack or strokes or other medical conditions) and triglycerides (other fatty substances) in the blood. Fenofibrate is in a class of medications called fibrates. It works by speeding the natural processes that remove cholesterol from the body.
Read the full MedlinePlus article ↗- It helps lower triglycerides, and in some products LDL cholesterol, while raising HDL in some cases. It works alongside a healthy diet, not instead of one. Which uses apply depends...
- It depends on the product. Tricor tablets and some capsules like Antara can be taken with or without food, while Lipofen should be taken with food. Check your label or ask me, and...
- Common ones include abdominal pain, back pain, headache, nausea, constipation and a stuffy nose. It can also raise liver enzymes, which is why you will need blood tests.
- Call right away for muscle pain or weakness, dark urine, yellow skin or eyes, severe belly pain, or leg swelling and chest pain. Seek emergency help for facial swelling, trouble br...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Fenofibrate — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3700 | $11.10 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 2, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 71335-0872-01 You're viewing this Main listing | 30 TABLET, FILM COATED in 1 BOTTLE | 2019-03-07 | — | Active |
| 71335-0872-02 71335-0872-2 | 90 TABLET, FILM COATED in 1 BOTTLE | 2018-06-20 | — | Active |
| 71335-0872-03 71335-0872-3 | 28 TABLET, FILM COATED in 1 BOTTLE | 2021-12-27 | — | Active |
You're viewing one of 3 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 71335-0872-03?
What NDC number is used to bill for this package of Fenofibrate 145 mg Tablet, Film Coated?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Fenofibrate 145 mg 63304-0449-05 | Sun | 500 tablets | $0.118 | — | FDA listed | — |
| Fenofibrate 145 mg 00378-3066-05 | Mylan | 500 tablets | $0.120 | AB | Availability likely | — |
| Fenofibrate 145 mg 00904-7480-04 | Major | 30 tablets | $0.120 | AB | Availability likely | — |
| Fenofibrate 145 mg 43547-0431-09 | Solco | 90 tablets | $0.120 | AB | Availability likely | — |
| Fenofibrate 145 mg 51079-0608-20 | Mylan | 1 tablet | $0.120 | AB | Availability likely | — |
| Fenofibrate 145 mg 60687-0629-01 | American | 100 tablets | $0.120 | AB | Availability likely | — |
| Fenofibrate 145 mg 68180-0389-02 | Lupin | 500 tablets | $0.120 | AB | Availability likely | — |
| Fenofibrate 145 mg 82009-0060-90 | QUALLENT | 90 tablets | $0.120 | AB | Availability likely | — |
| Fenofibrate 145 mg 00904-7161-04 | Major | 30 tablets | $0.120 | AB | Discontinued | — |
| fenofibrate 145 mg 69315-0288-05 | Leading | 500 tablets | $0.140 | AB | FDA listed | — |
| Fenofibrate 145 mg 00615-8530-39 | NCS | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 31722-0596-30 | Camber | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 33342-0340-07 | Macleods | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 35561-0250-03 | Bostal | 500 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 42291-0045-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| fenofibrate 145 mg 42385-0951-11 | Laurus | 1000 tablets | — | AB | FDA listed | — |
| Tricor 145 mg 43353-0272-30 | Aphena | 30 tablets | — | — | Discontinued | — |
| Fenofibrate 145 mg 46708-0361-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 48433-0040-20 | Safecor | 1 tablet | — | AB | FDA listed | — |
| Tricor 145 mg 50090-2899-02 | A-S | 90 tablets | — | — | FDA listed | — |
| Fenofibrate 145 mg 50090-3044-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 50090-4031-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 50090-5796-00 | A-S | 90 tablets | — | — | FDA listed | — |
| Fenofibrate 145 mg 50090-6934-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 50090-7242-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 51407-0006-90 | Golden | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 51655-0234-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 51655-0433-52 | Northwind | 30 tablets | — | — | FDA listed | — |
| Fenofibrate 145 mg 62332-0361-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 65862-0769-01 | Aurobindo | 100 tablets | — | AB | FDA listed | — |
| fenofibrate 145 mg 68071-1712-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 68071-5101-09 | NuCare | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 68788-4006-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 68788-8106-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 69097-0458-02 | Cipla | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 69238-1261-09 | Amneal | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 70518-4672-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mgthis 71335-0872-01 | Bryant | 30 tablets | — | — | FDA listed | — |
| Fenofibrate 145 mg 71335-2016-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| fenofibrate 145 mg 71335-2413-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 71335-2688-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 73190-0016-90 | AvKARE | 90 tablets | — | AB | FDA listed | — |
| Fenofibrate 145 mg 82868-0018-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 68401960MK
Crospovidone is a synthetic polymer made from polyvinylpyrrolidone. It acts as a disintegrant, helping tablets break apart quickly in the stomach so the medicine dissolves and absorbs into the body.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 1DI56QDM62
A natural fatty substance from soybeans that helps mix oil and water-based ingredients together. It acts as an emulsifier and lubricant in medicines to improve texture and help the product break down properly in your body.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 532B59J990
Polyvinyl alcohol is a synthetic polymer made from plant-derived materials. It's used as a binder to hold ingredients together, a film-former in coatings, and a thickener in liquid formulations.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII TTV12P4NEE
Xanthan gum is a thickening and stabilizing ingredient made from fermented corn or other sugars. It's added to medicines to improve texture, prevent separation of liquids and solids, and help the product stay consistent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Fenofibrate tablets are a peroxisome proliferator-activated receptor (PPAR) alpha agonist indicated as an adjunct to diet: • To reduce elevated LDL-C, Total-C, TG and Apo B, and to increase HDL-C in adult patients with primary hypercholesterolemia or mixed dyslipidemia (1.1). • For treatment of adult patients with severe hypertriglyceridemia (1.2). Limitations of Use: Fenofibrate was not shown to reduce coronary heart disease morbidity and mortality in patients with type 2 diabetes mellitus (5.1).
1.1Primary Hypercholesterolemia or Mixed Dyslipidemia Fenofibrate tablets are indicated as adjunctive therapy to diet to reduce elevated low-density lipoprotein cholesterol (LDL-C), total cholesterol (Total-C), Triglycerides and apolipoprotein B (Apo B), and to increase high-density lipoprotein cholesterol (HDL-C) in adult patients with primary hypercholesterolemia or mixed dyslipidemia.
1.2Severe Hypertriglyceridemia Fenofibrate tablets are also indicated as adjunctive therapy to diet for treatment of adult patients with severe hypertriglyceridemia. Improving glycemic control in diabetic patients showing fasting chylomicronemia will usually obviate the need for pharmacologic intervention. Markedly elevated levels of serum triglycerides (e.g. > 2,000 mg/dL) may increase the risk of developing pancreatitis.
The effect of fenofibrate therapy on reducing this risk has not been adequately studied.
1.3Important Limitations of Use Fenofibrate at a dose equivalent to 145 mg of fenofibrate tablets was not shown to reduce coronary heart disease morbidity and mortality in a large, randomized controlled trial of patients with type 2 diabetes mellitus [see Warnings and Precautions (5.1)] .
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION • Primary hypercholesterolemia or mixed dyslipidemia: Initial dose of 145 mg once daily (2.2). • Severe hypertriglyceridemia: Initial dose of 48 to 145 mg once daily. Maximum dose is 145 mg (2.3). • Renally impaired patients: Initial dose of 48 mg once daily (2.4). • Geriatric patients: Select the dose on the basis of renal function (2.5). • Maybe taken without regard to meals (2.1).
2.1General Considerations Patients should be placed on an appropriate lipid-lowering diet before receiving fenofibrate tablets, and should continue this diet during treatment with fenofibrate tablets. Fenofibrate tablets can be given without regard to meals. The initial treatment for dyslipidemia is dietary therapy specific for the type of lipoprotein abnormality.
Excess body weight and excess alcoholic intake may be important factors in hypertriglyceridemia and should be addressed prior to any drug therapy. Physical exercise can be an important ancillary measure. Diseases contributory to hyperlipidemia, such as hypothyroidism or diabetes mellitus should be looked for and adequately treated.
Estrogen therapy, thiazide diuretics and beta-blockers, are sometimes associated with massive rises in plasma triglycerides, especially in subjects with familial hypertriglyceridemia. In such cases, discontinuation of the specific etiologic agent may obviate the need for specific drug therapy of hypertriglyceridemia. Lipid levels should be monitored periodically and consideration should be given to reducing the dosage of fenofibrate tablets if lipid levels fall significantly below the targeted range.
Therapy should be withdrawn in patients who do not have an adequate response after two months of treatment with the maximum recommended dose of 145 mg once daily.
2.2Primary Hypercholesterolemia or Mixed Dyslipidemia The initial dose of fenofibrate tablets is 145 mg once daily.
2.3Severe Hypertriglyceridemia The initial dose is 48 to 145 mg per day. Dosage should be individualized according to patient response, and should be adjusted if necessary following repeat lipid determinations at 4 to 8 week intervals. The maximum dose is 145 mg once daily.
2.4Impaired Renal Function Treatment with fenofibrate tablets should be initiated at a dose of 48 mg per day in patients having mild to moderately impaired renal function, and increased only after evaluation of the effects on renal function and lipid levels at this dose. The use of fenofibrate tablets should be avoided in patients with severe renal impairment [see Use in Specific Populations (8.6) and Clinical Pharmacology (12.3)] .
2.5Geriatric Patients Dose selection for the elderly should be made on the basis of renal function [see Use in Specific Populations (8.5)] .
2.1General Considerations Patients should be placed on an appropriate lipid-lowering diet before receiving fenofibrate tablets, and should continue this diet during treatment with fenofibrate tablets. Fenofibrate tablets can be given without regard to meals. The initial treatment for dyslipidemia is dietary therapy specific for the type of lipoprotein abnormality.
Excess body weight and excess alcoholic intake may be important factors in hypertriglyceridemia and should be addressed prior to any drug therapy. Physical exercise can be an important ancillary measure. Diseases contributory to hyperlipidemia, such as hypothyroidism or diabetes mellitus should be looked for and adequately treated.
Estrogen therapy, thiazide diuretics and beta-blockers, are sometimes associated with massive rises in plasma triglycerides, especially in subjects with familial hypertriglyceridemia. In such cases, discontinuation of the specific etiologic agent may obviate the need for specific drug therapy of hypertriglyceridemia. Lipid levels should be monitored periodically and consideration should be given to reducing the dosage of fenofibrate tablets if lipid levels fall significantly below the targeted range.
Therapy should be withdrawn in p… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS • 48 mg white to off-white, oval-shaped, biconvex, film-coated tablets debossed with ‘ RH37 ’ on one side and other side plain. • 145 mg white to off-white, oval-shaped, biconvex, film-coated tablets debossed with ‘ RH38 ’ on one side and other side plain. Oral Tablets: 48 mg and 145 mg (3).
⛔ Contraindications ▾
4 CONTRAINDICATIONS Fenofibrate is contraindicated in: • patients with severe renal impairment, including those receiving dialysis [see Clinical Pharmacology (12.3)] . • patients with active liver disease, including those with primary biliary cirrhosis and unexplained persistent liver function abnormalities [see Warnings and Precautions (5.2)] . • patients with preexisting gallbladder disease [see Warnings and Precautions (5.5)] . • nursing mothers [see Use in Specific Populations (8.2)] . • patients with known hypersensitivity to fenofibrate or fenofibric acid [see Warnings and Precautions (5.9)] . • Severe renal dysfunction, including dialysis patients (4, 8.6, 12.3). • Active liver disease (4, 5.3). • Gallbladder disease (4, 5.5). • Known hypersensitivity to fenofibrate (4). • Nursing mothers (4, 8.2).
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Hepatotoxicity : Serious drug-induced liver injury, including liver transplantation and death, has been reported with fenofibrate. Monitor patient’s liver function, including serum ALT, AST, and total bilirubin, at baseline and periodically for the duration of therapy. Discontinue if signs or symptoms of liver injury develop or if elevated enzyme levels persist (5.2). • Myopathy and rhabdomyolysis: Have been reported in patients taking fenofibrate.
Risks are increased during co-administration with a statin (with a significantly higher rate observed for gemfibrozil), particularly in elderly patients and patients with diabetes, renal failure, or hypothyroidism (5.3) • Serum Creatinine: Fenofibrate can reversibly increase serum creatinine levels (5.4). Monitor renal function periodically in patients with renal impairment (8.6). • Cholelithiasis: Fenofibrate increases cholesterol excretion into the bile, leading to risk of cholelithiasis. If cholelithiasis is suspected, gallbladder studies are indicated (5.5). • Coumarin anticoagulants: Use caution in concomitant treatment with oral coumarin anticoagulants.
Adjust the dosage of coumarin anticoagulant to maintain the prothrombin time/INR at the desired level to prevent bleeding complications (5.6). • Hypersensitivity Reactions: Acute hypersensitivity reactions, including anaphylaxis and angioedema, and delayed hypersensitivity reactions, including severe cutaneous adverse drug reactions have been reported postmarketing. Some cases were life-threatening and required emergency treatment. Discontinue fenofibrate and treat patients appropriately if reactions occur (5.9).
5.1Mortality and Coronary Heart Disease Morbidity The effect of fenofibrate on coronary heart disease morbidity and mortality and non-cardiovascular mortality has not been established. The Action to Control Cardiovascular Risk in Diabetes Lipid (ACCORD Lipid) trial was a randomized placebo-controlled study of 5518 patients with type 2 diabetes mellitus on background statin therapy treated with fenofibrate. The mean duration of follow-up was 4.7 years.
Fenofibrate plus statin combination therapy showed a non-significant 8% relative risk reduction in the primary outcome of major adverse cardiovascular events (MACE), a composite of non-fatal myocardial infarction, non-fatal stroke, and cardiovascular disease death (hazard ratio [HR] 0.92, 95% CI 0.79 to 1.08) (p = 0.32) as compared to statin monotherapy. In a gender subgroup analysis, the hazard ratio for MACE in men receiving combination therapy versus statin monotherapy was 0.82 (95% CI 0.69 to 0.99), and the hazard ratio for MACE in women receiving combination therapy versus statin monotherapy was 1.38 (95% CI 0.98 to 1.94) (interaction p = 0.01).
The clinical significance of this subgroup finding is unclear. The Fenofibrate Intervention and Event Lowering in Diabetes (FIELD) study was a 5-year randomized, placebo-controlled study of 9795 patients with type 2 diabetes mellitus treated with fenofibrate. Fenofibrate demonstrated a non-significant 11% relative reduction in the primary outcome of coronary heart disease events (hazard ratio [HR] 0.89, 95% CI 0.75 to 1.05, p = 0.16) and a significant 11% reduction in the secondary outcome of total cardiovascular disease events (HR 0.89 [0.80 to 0.99], p = 0.04).
There was a non-significant 11% (HR 1.11 [0.95, 1.29], p = 0.18) and 19% (HR 1.19 [0.90, 1.57], p = 0.22) increase in total and coronary heart disease mortality, respectively, with fenofibrate as compared to placebo. Because of chemical, pharmacological, and clinical similarities between fenofibrate tablets, clofibrate, and gemfibrozil, the adverse findings in 4 large randomized, placebo-controlled clinical studies with these other fibrate drugs may also apply to fenofibrate. In the Coronary Drug Project, a large study of post myocardial infarction of patients treated for 5 years with clofibrate, there was no difference in mortality seen… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in the labeling: • Mortality and coronary heart disease morbidity [see Warnings and Precautions (5.1)] • Hepatotoxicity [see Warnings and Precautions (5.2)] • Pancreatitis [see Warnings and Precautions (5.7)] • Hypersensitivity reactions [see Warnings and Precautions (5.9)] • Venothromboembolic disease [see Warnings and Precautions (5.10)] Adverse reactions > 2% and at least 1% greater than placebo: Abnormal liver tests, increased AST, increased ALT, increased CPK, and rhinitis (6).
To report SUSPECTED ADVERSE REACTIONS, contact Sun Pharmaceutical Industries Inc. at 1-800-406-7984 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in practice. Adverse events reported by 2% or more of patients treated with fenofibrate (and greater than placebo) during the double-blind, placebo-controlled trials, regardless of causality, are listed in Table 1 below. Adverse events led to discontinuation of treatment in 5% of patients treated with fenofibrate and in 3% treated with placebo.
Increases in liver function tests were the most frequent events, causing discontinuation of fenofibrate treatment in 1.6% of patients in double-blind trials. Table 1. Adverse Reactions Reported by 2% or More of Patients Treated with Fenofibrate and Greater than Placebo During the Double-Blind, Placebo-Controlled Trials BODY SYSTEM Adverse Reaction Fenofibrate * (N = 439) Placebo (N = 365) BODY AS A WHOLE Abdominal Pain 4.6% 4.4% Back Pain 3.4% 2.5% Headache 3.2% 2.7% DIGESTIVE Nausea 2.3% 1.9% Constipation 2.1% 1.4% METABOLIC AND NUTRITIONAL DISORDERS Abnormal Liver Function Tests 7.5% ** 1.4% Increased ALT 3% 1.6% Increased CPK 3% 1.4% Increased AST 3.4% ** 0.5% RESPIRATORY Respiratory Disorder 6.2% 5.5% Rhinitis 2.3% 1.1% * Dosage equivalent to 145 mg fenofibrate. ** Significantly different from Placebo.
Urticaria was seen in 1.1% vs. 0%, and rash in 1.4% vs. 0.8% of fenofibrate and placebo patients respectively in controlled trials.
Increases in Liver Enzymes In a pooled analysis of 10 placebo-controlled trials, increases to > 3 times the upper limit of normal in ALT occurred in 5.3% of patients taking fenofibrate at doses equivalent to 96 mg to 145 mg fenofibrate daily versus 1.1% of patients treated with placebo [see Warnings and Precautions (5.2)] . In an 8-week study, the incidence of ALT or AST elevations ≥ 3 times the upper limit of normal was 13% in patients receiving dosages equivalent to 96 mg to 145 mg fenofibrate daily and was 0% in those receiving dosages equivalent to 48 mg or less fenofibrate daily or placebo.
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of fenofibrate. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure: myalgia, rhabdomyolysis, pancreatitis, acute renal failure, muscle spasm, hepatitis, cirrhosis, increased total bilirubin, anemia, arthralgia, decreases in hemoglobin, decreases in hematocrit, white blood cell decreases, asthenia, severely depressed HDL-cholesterol levels, and interstitial lung disease.
Photosensitivity reactions have occurred days to months after initiation; in some of these cases, patients reported a prior photosensitivity reaction to ketoprofen.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to rates in the clinical studies of another drug and may not reflect the rates observed in p… [Excerpted — this section continues on DailyMed.]
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS • Coumarin anticoagulants: (7.1). • Immunosuppressants: (7.2). • Bile acid resins: (7.3).
7.1Coumarin Anticoagulants Potentiation of coumarin-type anticoagulant effects has been observed with prolongation of the PT/INR. Caution should be exercised when coumarin anticoagulants are given in conjunction with fenofibrate. The dosage of the anticoagulants should be reduced to maintain the PT/INR at the desired level to prevent bleeding complications.
Frequent PT/INR determinations are advisable until it has been definitely determined that the PT/INR has stabilized [see Warnings and Precautions (5.6)] .
7.2Immunosuppressants Immunosuppressants such as cyclosporine and tacrolimus can produce nephrotoxicity with decreases in creatinine clearance and rises in serum creatinine, and because renal excretion is the primary elimination route of fibrate drugs including fenofibrate, there is a risk that an interaction will lead to deterioration of renal function. The benefits and risks of using fenofibrate tablets with immunosuppressants and other potentially nephrotoxic agents should be carefully considered, and the lowest effective dose employed and renal function monitored.
7.3Bile Acid Binding Resins Since bile acid binding resins may bind other drugs given concurrently, patients should take fenofibrate at least 1 hour before or 4 to 6 hours after a bile acid binding resin to avoid impeding its absorption.
7.4Colchicine Cases of myopathy, including rhabdomyolysis, have been reported with fenofibrates co-administered with colchicine, and caution should be exercised when prescribing fenofibrate with colchicine.
7.1Coumarin Anticoagulants Potentiation of coumarin-type anticoagulant effects has been observed with prolongation of the PT/INR. Caution should be exercised when coumarin anticoagulants are given in conjunction with fenofibrate. The dosage of the anticoagulants should be reduced to maintain the PT/INR at the desired level to prevent bleeding complications.
Frequent PT/INR determinations are advisable until it has been definitely determined that the PT/INR has stabilized [see Warnings and Precautions (5.6)] .
7.2Immunosuppressants Immunosuppressants such as cyclosporine and tacrolimus can produce nephrotoxicity with decreases in creatinine clearance and rises in serum creatinine, and because renal excretion is the primary elimination route of fibrate drugs including fenofibrate, there is a risk that an interaction will lead to deterioration of renal function. The benefits and risks of using fenofibrate tablets with immunosuppressants and other potentially nephrotoxic agents should be carefully considered, and the lowest effective dose employed and renal function monitored.
7.3Bile Acid Binding Resins Since bile acid binding resins may bind other drugs given concurrently, patients should take fenofibrate at least 1 hour before or 4 to 6 hours after a bile acid binding resin to avoid impeding its absorption.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS • Geriatric Use: Determine dose selection based on renal function (8.5). • Renal Impairment: Avoid use in severe renal impairment patients. Dose reduction is required in mild to moderate renal impairment patients (8.6).
8.1Pregnancy Risk Summary Limited available data with fenofibrate use in pregnant women are insufficient to determine a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, no evidence of embryo-fetal toxicity was observed with oral administration of fenofibrate in rats and rabbits during organogenesis at doses less than or equivalent to the maximum recommended clinical dose of 145 mg daily, based on body surface area (mg/m 2 ). Adverse reproductive outcomes occurred at higher doses in the presence of maternal toxicity (see Data).
Fenofibrate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In pregnant rats given oral dietary doses of 14, 127, and 361 mg/kg/day from gestation day 6 to 15 during the period of organogenesis, no adverse developmental findings were observed at 14 mg/kg/day (less than the clinical exposure at the maximum recommended human dose [MRHD] of 300 mg fenofibrate daily, equivalent to 145 mg fenofibrate daily, based on body surface area comparisons). Increased fetal skeletal malformations were observed at maternally toxic doses (361 mg/kg/day, corresponding to 12 times the clinical exposure at the MRHD) that significantly suppressed maternal body weight gain.
In pregnant rabbits given oral gavage doses of 15, 150, and 300 mg/kg/day from gestation day 6 to 18 during the period of organogenesis and allowed to deliver, no adverse developmental findings were observed at 15 mg/kg/day (a dose that approximates the clinical exposure at the MRHD, based on body surface area comparisons). Aborted litters were observed at maternally toxic doses (≥ 150 mg/kg/day, corresponding to ≥ 10 times the clinical exposure at the MRHD) that suppressed maternal body weight gain. In pregnant rats given oral dietary doses of 15, 75, and 300 mg/kg/day from gestation day 15 through lactation day 21 (weaning), no adverse developmental effects were observed at 15 mg/kg/day (less than the clinical exposure at the MRHD, based on body surface area comparisons), despite maternal toxicity (decreased weight gain).
Post-implantation loss was observed at ≥ 75 mg/kg/day (≥ 2 times the clinical exposure at the MRHD) in the presence of maternal toxicity (decreased weight gain). Decreased pup survival was noted at 300 mg/kg/day (10 times the clinical exposure at the MRHD), which was associated with decreased maternal body weight gain/maternal neglect.
8.2Lactation Risk Summary There is no available information on the presence of fenofibrate in human milk, effects of the drug on the breastfed infant, or the effects on milk production. Fenofibrate is present in the milk of rats, and is therefore likely to be present in human milk. Because of the potential for serious adverse reactions in breastfed infants, such as disruption of infant lipid metabolism, women should not breastfeed during treatment with fenofibrate and for 5 days after the final dose [see Contraindications (4)] .
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients.
8.5Geriatric Use Fenofibric acid is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Fenofibric acid exposure is not influenced by age. Since elderly patients have a higher incidence of renal impairment, dos… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Limited available data with fenofibrate use in pregnant women are insufficient to determine a drug associated risk of major birth defects, miscarriage or adverse maternal or fetal outcomes. In animal reproduction studies, no evidence of embryo-fetal toxicity was observed with oral administration of fenofibrate in rats and rabbits during organogenesis at doses less than or equivalent to the maximum recommended clinical dose of 145 mg daily, based on body surface area (mg/m 2 ). Adverse reproductive outcomes occurred at higher doses in the presence of maternal toxicity (see Data).
Fenofibrate should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively.
Data Animal Data In pregnant rats given oral dietary doses of 14, 127, and 361 mg/kg/day from gestation day 6 to 15 during the period of organogenesis, no adverse developmental findings were observed at 14 mg/kg/day (less than the clinical exposure at the maximum recommended human dose [MRHD] of 300 mg fenofibrate daily, equivalent to 145 mg fenofibrate daily, based on body surface area comparisons). Increased fetal skeletal malformations were observed at maternally toxic doses (361 mg/kg/day, corresponding to 12 times the clinical exposure at the MRHD) that significantly suppressed maternal body weight gain.
In pregnant rabbits given oral gavage doses of 15, 150, and 300 mg/kg/day from gestation day 6 to 18 during the period of organogenesis and allowed to deliver, no adverse developmental findings were observed at 15 mg/kg/day (a dose that approximates the clinical exposure at the MRHD, based on body surface area comparisons). Aborted litters were observed at maternally toxic doses (≥ 150 mg/kg/day, corresponding to ≥ 10 times the clinical exposure at the MRHD) that suppressed maternal body weight gain. In pregnant rats given oral dietary doses of 15, 75, and 300 mg/kg/day from gestation day 15 through lactation day 21 (weaning), no adverse developmental effects were observed at 15 mg/kg/day (less than the clinical exposure at the MRHD, based on body surface area comparisons), despite maternal toxicity (decreased weight gain).
Post-implantation loss was observed at ≥ 75 mg/kg/day (≥ 2 times the clinical exposure at the MRHD) in the presence of maternal toxicity (decreased weight gain). Decreased pup survival was noted at 300 mg/kg/day (10 times the clinical exposure at the MRHD), which was associated with decreased maternal body weight gain/maternal neglect.
🧒 Pediatric Use ▾
8.4Pediatric Use Safety and effectiveness have not been established in pediatric patients.
🧓 Geriatric Use ▾
8.5Geriatric Use Fenofibric acid is known to be substantially excreted by the kidney, and the risk of adverse reactions to this drug may be greater in patients with impaired renal function. Fenofibric acid exposure is not influenced by age. Since elderly patients have a higher incidence of renal impairment, dose selection for the elderly should be made on the basis of renal function [see Dosage and Administration (2.5) and Clinical Pharmacology (12.3)] .
Elderly patients with normal renal function should require no dose modifications. Consider monitoring renal function in elderly patients taking fenofibrate.
🆘 Overdosage ▾
10 OVERDOSAGE There is no specific treatment for overdose with fenofibrate. General supportive care of the patient is indicated, including monitoring of vital signs and observation of clinical status, should an overdose occur. If indicated, elimination of unabsorbed drug should be achieved by emesis or gastric lavage; usual precautions should be observed to maintain the airway.
Because fenofibric acid is highly bound to plasma proteins, hemodialysis should not be considered.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action The active moiety of fenofibrate is fenofibric acid. The pharmacological effects of fenofibric acid in both animals and humans have been extensively studied through oral administration of fenofibrate. The lipid-modifying effects of fenofibric acid seen in clinical practice have been explained in vivo in transgenic mice and in vitro in human hepatocyte cultures by the activation of peroxisome proliferator activated receptor α (PPARα).
Through this mechanism, fenofibrate increases lipolysis and elimination of triglyceride-rich particles from plasma by activating lipoprotein lipase and reducing production of apoprotein C-III (an inhibitor of lipoprotein lipase activity). The resulting decrease in TG produces an alteration in the size and composition of LDL from small, dense particles (which are thought to be atherogenic due to their susceptibility to oxidation), to large buoyant particles. These larger particles have a greater affinity for cholesterol receptors and are catabolized rapidly.
Activation of PPARα also induces an increase in the synthesis of apolipoproteins A-I, A-II and HDL-cholesterol. Fenofibrate also reduces serum uric acid levels in hyperuricemic and normal individuals by increasing the urinary excretion of uric acid.
12.2Pharmacodynamics A variety of clinical studies have demonstrated that elevated levels of total-C, LDL-C, and apo B, an LDL membrane complex, are associated with human atherosclerosis. Similarly, decreased levels of HDL-C and its transport complex, apolipoprotein A (apo AI and apo AII) are associated with the development of atherosclerosis. Epidemiologic investigations have established that cardiovascular morbidity and mortality vary directly with the level of total-C, LDL-C, and TG, and inversely with the level of HDL-C.
The independent effect of raising HDL-C or lowering triglycerides (TG) on the risk of cardiovascular morbidity and mortality has not been determined. Fenofibric acid, the active metabolite of fenofibrate, produces reductions in total cholesterol, LDL cholesterol, apolipoprotein B, total triglycerides and triglyceride rich lipoprotein (VLDL) in treated patients. In addition, treatment with fenofibrate results in increases in high density lipoprotein (HDL) and apolipoproteins apoAI and apoAII.
12.3Pharmacokinetics Plasma concentrations of fenofibric acid after administration of three 48 mg or one 145 mg tablets are equivalent under fed conditions to one 200 mg micronized fenofibrate capsule. Fenofibrate is a pro-drug of the active chemical moiety fenofibric acid. Fenofibrate is converted by ester hydrolysis in the body to fenofibric acid which is the active constituent measurable in the circulation.
Absorption The absolute bioavailability of fenofibrate cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. However, fenofibrate is well absorbed from the gastrointestinal tract. Following oral administration in healthy volunteers, approximately 60% of a single dose of radiolabelled fenofibrate appeared in urine, primarily as fenofibric acid and its glucuronate conjugate, and 25% was excreted in the feces.
Peak plasma levels of fenofibric acid occur within 6 to 8 hours after administration. Exposure to fenofibric acid in plasma, as measured by C max and AUC, is not significantly different when a single 145 mg dose of fenofibrate is administered under fasting or nonfasting conditions. Distribution Upon multiple dosing of fenofibrate, fenofibric acid steady state is achieved within 9 days.
Plasma concentrations of fenofibric acid at steady state are approximately double of those following a single dose. Serum protein binding was approximately 99% in normal and hyperlipidemic subjects. Metabolism Following oral administration, fenofibrate is rapidly hydrolyzed by esterases to the active metabolite, fenofibric acid; no unchanged fenofibrate is detected in plasma.
Fenofibric acid is primarily… [Excerpted — this section continues on DailyMed.]
🧬 Mechanism of Action ▾
12.1Mechanism of Action The active moiety of fenofibrate is fenofibric acid. The pharmacological effects of fenofibric acid in both animals and humans have been extensively studied through oral administration of fenofibrate. The lipid-modifying effects of fenofibric acid seen in clinical practice have been explained in vivo in transgenic mice and in vitro in human hepatocyte cultures by the activation of peroxisome proliferator activated receptor α (PPARα).
Through this mechanism, fenofibrate increases lipolysis and elimination of triglyceride-rich particles from plasma by activating lipoprotein lipase and reducing production of apoprotein C-III (an inhibitor of lipoprotein lipase activity). The resulting decrease in TG produces an alteration in the size and composition of LDL from small, dense particles (which are thought to be atherogenic due to their susceptibility to oxidation), to large buoyant particles. These larger particles have a greater affinity for cholesterol receptors and are catabolized rapidly.
Activation of PPARα also induces an increase in the synthesis of apolipoproteins A-I, A-II and HDL-cholesterol. Fenofibrate also reduces serum uric acid levels in hyperuricemic and normal individuals by increasing the urinary excretion of uric acid.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Fenofibrate tablets, USP 145 mg white to off-white, oval-shaped, biconvex, film-coated tablets debossed with ‘RH38’ on one side and other side NDC: 71335-0872-1: 30 Tablets in a BOTTLE NDC: 71335-0872-2: 90 Tablets in a BOTTLE NDC: 71335-0872-3: 28 Tablets in a BOTTLE Storage Store at 20º - 25º C (68º - 77º F) [See USP Controlled Room Temperature]. Keep out of the reach of children. Protect from moisture.
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 91504
📋 Description ▾
11 DESCRIPTION Fenofibrate, USP is a lipid regulating agent available as tablets for oral administration. Each tablet contains 48 mg or 145 mg of fenofibrate, USP. The chemical name for fenofibrate, USP is 2-[4-(4-chlorobenzoyl) phenoxy]-2-methyl-propanoic acid, 1-methylethyl ester with the following structural formula: The molecular formula is C 20 H 21 O 4 Cl and the molecular weight is 360.83; fenofibrate, USP is very soluble in methylene chloride, slightly soluble in alcohol and practically insoluble in water.
The melting point is 79-82° C. Fenofibrate, USP is a white or almost white crystalline powder. Inactive Ingredients Each film-coated tablet contains colloidal silicon dioxide, crospovidone, hypromellose (3 cps), microcrystalline cellulose, polyvinyl alcohol, pregelatinized starch, sucrose, sodium lauryl sulfate, sodium stearyl fumarate, soybean lecithin, talc, titanium dioxide, and xanthan gum.
Meets USP Dissolution Test 1.
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Patients should be advised: • of the potential benefits and risks of fenofibrate tablets, USP. • not to use fenofibrate tablets, USP if there is a known hypersensitivity to fenofibrate or fenofibric acid. • of medications that should not be taken in combination with fenofibrate tablets, USP. • that if they are taking coumarin anticoagulants, fenofibrate tablets, USP may increase their anti-coagulant effect, and increased monitoring may be necessary. • to continue to follow an appropriate lipid-modifying diet while taking fenofibrate tablets, USP. • to take fenofibrate tablets, USP once daily, without regard to food, at the prescribed dose, swallowing each tablet whole. • to return to their physician’s office for routine monitoring. • to inform their physician of all medications, supplements, and herbal preparations they are taking and any change to their medical condition.
Patients should also be advised to inform their physicians prescribing a new medication that they are taking fenofibrate tablets, USP. • to inform their physician of symptoms of liver injury (e.g., jaundice, abdominal pain, nausea, malaise, dark urine, abnormal stool, pruritus); any muscle pain, tenderness, or weakness; or any other new symptoms. • not to breastfeed during treatment with fenofibrate tablets, USP and for 5 days after the final dose. Manufactured by: Sun Pharmaceutical Industries Ltd. Mohali, INDIA Distributed by: Sun Pharmaceutical Industries, Inc.
Cranbury, NJ 08512 July 2021 FDA-08
Patients should be advised: • of the potential benefits and risks of fenofibrate tablets, USP. • not to use fenofibrate tablets, USP if there is a known hypersensitivity to fenofibrate or fenofibric acid. • of medications that should not be taken in combination with fenofibrate tablets, USP. • that if they are taking coumarin anticoagulants, fenofibrate tablets, USP may increase their anti-coagulant effect, and increased monitoring may be necessary. • to continue to follow an appropriate lipid-modifying diet while taking fenofibrate tablets, USP. • to take fenofibrate tablets, USP once daily, without regard to food, at the prescribed dose, swallowing each tablet whole. • to return to their physician’s office for routine monitoring. • to inform their physician of all medications, supplements, and herbal preparations they are taking and any change to their medical condition.
Patients should also be advised to inform their physicians prescribing a new medication that they are taking fenofibrate tablets, USP. • to inform their physician of symptoms of liver injury (e.g., jaundice, abdominal pain, nausea, malaise, dark urine, abnormal stool, pruritus); any muscle pain, tenderness, or weakness; or any other new symptoms. • not to breastfeed during treatment with fenofibrate tablets, USP and for 5 days after the final dose. Manufactured by: Sun Pharmaceutical Industries Ltd. Mohali, INDIA Distributed by: Sun Pharmaceutical Industries, Inc.
Cranbury, NJ 08512 July 2021 FDA-08
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics Plasma concentrations of fenofibric acid after administration of three 48 mg or one 145 mg tablets are equivalent under fed conditions to one 200 mg micronized fenofibrate capsule. Fenofibrate is a pro-drug of the active chemical moiety fenofibric acid. Fenofibrate is converted by ester hydrolysis in the body to fenofibric acid which is the active constituent measurable in the circulation.
Absorption The absolute bioavailability of fenofibrate cannot be determined as the compound is virtually insoluble in aqueous media suitable for injection. However, fenofibrate is well absorbed from the gastrointestinal tract. Following oral administration in healthy volunteers, approximately 60% of a single dose of radiolabelled fenofibrate appeared in urine, primarily as fenofibric acid and its glucuronate conjugate, and 25% was excreted in the feces.
Peak plasma levels of fenofibric acid occur within 6 to 8 hours after administration. Exposure to fenofibric acid in plasma, as measured by C max and AUC, is not significantly different when a single 145 mg dose of fenofibrate is administered under fasting or nonfasting conditions. Distribution Upon multiple dosing of fenofibrate, fenofibric acid steady state is achieved within 9 days.
Plasma concentrations of fenofibric acid at steady state are approximately double of those following a single dose. Serum protein binding was approximately 99% in normal and hyperlipidemic subjects. Metabolism Following oral administration, fenofibrate is rapidly hydrolyzed by esterases to the active metabolite, fenofibric acid; no unchanged fenofibrate is detected in plasma.
Fenofibric acid is primarily conjugated with glucuronic acid and then excreted in urine. A small amount of fenofibric acid is reduced at the carbonyl moiety to a benzhydrol metabolite which is, in turn, conjugated with glucuronic acid and excreted in urine. In vivo metabolism data indicate that neither fenofibrate nor fenofibric acid undergo oxidative metabolism (e.g., cytochrome P450) to a significant extent.
Elimination After absorption, fenofibrate is mainly excreted in the urine in the form of metabolites, primarily fenofibric acid and fenofibric acid glucuronide. After administration of radiolabelled fenofibrate, approximately 60% of the dose appeared in the urine and 25% was excreted in the feces. Fenofibric acid is eliminated with a half-life of 20 hours, allowing once daily dosing.
Special Populations Geriatrics In elderly volunteers 77 to 87 years of age, the oral clearance of fenofibric acid following a single oral dose of fenofibrate was
1.2 L/h, which compares to
1.1L/h in young adults. This indicates that a similar dosage regimen can be used in elderly with normal renal function, without increasing accumulation of the drug or metabolites [see Dosage and Administration (2.5) and Use in Specific Populations (8.5)] . Pediatrics The pharmacokinetics of fenofibrate has not been studied in pediatric populations.
Gender No pharmacokinetic difference between males and females has been observed for fenofibrate. Race The influence of race on the pharmacokinetics of fenofibrate has not been studied, however fenofibrate is not metabolized by enzymes known for exhibiting inter-ethnic variability. Renal Impairment The pharmacokinetics of fenofibric acid was examined in patients with mild, moderate, and severe renal impairment.
Patients with severe renal impairment (estimated glomerular filtration rate [eGFR] < 30 mL/min/1.73 m 2 ) showed 2.7-fold increase in exposure for fenofibric acid and increased accumulation of fenofibric acid during chronic dosing compared to that of healthy subjects. Patients with mild to moderate renal impairment (eGFR 30 to 59 mL/min/1.73 m 2 ) had similar exposure but an increase in the half-life for fenofibric acid compared to that of healthy subjects. Based on these findings, the use of fenofibrate should be avoided in patients who have severe renal impairment and dose reduction is require… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics A variety of clinical studies have demonstrated that elevated levels of total-C, LDL-C, and apo B, an LDL membrane complex, are associated with human atherosclerosis. Similarly, decreased levels of HDL-C and its transport complex, apolipoprotein A (apo AI and apo AII) are associated with the development of atherosclerosis. Epidemiologic investigations have established that cardiovascular morbidity and mortality vary directly with the level of total-C, LDL-C, and TG, and inversely with the level of HDL-C.
The independent effect of raising HDL-C or lowering triglycerides (TG) on the risk of cardiovascular morbidity and mortality has not been determined. Fenofibric acid, the active metabolite of fenofibrate, produces reductions in total cholesterol, LDL cholesterol, apolipoprotein B, total triglycerides and triglyceride rich lipoprotein (VLDL) in treated patients. In addition, treatment with fenofibrate results in increases in high density lipoprotein (HDL) and apolipoproteins apoAI and apoAII.
🔬 Clinical Studies ▾
14 CLINICAL STUDIES
14.1Primary Hypercholesterolemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia The effects of fenofibrate at a dose equivalent to 145 mg fenofibrate tablets per day were assessed from four randomized, placebo-controlled, double-blind, parallel-group studies including patients with the following mean baseline lipid values: total-C 306.9 mg/dL; LDL-C 213.8 mg/dL; HDL-C 52.3 mg/dL; and triglycerides 191 mg/dL. Fenofibrate therapy lowered LDL-C, Total-C, and the LDL-C/HDL-C ratio. Fenofibrate therapy also lowered triglycerides and raised HDL-C (see Table 4).
Table 4. Mean Percent Change in Lipid Parameters at End of Treatment † Treatment Group Total-C LDL-C HDL-C TG Pooled Cohort Mean baseline lipid values (n = 646) 306.9 mg/dL 213.8 mg/dL 52.3 mg/dL 191 mg/dL All FEN (n = 361) -18.7% * -20.6% * +11% * -28.9% * Placebo (n = 285) -0.4% -2.2% +0.7% +7.7% Baseline LDL-C > 160 mg/dL and TG < 150 mg/dL Mean baseline lipid values (n = 334) 307.7 mg/dL 227.7 mg/dL 58.1 mg/dL 101.7 mg/dL All FEN (n = 193) -22.4% * -31.4% * +9.8% * -23.5% * Placebo (n = 141) +0.2% -2.2% +2.6% +11.7% Baseline LDL-C > 160 mg/dL and TG ≥ 150 mg/dL Mean baseline lipid values (n = 242) 312.8 mg/dL 219.8 mg/dL 46.7 mg/dL 231.9 mg/dL All FEN (n = 126) -16.8% * -20.1% * +14.6% * -35.9% * Placebo (n = 116) -3% -6.6% +2.3% +0.9% † Duration of study treatment was 3 to 6 months. * p = < 0.05 vs.
Placebo In a subset of the subjects, measurements of apo B were conducted. Fenofibrate treatment significantly reduced apo B from baseline to endpoint as compared with placebo (-25.1% vs. 2.4%, p < 0.0001, n = 213 and 143 respectively).
14.2Severe Hypertriglyceridemia The effects of fenofibrate on serum triglycerides were studied in two randomized, double-blind, placebo-controlled clinical trials of 147 hypertriglyceridemic patients. Patients were treated for eight weeks under protocols that differed only in that one entered patients with baseline TG levels of 500 to 1500 mg/dL, and the other TG levels of 350 to 500 mg/dL. In patients with hypertriglyceridemia and normal cholesterolemia with or without hyperchylomicronemia, treatment with fenofibrate at dosages equivalent to fenofibrate 145 mg per day decreased primarily very low density lipoprotein (VLDL) triglycerides and VLDL cholesterol.
Treatment of patients with elevated triglycerides often results in an increase of LDL-C (see Table 5). Table 5. Effects of Fenofibrate in Patients With Severe Hypertriglyceridemia Study 1 Placebo Fenofibrate Baseline TG levels 350 to 499 mg/dL N Baseline (Mean) Endpoint (Mean) % Change (Mean) N Baseline (Mean) Endpoint (Mean) % Change (Mean) Triglycerides 28 449 450 -0.5 27 432 223 -46.2 * VLDL Triglycerides 19 367 350 2.7 19 350 178 -44.1 * Total Cholesterol 28 255 261 2.8 27 252 227 -9.1 * HDL Cholesterol 28 35 36 4 27 34 40 19.6 * LDL Cholesterol 28 120 129 12 27 128 137
14.5VLDL Cholesterol 27 99 99 5.8 27 92 46 -44.7 * Study 2 Placebo Fenofibrate Baseline TG levels 500 to 1500 mg/dL N Baseline (Mean) Endpoint (Mean) % Change (Mean) N Baseline (Mean) Endpoint (Mean) % Change (Mean) Triglycerides 44 710 750 7.2 48 726 308 -54.5 * VLDL Triglycerides 29 537 571 18.7 33 543 205 -50.6 * Total Cholesterol 44 272 271 0.4 48 261 223 -13.8 * HDL Cholesterol 44 27 28 5 48 30 36 22.9 * LDL Cholesterol 42 100 90 -4.2 45 103 131 45 * VLDL Cholesterol 42 137 142 11 45 126 54 -49.4 * * = p < 0.05 vs.
Placebo The effect of fenofibrate on cardiovascular morbidity and mortality has not been determined.
14.1Primary Hypercholesterolemia (Heterozygous Familial and Nonfamilial) and Mixed Dyslipidemia The effects of fenofibrate at a dose equivalent to 145 mg fenofibrate tablets per day were assessed from four randomized, placebo-controlled, double-blind, parallel-group studies including patients with the following mean baseline lipid values: total-C 306.9 mg/dL; LDL-C 213.8 mg/dL; HDL-C 52.3 mg/dL; and triglycerides 191 mg/dL. Fenofibrate therapy lowered LDL-C, Total… [Excerpted — this section continues on DailyMed.]
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis and Mutagenesis and Impairment of Fertility Two dietary carcinogenicity studies have been conducted in rats with fenofibrate. In the first 24-month study, Wistar rats were dosed with fenofibrate at 10, 45, and 200 mg/kg/day, approximately 0.3, 1, and 6 times the maximum recommended human dose (MRHD) of 300 mg fenofibrate daily, equivalent to 145 mg fenofibrate daily based on body surface area comparisons. At a dose of 200 mg/kg/day (at 6 times the MRHD), the incidence of liver carcinomas was significantly increased in both sexes.
A statistically significant increase in pancreatic carcinomas was observed in males at 1 and 6 times the MRHD; an increase in pancreatic adenomas and benign testicular interstitial cell tumors was observed at 6 times the MRHD in males. In a second 24-month rat carcinogenicity study in a different strain of rats (Sprague-Dawley), doses of 10 and 60 mg/kg/day (0.3 and 2 times the MRHD) produced significant increases in the incidence of pancreatic acinar adenomas in both sexes and increases in testicular interstitial cell tumors in males at 2 times the MRHD.
A 117-week carcinogenicity study was conducted in rats comparing three drugs: fenofibrate 10 and 60 mg/kg/day (0.3 and 2 times the MRHD, based on body surface area comparisons), clofibrate (400 mg/kg/day; 2 times the human dose), and gemfibrozil (250 mg/kg/day; 2 times the human dose, based on mg/m 2 surface area). Fenofibrate increased pancreatic acinar adenomas in both sexes. Clofibrate increased hepatocellular carcinoma and pancreatic acinar adenomas in males and hepatic neoplastic nodules in females.
Gemfibrozil increased hepatic neoplastic nodules in males and females, while all three drugs increased testicular interstitial cell tumors in males. In a 21-month study in CF-1 mice, fenofibrate 10, 45, and 200 mg/kg/day (approximately 0.2, 1, and 3 times the MRHD, based on body surface area comparisons) significantly increased the liver carcinomas in both sexes at 3 times the MRHD. In a second 18-month study at 10, 60, and 200 mg/kg/day, fenofibrate significantly increased the liver carcinomas in male mice and liver adenomas in female mice at 3 times the MRHD.
Electron microscopy studies have demonstrated peroxisomal proliferation following fenofibrate administration to the rat. An adequate study to test for peroxisome proliferation in humans has not been done, but changes in peroxisome morphology and numbers have been observed in humans after treatment with other members of the fibrate class when liver biopsies were compared before and after treatment in the same individual. Fenofibrate has been demonstrated to be devoid of mutagenic potential in the following tests: Ames, mouse lymphoma, chromosomal aberration and unscheduled DNA synthesis in primary rat hepatocytes.
In fertility studies rats were given oral dietary doses of fenofibrate, males received 61 days prior to mating and females 15 days prior to mating through weaning which resulted in no adverse effect on fertility at doses up to 300 mg/kg/day (10 times the MRHD, based on body surface area comparisons).
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis and Mutagenesis and Impairment of Fertility Two dietary carcinogenicity studies have been conducted in rats with fenofibrate. In the first 24-month study, Wistar rats were dosed with fenofibrate at 10, 45, and 200 mg/kg/day, approximately 0.3, 1, and 6 times the maximum recommended human dose (MRHD) of 300 mg fenofibrate daily, equivalent to 145 mg fenofibrate daily based on body surface area comparisons. At a dose of 200 mg/kg/day (at 6 times the MRHD), the incidence of liver carcinomas was significantly increased in both sexes.
A statistically significant increase in pancreatic carcinomas was observed in males at 1 and 6 times the MRHD; an increase in pancreatic adenomas and benign testicular interstitial cell tumors was observed at 6 times the MRHD in males. In a second 24-month rat carcinogenicity study in a different strain of rats (Sprague-Dawley), doses of 10 and 60 mg/kg/day (0.3 and 2 times the MRHD) produced significant increases in the incidence of pancreatic acinar adenomas in both sexes and increases in testicular interstitial cell tumors in males at 2 times the MRHD.
A 117-week carcinogenicity study was conducted in rats comparing three drugs: fenofibrate 10 and 60 mg/kg/day (0.3 and 2 times the MRHD, based on body surface area comparisons), clofibrate (400 mg/kg/day; 2 times the human dose), and gemfibrozil (250 mg/kg/day; 2 times the human dose, based on mg/m 2 surface area). Fenofibrate increased pancreatic acinar adenomas in both sexes. Clofibrate increased hepatocellular carcinoma and pancreatic acinar adenomas in males and hepatic neoplastic nodules in females.
Gemfibrozil increased hepatic neoplastic nodules in males and females, while all three drugs increased testicular interstitial cell tumors in males. In a 21-month study in CF-1 mice, fenofibrate 10, 45, and 200 mg/kg/day (approximately 0.2, 1, and 3 times the MRHD, based on body surface area comparisons) significantly increased the liver carcinomas in both sexes at 3 times the MRHD. In a second 18-month study at 10, 60, and 200 mg/kg/day, fenofibrate significantly increased the liver carcinomas in male mice and liver adenomas in female mice at 3 times the MRHD.
Electron microscopy studies have demonstrated peroxisomal proliferation following fenofibrate administration to the rat. An adequate study to test for peroxisome proliferation in humans has not been done, but changes in peroxisome morphology and numbers have been observed in humans after treatment with other members of the fibrate class when liver biopsies were compared before and after treatment in the same individual. Fenofibrate has been demonstrated to be devoid of mutagenic potential in the following tests: Ames, mouse lymphoma, chromosomal aberration and unscheduled DNA synthesis in primary rat hepatocytes.
In fertility studies rats were given oral dietary doses of fenofibrate, males received 61 days prior to mating and females 15 days prior to mating through weaning which resulted in no adverse effect on fertility at doses up to 300 mg/kg/day (10 times the MRHD, based on body surface area comparisons).
📄 Recent Major Changes ▾
Warnings and Precautions, Hepatotoxicity (5.2) 03/2021
📄 Package Label / Principal Display Panel ▾
Fenofibrate 145mg Tablet Label
Medicare Part D spend CMS · PART D · 2026 (Q1)
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | — Not published for this NDC Applies only to products approved under an NDA/ANDA; many listings are out of scope. |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |