
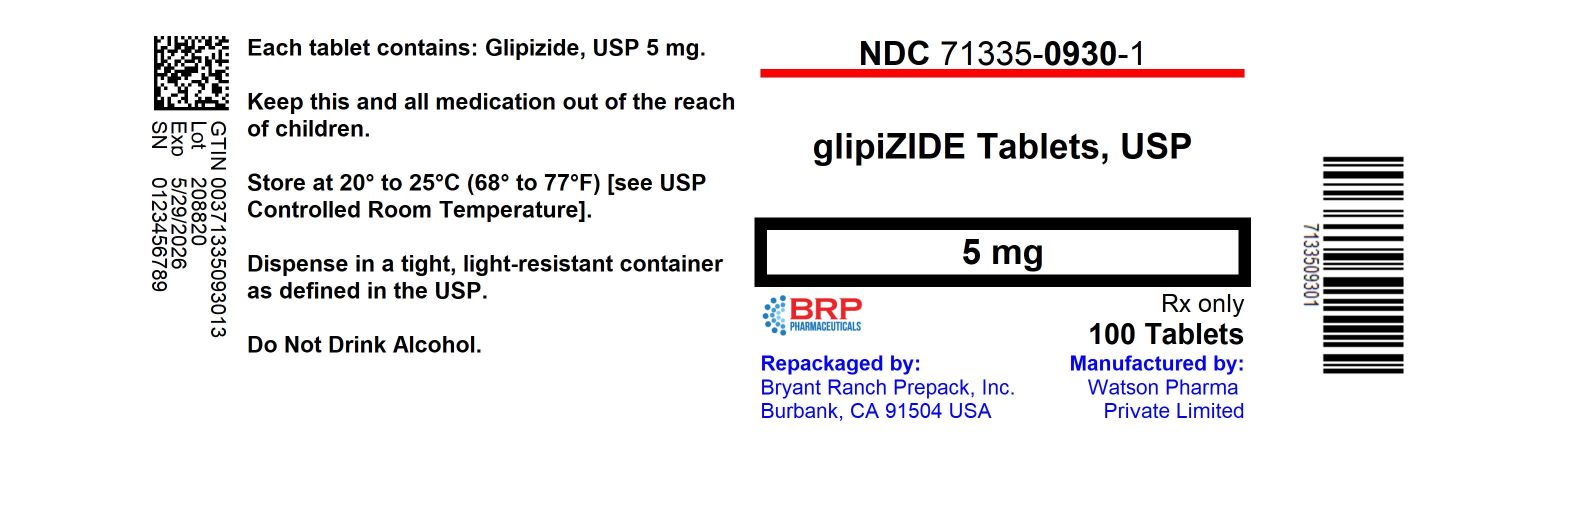
Glipizide 5 mg Tablet, 30-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Sulfonylurea class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Glipizide is used to help lower blood sugar in adults with type 2 diabetes. It works by telling your pancreas to release more insulin after you eat. It's meant to be used alongside...
- What exactly is glipizide for, and how does it help my diabetes?
- Timing really does matter with this one. If you're taking the regular tablet, aim to take it about 30 minutes before a meal — that way it's working right when your blood sugar star...
- When should I take my glipizide, and does it matter if I eat?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Glipizide — tap one for details:
Glipizide may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 3SY5LH9PMK
Anhydrous lactose is a milk sugar with no water content. It acts as a filler and binder in tablets and capsules, adding bulk and helping ingredients stick together.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 5856J3G2A2
A starch-based powder made from potatoes and processed with sodium. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the medicine can be absorbed.
4 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.0806 | $2.42 / 30 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Glipizide 5 mg 00591-0460-01 | Actavis | 100 tablets | $0.035 | — | Availability likely | — |
| Glipizide 5 mg 00904-6637-61 | Major | 100 tablets | $0.035 | AB | Availability likely | — |
| Glipizide 5 mg 50268-0361-15 | AvPAK | 50 tablets | $0.035 | AB | Availability likely | — |
| Glipizide 5 mg 60505-0141-00 | Apotex | 100 tablets | $0.035 | AB | Availability likely | — |
| Glipizide 5 mg 60687-0690-01 | American | 100 tablets | $0.035 | AB | Availability likely | — |
| Glipizide 5 mg 62559-0315-10 | ANI | 1000 tablets | $0.035 | AB | Availability likely | — |
| Glipizide 5 mg 68645-0574-54 | Legacy | 30 tablets | $0.035 | AB | Availability likely | — |
| Glipizide 5 mg 69584-0309-10 | Oxford | 100 tablets | $0.035 | AB | Availability likely | — |
| Glipizide 5 mg 72888-0116-00 | Advagen | 1000 tablets | $0.035 | — | Availability likely | — |
| Glipizide 5 mg 00615-8407-05 | NCS | 15 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 43353-0207-45 | Aphena | 45 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 50090-0502-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 50090-6473-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 50090-6975-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 50090-7755-00 | A-S | 30 tablets | — | — | FDA listed | — |
| Glipizide 5 mg 50090-7756-00 | A-S | 90 tablets | — | — | FDA listed | — |
| Glipizide 5 mg 50090-7908-00 | A-S | 90 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 51407-0620-10 | Golden | 1000 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 51655-0180-25 | Northwind | 60 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 55154-7987-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 55289-0806-93 | PD-Rx | 180 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 63629-1398-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 67046-0236-03 | Coupler | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68071-3548-06 | NuCare | 60 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68071-4085-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68071-4223-03 | NuCare | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68071-4857-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68071-4939-01 | NuCare | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68788-0141-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68788-4020-01 | Preferred | 100 tablets | — | — | FDA listed | — |
| Glipizide 5 mg 68788-8512-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 70518-0552-00 | REMEDYREPACK | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 71205-0041-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mgthis 71335-0930-02 | Bryant | 30 tablets | — | AB | Discontinued | — |
| Glipizide 5 mg 71335-2520-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 71335-2528-01 | Bryant | 100 tablets | — | — | FDA listed | — |
| Glipizide 5 mg 71335-3133-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 71610-0175-60 | Aphena | 90 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 71610-0680-45 | Aphena | 45 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 72162-2103-00 | Bryant | 1000 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 72789-0130-30 | PD-Rx | 30 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 72789-0464-86 | PD-Rx | 360 tablets | — | — | FDA listed | — |
| Glipizide 5 mg 82804-0174-30 | Proficient | 30 tablets | — | — | FDA listed | — |
| Glipizide 5 mg 82804-0959-00 | Proficient | 100 tablets | — | AB | FDA listed | — |
| Glipizide 5 mg 68788-4178-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-0930-01 | 100 TABLET in 1 BOTTLE (71335-0930-1) | 2005-08-08 | Discontinued by firm |
| 71335-0930-02 You're viewing this | 30 TABLET in 1 BOTTLE (71335-0930-2) | 2005-08-08 | Discontinued by firm |
| 71335-0930-03 | 60 TABLET in 1 BOTTLE (71335-0930-3) | 2005-08-08 | Discontinued by firm |
| 71335-0930-04 | 90 TABLET in 1 BOTTLE (71335-0930-4) | 2005-08-08 | Discontinued by firm |
| 71335-0930-05 | 20 TABLET in 1 BOTTLE (71335-0930-5) | 2005-08-08 | Discontinued by firm |
| 71335-0930-06 | 180 TABLET in 1 BOTTLE (71335-0930-6) | 2005-08-08 | Discontinued by firm |
| 71335-0930-07 | 10 TABLET in 1 BOTTLE (71335-0930-7) | 2005-08-08 | Discontinued by firm |
You're viewing one of 7 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-0930-02?
What is the difference between NDC 71335-0930-02 and NDC 71335-0930-07?
What NDC number is used to bill for this package of Glipizide 5 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
What does the discontinued status mean for this NDC?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Glipizide tablets are indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION There is no fixed dosage regimen for the management of diabetes mellitus with glipizide or any other hypoglycemic agent. In addition to the usual monitoring of urinary glucose, the patient's blood glucose must also be monitored periodically to determine the minimum effective dose for the patient; to detect primary failure, i.e., inadequate lowering of blood glucose at the maximum recommended dose of medication; and to detect secondary failure, i.e., loss of an adequate blood-glucose-lowering response after an initial period of effectiveness.
Glycosylated hemoglobin levels may also be of value in monitoring the patient's response to therapy. Short-term administration of glipizide may be sufficient during periods of transient loss of control in patients usually controlled well on diet. In general, glipizide tablets should be given approximately 30 minutes before a meal to achieve the greatest reduction in postprandial hyperglycemia.
Initial Dose The recommended starting dose is 5 mg, given before breakfast. Geriatric patients or those with liver disease may be started on 2.5 mg. Titration Dosage adjustments should ordinarily be in increments of 2.5 to 5 mg, as determined by blood glucose response.
At least several days should elapse between titration steps. If response to a single dose is not satisfactory, dividing that dose may prove effective. The maximum recommended once daily dose is 15 mg.
Doses above 15 mg should ordinarily be divided and given before meals of adequate caloric content. The maximum recommended total daily dose is 40 mg. Maintenance Some patients may be effectively controlled on a once-a-day regimen, while others show better response with divided dosing.
Total daily doses above 15 mg should ordinarily be divided. Total daily doses above 30 mg have been safely given on a b.i.d. basis to long-term patients. In elderly patients, debilitated or malnourished patients, and patients with impaired renal or hepatic function, the initial and maintenance dosing should be conservative to avoid hypoglycemic reactions (see PRECAUTIONS section).
Patients Receiving Insulin As with other sulfonylurea-class hypoglycemics, many stable non-insulin-dependent diabetic patients receiving insulin may be safely placed on glipizide. When transferring patients from insulin to glipizide, the following general guidelines should be considered: For patients whose daily insulin requirement is 20 units or less, insulin may be discontinued and glipizide therapy may begin at usual dosages. Several days should elapse between glipizide titration steps.
For patients whose daily insulin requirement is greater than 20 units, the insulin dose should be reduced by 50% and glipizide therapy may begin at usual dosages. Subsequent reductions in insulin dosage should depend on individual patient response. Several days should elapse between glipizide titration steps.
During the insulin withdrawal period, the patient should test urine samples for sugar and ketone bodies at least three times daily. Patients should be instructed to contact the prescriber immediately if these tests are abnormal. In some cases, especially when patient has been receiving greater than 40 units of insulin daily, it may be advisable to consider hospitalization during the transition period.
Patients Receiving Other Oral Hypoglycemic Agents As with other sulfonylurea-class hypoglycemics, no transition period is necessary when transferring patients to glipizide. Patients should be observed carefully (1 to 2 weeks) for hypoglycemia when being transferred from longer half-life sulfonylureas (e.g., chlorpropamide) to glipizide due to potential overlapping of drug effect. When colesevelam is coadministered with glipizide ER, maximum plasma concentration and total exposure to glipizide is reduced.
Therefore, glipizide should be administered at least 4 hours prior to colesevelam.
⛔ Contraindications ▾
CONTRAINDICATIONS Glipizide is contraindicated in patients with: 1. Known hypersensitivity to the drug. 2. Type 1 diabetes mellitus, diabetic ketoacidosis, with or without coma. This condition should be treated with insulin.
⚠️ Warnings ▾
WARNINGS SPECIAL WARNING ON INCREASED RISK OF CARDIOVASCULAR MORTALITY The administration of oral hypoglycemic drugs has been reported to be associated with increased cardiovascular mortality as compared to treatment with diet alone or diet plus insulin. This warning is based on the study conducted by the University Group Diabetes Program (UGDP), a long-term prospective clinical trial designed to evaluate the effectiveness of glucose-lowering drugs in preventing or delaying vascular complications in patients with non-insulin-dependent diabetes.
The study involved 823 patients who were randomly assigned to one of four treatment groups (Diabetes, 19, supp. 2: 747-830, 1970). UGDP reported that patients treated for 5 to 8 years with diet plus a fixed dose of tolbutamide (1.5 grams per day) had a rate of cardiovascular mortality approximately 2 1 / 2 times that of patients treated with diet alone.
A significant increase in total mortality was not observed, but the use of tolbutamide was discontinued based on the increase in cardiovascular mortality, thus limiting the opportunity for the study to show an increase in overall mortality. Despite controversy regarding the interpretation of these results, the findings of the UGDP study provide an adequate basis for this warning. The patient should be informed of the potential risks and advantages of glipizide and of alternative modes of therapy.
Although only one drug in the sulfonylurea class (tolbutamide) was included in this study, it is prudent from a safety standpoint to consider that this warning may also apply to other oral hypoglycemic drugs in this class, in view of their close similarities in mode of action and chemical structure.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In U.S. and foreign controlled studies, the frequency of serious adverse reactions reported was very low. Of 702 patients, 11.8% reported adverse reactions and in only 1.5% was glipizide discontinued. Hypoglycemia See PRECAUTIONS and OVERDOSAGE sections.
Gastrointestinal Gastrointestinal disturbances are the most common reactions. Gastrointestinal complaints were reported with the following approximate incidence: nausea and diarrhea, one in seventy; constipation and gastralgia, one in one hundred. They appear to be dose-related and may disappear on division or reduction of dosage.
Cholestatic jaundice may occur rarely with sulfonylureas: glipizide should be discontinued if this occurs. Dermatologic Allergic skin reactions including erythema, morbilliform or maculopapular eruptions, urticaria, pruritus, and eczema have been reported in about one in seventy patients. These may be transient and may disappear despite continued use of glipizide; if skin reactions persist, the drug should be discontinued.
Porphyria cutanea tarda and photosensitivity reactions have been reported with sulfonylureas. Hematologic Leukopenia, agranulocytosis, thrombocytopenia, hemolytic anemia (see PRECAUTIONS ), aplastic anemia, and pancytopenia have been reported with sulfonylureas. Metabolic Hepatic porphyria and disulfiram-like reactions have been reported with sulfonylureas.
In the mouse, glipizide pretreatment did not cause an accumulation of acetaldehyde after ethanol administration. Clinical experience to date has shown that glipizide has an extremely low incidence of disulfiram-like alcohol reactions. Endocrine Reactions Cases of hyponatremia and the syndrome of inappropriate antidiuretic hormone (SIADH) secretion have been reported with this and other sulfonylureas.
Miscellaneous Dizziness, drowsiness, and headache have each been reported in about one in fifty patients treated with glipizide. They are usually transient and seldom require discontinuance of therapy. Laboratory Tests The pattern of laboratory test abnormalities observed with glipizide was similar to that for other sulfonylureas.
Occasional mild to moderate elevations of SGOT, LDH, alkaline phosphatase, BUN, and creatinine were noted. One case of jaundice was reported. The relationship of these abnormalities to glipizide is uncertain, and they have rarely been associated with clinical symptoms.
Post-Marketing Experience The following adverse events have been reported in post-marketing surveillance : Hepatobiliary Cholestatic and hepatocellular forms of liver injury accompanied by jaundice have been reported rarely in association with glipizide; glipizide should be discontinued if this occurs.
🔄 Drug Interactions ▾
Drug Interactions The hypoglycemic action of sulfonylureas may be potentiated by certain drugs including nonsteroidal anti-inflammatory agents, some azoles, and other drugs that are highly protein bound, salicylates, sulfonamides, chloramphenicol, probenecid, coumarins, monoamine oxidase inhibitors, quinolones and beta adrenergic blocking agents. When such drugs are administered to a patient receiving glipizide, the patient should be observed closely for hypoglycemia. When such drugs are withdrawn from a patient receiving glipizide, the patient should be observed closely for loss of control.
In vitro binding studies with human serum proteins indicate that glipizide binds differently than tolbutamide and does not interact with salicylate or dicumarol. However, caution must be exercised in extrapolating these findings to the clinical situation and in the use of glipizide with these drugs. Certain drugs tend to produce hyperglycemia and may lead to loss of control.
These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, and isoniazid. When such drugs are administered to a patient receiving glipizide, the patient should be closely observed for loss of control. When such drugs are withdrawn from a patient receiving glipizide, the patient should be observed closely for hypoglycemia.
A potential interaction between oral miconazole and oral hypoglycemic agents leading to severe hypoglycemia has been reported. Whether this interaction also occurs with the intravenous, topical, or vaginal preparations of miconazole is not known. The effect of concomitant administration of fluconazole and glipizide has been demonstrated in a placebo-controlled crossover study in normal volunteers.
All subjects received glipizide alone and following treatment with 100 mg of fluconazole as a single daily oral dose for 7 days. The mean percentage increase in the glipizide AUC after fluconazole administration was 56.9% (range: 35 to 81). In studies assessing the effect of colesevelam on the pharmacokinetics of glipizide ER in healthy volunteers, reductions in glipizide AUC 0-∞ and C max of 12% and 13%, respectively were observed when colesevelam was coadministered with glipizide ER.
When glipizide ER was administered 4 hours prior to colesevelam, there was no significant change in glipizide AUC 0-∞ or C max , -4% and 0%, respectively. Therefore, glipizide should be administered at least 4 hours prior to colesevelam to ensure that colesevelam does not reduce the absorption of glipizide.
🤰 Pregnancy ▾
Pregnancy Pregnancy Category C Glipizide was found to be mildly fetotoxic in rat reproductive studies at all dose levels (5 to 50 mg/kg). This fetotoxicity has been similarly noted with other sulfonylureas, such as tolbutamide and tolazamide. The effect is perinatal and believed to be directly related to the pharmacologic (hypoglycemic) action of glipizide.
In studies in rats and rabbits, no teratogenic effects were found. There are no adequate and well controlled studies in pregnant women. Glipizide should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
Because recent information suggests that abnormal blood glucose levels during pregnancy are associated with a higher incidence of congenital abnormalities, many experts recommend that insulin be used during pregnancy to maintain blood glucose levels as close to normal as possible.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in children have not been established.
🧓 Geriatric Use ▾
Geriatric Use A determination has not been made whether controlled clinical studies of glipizide included sufficient numbers of subjects aged 65 and over to define a difference in response from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of decreased hepatic, renal, or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE There is no well documented experience with glipizide overdosage. The acute oral toxicity was extremely low in all species tested (LD 50 greater than 4 g/kg). Overdosage of sulfonylureas, including glipizide, can produce hypoglycemia.
Mild hypoglycemic symptoms without loss of consciousness or neurologic findings should be treated aggressively with oral glucose and adjustments in drug dosage and/or meal patterns. Close monitoring should continue until the physician is assured that the patient is out of danger. Severe hypoglycemic reactions with coma, seizure, or other neurological impairment occur infrequently, but constitute medical emergencies requiring immediate hospitalization.
If hypoglycemic coma is diagnosed or suspected, the patient should be given a rapid intravenous injection of concentrated (50%) glucose solution. This should be followed by a continuous infusion of a more dilute (10%) glucose solution at a rate that will maintain the blood glucose at a level above 100 mg/dL. Patients should be closely monitored for a minimum of 24 to 48 hours since hypoglycemia may recur after apparent clinical recovery.
Clearance of glipizide from plasma would be prolonged in persons with liver disease. Because of the extensive protein binding of glipizide, dialysis is unlikely to be of benefit.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action The primary mode of action of glipizide in experimental animals appears to be the stimulation of insulin secretion from the beta cells of pancreatic islet tissue and is thus dependent on functioning beta cells in the pancreatic islets. In humans, glipizide appears to lower the blood glucose acutely by stimulating the release of insulin from the pancreas, an effect dependent upon functioning beta cells in the pancreatic islets. The mechanism by which glipizide lowers blood glucose during long-term administration has not been clearly established.
In man, stimulation of insulin secretion by glipizide in response to a meal is undoubtedly of major importance. Fasting insulin levels are not elevated even on long-term glipizide administration, but the postprandial insulin response continues to be enhanced after at least 6 months of treatment. The insulinotropic response to a meal occurs within 30 minutes after an oral dose of glipizide in diabetic patients, but elevated insulin levels do not persist beyond the time of the meal challenge.
Extrapancreatic effects may play a part in the mechanism of action of oral sulfonylurea hypoglycemic drugs. Blood sugar control persists in some patients for up to 24 hours after a single dose of glipizide, even though plasma levels have declined to a small fraction of peak levels by that time (see Pharmacokinetics below). Some patients fail to respond initially, or gradually lose their responsiveness to sulfonylurea drugs, including glipizide.
Alternatively, glipizide may be effective in some patients who have not responded or have ceased to respond to other sulfonylureas. Other Effects It has been shown that glipizide therapy was effective in controlling blood sugar without deleterious changes in the plasma lipoprotein profiles of patients treated for NIDDM. In a placebo-controlled, crossover study in normal volunteers, glipizide had no antidiuretic activity and, in fact, led to a slight increase in free water clearance.
Pharmacokinetics Gastrointestinal absorption of glipizide in man is uniform, rapid, and essentially complete. Peak plasma concentrations occur 1 to 3 hours after a single oral dose. The half-life of elimination ranges from 2 to 4 hours in normal subjects, whether given intravenously or orally.
The metabolic and excretory patterns are similar with the two routes of administration, indicating that first-pass metabolism is not significant. Glipizide does not accumulate in plasma on repeated oral administration. Total absorption and disposition of an oral dose was unaffected by food in normal volunteers, but absorption was delayed by about 40 minutes.
Thus, glipizide was more effective when administered about 30 minutes before, rather than with, a test meal in diabetic patients. Protein binding was studied in serum from volunteers who received either oral or intravenous glipizide and found to be 98 to 99% one hour after either route of administration. The apparent volume of distribution of glipizide after intravenous administration was 11 liters, indicative of localization within the extracellular fluid compartment.
In mice, no glipizide or metabolites were detectable autoradiographically in the brain or spinal cord of males or females, nor in the fetuses of pregnant females. In another study, however, very small amounts of radioactivity were detected in the fetuses of rats given labeled drug. The metabolism of glipizide is extensive and occurs mainly in the liver.
The primary metabolites are inactive hydroxylation products and polar conjugates and are excreted mainly in the urine. Less than 10% unchanged glipizide is found in the urine.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Glipizide Tablets, USP are supplied as white to off-white, round, scored tablets, imprinted as follows: 5 mg- “APO” on the side and “GLP” over bisect “5” on the other side. NDC: 71335-0930-1: 100 Tablets in a BOTTLE NDC: 71335-0930-2: 30 Tablets in a BOTTLE NDC: 71335-0930-3: 60 Tablets in a BOTTLE NDC: 71335-0930-4: 90 Tablets in a BOTTLE NDC: 71335-0930-5: 20 Tablets in a BOTTLE NDC: 71335-0930-6: 180 Tablets in a BOTTLE NDC: 71335-0930-7: 10 Tablets in a BOTTLE Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 91504
📋 Description ▾
DESCRIPTION Glipizide is an oral blood-glucose-lowering drug of the sulfonylurea class. The Chemical Abstracts name of glipizide is 1-cyclohexyl-3-[[p-[2-(5-methylpyrazine-carboxamido)ethyl]phenyl]sulfonyl]urea. The molecular formula is C 21 H 27 N 5 O 4 S; the molecular weight is 445.55; the structural formula is shown below: Glipizide is a whitish, odorless powder with a pKa of 5.9. It is insoluble in water and alcohols, but soluble in
0.1N NaOH; it is freely soluble in dimethylformamide. Glipizide tablets, USP for oral use are available in 5 and 10 mg strengths. Inert ingredients are: anhydrous lactose; colloidal silicon dioxide; magnesium stearate; sodium starch glycolate. Meets USP Dissolution Test 2.