
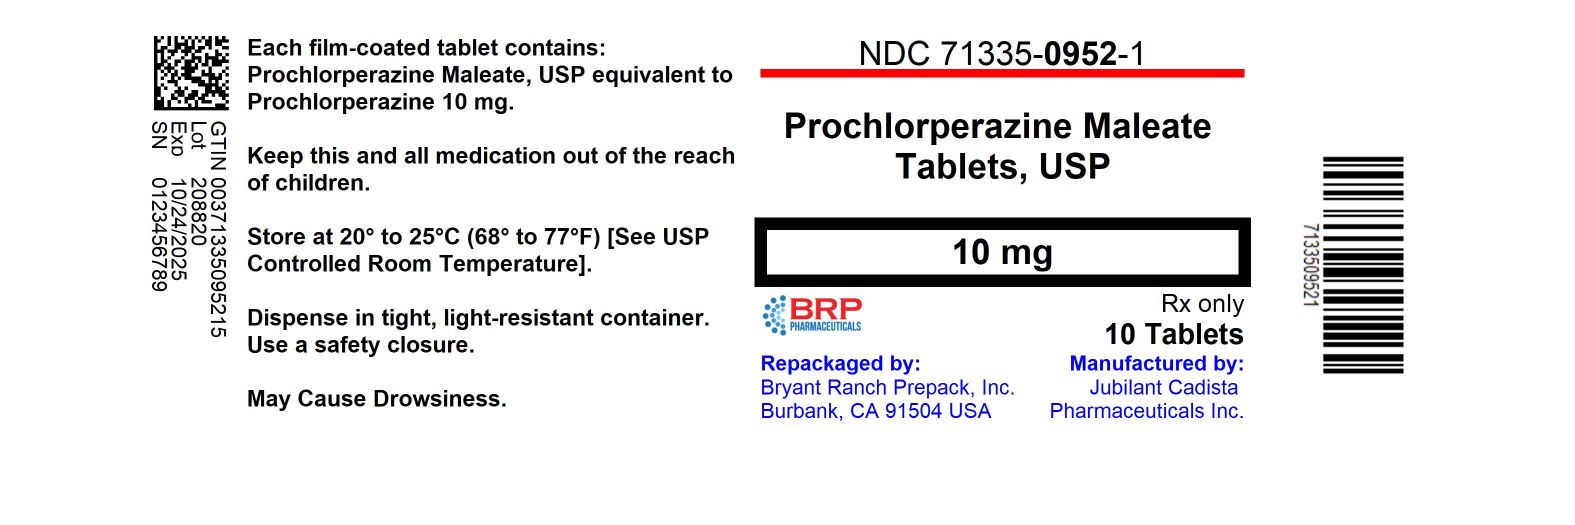
PROCHLORPERAZINE MALEATE 10 mg Tablet, 100-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Phenothiazine class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Prochlorperazine suppositories and tablets are used to control severe nausea and vomiting. Prochlorperazine tablets are also used to treat the symptoms of schizophrenia (a mental illness that causes disturbed or unusual thinking, loss of interest in life, and strong or inappropriate emotions). Prochlorperazine tablets are also used on a short-term basis to treat anxiety that could not be controlled by other medications. Prochlorperazine should not be used to treat any condition in children who are younger than 2 years old or who weigh less than 20 pounds (about 9 kilograms). Prochlorperazine i...
Read the full MedlinePlus article ↗- Prochlorperazine is most commonly used to control severe nausea and vomiting. Depending on the form your doctor prescribed, it may also be used to treat schizophrenia. The tablet f...
- What is prochlorperazine actually used for?
- The most common ones are drowsiness, dizziness, blurred vision, and a drop in blood pressure when you stand up quickly. More serious — but less common — reactions include uncontrol...
- What side effects should I watch out for?
Patient education
Supplement & herbal interactions
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII LMI26O6933
Alumina is a white powder form of aluminum oxide. It's used as a filler to add bulk to tablets and capsules, and sometimes as a thickening or anti-caking agent in powdered formulations.
-
UNII 35SW5USQ3G
A synthetic yellow dye used to color medicines. It helps make tablets, capsules, and liquids visually distinct so patients can easily identify their medication.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 6OZP39ZG8H
Polysorbate 80 is a synthetic emulsifier derived from sorbitol and oleic acid. It helps mix oil and water-based ingredients together in medications and improves how the product disperses in the body.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 4ELV7Z65AP
Stearic acid is a fatty acid derived from plant or animal sources. It acts as a binder and lubricant in tablets and capsules, helping them hold together and flow smoothly during manufacturing.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.2949 | $29.49 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Prochlorperazine Maleate 10 mg 00904-7382-06 | Major | 50 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 27241-0287-01 | Ajanta | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 50268-0685-15 | AvPAK | 50 tablets | $0.169 | AB | Availability likely | — |
| prochlorperazine maleate 10 mg 59651-0774-01 | Aurobindo | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 59746-0115-06 | Jubilant | 100 tablets | $0.169 | AB | Availability likely | — |
| prochlorperazine maleate 10 mg 60219-2039-01 | Amneal | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 60687-0825-65 | American | 1 tablet | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 62135-0674-90 | Chartwell | 90 tablets | $0.169 | — | Availability likely | — |
| Prochlorperazine Maleate 10 mg 68462-0947-01 | GLENMARK | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 69315-0266-01 | Leading | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 69452-0310-20 | Bionpharma | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 69452-0472-20 | Bionpharma | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 70710-1668-01 | Zydus | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 70954-0689-10 | ANI | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 72603-0169-01 | Northstar | 100 tablets | $0.169 | AB | Availability likely | — |
| Prochlorperazine Maleate 10 mg 42708-0103-12 | QPharma, | 12 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 43063-0742-06 | PD-Rx | 6 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 50090-2839-00 | A-S | 30 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 51655-0330-52 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 55154-4342-00 | Cardinal | 10 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 63187-0251-15 | Proficient | 15 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 67296-2195-01 | Redpharm | 100 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 68788-8708-01 | Preferred | 10 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 70518-1620-00 | REMEDYREPACK | 30 tablets | — | AB | Discontinued | — |
| Prochlorperazine Maleate 10 mg 70518-4200-00 | REMEDYREPACK | 10 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 70518-4319-00 | REMEDYREPACK | 10 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 70771-1698-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mgthis 71335-0952-07 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 71335-2386-01 | Bryant | 10 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 72162-2262-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 72189-0503-30 | Direct_Rx | 30 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 72789-0518-01 | PD-Rx | 100 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 82868-0044-30 | Northwind | 30 tablets | — | AB | FDA listed | — |
| Prochlorperazine Maleate 10 mg 85766-0233-01 | Sportpharm | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-0952-01 | 10 TABLET in 1 BOTTLE (71335-0952-1) | 2006-03-14 | Active |
| 71335-0952-02 | 30 TABLET in 1 BOTTLE (71335-0952-2) | 2006-03-14 | Active |
| 71335-0952-03 | 20 TABLET in 1 BOTTLE (71335-0952-3) | 2006-03-14 | Active |
| 71335-0952-04 | 60 TABLET in 1 BOTTLE (71335-0952-4) | 2006-03-14 | Active |
| 71335-0952-05 | 4 TABLET in 1 BOTTLE (71335-0952-5) | 2006-03-14 | Active |
| 71335-0952-06 | 5 TABLET in 1 BOTTLE (71335-0952-6) | 2006-03-14 | Active |
| 71335-0952-07 You're viewing this | 100 TABLET in 1 BOTTLE (71335-0952-7) | 2006-03-14 | Active |
| 71335-0952-08 | 6 TABLET in 1 BOTTLE (71335-0952-8) | 2006-03-14 | Active |
You're viewing the largest of 8 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-0952-07?
What is the difference between NDC 71335-0952-07 and NDC 71335-0952-05?
What NDC number is used to bill for this package of PROCHLORPERAZINE MALEATE 10 mg Tablet?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of seventeen placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5% compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Observational studies suggest that, similar to atypical antipsychotic drugs, treatment with conventional antipsychotic drugs may increase mortality. The extent to which the findings of increased mortality in observational studies may be attributed to the antipsychotic drug as opposed to some characteristic(s) of the patients is not clear.
Prochlorperazine maleate is not approved for the treatment of patients with dementia-related psychosis (see WARNINGS ). Structure of Prochlorperazine
🎯 Indications and Usage ▾
INDICATIONS AND USAGE For control of severe nausea and vomiting. For the treatment of schizophrenia. Prochlorperazine is effective for the short-term treatment of generalized non-psychotic anxiety.
However, prochlorperazine is not the first drug to be used in therapy for most patients with non-psychotic anxiety, because certain risks associated with its use are not shared by common alternative treatments (e.g., benzodiazepines). When used in the treatment of non-psychotic anxiety, prochlorperazine should not be administered at doses of more than 20 mg per day or for longer than 12 weeks, because the use of prochlorperazine at higher doses or for longer intervals may cause persistent tardive dyskinesia that may prove irreversible (see WARNINGS ).
The effectiveness of prochlorperazine as treatment for non-psychotic anxiety was established in 4-week clinical studies of outpatients with generalized anxiety disorder. This evidence does not predict that prochlorperazine will be useful in patients with other non-psychotic conditions in which anxiety, or signs that mimic anxiety, are found (e.g., physical illness, organic mental conditions, agitated depression, character pathologies, etc.). Prochlorperazine has not been shown effective in the management of behavioral complications in patients with mental retardation.
⏱️ Dosage and Administration ▾
DOSAGE & ADMINISTRATION - ADULTS (For children’s dosage and administration, see below.) Dosage should be increased more gradually in debilitated or emaciated patients. Elderly Patients: In general, dosages in the lower range are sufficient for most elderly patients. Since they appear to be more susceptible to hypotension and neuromuscular reactions, such patients should be observed closely.
Dosage should be tailored to the individual, response carefully monitored and dosage adjusted accordingly. Dosage should be increased more gradually in elderly patients. 1.To Control Severe Nausea and Vomiting: Adjust dosage to the response of the individual.
Begin with the lowest recommended dosage. Oral Dosage-Tablets: Usually one 5mg or 10mg tablet 3 or 4 times daily. Daily dosages above 40 mgs should be used only in resistant cases.
2.In Adult Psychiatric Disorders: Adjust dosage to the response of the individual and according to the severity of the condition. Begin with the lowest recommended dose. Although response ordinarily is seen within a day or 2, longer treatment is usually required before maximal improvement is seen.
Oral Dosage: Non-Psychotic Anxiety--Usual dosage is 5 mg 3 or4 times daily. Do not administer in doses of more than 20mg per day or for longer than 12 weeks. Psychotic Disorders including Schizophrenia -- In relatively mild conditions , as seen in private psychiatric practice or in out patient clinics, dosage is 5 or 10 mg 3 or 4 times daily.
In moderate to severe conditions, for hospitalized or adequately supervised patients, usual starting dosage is 10 mg 3 or 4 times daily. Increase dosage gradually until symptoms are controlled or side effects become bothersome. When dosage is increased by small increments every 2 or 3 days, side effects either do not occur or are easily controlled.
Some patients respond satisfactorily on 50 to 75mg daily. In more severe disturbances, optimum dosage is usually 100 to 150mg daily. DOSAGE AND ADMINISTRATION--CHILDREN Do not use in pediatric surgery.
Children seem more prone to develop extrapyramidal reactions, even on moderate doses. Therefore, use lowest effective dosage. Tell parents not to exceed prescribed dosage, since the possibility for adverse reactions increases as dosage rises.
Occasionally the patient may react to the drug with signs of restlessness and excitement; if this occurs, do not administer additional doses. Take particular precaution in administering the drug to children with acute illnesses or dehydration (see under Dystonias). 1.
Severe Nausea and Vomiting in Children: Prochlorperazine should not be used in pediatric patients under 20 pounds in weight or 2 years of age. It should not be used in conditions for which children’s dosages have not been established. Dosage and frequency of administration should be adjusted according to the severity of the symptoms and the response of the patient.
The duration of activity following intramuscular administration may last up to 12 hours. Subsequent doses may be given by the same route if necessary. Oral Dosage: More than 1 day’s therapy is seldom necessary.
Weight Usual Dosage Not to Exceed under 20 lbs not recommended 20 to 29 lbs 2½ mg 1 or 2 times a day 7.5 mg per day 30 to 39 lbs 2½ mg 2 or 3 times a day 10 mg per day 40 to 85 lbs 2½ mg 3 times a day or 5 mg 2 times a day 15 mg per day 2. Children with schizophrenia: Oral Dosage: For children 2 to 12 years, starting dosage is 2 1 /2 mg 2 or 3 times daily. Do not give more than 10 mg the first day.
Then increase dosage according to patient’s response. FOR AGES 2 to 5, total daily dosage usually does not exceed 20 mg. FOR AGES 6 to 12, total daily dosage usually does not exceed 25 mg.
⛔ Contraindications ▾
CONTRAINDICATIONS Do not use in patients with known hypersensitivity to phenothiazines. Do not use in comatose states or in the presence of large amounts of central nervous system depressants (alcohol, barbiturates, narcotics, etc.). Do not use in pediatric surgery. Do not use in pediatric patients under 2 years of age or under 20 lbs. Do not use in children for conditions for which dosage has not been established.
⚠️ Warnings ▾
WARNINGS Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Prochlorperazine maleate is not approved for the treatment of patients with dementia-related psychosis (see BOXED WARNING ). The extrapyramidal symptoms which can occur secondary to prochlorperazine may be confused with the central nervous system signs of an undiagnosed primary disease responsible for the vomiting, e.g., Reye’s syndrome or other encephalopathy.
The use of prochlorperazine and other potential hepatotoxins should be avoided in children and adolescents whose signs and symptoms suggest Reye’s syndrome. Tardive Dyskinesia: Tardive dyskinesia, a syndrome consisting of potentially irreversible, involuntary, dyskinetic movements, may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic drug treatment, which patients are likely to develop the syndrome.
Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown. Both the risk of developing the syndrome and the likelihood that it will become irreversible are believed to increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses.
There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic drug treatment is withdrawn. Antipsychotic drug treatment itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and thereby may possibly mask the underlying disease process. The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown.
Given these considerations, antipsychotic drugs should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia especially in the elderly. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that, 1) is known to respond to antipsychotic drugs, and 2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate. In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought.
The need for continued treatment should be reassessed periodically. If signs and symptoms of tardive dyskinesia appear in a patient on antipsychotics, drug discontinuation should be considered. However, some patients may require treatment despite the presence of the syndrome.
For further information about the description of tardive dyskinesia and its clinical detection, please refer to the sections on PRECAUTIONS and ADVERSE REACTIONS . Neuroleptic Malignant Syndrome (NMS): A potentially fatal syndrome complex sometimes referred to as neuroleptic Malignant Syndrome (NMS) has been reported in association with antipsychotic drugs. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis and cardiac dysrhythmias).
The diagnostic evaluation of patients with this syndrome is complicated. In arriving at a diagnosis, it is important to identify cases where the clinical presentation includes both serious medical illness (e.g., pneumonia, systemic infection, etc.) and untreated or inadequately treated extrapyramidal signs and symptoms (EPS). Other important considerations in the differential diagnosis include central anticholinergic toxicity, he…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Drowsiness, dizziness, amenorrhea, blurred vision, skin reactions and hypotension may occur. Neuroleptic Malignant Syndrome (NMS) has been reported in association with antipsychotic drugs (see WARNINGS ). Cholestatic jaundice has occurred.
If fever with grippe-like symptoms occurs, appropriate liver studies should be conducted. If tests indicate an abnormality, stop treatment. There have been a few observations of fatty changes in the livers of patients who have died while receiving the drug.
No causal relationship has been established. Leukopenia and agranulocytosis have occurred. Warn patients to report the sudden appearance of sore throat or other signs of infection.
If white blood cell and differential counts indicate leukocyte depression, stop treatment and start antibiotic and other suitable therapy. Neuromuscular (Extrapyramidal) Reactions These symptoms are seen in a significant number of hospitalized mental patients. They maybe characterized by motor restlessness, be of the dystonic type, or they may resemble parkinsonism.
Depending on the severity of symptoms, dosage should be reduced or discontinued. If therapy is reinstituted, it should be at a lower dosage. Should these symptoms occur in children or pregnant patients, the drug should be stopped and not reinstituted.
In most cases barbiturates by suitable route of administration will suffice. (Or, injectable Benadryl ® ll may be useful). In more severe cases, the administration of an anti-parkinsonism agent, except levodopa (See PDR), usually produces rapid reversal of symptoms.
Suitable supportive measures such as maintaining a clear airway and adequate hydration should be employed. Dystonia Class effect: Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue.
While these symptoms can occur at low doses, they occur more frequently and with greater severity with high potency and at higher doses of first generation antipsychotic drugs. An elevated risk of acute dystonia is observed in males and younger age groups. These usually subside within a few hours, and almost always within 24 to 48 hours, after the drug has been discontinued.
Motor Restlessness: Symptoms may include agitation or jitteriness and sometimes insomnia. These symptoms often disappear spontaneously. At times these symptoms may be similar to the original neurotic or psychotic symptoms.
Dosage should not be increased until these side effects have subsided. If these symptoms become too troublesome, they can usually be controlled by a reduction of dosage or change of drug. Treatment with anti-parkinsonian agents, benzodiazepines or propranolol may be helpful.
Pseudo-Parkinsonism: Symptoms may include: mask-like facies; drooling; tremors; pillrolling motion; cog-wheel rigidity; and shuffling gait. Reassurance and sedation are important. In most cases these symptoms are readily controlled when an anti-parkinsonism agent is administered concomitantly.
Anti- parkinsonism agents should be used only when required. Generally, therapy of a few weeks to 2 or 3 months will suffice. After this time patients should be evaluated to determine their need for continued treatment.
(Note: Levodopa has not been found effective in pseudo-parkinsonism). Occasionally it is necessary to lower the dosage of prochlorperazine or to discontinue the drug. Tardive Dyskinesia: As with all antipsychotic agents, tardive dyskinesia may appear in some patients on long-term therapy or may appear after drug therapy has been discontinued.
The syndrome can also develop, although much less frequently, after relatively brief treatment periods at low doses. This syndrome appears in all age groups. Although its prevalence appears to be highest among elderly…
🆘 Overdosage ▾
OVERDOSAGE (See also ADVERSE REACTIONS . ) SYMPTOMS --Primarily involvement of the extrapyramidal mechanism producing some of the dystonic reactions described above. Symptoms of central nervous system depression to the point of somnolence or coma. Agitation and restlessness may also occur.
Other possible manifestations include convulsions, EKG changes and cardiac arrhythmias, fever and autonomic reactions such as hypotension, dry mouth and ileus. TREATMENT--It is important to determine other medications taken by the patient since multiple-dose therapy is common in overdosage situations. Treatment is essentially symptomatic and supportive.
Early gastric lavage is helpful. Keep patient under observation and maintain an open airway, since involvement of the extrapyramidal mechanism may produce dysphagia and respiratory difficulty in severe overdosage. Do not attempt to induce emesis because a dystonic reaction of the head or neck may develop that could result in aspiration of vomitus.
Extrapyramidal symptoms may be treated with antiparkinsonism drugs, barbiturates or Benadryl. See prescribing information for these products. Care should be taken to avoid increasing respiratory depression.
If administration of a stimulant is desirable, amphetamine, dextroamphetamine or caffeine with sodium benzoate is recommended. Stimulants that may cause convulsions (e.g., picrotoxin or pentylenetetrazol) should be avoided. If hypotension occurs, the standard measures for managing circulatory shock should be initiated.
If it is desirable to administer a vasoconstrictor, Levophed and Neo-Synephrine are most suitable. Other pressor agents, including epinephrine, are not recommended because phenothiazine derivatives may reverse the usual elevating action of these agents and cause further lowering of blood pressure. Limited experience indicates that phenothiazines are not dialyzable.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED 10mg Chartreuse, round, film-coated tablet debossed with "TL" on the top and "115" on the bottom of the score line on one side and plain on the other side. Product: 71335-0952 NDC: 71335-0952-1 10 TABLET in a BOTTLE NDC: 71335-0952-2 30 TABLET in a BOTTLE NDC: 71335-0952-3 20 TABLET in a BOTTLE NDC: 71335-0952-4 60 TABLET in a BOTTLE NDC: 71335-0952-5 4 TABLET in a BOTTLE NDC: 71335-0952-6 5 TABLET in a BOTTLE NDC: 71335-0952-7 100 TABLET in a BOTTLE NDC: 71335-0952-8 6 TABLET in a BOTTLE Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 91504
📦 Storage and Handling ▾
STORAGE Store at 20 to 25°C (68 to 77°F) [See USP Controlled Room Temperature]. Protect from light. Dispense in a tight, light-resistant container. * norepinephrine bitartrate, Abbott Laboratories. ** phenylephrine hydrochloride, Abbott Laboratories. *** phenytoin, Parke Davis. § metrizamide, Sanofi Pharmaceuticals. ll diphenhydramine hydrochloride, Parke Davis.
Manufactured by: Jubilant Cadista Pharmaceuticals Inc. Salisbury, MD 21801, USA Revised: 10/2018
📋 Description ▾
DESCRIPTION Prochlorperazine, USP is a phenothiazine derivative, present in prochlorperazine tablets as the maleate. Prochlorperazine maleate is designated chemically as 2-chloro-10-[3-(4- methyl-1 -piperazinyl)propyl] phenothiazine maleate [molecular weight 606.10] and has the following structure Prochlorperazine Maleate is classified as an anti-emetic and antipsychotic agent. Prochlorperazine maleate is white or pale yellow, practically odorless crystalline powder.
It is practically insoluble in water and in alcohol; slightly soluble in warm chloroform. Each tablet, for oral administration contains prochlorperazine maleate equivalent to 5 mg or 10 mg of prochlorperazine. In addition, each tablet contains the following inactive ingredients: D&C yellow no.
10 aluminum lake, FD&C blue no. 2 aluminum lake, FD&C yellow no. 6 aluminum lake, hydroxypropyl methylcellulose, lactose monohydrate, magnesium stearate, microcrystalline cellulose, polyethylene glycol, polysorbate 80, pregelatinized starch, stearic acid and titanium dioxide.