
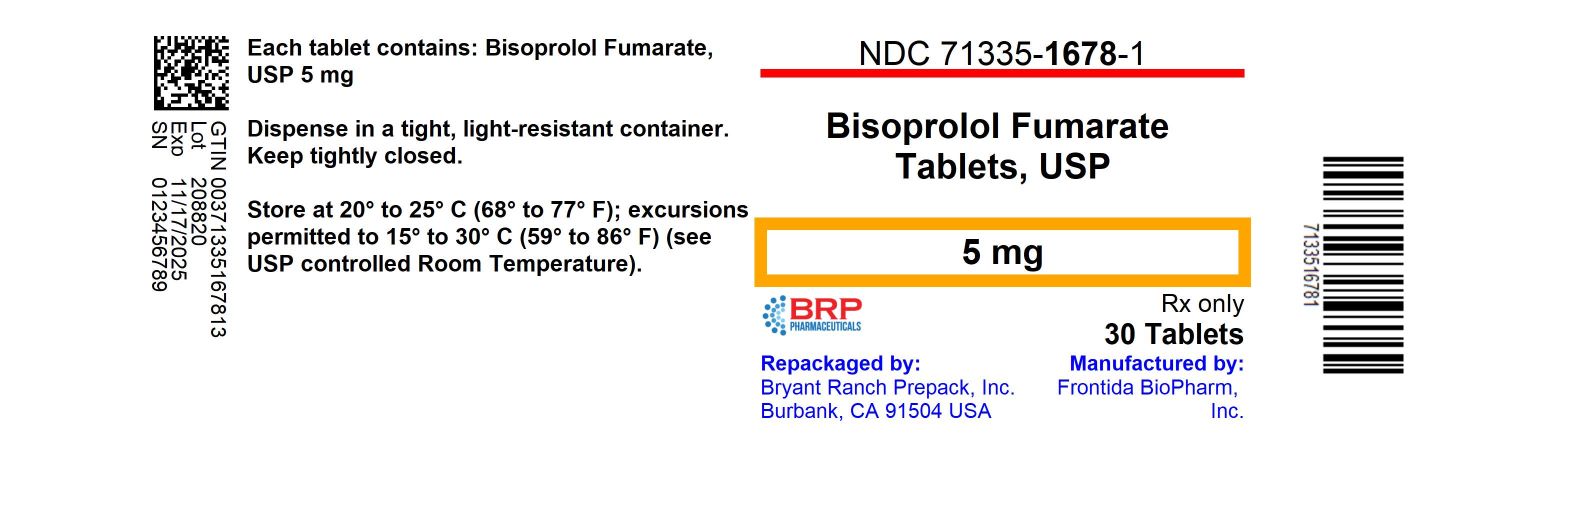
Bisoprolol 5 mg Tablet, Film Coated, 120-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- Bisoprolol is used to lower high blood pressure (hypertension). It works by slowing your heart rate and reducing the force of each heartbeat, which takes pressure off your arteries...
- Please don't stop it suddenly without talking to your doctor first. Even if you feel great, stopping bisoprolol abruptly — especially if you have any underlying heart disease — can...
- Can I stop taking bisoprolol if I feel fine?
- Beta-blockers like bisoprolol generally aren't recommended if you have asthma or COPD because they can cause airway tightening (bronchospasm). That said, bisoprolol is more heart-s...
Patient education
Supplement & herbal interactions
Bisoprolol may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII R12CBM0EIZ
A natural wax derived from a Brazilian palm tree, used as a coating and polish on tablets and capsules. It creates a smooth, shiny finish that protects the medicine and improves appearance.
-
UNII 2S7830E561
Crospovidone is a synthetic polymer derived from povidone. It acts as a disintegrant, helping the tablet or capsule break apart quickly in the stomach so the active ingredient can be absorbed.
-
UNII O7TSZ97GEP
A mineral compound that serves as a filler and binding agent in tablets and capsules. It adds bulk to the medicine and helps hold ingredients together during manufacturing.
-
UNII L06K8R7DQK
A synthetic blue dye approved by the FDA for use in medications and foods. It serves as a colorant to make pills and liquids visually distinct and easier to identify.
-
UNII WZB9127XOA
A synthetic red dye used to color medications and make them easier to identify. It serves as a colorant in tablets, capsules, and liquid formulations.
-
UNII H77VEI93A8
A synthetic yellow dye used to color medications. It helps identify the drug and make it visually distinctive, with no effect on how the medicine works.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII VH2XOU12IE
Polydextrose is a synthetic polymer made from dextrose (sugar) that acts as a bulking agent and filler in medicines. It helps give tablets and capsules proper volume and texture while often adding slight sweetness.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
-
UNII XHX3C3X673
Triacetin is a clear, oily liquid made from glycerin and acetic acid. It works as a plasticizer and solvent in medicines, helping soften coatings and improve how liquids mix together in formulations.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3944 | $47.33 / 120 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Bisoprolol Fumarate 5 mg 16714-0529-01 | NorthStar | 30 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 29300-0126-01 | Unichem | 100 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol fumarate 5 mg 43547-0616-03 | Solco | 30 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 50268-0127-15 | AvPAK | 1 tablet | $0.123 | AB | Availability likely | — |
| Bisoprolol 5 mg 52817-0270-10 | TruPharma, | 100 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 60687-0679-21 | American | 30 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 62332-0603-30 | Alembic | 30 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 64980-0709-01 | Rising | 100 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 65862-0086-01 | Aurobindo | 100 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 70095-0020-01 | Sun | 30 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 70954-0455-10 | Novitium | 30 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol Fumarate 5 mg 72578-0111-01 | Viona | 100 tablets | $0.123 | AB | Availability likely | — |
| Bisoprolol 5 mg 42571-0470-01 | Micro | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 46708-0603-30 | Alembic | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 51407-0645-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 63187-0871-30 | Proficient | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 63629-5173-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 68788-8671-01 | Preferred | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol fumarate 5 mg 69339-0236-01 | Natco | 100 tablets | — | — | FDA listed | — |
| Bisoprolol Fumarate 5 mg 70771-1726-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol 5 mgthis 71335-1678-05 | Bryant | 120 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 71335-2178-01 | Bryant | 30 tablets | — | AB | FDA listed | — |
| Bisoprolol 5 mg 72162-2177-01 | Bryant | 100 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 72789-0392-82 | PD-Rx | 500 tablets | — | AB | FDA listed | — |
| Bisoprolol Fumarate 5 mg 72888-0092-00 | Advagen | 1000 tablets | — | — | FDA listed | — |
| Bisoprolol Fumarate 5 mg 82638-0107-01 | Harman | 30 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1678-01 | 30 TABLET, FILM COATED in 1 BOTTLE (71335-1678-1) | 2020-07-28 | Active |
| 71335-1678-02 | 100 TABLET, FILM COATED in 1 BOTTLE (71335-1678-2) | 2021-12-29 | Active |
| 71335-1678-03 | 90 TABLET, FILM COATED in 1 BOTTLE (71335-1678-3) | 2021-12-29 | Active |
| 71335-1678-04 | 28 TABLET, FILM COATED in 1 BOTTLE (71335-1678-4) | 2021-12-29 | Active |
| 71335-1678-05 You're viewing this | 120 TABLET, FILM COATED in 1 BOTTLE (71335-1678-5) | 2021-12-29 | Active |
You're viewing the largest of 5 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1678-05?
What is the difference between NDC 71335-1678-05 and NDC 71335-1678-04?
What NDC number is used to bill for this package of Bisoprolol 5 mg Tablet, Film Coated?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Bisoprolol fumarate tablets are indicated in the management of hypertension. It may be used alone or in combination with other antihypertensive agents.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION The dose of bisoprolol fumarate must be individualized to the needs of the patient. The usual starting dose is 5 mg once daily. In some patients, 2.5 mg may be an appropriate starting dose (see WARNINGS : Bronchospastic Disease ).
If the antihypertensive effect of 5 mg is inadequate, the dose may be increased to 10 mg and then, if necessary, to 20 mg once daily. Patients with Renal or Hepatic Impairment In patients with hepatic impairment (hepatitis or cirrhosis) or renal dysfunction (creatinine clearance less than 40 mL/min), the initial daily dose should be 2.5 mg and caution should be used in dose titration. Since limited data suggest that bisoprolol fumarate is not dialyzable, drug replacement is not necessary in patients undergoing dialysis.
Geriatric Patients It is not necessary to adjust the dose in the elderly, unless there is also significant renal or hepatic dysfunction (see above and Geriatric Use in PRECAUTIONS ). Pediatric Patients There is no pediatric experience with bisoprolol fumarate.
⛔ Contraindications ▾
CONTRAINDICATIONS Bisoprolol fumarate tablets are contraindicated in patients with cardiogenic shock, overt cardiac failure, second or third degree AV block and marked sinus bradycardia.
⚠️ Warnings ▾
WARNINGS Cardiac Failure Sympathetic stimulation is a vital component supporting circulatory function in the setting of congestive heart failure, and beta-blockade may result in further depression of myocardial contractility and precipitate more severe failure. In general, beta-blocking agents should be avoided in patients with overt congestive failure. However, in some patients with compensated cardiac failure it may be necessary to utilize them.
In such a situation, they must be used cautiously. In Patients Without a History of Cardiac Failure Continued depression of the myocardium with beta-blockers can, in some patients, precipitate cardiac failure. At the first signs or symptoms of heart failure, discontinuation of bisoprolol fumarate tablets should be considered.
In some cases, beta-blocker therapy can be continued while heart failure is treated with other drugs. Abrupt Cessation of Therapy Exacerbation of angina pectoris, and, in some instances, myocardial infarction or ventricular arrhythmia, have been observed in patients with coronary artery disease following abrupt cessation of therapy with beta-blockers. Such patients should, therefore, be cautioned against interruption or discontinuation of therapy without the physician’s advice.
Even in patients without overt coronary artery disease, it may be advisable to taper therapy with bisoprolol fumarate tablets over approximately one week with the patient under careful observation. If withdrawal symptoms occur, bisoprolol fumarate tablets therapy should be reinstituted, at least temporarily. Peripheral Vascular Disease Beta-blockers can precipitate or aggravate symptoms of arterial insufficiency in patients with peripheral vascular disease.
Caution should be exercised in such individuals. Bronchospastic Disease PATIENTS WITH BRONCHOSPASTIC DISEASE SHOULD, IN GENERAL, NOT RECEIVE BETA-BLOCKERS. Because of its relative beta 1 -selectivity, however, bisoprolol may be used with caution in patients with bronchospastic disease who do not respond to, or who cannot tolerate other antihypertensive treatment.
Since beta 1 -selectivity is not absolute, the lowest possible dose of bisoprolol fumarate tablets should be used, with therapy starting at 2.5 mg. A beta 2 agonist (bronchodilator) should be made available. Major Surgery Chronically administered beta-blocking therapy should not be routinely withdrawn prior to major surgery; however, the impaired ability of the heart to respond to reflex adrenergic stimuli may augment the risks of general anesthesia and surgical procedures.
Diabetes and Hypoglycemia Beta-blockers may mask some of the manifestations of hypoglycemia, particularly tachycardia. Nonselective beta-blockers may potentiate insulin-induced hypoglycemia and delay recovery of serum glucose levels. Because of its beta1-selectivity, this is less likely with bisoprolol fumarate tablets.
However, patients subject to spontaneous hypoglycemia, or diabetic patients receiving insulin or oral hypoglycemic agents, should be cautioned about these possibilities and bisoprolol fumarate should be used with caution. Thyrotoxicosis Beta-adrenergic blockade may mask clinical signs of hyperthyroidism, such as tachycardia. Abrupt withdrawal of beta-blockade may be followed by an exacerbation of the symptoms of hyperthyroidism or may precipitate thyroid storm.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Safety data are available in more than 30,000 patients or volunteers. Frequency estimates and rates of withdrawal of therapy for adverse events were derived from two U.S. placebo-controlled studies. In Study A, doses of 5 mg, 10 mg and 20 mg bisoprolol fumarate were administered for 4 weeks.
In Study B, doses of 2.5 mg, 10 mg and 40 mg of bisoprolol fumarate were administered for 12 weeks. A total of 273 patients were treated with 5 mg to 20 mg of bisoprolol fumarate; 132 received placebo. Withdrawal of therapy for adverse events was 3.3% for patients receiving bisoprolol fumarate and 6.8% for patients on placebo.
Withdrawals were less than 1% for either bradycardia or fatigue/lack of energy. The following table presents adverse experiences, whether or not considered drug related, reported in at least 1% of patients in these studies, for all patients studied in placebo-controlled clinical trials (2.5 mg to 40 mg), as well as for a subgroup that was treated with doses within the recommended dosage range (5 mg to 20 mg). Of the adverse events listed in the table, bradycardia, diarrhea, asthenia, fatigue and sinusitis appear to be dose related.
Body System/Adverse Experience All Adverse Experiences (% a ) Bisoprolol Fumarate Placebo (n = 132) % 5 mg to 20 mg (n = 273) % 2.5 mg to 40 mg (n = 404) % Skin increased sweating 1.5 0.7
1.0Musculoskeletal arthralgia 2.3 2.2
2.7Central Nervous System dizziness 3.8 2.9 3.5 headache 11.4 8.8 10.9 hypoaesthesia 0.8 1.1
1.5Autonomic Nervous System dry mouth 1.5 0.7
1.3Heart Rate/Rhythm bradycardia 0 0.4
0.5Psychiatric vivid dreams 0 0 0 insomnia 2.3 1.5 2.5 depression 0.8 0
0.2Gastrointestinal diarrhea 1.5 2.6 3.5 nausea 1.5 1.5 2.2 vomiting 0 1.1
1.5Respiratory bronchospasm 0 0 0 cough 4.5 2.6 2.5 dyspnea 0.8 1.1 1.5 pharyngitis 2.3 2.2 2.2 rhinitis 3.0 2.9 4.0 sinusitis 1.5 2.2
2.2URI 3.8 4.8
5.0Body as a Whole asthenia 0 0.4 1.5 chest pain 0.8 1.1 1.5 fatigue 1.5 6.6 8.2 edema (peripheral) 3.8 3.7 3.0 a percentage of patients with event. The following is a comprehensive list of adverse experiences reported with bisoprolol fumarate in worldwide studies, or in post-marketing experience (in italics): Central Nervous System: Dizziness, unsteadiness , vertigo , syncope, headache, paresthesia, hypoaesthesia, hyperesthesia, somnolence, sleep disturbances , anxiety/restlessness, decreased concentration/memory.
Autonomic Nervous System: Dry mouth. Cardiovascular: Bradycardia, palpitations and other rhythm disturbances, cold extremities, claudication, hypotension, orthostatic hypotension, chest pain, congestive heart failure, dyspnea on exertion. Psychiatric: Vivid dreams, insomnia, depression.
Gastrointestinal: Gastric/epigastric/abdominal pain, gastritis, dyspepsia, nausea, vomiting, diarrhea, constipation, peptic ulcer. Musculoskeletal: Muscle/joint pain, arthralgia , back/neck pain, muscle cramps, twitching/tremor. Skin: Rash, acne, eczema, psoriasis , skin irritation, pruritus, flushing, sweating, alopecia, dermatitis , angioedema , exfoliative dermatitis , cutaneous vasculitis.
Special Senses: Visual disturbances, ocular pain/pressure, abnormal lacrimation, tinnitus, decreased hearing , earache, taste abnormalities. Metabolic: Gout. Respiratory: Asthma/bronchospasm, bronchitis, coughing, dyspnea, pharyngitis, rhinitis, sinusitis, URI.
Genitourinary: Decreased libido/impotence, Peyronie's disease , cystitis, renal colic, polyuria. Hematologic: Purpura. General: Fatigue, asthenia, chest pain, malaise, edema, weight gain, angioedema.
In addition, a variety of adverse effects have been reported with other beta-adrenergic blocking agents and should be considered potential adverse effects of bisoprolol fumarate tablets: Central Nervous System: Reversible mental depression progressing to catatonia, hallucinations, an acute reversible syndrome characterized by disorientation to time and place, emotional lability, slightly clouded sensorium. Allergic: Fever, combined with ach…
🔄 Drug Interactions ▾
Drug Interactions Bisoprolol fumarate should not be combined with other beta-blocking agents. Patients receiving catecholamine-depleting drugs, such as reserpine or guanethidine, should be closely monitored, because the added beta-adrenergic blocking action of bisoprolol fumarate tablets may produce excessive reduction of sympathetic activity. In patients receiving concurrent therapy with clonidine, if therapy is to be discontinued, it is suggested that bisoprolol fumarate tablets be discontinued for several days before the withdrawal of clonidine.
Bisoprolol fumarate should be used with care when myocardial depressants or inhibitors of AV conduction, such as certain calcium antagonists [particularly of the phenylalkylamine (verapamil) and benzothiazepine (diltiazem) classes], or antiarrhythmic agents, such as disopyramide, are used concurrently. Both digitalis glycosides and beta-blockers slow atrioventricular conduction and decrease heart rate. Concomitant use can increase the risk of bradycardia.
Concurrent use of rifampin increases the metabolic clearance of bisoprolol fumarate, resulting in a shortened elimination half-life of bisoprolol fumarate. However, initial dose modification is generally not necessary. Pharmacokinetic studies document no clinically relevant interactions with other agents given concomitantly, including thiazide diuretics and cimetidine.
There was no effect of bisoprolol fumarate on prothrombin time in patients on stable doses of warfarin. Risk of Anaphylactic Reaction While taking beta-blockers, patients with a history of severe anaphylactic reaction to a variety of allergens may be more reactive to repeated challenge, either accidental, diagnostic or therapeutic. Such patients may be unresponsive to the usual doses of epinephrine used to treat allergic reactions.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Bisoprolol fumarate has been used in elderly patients with hypertension. Response rates and mean decreases in systolic and diastolic blood pressure were similar to the decreases in younger patients in the U.S. clinical studies. Although no dose-response study was conducted in elderly patients, there was a tendency for older patients to be maintained on higher doses of bisoprolol fumarate.
Observed reductions in heart rate were slightly greater in the elderly than in the young and tended to increase with increasing dose. In general, no disparity in adverse experience reports or dropouts for safety reasons was observed between older and younger patients. Dose adjustment based on age is not necessary.
🆘 Overdosage ▾
OVERDOSAGE The most common signs expected with overdosage of a beta-blocker are bradycardia, hypotension, congestive heart failure, bronchospasm and hypoglycemia. To date, a few cases of overdose (maximum: 2000 mg) with bisoprolol fumarate have been reported. Bradycardia and/or hypotension were noted.
Sympathomimetic agents were given in some cases, and all patients recovered. In general, if overdose occurs, bisoprolol fumarate therapy should be stopped and supportive and symptomatic treatment should be provided. Limited data suggest that bisoprolol fumarate is not dialyzable.
Based on the expected pharmacologic actions and recommendations for other beta-blockers, the following general measures should be considered when clinically warranted: Bradycardia Administer IV atropine. If the response is inadequate, isoproterenol or another agent with positive chronotropic properties may be given cautiously. Under some circumstances, transvenous pacemaker insertion may be necessary.
Hypotension IV fluids and vasopressors should be administered. Intravenous glucagon may be useful. Heart Block (Second or Third Degree) Patients should be carefully monitored and treated with isoproterenol infusion or transvenous cardiac pacemaker insertion, as appropriate.
Congestive Heart Failure Initiate conventional therapy (i.e., digitalis, diuretics, inotropic agents, vasodilating agents). Bronchospasm Administer bronchodilator therapy such as isoproterenol and/or aminophylline. Hypoglycemia Administer IV glucose.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Bisoprolol fumarate is a beta 1 -selective (cardioselective) adrenoceptor blocking agent without significant membrane stabilizing activity or intrinsic sympathomimetic activity in its therapeutic dosage range. Cardioselectivity is not absolute, however, and at higher doses (≥ 20 mg) bisoprolol fumarate also inhibits beta 2 -adrenoceptors, chiefly located in the bronchial and vascular musculature; to retain selectivity it is therefore important to use the lowest effective dose. Pharmacokinetics and Metabolism The absolute bioavailability after a 10 mg oral dose of bisoprolol fumarate is about 80%.
Absorption is not affected by the presence of food. The first pass metabolism of bisoprolol fumarate is about 20%. Binding to serum proteins is approximately 30%.
Peak plasma concentrations occur within 2 to 4 hours of dosing with 5 mg to 20 mg, and mean peak values range from 16 ng/mL at 5 mg to 70 ng/mL at 20 mg. Once daily dosing with bisoprolol fumarate results in less than 2-fold intersubject variation in peak plasma levels. The plasma elimination half-life is 9 to 12 hours and is slightly longer in elderly patients, in part because of decreased renal function in that population.
Steady-state is attained within 5 days of once daily dosing. In both young and elderly populations, plasma accumulation is low; the accumulation factor ranges from 1.1 to 1.3, and is what would be expected from the first order kinetics and once daily dosing. Plasma concentrations are proportional to the administered dose in the range of 5 mg to 20 mg.
Pharmacokinetic characteristics of the two enantiomers are similar. Bisoprolol fumarate is eliminated equally by renal and non-renal pathways with about 50% of the dose appearing unchanged in the urine and the remainder appearing in the form of inactive metabolites. In humans, the known metabolites are labile or have no known pharmacologic activity.
Less than 2% of the dose is excreted in the feces. Bisoprolol fumarate is not metabolized by cytochrome P450 II D6 (debrisoquin hydroxylase). In subjects with creatinine clearance less than 40 mL/min, the plasma half-life is increased approximately 3-fold compared to healthy subjects.
In patients with cirrhosis of the liver, the elimination of bisoprolol fumarate is more variable in rate and significantly slower than that in healthy subjects, with plasma half-life ranging from 8.3 to 21.7 hours. Pharmacodynamics The most prominent effect of bisoprolol fumarate tablets is the negative chronotropic effect, resulting in a reduction in resting and exercise heart rate. There is a fall in resting and exercise cardiac output with little observed change in stroke volume, and only a small increase in right atrial pressure, or pulmonary capillary wedge pressure at rest or during exercise.
Findings in short-term clinical hemodynamics studies with bisoprolol fumarate tablets are similar to those observed with other beta-blocking agents. The mechanism of action of its antihypertensive effects has not been completely established. Factors which may be involved include: 1) Decreased cardiac output, 2) Inhibition of renin release by the kidneys, 3) Diminution of tonic sympathetic outflow from the vasomotor centers in the brain.
In normal volunteers, bisoprolol fumarate tablets therapy resulted in a reduction of exercise- and isoproterenol-induced tachycardia. The maximal effect occurred within 1 to 4 hours post-dosing. Effects persisted for 24 hours at doses equal to or greater than 5 mg.
Electrophysiology studies in man have demonstrated that bisoprolol fumarate tablets significantly decreases heart rate, increases sinus node recovery time, prolongs AV node refractory periods, and, with rapid atrial stimulation, prolongs AV nodal conduction. Beta 1 -selectivity of bisoprolol fumarate tablets has been demonstrated in both animal and human studies. No effects at therapeutic doses on beta 2 -adrenoceptor density have been observed.
Pulmonary function studies…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Bisoprolol Fumarate Tablets, 5 mg, red, film-coated, scored, debossed MP711. NDC: 71335-1678-1: 30 Tablets in a BOTTLE NDC: 71335-1678-2: 100 Tablets in a BOTTLE NDC: 71335-1678-3: 90 Tablets in a BOTTLE NDC: 71335-1678-4: 28 Tablets in a BOTTLE NDC: 71335-1678-5: 120 Tablets in a BOTTLE Store at 20° to 25°C (68° to 77°F). [See USP Controlled Room Temperature] Protect from moisture. DISPENSE IN TIGHT, LIGHT-RESISTANT CONTAINER as defined in the USP.
Repackaged/Relabeled by: Bryant Ranch Prepack, Inc. Burbank, CA 9150
📋 Description ▾
DESCRIPTION Bisoprolol fumarate, USP is a synthetic, beta1-selective (cardio-selective) adrenoceptor blocking agent. The chemical name for bisoprolol fumarate is (±)-1-[4-[[2-(1-Methylethoxy)ethoxy]methyl]phenoxy]-3-[(1-methylethyl)amino]-2-propanol( E )-2-butenedioate (2:1) (salt). It possesses an asymmetric carbon atom in its structure and is provided as a racemic mixture.
The S(-) enantiomer is responsible for most of the beta-blocking activity. Its molecular formula is (C 18 H 31 NO 4 ) 2 •C 4 H 4 O 4 and its structure is: Bisoprolol fumarate has a molecular weight of 766.97. It is a white crystalline powder which is approximately equally hydrophilic and lipophilic, and is readily soluble in water, methanol, ethanol and chloroform.
Bisoprolol fumarate is available as 5 mg or 10 mg for oral administration. Inactive ingredients include carnauba wax, colloidal silicon dioxide, corn starch, crospovidone, dibasic calcium phosphate, hydroxypropyl methylcellulose, magnesium stearate, microcrystalline cellulose, polydextrose, polyethylene glycol, titanium dioxide, triacetin. The 5 mg tablets also contain FD&C Yellow No.
6 Aluminum Lake, FD&C Red No. 40 Aluminum Lake, FD&C Blue No. 2 Aluminum Lake.
Meets USP Dissolution Test 2.
💬 Information for Patients ▾
Information for Patients Patients, especially those with coronary artery disease, should be warned about discontinuing use of bisoprolol fumarate without a physician’s supervision. Patients should also be advised to consult a physician if any difficulty in breathing occurs, or if they develop signs or symptoms of congestive heart failure or excessive bradycardia. Patients subject to spontaneous hypoglycemia, or diabetic patients receiving insulin or oral hypoglycemic agents, should be cautioned that beta-blockers may mask some of the manifestations of hypoglycemia, particularly tachycardia, and bisoprolol fumarate should be used with caution.
Patients should know how they react to this medicine before they operate automobiles and machinery or engage in other tasks requiring alertness.