
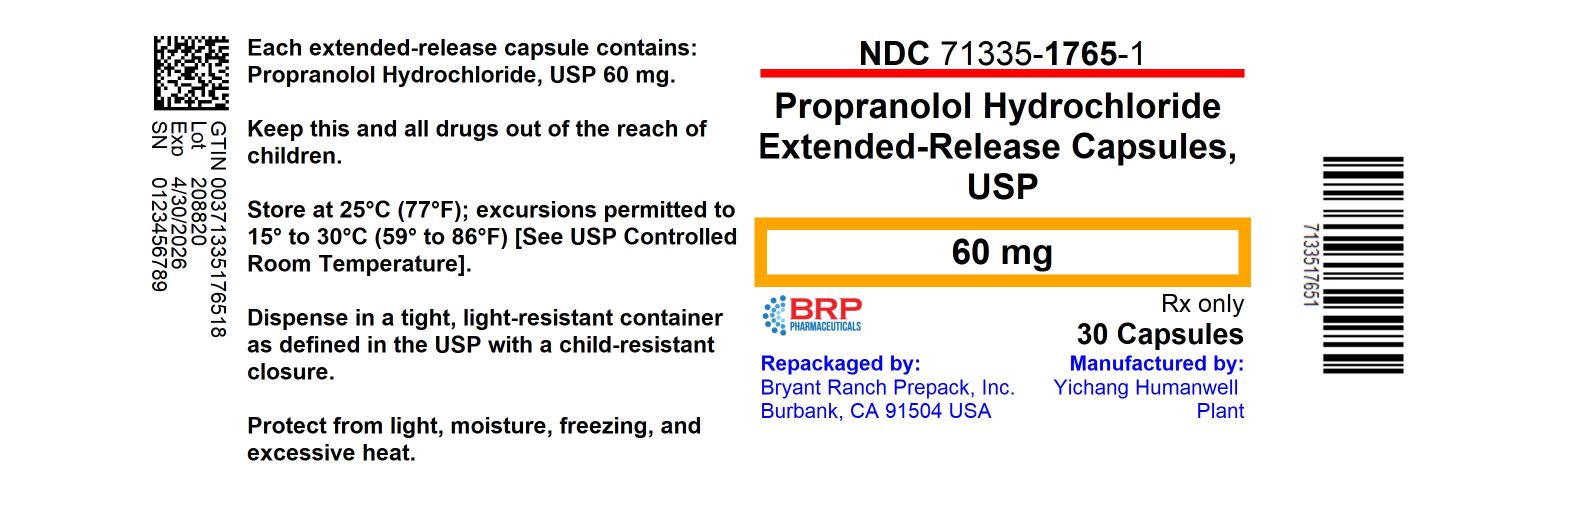
Propranolol Hydrochloride 60 mg Capsule, Extended Release, 90-count
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the beta-Adrenergic Blocker class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Propranolol is used to treat high blood pressure irregular heartbeats pheochromocytoma (tumor on a small gland near the kidneys) certain types of tremor hypertrophic subaortic stenosis (a heart muscle disease angina (chest pain) migraine headaches Propranolol is also used to improve survival after a heart attack. Propranolol is in a class of medications called beta blockers. It works by relaxing blood vessels and slowing heart rate to improve blood flow and decrease blood pressure.
Read the full MedlinePlus article ↗- Please don't stop propranolol on your own — even if you feel great. Stopping suddenly, especially if you have angina or any underlying heart disease, can cause a dangerous rebound...
- Can I stop taking propranolol if I feel fine and my blood pressure is under control?
- Bronchial asthma is actually a contraindication for propranolol, meaning it should not be used if you have asthma. Propranolol blocks receptors in your airways that help keep them...
- I have asthma — is it safe for me to take propranolol?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Propranolol Hydrochloride — tap one for details:
Propranolol Hydrochloride may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 47MLB0F1MV
Ethylcellulose is a plant-based thickening agent made from cellulose. It slows how fast the medicine dissolves, helping control drug release in the stomach and intestines.
-
UNII H3R47K3TBD
FD&C Blue No. 1 is a synthetic blue dye approved for use in foods and medicines. It serves as a colorant to give the medication its distinctive appearance and help with product identification.
-
UNII PN2ZH5LOQY
A synthetic red dye approved by the FDA for use in foods, medicines, and cosmetics. It serves as a colorant to make tablets, capsules, and liquids visually distinctive for product identification.
-
UNII XM0M87F357
A dark iron oxide compound that gives medicines their black or dark color. It's used as a colorant in tablets and capsules to help identify the product and make it visually distinctive.
-
UNII 2G86QN327L
Gelatin is a protein derived from animal collagen, commonly used in medicines as a gelling agent and capsule material. It helps create soft or hard capsule shells that hold and release medication, and can also thicken liquid formulations.
-
UNII 5Y0974F5PW
Hydroxypropyl cellulose is a plant-derived thickener and binder made by chemically treating cellulose. In medicines, it helps hold tablets together, thickens liquids, and can form a protective coating on capsules.
-
UNII R75537T0T4
Hypromellose 2910 is a plant-derived thickening agent made from cellulose. It serves as a binder that holds tablet ingredients together, a film-coating for pills, and a viscosity controller in liquids.
-
UNII WZH3C48M4T
Potassium hydroxide is a strong alkaline chemical used in medicines to adjust and maintain the pH level of liquid formulations, helping keep the product stable and the active ingredients effective.
-
UNII 46N107B71O
Shellac is a natural resin secreted by the lac beetle. It's used as a coating on tablets and capsules to control how quickly the medicine dissolves and to improve appearance and stability.
-
UNII O8232NY3SJ
A plant-based carbohydrate derived from corn kernels. It acts as a filler to add bulk, a binder to hold ingredients together, and a disintegrant to help the tablet break apart in your stomach for absorption.
-
UNII C151H8M554
A natural sugar derived from sugar cane or sugar beets. It's used as a sweetener, filler, and binder to improve taste, add bulk, and help hold tablet or capsule ingredients together.
-
UNII 7SEV7J4R1U
A powder made from a naturally occurring mineral. In medicines, talc works as a glidant and anti-caking agent, helping tablets and capsules flow smoothly during manufacturing and preventing clumping.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
13 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.3923 | $35.31 / 90 capsules |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Propranolol Hydrochloride 60 mg 00228-2778-11 | Actavis | 100 capsules | $0.170 | AB | Availability likely | — |
| Propranolol Hydrochloride 60 mg 00527-4116-37 | Lannett | 100 capsules | $0.170 | AB | Availability likely | — |
| propranolol hydrochloride 60 mg 51991-0817-01 | Breckenridge | 100 capsules | $0.170 | AB | Availability likely | — |
| Propranolol Hydrochloride 60 mg 60687-0215-01 | American | 1 capsule | $0.170 | AB | Availability likely | — |
| Propranolol Hydrochloride ER 60 mg 62559-0530-01 | ANI | 100 capsules | $0.190 | AB | FDA listed | — |
| propranolol hydrochloride 60 mg 42291-0522-01 | AvKARE | 100 capsules | — | AB | FDA listed | — |
| propranolol hydrochloride 60 mg 60760-0867-30 | St. | 30 capsules | — | AB | FDA listed | — |
| Inderal La 60 mg 62559-0520-01 | ANI | 100 capsules | — | AB | FDA listed | — |
| propranolol hydrochloride 60 mg 63629-2071-01 | Bryant | 100 capsules | — | AB | FDA listed | — |
| Propranolol Hydrochloride 60 mg 71205-0760-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| propranolol hydrochloride 60 mg 71335-0234-01 | Bryant | 30 capsules | — | AB | FDA listed | — |
| Propranolol Hydrochloride 60 mgthis 71335-1765-03 | Bryant | 90 capsules | — | AB | FDA listed | — |
| propranolol hydrochloride 60 mg 72162-1602-01 | Bryant | 100 capsules | — | AB | FDA listed | — |
| propranolol hydrochloride 60 mg 82804-0072-30 | Proficient | 30 capsules | — | AB | FDA listed | — |
| Propranolol Hydrochloride 60 mg 82619-0132-01 | Creekwood | 100 capsules | — | — | FDA listed | — |
| propranolol hydrochloride 60 mg 84677-0035-01 | Golden | 100 capsules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 71335-1765-01 | 30 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-1765-1) | 2021-02-01 | Active |
| 71335-1765-02 | 18 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-1765-2) | 2021-02-01 | Active |
| 71335-1765-03 You're viewing this | 90 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-1765-3) | 2021-02-01 | Active |
| 71335-1765-04 | 28 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-1765-4) | 2021-02-01 | Active |
| 71335-1765-05 | 60 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-1765-5) | 2021-02-01 | Active |
| 71335-1765-06 | 10 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-1765-6) | 2021-02-01 | Active |
| 71335-1765-07 | 100 CAPSULE, EXTENDED RELEASE in 1 BOTTLE (71335-1765-7) | 2021-02-01 | Active |
You're viewing one of 7 pack sizes for this product.
Pack size FAQ
What quantity is in NDC 71335-1765-03?
What is the difference between NDC 71335-1765-03 and NDC 71335-1765-06?
What NDC number is used to bill for this package of Propranolol Hydrochloride 60 mg Capsule, Extended Release?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Hypertension Propranolol Hydrochloride Extended-Release Capsules are indicated in the management of hypertension. It may be used alone or used in combination with other antihypertensive agents, particularly a thiazide diuretic. Propranolol Hydrochloride Extended-Release Capsules are not indicated in the management of hypertensive emergencies.
Angina Pectoris Due to Coronary Atherosclerosis Propranolol Hydrochloride Extended-Release Capsules are indicated to decrease angina frequency and increase exercise tolerance in patients with angina pectoris. Migraine Propranolol Hydrochloride Extended-Release Capsules are indicated for the prophylaxis of common migraine headache. The efficacy of propranolol in the treatment of a migraine attack that has started has not been established, and propranolol is not indicated for such use.
Hypertrophic Subaortic Stenosis Propranolol Hydrochloride Extended-Release Capsules improve NYHA functional class in symptomatic patients with hypertrophic subaortic stenosis.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION General Propranolol hydrochloride extended-release capsules provide propranolol hydrochloride in a sustained-release capsule for administration once daily. If patients are switched from propranolol hydrochloride tablets to propranolol hydrochloride extended-release capsules, care should be taken to assure that the desired therapeutic effect is maintained. Propranolol hydrochloride extended-release capsules should not be considered a simple mg-for-mg substitute for propranolol hydrochloride tablets.
Propranolol hydrochloride extended-release capsules have different kinetics and produce lower blood levels. Retitration may be necessary, especially to maintain effectiveness at the end of the 24-hour dosing interval. Hypertension The usual initial dosage is 80 mg propranolol hydrochloride extended-release capsules once daily, whether used alone or added to a diuretic.
The dosage may be increased to 120 mg once daily or higher until adequate blood pressure control is achieved. The usual maintenance dosage is 120 to 160 mg once daily. In some instances a dosage of 640 mg may be required.
The time needed for full hypertensive response to a given dosage is variable and may range from a few days to several weeks. Angina Pectoris Starting with 80 mg propranolol hydrochloride extended-release capsules once daily, dosage should be gradually increased at three- to seven-day intervals until optimal response is obtained. Although individual patients may respond at any dosage level, the average optimal dosage appears to be 160 mg once daily.
In angina pectoris, the value and safety of dosage exceeding 320 mg per day have not been established. If treatment is to be discontinued, reduce dosage gradually over a period of a few weeks (see “ WARNINGS ”). Migraine The initial oral dose is 80 mg propranolol hydrochloride extended-release capsules once daily.
The usual effective dose range is 160 to 240 mg once daily. The dosage may be increased gradually to achieve optimal migraine prophylaxis. If a satisfactory response is not obtained within four to six weeks after reaching the maximal dose, propranolol hydrochloride extended-release capsules therapy should be discontinued.
It may be advisable to withdraw the drug gradually over a period of several weeks depending on the patient's age, comorbidity, and dose of propranolol hydrochloride extended-release capsules. Hypertrophic Subaortic Stenosis The usual dosage is 80 to 160 mg propranolol hydrochloride extended-release capsules once daily.
⛔ Contraindications ▾
CONTRAINDICATIONS Propranolol is contraindicated in 1) cardiogenic shock; 2) sinus bradycardia and greater than first-degree block; 3) bronchial asthma; and 4) in patients with known hypersensitivity to propranolol hydrochloride.
⚠️ Warnings ▾
WARNINGS Angina Pectoris There have been reports of exacerbation of angina and, in some cases, myocardial infarction, following abrupt discontinuance of propranolol therapy. Therefore, when discontinuance of propranolol is planned, the dosage should be gradually reduced over at least a few weeks, and the patient should be cautioned against interruption or cessation of therapy without the physician's advice. If propranolol therapy is interrupted and exacerbation of angina occurs, it usually is advisable to reinstitute propranolol therapy and take other measures appropriate for the management of unstable angina pectoris.
Since coronary artery disease may be unrecognized, it may be prudent to follow the above advice in patients considered at risk of having occult atherosclerotic heart disease who are given propranolol for other indications. Hypersensitivity and Skin Reactions Hypersensitivity reactions, including anaphylactic/anaphylactoid reactions, have been associated with the administration of propranolol (see ADVERSE REACTIONS ). Cutaneous reactions, including Stevens-Johnson Syndrome, toxic epidermal necrolysis, exfoliative dermatitis, erythema multiforme, and urticaria, have been reported with use of propranolol (see ADVERSE REACTIONS ).
Cardiac Failure Sympathetic stimulation may be a vital component supporting circulatory function in patients with congestive heart failure, and its inhibition by beta blockade may precipitate more severe failure. Although beta blockers should be avoided in overt congestive heart failure, some have been shown to be highly beneficial when used with close follow-up in patients with a history of failure who are well compensated and are receiving diuretics as needed. Beta-adrenergic blocking agents do not abolish the inotropic action of digitalis on heart muscle.
In Patients without a History of Heart Failure, continued use of beta blockers can, in some cases, lead to cardiac failure. Nonallergic Bronchospasm (e.g., Chronic Bronchitis, Emphysema) In general, patients with bronchospastic lung disease should not receive beta-blockers. Propranolol should be administered with caution in this setting since it may provoke a bronchial asthmatic attack by blocking bronchodilation produced by endogenous and exogenous catecholamine stimulation of beta-receptors.
Major Surgery Chronically administered beta-blocking therapy should not be routinely withdrawn prior to major surgery, however the impaired ability of the heart to respond to reflex adrenergic stimuli may augment the risks of general anesthesia and surgical procedures. Hypoglycemia Beta-blockers may prevent early warning signs of hypoglycemia, such as tachycardia, and increase the risk for severe or prolonged hypoglycemia at any time during treatment, especially in patients with diabetes mellitus or children and patients who are fasting (i.e., surgery, not eating regularly, or are vomiting).
If severe hypoglycemia occurs, patients should be instructed to seek emergency treatment. Hypoglycemia has been reported in patients taking propranolol after prolonged physical exertion and in patients with renal insufficiency. Thyrotoxicosis Beta-adrenergic blockade may mask certain clinical signs of hyperthyroidism.
Therefore, abrupt withdrawal of propranolol may be followed by an exacerbation of symptoms of hyperthyroidism, including thyroid storm. Propranolol may change thyroid-function tests, increasing T 4 and reverse T 3 , and decreasing T 3 . Wolff-Parkinson-White Syndrome Beta-adrenergic blockade in patients with Wolff-Parkinson-White syndrome and tachycardia has been associated with severe bradycardia requiring treatment with a pacemaker.
In one case, this result was reported after an initial dose of 5 mg propranolol.
🤒 Adverse Reactions ▾
ADVERSE REACTIONS The following adverse events were observed and have been reported in patients using propranolol. Cardiovascular: Bradycardia; congestive heart failure; intensification of AV block; hypotension; paresthesia of hands; thrombocytopenic purpura; arterial insufficiency, usually of the Raynaud type. Central Nervous System: Light-headedness; mental depression manifested by insomnia, lassitude, weakness, fatigue; catatonia; visual disturbances; hallucinations; vivid dreams; an acute reversible syndrome characterized by disorientation for time and place, short-term memory loss, emotional lability, slightly clouded sensorium, and decreased performance on neuropsychometrics.
For immediate release formulations, fatigue, lethargy, and vivid dreams appear dose related. Gastrointestinal: Nausea, vomiting, epigastric distress, abdominal cramping, diarrhea, constipation, mesenteric arterial thrombosis, ischemic colitis. Allergic: Hypersensitivity reactions, including anaphylactic/anaphylactoid reactions; pharyngitis and agranulocytosis; erythematous rash; fever combined with aching and sore throat; laryngospasm; respiratory distress.
Respiratory: Bronchospasm. Hematologic: Agranulocytosis, nonthrombocytopenic purpura, and thrombocytopenic purpura. Autoimmune: Systemic lupus erythematosus (SLE).
Skin and mucous membranes: Stevens-Johnson Syndrome, toxic epidermal necrolysis, dry eyes, exfoliative dermatitis, erythema multiforme, urticaria, alopecia, SLE-like reactions, and psoriasisiform rashes. Oculomucocutaneous syndrome involving the skin, serous membranes, and conjunctivae reported for a beta-blocker (practolol) have not been associated with propranolol. Genitourinary: Male impotence; Peyronie's disease.
🔄 Drug Interactions ▾
Drug Interactions All drug interaction studies were conducted with propranolol. There are no data on drug interactions with propranolol hydrochloride extended-release capsules. Interactions with Substrates, Inhibitors or Inducers of Cytochrome P-450 Enzymes Because propranolol’s metabolism involves multiple pathways in the Cytochrome P-450 system (CYP2D6, 1A2, 2C19), co-administration with drugs that are metabolized by, or affect the activity (induction or inhibition) of one or more of these pathways may lead to clinically relevant drug interactions (see Drug Interactions under PRECAUTIONS ).
Substrates or Inhibitors of CYP2D6 Blood levels and/or toxicity of propranolol may be increased by co-administration with substrates or inhibitors of CYP2D6, such as amiodarone, cimetidine, delavudin, fluoxetine, paroxetine, quinidine, and ritonavir. No interactions were observed with either ranitidine or lansoprazole. Substrates or Inhibitors of CYP1A2 Blood levels and/or toxicity of propranolol may be increased by co-administration with substrates or inhibitors of CYP1A2, such as imipramine, cimetidine, ciprofloxacin, fluvoxamine, isoniazid, ritonavir, theophylline, zileuton, zolmitriptan, and rizatriptan.
Substrates or Inhibitors of CYP2C19 Blood levels and/or toxicity of propranolol may be increased by co-administration with substrates or inhibitors of CYP2C19, such as fluconazole, cimetidine, fluoxetine, fluvoxamine, tenioposide, and tolbutamide. No interaction was observed with omeprazole. Inducers of Hepatic Drug Metabolism Blood levels of propranolol may be decreased by co-administration with inducers such as rifampin, ethanol, phenytoin, and phenobarbital.
Cigarette smoking also induces hepatic metabolism and has been shown to increase up to 77% the clearance of propranolol, resulting in decreased plasma concentrations. Cardiovascular Drugs Antiarrhythmics The AUC of propafenone is increased by more than 200% by co-administration of propranolol. The metabolism of propranolol is reduced by co-administration of quinidine, leading to a two to three fold increased blood concentration and greater degrees of clinical beta-blockade.
The metabolism of lidocaine is inhibited by co-administration of propranolol, resulting in a 25% increase in lidocaine concentrations. Calcium Channel Blockers The mean C max and AUC of propranolol are increased respectively, by 50% and 30% by co-administration of nisoldipine and by 80% and 47%, by co-administration of nicardipine. The mean C max and AUC of nifedipine are increased by 64% and 79%, respectively, by co-administration of propranolol.
Propranolol does not affect the pharmacokinetics of verapamil and norverapamil. Verapamil does not affect the pharmacokinetics of propranolol. Non-Cardiovascular Drugs Migraine Drugs Administration of zolmitriptan or rizatriptan with propranolol resulted in increased concentrations of zolmitriptan (AUC increased by 56% and C max by 37%) or rizatriptan (the AUC and C max were increased by 67% and 75%, respectively).
Theophylline Co-administration of theophylline with propranolol decreases theophylline oral clearance by 30% to 52%. Benzodiazepines Propranolol can inhibit the metabolism of diazepam, resulting in increased concentrations of diazepam and its metabolites. Diazepam does not alter the pharmacokinetics of propranolol.
The pharmacokinetics of oxazepam, triazolam, lorazepam, and alprazolam are not affected by co-administration of propranolol. Neuroleptic Drugs Co-administration of long-acting propranolol at doses greater than or equal to 160 mg/day resulted in increased thioridazine plasma concentrations ranging from 55% to 369% and increased thioridazine metabolite (mesoridazine) concentrations ranging from 33% to 209%. Co-administration of chlorpromazine with propranolol resulted in a 70% increase in propranolol plasma level.
Anti-Ulcer Drugs Co-administration of propranolol with cimetidine, a non-specific CYP450 inhibitor, increased propranolol AUC and C m…
🤰 Pregnancy ▾
Pregnancy In a series of reproductive and developmental toxicology studies, propranolol was given to rats by gavage or in the diet throughout pregnancy and lactation. At doses of 150 mg/kg/day, but not at doses of 80 mg/kg/day (equivalent to the MRHD on a body surface area basis), treatment was associated with embryotoxicity (reduced litter size and increased resorption rates) as well as neonatal toxicity (deaths). Propranolol hydrochloride also was administered (in the feed) to rabbits (throughout pregnancy and lactation) at doses as high as 150 mg/kg/day (about 5 times the maximum recommended human oral daily dose).
No evidence of embryo or neonatal toxicity was noted. There are no adequate and well-controlled studies in pregnant women. Intrauterine growth retardation, small placentas, and congenital abnormalities have been reported in neonates whose mothers received propranolol during pregnancy.
Neonates whose mothers are receiving propranolol at parturition have exhibited bradycardia, hypoglycemia and/or respiratory depression. Adequate facilities for monitoring such infants at birth should be available. Propranolol hydrochloride extended-release capsules should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🧒 Pediatric Use ▾
Pediatric Use Safety and effectiveness of propranolol in pediatric patients have not been established. Bronchospasm and congestive heart failure have been reported coincident with the administration of propranolol therapy in pediatric patients.
🧓 Geriatric Use ▾
Geriatric Use Clinical studies of propranolol hydrochloride extended-release capsules did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. In general, dose selection for an elderly patient should be cautious, usually starting at the low end of the dosing range, reflecting the greater frequency of the decreased hepatic, renal or cardiac function, and of concomitant disease or other drug therapy.
🆘 Overdosage ▾
OVERDOSAGE Propranolol is not significantly dialyzable. In the event of overdosage or exaggerated response, the following measures should be employed: General: If ingestion is or may have been recent, evacuate gastric contents, taking care to prevent pulmonary aspiration. Supportive Therapy: Hypotension and bradycardia have been reported following propranolol overdose and should be treated appropriately.
Glucagon can exert potent inotropic and chronotropic effects and may be particularly useful for the treatment of hypotension or depressed myocardial function after a propranolol overdose. Glucagon should be administered as 50 to 150 mcg/kg intravenously followed by continuous drip of 1 to 5 mg/hour for positive chronotropic effect. Isoproterenol, dopamine or phosphodiesterase inhibitors may also be useful.
Epinephrine, however, may provoke uncontrolled hypertension. Bradycardia can be treated with atropine or isoproterenol. Serious bradycardia may require temporary cardiac pacing.
The electrocardiogram, pulse, blood pressure, neurobehavioral status and intake and output balance must be monitored. Isoproterenol and aminophylline may be used for bronchospasm.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY General Propranolol is a nonselective, beta-adrenergic receptor-blocking agent possessing no other autonomic nervous system activity. It specifically competes with beta-adrenergic receptor-stimulating agents for available receptor sites. When access to beta-receptor sites is blocked by propranolol, the chronotropic, inotropic, and vasodilator responses to beta-adrenergic stimulation are decreased proportionately.
At dosages greater than required for beta blockade, propranolol also exerts a quinidine-like or anesthetic-like membrane action, which affects the cardiac action potential. The significance of the membrane action in the treatment of arrhythmias is uncertain. Propranolol hydrochloride extended-release capsules should not be considered a simple mg-for-mg substitute for conventional propranolol and the blood levels achieved do not match (are lower than) those of two to four times daily dosing with the same dose (see DOSAGE AND ADMINISTRATION ).
When changing to propranolol hydrochloride extended-release capsules from conventional propranolol, a possible need for retitration upwards should be considered, especially to maintain effectiveness at the end of the dosing interval. In most clinical settings, however, such as hypertension or angina where there is little correlation between plasma levels and clinical effect, propranolol hydrochloride extended-release capsules have been therapeutically equivalent to the same mg dose of conventional propranolol hydrochloride as assessed by 24-hour effects on blood pressure and on 24-hour exercise responses of heart rate, systolic pressure, and rate pressure product.
Mechanism of Action The mechanism of the antihypertensive effect of propranolol has not been established. Among the factors that may be involved in contributing to the antihypertensive action include: (1) decreased cardiac output, (2) inhibition of renin release by the kidneys, and (3) diminution of tonic sympathetic nerve outflow from vasomotor centers in the brain. Although total peripheral resistance may increase initially, it readjusts to or below the pretreatment level with chronic use of propranolol.
Effects of propranolol on plasma volume appear to be minor and somewhat variable. In angina pectoris, propranolol generally reduces the oxygen requirement of the heart at any given level of effort by blocking the catecholamine-induced increases in the heart rate, systolic blood pressure, and the velocity and extent of myocardial contraction. Propranolol may increase oxygen requirements by increasing left ventricular fiber length, end diastolic pressure, and systolic ejection period.
The net physiologic effect of beta-adrenergic blockade is usually advantageous and is manifested during exercise by delayed onset of pain and increased work capacity. Propranolol exerts its antiarrhythmic effects in concentrations associated with beta-adrenergic blockade, and this appears to be its principal antiarrhythmic mechanism of action. In dosages greater than required for beta blockade, propranolol also exerts a quinidine-like or anesthetic-like membrane action which affects the cardiac action potential.
The significance of the membrane action in the treatment of arrhythmias is uncertain. The mechanism of the anti-migraine effect of propranolol has not been established. Beta-adrenergic receptors have been demonstrated in the pial vessels of the brain.
General Propranolol is a nonselective, beta-adrenergic receptor-blocking agent possessing no other autonomic nervous system activity. It specifically competes with beta-adrenergic receptor-stimulating agents for available receptor sites. When access to beta-receptor sites is blocked by propranolol, the chronotropic, inotropic, and vasodilator responses to beta-adrenergic stimulation are decreased proportionately.
At dosages greater than required for beta blockade, propranolol also exerts a quinidine-like or anesthetic-like membrane action, which affects the cardi…
🧬 Mechanism of Action ▾
Mechanism of Action The mechanism of the antihypertensive effect of propranolol has not been established. Among the factors that may be involved in contributing to the antihypertensive action include: (1) decreased cardiac output, (2) inhibition of renin release by the kidneys, and (3) diminution of tonic sympathetic nerve outflow from vasomotor centers in the brain. Although total peripheral resistance may increase initially, it readjusts to or below the pretreatment level with chronic use of propranolol.
Effects of propranolol on plasma volume appear to be minor and somewhat variable. In angina pectoris, propranolol generally reduces the oxygen requirement of the heart at any given level of effort by blocking the catecholamine-induced increases in the heart rate, systolic blood pressure, and the velocity and extent of myocardial contraction. Propranolol may increase oxygen requirements by increasing left ventricular fiber length, end diastolic pressure, and systolic ejection period.
The net physiologic effect of beta-adrenergic blockade is usually advantageous and is manifested during exercise by delayed onset of pain and increased work capacity. Propranolol exerts its antiarrhythmic effects in concentrations associated with beta-adrenergic blockade, and this appears to be its principal antiarrhythmic mechanism of action. In dosages greater than required for beta blockade, propranolol also exerts a quinidine-like or anesthetic-like membrane action which affects the cardiac action potential.
The significance of the membrane action in the treatment of arrhythmias is uncertain. The mechanism of the anti-migraine effect of propranolol has not been established. Beta-adrenergic receptors have been demonstrated in the pial vessels of the brain.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Propranolol Hydrochloride Extended-Release Capsules, USP 60 mg, Capsule # 3, Opaque white cap printed with ink in black ink; Opaque light blue body printed with 107 in black ink. NDC: 71335-1765-1: 30 Capsules in a BOTTLE NDC: 71335-1765-2: 18 Capsules in a BOTTLE NDC: 71335-1765-3: 90 Capsules in a BOTTLE NDC: 71335-1765-4: 28 Capsules in a BOTTLE NDC: 71335-1765-5: 60 Capsules in a BOTTLE NDC: 71335-1765-6: 10 Capsules in a BOTTLE NDC: 71335-1765-7: 100 Capsules in a BOTTLE Store at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F). [See USP Controlled Room Temperature] Protect from light, moisture, freezing, and excessive heat.
Dispense in a tight, light-resistant container as defined in the USP with a child-resistant closure. Keep this and all medication out of the reach of children. Repackaged/Relabeled by: Bryant Ranch Prepack, Inc.
Burbank, CA 91504
📋 Description ▾
DESCRIPTION Propranolol hydrochloride, USP is a synthetic beta-adrenergic receptor-blocking agent chemically described as 2-Propanol, 1-[(1-methylethyl)amino]-3-(1-naphthalenyloxy)-, hydrochloride, (±)-. Its molecular and structural formulae are: C 16 H 21 NO 2 ·HCl Propranolol hydrochloride, USP is a stable, white, crystalline solid which is readily soluble in water and ethanol. Its molecular weight is 295.80.
Propranolol Hydrochloride Extended-Release Capsules, USP are formulated to provide a sustained release of propranolol hydrochloride, USP. Propranolol Hydrochloride Extended-Release Capsules, USP are available as 60 mg, 80 mg, 120 mg, and 160 mg capsules for oral administration. Each 60 mg capsule contains 60 mg propranolol hydrochloride, USP (equivalent to 52.60 mg of propranolol).
Each 80 mg capsule contains 80 mg propranolol hydrochloride, USP (equivalent to 70.14 mg of propranolol). Each 120 mg capsule contains 120 mg propranolol hydrochloride, USP (equivalent to 105.21 mg of propranolol). Each 160 mg capsule contains 160 mg propranolol hydrochloride, USP (equivalent to 140.28 mg of propranolol).
The inactive ingredients contained in Propranolol Hydrochloride Extended-Release Capsules, USP are: empty hard gelatin capsules, ethylcellulose, hydroxypropyl cellulose, hypromellose, sugar spheres, and talc. The capsule shell contains FD&C blue 1, FD&C red 3 (60 mg, 80 mg and 120 mg), gelatin, and titanium dioxide. The imprinting ink contains black iron oxide, potassium hydroxide and shellac.
These capsules comply with USP Dissolution Test 6.