
Metformin hydrochloride 500 mg Tablet, Extended Release, 270-count — NDC 71610-554-92 (Billing 71610-0554-92)
This is a package of 270 tablets of Metformin hydrochloride 500 mg Tablet, Extended Release from Aphena Pharma Solutions - Tennessee, LLC, marketed since Jul 2018 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 71610-554-92 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 71610 labeler · 554 product · 92 package
- Package marketed since
- Jun 18, 2021
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 270 EA per package
- Barcode (UPC-A, from the NDC)
- 3 7161055492 5
- FDA record last changed
- Jul 24, 2026
Other active recalls for Metformin Hydrochloride (different manufacturers) — 1 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 046754
- GCN: 89863
- GPI-14 (Medi-Span): 27250050007520
- HICL (First Databank): 004763
- AHFS class code: 68:20.04.00
- RxCUI (RxNorm): 860975
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 8, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 8, 2026
RxNorm drug class
This medicine belongs to the Biguanide class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 8, 2026
Clinical
Metformin is used alone or with other medications, including insulin, to treat type 2 diabetes (condition in which the body does not use insulin normally and, therefore, cannot control the amount of sugar in the blood). Metformin is in a class of drugs called biguanides. Metformin helps to control the amount of glucose (sugar) in your blood. It decreases the amount of glucose you absorb from your food and the amount of glucose made by your liver. Metformin also increases your body's response to insulin, a natural substance that controls the amount of glucose in the blood. Metformin is not used...
Read the full MedlinePlus article ↗- Metformin works in three ways: it lowers the amount of sugar your liver dumps into your bloodstream, slows how much sugar your gut absorbs from food, and helps your body respond to...
- What exactly is metformin doing for my diabetes?
- Yes, this is very common — diarrhea, nausea, and stomach discomfort are the most frequently reported side effects, and they're often worst when you first start or when your dose go...
- My stomach has been a mess since I started metformin. Is that normal? Will it get better?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Metformin Hydrochloride — tap one for details:
Metformin Hydrochloride may be associated with lower levels of 4 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 8, 2026
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.1129 | $30.48 / 270 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 9, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 71610-0554-30 71610-554-30 Main listing | 30 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2021-05-12 | — | Active |
| 71610-0554-53 71610-554-53 | 60 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2022-01-31 | — | Active |
| 71610-0554-60 71610-554-60 | 90 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2021-05-12 | — | Active |
| 71610-0554-70 71610-554-70 | 120 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2021-06-09 | — | Active |
| 71610-0554-80 71610-554-80 | 180 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2022-01-18 | — | Active |
| 71610-0554-92 You're viewing this | 270 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2021-06-18 | — | Active |
| 71610-0554-94 71610-554-94 | 360 TABLET, EXTENDED RELEASE in 1 BOTTLE, PLASTIC | 2021-08-18 | — | Active |
You're viewing one of 7 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 71610-0554-30?
What NDC number is used to bill for this package of Metformin hydrochloride 500 mg Tablet, Extended Release?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Metformin Hydrochloride 500 mg 29300-0389-01 | Unichem | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 42385-0977-01 | Laurus | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 42806-0632-01 | Epic | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride Extended Release 500 mg 49483-0623-01 | TIME | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 50268-0550-15 | AvPAK | 1 tablet | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 67877-0159-01 | Ascend | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 67877-0413-01 | Ascend | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 68094-0904-50 | Precision | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin 500 mg 68645-0595-59 | Legacy | 60 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride Er 500 mg 69315-0410-01 | Leading | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin 500 mg 70010-0491-01 | Granules | 100 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin ER 500 mg 82009-0117-10 | Quallent | 1000 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 82009-0180-05 | Quallent | 500 tablets | $0.028 | AB1 | Availability likely | — |
| Metformin Hydrochloride 500 mg 62756-0142-01 | Sun | 100 tablets | $0.029 | — | FDA listed | — |
| Metformin hydrochloride 500 mg 33342-0239-11 | Macleods | 100 tablets | $0.031 | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 51224-0007-50 | TAGI | 100 tablets | $0.031 | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 69367-0412-60 | Westminster | 60 tablets | $0.164 | AB2 | Availability likely | — |
| Metformin hydrochloride 500 mg 27241-0188-60 | Ajanta | 60 tablets | $0.164 | AB2 | Availability likely | — |
| Metformin Hydrochloride 500 mg 59651-0042-60 | Aurobindo | 60 tablets | $0.164 | AB2 | Availability likely | — |
| Metformin Hydrochloride 500 mg 42571-0333-01 | Micro | 100 tablets | $0.271 | AB3 | Availability likely | — |
| Metformin Hydrochloride 500 mg 68180-0338-01 | Lupin | 100 tablets | $0.271 | AB3 | Availability likely | — |
| Metformin Hydrochloride 500 mg 70010-0496-01 | Granules | 100 tablets | $0.271 | AB3 | Availability likely | — |
| Metformin hydrochloride 500 mg 27241-0240-01 | Ajanta | 100 tablets | $0.271 | AB3 | Availability likely | — |
| Metformin Hydrochloride 500 mg 68462-0520-01 | GLENMARK | 100 tablets | $0.271 | AB3 | Availability likely | — |
| Metformin hydrochloride 500 mg 68682-0021-50 | Oceanside | 100 tablets | $0.402 | — | FDA listed | — |
| Glumetza 500 mg 68012-0004-50 | Santarus, | 100 tablets | $49.542 | — | FDA listed | — |
| Metformin Hydrochloride 500 mg 00615-8289-39 | NCS | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 10135-0823-05 | Marlex | 500 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride Extended-Release 500mg 500 mg 17224-0311-28 | Calvin | 28 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 25000-0101-03 | MARKSANS | 30 tablets | — | AB1 | FDA listed | — |
| Metformin hydrochloride 500 mg 42291-0825-10 | AvKARE | 1000 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 42708-0201-60 | QPharma | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-1494-00 | A-S | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-5396-00 | A-S | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-5397-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Metformin 500 mg 50090-6515-00 | A-S | 60 tablets | — | AB1 | FDA listed | — |
| Metformin 500 mg 50090-6516-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7116-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7576-00 | A-S | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7577-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7579-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 50090-7918-00 | A-S | 90 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride Extended Release 500 mg 51655-0555-96 | Northwind | 180 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 51655-0559-25 | Northwind | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 51655-0853-25 | Northwind | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 59651-0548-25 | Aurobindo | 25000 tablets | — | AB1 | FDA listed | — |
| Metformin ER 500 mg 62207-0491-31 | Granules | 5000 tablets | — | AB1 | FDA listed | — |
| Metformin hydrochloride 500 mg 63187-0779-00 | Proficient | 100 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 65162-0178-03 | Amneal | 30 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride 500 mg 65841-0027-01 | Zydus | 100 tablets | — | AB1 | Discontinued | — |
| Metformin Hydrochloride 500 mg 65841-0809-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Metformin 500 mg 67046-0437-03 | Coupler | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 67296-1701-06 | RedPharm | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride Extended Release 500 mg 68071-3111-02 | NuCare | 120 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 68788-8814-01 | Preferred | 100 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 68788-8866-01 | Preferred | 100 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 68788-8903-01 | Preferred | 100 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 69238-2125-01 | Amneal | 100 tablets | — | — | FDA listed | — |
| Metformin 500 mg 70518-4370-00 | REMEDYREPACK | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71205-0186-20 | Proficient | 20 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71205-0686-30 | Proficient | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride Extended Release 500 mg 71335-0293-01 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-0720-01 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-0886-01 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
| Metformin 500 mg 71335-2354-01 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-2568-01 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-9683-01 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0447-30 | Aphena | 30 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride Extended Release 500 mg 71610-0454-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0533-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Metformin hydrochloride 500 mgthis 71610-0554-92 | Aphena | 270 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0578-60 | Aphena | 90 tablets | — | AB1 | FDA listed | — |
| Metformin hydrochloride 500 mg 71610-0587-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Metformin 500 mg 71610-0613-60 | Aphena | 90 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0652-30 | Aphena | 30 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride 500 mg 71610-0837-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Metformin hydrochloride 500 mg 71610-0858-30 | Aphena | 30 tablets | — | AB1 | FDA listed | — |
| Metformin 500 mg 72162-2424-00 | Bryant | 1000 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride Extended Release 500 mg 72189-0064-30 | direct | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 72189-0150-30 | direct | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 72578-0035-01 | Viona | 100 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 72664-0227-01 | VGYAAN | 100 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride Extended Release 500 mg 72789-0009-30 | PD-Rx | 30 tablets | — | AB1 | FDA listed | — |
| Metformin hydrochloride 500 mg 72789-0105-01 | PD-Rx | 100 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 72789-0400-01 | PD-Rx | 100 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 72789-0454-60 | PD-Rx | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 72789-0455-30 | PD-Rx | 30 tablets | — | AB1 | FDA listed | — |
| Metformin hydrochloride 500 mg 76385-0128-01 | UNICHEM | 100 tablets | — | AB1 | FDA listed | — |
| Metformin 500 mg 82804-0147-30 | Proficient | 30 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 82804-0195-60 | Proficient | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 43547-0503-10 | Solco | 100 tablets | — | AB3 | FDA listed | — |
| Metformin Hydrochloride 500 mg 47335-0305-18 | Sun | 1000 tablets | — | — | Discontinued | — |
| Glumetza 500 mg 68012-0002-13 | Santarus, | 100 tablets | — | — | FDA listed | — |
| Metformin Hydrochloride 500 mg 68180-0336-01 | Lupin | 100 tablets | — | AB2 | FDA listed | — |
| Metformin Hydrochloride 500 mg 62207-0496-47 | Granules | 500 tablets | — | AB3 | FDA listed | — |
| Metformin hydrochloride 500 mg 68071-1419-02 | NuCare | 20 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 71335-3166-01 | Bryant | 60 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 67296-2305-09 | Redpharm | 90 tablets | — | AB1 | FDA listed | — |
| Metformin Hydrochloride 500 mg 70518-4639-00 | REMEDYREPACK | 1 tablet | — | AB1 | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- FDA Orange Book · refreshed Oct 9, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 9, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 8, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
🧪 Avoiding an ingredient? See Metformin inactive ingredients by manufacturer: every current product's list side by side, so you can ask your pharmacy for the version that does not list it.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII K679OBS311
Carboxymethylcellulose sodium is a plant-derived thickening agent made from cellulose. In medicines, it acts as a binder to hold ingredients together, a disintegrant to help the tablet break apart, or a thickener in liquids.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII 3NXW29V3WO
Hypromellose is a plant-based thickener made from cellulose. It's used in medicines as a binder to hold ingredients together, a coating for tablets, and a thickener for liquids.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 8, 2026
- FDA openFDA NDC Directory · synced Oct 8, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Aphena Pharma Solutions - Tennessee, LLC labeler code 71610
- Meloxicam 15 mg Tablet NDC 71610-544-30
- Folic acid 1 mg Tablet NDC 71610-545-30
- IBU Ibuprofen 600 mg Tablet NDC 71610-547-60
- Hydralazine Hydrochloride 100 mg Tablet NDC 71610-549-02
- IBU Ibuprofen 800 mg Tablet NDC 71610-550-60
- Vitamin D ergocalciferol 1.25 mg Capsule NDC 71610-552-03
- Metoprolol Succinate 25 mg Tablet, Extended Release NDC 71610-555-45
- Metoprolol Tartrate 25 mg Tablet, Film Coated NDC 71610-556-30
- lithium carbonate 300 mg Capsule NDC 71610-557-70
- Metoprolol Succinate 100 mg Tablet, Extended Release NDC 71610-558-45
- Metoprolol Tartrate 100 mg Tablet, Film Coated NDC 71610-559-53
- Hydralazine Hydrochloride 25 mg Tablet NDC 71610-561-60
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 8, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNINGS Lactic Acidosis: Lactic acidosis is a rare, but serious, metabolic complication that can occur due to metformin accumulation during treatment with Metformin Hydrochloride; when it occurs, it is fatal in approximately 50% of cases. Lactic acidosis may also occur in association with a number of pathophysiologic conditions, including diabetes mellitus, and whenever there is significant tissue hypoperfusion and hypoxemia. Lactic acidosis is characterized by elevated blood lactate levels (>5 mmol/L), decreased blood pH, electrolyte disturbances with an increased anion gap, and an increased lactate/pyruvate ratio.
When metformin is implicated as the cause of lactic acidosis, metformin plasma levels >5 μg/mL are generally found. The reported incidence of lactic acidosis in patients receiving metformin Hydrochloride is very low (approximately 0.03 cases/1000 patient-years, with approximately 0.015 fatal cases/1000 patientyears). In more than 20,000 patient-years exposure to metformin in clinical trials, there were no reports of lactic acidosis.
Reported cases have occurred primarily in diabetic patients with significant renal insufficiency, including both intrinsic renal disease and renal hypoperfusion, often in the setting of multiple concomitant medical/surgical problems and multiple concomitant medications. Patients with congestive heart failure requiring pharmacologic management, in particular those with unstable or acute congestive heart failure who are at risk of hypoperfusion and hypoxemia, are at increased risk of lactic acidosis. The risk of lactic acidosis increases with the degree of renal dysfunction and the patient's age.
The risk of lactic acidosis may, therefore, be significantly decreased by regular monitoring of renal function in patients taking Metformin Hydrochloride by use of the minimum effective dose of Metformin Hydrochloride. In particular, treatment of the elderly should be accompanied by careful monitoring of renal function. Metformin Hydrochloride treatment should not be initiated in patients ≥80 years of age unless measurement of creatinine clearance demonstrates that renal function is not reduced, as these patients are more susceptible to developing lactic acidosis.
In addition, Metformin Hydrochloride should be promptly withheld in the presence of any condition associated with hypoxemia, dehydration, or sepsis. Because impaired hepatic function may significantly limit the ability to clear lactate, Metformin Hydrochloride should generally be avoided in patients with clinical or laboratory evidence of hepatic disease. Patients should be cautioned against excessive alcohol intake, either acute or chronic, when taking Metformin Hydrochloride, since alcohol potentiates the effects of metformin Hydrochloride on lactate metabolism.
In addition, Metformin Hydrochloride should be temporarily discontinued prior to any intravascular radiocontrast study and for any surgical procedure (see also PRECAUTIONS ). The onset of lactic acidosis often is subtle, and accompanied only by nonspecific symptoms such as malaise, myalgias, respiratory distress, increasing somnolence, and nonspecific abdominal distress. There may be associated hypothermia, hypotension, and resistant bradyarrhythmias with more marked acidosis.
The patient and the patient's physician must be aware of the possible importance of such symptoms and the patient should be instructed to notify the physician immediately if they occur (see also PRECAUTIONS ). Metformin Hydrochloride should be withdrawn until the situation is clarified. Serum electrolytes, ketones, blood glucose, and if indicated, blood pH, lactate levels, and even blood metformin levels may be useful.
Once a patient is stabilized on any dose level of Metformin Hydrochloride, gastrointestinal symptoms, which are common during initiation of therapy, are unlikely to be drug related. Later occurrence of gastrointestinal symptoms could be due to lactic acidosis or other serious disease. Lev… [Excerpted — this section continues on DailyMed.]
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Metformin Hydrochloride Extended-release Tablets is indicated as an adjunct to diet and exercise to improve glycemic control in adults with type 2 diabetes mellitus.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION There is no fixed dosage regimen for the management of hyperglycemia in patients with type 2 diabetes with Metformin Hydrochloride Extended-release Tablets or any other pharmacologic agent. Dosage of Metformin Hydrochloride Extended-release Tablets must be individualized on the basis of both effectiveness and tolerance, while not exceeding the maximum recommended daily doses. The maximum recommended daily dose of Metformin Hydrochloride Extended-release Tablets in adults is 2000 mg.
Metformin Hydrochloride Extended-release Tablets should generally be given once daily with the evening meal. Metformin Hydrochloride Extended-release Tablets should be started at a low dose, with gradual dose escalation, both to reduce gastrointestinal side effects and to permit identification of the minimum dose required for adequate glycemic control of the patient. During treatment initiation and dose titration (see Recommended Dosing Schedule ), fasting plasma glucose should be used to determine the therapeutic response to Metformin Hydrochloride Extended-release Tablets and identify the minimum effective dose for the patient.
Thereafter, glycosylated hemoglobin should be measured at intervals of approximately 3 months. The therapeutic goal should be to decrease both fasting plasma glucose and glycosylated hemoglobin levels to normal or near normal by using the lowest effective dose of Metformin Hydrochloride Extended-release Tablets either when used as monotherapy or in combination with sulfonylurea or insulin. Monitoring of blood glucose and glycosylated hemoglobin will also permit detection of primary failure, i.e., inadequate lowering of blood glucose at the maximum recommended dose of medication, and secondary failure, i.e., loss of an adequate blood glucose lowering response after an initial period of effectiveness.
Short-term administration of Metformin Hydrochloride Extended-release Tablets may be sufficient during periods of transient loss of control in patients usually well-controlled on diet alone. Metformin Hydrochloride Extended-release Tablets must be swallowed whole and never crushed or chewed. Occasionally, the inactive ingredients of Metformin Hydrochloride Extended-release Tablets will be eliminated in the feces as a soft, hydrated mass.
(See Patient Information printed below.)
⛔ Contraindications ▾
CONTRAINDICATIONS Metformin Hydrochloride is contraindicated in patients with: Renal disease or renal dysfunction (e.g., as suggested by serum creatinine levels ≥1.5 mg/dL [males], ≥1.4 mg/dL [females] or abnormal creatinine clearance) which may also result from conditions such as cardiovascular collapse (shock), acute myocardial infarction, and septicemia (see WARNINGS and PRECAUTIONS ). Known hypersensitivity to Metformin Hydrochloride. Acute or chronic metabolic acidosis, including diabetic ketoacidosis, with or without coma.
Diabetic ketoacidosis should be treated with insulin. Metformin Hydrochloride should be temporarily discontinued in patients undergoing radiologic studies involving intravascular administration of iodinated contrast materials, because use of such products may result in acute alteration of renal function. (See also PRECAUTIONS. )
🤒 Adverse Reactions ▾
ADVERSE REACTIONS In a US double-blind clinical study of Metformin Hydrochloride Tablets in patients with type 2 diabetes, a total of 141patients received Metformin Hydrochloride Tablets therapy (up to 2550 mg per day) and 145 patients received placebo.Adverse reactions reported in greater than 5% of the Metformin Hydrochloride Tablets patients, and that were more common in Metformin Hydrochloride Tablets - than placebo-treated patients, are listed in Table 11. . Table 11: Most Common Adverse Reactions (>5.0 Percent) in Placebo-Controlled Studies of Metformin Hydrochloride Tablets Monotherapy Reactions that were more common in metformin Hydrochloride Extended-release Tablets - than placebo-treated patients.
Metformin Hydrochloride Extended-release Tablets Monotherapy n=141) Placebo (n=145) Adverse Reaction % of Patients Diarrhea 53.2
11.7Nausea/Vomiting 25.5
8.3Flatulance 12.1
5.5Asthenia 9.2
5.5Indigestion 7.1
4.1Abdominal Discomfort 6.4
4.8Headache 5.7
4.8Diarrhea led to discontinuation of study medication in 6% of patients treated with Metformin Hydrochloride Tablets. Additionally, the following adverse reactions were reported in ≥1.0% to ≤5.0% of Metformin Hydrochloride Tablets patients and were more commonly reported with Metformin Hydrochloride Tablets than placebo: abnormal stools, hypoglycemia, myalgia, lightheaded, dyspnea, nail disorder, rash, sweating increased, taste disorder,chest discomfort, chills, flu syndrome, flushing, palpitation. In worldwide clinical trials over 900 patients with type 2 diabetes have been treated with Metformin Hydrochloride Extended-release Tablets in placebo- and active-controlled studies.
In placebo-controlled trials, 781 patients were administered Metformin Hydrochloride Extended-release Tablets and 195 patients received placebo. Adverse reactions reported in greater than 5% of the Metformin Hydrochloride Extended-release Tablets patients, and that were more common in Metformin Hydrochloride Extended-release Tablets - than placebo-treated patients, are listed in Table 12. Table 12: Most Common Adverse Reactions (>5.0 Percent) in Placebo-Controlled Studies of Metformin Hydrochloride Extended-release Tablets Reactions that were more common in metformin Hydrochloride Extended-release Tablets - than placebo-treated patients.
Metformin Hydrochloride Extended-release Tablets n=781) Placebo (n=195) Adverse Reaction % of Patients Diarrhea 9.6
2.6Nausea/Vomiting 6.5
1.5Diarrhea led to discontinuation of study medication in 0.6% of patients treated with Metformin Hydrochloride Extended-release Tablets. Additionally, the following adverse reactions were reported in ≥1.0% to ≤5.0% of Metformin Hydrochloride Extended-release Tablets patients and were more commonly reported with Metformin Hydrochloride Extended-release Tablets than placebo: abdominal pain, constipation, distention abdomen, dyspepsia/heartburn, flatulence, dizziness, headache, upper respiratory infection, taste disturbance.
Liver function test abnormalities or hepatitis, resolving upon metformin discontinuation, have been reported very rarely.
🔄 Drug Interactions ▾
Drug Interactions (Clinical Evaluation of Drug Interactions Conducted with Metformin Hydrochloride Tablets) Glyburide - In a single-dose interaction study in type 2 diabetes patients, coadministration of metformin and glyburide did not result in any changes in either metformin pharmacokinetics or pharmacodynamics. Decreases in glyburide AUC and C max were observed, but were highly variable. The single-dose nature of this study and the lack of correlation between glyburide blood levels and pharmacodynamic effects, makes the clinical significance of this interaction uncertain (see DOSAGE AND ADMINISTRATION: Concomitant Metformin Hydrochloride and Oral Sulfonylurea Therapy in Adult Patients ).
Furosemide - A single-dose, metformin-furosemide drug interaction study in healthy subjects demonstrated that pharmacokinetic parameters of both compounds were affected by coadministration. Furosemide increased the metformin plasma and blood C max by 22% and blood AUC by 15%, without any significant change in metformin renal clearance. When administered with metformin, the C max and AUC of furosemide were 31% and 12% smaller, respectively, than when administered alone, and the terminal half-life was decreased by 32%, without any significant change in furosemide renal clearance.
No information is available about the interaction of metformin and furosemide when coadministered chronically. Nifedipine - A single-dose, metformin-nifedipine drug interaction study in normal healthy volunteers demonstrated that coadministration of nifedipine increased plasma metformin C max and AUC by 20% and 9%, respectively, and increased the amount excreted in the urine. T max and half-life were unaffected.
Nifedipine appears to enhance the absorption of metformin. Metformin had minimal effects on nifedipine. Cationic drugs - Cationic drugs (e.g., amiloride, digoxin, morphine, procainamide, quinidine, quinine, ranitidine, triamterene, trimethoprim, or vancomycin) that are eliminated by renal tubular secretion theoretically have the potential for interaction with metformin by competing for common renal tubular transport systems.
Such interaction between metformin and oral cimetidine has been observed in normal healthy volunteers in both single- and multiple-dose, metformin-cimetidine drug interaction studies, with a 60% increase in peak metformin plasma and whole blood concentrations and a 40% increase in plasma and whole blood metformin AUC. There was no change in elimination half-life in the single-dose study. Metformin had no effect on cimetidine pharmacokinetics.
Although such interactions remain theoretical (except for cimetidine), careful patient monitoring and dose adjustment of metformin hydrochloride and/or the interfering drug is recommended in patients who are taking cationic medications that are excreted via the proximal renal tubular secretory system. Other - Certain drugs tend to produce hyperglycemia and may lead to loss of glycemic control. These drugs include the thiazides and other diuretics, corticosteroids, phenothiazines, thyroid products, estrogens, oral contraceptives, phenytoin, nicotinic acid, sympathomimetics, calcium channel blocking drugs, and isoniazid.
When such drugs are administered to a patient receiving metformin hydrochloride, the patient should be closely observed for loss of blood glucose control. When such drugs are withdrawn from a patient receiving metformin hydrochloride, the patient should be observed closely for hypoglycemia. In healthy volunteers, the pharmacokinetics of metformin and propranolol, and metformin and ibuprofen were not affected when coadministered in single-dose interaction studies.
Metformin is negligibly bound to plasma proteins and is, therefore, less likely to interact with highly protein-bound drugs such as salicylates, sulfonamides, chloramphenicol, and probenecid, as compared to the sulfonylureas, which are extensively bound to serum proteins.
🤰 Pregnancy ▾
Pregnancy Teratogenic Effects Recent information strongly suggests that abnormal blood glucose levels during pregnancy are associated with a higher incidence of congenital abnormalities. Most experts recommend that insulin be used during pregnancy to maintain blood glucose levels as close to normal as possible. Because animal reproduction studies are not always predictive of human response, metformin hydrochloride should not be used during pregnancy unless clearly needed.
There are no adequate and well-controlled studies in pregnant women with metformin hydrochloride. Metformin was not teratogenic in rats and rabbits at doses up to 600 mg/kg/day. This represents an exposure of about two and six times the maximum recommended human daily dose of 2000 mg based on body surface area comparisons for rats and rabbits, respectively.
Determination of fetal concentrations demonstrated a partial placental barrier to metformin.
🧒 Pediatric Use ▾
Pediatric Use The safety and effectiveness of Metformin Hydrochloride Tablets for the treatment of type 2 diabetes have been established in pediatric patients ages 10 to 16 years (studies have not been conducted in pediatric patients below the age of 10 years). Use of Metformin Hydrochloride Tablets in this age group is supported by evidence from adequate and well-controlled studies of Metformin Hydrochloride Tablets in adults with additional data from a controlled clinical study in pediatric patients ages 10 to 16 years with type 2 diabetes, which demonstrated a similar response in glycemic control to that seen in adults.
(See CLINICAL PHARMACOLOGY: Pediatric Clinical Studies .) In this study, adverse effects were similar to those described in adults. (See ADVERSE REACTIONS: Pediatric Patients .) A maximum daily dose of 2000 mg is recommended. (See DOSAGE AND ADMINISTRATION: Recommended Dosing Schedule: Pediatrics .) Safety and effectiveness of Metformin Hydrochloride Extended - Release Tablets in pediatric patients have not been established.
🧓 Geriatric Use ▾
Geriatric Use Controlled clinical studies of metformin hydrochloride did not include sufficient numbers of elderly patients to determine whether they respond differently from younger patients, although other reported clinical experience has not identified differences in responses between the elderly and younger patients. Metformin is known to be substantially excreted by the kidney and because the risk of serious adverse reactions to the drug is greater in patients with impaired renal function, metformin hydrochloride should only be used in patients with normal renal function (see CONTRAINDICATIONS, WARNINGS , and CLINICAL PHARMACOLOGY: Pharmacokinetics ).
Because aging is associated with reduced renal function, metformin Hydrochloride Extended-release Tablets should be used with caution as age increases. Care should be taken in dose selection and should be based on careful and regular monitoring of renal function. Generally, elderly patients should not be titrated to the maximum dose of metformin hydrochloride (see also WARNINGS and DOSAGE AND ADMINISTRATION ).
🆘 Overdosage ▾
OVERDOSAGE Overdose of metformin hydrochloride has occurred, including ingestion of amounts greater than 50 grams. Hypoglycemia was reported in approximately 10% of cases, but no causal association with metformin Hydrochloride has been established. Lactic acidosis has been reported in approximately 32% of metformin overdose cases (see WARNINGS ).
Metformin is dialyzable with a clearance of up to 170 mL/min under good hemodynamic conditions. Therefore, hemodialysis may be useful for removal of accumulated drug from patients in whom metformin overdosage is suspected.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Metformin is an antihyperglycemic agent which improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose. Its pharmacologic mechanisms of action are different from other classes of oral antihyperglycemic agents. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
Unlike sulfonylureas, metformin does not produce hypoglycemia in either patients with type 2 diabetes or normal subjects (except in special circumstances, see PRECAUTIONS ) and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease.
🧬 Mechanism of Action ▾
Mechanism of Action Metformin is an antihyperglycemic agent which improves glucose tolerance in patients with type 2 diabetes, lowering both basal and postprandial plasma glucose. Its pharmacologic mechanisms of action are different from other classes of oral antihyperglycemic agents. Metformin decreases hepatic glucose production, decreases intestinal absorption of glucose, and improves insulin sensitivity by increasing peripheral glucose uptake and utilization.
Unlike sulfonylureas, metformin does not produce hypoglycemia in either patients with type 2 diabetes or normal subjects (except in special circumstances, see PRECAUTIONS ) and does not cause hyperinsulinemia. With metformin therapy, insulin secretion remains unchanged while fasting insulin levels and day-long plasma insulin response may actually decrease.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Metformin Hydrochloride Extended-release TabletsUSP are available as follows: 500 mg Bottles of 90 NDC 72789-105-90 500 mg Bottles of 100 NDC 72789-105-01 500 mg Bottles of 180 NDC 72789-105-93 500 mg Bottles of 500 NDC 72789-105-82 500 mg Bottles of 1000 NDC 72789-105-95 750 mg Bottles of 90 NDC 72789-106-90 750 mg Bottles of 100 NDC 72789-106-01 750 mg Bottles of 180 NDC 72789-106-93 750 mg Bottles of 500 NDC 72789-106-82 750 mg Bottles of 1000 NDC 72789-106-95 Metformin Hydrochloride Extended-release Tablets USP, 500 mg are white to off-white color, round, biconvex tablet, having B115 on one side and plain on the other.
Metformin Hydrochloride Extended-release Tablets USP, 750 mg are white to off-white color, capsule shape, biconvex tablet, having B116 on one side and plain on the other.
📦 Storage and Handling ▾
Storage Store at 20° - 25° C (68° - 77° F); excursions permitted to 15° - 30° C (59° - 86° F). [See USP Controlled Room Temperature.] Dispense in light-resistant containers.
📋 Description ▾
DESCRIPTION Metformin Hydrochloride Extended-release Tablets USP are oral antihyperglycemic drugs used in the management of type 2 diabetes. Metformin Hydrochloride (N,N-dimethylimidodicarbonimidic diamide Hydrochloride) is not chemically or pharmacologically related to any other classes of oral antihyperglycemic agents. The structural formula is as shown: Metformin Hydrochloride is a white to off-white crystalline compound with a molecular formula of C 4 H 11 N 5 • HCl and a molecular weight of 165.63.
Metformin Hydrochloride is freely soluble in water and is practically insoluble in acetone, ether, and chloroform. The pK a of metformin is 12.4. The pH of a 1% aqueous solution of metformin Hydrochloride is 6.68.
Metformin Hydrochloride Extended-release Tablets USP contain 500 mg or 750 mg of Metformin Hydrochloride USP as the active ingredient. Metformin Hydrochloride Extended-release Tablets USP 500 mg and 750 mg contain the inactive ingredients microcrystalline cellulose, hypromellose, povidone, sodium carboxymethyl cellulose, and magnesium stearate. System Components and Performance- Metformin Hydrochloride Extended-release Tablets USP comprises a duel hydrophilic polymer matrix system.
Metformin hydrochloride is combined with a drug release controlling polymers to form a monophasic matrix system. After administration, fluid from the gastrointestinal (GI) tract enters the tablet, causing the polymers to hydrate and swell. Drug is released slowly from the dosage form by a process of diffusion through the gel matrix that is essentially independent of pH.
The hydrated polymer system is not rigid and is expected to be broken up by normal peristalsis in the GI tract. The biologically inert components of the tablet may occasionally remain intact during GI transit and will be eliminated in the feces as a soft, hydrated mass. The USP Dissolution Test is pending. structure
💬 Information for Patients ▾
Information for Patients Patients should be informed of the potential risks and benefits of metformin hydrochloride and of alternative modes of therapy. They should also be informed about the importance of adherence to dietary instructions, of a regular exercise program, and of regular testing of blood glucose, glycosylated hemoglobin, renal function, and hematologic parameters. The risks of lactic acidosis, its symptoms, and conditions that predispose to its development, as noted in the WARNINGS and PRECAUTIONS sections, should be explained to patients.
Patients should be advised to discontinue metformin hydrochloride immediately and to promptly notify their health practitioner if unexplained hyperventilation, myalgia, malaise, unusual somnolence, or other nonspecific symptoms occur. Once a patient is stabilized on any dose level of metformin hydrochloride, gastrointestinal symptoms, which are common during initiation of metformin therapy, are unlikely to be drug related. Later occurrence of gastrointestinal symptoms could be due to lactic acidosis or other serious disease.
Patients should be counselled against excessive alcohol intake, either acute or chronic, while receiving metformin hydrochloride. Metformin hydrochloride alone does not usually cause hypoglycemia, although it may occur when metformin hydrochloride are used in conjunction with oral sulfonylureas and insulin. When initiating combination therapy, the risks of hypoglycemia, its symptoms and treatment, and conditions that predispose to its development should be explained to patients and responsible family members.
(See Patient Information printed below.) Patients should be informed that metformin Hydrochloride Extended-release Tablets must be swallowed whole and not crushed or chewed, and that the inactive ingredients may occasionally be eliminated in the feces as a soft mass that may resemble the original tablet.
⚠️ Precautions ▾
PRECAUTIONS General Macrovascular Outcomes - There have been no clinical studies establishing conclusive evidence of macrovascular risk reduction with metformin hydrochloride or any other antidiabetic drug. Monitoring of renal function - Metformin is known to be substantially excreted by the kidney, and the risk of metformin accumulation and lactic acidosis increases with the degree of impairment of renal function. Thus, patients with serum creatinine levels above the upper limit of normal for their age should not receive metformin hydrochloride.
In patients with advanced age, metformin hydrochloride should be carefully titrated to establish the minimum dose for adequate glycemic effect, because aging is associated with reduced renal function. In elderly patients, particularly those ≥80 years of age, renal function should be monitored regularly and, generally, metformin Hydrochloride Extended-release Tablets should not be titrated to the maximum dose (see WARNINGS and DOSAGE AND ADMINISTRATION ). Before initiation of metformin hydrochloride therapy and at least annually hereafter, renal function should be assessed and verified as normal.
In patients in whom development of renal dysfunction is anticipated, renal function should be assessed more frequently and metformin hydrochloride discontinued if evidence of renal impairment is present. Use of concomitant medications that may affect renal function or metformin disposition - Concomitant medication(s) that may affect renal function or result in significant hemodynamic change or may interfere with the disposition of metformin, such as cationic drugs that are eliminated by renal tubular secretion (see PRECAUTIONS: Drug Interactions ), should be used with caution.
Radiologic studies involving the use of intravascular iodinated contrast materials (for example, intravenous urogram, intravenous cholangiography, angiography, and computed tomography (CT) scans with intravascular contrast materials) - Intravascular contrast studies with iodinated materials can lead to acute alteration of renal function and have been associated with lactic acidosis in patients receiving metformin (see CONTRAINDICATIONS ). Therefore, in patients in whom any such study is planned, metformin hydrochloride should be temporarily discontinued at the time of or prior to the procedure, and withheld for 48 hours subsequent to the procedure and reinstituted only after renal function has been re-evaluated and found to be normal.
Hypoxic states - Cardiovascular collapse (shock) from whatever cause, acute congestive heart failure, acute myocardial infarction and other conditions characterized by hypoxemia have been associated with lactic acidosis and may also cause prerenal azotemia. When such events occur in patients on metformin hydrochloride therapy, the drug should be promptly discontinued. Surgical procedures - Metformin hydrochloride therapy should be temporarily suspended for any surgical procedure (except minor procedures not associated with restricted intake of food and fluids) and should not be restarted until the patient's oral intake has resumed and renal function has been evaluated as normal.
Alcohol intake - Alcohol is known to potentiate the effect of metformin on lactate metabolism. Patients, therefore, should be warned against excessive alcohol intake, acute or chronic, while receiving metformin hydrochloride. Impaired hepatic function - Since impaired hepatic function has been associated with some cases of lactic acidosis, metformin hydrochloride should generally be avoided in patients with clinical or laboratory evidence of hepatic disease.
Vitamin B 12 levels - In controlled clinical trials of metformin Hydrochloride Tablets of 29 weeks duration, a decrease to subnormal levels of previously normal serum vitamin B 12 levels, without clinical manifestations, was observed in approximately 7% of patients. Such decrease, possibly due to interference with B 12 absorption from the B 12 -intrinsic factor… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers Studies in lactating rats show that metformin is excreted into milk and reaches levels comparable to those in plasma. Similar studies have not been conducted in nursing mothers. Because the potential for hypoglycemia in nursing infants may exist, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
If metformin hydrochloride are discontinued, and if diet alone is inadequate for controlling blood glucose, insulin therapy should be considered.
🧬 Pharmacokinetics ▾
Pharmacokinetics Absorption and Bioavailability The absolute bioavailability of a Metformin Hydrochloride 500 mg tablet given under fasting conditions is approximately 50% to 60%. Studies using single oral doses of Metformin Hydrochloride 500 to 1500 mg, and 850 to 2550 mg, indicate that there is a lack of dose proportionality with increasing doses, which is due to decreased absorption rather than an alteration in elimination. Food decreases the extent of and slightly delays the absorption of metformin, as shown by approximately a 40% lower mean peak plasma concentration (C max ), a 25% lower area under the plasma concentration versus time curve (AUC), and a 35-minute prolongation of time to peak plasma concentration (T max ) following administration of a single 850 mg tablet of metformin with food, compared to the same tablet strength administered fasting.
The clinical relevance of these decreases is unknown. Following a single oral dose of Metformin Hydrochloride Extended-release tablet, C max is achieved with a median value of 7 hours and a range of 4 to 8 hours. Peak plasma levels are approximately 20% lower compared to the same dose of Metformin Hydrochloride tablet, however, the extent of absorption (as measured by AUC) is similar to Metformin Hydrochloride tablet.
At steady state, the AUC and C max are less than dose proportional for Metformin Hydrochloride Extended-release Tablets within the range of 500 to 2000 mg administered once daily. Peak plasma levels are approximately 0.6, 1.1, 1.4, and 1.8 mcg/mL for 500, 1000, 1500, and 2000 mg once-daily doses, respectively. The extent of metformin absorption (as measured by AUC) from Metformin Hydrochloride Extended-release tablet at a 2000 mg once-daily dose is similar to the same total daily dose administered as Metformin Hydrochloride Tablets 1000 mg twice daily.
After repeated administration of Metformin Hydrochloride Extended-release Tablets, metformin did not accumulate in plasma. Within-subject variability in C max and AUC of metformin from Metformin Hydrochloride Extended-release Tablets is comparable to that with Metformin Hydrochloride Tablets. Although the extent of metformin absorption (as measured by AUC) from the Metformin Hydrochloride Extended-release Tablets increased by approximately 50% when given with food, there was no effect of food on C max and T max of metformin.
Both high and low fat meals had the same effect on the pharmacokinetics of Metformin Hydrochloride Extended-release Tablets.
🔬 Clinical Studies ▾
Clinical Studies Metformin Hydrochloride Tablets In a double-blind, placebo-controlled, multicenter US clinical trial involving obese patients with type 2 diabetes whose hyperglycemia was not adequately controlled with dietary management alone (baseline fasting plasma glucose [FPG] of approximately 240 mg/dL), treatment with Metformin Hydrochloride Tablets (up to 2550 mg/day) for 29 weeks resulted in significant mean net reductions in fasting and postprandial plasma glucose (PPG) and hemoglobin A1c (HbA1c) of 59 mg/dL, 83 mg/dL, and 1.8%, respectively, compared to the placebo group (see Table 2 ).
Table 2. Metformin vs Placebo Summary of Mean Changes from Baseline All patients on diet therapy at Baseline in Fasting Plasma Glucose, HbA1c and Body Weight, at Final Visit (29-week study) Metformin Hydrochloride Tablets (n=141) Placebo (n=145) p–Value FPG (mg/dL) Baseline Change at FINAL VISIT 241.5 -53.0 237.7
6.3NS Not statistically significant 0.001 Hemoglobin A 1c (%) Baseline Change at FINAL VISIT 8.4 -1.4 8.2
0.4NS 0.001 Body Weight (lbs) Baseline Change at FINAL VISIT 201.0 -1.4 206.0 -2.4 NS NS A 29-week, double-blind, placebo-controlled study of Metformin Hydrochloride Tablets and glyburide, alone and in combination, was conducted in obese patients with type 2 diabetes who had failed to achieve adequate glycemic control while on maximumdoses of glyburide (baseline FPG of approximately 250 mg/dL) (see Table 3). Patients randomized to the combination armstarted therapy with Metformin Hydrochloride Tablets 500 mgand glyburide 20 mg.
At the end of each week of the first 4 weeks of the trial, these patients had theirdosages of Metformin Hydrochloride Tablets increased by 500 mg if they had failed to reach target fasting plasma glucose. After week 4, such dosage adjustments were made monthly, although no patient was allowed toexceed Metformin Hydrochloride Tablets 2500 mg. Patients in the Metformin Hydrochloride Tablets only arm(metformin plus placebo) followed the same titration schedule.
At the end of the trial, approximately 70% of the patients in the combination group were taking Metformin Hydrochloride Tablets 2000 mg/glyburide 20 mg or Metformin Hydrochloride Tablets 2500 mg/glyburide 20 mg. Patients randomized to continue on glyburide experienced worsening of glycemiccontrol, with mean increases in FPG, PPG, and HbA1c of 14 mg/dL, 3 mg/dL, and 0.2%, respectively. Incontrast, those randomized to Metformin Hydrochloride Tablets (up to 2500 mg/day) experienced a slight improvement, with mean reductions in FPG, PPG, and HbA1c of 1 mg/dL, 6 mg/dL, and 0.4%, respectively.
The combination of Metformin Hydrochloride Tablets and glyburide was effective in reducing FPG, PPG, and HbA1c levels by 63 mg/dL, 65 mg/dL, and 1.7%, respectively. Compared to results of glyburide treatment alone, the net differences with combination treatment were –77 mg/dL, –68 mg/dL, and –1.9%, respectively (see Table 3 ). Table 3.
Combined Metformin Hydrochloride Tablets /Glyburide (Comb) vs Glyburide (Glyb) or Metformin Hydrochloride Tablets (Met) Monotherapy: Summary of Mean Changes from Baseline All patients on glyburide, 20 mg/day, at Baseline in Fasting Plasma Glucose, HbA 1c and Body Weight, at Final Visit (29-week study) p-values Comb (n=213) Glyb (n=209) MET (n=210) Glyb vs Comb MET vs Comb MET vs Glyb Fasting Plasma Glucose (mg/dL) Baseline Change at FINAL VISIT 250.5 -63.5 247.5 13.7 253.9 -0.9 NS Not statistically significant 0.001 NS 0.001 NS 0.025 Hemoglobin A 1c (%) Baseline Change at FINAL VISIT 8.8 -1.7 8.5 0.2 8.9 -0.4 NS 0.001 NS 0.001 0.007 0.001 Body Weight (lbs) Baseline Change at FINAL VISIT 202.2 0.9 203.0 -0.7 204.0 -8.4 NS 0.011 NS 0.001 NS 0.001 The magnitude of the decline in fasting blood glucose concentration following the institution of Metformin Hydrochloride Tablets therapy was proportional to the level of fasting hyperglycemia.
Patients withtype 2 diabetes with higher fasting glucose concentrations experienced greater de… [Excerpted — this section continues on DailyMed.]
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
Carcinogenesis, Mutagenesis, Impairment of Fertility Long-term carcinogenicity studies have been performed in rats (dosing duration of 104 weeks) and mice (dosing duration of 91 weeks) at doses up to and including 900 mg/kg/day and 1500 mg/kg/day, respectively. These doses are both approximately four times the maximum recommended human daily dose of 2000 mg based on body surface area comparisons. No evidence of carcinogenicity with metformin was found in either male or female mice.
Similarly, there was no tumorigenic potential observed with metformin in male rats. There was, however, an increased incidence of benign stromal uterine polyps in female rats treated with 900 mg/kg/day. There was no evidence of a mutagenic potential of metformin in the following in vitro tests: Ames test ( S. typhimurium ), gene mutation test (mouse lymphoma cells), or chromosomal aberrations test (human lymphocytes).
Results in the in vivo mouse micronucleus test were also negative. Fertility of male or female rats was unaffected by metformin when administered at doses as high as 600 mg/kg/day, which is approximately three times the maximum recommended human daily dose based on body surface area comparisons.
📄 Patient Package Insert ▾
PATIENT INFORMATION Rx only Metformin ER Tablets (Metformin Hydrochloride) Extended-release Tablets USP, 500 mg and 750 mg Read this information carefully before you start taking this medicine and each time you refill your prescription. There may be new information. This information does not take the place of your doctor’s advice.
Ask your doctor or pharmacist if you do not understand some of this information or if you want to know more about this medicine. What is Metformin Hydrochloride? Metformin Hydrochloride is used to treat type 2 diabetes.
This is also known as non-insulin-dependent diabetes mellitus. People with type 2 diabetes are not able to make enough insulin or respond normally to the insulin their bodies make. When this happens, sugar (glucose) builds up in the blood.
This can lead to serious medical problems including kidney damage, amputations, and blindness. Diabetes is also closely linked to heart disease. The main goal of treating diabetes is to lower your blood sugar to a normal level.
High blood sugar can be lowered by diet and exercise, by a number of medicines taken by mouth, and by insulin shots. Before you take Metformin Hydrochloride, try to control your diabetes by exercise and weight loss. While you take your diabetes medicine, continue to exercise and follow the diet advised for your diabetes.
No matter what your recommended diabetes management plan is, studies have shown that maintaining good blood sugar control can prevent or delay complications of diabetes, such as blindness. This medicine helps control your blood sugar in a number of ways. These include helping your body respond better to the insulin it makes naturally, decreasing the amount of sugar your liver makes, and decreasing the amount of sugar your intestines absorb.
Metformin Hydrochloride does not cause your body to make more insulin. Because of this, when taken alone, they rarely cause hypoglycemia (low blood sugar), and usually do not cause weight gain. However, when they are taken with a sulfonylurea or with insulin, hypoglycemia is more likely to occur, as is weight gain.
WARNING: A small number of people who have taken Metformin Hydrochloride have developed a serious condition called lactic acidosis. Lactic acidosis is caused by a buildup of lactic acid in the blood. This happens more often in people with kidney problems.
Most people with kidney problems should not take Metformin Hydrochloride. (See " What are the side effects of Metformin Hydrochloride? ") Who should not take Metformin Hydrochloride? Some conditions increase your chance of getting lactic acidosis, or cause other problems if you take either of these medicines.
Most of the conditions listed below can increase your chance of getting lactic acidosis. Do not take Metformin Hydrochloride if you: have kidney problems have liver problems have heart failure that is treated with medicines, such as digoxin or furosemide drink a lot of alcohol. This means you binge drink for short periods or drink all the time are seriously dehydrated (have lost a lot of water from your body) are going to have an x-ray procedure with injection of dyes (contrast agents) are going to have surgery develop a serious condition, such as heart attack, severe infection, or a stroke are 80 years or older and you have NOT had your kidney function tested Tell your doctor if you are pregnant or plan to become pregnant.
Metformin Hydrochloride may not be right for you. Talk with your doctor about your choices. You should also discuss your choices with your doctor if you are nursing a child.
Can Metformin Hydrochloride Extended-release Tablets USP be used in children? Metformin Hydrochloride Extended-release Tablets USP have not been studied in children. How should I take Metformin Hydrochloride?
Your doctor will tell you how much medicine to take and when to take it. You will probably start out with a low dose of the medicine. Your doctor may slowly increase your dose until your blood sugar is better c… [Excerpted — this section continues on DailyMed.]
📄 Package Label / Principal Display Panel ▾
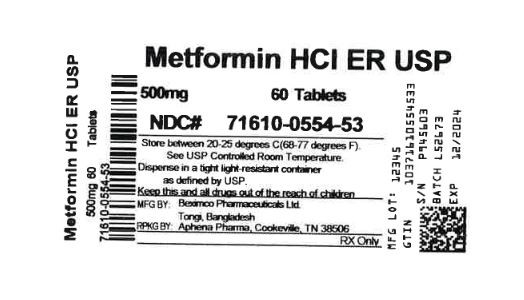
PRINCIPAL DISPLAY PANEL - 500 mg NDC 71610-554 - Metformin HCl ER, USP 500mg Tablets - Rx Only Bottle Label 500 mg
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |