
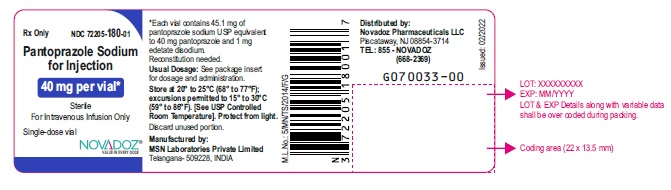
Pantoprazole Sodium 40 mg/10mL Injection, Powder, For Solution
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Proton Pump Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Pantoprazole injection is used as a short-term treatment to treat gastroesophageal reflux disease (GERD; a condition in which backward flow of acid from the stomach causes heartburn and possible injury of the esophagus [the tube between the throat and stomach]) in people who have had damage to their esophagus and who are unable to take pantoprazole by mouth. It is also used to treat conditions where the stomach produces too much acid, such as Zollinger-Ellison syndrome (tumors in the pancreas and small intestine that caused increased production of stomach acid). Pantoprazole is in a class of m...
Read the full MedlinePlus article ↗- Pantoprazole shuts down the pumps in your stomach that produce acid. Most people notice relief from heartburn and related symptoms within a few days of starting it, but the full he...
- What exactly does pantoprazole do, and how quickly will I feel better?
- It depends on the form you're taking. If you're on the delayed-release tablet, you can take it with or without food — meals just delay it a bit but don't affect how much gets absor...
- Does it matter when I take pantoprazole — with food or without?
Patient education
Supplement & herbal interactions
Pantoprazole may be associated with lower levels of 9 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
1 mg / 10 mL
UNII 7FLD91C86K
Edetate disodium is a chemical compound that binds and removes certain metal ions. In medicines, it acts as a preservative and stabilizer by preventing metals like calcium from interfering with the product's shelf life and consistency.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
2 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Pantoprazole Sodium 40 mg 00143-9284-10 | Hikma | 10 vials | $2.374 | AP | Availability likely | — |
| Pantoprazole Sodium 40 mg 00143-9300-10 | Hikma | 10 vials | $2.374 | AP | Availability likely | — |
| Pantoprazole Sodium 40 mg/10mL 25021-0751-10 | Sagent | 10 vials | $2.374 | AP | Availability likely | — |
| pantoprazole sodium 40 mg 31722-0204-10 | Camber | 10 vials | $2.374 | AP | Availability likely | — |
| Pantoprazole Sodium 40 mg 55150-0202-10 | Eugia | 10 vials | $2.374 | AP | Availability likely | — |
| Pantoprazole Sodium I.v. 40 mg/10mL 66794-0258-41 | Piramal | 1 vial | $2.374 | AP | Availability likely | — |
| Pantoprazole sodium 40 mg/10mL 70095-0024-02 | Sun | 1 vial | $2.374 | AP | Availability likely | — |
| Pantoprazole Sodium 40 mg/10mL 71288-0600-11 | Meitheal | 10 vials | $2.374 | AP | Availability likely | — |
| Pantoprazole Sodium 40 mg/10mL 72603-0128-10 | Northstar | 10 vials | $2.374 | AP | Availability likely | — |
| Protonix I.V. 40 mg/10mL 00008-0923-51 | Wyeth | 1 vial | — | AP | FDA listed | — |
| Protonix I.V. 40 mg/10mL 00008-4001-10 | Wyeth | 1 vial | — | AP | FDA listed | — |
| Pantoprazole Sodium I.v. 40 mg/10mL 00781-3480-95 | Sandoz | 10 vials | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg/10mL 46708-0071-01 | Alembic | 1 vial | — | AP | FDA listed | — |
| Protonix I.V. 40 mg/10mL 55154-4225-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Protonix I.V. 40 mg/10mL 55154-4236-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg 55154-7477-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg 55154-8336-05 | Cardinal | 5 vials | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg/10mL 62332-0071-01 | Alembic | 1 vial | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg/10mL 62756-0129-40 | Sun | 1 vial | — | — | FDA listed | — |
| Pantoprazole Sodium 40 mg/10mL 65219-0385-10 | Fresenius | 10 vials | — | AP | FDA listed | — |
| Pantoprazole sodium 40 mg/10mL 68083-0493-01 | Gland | 1 vial | — | AP | FDA listed | — |
| Pantoprazole sodium 40 mg/10mL 71839-0122-01 | BE | 1 vial | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg/10mLthis 72205-0180-07 | Novadoz | 10 vials | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg 72572-0553-10 | Civica, | 10 vials | — | AP | FDA listed | — |
| Pantoprazole Sodium 40 mg/10mL 73043-0020-01 | Devatis | 1 vial | — | AP | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72205-0180-07 You're viewing this | 10 VIAL in 1 CARTON (72205-180-07) / 10 mL in 1 VIAL (72205-180-01) | 2022-05-19 | Active |
| 72205-0180-09 | 25 VIAL in 1 CARTON (72205-180-09) / 10 mL in 1 VIAL (72205-180-01) | 2022-05-19 | Active |
Pack size FAQ
What quantity is in NDC 72205-0180-07?
What NDC number is used to bill for this package of Pantoprazole Sodium 40 mg/10mL Injection, Powder, For Solution?
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Does this product come in other package sizes?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Pantoprazole sodium is a proton pump inhibitor (PPI) indicated in adults for the following: • Short-term treatment (7 to 10 days) of gastroesophageal reflux disease (GERD) associated with a history of Erosive Esophagitis (EE). (1.1) • Pathological hypersecretion conditions including Zollinger-Ellison (ZE) Syndrome. (1.2)
1.1Gastroesophageal Reflux Disease Associated with a History of Erosive Esophagitis Pantoprazole sodium for injection is indicated for short-term treatment (7 to 10 days) of adult patients with gastroesophageal reflux disease (GERD) and a history of erosive esophagitis (EE). Safety and efficacy of pantoprazole sodium for injection as a treatment of patients with GERD and a history of EE for more than 10 days have not been demonstrated.
1.2Pathological Hypersecretion Including Zollinger-Ellison Syndrome Pantoprazole sodium for injection is indicated for the treatment of pathological hypersecretory conditions including Zollinger-Ellison (ZE) Syndrome in adults.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION GERD Associated with EE (2.1) • The recommended adult dosage is 40 mg given once daily by intravenous infusion for 7 to 10 days. (2.1) Pathological Hypersecretion Conditions, Including ZE Syndrome (2.3) : • The recommended adult dosage is 80 mg administered every 12 hours by intravenous infusion. For information on how to adjust dosing for individual patient needs, see the full prescribing information.
Administration (2.2 , 2.4 ): • Only for intravenous infusion. • The intravenous infusion can be administered over 2 minutes or 15 minutes. • For information on how to prepare and administer for each indication, see the full prescribing information.
2.1Dosage for Gastroesophageal Reflux Disease Associated With a History of Erosive Esophagitis The recommended adult dosage of pantoprazole sodium for injection is 40 mg given once daily by intravenous infusion for 7 to 10 days. Discontinue treatment with pantoprazole sodium for injection as soon as the patient is able to receive treatment with pantoprazole sodium delayed-release tablets or oral suspension. Data on the safe and effective dosing for conditions other than those described [see Indications and Usage (1)] such as life-threatening upper gastrointestinal bleeds, are not available.
Pantoprazole sodium for injection 40 mg once daily does not raise gastric pH to levels sufficient to contribute to the treatment of such life-threatening conditions.
2.2Preparation and Administration Instructions for Gastroesophageal Reflux Disease Associated with a History of Erosive Esophagitis Only for intravenous infusion; other parenteral routes of administration are not recommended. Fifteen Minute Infusion 1. Reconstitute pantoprazole sodium for injection with 10 mL of 0.9% Sodium Chloride Injection, USP.
2. Further dilute with 100 mL of 5% Dextrose Injection, USP, 0.9% Sodium Chloride Injection, USP, or Lactated Ringer's Injection, USP, to a final concentration of approximately 0.4 mg/mL. 3.
Inspect the diluted pantoprazole sodium for injection solution visually for particular matter and discoloration prior to and during administration. 4. Administer intravenously over a period of approximately 15 minutes at a rate of approximately 7 mL/min.
Storage The reconstituted solution may be stored for up to 6 hours at room temperature prior to further dilution. The admixed solution may be stored at room temperature and must be used within 24 hours from the time of initial reconstitution. Both the reconstituted solution and the admixed solution do not need to be protected from light.
Do not freeze the reconstituted solution. Discard unused portion. Two Minute Infusion 1.
Reconstitute pantoprazole sodium for injection with 10 mL of 0.9% Sodium Chloride Injection, USP, to a final concentration of approximately 4 mg/mL. 2. Inspect the diluted pantoprazole sodium for injection solution visually for particular matter and discoloration prior to and during administration.
3. Administer intravenously over a period of at least 2 minutes. Storage The reconstituted solution may be stored for up to 24 hours at room temperature prior to intravenous infusion and does not need to be protected from light.
Do not freeze the reconstituted solution. Discard unused portion.
2.3Dosage for Pathological Hypersecretion Including Zollinger-Ellison Syndrome The recommended adult dosage of pantoprazole sodium for injection is 80 mg intravenously every 12 hours. The frequency of dosing can be adjusted to individual patient needs based on acid output measurements. In those patients who need a higher dosage, 80 mg intravenously every 8 hours is expected to maintain acid output below 10 mEq/h.
Daily doses higher than 240 mg or administered for more than 6 days have not been studied [see Clinical Studies (14)] . Transition from oral to intravenous and from intravenous to oral formulations of gastric acid inhibitors should be performed in such a manner to ensure continuity of effect of suppression of a…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS For Injection: 40 mg of pantoprazole white to off-white lyophilized cake or powder in a single-dose vial for reconstitution. • For Injection: 40 mg pantoprazole lyophilized cake or powder in a single-dose vial for reconstitution. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS • Pantoprazole sodium for injection is contraindicated in patients with known hypersensitivity reactions including anaphylaxis to the formulation or any substituted benzimidazole. Hypersensitivity reactions may include anaphylaxis, anaphylactic shock, angioedema, bronchospasm, acute tubulointerstitial nephritis, and urticaria [see Warnings and Precautions ( 5.2 , 5.4 ), Adverse Reactions (6)] . • Proton pump inhibitors (PPIs), including pantoprazole sodium for injection, are contraindicated in patients receiving rilpivirine-containing products [see Drug Interactions (7)] . • Patients with a known hypersensitivity to any component of the formulation or to substituted benzimidazoles.
(4) • Patients receiving rilpivirine-containing products. (4 , 7)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS • Gastric Malignancy: In adults, symptomatic response to therapy with pantoprazole sodium for injection does not preclude the presence of gastric malignancy. Consider additional follow-up and diagnostic testing. (5.1) • Injection Site Reactions: Thrombophlebitis is associated with the administration of intravenous pantoprazole.
( 5.2 ) • Potential Exacerbation of Zinc Deficiency: Consider zinc supplementation in patients who are prone to zinc deficiency. Caution should be used when other EDTA containing products are also co-administered intravenously. ( 5.3 ) • Acute Tubulointerstitial Nephritis: Discontinue treatment and evaluate patients.
( 5.4 ) • Clostridium difficile-Associated Diarrhea: PPI therapy may be associated with increased risk. ( 5.5 ) • Bone Fracture: Long term and multiple daily dose PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist or spine. ( 5.6 ) • Severe Cutaneous Adverse Reactions: Discontinue at the first signs or symptoms of severe cutaneous adverse reactions or other signs of hypersensitivity and consider further evaluation.
( 5.7 ) • Cutaneous and Systemic Lupus Erythematosus: Mostly cutaneous; new onset or exacerbation of existing disease; discontinue pantoprazole sodium for injection and refer to specialist for evaluation. (5.8) • Hepatic Effects : Elevations of transaminases observed. (5.9) • Hypomagnesemia and Mineral Metabolism: Reported rarely with prolonged treatment with PPIs.
(5.10) • Fundic Gland Polyps: Risk increases with long-term use, especially beyond one year. Use the shortest duration of therapy. (5.11)
5.1Presence of Gastric Malignancy In adults, symptomatic response to therapy with pantoprazole sodium for injection does not preclude the presence of gastric malignancy. Consider additional follow-up and diagnostic testing in adult patients who have a suboptimal response or an early symptomatic relapse after completing treatment with a PPI. In older patients, also consider an endoscopy.
5.2Injection Site Reactions Thrombophlebitis was associated with the administration of pantoprazole sodium for injection.
5.3Potential for Exacerbation of Zinc Deficiency Pantoprazole sodium for injection contains edetate disodium (the salt form of EDTA), a chelator of metal ions including zinc. Therefore, zinc supplementation should be considered in patients treated with pantoprazole sodium for injection who are prone to zinc deficiency. Caution should be used when other EDTA containing products are also co-administered intravenously [see Dosage and Administration (2.5)].
5.4Acute Tubulointerstitial Nephritis Acute tubulointerstitial nephritis (TIN) has been observed in patients taking PPIs and may occur at any point during PPI therapy. Patients may present with varying signs and symptoms from symptomatic hypersensitivity reactions to non-specific symptoms of decreased renal function (e.g., malaise, nausea, anorexia). In reported case series, some patients were diagnosed on biopsy and in the absence of extra-renal manifestations (e.g., fever, rash or arthralgia).
Discontinue pantoprazole sodium for injection and evaluate patients with suspected acute TIN [see Contraindications (4) ].
5.5Clostridium difficile -Associated Diarrhea Published observational studies suggest that PPI therapy like pantoprazole sodium for injection may be associated with an increased risk of Clostridium difficile associated diarrhea, especially in hospitalized patients. This diagnosis should be considered for diarrhea that does not improve [see Adverse Reactions (6.2)] . Patients should use the lowest dose and shortest duration of PPI therapy appropriate to the condition being treated.
5.6Bone Fracture Several published observational studies suggest that PPI therapy may be associated with an increased risk for osteoporosis-related fractures of the hip, wrist, or spine. The risk of fracture was increased in patients who received high-dose,…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are described below and elsewhere in labeling: • Injection Site Reactions [see Warnings and Precautions (5.2) ] • Potential for Exacerbation of Zinc Deficiency [see Warnings and Precautions (5.3) ] • Acute Tubulointerstitial Nephritis [see Warnings and Precautions (5.4) ] • Clostridium difficile-Associated Diarrhea [see Warnings and Precautions (5.5) ] • Bone Fracture [see Warnings and Precautions (5.6 )] • Severe Cutaneous Adverse Reactions [see Warnings and Precautions (5.7) ] • Cutaneous and Systemic Lupus Erythematosus [see Warnings and Precautions (5.8)] • Hepatic Effects [see Warnings and Precautions (5.9)] • Hypomagnesemia and Mineral Metabolism [see Warnings and Precautions (5.10)] • Fundic Gland Polyps [see Warnings and Precautions (5.11)] Most common adverse reactions (>2%) are: headache, diarrhea, nausea, abdominal pain, vomiting, flatulence, dizziness, and arthralgia.
(6.1) To report SUSPECTED ADVERSE REACTIONS, contact Novadoz Pharmaceuticals LLC at 1-855-668-2369 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in clinical practice. Worldwide, approximately 80,500 patients have been treated with pantoprazole in clinical trials involving various dosages and duration of treatment. Gastroesophageal Reflux Disease (GERD) Safety in nine randomized comparative US clinical trials in patients with GERD included 1,473 patients on oral pantoprazole sodium (20 mg or 40 mg), 299 patients on an H 2 -receptor antagonist, 46 patients on another PPI, and 82 patients on placebo.
The most frequently occurring adverse reactions are listed in Table 1. The number of patients treated in comparative studies with pantoprazole sodium for injection is limited; however, the adverse reactions seen were similar to those seen in the oral studies. Thrombophlebitis was the only new adverse reaction identified with pantoprazole sodium for injection.
Table 1: Adverse Reactions Reported in Clinical Trials of Adult Patients with GERD at a Frequency of > 2% Oral Pantoprazole Sodium (n=1473) % Comparators (n=345) % Placebo (n=82) % Headache 12.2 12.8
8.5Diarrhea 8.8 9.6
4.9Nausea 7.0 5.2
9.8Abdominal pain 6.2 4.1
6.1Vomiting 4.3 3.5
2.4Flatulence 3.9 2.9
3.7Dizziness 3.0 2.9
1.2Arthralgia 2.8 1.4
1.2Additional adverse reactions that were reported for oral pantoprazole sodium in US clinical trials with a frequency of ≤2% are listed below by body system: Body as a Whole: allergic reaction, fever, photosensitivity reaction, facial edema, thrombophlebitis (I.V. only) Gastrointestinal: constipation, dry mouth, hepatitis Hematologic: leukopenia (reported in ex-US clinical trials only), thrombocytopenia Metabolic/Nutritional: elevated CPK (creatine phosphokinase), generalized edema, elevated triglycerides, liver function tests abnormal Musculoskeletal: myalgia Nervous: depression, vertigo Skin and Appendages: urticaria, rash, pruritus Special Senses: blurred vision Zollinger-Ellison (ZE) Syndrome In clinical studies of ZE Syndrome, adverse reactions reported in 35 patients administered pantoprazole sodium for injection doses of 80 mg to 240 mg per day for up to 2 years were similar to those reported in adult patients with GERD.
6.2Postmarketing Experience The following adverse reactions have been identified during postapproval use of pantoprazole sodium and pantoprazole sodium for injection. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure. These adverse reactions are listed below by body system: General Disorders and Administration Conditions: asthenia, fatigue,…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Table 2 includes drugs with clinically important drug interactions and interaction with diagnostics when administered concomitantly with pantoprazole sodium for injection and instructions for preventing or managing them. Consult the labeling of concomitantly used drugs to obtain further information about interactions with PPIs. Table 2: Clinically Relevant Interactions Affecting Drugs Co-Administered with Pantoprazole Sodium for Injection and Interaction with Diagnostics Antiretrovirals Clinical Impact: The effect of PPIs on antiretroviral drugs is variable.
The clinical importance and the mechanisms behind these interactions are not always known. Decreased exposure of some antiretroviral drugs (e.g., rilpivirine atazanavir, and nelfinavir) when used concomitantly with pantoprazole may reduce antiviral effect and promote the development of drug resistance. Increased exposure of other antiretroviral drugs (e.g., saquinavir) when used concomitantly with pantoprazole may increase toxicity of the antiretroviral drugs.
There are other antiretroviral drugs which do not result in clinically relevant interactions with pantoprazole. Intervention: Rilpivirine-containing products: Concomitant use with pantoprazole sodium for injection is contraindicated [see Contraindications (4)] . See prescribing information.
Atazanavir : See prescribing information for atazanavir for dosing information. Nelfinavir: Avoid concomitant use with pantoprazole sodium for injection. See prescribing information for nelfinavir.
Saquinavir: See the prescribing information for saquinavir and monitor for potential saquinavir toxicities. Other antiretrovirals: See prescribing information. Warfarin Clinical Impact: Increased INR and prothrombin time in patients receiving PPIs, including pantoprazole, and warfarin concomitantly.
Increases in INR and prothrombin time may lead to abnormal bleeding and even death. Intervention: Monitor INR and prothrombin time. Dose adjustment of warfarin may be needed to maintain target INR range.
See prescribing information for warfarin. Clopidogrel Clinical Impact: Concomitant administration of pantoprazole and clopidogrel in healthy subjects had no clinically important effect on exposure to the active metabolite of clopidogrel or clopidogrel-induced platelet inhibition [see Clinical Pharmacology (12.3)]. Intervention: No dose adjustment of clopidogrel is necessary when administered with an approved dose of pantoprazole sodium for injection.
Methotrexate Clinical Impact: Concomitant use of PPIs with methotrexate (primarily at high dose) may elevate and prolong serum concentrations of methotrexate and/or its metabolite hydroxymethotrexate, possibly leading to methotrexate toxicities. No formal drug interaction studies of high-dose methotrexate with PPIs have been conducted [see Warnings and Precautions (5.14)]. Intervention: A temporary withdrawal of pantoprazole sodium for injection may be considered in some patients receiving high-dose methotrexate.
Drugs Dependent on Gastric pH for Absorption (e.g., iron salts, erlotinib, dasatinib, nilotinib, mycophenolate mofetil, ketoconazole/itraconazole) Clinical Impact: Pantoprazole can reduce the absorption of other drugs due to its effect on reducing intragastric acidity. Intervention: Mycophenolate mofetil (MMF): Co-administration of pantoprazole sodium in healthy subjects and in transplant patients receiving MMF has been reported to reduce the exposure to the active metabolite, mycophenolic acid (MPA), possibly due to a decrease in MMF solubility at an increased gastric pH [see Clinical Pharmacology (12.3)].
The clinical relevance of reduced MPA exposure on organ rejection has not been established in transplant patients receiving pantoprazole sodium for injection and MMF. Use pantoprazole sodium for injection with caution in transplant patients receiving MMF. See the prescribing information for other drugs dependent on gastric pH for absorption.
Interactions with Inve…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Pregnancy: Based on animal data, may cause fetal harm. (8.1)
8.1Pregnancy Risk Summary Available data from published observational studies did not demonstrate an association of major malformations or other adverse pregnancy outcomes with pantoprazole. In animal reproduction studies, no evidence of adverse development outcomes was observed with pantoprazole. Reproduction studies have been performed in rats at intravenous doses up to 20 mg/kg/day (4 times the recommended human dose) and rabbits at intravenous doses up to 15 mg/kg/day (6 times the recommended human dose) with administration of pantoprazole during organogenesis in pregnant animals and have revealed no evidence of harm to the fetus due to pantoprazole in this study (see Data).
A pre-and post-natal development toxicity study in rats with additional endpoints to evaluate the effect on bone development was performed with pantoprazole sodium. Oral pantoprazole doses of 5, 15, and 30 mg/kg/day (approximately 1, 3, and 6 times the human dose of 40 mg/day) were administered to pregnant females from gestation day (GD) 6 through lactation day (LD) 21. Changes in bone morphology were observed in pups exposed to pantoprazole in utero and through milk during the period of lactation as well as by oral dosing from postnatal day (PND) 4 through PND 21 [see Use in Specific Populations (8.4)].
There were no drug-related findings in maternal animals. Advise pregnant women of the potential risk of fetal harm. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data Available data from published observational studies failed to demonstrate an association of adverse pregnancy-related outcomes and pantoprazole use.
Methodological limitations of these observational studies cannot definitely establish or exclude any drug-associated risk during pregnancy. In a prospective study by the European Network of Teratology Information Services, outcomes from a group of 53 pregnant women administered median daily doses of 40 mg pantoprazole were compared to a control group of 868 pregnant women who did not take any proton pump inhibitors (PPIs). There was no difference in the rate of major malformations between women exposed to PPIs and the control group, corresponding to a Relative Risk (RR)=0.55, [95% Confidence Interval (CI) 0.08-3.95].
In a population-based retrospective cohort study covering all live births in Denmark from 1996 to 2008, there was no significant increase in major birth defects during analysis of first trimester exposure to pantoprazole in 549 live births. A meta-analysis that compared 1,530 pregnant women exposed to PPIs in at least the first trimester with 133,410 unexposed pregnant women showed no significant increases in risk for congenital malformations or spontaneous abortion with exposure to PPIs (for major malformations OR=1.12 ([95% CI 0.86-1.45] and for spontaneous abortions OR=1.29 [95% CI 0.84-1.97]).
Animal Data Reproduction studies have been performed in rats at intravenous pantoprazole doses up to 20 mg/kg/day (4 times the recommended human dose based on body surface area) and rabbits at intravenous doses up to 15 mg/kg/day (6 times the recommended human dose based on body surface area) with administration of pantoprazole sodium during organogenesis in pregnant animals and have revealed no evidence of impaired fertility or harm to the fetus due to pantoprazole. A pre-and post-natal development toxicity study in rats with additional endpoints to evaluate the effect on bone development was performed with pantoprazole sodium.
Oral pantoprazole doses of 5, 15, and 30 mg/kg/day (approximately 1, 3, and 6 ti…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Available data from published observational studies did not demonstrate an association of major malformations or other adverse pregnancy outcomes with pantoprazole. In animal reproduction studies, no evidence of adverse development outcomes was observed with pantoprazole. Reproduction studies have been performed in rats at intravenous doses up to 20 mg/kg/day (4 times the recommended human dose) and rabbits at intravenous doses up to 15 mg/kg/day (6 times the recommended human dose) with administration of pantoprazole during organogenesis in pregnant animals and have revealed no evidence of harm to the fetus due to pantoprazole in this study (see Data).
A pre-and post-natal development toxicity study in rats with additional endpoints to evaluate the effect on bone development was performed with pantoprazole sodium. Oral pantoprazole doses of 5, 15, and 30 mg/kg/day (approximately 1, 3, and 6 times the human dose of 40 mg/day) were administered to pregnant females from gestation day (GD) 6 through lactation day (LD) 21. Changes in bone morphology were observed in pups exposed to pantoprazole in utero and through milk during the period of lactation as well as by oral dosing from postnatal day (PND) 4 through PND 21 [see Use in Specific Populations (8.4)].
There were no drug-related findings in maternal animals. Advise pregnant women of the potential risk of fetal harm. The estimated background risk of major birth defects and miscarriage for the indicated population is unknown.
All pregnancies have a background risk of birth defect, loss or other adverse outcomes. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in the clinically recognized pregnancies is 2 to 4% and 15 to 20%, respectively. Data Human Data Available data from published observational studies failed to demonstrate an association of adverse pregnancy-related outcomes and pantoprazole use.
Methodological limitations of these observational studies cannot definitely establish or exclude any drug-associated risk during pregnancy. In a prospective study by the European Network of Teratology Information Services, outcomes from a group of 53 pregnant women administered median daily doses of 40 mg pantoprazole were compared to a control group of 868 pregnant women who did not take any proton pump inhibitors (PPIs). There was no difference in the rate of major malformations between women exposed to PPIs and the control group, corresponding to a Relative Risk (RR)=0.55, [95% Confidence Interval (CI) 0.08-3.95].
In a population-based retrospective cohort study covering all live births in Denmark from 1996 to 2008, there was no significant increase in major birth defects during analysis of first trimester exposure to pantoprazole in 549 live births. A meta-analysis that compared 1,530 pregnant women exposed to PPIs in at least the first trimester with 133,410 unexposed pregnant women showed no significant increases in risk for congenital malformations or spontaneous abortion with exposure to PPIs (for major malformations OR=1.12 ([95% CI 0.86-1.45] and for spontaneous abortions OR=1.29 [95% CI 0.84-1.97]).
Animal Data Reproduction studies have been performed in rats at intravenous pantoprazole doses up to 20 mg/kg/day (4 times the recommended human dose based on body surface area) and rabbits at intravenous doses up to 15 mg/kg/day (6 times the recommended human dose based on body surface area) with administration of pantoprazole sodium during organogenesis in pregnant animals and have revealed no evidence of impaired fertility or harm to the fetus due to pantoprazole. A pre-and post-natal development toxicity study in rats with additional endpoints to evaluate the effect on bone development was performed with pantoprazole sodium.
Oral pantoprazole doses of 5, 15, and 30 mg/kg/day (approximately 1, 3, and 6 times the human dose of 40 mg/day on a body surface area basis) were administered to pregnant…
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of pantoprazole sodium for injection have not been established in pediatric patients. Animal Toxicity Data In a pre- and post-natal development toxicity study in rats, the pups were administered oral doses of pantoprazole at 5, 15, and 30 mg/kg/day on postnatal day (PND 4) through PND 21, in addition to lactational exposure through milk. On PND 21, decreased mean femur length and weight and changes in femur bone mass and geometry were observed in the offspring at 5 mg/kg/day and higher doses.
Changes in bone parameters were partially reversible following a recovery period [ see Use in Specific Populations (8.1)]. In neonatal/juvenile animals (rats and dogs) toxicities were similar to those observed in adult animals, including gastric alterations, decreases in red cell mass, increases in lipids, enzyme induction and hepatocellular hypertrophy. An increased incidence of eosinophilic chief cells in adult and neonatal/juvenile rats, and atrophy of chief cells in adult rats and in neonatal/juvenile dogs, was observed in the fundic mucosa of stomachs in repeated-dose studies.
Full to partial recovery of these effects were noted in animals of both age groups following a recovery period.
🧓 Geriatric Use ▾
8.5Geriatric Use Of 286 patients in clinical studies of intravenous pantoprazole sodium in patients with GERD and a history of EE, 86 (43%) were 65 years of age and over. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience with oral pantoprazole sodium has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🆘 Overdosage ▾
10 OVERDOSAGE Experience in patients taking very high doses of pantoprazole (greater than 240 mg) is limited. Adverse reactions seen in spontaneous reports of overdose generally reflect the known safety profile of pantoprazole. Pantoprazole is not removed by hemodialysis.
In case of overdose, treatment should be symptomatic and supportive. Single intravenous doses of pantoprazole at 378, 230, and 266 mg/kg (38, 46, and 177 times the recommended human dose based on body surface area) were lethal to mice, rats and dogs, respectively. The symptoms of acute toxicity were hypoactivity, ataxia, hunched sitting, limb-splay, lateral position, segregation, absence of ear reflex, and tremor.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Pantoprazole is a PPI that suppresses the final step in gastric acid production by covalently binding to the (H + , K + )-ATPase enzyme system at the secretory surface of the gastric parietal cell. This effect leads to inhibition of both basal and stimulated gastric acid secretion irrespective of the stimulus. The binding to the (H + , K + )-ATPase results in a duration of antisecretory effect that persists longer than 24 hours for all doses tested (20 mg to 120 mg).
12.2Pharmacodynamics Antisecretory Activity The magnitude and time course for inhibition of pentagastrin-stimulated acid output (PSAO) by single doses (20 to 120 mg) of pantoprazole sodium for injection were assessed in a single-dose, open-label, placebo-controlled, dose-response study. The results of this study are shown in Table 3. Healthy subjects received a continuous infusion for 25 hours of pentagastrin (PG) at 1 mcg/kg/h, a dose known to produce submaximal gastric acid secretion.
The placebo group showed a sustained, continuous acid output for 25 hours, validating the reliability of the testing model. Pantoprazole sodium for injection had an onset of antisecretory activity within 15 to 30 minutes of administration. Doses of 20 to 80 mg of pantoprazole sodium for injection substantially reduced the 24-hour cumulative PSAO in a dose-dependent manner, despite a short plasma elimination half-life.
Complete suppression of PSAO was achieved with 80 mg within approximately 2 hours and no further significant suppression was seen with 120 mg. The duration of action of pantoprazole sodium for injection was 24 hours. Table 3: Gastric Acid Output (mEq/hr, Mean ± SD) and Percent Inhibition a (Mean ± SD) of Pentagastrin-Stimulated Acid Output Over 24 Hours Following a Single Dose of Pantoprazole Sodium for Injection b in Healthy Subjects Treatment Dose ------2 hours------ ------4 hours------ ------12 hours------ ------24 hours------ Acid Output % Inhibition Acid Output % Inhibition Acid Output % Inhibition Acid Output % Inhibition 0 mg (Placebo, n=4) 39 ± 21 NA 26 ± 14 NA 32 ± 20 NA 38 ± 24 NA 20 mg (n=4-6) 13 ± 18 47 ± 27 6 ± 8 83 ± 21 20 ± 20 54 ± 44 30 ± 23 45 ± 43 40 mg (n=8) 5 ± 5 82 ± 11 4 ± 4 90 ± 11 11 ± 10 81 ± 13 16 ± 12 52 ± 36 80 mg (n=8) 0.1 ± 0.2 96 ± 6 0.3 ± 0.4 99 ± 1 2 ± 2 90 ± 7 7 ± 4 63 ± 18 a: Compared to individual subject baseline prior to treatment with pantoprazole sodium for injection.
NA = not applicable. b: Inhibition of gastric acid output and the percent inhibition of stimulated acid output in response to pantoprazole sodium for injection may be higher after repeated doses. In one study of gastric pH in healthy subjects, pantoprazole sodium was administered orally (40 mg enteric coated tablets) or pantoprazole sodium for injection (40 mg) once daily for 5 days and pH was measured for 24 hours following the fifth dose. The outcome measure was median percent of time that pH was ≥4 and the results were similar for intravenous and oral medications; however, the clinical significance of this parameter is unknown.
Serum Gastrin Effects Serum gastrin concentrations were assessed in two placebo-controlled studies. In a 5-day study of oral pantoprazole with 40 and 60 mg doses in healthy subjects, following the last dose on day 5, median 24-hour serum gastrin concentrations were elevated by 3- to 4-fold compared to placebo in both 40 and 60 mg dose groups. However, by 24 hours following the last dose, median serum gastrin concentrations for both groups returned to normal levels.
In another placebo-controlled, 7-day study of 40 mg intravenous or oral pantoprazole in patients with GERD and a history of EE, the mean serum gastrin concentration increased approximately 50% from baseline and as compared with placebo, but remained within the normal range. During 6 days of repeated administration of pantoprazole sodium for injection in patients with ZE Syndrome, consistent changes of serum gastrin concentratio…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Pantoprazole is a PPI that suppresses the final step in gastric acid production by covalently binding to the (H + , K + )-ATPase enzyme system at the secretory surface of the gastric parietal cell. This effect leads to inhibition of both basal and stimulated gastric acid secretion irrespective of the stimulus. The binding to the (H + , K + )-ATPase results in a duration of antisecretory effect that persists longer than 24 hours for all doses tested (20 mg to 120 mg).
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Pantoprazole sodium for injection (pantoprazole sodium) is supplied in a single-dose vial as a white to off-white lyophilised cake or powder for reconstitution containing 40 mg of pantoprazole. Pantoprazole sodium for injection is available as follows: NDC 72205-180-01 – Package of 1 carton. 1 carton contains 1 vial of pantoprazole sodium for injection equivalent to 40 mg pantoprazole.
NDC 72205-180-07 – Package of 10 cartons. Each carton contains 1 vial of pantoprazole sodium for injection equivalent to 40 mg pantoprazole. NDC 72205-180-09– Package of 25 cartons.
Each carton contains 1 vial of pantoprazole sodium for injection equivalent to 40 mg pantoprazole. Storage and Handling Store Pantoprazole sodium for injection at 20° to 25°C (68° to 77°F); excursions permitted to 15° to 30°C (59° to 86°F) [see USP Controlled Room Temperature]. Protect from light.
📋 Description ▾
11 DESCRIPTION The active ingredient in pantoprazole sodium for injection (pantoprazole sodium), a PPI, is a substituted benzimidazole, sodium 5-(difluoromethoxy)-2-[[(3,4-dimethoxy-2-pyridinyl)methyl] sulfinyl]-1 H -benzimidazole, a compound that inhibits gastric acid secretion. Its empirical formula is C 16 H 14 F 2 N 3 NaO 4 S, with a molecular weight of 405.4. The structural formula is: Pantoprazole sodium USP is a white to off-white powder and is racemic.
Pantoprazole has weakly basic and acidic properties. Pantoprazole sodium is freely soluble in water, in methanol, and in dehydrated alcohol, practically insoluble in hexane and in dichloromethane. The stability of the compound in aqueous solution is pH-dependent.
The rate of degradation increases with decreasing pH. The reconstituted solution of pantoprazole sodium for injection is in the pH range 9.0 to 10.5. Pantoprazole sodium for injection is supplied for intravenous administration as a sterile, lyophilised cake or powder in a single-dose clear glass vial fitted with a rubber stopper and crimp seal.
Each vial contains 40 mg pantoprazole (equivalent to 45.1 mg of pantoprazole sodium USP), edetate disodium (1 mg), and sodium hydroxide to adjust pH. pantoprazole -str
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Adverse Reactions Advise patients to report to their healthcare provider if they experience any signs or symptoms consistent with: • Injection Site Reactions [see Warnings and Precautions (5.2) ] • Potential for Exacerbation of Zinc Deficiency [see Warnings and Precautions (5.3) ] • Acute Tubulointerstitial Nephritis [see Contraindications (4) , Warnings and Precautions (5.4) ] • Clostridium difficile-Associated Diarrhea [see Warnings and Precautions (5.5) ] • Bone Fracture [see Warnings and Precautions (5.6) ] • Severe Cutaneous Adverse Reactions [see Warnings and Precautions (5.7) ] • Cutaneous and Systemic Lupus Erythematosus [see Warnings and Precautions (5.8)] • Hepatic Effects [see Warnings and Precautions (5.9)] • Hypomagnesemia and Mineral Metabolism [see Warnings and Precautions (5.10)] Drug Interactions Instruct patients to inform their healthcare provider of any other medications they are currently taking, including rilpivirine-containing products [Contraindications (4)] and high dose methotrexate [Warnings and Precautions (5.14)].
Pregnancy Advise a pregnant woman of the potential risk to a fetus. Advise females of reproductive potential to inform their healthcare provider of a known or suspected pregnancy [see Use in Specific Populations (8.1)]. Manufactured by: MSN Laboratories Private Limited Telangana – 509 228, INDIA Distributed by: Novadoz Pharmaceuticals LLC Piscataway, NJ 08854-3714 Issued on: 03/2022