
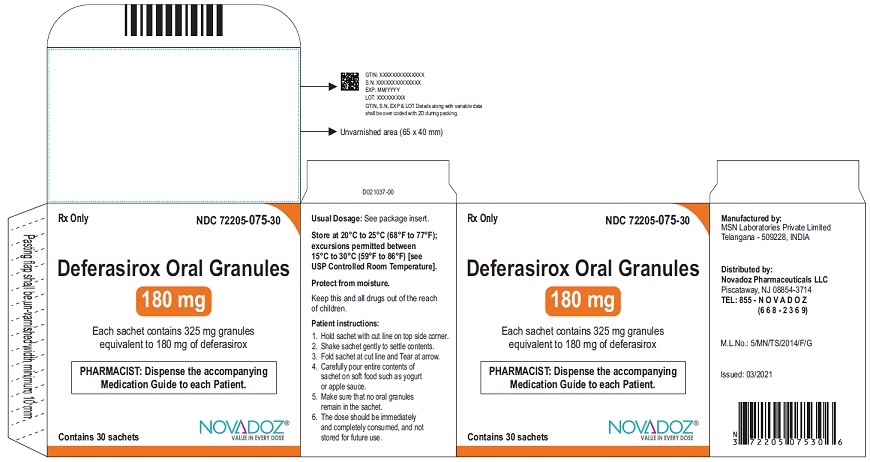
Deferasorox Deferasirox 90 mg Granule, 30-count
Other active recalls for Deferasirox (different manufacturers) — 1 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Iron Chelator class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
Deferasirox is used to treat adults and children 2 years of age and older who have too much iron in their body because they received many blood transfusions. It is also used to treat adults and children 10 years of age and older who have too much iron in their body because of a genetic blood disorder called non–transfusion-dependent thalassemia (NTDT). Deferasirox is in a class of medications called iron chelators. It works by attaching to iron in the body so that it can be excreted (removed from the body) in feces.
Read the full MedlinePlus article ↗- Deferasirox is an iron chelator — think of it like a molecular magnet that grabs onto excess iron in your body and carries it out, mostly through your stool. When you get lots of b...
- What exactly is deferasirox doing in my body?
- It depends on which product you have. Jadenu tablets can be taken with water or a light meal — that's fine. But a high-fat meal (think a full cheeseburger and fries) increases how...
- Nausea, vomiting, diarrhea, stomach pain, and a mild skin rash are common and often manageable — mild rashes sometimes go away on their own without changing the dose. But call your...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Deferasirox — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII D5340Y2I9G
Castor oil is a natural plant-based oil used in medicines as a lubricant, laxative agent, and solvent. It helps medicine ingredients dissolve or flow smoothly and can aid bowel movement in formulations designed for that purpose.
-
UNII OP1R32D61U
Microcrystalline cellulose is a purified form of cellulose, a natural fiber from plant sources. It acts as a binder and filler in tablets and capsules, helping hold ingredients together and give the medicine its shape and size.
-
UNII M28OL1HH48
Croscarmellose sodium is a plant-based substance derived from cellulose. It acts as a disintegrant, helping tablets and capsules break down quickly in the digestive system so the medicine can be absorbed.
-
UNII 2165RE0K14
A plant-based thickener made from cellulose that helps control how quickly the medicine dissolves and releases its active ingredient. It also binds ingredients together and improves the tablet's texture and handling during manufacturing.
-
UNII EWQ57Q8I5X
Lactose monohydrate is a natural sugar derived from milk. It serves as a filler and binder in tablets and capsules, helping create the proper size, texture, and consistency of the medicine.
-
UNII LQA7B6G8JG
A synthetic polymer made by combining water-soluble compounds. It acts as a surfactant and solubilizer to help mix oil and water-based ingredients, improving the medicine's texture and how active ingredients dissolve.
-
UNII U725QWY32X
Povidone K30 is a synthetic polymer made from petroleum. It acts as a binder to hold tablet ingredients together and as a disintegrant to help the tablet break apart in the stomach so the medicine can be absorbed.
-
UNII ETJ7Z6XBU4
Silicon dioxide is a naturally occurring mineral used as a glidant and anti-caking agent. It helps powder ingredients flow smoothly and prevents clumping during manufacturing and storage.
-
UNII 7CV7WJK4UI
Sodium stearyl fumarate is a synthetic compound made from stearyl alcohol and fumaric acid. It acts as a lubricant and glidant in tablets and capsules, helping ingredients flow smoothly during manufacturing and preventing sticking.
9 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $16.16 | — |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Jadenu 90 mg 00078-0727-15 | Novartis | 30 granules | — | AB | FDA listed | — |
| Deferasirox 90 mg 31722-0029-32 | Camber | 30 granules | — | AB | FDA listed | — |
| Deferasirox Oral Granules 90 mg 42806-0371-30 | EPIC | 30 granules | — | AB | FDA listed | — |
| Deferasirox 90 mg 59651-0447-30 | Aurobindo | 30 granules | — | AB | FDA listed | — |
| Deferasirox oral 90 mg 67877-0675-84 | Ascend | 30 granules | — | AB | FDA listed | — |
| Deferasirox 90 mg 69097-0550-53 | Cipla | 30 granules | — | AB | FDA listed | — |
| Deferasorox 90 mgthis 72205-0176-30 | Novadoz | 30 granules | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 72205-0176-30 You're viewing this | 30 PACKET in 1 CARTON (72205-176-30) / 1 GRANULE in 1 PACKET (72205-176-61) | 2022-05-21 | Active |
🧭 About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |
Questions about this listing
Why is there no price listed?
Is the NDC printed on the package the same as the 11-digit billing NDC?
What do the three segments of this NDC mean?
Is this package still being marketed?
Who lists this product with the FDA?
Do I need a prescription for this product?
Where does this data come from?
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: RENAL FAILURE, HEPATIC FAILURE, and GASTROINTESTINAL HEMORRHAGE Renal Failure Deferasirox can cause acute renal failure and death, particularly in patients with comorbidities and those who are in the advanced stages of their hematologic disorders. Evaluate baseline renal function prior to starting or increasing deferasirox dosing in all patients. Deferasirox is contraindicated in adult and pediatric patients with eGFR less than 40 mL/min/1.73 m 2 .
Measure serum creatinine in duplicate prior to initiation of therapy. Monitor renal function at least monthly. For patients with baseline renal impairment or increased risk of acute renal failure, monitor renal function weekly for the first month, then at least monthly.
Reduce the starting dose in patients with preexisting renal disease. During therapy, increase the frequency of monitoring and modify the dose for patients with an increased risk of renal impairment, including use of concomitant nephrotoxic drugs, and pediatric patients with volume depletion or overchelation [see Dosage and Administration (2.1 , 2.4, 2.5 ), Warnings and Precautions (5.1), Adverse Reactions (6.1 , 6.2) ] . Hepatic Failure Deferasirox can cause hepatic injury including hepatic failure and death.
Measure serum transaminases and bilirubin in all patients prior to initiating treatment, every 2 weeks during the first month, and at least monthly thereafter. Avoid use of deferasirox in patients with severe (Child-Pugh C) hepatic impairment and reduce the dose in patients with moderate (Child-Pugh B) hepatic impairment [see Dosage and Administration (2.4) , Warnings and Precautions (5.2) ] . Gastrointestinal Hemorrhage Deferasirox can cause gastrointestinal (GI) hemorrhages, which may be fatal, especially in elderly patients who have advanced hematologic malignancies and/or low platelet counts.
Monitor patients and discontinue deferasirox for suspected GI ulceration or hemorrhage [ see Warnings and Precautions (5.3) ]. WARNING: RENAL FAILURE, HEPATIC FAILURE, and GASTROINTESTINAL HEMORRHAGE See full prescribing information for complete boxed warning. Deferasirox may cause serious and fatal: acute kidney injury, including acute renal failure requiring dialysis and renal tubular toxicity including Fanconi syndrome (5.1) hepatic toxicity, including failure (5.2) gastrointestinal hemorrhage (5.3) Deferasirox therapy requires close patient monitoring, including laboratory tests of renal and hepatic function.
(5)
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE Deferasirox oral granules are an iron chelator indicated for the treatment of chronic iron overload due to blood transfusions in patients 2 years of age and older. ( 1.1 ) Deferasirox oral granules are indicated for the treatment of chronic iron overload in patients 10 years of age and older with non-transfusion-dependent thalassemia (NTDT) syndromes, and with a liver iron (Fe) concentration (LIC) of at least 5 mg Fe per gram of dry weight (Fe/g dw) and a serum ferritin greater than 300 mcg/L.
( 1.2 ) Limitations of Use: The safety and efficacy of deferasirox oral granules when administered with other iron chelation therapy have not been established. ( 1.3 )
1.1Treatment of Chronic Iron Overload Due to Blood Transfusions (Transfusional Iron Overload) Deferasirox oral granules are indicated for the treatment of chronic iron overload due to blood transfusions (transfusional hemosiderosis) in patients 2 years of age and older
1.2Treatment of Chronic Iron Overload in Non-Transfusion-Dependent Thalassemia Syndromes Deferasirox oral granules are indicated for the treatment of chronic iron overload in patients 10 years of age and older with non-transfusion dependent thalassemia (NTDT) syndromes and with a liver iron concentration (LIC) of at least 5 milligrams of iron per gram of liver dry weight (mg Fe/g dw) and a serum ferritin greater than 300 mcg/L.
1.3Limitations of Use The safety and efficacy of deferasirox oral granules when administered with other iron chelation therapy have not been established.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Transfusional Iron Overload: Initial dose for patients with estimated glomerular filtration rate (eGFR) greater than 60 mL/min/1.73 m 2 is 14 mg per kg (calculated to nearest whole sachet content for granules) once daily. ( 2.1 ) NTDT Syndromes: Initial dose for patients with eGFR greater than 60 mL/min/1.73 m 2 is 7 mg per kg (calculated to nearest whole sachet content for granules) once daily. (2.2) See full prescribing information for information regarding monitoring, administration, and dose-reductions for organ impairment.
(2.1 , 2.2 , 2.3 , 2.4)
2.1Transfusional Iron Overload Deferasirox oral granules therapy should only be considered when a patient has evidence of chronic transfusional iron overload. The evidence should include the transfusion of at least 100 mL/kg of packed red blood cells (e.g., at least 20 units of packed red blood cells for a 40 kg person or more in individuals weighing more than 40 kg), and a serum ferritin consistently greater than 1,000 mcg/L. Prior to starting therapy, or increasing dose, evaluate: Serum ferritin level Baseline renal function: Obtain serum creatinine in duplicate (due to variations in measurements).
Calculate the estimated glomerular filtration rate (eGFR). Use a prediction equation appropriate for adult patients (e.g., CKD-EPI, MDRD method) and in pediatric patients (e.g., Schwartz equations). Obtain urinalyses and serum electrolytes to evaluate renal tubular function [see Dosage and Administration (2.4) , Warnings and Precautions (5.1) ] .
Serum transaminases and bilirubin [see Dosage and Administration (2.4) , Warnings and Precautions (5.2) ] Baseline auditory and ophthalmic examinations [see Warnings and Precautions (5.10) ] Initiating Therapy: The recommended initial dose of deferasirox oral granules for patients 2 years of age and older with eGFR greater than 60 mL/min/1.73 m 2 is 14 mg per kg body weight orally, once daily. Calculate doses (mg per kg per day) to the nearest whole sachet content for granules. Changes in weight of pediatric patients over time must be taken into account when calculating the dose.
During Therapy: Monitor serum ferritin monthly and adjust the dose of deferasirox oral granules, if necessary, every 3 to 6 months based on serum ferritin trends. Use the minimum effective dose to achieve a trend of decreasing ferritin Make dose adjustments in steps of 3.5 or 7 mg per kg and tailor adjustments to the individual patient’s response and therapeutic goals. In patients not adequately controlled with doses of 21 mg per kg (e.g., serum ferritin levels persistently above 2,500 mcg/L and not showing a decreasing trend over time), doses of up to 28 mg per kg may be considered.
Doses above 28 mg per kg are not recommended [see Warnings and Precautions (5.6) ]. Adjust dose based on serum ferritin levels If the serum ferritin falls below 1,000 mcg/L at 2 consecutive visits, consider dose reduction especially if the deferasirox oral granules dose is greater than 17.5 mg/kg/day [see Adverse Reactions (6.1) ]. If the serum ferritin falls below 500 mcg/L, interrupt deferasirox oral granules therapy to minimize the risk of overchelation, and continue monthly monitoring [ see Warnings and Precautions (5.6)].
Evaluate the need for ongoing chelation therapy for patients whose conditions no longer require regular blood transfusions. Use the minimum effective dose to maintain iron burden in the target range [see Warnings and Precautions (5.6) ]. Monitor blood counts, liver function, renal function and ferritin monthly [see Warnings and Precautions (5.1 , 5.2 , 5.4) ] .
Interrupt deferasirox oral granules for pediatric patients who have acute illnesses, which can cause volume depletion, such as vomiting, diarrhea, or prolonged decreased oral intake, and monitor more frequently. Resume therapy as appropriate, based on assessments of renal function, when oral intake and volume status are normal [see Dosage and Administration (2.4 , 2.5), Warnings…
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS 90 mg deferasirox oral granules Supplied in cartons containing 30 child resistant foil sachets. Each sachet contains 162.5 mg of white to almost white granules, equivalent to 90 mg deferasirox. 180 mg deferasirox oral granules Supplied in cartons containing 30 child resistant foil sachets.
Each sachet contains 325 mg of white to almost white granules, equivalent to 180 mg deferasirox. 360 mg deferasirox oral granules Supplied in cartons containing 30 child resistant foil sachets. Each sachet contains 650 mg of white to almost white granules, equivalent to 360 mg deferasirox.
Granules: 90 mg, 180 mg, 360 mg. (3)
⛔ Contraindications ▾
4 CONTRAINDICATIONS Deferasirox is contraindicated in patients with: Estimated GFR less than 40 mL/min/1.73 m 2 [see Dosage and Administration (2.5) , Warnings and Precautions (5.1) ] ; Poor performance status [see Warnings and Precautions (5.1 , 5.3)] ; High-risk myelodysplastic syndromes (this patient population was not studied and is not expected to benefit from chelation therapy) ; Advanced malignancies [see Warnings and Precautions (5.1 , 5.3) ] ; Platelet counts less than 50 x 10 9 /L [see Warnings and Precautions (5.3 , 5.4) ] ; Known hypersensitivity to deferasirox or any component of deferasirox [see Warnings and Precautions (5.7) , Adverse Reactions (6.2) ] .
Estimated GFR less than 40 mL/min/1.73 m 2 . ( 4) Patients with poor performance status. (4) Patients with high-risk myelodysplastic syndrome (MDS).
(4) Patients with advanced malignancies. (4) Patients with platelet counts less than 50 x 10 9 /L. (4) Known hypersensitivity to deferasirox or any component of deferasirox.
(4)
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Acute Kidney Injury: Measure serum creatinine in duplicate before starting therapy. Monitor renal function during deferasirox therapy and reduce dose or interrupt therapy for toxicity. ( 2.1 , 2.4, 5.1 ) Hepatic Toxicity: Monitor hepatic function.
Reduce dose or interrupt therapy for toxicity. ( 5.2 ) Fatal and Nonfatal Gastrointestinal (GI) Bleeding, Ulceration, and Irritation: Risk may be greater in patients who are taking deferasirox in combination with drugs that have known ulcerogenic or hemorrhagic potential. ( 5.3 ) Bone Marrow Suppression: Neutropenia, agranulocytosis, worsening anemia, and thrombocytopenia, including fatal events; monitor blood counts during deferasirox therapy.
Interrupt therapy for toxicity. ( 5.4 ) Age-related Risk of Toxicity: Monitor elderly and pediatric patients closely for toxicity. ( 5.5 ) Hypersensitivity Reactions: Discontinue deferasirox for severe reactions and institute medical intervention.
( 5.7 ) Severe Skin Reactions including Stevens-Johnson syndrome (SJS), toxic epidermal necrolysis (TEN), and drug reaction with eosinophilia and systemic symptoms (DRESS): Discontinue deferasirox. ( 5.8 )
5.1Acute Kidney Injury, Including Acute Renal Failure Requiring Dialysis and Renal Tubular Toxicity Including Fanconi Syndrome Deferasirox is contraindicated in patients with eGFR less than 40 mL/min/1.73 m 2 . Exercise caution in pediatric patients with eGFR between 40 and 60 mL/min/1.73 m 2 . If treatment is needed, use the minimum effective dose and monitor renal function frequently.
Individualize dose titration based on improvement in renal injury [see Use in Specific Populations (8.6)] . For patients with renal impairment (eGFR 40 to 60 mL/min/1.73 m 2 ) reduce the starting dose by 50% [see Dosage and Administration (2.4 , 2.5), Use in Specific Populations (8.6) ] . Deferasirox can cause acute kidney injury including renal failure requiring dialysis that has resulted in fatal outcomes.
Based on postmarketing experience, most fatalities have occurred in patients with multiple comorbidities and who were in advanced stages of their hematological disorders. In the clinical trials, adults and pediatric deferasirox-treated patients with no preexisting renal disease experienced dose-dependent mild, non-progressive increases in serum creatinine and proteinuria. Preexisting renal disease and concomitant use of other nephrotoxic drugs may increase the risk of acute kidney injury in adult and pediatric patients.
Acute illnesses associated with volume depletion and overchelation may increase the risk of acute kidney injury in pediatric patients. In pediatric patients, small decreases in eGFR can result in increases in deferasirox exposure, particularly in younger patients with body surface area typical of patients less than age 7 years. This can lead to a cycle of worsening renal function and further increases in deferasirox tablets for oral suspension exposure, unless the dose is reduced or interrupted.
Renal tubular toxicity, including acquired Fanconi syndrome, has been reported in patients treated with deferasirox, most commonly in pediatric patients with beta-thalassemia and serum ferritin levels less than 1,500 mcg/L [see Warnings and Precautions (5.6) , Adverse Reactions (6.1, 6.2) , Use in Specific Populations (8.4) , Clinical Pharmacology (12.3) ] . Evaluate renal glomerular and tubular function before initiating therapy or increasing the dose. Use prediction equations validated for use in adult and pediatric patients to estimate GFR.
Obtain serum electrolytes and urinalysis in all patients to evaluate renal tubular function [see Dosage and Administration (2.1, 2.2) ] . Monitor all patients for changes in eGFR and for renal tubular toxicity weekly during the first month after initiation or modification of therapy and at least monthly thereafter. Dose reduction or interruption may be considered if abnormalities occur in levels of markers of renal tubular function and/or…
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following clinically significant adverse reactions are also discussed in other sections of the labeling: Acute Kidney Injury, Including Acute Renal Failure Requiring Dialysis, and Renal Tubular Toxicity Including Fanconi Syndrome [see Warnings and Precautions (5.1,5.6) ] Hepatic Toxicity and Failure [see Warnings and Precautions (5.2,5.6) ] GI Hemorrhage [see Warnings and Precautions (5.3) ] Bone Marrow Suppression [see Warnings and Precautions (5.4) ] Hypersensitivity [see Warnings and Precautions (5.7) ] Severe Skin Reactions [see Warnings and Precautions (5.8) ] Skin Rash [see Warnings and Precautions (5.9) ] Auditory and Ocular Abnormalities [see Warnings and Precautions (5.10) ] In patients with transfusional iron overload, the most frequently occurring (greater than 5%) adverse reactions are diarrhea, vomiting, nausea, abdominal pain, skin rashes, and increases in serum creatinine.
In deferasirox-treated patients with NTDT syndromes, the most frequently occurring (greater than 5%) adverse reactions are diarrhea, rash, and nausea. (6.1) To report SUSPECTED ADVERSE REACTIONS, contact Novadoz Pharmaceuticals LLC at 1-855-668-2369 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Deferasirox was evaluated in healthy volunteer trials. Currently, there are no clinical data in patients with deferasirox oral granules.
Deferasirox contains the same active ingredient as deferasirox tablets for oral suspension. The following adverse reactions have been reported with deferasirox tablets for oral suspension. Transfusional Iron Overload A total of 700 adult and pediatric patients were treated with deferasirox for 48 weeks in premarketing studies.
These included 469 patients with beta-thalassemia, 99 with rare anemias, and 132 with sickle cell disease. Of these patients, 45% were male, 70% were Caucasian, and 292 patients were less than 16 years of age. In the sickle cell disease population, 89% of patients were black.
Median treatment duration among the sickle cell patients was 51 weeks. Of the 700 patients treated, 469 (403 beta-thalassemia and 66 rare anemias) were entered into extensions of the original clinical protocols. In ongoing extension studies, median durations of treatment were 88 to 205 weeks.
Six hundred twenty-seven (627) patients with myelodysplastic syndrome (MDS) were enrolled across 5 uncontrolled trials. These studies varied in duration from 1 to 5 years. The discontinuation rate across studies in the first year was 46% (Adverse Events (AEs) 20%, withdrawal of consent 10%, death 8%, other 4%, lab abnormalities 3%, and lack of efficacy 1%).
Among 47 patients enrolled in the study of 5-year duration, 10 remained on deferasirox at the completion of the study. Table 1 displays adverse reactions occurring in greater than 5% of deferasirox-treated beta-thalassemia patients (Study 1), sickle cell disease patients (Study 3), and patients with MDS (MDS pool). Abdominal pain, nausea, vomiting, diarrhea, skin rashes, and increases in serum creatinine were the most frequent adverse reactions reported with a suspected relationship to deferasirox.
Gastrointestinal symptoms, increases in serum creatinine, and skin rash were dose related. Table 1. Adverse Reactions a Occurring in >5% of Deferasirox-treated Patients in Study 1, Study 3, and MDS Pool Study 1 (Beta-thalassemia) Study 3 (Sickle Cell Disease) MDS Pool Adverse Reactions Deferasirox N=296 n(%) Deferoxamine N=290 n(%) Deferasirox N=132 n(%) Deferoxamine N=63 n(%) Deferasirox N=627 n(%) Abdominal Pain b 63 (21) 41 (14) 37 (28) 9 (14) 145 (23) Diarrhea 35 (12) 21 (7) 26 (20) 3 (5) 297 (47) Creatinine Increased c 33 (11) 0 (0) 9 (7) 0 89 (14) Nausea 31 (11) 14…
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Do not take deferasirox with aluminum-containing antacid preparations. ( 7.1 ) Deferasirox increases the exposure of repaglinide. Consider repaglinide dose reduction and monitor blood glucose levels.
( 7.3 ) Avoid the use of deferasirox with theophylline as theophylline levels could be increased. ( 7.4 ) Deferasirox increases exposure of busulfan. Monitor plasma concentrations of busulfan when coadministered with deferasirox to allow dose adjustment of busulfan, as needed.
( 7.7 )
7.1Aluminum-Containing Antacid Preparations The concomitant administration of deferasirox and aluminum-containing antacid preparations has not been formally studied. Although deferasirox has a lower affinity for aluminum than for iron, do not take deferasirox with aluminum-containing antacid preparations.
7.2Agents Metabolized by CYP3A4 Deferasirox may induce CYP3A4 resulting in a decrease in CYP3A4 substrate concentration when these drugs are coadministered. Closely monitor patients for signs of reduced effectiveness when deferasirox is administered with drugs metabolized by CYP3A4 (e.g., alfentanil, aprepitant, budesonide, buspirone, conivaptan, cyclosporine, darifenacin, darunavir, dasatinib, dihydroergotamine, dronedarone, eletriptan, eplerenone, ergotamine, everolimus, felodipine, fentanyl, hormonal contraceptive agents, indinavir, fluticasone, lopinavir, lovastatin, lurasidone, maraviroc, midazolam, nisoldipine, pimozide, quetiapine, quinidine, saquinavir, sildenafil, simvastatin, sirolimus, tacrolimus, tolvaptan, tipranavir, triazolam, ticagrelor, and vardenafil) [see Clinical Pharmacology (12.3) ].
7.3Agents Metabolized by CYP2C8 Deferasirox inhibits CYP2C8 resulting in an increase in CYP2C8 substrate (e.g., repaglinide and paclitaxel) concentration when these drugs are coadministered. If deferasirox and repaglinide are used concomitantly, consider decreasing the dose of repaglinide and perform careful monitoring of blood glucose levels. Closely monitor patients for signs of exposure related toxicity when deferasirox is coadministered with other CYP2C8 substrates [see Clinical Pharmacology (12.3) ] .
7.4Agents Metabolized by CYP1A2 Deferasirox inhibits CYP1A2 resulting in an increase in CYP1A2 substrate (e.g., alosetron, caffeine, duloxetine, melatonin, ramelteon, tacrine, theophylline, tizanidine) concentration when these drugs are coadministered. An increase in theophylline plasma concentrations could lead to clinically significant theophylline induced CNS or other adverse reactions. Avoid the concomitant use of theophylline or other CYP1A2 substrates with a narrow therapeutic index (e.g., tizanidine) with deferasirox.
Monitor theophylline concentrations and consider theophylline dose modification if you must coadminister theophylline with deferasirox. Closely monitor patients for signs of exposure related toxicity when deferasirox is coadministered with other drugs metabolized by CYP1A2 [see Clinical Pharmacology (12.3) ] .
7.5Agents Inducing UDP-glucuronosyltransferase (UGT) Metabolism Deferasirox is a substrate of UGT1A1 and to a lesser extent UGT1A3. The concomitant use of deferasirox with strong UGT inducers (e.g., rifampicin, phenytoin, phenobarbital, ritonavir) may result in a decrease in deferasirox efficacy due to a possible decrease in deferasirox concentration. Avoid the concomitant use of strong UGT inducers with deferasirox.
Consider increasing the initial dose of deferasirox if you must coadminister these agents together [see Dosage and Administration (2.5) , Clinical Pharmacology (12.3) ] .
7.6Bile Acid Sequestrants Avoid the concomitant use of bile acid sequestrants (e.g., cholestyramine, colesevelam, colestipol) with deferasirox due to a possible decrease in deferasirox concentration. If you must coadminister these agents together, consider increasing the initial dose of deferasirox [see Dosage and Administration (2.5) , Clinical Pharmacology (12.3) ] .
7.7 Busulfan Increased exposure of busulfan w…
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS Lactation: Advise women not to breastfeed. ( 8.2 )
8.1Pregnancy Risk Summary There are no studies with the use of deferasirox in pregnant women to inform drug-associated risks. Administration of deferasirox to rats during pregnancy resulted in decreased offspring viability and an increase in renal anomalies in male offspring at doses that were about or less than the recommended human dose on a mg/m 2 basis. No fetal effects were noted in pregnant rabbits at doses equivalent to the human recommended dose on an mg/m 2 basis.
Deferasirox should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies had a background risk of birth defect, loss, or other adverse outcomes.
However, the background risk in the U.S. general population of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data In embryo-fetal developmental studies, pregnant rats and rabbits received oral deferasirox during the period of organogenesis at doses up to 100 mg/kg/day in rats and 50 mg/kg/day in rabbits (1.2 times the maximum recommended human dose (MRHD) on an mg/m 2 basis). These doses resulted in maternal toxicity but no fetal harm was observed.
In a prenatal and postnatal developmental study, pregnant rats received oral deferasirox daily from organogenesis through lactation day 20 at doses of 10, 30, and 90 mg/kg/day (0.1, 0.3, and 1.0 times the MRHD on a mg/m 2 basis). Maternal toxicity, loss of litters, and decreased offspring viability occurred at 90 mg/kg/day (1.0 times the MRHD on a mg/m 2 basis), and increases in renal anomalies in male offspring occurred at 30 mg/kg/day (0.3 times the MRHD on a mg/m 2 basis).
8.2Lactation Risk Summary No data are available regarding the presence of deferasirox or its metabolites in human milk, the effects of the drug on the breastfed child, or the effects of the drug on milk production. Deferasirox and its metabolites were excreted in rat milk. Because many drugs are excreted in human milk and because of the potential for serious adverse reactions in a breastfeeding child from deferasirox and its metabolites, a decision should be made whether to discontinue breastfeeding or to discontinue the drug, taking into account the importance of the drug to the mother.
8.3Females and Males of Reproductive Potential Contraception Counsel patients to use non-hormonal method(s) of contraception since deferasirox can render hormonal contraceptives ineffective [see Drug Interactions (7.2) ] .
8.4Pediatric Use Transfusional Iron Overload The safety and effectiveness of deferasirox have been established in pediatric patients 2 years of age and older for the treatment of transfusional iron overload [see Dosage and Administration (2.1) ]. Safety and effectiveness have not been established in pediatric patients less than 2 years of age for the treatment of transfusional iron overload. Pediatric approval for treatment of transfusional iron overload was based on clinical studies of 292 pediatric patients 2 years to less than 16 years of age with various congenital and acquired anemias.
Seventy percent of these patients had beta-thalassemia [see Indications and Usage (1) , Dosage and Administration (2.1 ), Clinical Studies (14) ]. In those clinical studies, 173 children (ages 2 to < 12 years) and 119 adolescents (ages 12 to < 17 years) were exposed to deferasirox. Iron Overload in Non-Transfusion-Dependent Thalassemia Syndromes The safety and effectiveness of deferasirox have been established in patients 10 years of age and older for the treatment of chronic iron overload with non-transfusion-dependent thalassemia (NTDT) syndromes [see Dosage and Administration (2.2) ].
Safety and effectiveness have not been established in patients less than 10 years of age with chronic iron overload in…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are no studies with the use of deferasirox in pregnant women to inform drug-associated risks. Administration of deferasirox to rats during pregnancy resulted in decreased offspring viability and an increase in renal anomalies in male offspring at doses that were about or less than the recommended human dose on a mg/m 2 basis. No fetal effects were noted in pregnant rabbits at doses equivalent to the human recommended dose on an mg/m 2 basis.
Deferasirox should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus. The background risk of major birth defects and miscarriage for the indicated population is unknown. All pregnancies had a background risk of birth defect, loss, or other adverse outcomes.
However, the background risk in the U.S. general population of major birth defects is 2% to 4% and of miscarriage is 15% to 20% of clinically recognized pregnancies. Data Animal Data In embryo-fetal developmental studies, pregnant rats and rabbits received oral deferasirox during the period of organogenesis at doses up to 100 mg/kg/day in rats and 50 mg/kg/day in rabbits (1.2 times the maximum recommended human dose (MRHD) on an mg/m 2 basis). These doses resulted in maternal toxicity but no fetal harm was observed.
In a prenatal and postnatal developmental study, pregnant rats received oral deferasirox daily from organogenesis through lactation day 20 at doses of 10, 30, and 90 mg/kg/day (0.1, 0.3, and 1.0 times the MRHD on a mg/m 2 basis). Maternal toxicity, loss of litters, and decreased offspring viability occurred at 90 mg/kg/day (1.0 times the MRHD on a mg/m 2 basis), and increases in renal anomalies in male offspring occurred at 30 mg/kg/day (0.3 times the MRHD on a mg/m 2 basis).
🆘 Overdosage ▾
10 OVERDOSAGE Cases of overdose (2 to 3 times the prescribed dose for several weeks) have been reported. In one case, this resulted in hepatitis which resolved without long-term consequences after a dose interruption. In one pediatric case, a dose of 2-3 times the prescribed dose for 6 days resulted in acute renal failure requiring hemofiltration and acute liver injury/failure, which were reversible with intensive care support.
Single doses of deferasirox up to 80 mg per kg per day with the tablet for oral suspension formulation in iron-overloaded beta-thalassemic patients have been tolerated with nausea and diarrhea noted. In healthy subjects, single doses of up to 40 mg per kg per day with the tablet for oral suspension formulation were tolerated. Early signs of acute overdose are digestive effects such as abdominal pain, diarrhea, nausea, and vomiting.
Hepatic and renal disorders have been reported, including cases of liver enzyme and creatinine increased with recovery after treatment discontinuation. An erroneously administered single dose of 90 mg/kg led to Fanconi syndrome which resolved after treatment. There is no specific antidote for deferasirox.
In case of overdose, it may be treated with induction of vomiting or gastric lavage, and by symptomatic treatment.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Deferasirox is an orally active chelator that is selective for iron (as Fe 3+ ). It is a tridentate ligand that binds iron with high affinity in a 2:1 ratio. Although deferasirox has very low affinity for zinc and copper, there are variable decreases in the serum concentration of these trace metals after the administration of deferasirox. The clinical significance of these decreases is uncertain.
12.2Pharmacodynamics Pharmacodynamic effects tested in an iron balance metabolic study with the tablet for oral suspension formulation showed that deferasirox (10, 20, and 40 mg per kg per day) was able to induce a mean net iron excretion (0.119, 0.329, and 0.445 mg Fe/kg body weight per day, respectively) within the clinically relevant range (0.1 to 0.5 mg per kg per day). Iron excretion was predominantly fecal. An analysis of pooled pediatric clinical trial data found a statistically significant relationship between exposure and the probability of renal toxicity (increase in serum creatinine and urinary protein), resulting in a decrease in renal function.
Decreases in renal function resulted in an increase in deferasirox exposure which may increase the probability of renal toxicity. Cardiac Electrophysiology At the maximum approved recommended dose, deferasirox does not prolong the QT interval to any clinically relevant extent.
12.3Pharmacokinetics Absorption Based on studies in patients with the tablet for oral suspension, deferasirox is absorbed following oral administration with median times to maximum plasma concentration (T max ) of about 1.5 to 4 hours. In healthy subjects, deferasirox showed comparable T max . The maximal concentrations (C max ) and area under the curve (AUC 0-24h , AUC τ ) of deferasirox increase approximately linearly with dose after both single administration and under steady-state conditions.
Exposure to deferasirox increased by an accumulation factor of 1.3 to 2.3 after multiple doses with the tablet for oral suspension formulation. Granules The bioavailability (as measured by AUC inf ) of deferasirox oral granules was 52% greater than with deferasirox tablets for oral suspension. After strength-adjustment, the mean AUC inf of the deferasirox oral granules (i.e., 4 x 90 mg strength) was similar to that of deferasirox tablets for oral suspension (i.e., 500 mg strength) under fasting conditions; however, the mean C max was increased by 34%.
The 34% increase in C max observed with deferasirox oral granules is not clinically meaningful. The administration of deferasirox oral granules with a soft meal (e.g., yogurt and applesauce) or with a low- fat (approximately 450 calories with fat content approximately 30% of total calories) indicated that the AUC inf and C max after a low-fat meal or soft foods were similar to that under fasting conditions. The administration of deferasirox oral granules with a high-fat meal (approximately 1,000 calories with fat content greater than 50% of total calories) increased AUC inf by 18% with no changes in C max compared to that under fasting conditions [see Dosage and Administration (2.3) ] .
Distribution Deferasirox is highly (~99%) protein bound almost exclusively to serum albumin. The percentage of deferasirox confined to the blood cells was 5% in humans. The volume of distribution at steady state (V ss ) of deferasirox is 14.
37 ±
2.69L in adults. Metabolism Glucuronidation is the main metabolic pathway for deferasirox, with subsequent biliary excretion. Deconjugation of glucuronidates in the intestine and subsequent reabsorption (enterohepatic recycling) is likely to occur.
Deferasirox is mainly glucuronidated by UGT1A1 and to a lesser extent UGT1A3. CYP450-catalyzed (oxidative) metabolism of deferasirox appears to be minor in humans (about 8%). Deconjugation of glucuronide metabolites in the intestine and subsequent reabsorption (enterohepatic recycling) was confirmed in a healthy subjects study in which the administr…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Deferasirox is an orally active chelator that is selective for iron (as Fe 3+ ). It is a tridentate ligand that binds iron with high affinity in a 2:1 ratio. Although deferasirox has very low affinity for zinc and copper, there are variable decreases in the serum concentration of these trace metals after the administration of deferasirox. The clinical significance of these decreases is uncertain.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING Deferasirox oral granules 90 mg are white to almost white granules in sachet. They are available in cartons of 30 sachets………………………………………………..(NDC 72205-176-30). Deferasirox oral granules 180 mg are white to almost white granules in sachet.They are available in cartons of 30 sachets………………………………………………..(NDC 72205-075-30).
Deferasirox oral granules 360 mg are white to almost white granules in sachet. They are available in cartons of 30 sachets………………………………………………..(NDC 72205-076-30). Store deferasirox oral granules at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C to 30°C (59°F to 86°F) [see USP Controlled Room Temperature].
Protect from moisture.
📋 Description ▾
11 DESCRIPTION Deferasirox is an iron-chelating agent provided as a granules for oral use. Deferasirox is designated chemically as 4-[3,5-bis(2-hydroxyphenyl)-1 H -1,2,4-triazol-1-yl] benzoic acid and has the following structural formula: Deferasirox is a white to slightly yellow powder. It has a molecular formula C 21 H 15 N 3 O 4 and molecular weight of 373.4 g/mol.
It is insoluble in water with a pH of suspension of 4.1. Deferasirox oral granules contain 90 mg, 180 mg, or 360 mg deferasirox. Inactive ingredients include colloidal silicon dioxide, croscarmellose sodium, hydrogenated castor oil, lactose monohydrate, low substituted hydroxy propyl cellulose, microcrystalline cellulose, poloxamer (188), povidone (K30) and sodium stearyl fumarate. def-str
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient to read the FDA-approved patient labeling (Medication Guide). Dosing Instructions Advise patients to take deferasirox oral granules by sprinkling the full dose on soft food (e.g., yogurt or applesauce) immediately prior to use and administered orally. Advise patients to take deferasirox oral granules once a day, preferably at the same time each day.
Deferasirox oral granules may be taken on an empty stomach or with a light meal (contains less than 7% fat content and approximately 250 calories). Examples of light meals include 1 whole wheat English muffin, 1 packet jelly (0.5 ounces), and skim milk (8 fluid ounces) or a turkey sandwich (2 oz. turkey on whole wheat bread w/lettuce, tomato, and 1 packet mustard). Blood Testing Advise patients that blood tests will be performed frequently to check for damage to kidneys, liver, or blood cells [see Warnings and Precautions (5.1 , 5.2 , 5.3 , 5.4 , 5.5 )] .
Acute Kidney Injury, Including Acute Renal Failure Caution patients about the potential for kidney toxicity when taking deferasirox oral granules. Inform patients of the signs and symptoms of kidney injury. Advise patients to contact their healthcare provider immediately if they experience any of these symptoms [see Warnings and Precautions (5.1) ] .
Hepatic Toxicity and Failure Caution patients about the potential for hepatic toxicity when taking deferasirox oral granules. Inform patients of the signs and symptoms of hepatic toxicity. Advise patients to contact their healthcare provider immediately if they experience any of these symptoms [see Warnings and Precautions (5.2) ] .
GI Ulceration and Hemorrhage Caution patients about the potential for the development of GI ulcers or bleeding when taking deferasirox in combination with drugs that have ulcerogenic or hemorrhagic potential, such as NSAIDs, corticosteroids, oral bisphosphonates, or anticoagulants. Inform patients of the signs and symptoms of GI ulcers or bleeding. Advise patients to contact their healthcare provider for symptoms of heartburn but to seek immediate medical attention for symptoms of GI hemorrhage [see Warnings and Precautions (5.3)].
Allergic Reactions Serious allergic reactions (which include swelling of the throat) have been reported in patients taking deferasirox, usually within the first month of treatment. If reactions are severe, advise patients to stop taking deferasirox immediately and seek immediate medical attention [see Warnings and Precautions (5.7) ] . Severe Skin Reactions Severe skin reactions have been reported in patients taking deferasirox oral granules.
Inform patients of the signs and symptoms of severe skin reactions. If reactions are severe, advise patients to stop taking deferasirox oral granules immediately and seek immediate medical attention [see Warnings and Precautions (5.8) ] . Skin Rash Skin rashes may occur during deferasirox treatment.
If the skin rash is severe, advise patients to stop taking deferasirox and seek medical attention [see Warnings and Precautions (5.9) ] . Pediatric Patients with Acute Illness Instruct pediatric patients and their caregivers to contact their healthcare provider during episodes of acute illness, especially if the patient has not been drinking fluids or the patient has volume depletion due to fever, vomiting, or diarrhea [see Warnings and Precautions (5.1) ] . Auditory and Ocular Testing Because auditory and ocular disturbances have been reported with deferasirox, conduct auditory testing and ophthalmic testing before starting deferasirox treatment and thereafter at regular intervals.
Advise patients to contact their healthcare provider if they develop visual or auditory changes during treatment [see Warnings and Precautions (5.10) ] . Drug Interactions Caution patients not to take aluminum containing antacids and deferasirox granules simultaneously [ see Drug Interactions (7.1) ] . Caution patients about potential loss of effectiveness of drugs…