
Chlorpromazine hydrochloride 25 mg/mL Injection, 25 ampules — NDC 73043-048-25 (Billing 73043-0048-25)
This is a package of 25 ampules of Chlorpromazine hydrochloride 25 mg/mL Injection from Devatis, Inc., marketed since Nov 2024 and currently FDA-listed. It is this product's only package size.
Other active recalls for Chlorpromazine Hydrochloride (different manufacturers) — 6 · tap to view
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 003788
- GCN: 14331
- GPI-14 (Medi-Span): 59200015102005
- HICL (First Databank): 001621
- AHFS class code: 28:16.08.24
- RxCUI (RxNorm): 1730076
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Phenothiazine class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
- It treats schizophrenia and other psychotic disorders, and the manic type of manic-depressive illness. It is also used for severe nausea and vomiting, stubborn hiccups, and a few o...
- Take it exactly as prescribed. Your dose is usually raised gradually and later lowered to the lowest amount that works. Benefit for psychotic symptoms can take weeks or months, so...
- Drowsiness is common, especially in the first week or two. You may also have dizziness when standing, dry mouth, a stuffy nose, constipation or weight gain. Stand up slowly and be...
- Call right away for a sudden sore throat or fever, yellowing of the skin or eyes, or high fever with stiff muscles and confusion. Also call for uncontrolled movements of the face,...
Patient education
Supplement & herbal interactions
Chlorpromazine may be associated with lower levels of 1 nutrient — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 1, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · quarterly | No Part D plan price is available for this NDC in our data. | |
| Medicare Part B allowsASP · J3230 | $18.143 / J3230 unit | — |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 3, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Billing & reimbursement
Where does this data come from?
- CMS ASP NDC-HCPCS crosswalk · refreshed Sep 22, 2026
- DMEPDAC NDC-HCPCS crosswalk
- openFDA NSDE billing units · refreshed Sep 7, 2026
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 73043-0048-25 You're viewing this Main listing | 25 AMPULE in 1 CARTON / 1 mL in 1 AMPULE | 2024-11-01 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Chlorpromazine Hydrochloride 25 mg/mL 00404-9836-01 | Henry | 1 ampule | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mL 00641-1397-35 | Hikma | 25 ampules | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 31722-0366-32 | Camber | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hci 25 mg/mL 43598-0140-25 | Dr. | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hci 25 mg/mL 51662-1406-01 | HF | 2 ml | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 55150-0318-25 | Eugia | 25 ampules | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 65219-0128-01 | Fresenius | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mL 66794-0249-42 | Piramal | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mL 68083-0533-25 | Gland | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 70710-1849-07 | Zydus | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 70771-1778-07 | Zydus | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 72205-0190-25 | Novadoz | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mLthis 73043-0048-25 | Devatis, | 25 ampules | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 70710-1850-07 | Zydus | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 55150-0319-25 | Eugia | 25 ampules | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mL 68083-0534-25 | Gland | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mL 73043-0049-25 | Devatis, | 25 ampules | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 72205-0191-25 | Novadoz | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mL 66794-0250-42 | Piramal | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine hydrochloride 25 mg/mL 00641-1398-35 | Hikma | 25 ampules | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 31722-0367-32 | Camber | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 70771-1779-07 | Zydus | 25 vials | — | AP | FDA listed | — |
| Chlorpromazine Hydrochloride 25 mg/mL 65219-0130-02 | Fresenius | 25 vials | — | AP | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Sep 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Sep 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
2 mg / 1 mL
UNII PQ6CK8PD0R
Ascorbic acid, also known as vitamin C, is a white crystalline powder. It serves as an antioxidant to prevent degradation of other ingredients and may also function as a preservative in the formulation.
-
6 mg / 1 mL
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
1 mg / 1 mL
UNII 4VON5FNS3C
Sodium metabisulfite is a preservative derived from sulfur compounds. It prevents microbial growth and oxidation in medicines, helping extend shelf life and maintain product stability.
-
1 mg / 1 mL
UNII VTK01UQK3G
Sodium sulfite is a salt preservative derived from sulfur. It prevents discoloration and microbial growth in medicines, helping keep products stable during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
5 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 1, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Analyses of seventeen placebo-controlled trials (modal duration of 10 weeks), largely in patients taking atypical antipsychotic drugs, revealed a risk of death in drug-treated patients of between 1.6 to 1.7 times the risk of death in placebo-treated patients. Over the course of a typical 10-week controlled trial, the rate of death in drug-treated patients was about 4.5%, compared to a rate of about 2.6% in the placebo group.
Although the causes of death were varied, most of the deaths appeared to be either cardiovascular (e.g., heart failure, sudden death) or infectious (e.g., pneumonia) in nature. Observational studies suggest that, similar to atypical antipsychotic drugs, treatment with conventional antipsychotic drugs may increase mortality. The extent to which the findings of increased mortality in observational studies may be attributed to the antipsychotic drug as opposed to some characteristic(s) of the patients is not clear.
Chlorpromazine Hydrochloride Injection is not approved for the treatment of patients with dementia-related psychosis ( see WARNINGS ).
🎯 Indications and Usage ▾
INDICATIONS AND USAGE For the treatment of schizophrenia; to control nausea and vomiting; for relief of restlessness and apprehension before surgery; for acute intermittent porphyria; as an adjunct in the treatment of tetanus; to control the manifestations of the manic type of manic-depressive illness; for relief of intractable hiccups; for the treatment of severe behavioral problems in children (1 to 12 years of age) marked by combativeness and/or explosive hyperexcitable behavior (out of proportion to immediate provocations), and in the short-term treatment of hyperactive children who show excessive motor activity with accompanying conduct disorders consisting of some or all of the following symptoms: impulsivity, difficulty sustaining attention, aggressivity, mood lability, and poor frustration tolerance.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Adults Adjust dosage to individual and the severity of his condition, recognizing that the milligram for milligram potency relationship among all dosage forms has not been precisely established clinically. It is important to increase dosage until symptoms are controlled. Dosage should be increased more gradually in debilitated or emaciated patients.
In continued therapy, gradually reduce dosage to the lowest effective maintenance level, after symptoms have been controlled for a reasonable period. Increase parenteral dosage only if hypotension has not occurred. Before using intramuscular, see Important Notes On Injection .
ELDERLY PATIENTS In general, dosages in the lower range are sufficient for most elderly patients. Since they appear to be more susceptible to hypotension and neuromuscular reactions, such patients should be observed closely. Dosage should be tailored to the individual, response carefully monitored, and dosage adjusted accordingly.
Dosage should be increased more gradually in elderly patients. PSYCHOTIC DISORDERS Increase dosage gradually until symptoms are controlled. Maximum improvement may not be seen for weeks or even months.
Continue optimum dosage for 2 weeks; then gradually reduce dosage to the lowest effective maintenance level. Daily dosage of 200 mg is not unusual. Some patients require higher dosages (e.g., 800 mg daily is not uncommon in discharged mental patients).
Hospitalized Patients: Acute Schizophrenic or Manic States Intramuscular : 25 mg (1 mL). If necessary, give additional 25 to 50 mg injection in 1 hour. Increase subsequent IM doses gradually over several days–up to 400 mg q4-6h in exceptionally severe cases–until patient is controlled.
Usually the patient becomes quiet and cooperative within 24 to 48 hours and oral doses may be substituted. Prompt Control of Severe Symptoms Intramuscular: 25 mg (1 mL). If necessary, repeat in 1 hour.
Subsequent doses should be oral, 25-50 mg tid. NAUSEA AND VOMITING Intramuscular: 25 mg (1 mL). If no hypotension occurs, give 25 to 50 mg q3-4h prn, until vomiting stops.
Then switch to oral dosage. During Surgery Intramuscular: 12.5 mg (0.5 mL). Repeat in 1 / 2 hour if necessary and if no hypotension occurs.
Intravenous : 2 mg per fractional injection, at 2-minute intervals. Do not exceed 25 mg. Dilute to 1 mg / mL, i.e., 1 mL (25 mg) mixed with 24 mL of saline.
PRESURGICAL APPREHENSION INTRACTABLE HICCUPS If symptoms persist for 2-3 days after trial with oral therapy, give 25 to 50 mg (1-2 mL) intramuscular. Should symptoms persist, use slow Intravenous infusion with patient flat in bed: 25 to 50 mg (1-2 mL) in 500 to 1000 mL of saline. Follow blood pressure closely.
ACUTE INTERMITTENT PORPHYRIA Intramuscular : 25 mg (1 mL) tid or qid until patient can take oral therapy. TETANUS Intramuscular : 25 to 50 mg (1-2 mL) given 3 or 4 times daily, usually in conjunction with barbiturates. Total doses and frequency of administration must be determined by the patient’s response, starting with low doses and increasing gradually.
Intravenous: 25 to 50 mg (1-2 mL). Dilute to at least 1 mg per mL and administer at a rate of 1 mg per minute. Pediatric Patients (6 months to 12 years of age) Chlorpromazine should generally not be used in pediatric patients under 6 months of age except where potentially lifesaving.
It should not be used in conditions for which specific pediatric dosages have not been established. SEVERE BEHAVIORAL PROBLEMS Outpatients Select route of administration according to severity of patient’s condition and increase dosage gradually as required. Intramuscular: 1 / 4 mg / lb body weight q6-8h, prn.
Hospitalized Patients As with outpatients, start with low doses and increase dosage gradually. In severe behavior disorders, higher dosages (50-100 mg daily, and in older children, 200 mg daily or more) may be necessary. There is little evidence that behavior improvement in severely disturbed mentally retarded patients is further… [Excerpted — this section continues on DailyMed.]
⛔ Contraindications ▾
CONTRAINDICATIONS Do not use in patients with known hypersensitivity to phenothiazines. Do not use in comatose states or in the presence of large amounts of central nervous system depressants (alcohol, barbiturates, narcotics, etc.).
⚠️ Warnings ▾
WARNINGS Increased Mortality in Elderly Patients with Dementia-Related Psychosis Elderly patients with dementia-related psychosis treated with antipsychotic drugs are at an increased risk of death. Chlorpromazine Hydrochloride Injection is not approved for the treatment of patients with dementia-related psychosis ( see BOXED WARNING ). The extrapyramidal symptoms which can occur secondary to chlorpromazine may be confused with the central nervous system signs of an undiagnosed primary disease responsible for the vomiting, e.g., Reye’s syndrome or other encephalopathy.
The use of chlorpromazine and other potential hepatotoxins should be avoided in children and adolescents whose signs and symptoms suggest Reye’s syndrome. Chlorpromazine Hydrochloride Injection contains sodium metabisulfite and sodium sulfite, sulfites that may cause allergic-type reactions including anaphylactic symptoms and life-threatening or less severe asthmatic episodes in certain susceptible people. The overall prevalence of sulfite sensitivity in the general population is unknown and probably low.
Sulfite sensitivity is seen more frequently in asthmatic than in nonasthmatic people. Tardive Dyskinesia Tardive dyskinesia, a syndrome consisting of potentially irreversible, involuntary, dyskinetic movements, may develop in patients treated with antipsychotic drugs. Although the prevalence of the syndrome appears to be highest among the elderly, especially elderly women, it is impossible to rely upon prevalence estimates to predict, at the inception of antipsychotic treatment, which patients are likely to develop the syndrome.
Whether antipsychotic drug products differ in their potential to cause tardive dyskinesia is unknown. Both the risk of developing the syndrome and the likelihood that it will become irreversible are believed to increase as the duration of treatment and the total cumulative dose of antipsychotic drugs administered to the patient increase. However, the syndrome can develop, although much less commonly, after relatively brief treatment periods at low doses.
There is no known treatment for established cases of tardive dyskinesia, although the syndrome may remit, partially or completely, if antipsychotic treatment is withdrawn. Antipsychotic treatment itself, however, may suppress (or partially suppress) the signs and symptoms of the syndrome and thereby may possibly mask the underlying disease process. The effect that symptomatic suppression has upon the long-term course of the syndrome is unknown.
Given these considerations, antipsychotics should be prescribed in a manner that is most likely to minimize the occurrence of tardive dyskinesia. Chronic antipsychotic treatment should generally be reserved for patients who suffer from a chronic illness that, 1) is known to respond to antipsychotic drugs, and, 2) for whom alternative, equally effective, but potentially less harmful treatments are not available or appropriate. In patients who do require chronic treatment, the smallest dose and the shortest duration of treatment producing a satisfactory clinical response should be sought.
The need for continued treatment should be reassessed periodically. If signs and symptoms of tardive dyskinesia appear in a patient on antipsychotics, drug discontinuation should be considered. However, some patients may require treatment despite the presence of the syndrome.
For further information about the description of tardive dyskinesia and its clinical detection, please refer to the sections on PRECAUTIONS and ADVERSE REACTIONS . Neuroleptic Malignant Syndrome (NMS) A potentially fatal symptom complex sometimes referred to as Neuroleptic Malignant Syndrome (NMS) has been reported in association with antipsychotic drugs. Clinical manifestations of NMS are hyperpyrexia, muscle rigidity, altered mental status and evidence of autonomic instability (irregular pulse or blood pressure, tachycardia, diaphoresis and cardiac dysrhythmias).
The diagnostic evaluation of… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
ADVERSE REACTIONS Note: Some adverse effects of chlorpromazine may be more likely to occur, or occur with greater intensity, in patients with special medical problems, e.g., patients with mitral insufficiency or pheochromocytoma have experienced severe hypotension following recommended doses. Drowsiness, usually mild to moderate, may occur, particularly during the first or second week, after which it generally disappears. If troublesome, dosage may be lowered.
Jaundice Overall incidence has been low, regardless of indication or dosage. Most investigators conclude it is a sensitivity reaction. Most cases occur between the second and fourth weeks of therapy.
The clinical picture resembles infectious hepatitis, with laboratory features of obstructive jaundice, rather than those of parenchymal damage. It is usually promptly reversible on withdrawal of the medication; however, chronic jaundice has been reported. There is no conclusive evidence that preexisting liver disease makes patients more susceptible to jaundice.
Alcoholics with cirrhosis have been successfully treated with chlorpromazine without complications. Nevertheless, the medication should be used cautiously in patients with liver disease. Patients who have experienced jaundice with a phenothiazine should not, if possible, be reexposed to chlorpromazine or other phenothiazines.
If fever with grippe-like symptoms occurs, appropriate liver studies should be conducted. If tests indicate an abnormality, stop treatment. Liver function tests in jaundice induced by the drug may mimic extrahepatic obstruction; withhold exploratory laparotomy until extrahepatic obstruction is confirmed.
Hematological Disorders, including agranulocytosis, eosinophilia, leukopenia, hemolytic anemia, aplastic anemia, thrombocytopenic purpura and pancytopenia have been reported. AGRANULOCYTOSIS Warn patients to report the sudden appearance of sore throat or other signs of infection. If white blood cell and differential counts indicate cellular depression, stop treatment and start antibiotic and other suitable therapy.
Most cases have occurred between the 4th and 10th weeks of therapy; patients should be watched closely during that period. Moderate suppression of white blood cells is not an indication for stopping treatment unless accompanied by the symptoms described above. Cardiovascular HYPOTENSIVE EFFECTS Postural hypotension, simple tachycardia, momentary fainting and dizziness may occur after the first injection; occasionally after subsequent injections; rarely, after the first oral dose.
Usually recovery is spontaneous and symptoms disappear within 1 / 2 to 2 hours. Occasionally, these effects may be more severe and prolonged, producing a shock-like condition. To minimize hypotension after injection, keep patient lying down and observe for at least 1 / 2 hour.
To control hypotension, place patient in head-low position with legs raised. If a vasoconstrictor is required, norepinephrine and phenylephrine are the most suitable. Other pressor agents, including epinephrine, should not be used as they may cause a paradoxical further lowering of blood pressure.
EKG CHANGES Particularly nonspecific, usually reversible Q and T wave distortions–have been observed in some patients receiving phenothiazine tranquilizers, including chlorpromazine. Note: Sudden death, apparently due to cardiac arrest, has been reported. CNS Reactions NEUROMUSCULAR (EXTRAPYRAMIDAL) REACTIONS Neuromuscular reactions include dystonia, motor restlessness, pseudo-parkinsonism and tardive dyskinesia, and appear to be dose-related.
They are discussed in the following paragraphs: Dystonia Class effect: Symptoms of dystonia, prolonged abnormal contractions of muscle groups, may occur in susceptible individuals during the first few days of treatment. Dystonic symptoms include: spasm of the neck muscles, sometimes progressing to tightness of the throat, swallowing difficulty, difficulty breathing, and/or protrusion of the tongue. While… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
Pregnancy NON-TERATOGENIC EFFECTS Neonates exposed to antipsychotic drugs, during the third trimester of pregnancy are at risk for extrapyramidal and/or withdrawal symptoms following delivery. There have been reports of agitation, hypertonia, hypotonia, tremor, somnolence, respiratory distress and feeding disorder in these neonates. These complications have varied in severity; while in some cases symptoms have been self-limited, in other cases neonates have required intensive care unit support and prolonged hospitalization.
Chlorpromazine Hydrochloride should be used during pregnancy only if the potential benefit justifies the potential risk to the fetus.
🆘 Overdosage ▾
OVERDOSAGE (See also ADVERSE REACTIONS .) Symptoms Primarily symptoms of central nervous system depression to the point of somnolence or coma. Hypotension and extrapyramidal symptoms. Other possible manifestations include agitation and restlessness, convulsions, fever, autonomic reactions such as dry mouth and ileus, EKG changes and cardiac arrhythmias.
Treatment It is important to determine other medications taken by the patient since multiple drug therapy is common in overdosage situations. Treatment is essentially symptomatic and supportive. Early gastric lavage is helpful.
Keep patient under observation and maintain an open airway, since involvement of the extrapyramidal mechanism may produce dysphagia and respiratory difficulty in severe overdosage. Do not attempt to induce emesis because a dystonic reaction of the head or neck may develop that could result in aspiration of vomitus. Extrapyramidal symptoms may be treated with anti-parkinsonism drugs, barbiturates or diphenhydramine.
See prescribing information for these products. Care should be taken to avoid increasing respiratory depression. If administration of a stimulant is desirable, amphetamine, dextroamphetamine or caffeine with sodium benzoate is recommended.
Stimulants that may cause convulsions (e.g., picrotoxin or pentylenetetrazol) should be avoided. If hypotension occurs, the standard measures for managing circulatory shock should be initiated. If it is desirable to administer a vasoconstrictor, norepinephrine and phenylephrine are most suitable.
Other pressor agents, including epinephrine, are not recommended because phenothiazine derivatives may reverse the usual elevating action of these agents and cause a further lowering of blood pressure. Limited experience indicates that phenothiazines are not dialyzable.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY The precise mechanism whereby the therapeutic effects of chlorpromazine are produced is not known. The principal pharmacological actions are psychotropic. It also exerts sedative and antiemetic activity.
Chlorpromazine has actions at all levels of the central nervous system—primarily at subcortical levels—as well as on multiple organ systems. Chlorpromazine has strong antiadrenergic and weaker peripheral anticholinergic activity; ganglionic blocking action is relatively slight. It also possesses slight antihistaminic and antiserotonin activity.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Chlorpromazine Hydrochloride Injection USP, 25 mg/mL and 50 mg/2 mL (25 mg/mL), are available in the following packages: 1 mL Single-Dose Ampule packaged in 25s (NDC 73043 048 25) 2 mL Single-Dose Ampule packaged in 25s (NDC 73043 049 25) Storage Protect from light, or discoloration may occur. Slight yellowing will not alter potency. Discard if markedly discolored.
Store at 20° to 25°C (68° to 77°F), excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]. Protect from freezing. To report SUSPECTED ADVERSE REACTIONS, contact Devatis, Inc. at 1-833-534-4406 or [email protected] or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
For Product Inquiry call 1-833-534-4406 Made in Turkey Distributed by: Devatis, Inc. San Clemente, CA 92672 Revised September 2024 KTP4879KT-00
📦 Storage and Handling ▾
Storage Protect from light, or discoloration may occur. Slight yellowing will not alter potency. Discard if markedly discolored.
Store at 20° to 25°C (68° to 77°F), excursions permitted to 15° to 30°C (59° to 86°F) [See USP Controlled Room Temperature]. Protect from freezing. To report SUSPECTED ADVERSE REACTIONS, contact Devatis, Inc. at 1-833-534-4406 or [email protected] or the FDA at 1-800-FDA-1088 or www.fda.gov/medwatch .
For Product Inquiry call 1-833-534-4406 Made in Turkey Distributed by: Devatis, Inc. San Clemente, CA 92672 Revised September 2024 KTP4879KT-00
📋 Description ▾
DESCRIPTION Chlorpromazine HCl is chemically designated as 2-Chloro-10-[3-(dimethylamino)propyl]-phenothiazine monohydrochloride and has the following structural formula: Chlorpromazine Hydrochloride Injection, USP is a sterile aqueous solution intended for deep intramuscular use. Each mL contains chlorpromazine hydrochloride 25 mg, ascorbic acid 2 mg, sodium metabisulfite 1 mg, sodium sulfite 1 mg and sodium chloride 6 mg in Water for Injection. pH is 3.4-5.4. Chlorpromazine Hydrochloride Injection structural formula
⚠️ Precautions ▾
PRECAUTIONS Leukopenia, Neutropenia and Agranulocytosis In clinical trial and postmarketing experience, events of leukopenia/neutropenia and agranulocytosis have been reported temporally related to antipsychotic agents. Possible risk factors for leukopenia/neutropenia include preexisting low white blood cell count (WBC) and history of drug induced leukopenia/neutropenia. Patients with a preexisting low WBC or a history of drug induced leukopenia/neutropenia should have their complete blood count (CBC) monitored frequently during the first few months of therapy and should discontinue Chlorpromazine Hydrochloride Injection USP at the first sign of a decline in WBC in the absence of other causative factors.
Patients with neutropenia should be carefully monitored for fever or other symptoms or signs of infection and treated promptly if such symptoms or signs occur. Patients with severe neutropenia (absolute neutrophil count <1000/mm 3 ) should discontinue Chlorpromazine Hydrochloride Injection, USP and have their WBC followed until recovery. General Given the likelihood that some patients exposed chronically to antipsychotics will develop tardive dyskinesia, it is advised that all patients in whom chronic use is contemplated be given, if possible, full information about this risk.
The decision to inform patients and/or their guardians must obviously take into account the clinical circumstances and the competency of the patient to understand the information provided. Chlorpromazine should be administered cautiously to persons with cardiovascular, liver or renal disease. There is evidence that patients with a history of hepatic encephalopathy due to cirrhosis have increased sensitivity to the CNS effects of chlorpromazine (i.e., impaired cerebration and abnormal slowing of the EEG).
Because of its CNS depressant effect, chlorpromazine should be used with caution in patients with chronic respiratory disorders such as severe asthma, emphysema and acute respiratory infections, particularly in children (1 to 12 years of age). Because chlorpromazine can suppress the cough reflex, aspiration of vomitus is possible. Chlorpromazine prolongs and intensifies the action of CNS depressants such as anesthetics, barbiturates and narcotics.
When chlorpromazine is administered concomitantly, about 1 / 4 to 1 / 2 the usual dosage of such agents is required. When chlorpromazine is not being administered to reduce requirements of CNS depressants, it is best to stop such depressants before starting chlorpromazine treatment. These agents may subsequently be reinstated at low doses and increased as needed.
Note: Chlorpromazine does not intensify the anticonvulsant action of barbiturates. Therefore, dosage of anticonvulsants, including barbiturates, should not be reduced if chlorpromazine is started. Instead, start chlorpromazine at low doses and increase as needed.
Use with caution in persons who will be exposed to extreme heat, organophosphorus insecticides and in persons receiving atropine or related drugs. Antipsychotic drugs elevate prolactin levels; the elevation persists during chronic administration. Tissue culture experiments indicate that approximately 1/3 of human breast cancers are prolactin-dependent in vitro , a factor of potential importance if the prescribing of these drugs is contemplated in a patient with a previously detected breast cancer.
Although disturbances such as galactorrhea, amenorrhea, gynecomastia and impotence have been reported, the clinical significance of elevated serum prolactin levels is unknown for most patients. An increase in mammary neoplasms has been found in rodents after chronic administration of antipsychotic drugs. Neither clinical nor epidemiologic studies conducted to date, however, have shown an association between chronic administration of these drugs and mammary tumorigenesis; the available evidence is considered too limited to be conclusive at this time.
Chromosomal aberrations in spermatocytes and abnorm… [Excerpted — this section continues on DailyMed.]
🍼 Nursing Mothers ▾
Nursing Mothers There is evidence that chlorpromazine is excreted in the breast milk of nursing mothers. Because of the potential for serious adverse reactions in nursing infants from chlorpromazine, a decision should be made whether to discontinue nursing or to discontinue the drug, taking into account the importance of the drug to the mother.
📄 Package Label / Principal Display Panel ▾
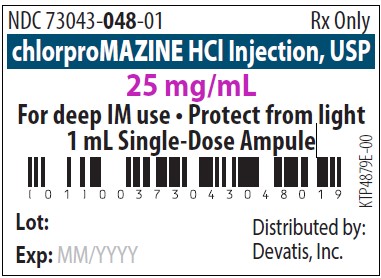
PRINCIPAL DISPLAY PANEL NDC 73043- 048 -01 Rx only chlorproMAZINE HCl Injection, USP 25 mg/mL For deep IM use Protect from light 1 mL Single-Dose Ampule Distributed by: Devatis, Inc. NDC 73043- 048 -25 Rx only chlorproMAZINE HCl Injection, USP 25 mg/mL For deep Intramuscular use 25 x 1 mL Single-Dose Ampule Devatis 1 mL ampul 25 mg / mL carton
PRINCIPAL DISPLAY PANEL NDC 73043- 049 -01Rx only chlorproMAZINE HCl Injection, USP 50 mg/2 mL (25 mg/mL) For deep IM use Protect from light 2 mL Single-Dose Ampule Distributed by: Devatis, Inc. NDC 73043- 049 -25 Rx only chlorproMAZINE HCl Injection, USP 50 mg/2 mL (25 mg/mL) For deep Intramuscular use 25 x 2 mL Single-Dose Ampule Devatis 2 mL ampul 50 mg per 2mL carton
Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | ✓ Available |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |