
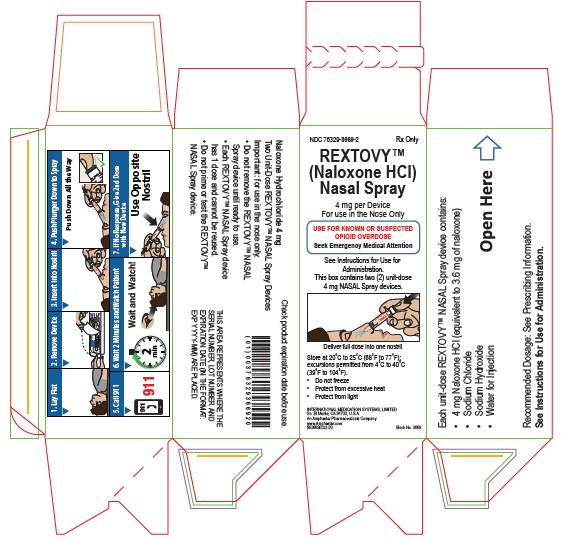
REXTOVY Naloxone Hydrochloride 4 mg/.25mL Spray, 25 mL — NDC 76329-3669-2 (Billing 76329-3669-02)
This is a package of 25 mL of REXTOVY Naloxone Hydrochloride 4 mg/.25mL Spray from International Medication Systems, Ltd., marketed since May 2024 and currently FDA-listed. It is this product's only package size.
NDC database record
One package, one record: these facts belong to NDC 76329-3669-2 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 76329 labeler · 3669 product · 2 package
- Package marketed since
- May 7, 2024
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Barcode (UPC-A, from the NDC)
- 3 7632936692 0
- Medicaid fills, this package
- 673 prescriptions in the last four reported quarters
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 075222
- GCN: 40233
- GPI-14 (Medi-Span): 93400020100922
- HICL (First Databank): 001874
- AHFS class code: 28:10.00.00
- RxCUI (RxNorm): 2637879
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Opioid Antagonist class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
Naloxone nasal spray is used along with emergency medical treatment to reverse the life-threatening effects of a known or suspected opiate (narcotic) overdose. Naloxone nasal spray is in a class of medications called opiate antagonists. It works by blocking the effects of opiates to relieve dangerous symptoms caused by high levels of opiates in the blood.
Read the full MedlinePlus article ↗- It is an emergency medicine that reverses an opioid overdose. Signs include very slow or stopped breathing and being unresponsive. Some injection forms have extra hospital or milit...
- Follow the instructions that came with your product. Nasal sprays go into one nostril. Zimhi goes into the outer thigh. Call 911 right away. If the person does not wake up or slips...
- Naloxone can wear off before the opioid does. Breathing problems can come back. Stay with the person until emergency help arrives.
- Why do I still need to call 911 if they wake up?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Naloxone Hydrochloride — tap one for details:
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 3, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per mL | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | $22.40 | $11.20 / 0.5 ml |
| Medicare drug plans payPart D · Q2 2026 | $22.52 | $11.26 / 0.5 ml |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · through Q1 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 76329-3669-02 You're viewing this Main listing | 2 CONTAINER in 1 CONTAINER / .25 mL in 1 CONTAINER | 2024-05-07 | — | Active |
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Rextovy 4 mg/.25mLthis 76329-3669-02 | International | 25 ml | — | — | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Code | What it grants | Expires |
|---|---|---|
| NP | New Product | Mar 7, 2026 |
Is there a generic version of REXTOVY 4 MG NASAL SPRAY?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 451W47IQ8X
Sodium chloride is common table salt. It's used in medicines as a buffer to maintain proper pH, as a filler to add bulk, or to adjust the osmotic balance in liquid formulations.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
3 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.- FDA label on DailyMed · label index refreshed Oct 3, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from International Medication Systems, Ltd. labeler code 76329
- Atropine Sulfate .1 mg/mL Injection NDC 76329-3340-1
- Sodium Bicarbonate 84 mg/mL Injection NDC 76329-3352-1
- Naloxone Hydrochloride 1 mg/mL Injection NDC 76329-3369-1
- Lidocaine Hydrochloride 20 mg/mL Injection NDC 76329-3390-1
- Procainamide Hydrochloride 100 mg/mL Injection NDC 76329-3399-5
- Naloxone Hydrochloride 1 mg/mL Injection NDC 76329-3469-1
- Lidocaine Hydrochloride 40 mg/mL Solution NDC 76329-6300-5
- Lorazepam 2 mg/mL Injection NDC 76329-8261-1
- Epinephrine 1 mg/mL Injection NDC 76329-9060-0
- Iron Sucrose 20 mg/mL Injection NDC 76329-9200-1
- Iron Sucrose 20 mg/mL Injection NDC 76329-9201-1
- Iron Sucrose 20 mg/mL Injection NDC 76329-9202-5
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE REXTOVY Nasal Spray is indicated for emergency treatment of known or suspected opioid overdose, as manifested by respiratory and/or central nervous system depression, for adult and pediatric patients. REXTOVY Nasal Spray is intended for immediate administration as emergency therapy in settings where opioids may be present. REXTOVY Nasal Spray is not a substitute for emergency medical care.
REXTOVY Nasal Spray is an opioid antagonist indicated for the emergency treatment of known or suspected opioid overdose, as manifested by respiratory and/or central nervous system depression for adults and pediatric patients. ( 1 ) REXTOVY Nasal Spray is intended for immediate administration as emergency therapy in settings where opioids may be present. ( 1 ) REXTOVY Nasal Spray is not a substitute for emergency medical care.
( 1 )
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION REXTOVY Nasal Spray is for intranasal use only. ( 2.1 ) Seek emergency medical care immediately after use. ( 2.1 ) Administer one spray of REXTOVY Nasal Spray to adults or pediatric patients intranasally into one nostril.
( 2.2 ) Administer additional doses of REXTOVY Nasal Spray using a new nasal spray device with each dose if the patient does not respond or responds and then relapses into respiratory depression. Additional doses of REXTOVY Nasal Spray may be given every 2 to 3 minutes until emergency medical assistance arrives. ( 2.2 ) Additional supportive and/or resuscitative measures may be helpful while awaiting emergency medical assistance.
( 2.2 )
2.1Important Administration Instructions REXTOVY Nasal Spray is for intranasal use only. The device is ready to use. Do not prime or test prior to administration.
Do not attempt to reuse REXTOVY Nasal Spray. Each unit-dose device contains a single dose of naloxone and cannot be reused. Figure 1 REXTOVY Nasal Spray Device Because treatment of suspected opioid overdose must be performed by someone other than the patient, instruct the prescription recipient to inform those around them about the presence of REXTOVY Nasal Spray and the Instructions for Use .
Instruct the users or caregiver to read the Instructions for Use at the time they receive a prescription for REXTOVY Nasal Spray. Emphasize the following instructions to the patient or caregiver: Administer REXTOVY Nasal Spray as quickly as possible because prolonged respiratory depression may result in damage to the central nervous system or death. Always seek immediate emergency medical assistance after the first dose of REXTOVY Nasal Spray has been administered in the event of a suspected, potentially life-threatening opioid emergency because the duration of action of most opioids exceeds that of naloxone hydrochloride.
Keep the patient under continued surveillance and administer repeated doses of REXTOVY Nasal Spray, as necessary, until emergency personnel arrive [see Warnings and Precautions ( 5.1 )] . Administer REXTOVY Nasal Spray according to the printed instructions on the carton and the Instructions for Use . ◦ Place the patient in the supine position. Prior to administration, be sure the device nozzle is inserted in either nostril of the patient and provide support to the back of the neck to allow the head to tilt back.
Do not prime or test the device prior to administration. ◦To administer the dose, press firmly on the green plunger of the device and remove the REXTOVY Nasal Spray nozzle from the nostril after use. ◦If the patient responds by waking up to the voice or touch or starts breathing normally, place the person on their side (recovery position) as shown in the Instructions for Use and call for emergency medical assistance immediately after the first dose of REXTOVY Nasal Spray. ◦Administer additional doses of REXTOVY Nasal Spray, using a new REXTOVY Nasal Spray, every 2 to 3 minutes as needed if the patient does not respond or responds and then relapses into respiratory depression.
Administer REXTOVY Nasal Spray in alternate nostrils with each dose [see Dosing and Administration ( 2.2 )] . figure1
2.2Dosing in Adults and Pediatric Patients Initial Dosing The recommended initial dose of REXTOVY Nasal Spray in adults and pediatric patients is one spray delivered by intranasal administration, which delivers 4 mg of naloxone hydrochloride. Repeat Dosing Seek emergency medical assistance as soon as possible after administering the REXTOVY Nasal Spray. The requirement for repeat doses of REXTOVY Nasal Spray depends upon the amount, type, and route of administration of the opioid being antagonized.
Administer REXTOVY Nasal Spray in alternate nostrils with each dose. If the patient responds to REXTOVY Nasal Spray and relapses back into respiratory depression before emergency assistance arrives, administer an additional dose of REXTOVY Nasal Spray in opposite nostril using a new REXTOV… [Excerpted — this section continues on DailyMed.]
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Nasal spray: 4 mg of naloxone hydrochloride per device. Each unit-dose REXTOVY nasal spray device delivers a single spray containing 4 mg of naloxone hydrochloride. Nasal Spray: 4 mg of naloxone hydrochloride per device. Each unit-dose REXTOVY nasal spray device delivers a single spray containing 4 mg of naloxone hydrochloride
⛔ Contraindications ▾
4 CONTRAINDICATIONS REXTOVY Nasal Spray is contraindicated in patients known to be hypersensitive to naloxone hydrochloride or to any of the other ingredients. Hypersensitivity to naloxone hydrochloride or to any of the other ingredients.
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Risk of Recurrent Respiratory and CNS Depression: Due to the duration of action of naloxone relative to the opioid, keep patient under continued surveillance and administer repeat doses of naloxone using a new nasal spray device with each dose, as necessary, while awaiting emergency medical assistance. ( 5.1 ) Risk of Limited Efficacy with Partial Agonists or Mixed Agonists/Antagonists: Reversal of respiratory depression caused by partial agonists or mixed agonists/antagonists, such as buprenorphine and pentazocine, may be incomplete.
Larger or repeat doses may be required. ( 5.2 ) Precipitation of Severe Opioid Withdrawal: Use in patients who are opioid dependent may precipitate opioid withdrawal. In neonates, opioid withdrawal may be life-threatening if not recognized and properly treated.
Monitor for the development of opioid withdrawal. ( 5.3 ) Risk of Cardiovascular (CV) Effects: Abrupt postoperative reversal of opioid depression may result in adverse CV effects. These events have primarily occurred in patients who had preexisting CV disorders or received other drugs that may have similar adverse CV effects.
Monitor these patients closely in an appropriate healthcare setting after use of REXTOVY Nasal Spray. ( 5.3 )
5.1Risk of Recurrent Respiratory and Central Nervous System Depression The duration of action of most opioids may exceed that of REXTOVY Nasal Spray resulting in a return of respiratory and/or central nervous system depression after an initial improvement in symptoms. Therefore, it is necessary to seek emergency medical assistance immediately after administration of REXTOVY Nasal Spray and to keep the patient under continued surveillance. Administer additional doses of REXTOVY Nasal Spray if the patient is not adequately responding or responds and then relapses back into respiratory depression, as necessary [see Dosage and Administration ( 2.2 )] .
Additional supportive and/or resuscitative measures may be helpful while awaiting emergency medical assistance.
5.2Risk of Limited Efficacy with Partial Agonists or Mixed Agonist/Antagonists Reversal of respiratory depression by partial agonists or mixed agonist/antagonists such as buprenorphine and pentazocine, may be incomplete. Larger or repeat doses of naloxone hydrochloride may be required to antagonize buprenorphine because the latter has a long duration of action due to its slow rate of binding and subsequent slow dissociation from the opioid receptor [see Dosage and Administration ( 2.3 )] . Buprenorphine antagonism is characterized by a gradual onset of the reversal effects and a decreased duration of action of the normally prolonged respiratory depression.
5.3Precipitation of Severe Opioid Withdrawal The use of REXTOVY Nasal Spray in patients who are opioid dependent may precipitate opioid withdrawal characterized by the following signs and symptoms: body aches, diarrhea, tachycardia, fever, runny nose, sneezing, piloerection, sweating, yawning, nausea or vomiting, nervousness, restlessness or irritability, shivering or trembling, abdominal cramps, weakness, and increased blood pressure. In neonates, opioid withdrawal may be life-threatening if not recognized and properly treated and may include the following signs and symptoms: convulsions, excessive crying, and hyperactive reflexes.
Monitor the patient for the development of the signs and symptoms of opioid withdrawal. Abrupt postoperative reversal of opioid depression after using naloxone hydrochloride may result in nausea, vomiting, sweating, tremulousness, tachycardia, hypotension, hypertension, seizures, ventricular tachycardia and fibrillation, pulmonary edema, and cardiac arrest. Death, coma, and encephalopathy have been reported as sequelae of these events.
These events have primarily occurred in patients who had pre-existing cardiovascular disorders or received other drugs that may have similar adverse cardiovascular effects. After use of naloxone hydrochloride, moni… [Excerpted — this section continues on DailyMed.]
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The following serious adverse reactions are discussed elsewhere in the labeling: Recurrent Respiratory and Central Nervous System Depression [see Warnings and Precautions ( 5.1 )] Precipitation of Severe Opioid Withdrawal [see Warnings and Precautions ( 5.3 )] The following adverse reactions were observed in a REXTOVY Nasal Spray clinical study: oral paraesthesia (3.7%), headache (3.7%) ( 6 ) To report SUSPECTED ADVERSE REACTIONS, contact Amphastar Pharmaceuticals, Inc. at 1-800-423-4136 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical studies are conducted under widely varying conditions, adverse reaction rates observed in the clinical studies of a drug cannot be directly compared to the rates in the clinical studies of another drug and may not reflect the rates observed in practice. In two clinical studies, N002-CL-A3 (Study A3) and N002-CL-A4 (Study A4), which comprised a total of 141 study treatments from 60 subjects, including 55 treatments using 4 mg and 10 mg of REXTOVY nasal spray (IN), the following adverse reactions were observed: oral paraesthesia (3.7%), headache (3.7%).
The following adverse reactions have been observed with other naloxone products: increased blood pressure, constipation, toothache, muscle spasms, musculoskeletal pain, headache, nasal dryness, nasal edema, nasal congestion, nasal inflammation, rhinalgia, xeroderma, abdominal pain, asthenia, dizziness, nasal discomfort, and presyncope.
6.2Postmarketing Experience The following adverse events have been identified during the post-approval use of naloxone hydrochloride injection in the postoperative setting. Because these reactions are reported voluntarily from a population of uncertain size, it is not always possible to reliably estimate their frequency or establish a causal relationship to drug exposure: hypotension, hypertension, ventricular tachycardia and fibrillation, dyspnea, pulmonary edema, and cardiac arrest. Death, coma, and encephalopathy have been reported as sequelae of these events.
Excessive doses of naloxone hydrochloride in postoperative patients have resulted in significant reversal of analgesia and have caused agitation. Abrupt reversal of opioid effects in persons who were physically dependent on opioids has precipitated an acute withdrawal syndrome. Signs and symptoms have included: body aches, fever, sweating, runny nose, sneezing, piloerection, yawning, weakness, shivering or trembling, nervousness, restlessness or irritability, diarrhea, nausea or vomiting, abdominal cramps, increased blood pressure, tachycardia.
In some patients, there was aggressive behavior upon abrupt reversal of an opioid overdose. In the neonate, opioid withdrawal signs and symptoms also included convulsions, excessive crying, and hyperactive reflexes [see Warnings and Precautions ( 5.3 )] . The following most frequently reported events (in decreasing frequency) have been identified primarily during postapproval use of naloxone hydrochloride (all routes of administration): withdrawal syndrome, vomiting, nonresponsiveness to stimuli, drug ineffective, agitation, somnolence, and loss of consciousness.
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary Life-sustaining therapy for opioid overdose should not be withheld (see Clinical Considerations) . There is an absence of data on naloxone hydrochloride administered for known or suspected opioid overdose in pregnant patients. Available data from retrospective cohort studies on oral naloxone use in pregnant women for opioid use disorder have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes.
In animal reproduction studies, no embryotoxic or teratogenic effects were observed in mice and rats treated with naloxone hydrochloride during the period of organogenesis at doses equivalent to 6-times and 12-times, respectively, a human dose of 8 mg/day (two REXTOVY Nasal Sprays) based on body surface area comparison ( see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk An opioid overdose is a medical emergency and can be fatal for the pregnant woman and fetus if left untreated. Treatment with REXTOVY Nasal Spray for opioid overdose should not be withheld because of potential concerns regarding the effects of REXTOVY Nasal Spray on the fetus. Data Animal Data Naloxone hydrochloride was administered during organogenesis to mice and rats at doses 6-times and 12-times, respectively, a human dose of 8 mg (two REXTOVY Nasal Sprays) based on body surface area comparison.
These studies demonstrated no embryotoxic or teratogenic effects due to naloxone hydrochloride.
8.2Lactation Risk Summary Naloxone hydrochloride is minimally orally bioavailable and is unlikely to affect the breastfed infant. There is no information regarding the presence of naloxone in human milk, or the effects of naloxone on the breastfed infant or on milk production. Published studies in lactating mothers have shown that naloxone does not affect prolactin or oxytocin hormone levels.
8.4Pediatric Use The safety and effectiveness of REXTOVY Nasal Spray have been established in pediatric patients for known or suspected opioid overdose, as manifested by respiratory and/or central nervous system depression. Use of naloxone hydrochloride in all pediatric patients is supported by adult bioequivalence studies coupled with evidence from the safe and effective use of other naloxone hydrochloride drug products. No pediatric studies were conducted for REXTOVY Nasal Spray.
Absorption of naloxone hydrochloride following intranasal administration in pediatric patients may be erratic or delayed. Even when the opiate-intoxicated pediatric patient responds appropriately to naloxone hydrochloride, he/she must be carefully monitored for at least 24 hours, as a relapse may occur as naloxone hydrochloride is metabolized. In opioid-dependent pediatric patients, (including neonates), administration of naloxone hydrochloride may result in an abrupt and complete reversal of opioid effects, precipitating an acute opioid withdrawal syndrome.
There may be clinical settings, particularly the postpartum period in neonates with known or suspected exposure to maternal opioid use, where it is preferable to avoid the abrupt precipitation of opioid withdrawal symptoms. Unlike acute opioid withdrawal in adults, acute opioid withdrawal in neonates manifesting in seizures may be life-threatening if not recognized and properly treated. Other signs and symptoms in neonates may include excessive crying and hyperactive reflexes.
In these settings where it may be preferable to avoid the abrupt precipitation of acute opioid withdrawal symptoms, consider use of an alternative, naloxone hydrochloride product that can be dosed according to weight and titrated to effect [see… [Excerpted — this section continues on DailyMed.]
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary Life-sustaining therapy for opioid overdose should not be withheld (see Clinical Considerations) . There is an absence of data on naloxone hydrochloride administered for known or suspected opioid overdose in pregnant patients. Available data from retrospective cohort studies on oral naloxone use in pregnant women for opioid use disorder have not identified a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes.
In animal reproduction studies, no embryotoxic or teratogenic effects were observed in mice and rats treated with naloxone hydrochloride during the period of organogenesis at doses equivalent to 6-times and 12-times, respectively, a human dose of 8 mg/day (two REXTOVY Nasal Sprays) based on body surface area comparison ( see Data ). The estimated background risk of major birth defects and miscarriage for the indicated population is unknown. In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively.
Clinical Considerations Disease-associated maternal and/or embryo/fetal risk An opioid overdose is a medical emergency and can be fatal for the pregnant woman and fetus if left untreated. Treatment with REXTOVY Nasal Spray for opioid overdose should not be withheld because of potential concerns regarding the effects of REXTOVY Nasal Spray on the fetus. Data Animal Data Naloxone hydrochloride was administered during organogenesis to mice and rats at doses 6-times and 12-times, respectively, a human dose of 8 mg (two REXTOVY Nasal Sprays) based on body surface area comparison.
These studies demonstrated no embryotoxic or teratogenic effects due to naloxone hydrochloride.
🧒 Pediatric Use ▾
8.4Pediatric Use The safety and effectiveness of REXTOVY Nasal Spray have been established in pediatric patients for known or suspected opioid overdose, as manifested by respiratory and/or central nervous system depression. Use of naloxone hydrochloride in all pediatric patients is supported by adult bioequivalence studies coupled with evidence from the safe and effective use of other naloxone hydrochloride drug products. No pediatric studies were conducted for REXTOVY Nasal Spray.
Absorption of naloxone hydrochloride following intranasal administration in pediatric patients may be erratic or delayed. Even when the opiate-intoxicated pediatric patient responds appropriately to naloxone hydrochloride, he/she must be carefully monitored for at least 24 hours, as a relapse may occur as naloxone hydrochloride is metabolized. In opioid-dependent pediatric patients, (including neonates), administration of naloxone hydrochloride may result in an abrupt and complete reversal of opioid effects, precipitating an acute opioid withdrawal syndrome.
There may be clinical settings, particularly the postpartum period in neonates with known or suspected exposure to maternal opioid use, where it is preferable to avoid the abrupt precipitation of opioid withdrawal symptoms. Unlike acute opioid withdrawal in adults, acute opioid withdrawal in neonates manifesting in seizures may be life-threatening if not recognized and properly treated. Other signs and symptoms in neonates may include excessive crying and hyperactive reflexes.
In these settings where it may be preferable to avoid the abrupt precipitation of acute opioid withdrawal symptoms, consider use of an alternative, naloxone hydrochloride product that can be dosed according to weight and titrated to effect [see Warnings and Precautions ( 5.3 )] . Also, in situations where the primary concern is for infants at risk for opioid overdose, consider whether the availability of alternate naloxone-containing products may be better suited than REXTOVY Nasal Spray.
🧓 Geriatric Use ▾
8.5Geriatric Use Clinical studies of REXTOVY Nasal Spray did not include sufficient numbers of subjects aged 65 and over to determine whether they respond differently from younger subjects. Other reported clinical experience has not identified differences in responses between the elderly and younger patients. Geriatric patients have a greater frequency of decreased hepatic, renal, or cardiac function and of concomitant disease or other drug therapy.
Therefore, the systemic exposure of naloxone hydrochloride can be higher in these patients.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Naloxone hydrochloride is an opioid antagonist that antagonizes opioid effects by competing for the same receptor sites. Naloxone hydrochloride reverses the effects of opioids, including respiratory depression, sedation, and hypotension. It can also reverse the psychotomimetic and dysphoric effects of agonist-antagonists such as pentazocine.
12.2Pharmacodynamics When naloxone hydrochloride is administered intravenously, the onset of action is generally apparent within two minutes. The time to onset of action is shorter for intravenous compared to subcutaneous or intramuscular routes of administration. The duration of action is dependent upon the dose and route of administration of naloxone hydrochloride.
12.3Pharmacokinetics In a pharmacokinetic study on healthy adult subjects, the relative bioavailability (BA) of one nasal spray in one nostril (4 mg total dose, 0.25 mL of 16 mg/mL naloxone hydrochloride solution) was compared to a single dose of 0.4 mg naloxone hydrochloride intramuscular (IM) injection, and 2 mg naloxone hydrochloride intravenous (IV) infusion. Absorption The pharmacokinetics parameters obtained in the study are shown in Table 1. The pharmacokinetic curves (0-6 hours and 0-30 minutes, respectively) for REXTOVY Nasal Spray 4 mg by IN and naloxone HCl 0.4 mg delivered by IM and 2 mg naloxone by IV are provided in Figure 2, respectively.
Table 1. Mean Pharmacokinetic Parameters for Naloxone Following REXTOVY Nasal Spray, IM Injection and IV Infusion of Naloxone HCl in Healthy Subjects Parameters 4 mg REXTOVY Nasal Spray 0.4 mg Naloxone HCl Intramuscular Injection 2 mg Naloxone HCl Intravenous Infusion Population N=25 N=27 N=26 AUC 0-6h (ng*hr/mL ) 6.41 ± 1.33 1.54 ± 1.27 8.44 ±
1.34AUC 0-inf (ng*hr/mL ) 6.63 ± 1.32 1.60 ± 1.27 8.64 ±
1.33C max (ng/mL) 3.71 ± 1.55 0.73 ± 1.56 11.10 ± 2.15 t max (min) 32.1 ± 1.6 24.4 ± 2.4 4.9 ± 1.4 t ½ (min) 67.6 ± 1.2 75.7 ± 1.2 66.2 ±
1.2Dose-Normalized Relative BA (%) vs. IV 40.7 ± 17.8 95.9 ± 28.5 --- Figure 2 Mean Plasma Concentration of Naloxone, (a) 0-6 hrs and (b) 0-1 hour Following Intranasal Administration of REXTOVY Nasal Spray (4mg) and IM Injection of Naloxone HCl (0.4mg) (a) (b) T he dose-normalized relative bioavailability of one (4 mg) dose of REXTOVY Nasal Spray as compared to the 0.4 mg dose of naloxone hydrochloride administered by IV was 40.7%. Distribution Following parenteral administration, naloxone hydrochloride is distributed in the body and readily crosses the placenta.
Plasma protein binding occurs but is relatively weak. Plasma albumin is the major binding constituent, but significant binding of naloxone hydrochloride also occurs to plasma constituents other than albumin. It is not known whether naloxone is excreted into human milk.
Elimination Following a single intranasal administration of REXTOVY Nasal Spray (4 mg dose of naloxone hydrochloride), the mean plasma half-life of naloxone hydrochloride in healthy adults was approximately 67.6 minutes, which was shorter than that observed after administrations of a 0.4 mg naloxone hydrochloride IM injection, where the half-life was 75.7 minutes. The half-life of 2 mg naloxone hydrochloride IV infusion is approximately 66.2 minutes. Metabolism Naloxone hydrochloride is metabolized in the liver, primarily by glucuronide conjugation, with naloxone-3-glucuronide as the major metabolite.
Excretion Naloxone is excreted mainly as metabolites in urine. figure2a figure2b
🧬 Mechanism of Action ▾
12.1Mechanism of Action Naloxone hydrochloride is an opioid antagonist that antagonizes opioid effects by competing for the same receptor sites. Naloxone hydrochloride reverses the effects of opioids, including respiratory depression, sedation, and hypotension. It can also reverse the psychotomimetic and dysphoric effects of agonist-antagonists such as pentazocine.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING
16.1How Supplied Each carton contains two unit-dose REXTOVY Nasal Spray devices. Each device delivers a single spray containing 4 mg of naloxone hydrochloride. One carton containing two REXTOVY Nasal Spray devices: NDC 76329-3669-2 REXTOVY Nasal Spray is not made with natural rubber latex.
16.2Storage and Handling Store REXTOVY Nasal Spray in the blister and cartons provided. Store at 20°C to 25°C (68°F to 77°F); excursions permitted from 4°C to 40°C (39°F to 104°F). Do not freeze.
Protect from light. Naloxone Hydrochloride freezes at temperatures below -15°C (5°F). If this happens, the device will not spray.
If Naloxone Hydrochloride is frozen and is needed in an emergency, do NOT wait for Naloxone Hydrochloride to thaw. Get emergency medical help right away. However, Naloxone Hydrochloride may be thawed by allowing it to sit at room temperature for 15 minutes, and it may still be used if it has been thawed after being previously frozen.
16.1How Supplied Each carton contains two unit-dose REXTOVY Nasal Spray devices. Each device delivers a single spray containing 4 mg of naloxone hydrochloride. One carton containing two REXTOVY Nasal Spray devices: NDC 76329-3669-2 REXTOVY Nasal Spray is not made with natural rubber latex.
📦 Storage and Handling ▾
16.2Storage and Handling Store REXTOVY Nasal Spray in the blister and cartons provided. Store at 20°C to 25°C (68°F to 77°F); excursions permitted from 4°C to 40°C (39°F to 104°F). Do not freeze.
Protect from light. Naloxone Hydrochloride freezes at temperatures below -15°C (5°F). If this happens, the device will not spray.
If Naloxone Hydrochloride is frozen and is needed in an emergency, do NOT wait for Naloxone Hydrochloride to thaw. Get emergency medical help right away. However, Naloxone Hydrochloride may be thawed by allowing it to sit at room temperature for 15 minutes, and it may still be used if it has been thawed after being previously frozen.
📋 Description ▾
11 DESCRIPTION Naloxone hydrochloride is an opioid antagonist. It is chemically identified as 17-allyl-4,5α-epoxy-3,14-dihydroxymorphinan-6-one hydrochloride dihydrate. Its molecular formula is C 19 H 21 NO 4 • HCl • 2H 2 O and has a molecular weight of 399.87 g/mol.
It has the following structural formula: Naloxone hydrochloride dihydrate occurs as a white to slightly off-white powder. It is soluble in water, in dilute acids, and in strong alkali; slightly soluble in alcohol; practically insoluble in ether and in chloroform. REXTOVY Nasal Spray is a prefilled unit-dose intranasal spray.
Naloxone hydrochloride is contained as a solution in a stoppered glass vial within the nasal spray device. Each REXTOVY device delivers a single spray containing 4 mg of naloxone hydrochloride (equivalent to 3.6 mg of naloxone) in 0.25 mL of aqueous solution with a pH of 3.5 to 5.0. Inactive ingredients include sodium chloride, sodium hydroxide to adjust pH, and water for injection USP. structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient and family members or caregivers to read the FDA-approved patient labeling (Patient Information and Instructions for Use) . Recognition of Opioid Overdose Inform patients and their family members or caregivers about how to recognize the signs and symptoms of an opioid overdose such as the following: Extreme somnolence -inability to awaken a patient verbally or upon a firm sternal rub. Respiratory depression -this can range from slow or shallow respiration to no respiration in a patient who is unarousable.
Other signs and symptoms that may accompany somnolence and respiratory depression include the following: ◦Miosis ◦Bradycardia and/or hypotension. Risk of Recurrent Respiratory and Central Nervous System Depression Instruct patients and their family members or caregivers that, since the duration of action of most opioids may exceed that of REXTOVY Nasal Spray, they must seek immediate emergency medical assistance after administration of REXTOVY Nasal Spray and keep the patient under continued surveillance [see Dosage and Administration (2.2), Warnings and Precautions (5.3)] .
Limited Efficacy for/with Partial Agonists or Mixed Agonist/Antagonists Instruct patients and their family members or caregivers that the reversal of respiratory depression caused by partial agonists or mixed agonist/antagonists, such as buprenorphine and pentazocine, may be incomplete and may require higher doses of naloxone hydrochloride or repeated administration of REXTOVY Nasal Spray, using a new nasal spray device each time [see Dosage and Administration (2.3), Warnings and Precautions (5.2)] . Precipitation of Severe Opioid Withdrawal Instruct patients and their family members or caregivers that the use of REXTOVY Nasal Spray in patients who are opioid dependent may precipitate opioid withdrawal [see Warnings and Precautions (5.3), Adverse Reactions (6)] .
Administration Instructions Instruct patients and their family members or caregivers to: Ensure REXTOVY Nasal Spray is readily available in locations where persons may be intentionally or accidentally exposed to an opioid overdose (i.e., opioid emergencies). Use each REXTOVY Nasal Spray device only one time. Do not test or prime prior to use [see Dosage and Administration (2.1)] .
Administer REXTOVY Nasal Spray as quickly as possible if a patient is unresponsive and an opioid overdose is suspected, even when in doubt, because prolonged respiratory depression may result in damage to the central nervous system or death. REXTOVY Nasal Spray is not a substitute for emergency medical care [see Dosage and Administration (2.1)] . Lay the patient on their back and administer REXTOVY Nasal Spray into one nostril while providing support to the back of the neck to allow the head to tilt back [see Dosage and Administration (2.1)] .
If the patient responds by waking up to the voice or touch or starts breathing normally, place them in the recovery position by turning them to their side as shown in the Instructions for Use and call for emergency medical assistance immediately after administration of REXTOVY Nasal Spray. Additional supportive and/or resuscitative measures may be helpful while awaiting emergency medical assistance [see Dosage and Administration (2.1)] . Monitor the patient and re-administer additional doses of REXTOVY Nasal Spray every 2 to 3 minutes, using a new REXTOVY Nasal Spray device.
If the patient is not responding or responds and then relapses back into respiratory depression, administer REXTOVY Nasal Spray in alternate nostrils with each dose [see Dosage and Administration (2.1)] . Replace REXTOVY Nasal Spray before its expiration date.
PATIENT INFORMATION REXTOVY (rex toe' vee) (Naloxone Hydrochloride) Nasal Spray You and your family members or caregivers should read this Patient Information leaflet before an opioid emergency happens. This information does not take the place of talking with your healthcare provider about your medica… [Excerpted — this section continues on DailyMed.]
🧬 Pharmacokinetics ▾
12.3Pharmacokinetics In a pharmacokinetic study on healthy adult subjects, the relative bioavailability (BA) of one nasal spray in one nostril (4 mg total dose, 0.25 mL of 16 mg/mL naloxone hydrochloride solution) was compared to a single dose of 0.4 mg naloxone hydrochloride intramuscular (IM) injection, and 2 mg naloxone hydrochloride intravenous (IV) infusion. Absorption The pharmacokinetics parameters obtained in the study are shown in Table 1. The pharmacokinetic curves (0-6 hours and 0-30 minutes, respectively) for REXTOVY Nasal Spray 4 mg by IN and naloxone HCl 0.4 mg delivered by IM and 2 mg naloxone by IV are provided in Figure 2, respectively.
Table 1. Mean Pharmacokinetic Parameters for Naloxone Following REXTOVY Nasal Spray, IM Injection and IV Infusion of Naloxone HCl in Healthy Subjects Parameters 4 mg REXTOVY Nasal Spray 0.4 mg Naloxone HCl Intramuscular Injection 2 mg Naloxone HCl Intravenous Infusion Population N=25 N=27 N=26 AUC 0-6h (ng*hr/mL ) 6.41 ± 1.33 1.54 ± 1.27 8.44 ±
1.34AUC 0-inf (ng*hr/mL ) 6.63 ± 1.32 1.60 ± 1.27 8.64 ±
1.33C max (ng/mL) 3.71 ± 1.55 0.73 ± 1.56 11.10 ± 2.15 t max (min) 32.1 ± 1.6 24.4 ± 2.4 4.9 ± 1.4 t ½ (min) 67.6 ± 1.2 75.7 ± 1.2 66.2 ±
1.2Dose-Normalized Relative BA (%) vs. IV 40.7 ± 17.8 95.9 ± 28.5 --- Figure 2 Mean Plasma Concentration of Naloxone, (a) 0-6 hrs and (b) 0-1 hour Following Intranasal Administration of REXTOVY Nasal Spray (4mg) and IM Injection of Naloxone HCl (0.4mg) (a) (b) T he dose-normalized relative bioavailability of one (4 mg) dose of REXTOVY Nasal Spray as compared to the 0.4 mg dose of naloxone hydrochloride administered by IV was 40.7%. Distribution Following parenteral administration, naloxone hydrochloride is distributed in the body and readily crosses the placenta.
Plasma protein binding occurs but is relatively weak. Plasma albumin is the major binding constituent, but significant binding of naloxone hydrochloride also occurs to plasma constituents other than albumin. It is not known whether naloxone is excreted into human milk.
Elimination Following a single intranasal administration of REXTOVY Nasal Spray (4 mg dose of naloxone hydrochloride), the mean plasma half-life of naloxone hydrochloride in healthy adults was approximately 67.6 minutes, which was shorter than that observed after administrations of a 0.4 mg naloxone hydrochloride IM injection, where the half-life was 75.7 minutes. The half-life of 2 mg naloxone hydrochloride IV infusion is approximately 66.2 minutes. Metabolism Naloxone hydrochloride is metabolized in the liver, primarily by glucuronide conjugation, with naloxone-3-glucuronide as the major metabolite.
Excretion Naloxone is excreted mainly as metabolites in urine. figure2a figure2b
🧬 Pharmacodynamics ▾
12.2Pharmacodynamics When naloxone hydrochloride is administered intravenously, the onset of action is generally apparent within two minutes. The time to onset of action is shorter for intravenous compared to subcutaneous or intramuscular routes of administration. The duration of action is dependent upon the dose and route of administration of naloxone hydrochloride.
🧪 Nonclinical Toxicology ▾
13 NONCLINICAL TOXICOLOGY
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term animal studies to evaluate the carcinogenic potential of naloxone have not been completed. Mutagenesis Naloxone was weakly positive in the Ames mutagenicity and in the in vitro human lymphocyte chromosome aberration test but was negative in the in vitro Chinese hamster V79 cell HGPRT mutagenicity assay and in the in vivo rat bone marrow chromosome aberration study. Impairment of Fertility Reproduction studies conducted in mice and rats at doses 6-times and 12-times, respectively, a human dose of 8 mg/day (two REXTOVY Nasal Sprays) based on body surface area comparison, demonstrated no adverse effects on fertility of naloxone hydrochloride.
📄 Carcinogenesis, Mutagenesis, Impairment of Fertility ▾
13.1Carcinogenesis, Mutagenesis, Impairment of Fertility Carcinogenesis Long-term animal studies to evaluate the carcinogenic potential of naloxone have not been completed. Mutagenesis Naloxone was weakly positive in the Ames mutagenicity and in the in vitro human lymphocyte chromosome aberration test but was negative in the in vitro Chinese hamster V79 cell HGPRT mutagenicity assay and in the in vivo rat bone marrow chromosome aberration study. Impairment of Fertility Reproduction studies conducted in mice and rats at doses 6-times and 12-times, respectively, a human dose of 8 mg/day (two REXTOVY Nasal Sprays) based on body surface area comparison, demonstrated no adverse effects on fertility of naloxone hydrochloride.
📖 Instructions for Use ▾
Instructions for Use REXTOVY (rex toe' vee) (Naloxone Hydrochloride) Nasal Spray You and your family members or caregivers should read the Instructions for Use that comes with REXTOVY™ Nasal Spray before using it. Talk to your healthcare provider if you and your family members or caregivers have any questions about the use of REXTOVY™ Nasal Spray. Use REXTOVY™ Nasal Spray for known or suspected opioid overdose in adults and children.
Important: For use in the nose only. Do not remove or test the REXTOVY™ Nasal Spray until ready to use. Each REXTOVY™ Nasal Spray has 1 dose and cannot be reused.
You do not need to prime REXTOVY™ Nasal Spray. How to use REXTOVY™ Nasal Spray: How should I store REXTOVY™ Nasal Spray? Store at room temperature between 68°F to 77°F (20°C to 25°C).
REXTOVY™ Nasal Spray may be stored for short periods between 39°F to 104°F (4°C to 40°C). Do not freeze. Do not expose to temperatures below 39°F (4°C) or above 104°F (40°C).
Keep REXTOVY™ Nasal Spray in its box until ready to use. Protect from light. Replace REXTOVY™ Nasal Spray before the expiration date on the box.
Keep REXTOVY™ Nasal Spray and all medicines out of the reach of children. Distributed by International Medication Systems, Limited, So. El Monte, CA 91733, U.S.A.
For more information, go to www.amphastar.com or call 1-800-423-4136. This Instructions for Use has been approved by the U.S. Food and Drug Administration.
Issued: 06/2023 7036690F/6-23 IFUInstruction
📄 Package Label / Principal Display Panel ▾
Carton Label Principal Display Panel Text: NDC 76329- 3669 -2 Rx Only REXTOVY™ (Naloxone HCl) Nasal Spray 4 mg per Device For use in the Nose Only USE FOR KNOWN OR SUSPECTED OPIOID OVERDOSE Seek Emergency Medical Attention See Instructions for Use for Administration. This box contains two (2) unit-dose 4 mg NASAL Spray devices. Deliver full dose into one nostril Store at 20˚C to 25˚C (68˚F to 77˚F); excursions permitted from 4˚C to 40˚C (39˚F to 104˚F).
Do not freeze Protect from excessive heat Protect from light INTERNATIONAL MEDICATION SYSTEMS, LIMITED So. El Monte, CA 91733, U.S.A. An Amphastar Pharmaceuticals Company www.Amphastar.com 5636690D/3-23 Stock No.
3669 carton
Medicaid utilization & spend
Medicare Part D spend CMS · PART D · 2026 (Q1)
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | ✓ Available |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | ✓ Available |