
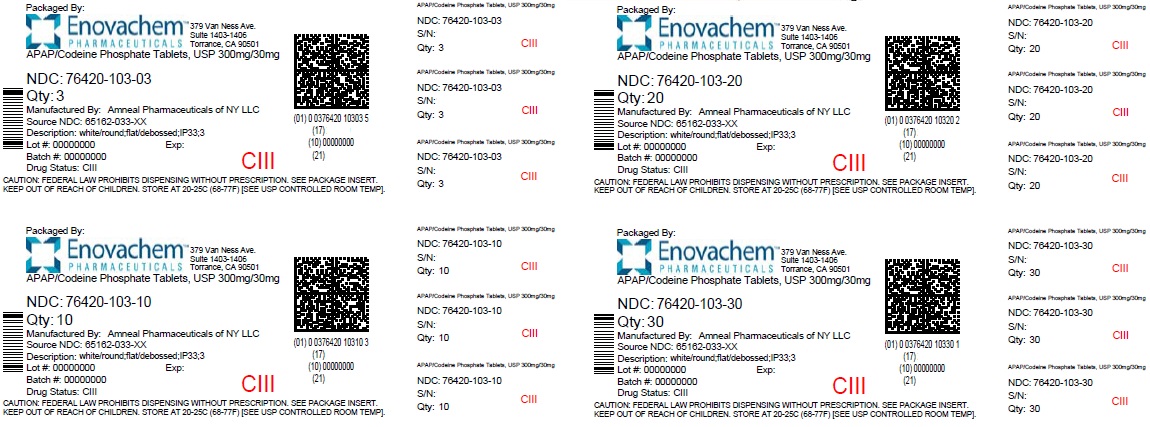
Acetaminophen and Codeine 300 mg; 30 mg Tablet, 30-count — NDC 76420-103-30 (Billing 76420-0103-30)
This is a package of 30 tablets of Acetaminophen and Codeine 300 mg; 30 mg Tablet from Asclemed USA, Inc., marketed since May 2008 and currently FDA-listed.
NDC database record
One package, one record: these facts belong to NDC 76420-103-30 alone.
- Record
- FDA NDC Directory package listing · Human prescription drug
- Code segments
- 76420 labeler · 103 product · 30 package
- Package marketed since
- Oct 30, 2020
- Sample package
- No — commercial package
- Listing certified through
- Dec 31, 2026
- Billing quantity
- 30 EA per package
- Barcode (UPC-A, from the NDC)
- 3 7642010330 1
- FDA record last changed
- Jul 24, 2026
Identity & classification
Regulatory identifiers FDA, NLM and CMS codes for this package
Drug-database identifiers Medi-Span GPI and First Databank GCN / HICL / AHFS classification
- GSN (GCN sequence number): 004165
- GCN: 70134
- HICL (First Databank): 001717
- AHFS class code: 28:08.08.00
- RxCUI (RxNorm): 993781
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
- RxNorm (NLM RxNav) · catalog refreshed Oct 1, 2026
- Medi-Span GPI (licensed)
- First Databank (licensed) · refreshed Oct 1, 2026
RxNorm drug class
This medicine belongs to the Anilides class.
Where does this data come from?
- RxClass (NLM) · catalog refreshed Oct 1, 2026
Clinical
The combination of acetaminophen and codeine is used to relieve pain. Acetaminophen is in a class of medications called analgesics (pain relievers) and antipyretics (fever reducers). It works by changing the way the body senses pain and by cooling the body. Codeine belongs to a class of medications called opiate (narcotic) analgesics. When codeine is used to treat pain, it works by changing the way the brain and nervous system respond to pain.
Read the full MedlinePlus article ↗- It treats mild to moderate pain when you need an opioid and other pain relievers have not worked or were not tolerated. It is not meant for long-term use unless your pain stays sev...
- Take it by mouth exactly as prescribed, usually as needed for pain. Your prescriber aims for the lowest dose for the shortest time. If you have the liquid, use an oral syringe or c...
- Drowsiness, dizziness, nausea, vomiting, sweating, and constipation are common. Call for help right away if you have slow or shallow breathing, extreme sleepiness, fainting, or sig...
- No, not without checking with me or your doctor first. Alcohol, benzodiazepines, and other sedating drugs can cause dangerous sleepiness, slowed breathing, coma, and death.
Patient education
Supplement & herbal interactions
Where does this data come from?
- MedlinePlus (NLM) · refreshed Oct 1, 2026
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Ask a licensed pharmacist directly — free, answered by our team.
Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per each | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | Not in the retail survey — common for institutional, discontinued, or low-volume packs. | |
| Medicaid paysCMS SDUD · 12 mo | No recent Medicaid claims on file for this NDC — rare and low-volume NDCs are suppressed in the public data. | |
| Medicare drug plans payPart D · Q2 2026 | $0.5009 | $15.03 / 30 tablets |
Where does this data come from?
- CMS NADAC weekly file
- CMS ASP pricing files · refreshed Sep 20, 2026
- CMS Medicaid State Drug Utilization Data · refreshed Oct 5, 2026
- CMS Part D plan pricing files · refreshed Sep 24, 2026
- VA National Acquisition Center price file
Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Marketing end | Status |
|---|---|---|---|---|
| 76420-0103-03 76420-103-03 Main listing | 3 TABLET in 1 BOTTLE | 2020-10-30 | — | Active |
| 76420-0103-10 76420-103-10 | 10 TABLET in 1 BOTTLE | 2020-10-30 | — | Active |
| 76420-0103-20 76420-103-20 | 20 TABLET in 1 BOTTLE | 2020-10-30 | — | Active |
| 76420-0103-30 You're viewing this | 30 TABLET in 1 BOTTLE | 2020-10-30 | — | Active |
You're viewing the largest of 4 pack sizes for this product.
Pack size FAQ
What quantity is in this package?
How does this package differ from NDC 76420-0103-03?
What NDC number is used to bill for this package of Acetaminophen and Codeine 300 mg; 30 mg Tablet?
Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 00406-0484-01 | SpecGx | 100 tablets | $0.256 | AA | Availability likely | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 13107-0059-01 | Aurolife | 100 tablets | $0.256 | AA | Availability likely | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 64380-0446-01 | Strides | 100 tablets | $0.256 | AA | Availability likely | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 65162-0033-10 | Amneal | 100 tablets | $0.256 | AA | Availability likely | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 71930-0055-12 | Eywa | 100 tablets | $0.256 | AA | Availability likely | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 49999-0060-30 | Quality | 30 tablets | — | AA | Discontinued | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 50090-4610-00 | A-S | 10 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 50090-4611-01 | A-S | 16 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 58118-4484-08 | Clinical | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 60760-0581-30 | St. | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 60760-0938-30 | ST. | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine 300 mg/1; 30 mg 61919-0484-18 | Direct_Rx | 18 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 63187-0106-15 | Proficient | 15 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 63187-0491-20 | Proficient | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 63187-0815-15 | Proficient | 15 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 63629-5666-01 | Bryant | 10 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 64850-0642-12 | Elite | 120 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 67296-1772-06 | RedPharm | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 67296-2239-02 | Redpharm | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 67544-0002-09 | Aphena | 9 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-3651-06 | NuCare | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-3658-02 | NuCare | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-3798-06 | NuCare | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-3824-06 | NuCare | 6 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-4475-02 | NuCare | 12 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68071-4533-02 | NuCare | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-4673-02 | NuCare | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 68071-5010-04 | NuCare | 4 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 68788-7835-01 | Preferred | 15 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 70518-2628-00 | REMEDYREPACK | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 70518-3705-00 | REMEDYREPACK | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 70518-4104-00 | REMEDYREPACK | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 71335-0256-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mg 71335-0545-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 71335-1522-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 71335-1818-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 71335-2916-00 | Bryant | 40 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 72162-2001-01 | Bryant | 100 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine 300 mg/1; 30 mgthis 76420-0103-30 | Asclemed | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 76420-0821-00 | Asclemed | 100 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 80425-0527-01 | Advanced | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 80425-0529-01 | Advanced | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 82804-0181-30 | Proficient | 30 tablets | — | AA | FDA listed | — |
| Acetaminophen and Codeine Phosphate 300 mg/1; 30 mg 82804-0283-20 | Proficient | 20 tablets | — | AA | FDA listed | — |
| Acetaminophen And Codeine Phosphate 300 mg/1; 30 mg 87441-0009-01 | Unit | 30 tablets | — | AA | FDA listed | — |
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- FDA Orange Book · refreshed Oct 3, 2026
- CMS NADAC weekly file
Availability & generic status
This product is an FDA-approved generic. Other versions of the same drug are listed under Therapeutic equivalents, least expensive first.
Where does this data come from?
- FDA Orange Book · refreshed Oct 3, 2026
What it looks like
Where does this data come from?
- FDA label on DailyMed · label index refreshed Oct 5, 2026
Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
Where does this data come from?
IACT rows and label-wide narrative are kept separate; availability and product-level specificity depend on the submitted label.- FDA label on DailyMed · label index refreshed Oct 5, 2026
- FDA openFDA NDC Directory · synced Oct 1, 2026
Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
Manufacturer & labeler
More NDCs from Asclemed USA, Inc. labeler code 76420
- Pregabalin 75 mg Capsule NDC 76420-097-30
- Pregabalin 100 mg Capsule NDC 76420-098-30
- Pregabalin 150 mg Capsule NDC 76420-099-30
- Pregabalin 200 mg Capsule NDC 76420-100-30
- Pregabalin 225 mg Capsule NDC 76420-101-30
- Pregabalin 300 mg Capsule NDC 76420-102-30
- Neomycin and Polymyxin B Sulfates and Hydrocortisone Neomycin Sulfate, 3.5 mg/mL; 10000 [USP'U]/mL; 10 mg/mL Solution/ Drops NDC 76420-104-10
- Tramadol Hydrochloride and Acetaminophen 37.5 mg; 325 mg Tablet, Film Coated NDC 76420-105-01
- Fluticasone Propionate 50 ug/.1g Spray, Metered NDC 76420-106-16
- Rabeprazole Sodium 20 mg Tablet, Delayed Release NDC 76420-107-30
- Phentermine hydrochloride 37.5 mg Tablet NDC 76420-108-30
- Hydrocortisone 5 mg Tablet NDC 76420-110-50
Where does this data come from?
- FDA openFDA NDC Directory · synced Oct 1, 2026
- Drugs@FDA
Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNING: ADDICTION, ABUSE, AND MISUSE; RISK EVALUATION AND MITIGATION STRATEGY (REMS); LIFE-THREATENING RESPIRATORY DEPRESSION; ACCIDENTAL INGESTION; ULTRA-RAPID METABOLISM OF CODEINE AND OTHER RISK FACTORS FOR LIFE-THREATENING RESPIRATORY DEPRESSION IN CHILDREN; NEONATAL OPIOID WITHDRAWAL SYNDROME; INTERACTIONS WITH DRUGS AFFECTING CYTOCHROME P450 ISOENZYMES; HEPATOTOXICITY; and RISKS FROM CONCOMITANT USE WITH BENZODIAZEPINES OR OTHER CNS DEPRESSANTS Addiction, Abuse and Misuse Acetaminophen and codeine phosphate tablets expose patients and other users to the risks of opioid addiction, abuse and misuse, which can lead to overdose and death.
Assess each patient’s risk prior to prescribing acetaminophen and codeine phosphate tablets, and monitor all patients regularly for the development of these behaviors and conditions (see WARNINGS ). Opioid Analgesic Risk Evaluation and Mitigation Strategy (REMS) To ensure that the benefits of opioid analgesics outweigh the risks of addiction, abuse, and misuse, the Food and Drug Administration (FDA) has required a REMS for these products (see WARNINGS ). Under the requirements of the REMS, drug companies with approved opioid analgesic products must make REMS-compliant education programs available to healthcare providers.
Healthcare providers are strongly encouraged to complete a REMS-compliant education program. counsel patients and/or their caregivers, with every prescription, on safe use, serious risks, storage, and disposal of these products. emphasize to patients and their caregivers the importance of reading the Medication Guide every time it is provided by their pharmacist. consider other tools to improve patient, household, and community safety. Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression may occur with use of acetaminophen and codeine phosphate tablets.
Monitor for respiratory depression, especially during initiation of acetaminophen and codeine phosphate tablets or following a dose increase (see WARNINGS ). Accidental Ingestion Accidental ingestion of acetaminophen and codeine phosphate tablets, especially by children, can result in a fatal overdose of acetaminophen and codeine phosphate tablets (see WARNINGS ). Ultra-Rapid Metabolism of Codeine and Other Risk Factors for Life-Threatening Respiratory Depression in Children Life-threatening respiratory depression and death have occurred in children who received codeine.
Most of the reported cases occurred following tonsillectomy and/or adenoidectomy and many of the children had evidence of being ultra-rapid metabolizers of codeine due to a CYP2D6 polymorphism (see WARNINGS , PRECAUTIONS; Information for Patients/Caregivers, Nursing Mothers ). Acetaminophen and codeine phosphate tablets are contraindicated in children younger than 12 years of age and in children younger than 18 years of age following tonsillectomy and/or adenoidectomy (see CONTRAINDICATIONS ). Avoid the use of acetaminophen and codeine phosphate tablets in adolescents 12 to 18 years of age who have other risk factors that may increase their sensitivity to the respiratory depressant effects of codeine.
Neonatal Opioid Withdrawal Syndrome Prolonged use of acetaminophen and codeine phosphate tablets during pregnancy can result in neonatal opioid withdrawal syndrome, which may be life-threatening if not recognized and treated, and requires management according to protocols developed by neonatology experts. If opioid use is required for a prolonged period in a pregnant woman, advise the patient of the risk of neonatal opioid withdrawal syndrome and ensure that appropriate treatment will be available (see WARNINGS ). Interactions with Drugs Affecting Cytochrome P450 Isoenzymes The effects of concomitant use or discontinuation of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with codeine are complex.
Use of cytochrome P450 3A4 inducers, 3A4 inhibitors, or 2D6 inhibitors with acetaminophen and codeine…
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Acetaminophen and codeine phosphate tablets are indicated for the management of mild to moderate pain, where treatment with an opioid is appropriate and for which alternative treatments are inadequate. Limitations of Use Because of the risks of addiction, abuse, and misuse, with opioids, even at recommended doses (see WARNINGS ), reserve acetaminophen and codeine phosphate tablets for use in patients for whom alternative treatment options (e.g., non-opioid analgesics). Have not provided adequate analgesia, or are not expected to provide adequate analgesia, Have not been tolerated, or are not expected to be tolerated.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION Important Dosage and Administration Instructions Use the lowest effective dosage for the shortest duration consistent with individual patient treatment goals (see WARNINGS ). Initiate the dosing regimen for each patient individually, taking into account the patient's severity of pain, patient response, prior analgesic treatment experience, and risk factors for addiction, abuse, and misuse (see WARNINGS ). Monitor patients closely for respiratory depression, especially within the first 24 to 72 hours of initiating therapy and following dosage increases with acetaminophen and codeine phosphate tablets and adjust the dosage accordingly (see WARNINGS ).
Initial Dosage Initiating Treatment with Acetaminophen and Codeine Phosphate Tablets Dosage should be adjusted according to severity of pain and response of the patient. However, it should be kept in mind that tolerance to codeine can develop with continued use and that the incidence of untoward effects is dose related. Adult doses of codeine higher than 60 mg are associated with an increased incidence of adverse reactions and are not associated with greater efficacy.
The usual adult dosage is: Acetaminophen and Codeine Phosphate Tablets (codeine 30 mg and acetaminophen 300 mg): Take 1 to 2 tablets every 4 hours as needed for pain. Single Doses (Range) Maximum 24-Hour Dose Codeine Phosphate 30 mg to 60 mg 360 mg Acetaminophen 300 mg to 1,000 mg 4,000 mg The prescriber must determine the number of tablets per dose, and the maximum number of tablets per 24 hours, based upon the above dosage guidance. This information should be conveyed in the prescription.
Conversion from Other Opioids to Acetaminophen and Codeine Phosphate Tablets There is inter-patient variability in the potency of opioid drugs and opioid formulations. Therefore, a conservative approach is advised when determining the total daily dosage of acetaminophen and codeine phosphate tablets. It is safer to underestimate a patient’s 24-hour acetaminophen and codeine phosphate tablets dosage than to overestimate the 24-hour acetaminophen and codeine phosphate tablets dosage and manage an adverse reaction due to overdose.
Titration and Maintenance of Therapy Individually titrate acetaminophen and codeine phosphate tablets to a dose that provides adequate analgesia and minimizes adverse reactions. Continually reevaluate patients receiving acetaminophen and codeine phosphate tablets to assess the maintenance of pain control and the relative incidence of adverse reactions, as well as monitoring for the development of addiction, abuse, or misuse (see WARNINGS ). Frequent communication is important among the prescriber, other members of the healthcare team, the patient, and the caregiver/family during periods of changing analgesic requirements, including initial titration.
If the level of pain increases after dosage stabilization, attempt to identify the source of increased pain before increasing the acetaminophen and codeine phosphate tablets dosage. If unacceptable opioid-related adverse reactions are observed, consider reducing the dosage. Adjust the dosage to obtain an appropriate balance between management of pain and opioid-related adverse reactions.
Safe Reduction or Discontinuation of Acetaminophen and Codeine Phosphate Tablets Do not abruptly discontinue acetaminophen and codeine phosphate tablets in patients who may be physically dependent on opioids. Rapid discontinuation of opioid analgesics in patients who are physically dependent on opioids has resulted in serious withdrawal symptoms, uncontrolled pain, and suicide. Rapid discontinuation has also been associated with attempts to find other sources of opioid analgesics, which may be confused with drug-seeking for abuse.
Patients may also attempt to treat their pain or withdrawal symptoms with illicit opioids, such as heroin, and other substances. When a decision has been made to decrease the dose or discontinue therapy in an opioid-dependent…
⛔ Contraindications ▾
CONTRAINDICATIONS Acetaminophen and codeine phosphate tablets are contraindicated for: All children younger than 12 years of age (see WARNINGS ). Post-operative management in children younger than 18 years of age following tonsillectomy and/or adenoidectomy (see WARNINGS ). Acetaminophen and codeine phosphate tablets are contraindicated in patients with: significant respiratory depression (see WARNINGS ). acute or severe bronchial asthma in an unmonitored setting or in the absence of resuscitative equipment (see WARNINGS ). concurrent use of monoamine oxidase inhibitors (MAOIs) or use of MAOIs within the last 14 days (see WARNINGS ). known or suspected gastrointestinal obstruction, including paralytic ileus (see WARNINGS ). hypersensitivity to codeine, acetaminophen, or any of the formulation excipients (e.g., anaphylaxis) (see WARNINGS ).
⚠️ Warnings ▾
WARNINGS Addiction, Abuse, and Misuse Acetaminophen and codeine phosphate tablets contain codeine. Codeine in combination with acetaminophen, is a Schedule III controlled substance. As an opioid, acetaminophen and codeine phosphate tablets expose users to the risks of addiction, abuse, and misuse (see DRUG ABUSE AND DEPENDENCE ).
Although the risk of addiction in any individual is unknown, it can occur in patients appropriately prescribed acetaminophen and codeine phosphate tablets. Addiction can occur at recommended dosages and if the drug is misused or abused. Assess each patient’s risk for opioid addiction, abuse, or misuse prior to prescribing acetaminophen and codeine phosphate tablets, and monitor all patients receiving acetaminophen and codeine phosphate tablets for the development of these behaviors and conditions.
Risks are increased in patients with a personal or family history of substance abuse (including drug or alcohol abuse or addiction) or mental illness (e.g., major depression). The potential for these risks should not, however, prevent the proper management of pain in any given patient. Patients at increased risk may be prescribed opioids such as acetaminophen and codeine phosphate tablets, but use in such patients necessitates intensive counseling about the risks and proper use of acetaminophen and codeine phosphate tablets along with intensive monitoring for signs of addiction, abuse, and misuse.
Opioids are sought by drug abusers and people with addiction disorders and are subject to criminal diversion. Consider these risks when prescribing or dispensing acetaminophen and codeine phosphate tablets. Strategies to reduce these risks include prescribing the drug in the smallest appropriate quantity and advising the patient on the proper disposal of unused drug (see PRECAUTIONS; Information for Patients/Caregivers ).
Contact local state professional licensing board or state controlled substances authority for information on how to prevent and detect abuse or diversion of this product. Opioid Analgesic Risk Evaluation and Mitigation Strategy (REMS) To ensure that the benefits of opioid analgesics outweigh the risks of addiction, abuse, and misuse, the Food and Drug Administration (FDA) has required a Risk Evaluation and Mitigation Strategy (REMS) for these products. Under the requirements of the REMS, drug companies with approved opioid analgesic products must make REMS-compliant education programs available to healthcare providers.
Healthcare providers are strongly encouraged to do all of the following: Complete a REMS-compliant education program offered by an accredited provider of continuing education (CE) or another education program that includes all the elements of the FDA Education Blueprint for Health Care Providers Involved in the Management or Support of Patients with Pain. Discuss the safe use, serious risks, and proper storage and disposal of opioid analgesics with patients and/or their caregivers every time these medicines are prescribed.
The Patient Counseling Guide (PCG) can be obtained at this link: www.fda.gov/OpioidAnalgesicREMSPCG. Emphasize to patients and their caregivers the importance of reading the Medication Guide that they will receive from their pharmacist every time an opioid analgesic is dispensed to them. Consider using other tools to improve patient, household, and community safety, such as patient-prescriber agreements that reinforce patient-prescriber responsibilities.
To obtain further information on the opioid analgesic REMS and for a list of accredited REMS CME/CE, call 800-503-0784, or log on to www.opioidanalgesicrems.com. The FDA Blueprint can be found at www.fda.gov/OpioidAnalgesicREMSBlueprint. Life-Threatening Respiratory Depression Serious, life-threatening, or fatal respiratory depression has been reported with the use of opioids, even when used as recommended.
Respiratory depression, if not immediately recognized and treated, may lead to respiratory arrest and death.…
🆘 Overdosage ▾
OVERDOSAGE Following an acute overdosage, toxicity may result from codeine or acetaminophen. Clinical Presentation Codeine Acute overdosage with codeine can be manifested by respiratory depression, somnolence progressing to stupor or coma, skeletal muscle flaccidity, cold and clammy skin, constricted pupils, and, in some cases, pulmonary edema, bradycardia, hypotension, partial or complete airway obstruction, atypical snoring, and death. Marked mydriasis rather than miosis may be seen with hypoxia in overdose situations.
Acetaminophen Dose-dependent, potentially fatal hepatic necrosis is the most serious adverse effect of acetaminophen overdose. Renal tubular necrosis, hypoglycemic coma, and coagulation defects may also occur. Early symptoms following a potentially hepatotoxic overdose may include; anorexia, nausea, vomiting, diaphoresis, pallor and general malaise.
Clinical and laboratory evidence of hepatic toxicity may not be apparent until 48 to 72 hours post-ingestion. Treatment of Overdose Codeine In case of overdose, priorities are the reestablishment of a patent and protected airway and institution of assisted or controlled ventilation, if needed. Employ other supportive measures (including oxygen and vasopressors) in the management of circulatory shock and pulmonary edema as indicated.
Cardiac arrest or serious arrhythmias will require advanced life-support measures. The opioid antagonists, naloxone or nalmefene, are specific antidotes to respiratory depression resulting from opioid overdose. For clinically significant respiratory or circulatory depression secondary to acetaminophen and codeine overdose, administer an opioid antagonist.
Opioid antagonists should not be administered in the absence of clinically significant respiratory or circulatory depression secondary to codeine overdose. Because the duration of opioid reversal is expected to be less than the duration of action of codeine in acetaminophen and codeine phosphate tablets, carefully monitor the patient until spontaneous respiration is reliably reestablished. If the response to an opioid antagonist is suboptimal or only brief in nature, administer additional antagonist as directed by the product’s prescribing information.
In an individual physically dependent on opioids, administration of the recommended usual dosage of the antagonist will precipitate an acute withdrawal syndrome. The severity of the withdrawal symptoms experienced will depend on the degree of physical dependence and the dose of the antagonist administered. If a decision is made to treat serious respiratory depression in the physically dependent patient, administration of the antagonist should be begun with care and by titration with smaller than usual doses of the antagonist.
Acetaminophen Gastric decontamination with activated charcoal should be administered just prior to N-acetylcysteine (NAC) to decrease systemic absorption if acetaminophen ingestion is known or suspected to have occurred within a few hours of presentation. Serum acetaminophen levels should be obtained immediately if the patient presents 4 hours or more after ingestion to assess potential risk of hepatotoxicity; acetaminophen levels drawn less than 4 hours post-ingestion may be misleading. To obtain the best possible outcome, (NAC) should be administered as soon as possible where impending or evolving liver injury is suspected.
Intravenous NAC may be administered when circumstances preclude oral administration. Vigorous supportive therapy is required in severe intoxication. Procedures to limit the continuing absorption of the drug must be readily performed since the hepatic injury is dose-dependent and occurs early in the course of intoxication.
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY Mechanism of Action Codeine is an opioid agonist relatively selective for the mu-opioid receptor, but with a much weaker affinity than morphine. The analgesic properties of codeine have been speculated to come from its conversion to morphine, although the exact mechanism of analgesic action remains unknown. The precise mechanism of the analgesic properties of acetaminophen is not established but is thought to involve central actions.
Pharmacodynamics Effects on the Central Nervous System Codeine produces respiratory depression by direct action on brain stem respiratory centers. The respiratory depression involves a reduction in the responsiveness of the brain stem respiratory centers to both increases in carbon dioxide tension and electrical stimulation. Codeine causes miosis, even in total darkness.
Pinpoint pupils are a sign of opioid overdose but are not pathognomonic (e.g., pontine lesions of hemorrhagic or ischemic origins may produce similar findings). Marked mydriasis rather than miosis may be seen due to hypoxia in overdose situations. Effects on the Gastrointestinal Tract and Other Smooth Muscle Codeine causes a reduction in motility associated with an increase in smooth muscle tone in the antrum of the stomach and duodenum.
Digestion of food in the small intestine is delayed and propulsive contractions are decreased. Propulsive peristaltic waves in the colon are decreased, while tone may be increased to the point of spasm, resulting in constipation. Other opioid-induced effects may include a reduction in biliary and pancreatic secretions, spasm of sphincter of Oddi, and transient elevations in serum amylase.
Effects on the Cardiovascular System Codeine produces peripheral vasodilation which may result in orthostatic hypotension or syncope. Manifestations of histamine release and/or peripheral vasodilation may include pruritus, flushing, red eyes, sweating, and/or orthostatic hypotension. Effects on the Endocrine System Opioids inhibit the secretion of adrenocorticotropic hormone (ACTH), cortisol, and luteinizing hormone (LH) in humans (see ADVERSE REACTIONS ).
They also stimulate prolactin, growth hormone (GH) secretion, and pancreatic secretion of insulin and glucagon. Chronic use of opioids may influence the hypothalamic-pituitary-gonadal axis, leading to androgen deficiency that may manifest as low libido, impotence, erectile dysfunction, amenorrhea, or infertility. The causal role of opioids in the clinical syndrome of hypogonadism is unknown because the various medical, physical, lifestyle, and psychological stressors that may influence gonadal hormone levels have not been adequately controlled for in studies conducted to date (see ADVERSE REACTIONS ).
Effects on the Immune System Opioids have been shown to have a variety of effects on components of the immune system. The clinical significance of these findings is unknown. Overall, the effects of opioids appear to be modestly immunosuppressive.
Concentration–Efficacy Relationships The minimum effective analgesic concentration will vary widely among patients, especially among patients who have been previously treated with potent agonist opioids. The minimum effective analgesic concentration of codeine for any individual patient may increase over time due to an increase in pain, the development of a new pain syndrome, and/or the development of analgesic tolerance (see DOSAGE AND ADMINISTRATION ). Concentration–Adverse Reaction Relationships There is a relationship between increasing codeine plasma concentration and increasing frequency of dose-related opioid adverse reactions such as nausea, vomiting, CNS effects, and respiratory depression.
In opioid-tolerant patients, the situation may be altered by the development of tolerance to opioid-related adverse reactions (see DOSAGE AND ADMINISTRATION ). Pharmacokinetics The behavior of the individual components is described below. Codeine Codeine is rapidly absorbed from the gastrointestinal tract…
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Acetaminophen and Codeine Phosphate Tablets, USP, 300 mg/30 mg are white, round, flat, beveled edged tablets debossed “IP 33” on obverse and “3” on reverse. They are available as follows: Bottles of 3: NDC 76420-103-03 (repackaged from NDC 65162-033-xx) Bottles of 10: NDC 76420-103-10 (repackaged from NDC 65162-033-xx) Bottles of 20: NDC 76420-103-20 (repackaged from NDC 65162-033-xx) Bottles of 30: NDC 76420-103-30 (repackaged from NDC 65162-033-xx) Store Acetaminophen and Codeine Phosphate Tablets, USP 300 mg/30 mg between 20° to 25°C (68° to 77°F) [see USP Controlled Room Temperature].
Dispense in tight, light-resistant container as defined in the USP. Store acetaminophen and codeine phosphate tablets securely and dispose of properly (see PRECAUTIONS ; Information for Patients/ Caregivers ). Repackaged by: Enovachem PHARMACEUTICALS Torrance, CA 90501
📋 Description ▾
DESCRIPTION Acetaminophen and codeine phosphate tablets, USP are supplied in tablet form for oral administration. Acetaminophen, 4'-hydroxyacetanilide, a slightly bitter, white, odorless, crystalline powder, is a non-opiate, non-salicylate analgesic and antipyretic. It has the following structural formula: Codeine phosphate, 7,8-didehydro-4, 5α-epoxy-3-methoxy-17-methylmorphinan-6α-ol phosphate (1:1) (salt) hemihydrate, a white crystalline powder, is a narcotic analgesic and antitussive.
It has the following structural formula: Each Acetaminophen and Codeine Phosphate Tablet, USP (300 mg/30 mg) contains: Acetaminophen .................................................. 300 mg Codeine Phosphate .............................................. 30 mg In addition, each acetaminophen and codeine phosphate tablet, USP contains the following inactive ingredients: croscarmellose sodium, crospovidone, lactose monohydrate, magnesium stearate, microcrystalline cellulose, povidone, pregelatinized starch and stearic acid.
1 2
Reported adverse events (FAERS)
Top reported reactions
Reporter sex
Serious outcomes
Where does this data come from?
About this NDC listing & data coverage
What data is (and isn’t) available for this NDC — tap to expand
| NDC identity (package / product / labeler codes) | ✓ Available |
| Labeler | ✓ Available |
| Product & package description | ✓ Available |
| Marketing category & status | ✓ Available |
| Active ingredient / dosage form / route | ✓ Available |
| FDA label (SPL via DailyMed) | ✓ Available |
| Package photos | ✓ Available |
| Inactive ingredients (structured) | — Not published for this NDC The labeler did not submit a structured excipient list, or no SPL is available. |
| NADAC pharmacy acquisition price (CMS) | — Not published for this NDC CMS publishes NADAC only for NDCs reported in its retail-pharmacy survey. |
| Orange Book / therapeutic-equivalence data | ✓ Available |
| HCPCS J-code billing crosswalk | — Not published for this NDC Most self-administered / retail products have no J-code — that is normal. |
| Medicaid utilization (CMS SDUD) | — Not published for this NDC CMS reports utilization only for NDCs with Medicaid claims above its privacy threshold. |