
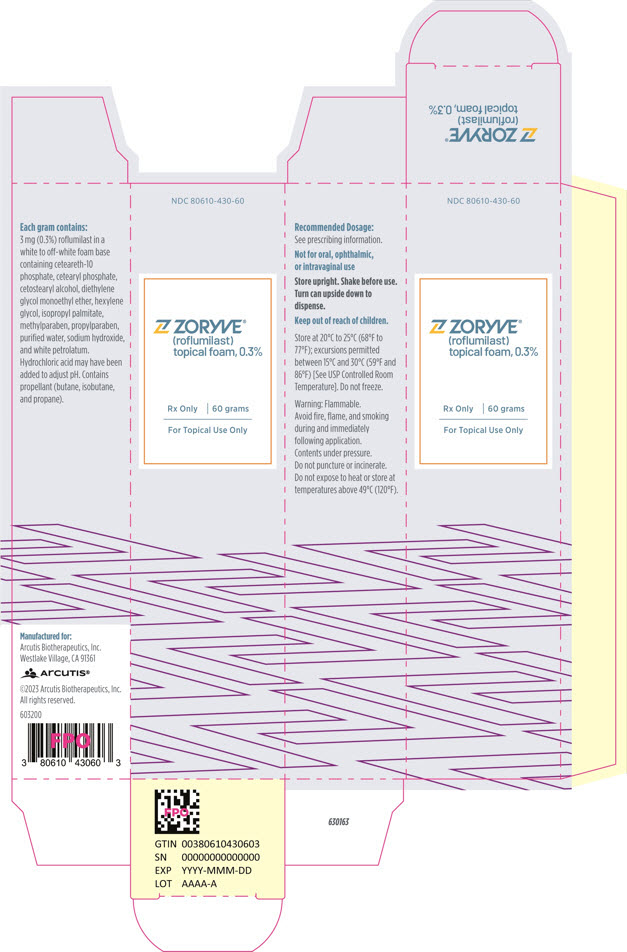
ZORYVE roflumilast 3 mg/g Aerosol, Foam
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Phosphodiesterase 4 Inhibitor class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- That depends on the form you have. The tablet (sold as Daliresp or generic roflumilast) is used to help prevent flare-ups in people with severe COPD tied to chronic bronchitis — it...
- No — and this is really important. Roflumilast tablets do not open up the airways, so they won't help during a sudden COPD flare or breathing emergency. You need a separate rescue...
- Can I use the COPD tablet during a sudden breathing attack?
- This is a real concern worth taking seriously. Roflumilast tablets have been linked to depression, anxiety, trouble sleeping, and in rare cases suicidal thoughts or behavior. It do...
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Roflumilast — tap one for details:
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII 6LV4FOR43R
Butane is a colorless gas derived from petroleum. In medicines, it serves as a propellant in inhalers and aerosol sprays, helping deliver the active drug to the lungs or skin.
-
UNII 099WOY1SA3
A synthetic emulsifier and solubilizer derived from cetyl and stearyl alcohols. It helps blend oil and water-based ingredients together and improves how medicines dissolve or spread in formulations.
-
UNII 4O6GCK4CTJ
A waxy substance derived from plant or animal oils that acts as an emulsifier and thickener. It helps blend water and oil ingredients together and gives the product a smooth, stable texture.
-
UNII 2DMT128M1S
A waxy solid derived from plant or animal sources. It acts as an emulsifier to blend oil and water components, and also thickens the medicine to give it the right texture and consistency.
-
UNII A1A1I8X02B
A clear liquid solvent derived from ethylene glycol. It helps dissolve active ingredients and improve how the medicine flows and mixes in liquid formulations.
-
UNII KEH0A3F75J
Hexylene glycol is a clear liquid alcohol used as a solvent and preservative in medicines. It helps dissolve other ingredients and keeps the product stable during storage.
-
UNII QTT17582CB
A strong acid used to adjust and maintain the proper pH level in liquid medicines, ensuring stability and preventing breakdown of active ingredients.
-
UNII BXR49TP611
Isobutane is a liquefied gas used as a propellant in aerosol inhalers and sprays. It helps push the medicine out of the container so you can breathe or spray it as directed.
-
UNII 8CRQ2TH63M
Isopropyl palmitate is an oily liquid derived from palm oil. It acts as an emollient and lubricant in medicines, helping soften the skin or improve how the product spreads and flows.
-
UNII A2I8C7HI9T
Methylparaben is a preservative derived from benzoic acid that prevents growth of bacteria, fungi, and mold in medicines. It extends the product's shelf life and maintains safety during storage.
-
UNII T75W9911L6
A flammable gas used as a propellant in aerosol formulations. It helps dispense the medicine as a fine mist or spray when you activate the inhaler or pump.
-
UNII Z8IX2SC1OH
Propylparaben is a chemical preservative used to prevent bacterial and fungal growth in medicines and personal care products. It helps extend shelf life and maintain product safety during storage.
-
UNII 55X04QC32I
A strong alkaline chemical used to adjust and maintain the pH balance of liquid medicines. It helps keep the medicine stable and ensures it stays effective during storage.
-
UNII 059QF0KO0R
Water is a liquid solvent that dissolves and mixes ingredients together in liquid medicines, syrups, and injections. It helps distribute the active drug evenly throughout the product.
-
UNII B6E5W8RQJ4
White petrolatum is a purified mineral oil product used as a lubricant and skin protectant in medications. It helps pills slide through manufacturing equipment and can soften or protect the skin when applied topically.
15 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per g | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $15.378 | $922.66 / 60 g |
| Medicaid paysCMS SDUD · 12 mo | $14.88 | $892.75 / 60 g |
| Medicare drug plans payPart D · Q2 2026 | $16.23 | $973.77 / 60 g |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Zoryve 3 mg/gthis 80610-0430-60 | Arcutis | 1 can | $15.378 | — | Availability likely | — |
Where does this data come from?
⏳ Availability & generic status
We did not find an FDA-approved generic match for this exact strength, form and route. Patent/protection dates below may affect future generic timing.
Why the date isn’t exact: Generic timing can change because patents may be challenged, settled, licensed, added, removed, or worked around with a narrower label — and FDA approval does not always mean a pharmacy can get the generic today.
🛈 What do these terms mean?
- Patent
- Legal protection listed in the Orange Book that may delay generic approval or launch. Issued by the U.S. Patent & Trademark Office.
- Substance patent
- Covers the active drug molecule itself — the hardest to design around. A generic generally can’t launch until it expires.
- Formulation (product) patent
- Covers a specific formulation or dosage form. A generic can sometimes work around it with a different formulation.
- Method-of-use patent
- A patent covering one specific approved use of the drug — not necessarily the whole molecule. A generic can sometimes launch with a “skinny label” that carves out the protected use and keeps the others.
- Skinny label
- A generic label that omits a still-patented use when the FDA allows it — letting a generic reach the market for the unprotected uses.
- Exclusivity
- FDA-granted marketing protection, separate from patents — e.g. 5-yr new chemical entity, 7-yr orphan drug, or a +6-month pediatric extension.
- Paragraph IV
- A generic applicant’s formal challenge to a listed patent. It can potentially lead to earlier generic entry, but often involves litigation or a settlement.
- RLD / RS
- Reference Listed Drug — the brand product the FDA uses as the reference for generic applications. Reference Standard — the product the FDA expects generics to compare against in bioequivalence testing.
- TE / AB rating
- FDA therapeutic-equivalence rating. An AB rating generally means the FDA considers a generic therapeutically equivalent to — and substitutable for — the brand.
- LOE (loss of exclusivity)
- The latest patent or exclusivity currently listed — the loss-of-exclusivity / latest-listed-protection date shown on this page. Paragraph-IV challenges and settlements can move the real date earlier; FDA approval and a manufacturer’s decision to market can move it later.
Built from the FDA Orange Book. The bars above are scaled to each protection’s expiry; the red LOE marker is the last one to lapse.
| Patent | Type | Use code | Expires |
|---|---|---|---|
| US 9907788 ↗ | Method of use | U-4203 | Jun 7, 2037 |
| US 11129818 ↗ | Method of use | U-4203 | Aug 25, 2037 |
| US 11819496 ↗ | Method of use | U-4203 | Jun 7, 2037 |
| US 11992480 ↗ | Method of use | U-4203 | Jun 7, 2037 |
| US 12005051 ↗ | Method of use | U-4203 | Jun 7, 2037 |
| US 12310956 ↗ | Method of use | U-3773 | Jun 7, 2037 |
| US 12310956 ↗ | Method of use | U-4203 | Jun 7, 2037 |
| US 12329751 ↗ | Method of use | U-3773 | Dec 3, 2041 |
| US 11992480 ↗ | Method of use | U-3773 | Jun 7, 2037 |
| US 12005051 ↗ | Method of use | U-3773 | Jun 7, 2037 |
| US 11129818 ↗ | Method of use | U-3773 | Aug 25, 2037 |
| US 9907788 ↗ | Method of use | U-3773 | Jun 7, 2037 |
| US 11707454 ↗ | Method of use | U-3773 | Dec 3, 2041 |
| US 11819496 ↗ | Method of use | U-3773 | Jun 7, 2037 |
| US 12011437 ↗ | Drug product | — | Jun 7, 2037 |
| US 12016848 ↗ | Drug product | — | Jun 7, 2037 |
| US 12453721 ↗ | Drug product | — | Aug 19, 2042 |
| US 12005052 ↗ | Drug product | — | Jun 7, 2037 |
| US 12257242 ↗ | Drug product | — | Jun 7, 2037 |
| US 12336983 ↗ | Drug product | — | Jun 7, 2037 |
| US 12220409 ↗ | Drug product | — | Jun 7, 2037 |
| US 12042487 ↗ | Drug product | — | Jun 7, 2037 |
| US 9884050 ↗ | Drug product | — | Jun 7, 2037 |
| US 10940142 ↗ | Drug product | — | Jun 7, 2037 |
| US 11793796 ↗ | Drug product | — | Jun 7, 2037 |
| US 12390453 ↗ | Drug product | — | Jun 7, 2037 |
| Code | What it grants | Expires |
|---|---|---|
| I-969 | New indication (3-year) | May 22, 2028 |
| NP | New Product | Dec 15, 2026 |
Is there a generic version of ZORYVE 0.3% FOAM?
The FDA approved a generic — why can’t I get it at my pharmacy yet?
Why do different websites show different generic release dates?
What does “FDA listed” mean?
What does a patent or protection date mean here?
What does “current Orange Book estimate” mean?
Can a generic come out before the last patent expires?
Can a generic come out after the listed dates?
What is the difference between patents and exclusivity?
Why are there multiple patent dates?
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
🔬 Reported adverse events (FAERS)
Top reported reactions
Age at onset
Reporter sex
Serious outcomes
Where does this data come from?
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 80610-0430-60 You're viewing this | 1 CAN in 1 CARTON (80610-430-60) / 60 g in 1 CAN | 2023-12-15 | Active |
📄 Full prescribing information FDA SPL
🎯 Indications and Usage ▾
1 INDICATIONS AND USAGE ZORYVE topical foam, 0.3%, is a phosphodiesterase 4 inhibitor indicated for the treatment of seborrheic dermatitis in adult and pediatric patients 9 years of age and older. ( 1.1 ) plaque psoriasis of the scalp and body in adult and pediatric patients 12 years of age and older. ( 1.2 )
1.1Seborrheic Dermatitis ZORYVE ® topical foam, 0.3%, is indicated for the treatment of seborrheic dermatitis in adult and pediatric patients 9 years of age and older.
1.2Plaque Psoriasis ZORYVE topical foam, 0.3%, is indicated for the treatment of plaque psoriasis of the scalp and body in adult and pediatric patients 12 years of age and older.
⏱️ Dosage and Administration ▾
2 DOSAGE AND ADMINISTRATION Shake can prior to each use. Apply a thin layer of ZORYVE foam, 0.3%, once daily to affected areas of body and/or scalp when they are not wet. Rub in completely.
Wash hands after application. Avoid fire, flame, and smoking during and immediately following application [see Warnings and Precautions (5.1) ] . ZORYVE foam, 0.3%, is for topical use only and not for ophthalmic, oral, or intravaginal use.
Apply once daily to affected areas. ( 2 ) For topical use only. Not for ophthalmic, oral, or intravaginal use.
( 2 )
💊 Dosage Forms and Strengths ▾
3 DOSAGE FORMS AND STRENGTHS Topical foam, 0.3%: 3 mg of roflumilast per gram of white to off-white foam in 60-gram pressurized cans. Topical foam, 0.3%: 3 mg of roflumilast per gram in 60-gram pressurized cans. ( 3 )
⛔ Contraindications ▾
4 CONTRAINDICATIONS ZORYVE foam, 0.3%, is contraindicated in patients with moderate to severe liver impairment (Child-Pugh B or C) [see Use in Specific Populations (8.6) , Clinical Pharmacology (12.3) ] . Moderate to severe liver impairment (Child-Pugh B or C). ( 4 )
⚠️ Warnings and Cautions ▾
5 WARNINGS AND PRECAUTIONS Flammability : The propellants in ZORYVE foam, 0.3%, are flammable. Avoid fire, flame, and smoking during and immediately following application. ( 5.1 )
5.1Flammability The propellants in ZORYVE foam, 0.3%, are flammable. Avoid fire, flame, and smoking during and immediately following application.
🤒 Adverse Reactions ▾
6 ADVERSE REACTIONS The most common adverse reactions (reported in ≥ 1% of patients) are: Seborrheic dermatitis : nasopharyngitis, nausea, and headache. ( 6.1 ) Plaque psoriasis of the scalp and body : headache, diarrhea, nausea, and nasopharyngitis. ( 6.1 ) To report SUSPECTED ADVERSE REACTIONS, contact Arcutis Biotherapeutics, Inc. at 1-844-692-6729 or FDA at 1-800-FDA-1088 or www.fda.gov/medwatch.
6.1Clinical Trials Experience Because clinical trials are conducted under widely varying conditions, adverse reaction rates observed in the clinical trials of a drug cannot be directly compared to rates in the clinical trials of another drug and may not reflect the rates observed in practice. Seborrheic Dermatitis In two multicenter, randomized, double-blind, vehicle-controlled trials (Trial 203 and STRATUM), 683 adult and pediatric subjects 9 years of age or older with seborrheic dermatitis were treated with ZORYVE foam, 0.3%, or vehicle foam once daily for 8 weeks [see Clinical Studies (14.1) ].
Table 1 presents adverse reactions that occurred in at least 1% of subjects treated with ZORYVE foam, 0.3%. Table 1: Adverse Reactions Reported in ≥1% of Adult and Pediatric Subjects 9 Years of Age and Older with Seborrheic Dermatitis Treated with ZORYVE Foam, 0.3%, for 8 Weeks in Trial 203 and Trial STRATUM Adverse Reaction ZORYVE foam, 0.3% (N=458) n (%) Vehicle foam (N=225) n (%) Nasopharyngitis 7 (1.5) 1 (0.4) Nausea 6 (1.3) 0 (0) Headache 5 (1.1) 0 (0) The following additional adverse reactions were reported in fewer than 1% of subjects treated with ZORYVE foam, 0.3%: diarrhea and insomnia.
The adverse reaction profile in pediatric subjects was consistent with that observed in adults [see Use in Specific Populations (8.4) , Clinical Pharmacology (12.3) ] . In 408 subjects who continued treatment with ZORYVE foam, 0.3%, for up to 24 to 52 weeks in an open-label, long-term trial, the adverse reaction profile was consistent with that observed in vehicle-controlled trials. Plaque Psoriasis In two multicenter, randomized, double-blind, vehicle-controlled trials (Trial 204 and ARRECTOR), 734 adult and pediatric subjects 12 years of age and older with plaque psoriasis of the scalp and body were treated with ZORYVE foam, 0.3%, or vehicle foam once daily for 8 weeks [see Clinical Studies (14.2) ].
Table 2 presents adverse reactions that occurred in at least 1% of subjects treated with ZORYVE foam, 0.3%. Table 2: Adverse Reactions Reported in ≥1% of Adult and Pediatric Subjects 12 Years of Age and Older with Plaque Psoriasis of the Scalp and Body Treated with ZORYVE Foam, 0.3%, for 8 Weeks in Trial 204 and Trial ARRECTOR Adverse Reaction ZORYVE foam, 0.3% (N=479) n (%) Vehicle foam (N=255) n (%) Headache 15 (3.1) 3 (1.2) Diarrhea 12 (2.5) 4 (1.6) Nausea 8 (1.7) 0 (0) Nasopharyngitis 6 (1.3) 2 (0.8) The following additional adverse reaction was reported in fewer than 1% of subjects treated with ZORYVE foam, 0.3%: insomnia.
The adverse reaction profile in pediatric subjects was consistent with that observed in adults [see Use in Specific Populations (8.4) , Clinical Pharmacology (12.3) ] .
🔄 Drug Interactions ▾
7 DRUG INTERACTIONS Co-administration of roflumilast with systemic CYP3A4 inhibitors or dual inhibitors that inhibit both CYP3A4 and CYP1A2 simultaneously may increase roflumilast systemic exposure and may result in increased adverse reactions. If these products are co-administered with ZORYVE foam, 0.3%, weigh the potential for increased adverse reactions against benefit. ( 7.1 ) Co-administration of roflumilast with oral contraceptives containing gestodene and ethinyl estradiol may increase roflumilast systemic exposure and may result in increased adverse reactions.
If these products are co-administered with ZORYVE foam, 0.3%, weigh the potential for increased adverse reactions against benefit. ( 7.1 )
7.1Effects of Other Drugs on ZORYVE Foam, 0.3% Drugs that Inhibit Cytochrome P450 (CYP) Enzymes No formal drug-drug interaction studies were conducted with ZORYVE foam, 0.3%; however, the co-administration of oral roflumilast with systemic CYP3A4 inhibitors or dual inhibitors that inhibit both CYP3A4 and CYP1A2 simultaneously may increase roflumilast systemic exposure and may result in increased adverse reactions. If these products are co-administered with ZORYVE foam, 0.3%, weigh the potential for increased adverse reactions against benefit [see Clinical Pharmacology (12.3) ] .
Oral Contraceptives Containing Gestodene and Ethinyl Estradiol The co-administration of roflumilast with oral contraceptives containing gestodene and ethinyl estradiol may increase roflumilast systemic exposure and may result in increased adverse reactions. If these products are co-administered with ZORYVE foam, 0.3%, weigh the potential for increased adverse reactions against benefit [see Clinical Pharmacology (12.3) ] .
👥 Use in Specific Populations ▾
8 USE IN SPECIFIC POPULATIONS
8.1Pregnancy Risk Summary There are insufficient data available on the use of ZORYVE foam, 0.3%, in pregnant women to inform a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In animal reproduction studies, roflumilast administered orally to pregnant rats and rabbits during the period of organogenesis produced no fetal structural abnormalities at doses up to 21 and 18 times the maximum recommended human dose (MRHD), respectively. Roflumilast induced post-implantation loss in rats at oral doses greater than or equal to 7 times the MRHD.
Roflumilast induced stillbirth and decreased pup viability in mice at oral doses 11 and 34 times the MRHD, respectively. Roflumilast has been shown to adversely affect pup post-natal development when dams were treated with an oral dose 34 times the MRHD during pregnancy and lactation periods in mice (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Labor and delivery Avoid using ZORYVE foam, 0.3%, during labor and delivery. There are no human studies that have investigated effects of ZORYVE foam, 0.3%, on preterm labor or labor at term; however, animal studies showed that oral roflumilast disrupted the labor and delivery process in mice.
Data Animal data In an embryo-fetal development study, pregnant rats were dosed orally during the period of organogenesis with up to 1.8 mg/kg/day roflumilast (21 times the MRHD on a mg/m 2 basis). No evidence of structural abnormalities or effects on survival rates were observed. Roflumilast did not affect embryo-fetal development at a maternal oral dose of 0.2 mg/kg/day (2 times the MRHD on a mg/m 2 basis).
In a fertility and embryo-fetal development study, male rats were dosed orally with up to 1.8 mg/kg/day roflumilast for 10 weeks and females for 2 weeks prior to pairing and throughout the organogenesis period. Roflumilast induced pre- and post-implantation loss at maternal oral doses greater than or equal to 0.6 mg/kg/day (7 times the MRHD on a mg/m 2 basis). Roflumilast did not cause fetal structural abnormalities at maternal oral doses up to 1.8 mg/kg/day (20 times the MRHD on a mg/m 2 basis).
In an embryo-fetal development study in rabbits, pregnant does were dosed orally with 0.8 mg/kg/day roflumilast during the period of organogenesis. Roflumilast did not cause fetal structural abnormalities at the maternal oral doses of 0.8 mg/kg/day (18 times the MRHD on a mg/m 2 basis). In pre- and post-natal developmental studies in mice, dams were dosed orally with up to 12 mg/kg/day roflumilast during the period of organogenesis and lactation.
Roflumilast induced stillbirth and decreased pup viability at maternal oral doses greater than 2 mg/kg/day and 6 mg/kg/day, respectively (11 and 34 times the MRHD on a mg/m 2 basis, respectively). Roflumilast induced delivery retardation in pregnant mice at maternal oral doses greater than 2 mg/kg/day (11 times the MRHD on a mg/m 2 basis). Roflumilast decreased pup rearing frequencies at a maternal oral dose of 6 mg/kg/day during pregnancy and lactation (34 times the MRHD on a mg/m 2 basis).
Roflumilast also decreased survival and forelimb grip reflex and delayed pinna detachment in mouse pups at a maternal oral dose of 12 mg/kg/day (68 times the MRHD on a mg/m 2 basis).
8.2Lactation Risk Summary There are no data on the presence of roflumilast or its metabolite in human milk, the effects on the breastfed infant, or the effects on milk production. Roflumilast and/or its metabolites are excreted into the milk of lactating rats (see Data ) . When a drug is present in animal milk, it is likely that the drug will be present in human milk. The developmental and health benefits of…
🤰 Pregnancy ▾
8.1Pregnancy Risk Summary There are insufficient data available on the use of ZORYVE foam, 0.3%, in pregnant women to inform a drug-associated risk of major birth defects, miscarriage, or other adverse maternal or fetal outcomes. In animal reproduction studies, roflumilast administered orally to pregnant rats and rabbits during the period of organogenesis produced no fetal structural abnormalities at doses up to 21 and 18 times the maximum recommended human dose (MRHD), respectively. Roflumilast induced post-implantation loss in rats at oral doses greater than or equal to 7 times the MRHD.
Roflumilast induced stillbirth and decreased pup viability in mice at oral doses 11 and 34 times the MRHD, respectively. Roflumilast has been shown to adversely affect pup post-natal development when dams were treated with an oral dose 34 times the MRHD during pregnancy and lactation periods in mice (see Data ) . The background risk of major birth defects and miscarriage for the indicated population is unknown.
In the U.S. general population, the estimated background risk of major birth defects and miscarriage in clinically recognized pregnancies is 2% to 4% and 15% to 20%, respectively. Clinical Considerations Labor and delivery Avoid using ZORYVE foam, 0.3%, during labor and delivery. There are no human studies that have investigated effects of ZORYVE foam, 0.3%, on preterm labor or labor at term; however, animal studies showed that oral roflumilast disrupted the labor and delivery process in mice.
Data Animal data In an embryo-fetal development study, pregnant rats were dosed orally during the period of organogenesis with up to 1.8 mg/kg/day roflumilast (21 times the MRHD on a mg/m 2 basis). No evidence of structural abnormalities or effects on survival rates were observed. Roflumilast did not affect embryo-fetal development at a maternal oral dose of 0.2 mg/kg/day (2 times the MRHD on a mg/m 2 basis).
In a fertility and embryo-fetal development study, male rats were dosed orally with up to 1.8 mg/kg/day roflumilast for 10 weeks and females for 2 weeks prior to pairing and throughout the organogenesis period. Roflumilast induced pre- and post-implantation loss at maternal oral doses greater than or equal to 0.6 mg/kg/day (7 times the MRHD on a mg/m 2 basis). Roflumilast did not cause fetal structural abnormalities at maternal oral doses up to 1.8 mg/kg/day (20 times the MRHD on a mg/m 2 basis).
In an embryo-fetal development study in rabbits, pregnant does were dosed orally with 0.8 mg/kg/day roflumilast during the period of organogenesis. Roflumilast did not cause fetal structural abnormalities at the maternal oral doses of 0.8 mg/kg/day (18 times the MRHD on a mg/m 2 basis). In pre- and post-natal developmental studies in mice, dams were dosed orally with up to 12 mg/kg/day roflumilast during the period of organogenesis and lactation.
Roflumilast induced stillbirth and decreased pup viability at maternal oral doses greater than 2 mg/kg/day and 6 mg/kg/day, respectively (11 and 34 times the MRHD on a mg/m 2 basis, respectively). Roflumilast induced delivery retardation in pregnant mice at maternal oral doses greater than 2 mg/kg/day (11 times the MRHD on a mg/m 2 basis). Roflumilast decreased pup rearing frequencies at a maternal oral dose of 6 mg/kg/day during pregnancy and lactation (34 times the MRHD on a mg/m 2 basis).
Roflumilast also decreased survival and forelimb grip reflex and delayed pinna detachment in mouse pups at a maternal oral dose of 12 mg/kg/day (68 times the MRHD on a mg/m 2 basis).
🧒 Pediatric Use ▾
8.4Pediatric Use Seborrheic Dermatitis The safety and effectiveness of ZORYVE topical foam, 0.3%, for the treatment of seborrheic dermatitis have been established in pediatric patients 9 years of age and older. Use of ZORYVE foam, 0.3%, in this age group is supported by data from two 8-week, vehicle-controlled trials which included 32 subjects 9 to 17 years of age, of whom 17 received ZORYVE foam, 0.3%, and from open-label trials of up to 52 weeks which included 23 pediatric subjects treated with ZORYVE foam, 0.3% [see Adverse Reactions (6.1) , Clinical Pharmacology (12.3) , Clinical Studies (14) ] .
The safety and effectiveness of ZORYVE foam, 0.3%, in pediatric patients below the age of 9 years have not been established. Plaque Psoriasis The safety and effectiveness of ZORYVE topical foam, 0.3%, for the treatment of plaque psoriasis of the scalp and body have been established in pediatric patients 12 years of age and older. Use of ZORYVE foam, 0.3%, in this age group is supported by data from two 8-week, vehicle-controlled trials which included 12 subjects 12 to 17 years of age, of whom 8 received ZORYVE foam, 0.3%.
Use of ZORYVE foam, 0.3%, in pediatric patients 12 years of age and older is also supported by data from an open-label trial of 8 weeks duration which included 7 subjects 12 to 17 years of age treated with ZORYVE foam, 0.3%. The safety and effectiveness of ZORYVE foam, 0.3%, in pediatric patients below the age of 12 years with plaque psoriasis have not been established.
🧓 Geriatric Use ▾
8.5Geriatric Use Seborrheic Dermatitis Of the 683 subjects with seborrheic dermatitis exposed to ZORYVE foam, 0.3%, or vehicle for up to 8 weeks in the controlled clinical trials, 98 (14%) were 65 years of age or older, and 33 (5%) were 75 years of age or older. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
Plaque Psoriasis Of the 734 subjects with plaque psoriasis of the scalp and body exposed to ZORYVE foam, 0.3%, or vehicle for up to 8 weeks in the controlled clinical trials, 82 (11%) were 65 years of age or older, and 21 (3%) were 75 years of age or older. No overall differences in safety or effectiveness were observed between these subjects and younger subjects, and other reported clinical experience has not identified differences in responses between the elderly and younger patients, but greater sensitivity of some older individuals cannot be ruled out.
🧬 Clinical Pharmacology ▾
12 CLINICAL PHARMACOLOGY
12.1Mechanism of Action Roflumilast and its active metabolite (roflumilast N-oxide) are inhibitors of PDE4. Roflumilast and roflumilast N-oxide inhibition of PDE4 (a major cyclic 3′,5′-adenosine monophosphate (cyclic AMP) metabolizing enzyme) activity leads to accumulation of intracellular cyclic AMP. The specific mechanism(s) by which roflumilast exerts its therapeutic action is not well defined.
12.2Pharmacodynamics Pharmacodynamics of ZORYVE foam, 0.3%, in the treatment of seborrheic dermatitis and plaque psoriasis is unknown.
12.3Pharmacokinetics Absorption Seborrheic Dermatitis The pharmacokinetics of ZORYVE foam, 0.3%, was investigated in 10 adult and 10 pediatric (11 to 16 years of age) subjects with seborrheic dermatitis. In this study, a mean dose of approximately 4.1 g of ZORYVE foam, 0.3%, was applied once daily for 15 days to a mean ± SD body surface area (BSA) involvement of 6.5 ± 1.08% and 5.5 ± 1.27% in adult and pediatric subjects, respectively. Plasma concentrations of roflumilast were quantifiable in all but two subjects at Day 15.
Plasma concentrations of roflumilast N-oxide were quantifiable in all subjects at Day 15. Following application of ZORYVE foam, 0.3%, the plasma concentration versus time profile was relatively flat, with mean peak-to-trough ratios of 1.68 and 1.62 for roflumilast and roflumilast N-oxide, respectively. In adults, the mean ± SD maximum concentration (C max ) was 2.2 ± 1.6 and 13.8 ± 9.0 ng/mL for roflumilast and the N-oxide metabolite, respectively.
The mean ± SD systemic exposure (AUC 0-24 ) was 36.6 ± 23.7 and 261 ± 190 h∙ng/mL for roflumilast and the N-oxide metabolite, respectively. In pediatric subjects, the extrapolated mean ± SD AUC 0-24 (based on pre-dose concentration) was 25.1 ± 30.2 and 253 ± 404 h∙ng/mL for roflumilast and the N-oxide metabolite, respectively. Plaque Psoriasis The pharmacokinetics of ZORYVE foam, 0.3%, was investigated in 19 adults and 7 pediatric subjects 12 to 16 years of age with plaque psoriasis of the scalp and body.
The entire scalp (BSA of approximately 4.5%) was treated in addition to the mean ± SD BSA involvement on the body of 25.0 ± 7.88% and 10.4 ± 0.54% in adults and pediatric subjects, respectively. In this study, the mean daily dose administered in adults was 10.3 g and in pediatric subjects from 12 to 16 years of age was 5.3 g of ZORYVE foam, 0.3%, once daily for 15 days. Following application of ZORYVE foam, 0.3%, the plasma concentration versus time profile was flat, with mean peak-to-trough ratios of approximately 1.2 for both roflumilast and roflumilast N-oxide.
In adults, the mean ± SD C max was 4.48 ± 2.28 and 29.9 ± 17.5 ng/mL for roflumilast and the N-oxide metabolite, respectively, on Day 15. The mean ± SD AUC 0-24 was 90 ± 58.7 and 567 ± 436 h∙ng/mL for roflumilast and the N-oxide metabolite, respectively, on Day 15. In pediatric subjects, the extrapolated mean ± SD AUC 0-24 (based on pre-dose concentration) was 35.5 ± 41.4 and 270 ± 293 h∙ng/mL for roflumilast and the N-oxide metabolite, respectively, on Day 15.
Distribution Plasma protein binding of roflumilast and its N-oxide metabolite is approximately 99% and 97%, respectively. Elimination The plasma clearance after short-term intravenous infusion of roflumilast is on average about
9.6L/h. Following topical administration, the mean half-lives of both roflumilast and the N-oxide metabolite were in the range of 3.6 to 5 days. Metabolism Roflumilast is extensively metabolized via Phase I (cytochrome P450) and Phase II (conjugation) reactions.
The N-oxide metabolite is the only major metabolite observed in the plasma of humans. Following oral administration, roflumilast and roflumilast N-oxide account for the majority (87.5%) of total dose administered in plasma. Roflumilast was not detectable in urine, while roflumilast N-oxide was only a trace metabolite (less than 1%).
Other conjugated metabolites such as roflumilast N-oxide glucuronide and 4-ami…
🧬 Mechanism of Action ▾
12.1Mechanism of Action Roflumilast and its active metabolite (roflumilast N-oxide) are inhibitors of PDE4. Roflumilast and roflumilast N-oxide inhibition of PDE4 (a major cyclic 3′,5′-adenosine monophosphate (cyclic AMP) metabolizing enzyme) activity leads to accumulation of intracellular cyclic AMP. The specific mechanism(s) by which roflumilast exerts its therapeutic action is not well defined.
📦 How Supplied / Storage and Handling ▾
16 HOW SUPPLIED/STORAGE AND HANDLING How Supplied ZORYVE (roflumilast) topical foam, 0.3%, is a white to off-white foam. It is supplied in a 60-gram pressurized aluminum can (NDC 80610-430-60). Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [See USP Controlled Room Temperature].
Do not freeze. Store upright. Flammable.
Contents under pressure. Do not puncture or incinerate. Do not expose to heat or store at temperatures above 49°C (120°F) [see Warnings and Precautions (5.1) ] .
📦 Storage and Handling ▾
Storage and Handling Store at 20°C to 25°C (68°F to 77°F); excursions permitted between 15°C and 30°C (59°F and 86°F) [See USP Controlled Room Temperature]. Do not freeze. Store upright. Flammable. Contents under pressure. Do not puncture or incinerate. Do not expose to heat or store at temperatures above 49°C (120°F) [see Warnings and Precautions (5.1) ] .
📋 Description ▾
11 DESCRIPTION ZORYVE (roflumilast) topical foam, 0.3%, is a white to off-white foam for topical use. The active ingredient, roflumilast, is a phosphodiesterase 4 (PDE4) inhibitor. The chemical name of roflumilast is 3-cyclopropylmethoxy- N -(3,5-dichloropyridin-4-yl)-4-(difluoromethoxy)benzamide with a molecular formula of C 17 H 14 Cl 2 F 2 N 2 O 3 and the molecular weight of 403.21.
The structural formula of roflumilast is: Roflumilast is practically insoluble in water and hexane, sparingly soluble in ethanol, and freely soluble in acetone. Each gram of ZORYVE topical foam, 0.3%, contains 3 mg of roflumilast in a foam base containing ceteareth-10 phosphate, cetearyl phosphate, cetostearyl alcohol, diethylene glycol monoethyl ether, hexylene glycol, isopropyl palmitate, methylparaben, propylparaben, purified water, sodium hydroxide, and white petrolatum. Hydrochloric acid may have been added to adjust pH.
ZORYVE topical foam, 0.3%, is dispensed from an aluminum can pressurized with propellant (butane, isobutane, and propane). Chemical Structure
💬 Information for Patients ▾
17 PATIENT COUNSELING INFORMATION Advise the patient or caregiver to read the FDA-approved patient labeling (Patient Information). Administration Instructions Advise patients or caregivers that ZORYVE foam, 0.3%, is for topical use only and is not for ophthalmic, oral, or intravaginal use [see Dosage and Administration (2) ] . Instruct patients or caregivers to shake the can of ZORYVE foam, 0.3%, prior to each use [see Dosage and Administration (2) ] .
Instruct patients or caregivers to wash hands after applying ZORYVE foam, 0.3% [see Dosage and Administration (2) ] . Flammability Because the propellants in ZORYVE foam, 0.3%, are flammable, instruct the patient to avoid fire, flame, and smoking during and immediately following application [see Dosage and Administration (2) , Warnings and Precautions (5.1) ] . Lactation Advise patients to use ZORYVE foam, 0.3%, on the smallest area of skin and for the shortest duration possible while breastfeeding.
Instruct patients who are breastfeeding not to apply ZORYVE foam, 0.3%, directly to the nipple or areola to avoid direct infant exposure. Instruct patients to avoid inadvertent contact of treated areas with infant skin [see Use in Specific Populations (8.2) ] .