
AcaI Advanced Energy Ingredients & Drug Interactions
by Isotonix
What is this page for?
First and foremost: checking AcaI Advanced Energy against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
AcaI Advanced Energy is a dietary supplement by Isotonix with 20 active ingredients. Its ingredients are commonly taken for general nutrition and energy, skin and hair health, acne (topical and oral).Based on those ingredients, 1,507 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Green Tea Leaf Extract, Yerba Mate Leaf Extract, Pomegranate Rind and Seed Extract. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against AcaI Advanced Energy by Isotonix
Ask about any prescription or over-the-counter medication and we check it for interactions with AcaI Advanced Energy by Isotonix — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of AcaI Advanced Energy by Isotonix
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Full disclosure
Isotonix AcaI Advanced Energy contains 20 active ingredients formulated to support energy and wellness. The formula includes vitamins — pantothenic acid, vitamin C, folate, folic acid, niacin, vitamin B6, and vitamin B12 — alongside minerals like zinc, potassium, copper, and sodium.
You'll also find amino acids (L-tyrosine, glycine, L-phenylalanine), plant extracts (green tea leaf, guarana seed, yerba mate, acai juice, mangosteen, pomegranate), and taurine — a compound your body produces naturally and uses in the brain and heart. The powder also contains inactive ingredients including fructose, malic acid, grape juice powder, citric acid, natural flavors (raspberry, white grape, black cherry), silicon dioxide, beet powder, stevia (rebaudioside A), and maltodextrin.
These are added for taste, texture, and stability.
Does it work?
Strong evidence
The evidence for effectiveness varies across these ingredients. Pantothenic acid is effective for pantothenic acid deficiency but has insufficient evidence for conditions like hay fever and alcoholism.
Taurine is possibly effective for liver disease and heart failure, but possibly ineffective for weight loss. Vitamin C is effective for C deficiency and possibly effective for anemia and exercise-related infections.
Caffeine is effective for certain types of apnea and possibly effective for alertness and athletic performance. Green tea is likely effective for HPV and possibly effective for ovarian cancer and high cholesterol.
L-tyrosine is effective for PKU and possibly effective for memory and focus, though possibly ineffective for athletic performance. Folic acid is effective for folate deficiency and likely effective for birth defect prevention.
Zinc is effective for zinc deficiency and possibly effective for acne and macular degeneration. The remaining ingredients — taurine, folate, guarana, niacin, sodium, vitamin B6, yerba mate, acai, mangosteen, and pomegranate — have limited evidence or insufficient data in our files.
How safe is it?
Well-documented data
Most ingredients are generally well tolerated at typical doses. Pantothenic acid is considered safe at standard supplement amounts but high-dose supplements warrant a doctor's approval.
Taurine is generally well tolerated short-term in healthy adults, though long-term safety is less certain. Vitamin C is safe at normal intakes but high doses can cause kidney stones, stomach upset, and other effects above 2 grams daily.
Caffeine in moderate amounts is fine for healthy adults, but high doses cause anxiety, insomnia, tremors, and serious effects are rare. Green tea is generally safe as a beverage but concentrated extracts in high doses carry rare risk of liver injury.
L-tyrosine is generally well tolerated with no serious documented effects, though fatigue, headache, and nausea occur at higher doses. Folic acid is safe at recommended doses; high doses may cause sleep changes and neuropathy (nerve damage).
Glycine is generally well tolerated at typical doses but long-term safety data are limited. Zinc is safe below 40 mg daily; above that, copper deficiency becomes a concern.
L-phenylalanine is generally tolerated but should be avoided entirely by people with phenylketonuria (PKU). Potassium from food is fine, but supplements can cause dangerously high blood levels, especially in people with kidney disease.
Niacin is usually well tolerated at recommended doses; high doses cause flushing and other effects. Sodium from typical intake is fine; high amounts link to high blood pressure and kidney disease.
Vitamin B6 is safe below 100 mg daily; very high chronic doses cause nerve damage. Yerba mate contains caffeine and has not been studied long-term at high doses.
Acai as a food is well tolerated; supplement safety is less certain. Mangosteen extracts have caused mild tiredness, headache, and GI upset in small-scale studies.
Pomegranate fruit and juice are safe; peel and leaf should not be used in large amounts.
Meds to double-check
Major interaction found
Check your medications if you take ephedrine (major risk of dangerous stimulant effects with caffeine and green tea), levodopa for Parkinson disease (phenylalanine and tyrosine reduce effectiveness), warfarin or other blood thinners (vitamin C, green tea, pomegranate may interfere), seizure medications like phenytoin, phenobarbital, and carbamazepine (caffeine, green tea, folic acid may reduce their effects), heart and blood pressure drugs including atorvastatin, nadolol, ACE inhibitors, and angiotensin receptor blockers (multiple interactions), certain antibiotics (zinc reduces absorption), lithium (taurine and sodium interfere), thyroid hormone (tyrosine may have additive effects), or methotrexate and certain chemotherapy drugs (folic acid may reduce effectiveness). No interactions are documented for the inactive ingredients we hold data on, but several active ingredients lack complete interaction information in our files.
The bottom line
Scorecard at a glanceFully disclosed formula with clinical evidence supporting its stated purpose. Major medication interactions have been identified, and safety information is well characterized.
If you take any heart, blood pressure, seizure, thyroid, anticoagulant, diabetes, or mental health medications, talk with your pharmacist or doctor before using this product — the interaction list is long. The formula works best for people looking to boost energy and general micronutrient intake who have no significant chronic conditions or prescription drugs.
Pregnant and breastfeeding people should avoid this product without explicit medical clearance, as several ingredients lack safety data or carry cautions in pregnancy and lactation.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 20 of 20 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Jul 25, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about AcaI Advanced Energy, straight from the product label.
| Brand | Isotonix |
|---|---|
| Barcode (UPC) | 848570002822 |
| Net contents | 10.6 Ounce(s); 300 Gram(s) |
| Market status | On market |
| Date entered into DSLD | Jul 25, 2024 |
| DSLD ID | 313387 |
| Product type | Other Combinations |
| Supplement form | Powder |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Gluten Free |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for AcaI Advanced Energy by Isotonix, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Pantothenic Acid | 4 mg | 80% |
| Taurine | 125 mg | -- |
| Vitamin C | 100 mg | 111% |
| Caffeine | 24 mg | -- |
| Calories | 15 Calorie(s) | -- |
| Total Carbohydrate | 3 Gram(s) | 1% |
| Total Sugars | 3 Gram(s) | -- |
| added Sugars | 1 Gram(s) | 2% |
| Folate | 85 mcg DFE | 21% |
| Green Tea Leaf Extract | 25 mg | -- |
| Guarana seed extract | 160 mg | -- |
| Zinc | 1.3 mg | 12% |
| L-Tyrosine | 100 mg | -- |
| Folic Acid | 50 mcg | -- |
| Glycine | 100 mg | -- |
| Copper | 0.17 mg | 19% |
| Vitamin B12 | 3.6 mcg | 150% |
| L-Phenylalanine | 200 mg | -- |
| Potassium | 165 mg | 4% |
| Niacin | 15 mg NE | 94% |
| Sodium | 75 mg | 3% |
| Vitamin B6 | 2.1 mg | 124% |
| Yerba Mate Leaf Extract | 45 mg | -- |
| Acai Juice, Powder | 300 mg | -- |
| Mangosteen, Powder | 100 mg | -- |
| Pomegranate Rind and Seed Extract | 50 mg | -- |
Other ingredients: Fructose, Malic Acid, Grape Juice, Powder, Citric Acid, natural Raspberry flavor, Silicon Dioxide, White Grape Flavor, Natural, Rebaudioside A, Beet, Powder, Raspberry Fruit Juice, Powder, natural Grape flavor, Luo Han Guo fruit extract, Grape skin extract, natural Black Cherry flavor, Maltodextrin, Stearic Acid
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formulation
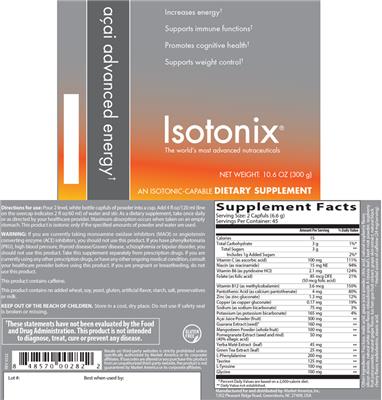
Increases energy Supports immune functions Promotes cognitive health Supports weight control
This product contains no added wheat, soy, yeast, gluten, artificial flavor, starch, salt, preservatives or milk.
Gluten free
Brand IP Statement(s)
Isotonix The world's most advanced nutraceuticals
FDA Statement of Identity
An isotonic-capable Dietary Supplement
Suggested/Recommended/Usage/Directions
Directions for use: Pour 2 level, white bottle capfuls of powder into a cup. Add 4 fl oz/120 ml (line on the overcap indicates 2 fl oz/60 ml) of water and stir. As a dietary supplement, take once daily or as directed by your healthcare provider. Maximum absorption occurs when taken on an empty stomach. This product is isotonic only if the specified amounts of powder and water are used.
Precautions
If you have phenylketonuria, (PKU), high blood pressure, thyroid disease/Graves' disease, schizophrenia or bipolar disorder, you should not use this product. This product contains caffeine. Do not use if safety seal is broken or missing. Resale on third-party websites is strictly prohibited unless specifically authorized by Market America or its corporate affiliates. If barcodes are altered or you purchase this product from an unauthorized third-party website, the product is not guaranteed by Market America or its corporate affiliates.
Keep out of the reach of children.
Warning: If you are currently taking monoamine oxidase inhibitors (MAOI) or angiotensin converting enzyme (ACE) inhibitors, you should not use this product.
Storage
Store in a cool, dry place.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure or prevent any disease.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
AcaI Advanced Energy by Isotonix label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in AcaI Advanced Energy by Isotonix
These are the 20 active ingredients this product is made of. Select any to open its full monograph.
Serving size6.6 Gram(s) Dosage formPowder Servings per container45 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Pantothenic Acid
No knowninteractions
Pantothenic acid is vitamin B5, an essential nutrient your body uses to turn food into energy. True deficiency is very rare because it is found in nea...
Pantothenic Acid monograph & interactionsTaurine
Interacts with173 drugs
Taurine is an amino acid your body makes naturally and that you also get from animal foods. It is widely used in energy drinks and sports supplements,...
Taurine monograph & interactionsVitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsFolate
Green Tea Leaf Extract
Interacts with1,293 drugs
Green tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentra...
Green Tea Leaf Extract monograph & interactionsGuarana seed extract
Interacts with655 drugs
Guarana is an Amazonian seed that is naturally high in caffeine, which explains most of its stimulant and energy effects. While it may give a short-te...
Guarana seed extract monograph & interactions- › Caffeine
Zinc
Interacts with67 drugs
Zinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but suppleme...
Zinc monograph & interactionsL-Tyrosine
Interacts with21 drugs
L-tyrosine is an amino acid your body uses to make brain chemicals like dopamine and norepinephrine. Some studies suggest it may help mental performan...
L-Tyrosine monograph & interactionsGlycine
Interacts with1 drug
Glycine is a non-essential amino acid your body makes on its own and that also appears in protein-rich foods. It is most studied for improving sleep q...
Glycine monograph & interactionsCopper
Interacts with31 drugs
Copper is an essential trace mineral your body needs in small amounts for making red blood cells, supporting nerves and bones, and helping enzymes wor...
Copper monograph & interactionsVitamin B12
Interacts with20 drugs
Vitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very h...
Vitamin B12 monograph & interactionsL-Phenylalanine
Interacts with16 drugs
Phenylalanine is an essential amino acid the body uses to make brain chemicals like dopamine and norepinephrine. Some people take it for mood, vitilig...
L-Phenylalanine monograph & interactionsPotassium
Interacts with62 drugs
Potassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanc...
Potassium monograph & interactionsNiacin
Interacts with124 drugs
Niacinamide (also called nicotinamide) is a form of vitamin B3 used in supplements and skin-care products. It is well established for preventing and t...
Niacin monograph & interactionsSodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsVitamin B6
Interacts with210 drugs
Vitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is b...
Vitamin B6 monograph & interactionsYerba Mate Leaf Extract
Interacts with1,086 drugs
Yerba mate is a caffeine-containing herbal beverage from South America that is widely enjoyed for its stimulating, coffee-like effects. While it is ri...
Yerba Mate Leaf Extract monograph & interactionsAcai Juice, Powder
Interacts with86 drugs
Acai is a nutritious Amazonian berry rich in antioxidants and healthy fats, and it is fine to enjoy as a food. However, strong human evidence is lacki...
Acai Juice, Powder monograph & interactionsMangosteen, Powder
Interacts with125 drugs
Mangosteen is a tropical fruit whose rind is rich in plant compounds called xanthones that act as antioxidants. While it is popular in juices and supp...
Mangosteen, Powder monograph & interactionsPomegranate Rind and Seed Extract
Interacts with922 drugs
Pomegranate is a nutrient-rich fruit that is high in antioxidants and is widely enjoyed as food and juice. Early research suggests it may support hear...
Pomegranate Rind and Seed Extract monograph & interactionsOther (inactive) ingredients: Fructose, Malic Acid, Grape Juice, Powder, Citric Acid, Natural Raspberry flavor, Silicon Dioxide, White Grape Flavor, Natural, Rebaudioside A, Beet, Powder, Raspberry Fruit Juice, Powder, Natural Grape flavor, Luo Han Guo fruit extract, Grape skin extract, Natural Black Cherry flavor, Maltodextrin, Stearic Acid. These complete the product’s ingredient list but are not active constituents.
AcaI Advanced Energy by Isotonix Drug Interactions
HelloPharmacist Interaction Report
Isotonix AcaI Advanced Energy is a 20-ingredient powder supplement that interacts with a substantial number of medications.
The most serious interaction involves caffeine and ephedrine — together they can trigger dangerous stimulant effects including heart attack, stroke, seizures, and in rare cases, death.
Read the full breakdown — every affected drug type, severity by severity
Vitamin C in this formula interacts with estrogens (birth control and hormone therapy), certain chemotherapy drugs, warfarin (a blood thinner), and several others at moderate severity. Green tea leaf extract shares caffeine-related interactions with ephedrine and several seizure medications, and also reduces the effectiveness of two common heart and cholesterol drugs — nadolol and atorvastatin — by up to 85% and 24%, respectively.
L-phenylalanine carries a major interaction with levodopa (Parkinson treatment) by reducing how much reaches the brain. Folic acid interacts with seizure medications and some cancer drugs.
Zinc reduces absorption of several antibiotics and HIV medications. Taurine may increase blood pressure-lowering effects and lithium levels.
Potassium poses a hyperkalemia (dangerous high potassium) risk with heart and blood pressure medications. The remaining ingredients — pantothenic acid, tyrosine, niacin, sodium, vitamin B6, yerba mate, acai, mangosteen, and pomegranate — each carry documented moderate or minor interactions with various drug classes.
Altogether, these interactions span 1,486 individual medications. Please use the medication checker below to verify your exact prescriptions before starting this product.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against AcaI Advanced Energy?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in AcaI Advanced Energy interact with 1,507 drugs. Click any drug to see the details.
19 of the 20 ingredients in AcaI Advanced Energy interact with drugs. Each result below shows which ingredient is responsible. Green Tea Leaf Extract Yerba Mate Leaf Extract Pomegranate Rind and Seed Extract Guarana seed extract Vitamin B6 Vitamin C Sodium Taurine Mangosteen, Powder Niacin Acai Juice, Powder Zinc Potassium Folic Acid Copper L-Tyrosine Vitamin B12 L-Phenylalanine Glycine
6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with AcaI Advanced Energy — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + 6-mercaptopurine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with AcaI Advanced Energy — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with AcaI Advanced Energy — through 1 ingredient. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Abacavir, Lamivudine interactionAbametapirXeglyze
How Abametapir interacts with AcaI Advanced Energy — through 4 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 1a2 (cyp1a2) Inhibitors Moderate
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Green Tea Leaf Extract + Abametapir interactionCaffeineCytochrome P450 1a2 (cyp1a2) Inhibitors Minor
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Caffeine + Abametapir interactionYerba Mate Leaf ExtractCytochrome P450 1a2 (cyp1a2) Inhibitors Minor
Interaction Summary
Theoretically, concomitant use of CYP1A2 inhibitors and yerba mate might increase levels and adverse effects of the caffeine in yerba mate.
Read the full Yerba Mate Leaf Extract + Abametapir interactionGuarana Seed ExtractCytochrome P450 1a2 (cyp1a2) Inhibitors Minor
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Guarana Seed Extract + Abametapir interactionAbciximabReoPro
How Abciximab interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Yerba Mate Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, the caffeine in yerba mate may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Yerba Mate Leaf Extract + Abciximab interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Abciximab interactionGreen Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Leaf Extract + Abciximab interactionGuarana Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, guarana may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Guarana Seed Extract + Abciximab interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacinamide may have additive effects when used with anticoagulant or antiplatelet drugs, especially in patients on hemodialysis.
Read the full Niacin + Abciximab interactionMangosteen, PowderAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of mangosteen with anticoagulant or antiplatelet drugs may increase the risk of bleeding.
Read the full Mangosteen, Powder + Abciximab interactionAbiraterone
How Abiraterone interacts with AcaI Advanced Energy — through 5 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Inhibitors +1 Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Abiraterone interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Abiraterone interactionYerba Mate Leaf ExtractCytochrome P450 1a2 (cyp1a2) Inhibitors, Cytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, concomitant use of CYP1A2 inhibitors and yerba mate might increase levels and adverse effects of the caffeine in yerba mate.
Read the full Yerba Mate Leaf Extract + Abiraterone interactionGuarana Seed ExtractCytochrome P450 1a2 (cyp1a2) Inhibitors Minor
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Guarana Seed Extract + Abiraterone interactionCaffeineCytochrome P450 1a2 (cyp1a2) Inhibitors Minor
Interaction Summary
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Read the full Caffeine + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with AcaI Advanced Energy — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Abiraterone Acetate interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Abiraterone Acetate interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with AcaI Advanced Energy — through 7 ingredients. Tap an ingredient for the detail:
Guarana Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, guarana may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Guarana Seed Extract + Abrocitinib interactionYerba Mate Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, the caffeine in yerba mate may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Yerba Mate Leaf Extract + Abrocitinib interactionGreen Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Leaf Extract + Abrocitinib interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Abrocitinib interactionMangosteen, PowderAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of mangosteen with anticoagulant or antiplatelet drugs may increase the risk of bleeding.
Read the full Mangosteen, Powder + Abrocitinib interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacinamide may have additive effects when used with anticoagulant or antiplatelet drugs, especially in patients on hemodialysis.
Read the full Niacin + Abrocitinib interactionPomegranate Rind And Seed ExtractCytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2C9.
Read the full Pomegranate Rind And Seed Extract + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with AcaI Advanced Energy — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Acalabrutinib interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acalabrutinib interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with AcaI Advanced Energy — through 5 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractAntidiabetes Drugs, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, taking green tea with antidiabetes drugs might interfere with blood glucose control.
Read the full Green Tea Leaf Extract + Acarbose interactionAcai Juice, PowderAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking acai with antidiabetes drugs might interfere with glycemic control.
Read the full Acai Juice, Powder + Acarbose interactionYerba Mate Leaf ExtractAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking yerba mate with antidiabetes drugs might interfere with blood glucose control.
Read the full Yerba Mate Leaf Extract + Acarbose interactionCaffeineAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking caffeine with antidiabetes drugs might interfere with blood glucose control.
Read the full Caffeine + Acarbose interactionGuarana Seed ExtractAntidiabetes Drugs Minor
Interaction Summary
Theoretically, taking guarana with antidiabetes drugs might interfere with blood glucose control.
Read the full Guarana Seed Extract + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with AcaI Advanced Energy — through 5 ingredients. Tap an ingredient for the detail:
TaurineAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taurine might increase the risk of hypotension when taken with antihypertensive drugs.
Read the full Taurine + Acebutolol interactionSodiumAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
Read the full Sodium + Acebutolol interactionVitamin B6Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Read the full Vitamin B6 + Acebutolol interactionPomegranate Rind And Seed ExtractAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking pomegranate with antihypertensive drugs might increase the risk of hypotension.
Read the full Pomegranate Rind And Seed Extract + Acebutolol interactionGreen Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Guarana Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, guarana may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Guarana Seed Extract + Acenocoumarol interactionYerba Mate Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, the caffeine in yerba mate may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Yerba Mate Leaf Extract + Acenocoumarol interactionGreen Tea Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Leaf Extract + Acenocoumarol interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Acenocoumarol interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacinamide may have additive effects when used with anticoagulant or antiplatelet drugs, especially in patients on hemodialysis.
Read the full Niacin + Acenocoumarol interactionMangosteen, PowderAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of mangosteen with anticoagulant or antiplatelet drugs may increase the risk of bleeding.
Read the full Mangosteen, Powder + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with AcaI Advanced Energy — through 2 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with AcaI Advanced Energy — through 7 ingredients. Tap an ingredient for the detail:
Mangosteen, PowderAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of mangosteen with anticoagulant or antiplatelet drugs may increase the risk of bleeding.
Read the full Mangosteen, Powder + Acetaminophen, Aspirin interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacinamide may have additive effects when used with anticoagulant or antiplatelet drugs, especially in patients on hemodialysis.
Read the full Niacin + Acetaminophen, Aspirin interactionGreen Tea Leaf ExtractHepatotoxic Drugs, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Aspirin interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Acetaminophen, Aspirin interactionYerba Mate Leaf ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, the caffeine in yerba mate may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Aspirin interactionGuarana Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, guarana may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Guarana Seed Extract + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with AcaI Advanced Energy — through 8 ingredients. Tap an ingredient for the detail:
Guarana Seed ExtractAnticoagulant/antiplatelet Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, guarana may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Guarana Seed Extract + Acetaminophen, Aspirin, Caffeine interactionYerba Mate Leaf ExtractStimulant Drugs, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use of stimulant drugs and yerba mate might increase stimulant adverse effects.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Aspirin, Caffeine interactionCaffeineAnticoagulant/antiplatelet Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Acetaminophen, Aspirin, Caffeine interactionGreen Tea Leaf ExtractAnticoagulant/antiplatelet Drugs, Stimulant Drugs +2 Moderate
Interaction Summary
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Green Tea Leaf Extract + Acetaminophen, Aspirin, Caffeine interactionNiacinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacinamide may have additive effects when used with anticoagulant or antiplatelet drugs, especially in patients on hemodialysis.
Read the full Niacin + Acetaminophen, Aspirin, Caffeine interactionMangosteen, PowderAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, concomitant use of mangosteen with anticoagulant or antiplatelet drugs may increase the risk of bleeding.
Read the full Mangosteen, Powder + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with AcaI Advanced Energy — through 5 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionYerba Mate Leaf ExtractPhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension as well as the levels and adverse effects of the caffeine in yerba mate.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionGreen Tea Leaf ExtractStimulant Drugs, Phenylpropanolamine +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionGuarana Seed ExtractPhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Read the full Guarana Seed Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with AcaI Advanced Energy — through 2 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Butalbital interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Butalbital, Caffeine interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Butalbital, Caffeine interactionGreen Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Acetaminophen, Butalbital, Caffeine interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractStimulant Drugs, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionPomegranate Rind And Seed ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Butalbital, Caffeine, Codeine interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with AcaI Advanced Energy — through 3 ingredients. Tap an ingredient for the detail:
Pomegranate Rind And Seed ExtractCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Butalbital, Codeine interactionGreen Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with AcaI Advanced Energy — through 3 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionPomegranate Rind And Seed ExtractCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Pomegranate Rind And Seed ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionGreen Tea Leaf ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Codeine interactionGreen Tea Leaf ExtractStimulant Drugs, Hepatotoxic Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Caffeine, Codeine interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Stimulant Drugs Moderate
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Caffeine, Codeine interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Caffeine, Codeine interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Yerba Mate Leaf ExtractStimulant Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of stimulant drugs and yerba mate might increase stimulant adverse effects.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionPomegranate Rind And Seed ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Codeine, Salicylamide interactionGreen Tea Leaf ExtractStimulant Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Dihydrocodeine interactionYerba Mate Leaf ExtractStimulant Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of stimulant drugs and yerba mate might increase stimulant adverse effects.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractStimulant Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Caffeine, Isometheptene interactionYerba Mate Leaf ExtractStimulant Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of stimulant drugs and yerba mate might increase stimulant adverse effects.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Caffeine, Isometheptene interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Caffeine, Isometheptene interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Yerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Stimulant Drugs +1 Moderate
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Caffeine, Pyrilamine interactionGreen Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Acetaminophen, Caffeine, Pyrilamine interactionGuarana Seed ExtractStimulant Drugs, Diuretic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Caffeine, Pyrilamine interactionCaffeineDiuretic Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, using caffeine with diuretic drugs might increase the risk of hypokalemia.
Read the full Caffeine + Acetaminophen, Caffeine, Pyrilamine interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Caffeine, Pyrilamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with AcaI Advanced Energy — through 4 ingredients. Tap an ingredient for the detail:
Pomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionGreen Tea Leaf ExtractHepatotoxic Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with AcaI Advanced Energy — through 6 ingredients. Tap an ingredient for the detail:
Yerba Mate Leaf ExtractStimulant Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, concomitant use of stimulant drugs and yerba mate might increase stimulant adverse effects.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionGreen Tea Leaf ExtractStimulant Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Green Tea Leaf Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionGuarana Seed ExtractStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Guarana Seed Extract + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with AcaI Advanced Energy — through 4 ingredients. Tap an ingredient for the detail:
Green Tea Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Green tea is unlikely to produce clinically significant changes in the levels and clinical effects of CYP3A4 substrates.
Read the full Green Tea Leaf Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionPomegranate Rind And Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate Rind And Seed Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionYerba Mate Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, yerba mate might increase the levels and clinical effects of CYP3A4 substrates.
Read the full Yerba Mate Leaf Extract + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionEach ingredient & the kinds of drugs it affects
For each ingredient in AcaI Advanced Energy with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Green Tea Leaf Extract
Atorvastatin (Lipitor)
Green tea extract seems to reduce the levels and clinical effects of atorvastatin.
In healthy humans, taking green tea extract 300 mg or 600 mg along with atorvastatin reduces plasma levels of atorvastatin by approximately 24%. The elimination of atorvastatin is not affected. Atorvastatin is a substrate of organic anion-transporting polypeptides (OATPs). Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs. Some OATPs are expressed in the small intestine and are responsible for the uptake of drugs and other compounds, which may have resulted in reduced plasma levels of atorvastatin. It is not clear if drinking green tea alters the absorption of atorvastatin.
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Green tea contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Nadolol (Corgard)
Green tea seems to reduce the levels and clinical effects of nadolol.
Preliminary clinical research shows that green tea consumption reduces plasma concentrations of nadolol. Compared to a control group, both peak levels and total drug exposure (AUC) of nadolol were reduced by approximately 85% in subjects who drank green tea daily for two weeks. Drinking green tea with nadolol also significantly reduced nadolol's systolic blood pressure lowering effect. Other clinical research shows that a single dose of green tea can affect plasma nadolol levels for at least one hour. Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is involved in the uptake of nadolol in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
5-Fluorouracil
Theoretically, high doses of green tea might increase the effects and side effects of 5-fluorouracil.
Animal research shows that taking green tea in amounts equivalent to about 6 cups daily in humans for 4 weeks prior to receiving a single injection of 5-fluorouracil increases the maximum plasma levels of 5-fluorouracil by about 2.5-fold and the area under the curve by 425%.
Adenosine (Adenocard)
Theoretically, green tea might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine doesn't seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, green tea may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Conflicting reports exist regarding the effect of green tea on bleeding risk when used with anticoagulant or antiplatelet drugs; however, most evidence suggests that drinking green tea in moderate amounts is unlikely to cause a significant interaction. Green tea contains small amounts of vitamin K, approximately 7 mcg per cup. Some case reports have associated the antagonism of warfarin with the vitamin K content of green tea. However, these reports are rare, and very large doses of green tea (about 8-16 cups daily) appear to be needed to cause these effects. Furthermore, the catechins and caffeine in green tea are reported to have antiplatelet activity.
Beta-Adrenergic Agonists
Green tea contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Bortezomib (Velcade)
Theoretically, green tea might interfere with the effects of bortezomib.
In vitro research shows that green tea polyphenols, such as epigallocatechin gallate (EGCG), interact with bortezomib and block its proteasome inhibitory action. This prevents the induction of cell death in multiple myeloma or glioblastoma cancer cell lines. Advise patients taking bortezomib, not to take green tea.
Carbamazepine (Tegretol)
Theoretically, green tea might reduce the effects of carbamazepine and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine 2-fold in healthy individuals.
Celiprolol (Celicard)
Theoretically, green tea might reduce the levels and clinical effects of celiprolol.
In a small human study, taking green tea daily for 4 days appears to decrease blood and urine levels of celiprolol by at least 98%. This interaction is possibly due to the inhibition of organic anion transporting polypeptide (OATP). Green tea catechins have been shown to inhibit organic anion transporting polypeptides (OATP), one of which, OATP1A2, is found in the intestine The interaction is thought to be due primarily to the epigallocatechin gallate (EGCG) content of green tea.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in green tea.
Green tea contains caffeine. Cimetidine can reduce caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, green tea might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Animal research suggests that, although green tea extract does not affect the elimination of clozapine, it delays the time to reach peak concentration and reduces the peak plasma levels. Also, concomitant administration of green tea and clozapine might theoretically cause acute exacerbation of psychotic symptoms due to the caffeine in green tea. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in green tea.
Green tea contains caffeine. Oral contraceptives can decrease caffeine clearance by 40% to 65%.
Cytochrome P450 1A2 (Cyp1A2) Inhibitors
Theoretically, concomitant use might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Caffeine is metabolized by cytochrome P450 1A2 (CYP1A2),. Theoretically, drugs that inhibit CYP1A2 may decrease the clearance rate of caffeine from green tea and increase caffeine levels.
Dipyridamole (Persantine)
Theoretically, green tea might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Green tea contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using green tea with diuretic drugs might increase the risk of hypokalemia.
Green tea contains caffeine. In excessive amounts, caffeine can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, green tea might reduce the effects of ethosuximide and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, green tea might reduce the effects of felbamate and increase the risk for convulsions.
Green tea contains caffeine. Animal research suggests that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Fexofenadine (Allegra)
Green tea can decrease blood levels of fexofenadine.
Clinical research shows that green tea can significantly decrease blood levels and excretion of fexofenadine. Taking green tea extract with a dose of fexofenadine decreased bioavailability of fexofenadine by about 30%. In vitro, green tea inhibits the cellular accumulation of fexofenadine by inhibiting the organic anion transporting polypeptide (OATP) drug transporter. Research shows that two of the major catechins found in green tea, epicatechin gallate (ECG) and epigallocatechin gallate (EGCG), inhibit OATPs, specifically OATP1A2, OATP1B1, and OATP2B1. In addition, green tea has been shown to reduce the absorption of some drugs that are OATP substrates.
Flutamide (Eulexin)
Theoretically, green tea might increase the levels and adverse effects of flutamide.
Green tea contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. Theoretically, concomitant use of caffeine and flutamide might increase serum concentrations of flutamide and increase the risk adverse effects.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Green tea contains caffeine. Fluvoxamine reduces caffeine metabolism.
Hepatotoxic Drugs
Theoretically, concomitant use might have additive adverse hepatotoxic effects.
Green tea extract supplements have been linked to several cases of hepatotoxicity and might have additive hepatotoxic effects with other drugs..
Imatinib (Gleevec)
Theoretically, green tea might reduce the levels and clinical effects of imatinib.
In animal research, a single dose of green tea extract reduces the area under the curve (AUC) of imatinib by up to approximately 64% and its main metabolite N-desmethyl imatinib by up to approximately 81%. This interaction has not been shown in humans. The mechanism of action is unclear but may involve multiple pathways.
Yerba Mate Leaf Extract
Ephedrine
Theoretically, the caffeine in yerba mate might increase the risk for stimulant adverse effects when used concomitantly with ephedrine.
Use of ephedrine with caffeine can increase the risk of stimulatory adverse effects. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Adenosine (Adenocard)
Theoretically, the caffeine in yerba mate might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Yerba mate contains caffeine. Some evidence shows that caffeine is a competitive inhibitor of adenosine and can reduce the vasodilatory effects of adenosine in humans. However, other research shows that caffeine does not seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. Still, some researchers recommend that methylxanthines, such as caffeine, as well as methylxanthine-containing products, should be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, the caffeine in yerba mate may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Yerba mate contains caffeine. Caffeine is reported to have antiplatelet activity. Theoretically, it might increase the risk of bleeding when used concomitantly with these agents; however, this interaction has not been reported in humans.
Benzodiazepines
Theoretically, the caffeine in yerba mate might reduce the efficacy of benzodiazepines.
Yerba mate contains caffeine. Caffeine can antagonize the anxiolytic effects of benzodiazepines.
Beta-Adrenergic Agonists
Theoretically, the caffeine in yerba mate might increase the cardiac inotropic effects of beta-agonists, especially if taken in large amounts.
Yerba mate contains caffeine. Caffeine can increase cardiac inotropic effects of beta-agonists.
Carbamazepine (Tegretol)
Theoretically, the caffeine in yerba mate might reduce the effects of carbamazepine and increase the risk for convulsions.
Yerba mate contains caffeine. Animal research suggests that caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when taken in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine two-fold in healthy individuals.
Cimetidine (Tagamet)
Theoretically, cimetidine might increase the levels and adverse effects of the caffeine contained in yerba mate.
Yerba mate contains caffeine. Cimetidine decreases caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, the caffeine in yerba mate might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Yerba mate contains caffeine. Caffeine might increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg per day inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Although researchers speculate that caffeine might inhibit CYP1A2, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients more sensitive to an interaction between clozapine and caffeine.
Dipyridamole (Persantine)
Theoretically, the caffeine in yerba mate might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Yerba mate contains caffeine. Caffeine inhibits dipyridamole-induced vasodilation. Still, some researchers recommend that methylxanthines, such as caffeine, as well as methylxanthine-containing products, should be stopped 24 hours prior to pharmacological stress. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the levels and adverse effects of the caffeine in yerba mate.
Yerba mate contains caffeine. Disulfiram decreases the rate of caffeine clearance.
Diuretic Drugs
Theoretically, the caffeine in yerba mate might increase the risk of hypokalemia when used concomitantly with other diuretics.
Yerba mate contains caffeine. Caffeine, especially in excessive amounts, can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of the caffeine in yerba mate.
Yerba mate contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, the caffeine in yerba mate might reduce the effects of ethosuximide and increase the risk for convulsion.
Yerba mate contains caffeine. Animal research shows that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. However, this effect has not been reported in humans.
Felbamate (Felbatol)
Theoretically, the caffeine in yerba mate might reduce the effects of felbamate and increase the risk for convulsion.
Yerba mate contains caffeine. Animal research shows that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. However, this effect has not been reported in humans.
Flutamide (Eulexin)
Theoretically, the caffeine in yerba mate might increase the levels and adverse effects of flutamide.
Yerba mate contains caffeine. In vitro evidence suggests that caffeine can inhibit the metabolism of flutamide. However, this effect has not been reported in humans.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of the caffeine in yerba mate.
Yerba mate contains caffeine. Fluvoxamine reduces caffeine metabolism.
Lithium
Theoretically, abrupt withdrawal of the caffeine in yerba mate might increase serum lithium levels.
Yerba mate contains caffeine, which has diuretic activity. When abruptly discontinued, it might alter the clearance of lithium. There are two case reports of lithium tremor that worsened upon abrupt coffee withdrawal.
Midazolam (Versed)
Theoretically, use of yerba mate with midazolam might increase midazolam metabolite levels and adverse effects.
In vitro research shows that yerba mate extract containing 6.75% chlorogenic acid significantly inhibits the metabolism of midazolam via inhibition of cytochrome P450 3A4 (CYP3A4).
Monoamine Oxidase Inhibitors (Maois)
Theoretically, the caffeine in yerba mate might increase risk of a hypertensive crisis when used concomitantly with MAOIs.
Yerba mate contains caffeine. Caffeine has been shown to inhibit monoamine oxidase (MAO) A and B in laboratory studies. Concomitant intake of large amounts of caffeine with MAOIs might precipitate a hypertensive crisis. In a case report, a patient that consumed 10-12 cups of caffeinated coffee and took the MAOI tranylcypromine presented with severe hypertension. Hypertension was resolved after the patient switched to drinking decaffeinated coffee.
Nicotine
Theoretically, the caffeine in yerba mate might increase risk of hypertension when used concomitantly with nicotine.
Yerba mate contains caffeine. Concomitant use of caffeine and nicotine has been shown to have additive cardiovascular effects, including increased heart rate and blood pressure. Blood pressure was increased by 10.8/12.4 mmHg when the agents were used concomitantly.
Pentobarbital (Nembutal)
Theoretically, the caffeine in yerba mate might decrease the effects of pentobarbital.
The caffeine in yerba mate might negate the hypnotic effects of pentobarbital.
Phenobarbital (Luminal)
Theoretically, the caffeine in yerba mate might reduce the effects of phenobarbital and increase the risk for convulsions.
Yerba mate contains caffeine. Animal research suggests that caffeine can decrease the anticonvulsant activity of phenobarbital. However, the exact mechanism of this interaction is unclear.
Phenylpropanolamine
Theoretically, phenylpropanolamine might increase the risk of hypertension as well as the levels and adverse effects of the caffeine in yerba mate.
Yerba mate contains caffeine. Concomitant use of phenylpropanolamine and caffeine might cause an additive increase in blood pressure. Phenylpropanolamine also seems to increase caffeine serum levels.
Phenytoin (Dilantin)
Theoretically, the caffeine in yerba mate might reduce the effects of phenytoin and increase the risk for convulsions.
Yerba mate contains caffeine. Animal research suggests that caffeine can decrease the anticonvulsant activity of phenytoin. The effect does not seem to be related to the seizure threshold-lowering effects of caffeine. However, the exact mechanism of this interaction is unclear.
Pioglitazone (Actos)
Theoretically, the caffeine in yerba mate might increase the levels and clinical effects of pioglitazone.
Yerba mate contains caffeine. Animal research suggests that caffeine can modestly increase the maximum concentration, area under the curve, and half-life of pioglitazone, and also reduce its clearance. This increased the antidiabetic effects of pioglitazone. However, the exact mechanism of this interaction is unclear.
Pomegranate Rind and Seed Extract
Ace Inhibitors (Aceis)
Theoretically, taking pomegranate with ACEIs might increase the risk of adverse effects.
Pomegranate juice is thought to have ACE inhibitor-like effects.
Antihypertensive Drugs
Theoretically, taking pomegranate with antihypertensive drugs might increase the risk of hypotension.
Consuming pomegranate juice can modestly lower blood pressure.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
In vitro, pomegranate juice inhibits CYP2D6. However, the clinical significance of this potential interaction in humans is not known.
Rosuvastatin (Crestor)
Theoretically, taking pomegranate with rosuvastatin might increase the risk of adverse effects.
In one case, a patient taking rosuvastatin 5 mg every other day in combination with ezetimibe 10 mg daily developed rhabdomyolysis after drinking pomegranate juice 200 mL twice weekly for 3 weeks. This patient had a history of elevated creatine kinase levels while not receiving any statin treatment. This suggests a possible underlying myopathy and predisposition to rhabdomyolysis.
Warfarin (Coumadin)
Theoretically, pomegranate might increase warfarin levels and increase the risk of bleeding. Also, discontinuing regular consumption of pomegranate juice might decrease warfarin levels.
In one case report, a patient had a stable, therapeutic bleeding time, as measured by international normalized ratio (INR), while taking warfarin in combination with pomegranate juice 2-3 times per week. The patient became subtherapeutic within about 10 days after discontinuing pomegranate juice, which required a warfarin dose increase. In another case report, a patient with a stable INR for over one year presented with an INR of 14. The patient noted no changes to medications or diet but did report consuming around 3 liters of pomegranate juice over the previous week. The patient's INR stabilized upon moderation of pomegranate juice consumption. The mechanism of this potential interaction is unclear.
Carbamazepine (Tegretol)
Theoretically, taking pomegranate with carbamazepine might increase the risk of adverse effects, although research suggests this interaction is unlikely to be clinically significant.
Animal research shows that pomegranate juice may inhibit cytochrome P450 3A4 (CYP3A4) metabolism of carbamazepine and increase levels of carbamazepine by 1.5 times without prolonging the elimination half-life. This suggests that pomegranate juice inhibits intestinal CYP3A4, but might not inhibit hepatic CYP3A4. However, some human research suggests that pomegranate does not significantly inhibit CYP3A4 drug metabolism in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2C9.
Some animal and in vitro research shows that pomegranate juice inhibits intestinal, but not hepatic, CYP2C9 isoenzyme activity. However, clinical research shows that neither pomegranate juice nor pomegranate extract have a significant effect on CYP2C9 activity in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Pomegranate contains several polyphenols that have individually been shown to inhibit CYP3A4. However, there is contradictory evidence about the effect of whole pomegranate juice on CYP3A4 activity. In vitro, pomegranate juice significantly inhibits the CYP3A4 enzyme, with comparable inhibition to grapefruit juice. In an animal model, pomegranate juice inhibits CYP3A4 metabolism of carbamazepine and increases levels of carbamazepine by 1.5 times; however, in human volunteers, drinking a single glass of pomegranate juice 240 mL or taking 200 mL daily for 2 weeks does not significantly affect levels of the CYP3A4 substrate midazolam after oral or intravenous administration. Another study in healthy volunteers shows that consuming pomegranate juice 300 mL three times daily for three days also does not significantly affect levels of simvastatin, a CYP3A4 substrate This suggests that pomegranate is unlikely to significantly affect levels of CYP3A4 substrates in humans.
Tolbutamide (Orinase)
Theoretically, pomegranate might increase levels of tolbutamide, although research suggests this interaction is unlikely to be clinically significant.
Animal research shows that pomegranate juice inhibits the cytochrome P450 2C9 (CYP2C9) metabolism of tolbutamide. Pomegranate juice increased tolbutamide levels by 1.2 times without prolonging the elimination half-life. This suggests that pomegranate juice inhibits intestinal CYP2C9, but might not inhibit hepatic CYP2C9. Despite this evidence, clinical research shows that neither pomegranate juice nor pomegranate extract have a significant effect on CYP2C9 activity in humans. This interaction does not appear to be clinically significant in humans.
Guarana seed extract
Ephedrine
Theoretically, concomitant use might increase the risk for stimulant adverse effects.
Guarana contains caffeine. Use of ephedrine with caffeine can increase the risk of stimulatory adverse effects. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death.
Adenosine (Adenocard)
Theoretically, guarana might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Guarana contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine does not seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Anticoagulant/Antiplatelet Drugs
Theoretically, guarana may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro and animal research suggests that guarana extract can inhibit platelet aggregation. This effect may be due to the caffeine in guarana, which is also reported to have antiplatelet activity. This interaction has not been reported in humans.
Beta-Adrenergic Agonists
Theoretically, concomitant use might increase the clinical effects of beta-adrenergic agonists.
Guarana contains caffeine. Theoretically, concomitant use of large amounts of caffeine might increase cardiac inotropic effects of beta-agonists.
Carbamazepine (Tegretol)
Theoretically, guarana might reduce the effects of carbamazepine and increase the risk for convulsions.
Animal research suggests that taking caffeine can lower the anticonvulsant effects of carbamazepine and can induce seizures when given to animals in doses above 400 mg/kg. Human research has shown that taking caffeine 300 mg in three divided doses along with carbamazepine 200 mg reduces the bioavailability of carbamazepine by 32% and prolongs the plasma half-life of carbamazepine two-fold in healthy individuals.
Cimetidine (Tagamet)
Theoretically, concomitant use might increase the effects and adverse effects of caffeine in guarana.
Guarana contains caffeine. Cimetidine decreases the rate of caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, guarana might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Guarana contains caffeine. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg per day inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients more sensitive to the interaction between clozapine and caffeine.
Dipyridamole (Persantine)
Theoretically, guarana might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Guarana contains caffeine. Caffeine might inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines and methylxanthine-containing products be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, using guarana with diuretic drugs might increase the risk of hypokalemia.
Guarana contains caffeine. Caffeine, especially in excessive amounts, can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Guarana contains caffeine. Estrogen inhibits caffeine metabolism.
Ethosuximide (Zarontin)
Theoretically, guarana might reduce the effects of ethosuximide and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that caffeine 92.4 mg/kg can decrease the anticonvulsant activity of ethosuximide. This effect has not been observed in humans.
Felbamate (Felbatol)
Theoretically, guarana might reduce the effects of felbamate and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that a high dose of caffeine 161.7 mg/kg can decreases the anticonvulsant activity of felbamate. This effect has not been observed in humans.
Flutamide (Eulexin)
Theoretically, guarana might increase the levels and adverse effects of flutamide.
Guarana contains caffeine. In vitro evidence shows that caffeine can inhibit the metabolism of flutamide. However, this effect has not been reported in humans.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Guarana contains caffeine. Fluvoxamine reduces caffeine metabolism.
Lithium
Theoretically, abrupt guarana withdrawal might increase the levels and adverse effects of lithium.
Guarana contains caffeine. Theoretically, abrupt caffeine withdrawal might increase serum lithium levels. There are two case reports of lithium tremor that worsened upon abrupt coffee withdrawal.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Guarana contains caffeine. Caffeine has been shown to inhibit MAO-A and -B in laboratory studies. Concomitant intake of large amounts of caffeine with MAOIs might precipitate a hypertensive crisis. In a case report, a patient that consumed 10-12 cups of caffeinated coffee and took the MAOI tranylcypromine presented with severe hypertension. Hypertension was resolved after the patient switched to drinking decaffeinated coffee.
Nicotine
Theoretically, concomitant use might increase the risk of hypertension.
Guarana contains caffeine. Concomitant use of caffeine and nicotine has been shown to have additive cardiovascular effects, including increased heart rate and blood pressure. Blood pressure was increased by 10.8/12.4 mmHg when the agents were used concomitantly.
Pentobarbital (Nembutal)
Theoretically, guarana might decrease the effects of pentobarbital.
Guarana contains caffeine. In vivo evidence suggests that caffeine can negate the hypnotic effects of pentobarbital in humans. However, animal research suggests that guarana does not alter the hypnotic effect of pentobarbital.
Phenobarbital (Luminal)
Theoretically, guarana might reduce the effects of phenobarbital and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that caffeine can decrease the anticonvulsant activity of phenobarbital. The exact mechanism of this interaction is unclear.
Phenylpropanolamine
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Guarana contains caffeine. Concomitant use of phenylpropanolamine and caffeine might cause an additive increase in blood pressure. Phenylpropanolamine also seems to increase caffeine serum levels.
Phenytoin (Dilantin)
Theoretically, guarana might reduce the effects of phenytoin and increase the risk for convulsions.
Guarana contains caffeine. Animal research shows that caffeine can decrease the anticonvulsant activity of phenytoin. The effect does not seem to be related to the seizure threshold-lowering effects of caffeine. However, the exact mechanism of this interaction is unclear.
Pioglitazone (Actos)
Theoretically, guarana might increase the levels and clinical effects of pioglitazone.
Guarana contains caffeine. Animal research suggests that caffeine can modestly increase the maximum concentration, area under the curve, and half-life of pioglitazone, and also reduce its clearance. This increased the antidiabetic effects of pioglitazone. However, the exact mechanism of this interaction is unclear.
Riluzole (Rilutek)
Theoretically, concomitant use might increase the levels and adverse effects of both caffeine and riluzole.
Guarana contains caffeine. Caffeine and riluzole are both metabolized by cytochrome P450 1A2 (CYP1A2), and concomitant use might reduce the metabolism of one or both agents.
Stimulant Drugs
Theoretically, concomitant use might increase stimulant adverse effects.
Guarana contains caffeine. Due to the central nervous system (CNS) stimulant effects of caffeine, concomitant use with stimulant drugs can increase the risk of adverse effects.
Vitamin B6
Amiodarone (Cordarone)
Theoretically, vitamin B6 might increase the photosensitivity caused by amiodarone.
Despite initial case reports suggesting that pyridoxine may have a protective effect against amiodarone-induced photosensitivity, preliminary clinical research suggests that pyridoxine may actually exacerbate this adverse effect.
Antihypertensive Drugs
Theoretically, vitamin B6 may have additive effects when used with antihypertensive drugs.
Research in hypertensive rats shows that vitamin B6 can decrease systolic blood pressure. Similarly, clinical research in patients with hypertension shows that taking high doses of vitamin B6 may reduce systolic and diastolic blood pressure, possibly by reducing plasma levels of epinephrine and norepinephrine.
Phenobarbital (Luminal)
High doses of vitamin B6 may reduce the levels and clinical effects of phenobarbital.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenobarbital, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenobarbital to avoid high doses of vitamin B6.
Phenytoin (Dilantin)
High doses of vitamin B6 may reduce the levels and clinical effects of phenytoin.
Preliminary clinical evidence suggests that vitamin B6 200 mg daily can reduce plasma levels of phenytoin, possibly by increasing metabolism. It is not known whether lower doses have any effect. Advise people taking phenytoin to avoid high doses of vitamin B6.
Levodopa
Vitamin B6 may increase the metabolism of levodopa when taken alone, but not when taken in conjunction with carbidopa.
Vitamin B6 (pyridoxine) enhances the metabolism of levodopa, reducing its clinical effects. However, this interaction does not occur when carbidopa is used concurrently with levodopa (Sinemet). Therefore, it is not likely to be a problem in most people.
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Taurine
Antihypertensive Drugs
Theoretically, taurine might increase the risk of hypotension when taken with antihypertensive drugs.
Some clinical evidence suggests that taurine can reduce both systolic and diastolic blood pressure.
Lithium
Theoretically, taurine might reduce excretion and increase plasma levels of lithium.
Taurine is thought to have diuretic properties, which might reduce the excretion of lithium.
Mangosteen, Powder
Anticoagulant/Antiplatelet Drugs
Theoretically, concomitant use of mangosteen with anticoagulant or antiplatelet drugs may increase the risk of bleeding.
In vitro and animal research shows that gamma-mangostin, a constituent of mangosteen, is a potent and competitive antagonist of the serotonin 2A (5-HT2A) receptor. Antagonism of the 5-HT2A receptor is believed to reduce platelet aggregation.
Donepezil (Aricept)
Theoretically, concomitant use of mangosteen with donepezil might increase the effects of donepezil.
Animal research shows that concomitant use of an aqueous extract of mangosteen pericarp with donepezil increases brain concentrations of donepezil at 4 hours by 64% without associated effects on systemic exposure.
Niacin
Anticoagulant/Antiplatelet Drugs
Theoretically, niacinamide may have additive effects when used with anticoagulant or antiplatelet drugs, especially in patients on hemodialysis.
Several cases of thrombocytopenia have been reported for hemodialysis patients treated with niacinamide 1 gram daily. Hemodialysis patients receiving niacinamide had almost a three-fold higher risk of developing thrombocytopenia when compared with those receiving placebo.
Carbamazepine (Tegretol)
Niacinamide might increase the levels and adverse effects of carbamazepine.
Plasma levels of carbamazepine were increased in two children given high-dose niacinamide, 60-80 mg/kg/day. This might be due to inhibition of the cytochrome P450 enzymes involved in carbamazepine metabolism. There is not enough data to determine the clinical significance of this interaction.
Primidone (Mysoline)
Niacinamide might increase the levels and adverse effects of primidone.
Case reports in children suggest niacinamide 60-100 mg/kg/day reduces hepatic metabolism of primidone to phenobarbital, and reduces the overall clearance rate of primidone; however, there is not enough data to determine the clinical significance of this potential interaction.
Warfarin (Coumadin)
There is limited evidence that niacinamide may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 8.4 after taking niacinamide 500 mg twice daily for 10 days. The patient's INR was previously stable, ranging between 2 and 3, with no other changes to current medications or diet reported. The elevated INR returned to the therapeutic range after receiving vitamin K and discontinuing niacinamide.
Acai Juice, Powder
Antidiabetes Drugs
Theoretically, taking acai with antidiabetes drugs might interfere with glycemic control.
Preliminary clinical research in healthy adults has shown that taking acai may increase or decrease levels of fasting blood glucose.
Zinc
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Theoretically, zinc might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after zinc containing products.
Cephalexin (Keflex)
Zinc might decrease cephalexin levels by chelating with cephalexin in the gut and preventing its absorption.
A pharmacokinetic study shows that zinc sulfate 250 mg taken concomitantly with cephalexin 500 mg decreases peak levels of cephalexin by 31% and reduces the exposure to cephalexin by 27%. Also, taking zinc sulfate 3 hours before cephalexin decreases peak levels of cephalexin by 11% and reduces the exposure to cephalexin by 18%. By decreasing cephalexin levels, zinc might increase the risk of treatment failure. This effect does not occur when zinc is taken 3 hours after the cephalexin dose. To avoid an interaction, advise patients take zinc sulfate 3 hours after taking cephalexin.
Cisplatin (Platinol-Aq)
Theoretically, zinc might interfere with the therapeutic effects of cisplatin.
Animal research suggests that zinc stimulates tumor cell production of the protein metallothionein, which binds and inactivates cisplatin. It is not known whether zinc supplements or high dietary zinc intake can cause clinically significant interference with cisplatin therapy. Cisplatin might also increase zinc excretion.
Integrase Inhibitors
Theoretically, taking zinc along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Zinc is a divalent cation. Pharmacokinetic studies have shown that other divalent cations such as calcium and iron can decrease blood levels of the integrase inhibitor dolutegravir through chelation.
Penicillamine (Cuprimine, Depen)
Zinc might reduce the levels and clinical effects of penicillamine.
By forming an insoluble complex with penicillamine, zinc interferes with penicillamine absorption and activity. Zinc supplements reduce the efficacy of low-dose penicillamine (0.5-1 gram/day), but do not seem to affect higher doses (1-2.75 gram/day), provided dosing times are separated. Advise patients to take zinc and penicillamine at least 2 hours apart.
Quinolone Antibiotics
Zinc can decrease the levels and clinical effects of quinolones antibiotics.
Quinolones form complexes with zinc in the gastrointestinal tract, reducing absorption of both the quinolone and zinc if taken at the same time. Advise patients to take these drugs at least 2 hours before, or 4-6 hours after, zinc supplements.
Ritonavir (Norvir)
Zinc modestly reduces levels of ritonavir.
Clinical research shows that zinc might reduce serum ritonavir levels by chelating with ritonavir in the gut and preventing its absorption. In patients with HIV, ritonavir is taken with atazanavir to prevent the metabolism and increase the effects of atazanavir. A pharmacokinetic study shows that, in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate (Solvazinc tablets) 125 mg as a single dose or as multiple daily doses for 2 weeks reduces plasma levels of ritonavir by about 16%. However, atazanavir levels still remains high enough to prevent HIV virus replication. Therefore, the decrease in ritonavir levels is not likely to be clinically significant.
Tetracycline Antibiotics
Zinc might reduce levels of tetracycline antibiotics.
Tetracyclines form complexes with zinc in the gastrointestinal tract, which can reduce absorption of both the tetracycline and zinc when taken at the same time. Taking zinc sulfate 200 mg with tetracycline reduces absorption of the antibiotic by 30% to 40%. Demeclocycline and minocycline cause a similar interaction. However, doxycycline does not seem to interact significantly with zinc. Advise patients to take tetracyclines at least 2 hours before, or 4-6 hours after, zinc supplements to avoid any interactions.
Amiloride (Midamor)
Amiloride can modestly reduce zinc excretion and increase zinc levels.
Clinical research shows that amiloride can reduce urinary zinc excretion, especially at doses of 10 mg per day or more. This zinc-sparing effect can help to counteract zinc losses caused by thiazide diuretics, but it is unlikely to cause zinc toxicity at usual amiloride doses. The other potassium-sparing diuretics, spironolactone (Aldactone) and triamterene (Dyrenium), do not seem to have a zinc-sparing effect.
Atazanavir (Reyataz)
Zinc modestly reduces levels of atazanavir, although this effect does not seem to be clinically significant.
Clinical research shows that zinc might decrease serum atazanavir levels by chelating with atazanavir in the gut and preventing its absorption. Although a single dose of zinc sulfate (Solvazinc tablets) 125 mg orally does not affect atazanavir concentrations in patients being treated with atazanavir/ritonavir, co-administration of zinc sulfate 125 mg daily for 2 weeks reduces plasma levels of atazanavir by about 22% in these patients. However, despite this decrease, atazanavir levels still remain at high enough concentrations for the prevention of HIV virus replication.
Potassium
Ace Inhibitors (Aceis)
Using ACEIs with high doses of potassium increases the risk of hyperkalemia.
ACEIs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Angiotensin Receptor Blockers (Arbs)
Using ARBs with high doses of potassium increases the risk of hyperkalemia.
ARBs block the actions of the renin-angiotensin-aldosterone system and reduce potassium excretion. Concomitant use of these drugs with potassium supplements increases the risk of hyperkalemia. However, concomitant use of these drugs with moderate dietary potassium intake (about 3775-5200 mg daily) does not increase serum potassium levels.
Potassium-Sparing Diuretics
Concomitant use increases the risk of hyperkalemia.
Using potassium-sparing diuretics with potassium supplements increases the risk of hyperkalemia.
Folic Acid
5-Fluorouracil
Theoretically, high doses of folic acid might increase the toxicity of 5-fluorouracil.
Increases in gastrointestinal side effects of 5-fluorouracil, such as stomatitis and diarrhea, have been described in two clinical studies when leucovorin, a form of folic acid, was administered with 5-fluorouracil.
Capecitabine (Xeloda)
Use of high-dose folic acid might contribute to capecitabine toxicity.
Clinical research suggests that higher serum folate levels are associated with an increased risk for moderate or severe toxicity during capecitabine-based treatment for colorectal cancer. Additionally, in one case report, taking folic acid 15 mg daily might have contributed to increased toxicity, including severe diarrhea, vomiting, edema, hand-foot syndrome, and eventually death, in a patient prescribed capecitabine.
Methotrexate (Trexall, Others)
Folic acid might reduce the efficacy of methotrexate as a cancer treatment when given concurrently.
Methotrexate exerts its cytotoxic effects by preventing conversion of folic acid to the active form needed by cells. There is some evidence that folic acid supplements reduce the efficacy of methotrexate in the treatment of acute lymphoblastic leukemia, and theoretically they could reduce its efficacy in the treatment of other cancers. Advise cancer patients to consult their oncologist before using folic acid supplements. In patients treated with long-term, low-dose methotrexate for rheumatoid arthritis (RA) or psoriasis, folic acid supplements can reduce the incidence of side effects, without reducing efficacy.
Phenobarbital (Luminal)
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of phenobarbital and worsening seizure control. Monitor closely for increased seizure activity.
Phenytoin (Dilantin)
Folic acid might reduce serum levels of phenytoin in some patients.
Folic acid may be a cofactor in phenytoin metabolism. Folic acid, in doses of 1 mg daily or more, can reduce serum levels of phenytoin in some patients. Increases in seizure frequency have been reported. If folic acid supplements are added to established phenytoin therapy, monitor serum phenytoin levels closely. If phenytoin and folic acid are started at the same time and continued together, adverse changes in phenytoin pharmacokinetics are avoided. Note that phenytoin also reduces serum folate levels.
Primidone (Mysoline)
Folic acid might have antagonistic effects on primidone and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of primidone and worsening seizure control. Monitor closely for increased seizure activity. Note that primidone also reduces serum folate levels.
Pyrimethamine (Daraprim)
Folic acid might antagonize the effects of pyrimethamine.
Folic acid can antagonize the antiparasitic effects of pyrimethamine against toxoplasmosis and Pneumocystis carinii pneumonia. Folic acid doesn't antagonize the effects of pyrimethamine in the treatment of malaria, because malarial parasites cannot use exogenous folic acid. Use folinic acid as an alternative to folic acid when indicated.
Copper
Penicillamine (Cuprimine, Depen)
Theoretically, taking copper with penicillamine might decrease the absorption of penicillamine; separate dosing by at least 2 hours.
Copper chelates penicillamine, which decreases its absorption and may reduce its clinical effects.
Contraceptive Drugs
Theoretically, taking copper with contraceptive drugs might increase the levels and toxic effects of copper.
A meta-analysis of clinical studies suggests that chronic use of oral contraceptives increases serum copper levels by a mean of 57 mcg/dL. In most people, this resulted in levels above the normal reference range for copper.
L-Tyrosine
Levodopa
Theoretically, tyrosine might decrease the effectiveness of levodopa.
Tyrosine and levodopa compete for absorption in the proximal duodenum by the large neutral amino acid (LNAA) transport system. Advise patients to separate doses of tyrosine and levodopa by at least 2 hours.
Thyroid Hormone
Theoretically, tyrosine might have additive effects with thyroid hormone medications.
Tyrosine is a precursor to thyroxine and might increase levels of thyroid hormones.
Vitamin B12
Metformin (Glucophage)
Metformin, a common medication used to manage type 2 diabetes, has been associated with lower vitamin B12 levels in some individuals. Prolonged use of metformin can interfere with the absorption of B12 in the digestive system, potentially leading to a deficiency in this essential vitamin.
L-Phenylalanine
Levodopa
Phenylalanine, especially in high doses, can reduce the effectiveness of levodopa.
Phenylalanine competes with levodopa for carrier-mediated transport into the brain. The resulting reduction in levels of levodopa in the brain can exacerbate tremor, rigidity, and the "on-off" phenomenon in patients with Parkinson disease.
Baclofen
Concomitant intake of phenylalanine may reduce the intestinal absorption of baclofen.
Phenylalanine and baclofen share the same intestinal carrier for absorption; phenylalanine competitively inhibits the absorption of baclofen, reducing its plasma levels.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use of L-phenylalanine and non-selective MAOIs might increase the risk of hypertensive crisis.
L-phenylalanine is metabolized to tyrosine. Some evidence suggests that L-phenylalanine, given with the non-selective MAOI pargyline, might prevent the elimination of tyramine, increasing the risk of hypertensive crisis. However, this was not reported in a small number of patients when using L-phenylalanine with the partially selective MAO-B inhibitor, selegiline.
Glycine
Clozapine (Clozaril)
Theoretically, glycine might decrease the effectiveness of clozapine.
One small clinical study in patients with schizophrenia shows that adding glycine to clozapine therapy worsens symptoms of schizophrenia when compared with clozapine alone. The mechanism of this interaction is unclear.
Brand information
Manufacturer and brand details for AcaI Advanced Energy, from the product label.
Isotonix
See all Isotonix products- Name
- Market America, Inc.
- Street Address
- 1302 Pleasant Ridge Road
- City
- Greensboro
- State
- NC
- ZipCode
- 27409
AcaI Advanced Energy by Isotonix: Common Questions
Does AcaI Advanced Energy by Isotonix interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Does this product have caffeine?
Is this safe to take if I'm pregnant?
Will this help me lose weight?
Can I take this if I have a seizure disorder?
What are the most common side effects?
Is there any ingredient this product doesn't have data on?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if AcaI Advanced Energy is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind AcaI Advanced Energy’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Pantothenic Acid
Pantothenic acid is vitamin B5, an essential nutrient your body uses to turn food into energy. True deficiency is very rare because it is found in nearly all foods, and most people meet thei...
Read the full Pantothenic Acid monograph → Herb & supplement monographTaurine
Interacts with 173 drugsTaurine is an amino acid your body makes naturally and that you also get from animal foods. It is widely used in energy drinks and sports supplements, and short-term use appears generally sa...
Read the full Taurine monograph → Herb & supplement monographVitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph → Herb & supplement monographFolic Acid
Interacts with 40 drugsFolic acid is the man-made form of vitamin B9 and is one of the most well-studied supplements, especially for preventing serious birth defects when taken before and during early pregnancy. I...
Read the full Folic Acid monograph → Herb & supplement monographGreen Tea
Interacts with 1,293 drugsGreen tea is a popular beverage rich in antioxidants called catechins, and drinking it in normal amounts is considered safe for most people. Concentrated green tea extracts are a different s...
Read the full Green Tea monograph → Herb & supplement monographGuarana
Interacts with 655 drugsGuarana is an Amazonian seed that is naturally high in caffeine, which explains most of its stimulant and energy effects. While it may give a short-term boost in alertness and reduce fatigue...
Read the full Guarana monograph → Herb & supplement monographCaffeine
Interacts with 655 drugsCaffeine is a natural stimulant found in coffee, tea, and many other plants and products. In moderate amounts it can boost alertness and reduce tiredness for most healthy adults, but too muc...
Read the full Caffeine monograph → Herb & supplement monographZinc
Interacts with 67 drugsZinc is an essential mineral that your body needs for immune function, wound healing, taste, and smell. Most people get enough from food, but supplements can help correct or prevent a defici...
Read the full Zinc monograph → Herb & supplement monographTyrosine
Interacts with 21 drugsL-tyrosine is an amino acid your body uses to make brain chemicals like dopamine and norepinephrine. Some studies suggest it may help mental performance during short-term stress, sleep loss,...
Read the full Tyrosine monograph → Herb & supplement monographGlycine
Interacts with 1 drugGlycine is a non-essential amino acid your body makes on its own and that also appears in protein-rich foods. It is most studied for improving sleep quality, where early research is promisin...
Read the full Glycine monograph → Herb & supplement monographCopper
Interacts with 31 drugsCopper is an essential trace mineral your body needs in small amounts for making red blood cells, supporting nerves and bones, and helping enzymes work. Most people get enough copper from fo...
Read the full Copper monograph → Herb & supplement monographVitamin B12
Interacts with 20 drugsVitamin B12 (cobalamin) is an essential nutrient your body needs to make red blood cells, keep nerves healthy, and support DNA. Supplements are very helpful for people who are deficient — su...
Read the full Vitamin B12 monograph → Herb & supplement monographPhenylalanine
Interacts with 16 drugsPhenylalanine is an essential amino acid the body uses to make brain chemicals like dopamine and norepinephrine. Some people take it for mood, vitiligo, or pain, but the evidence is mostly l...
Read the full Phenylalanine monograph → Herb & supplement monographPotassium
Interacts with 62 drugsPotassium is an essential mineral your body needs for nerve signals, muscle function, and a steady heartbeat, and most people get enough from a balanced diet rich in fruits and vegetables. P...
Read the full Potassium monograph → Herb & supplement monographNiacinamide
Interacts with 124 drugsNiacinamide (also called nicotinamide) is a form of vitamin B3 used in supplements and skin-care products. It is well established for preventing and treating vitamin B3 deficiency, and there...
Read the full Niacinamide monograph → Herb & supplement monographSodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographVitamin B6
Interacts with 210 drugsVitamin B6 (pyridoxine) is an essential water-soluble vitamin that your body needs for metabolism, brain function, and making red blood cells. It is best known for helping with pregnancy-rel...
Read the full Vitamin B6 monograph → Herb & supplement monographYerba Mate
Interacts with 1,086 drugsYerba mate is a caffeine-containing herbal beverage from South America that is widely enjoyed for its stimulating, coffee-like effects. While it is rich in antioxidants and is being studied...
Read the full Yerba Mate monograph → Herb & supplement monographAcai
Interacts with 86 drugsAcai is a nutritious Amazonian berry rich in antioxidants and healthy fats, and it is fine to enjoy as a food. However, strong human evidence is lacking for the bold health claims often atta...
Read the full Acai monograph → Herb & supplement monographMangosteen
Interacts with 125 drugsMangosteen is a tropical fruit whose rind is rich in plant compounds called xanthones that act as antioxidants. While it is popular in juices and supplements for inflammation, immune support...
Read the full Mangosteen monograph → Herb & supplement monographPomegranate
Interacts with 922 drugsPomegranate is a nutrient-rich fruit that is high in antioxidants and is widely enjoyed as food and juice. Early research suggests it may support heart health and blood pressure, but the evi...
Read the full Pomegranate monograph →Sources & How We Checked
AcaI Advanced Energy's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 1,131 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Pantothenic Acid 11 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Debourdeau PM, Djezzar S, Estival JL, et al. Life-threatening eosinophilic pleuropericardial effusion related to vitamins B5 and H. Ann Pharmacother 2001;35:424-6. DOI
- Schmuth, M., Wimmer, M. A., Hofer, S., Sztankay, A., Weinlich, G., Linder, D. M., Elias, P. M., Fritsch, P. O., and Fritsch, E. Topical corticosteroid therapy for acute radiation dermatitis: a prospective, randomized, double-blind study. Br.J.Dermatol. 2 PubMed
- Schreck, U., Paulsen, F., Bamberg, M., and Budach, W. Intraindividual comparison of two different skin care conceptions in patients undergoing radiotherapy of the head-and-neck region. Creme or powder? Strahlenther.Onkol. 2002;178(6):321-329. PubMed
- Herbst, R. A., Uter, W., Pirker, C., Geier, J., and Frosch, P. J. Allergic and non-allergic periorbital dermatitis: patch test results of the Information Network of the Departments of Dermatology during a 5-year period. Contact Dermatitis 2004;51(1):13-1 PubMed
- Champault, G. and Patel, J. C. [Treatment of constipation with Bepanthene]. Med.Chir Dig. 1977;6(1):57-59.
- Scott LN, Fiume M, Bergfeld WF, et al. Safety Assessment of Panthenol, Pantothenic Acid, and Derivatives as Used in Cosmetics. Int J Toxicol 2022;41(3_suppl):77-128. PubMed
- Han J, Warshaw EM. Allergic Contact Dermatitis to Panthenol in "Hypoallergenic" Products. Dermatitis 2023;34(1):62-63. PubMed
- Blanchard G, Kerre S, Walker A, et al. Allergic contact dermatitis from pantolactone and dexpanthenol in wound healing creams. Contact Dermatitis 2022;87(5):468-471. PubMed
- Peltier E, Trapp S, de Salvo R, et al. A new dexpanthenol-containing liquid cleanser for atopic-prone skin: Results from two prospective clinical studies evaluating cutaneous tolerability, moisturization potential, and effects on barrier function. J Cosme PubMed
Taurine 21 references
- Ahmad S, Robertson HT, Golper TA, et al. Multicenter trial of L-carnitine in maintenance hemodialysis patients. II. Clinical and biochemical effects. Kidney Int 1990;38:912-8. PubMed
- Machado-Vieira R, Viale CI, Kapczinski F. Mania associated with an energy drink: the possible role of caffeine, taurine, and inositol. Can J Psychiatry 2001;46:454-5. PubMed
- Obermann M, Schorn CF, Mummel P, et al. Taurine induced toxic encephalopathy? Clin Neurol Neurosurg 2006;108:812-3. PubMed
- Bichler, A., Swenson, A., and Harris, M. A. A combination of caffeine and taurine has no effect on short term memory but induces changes in heart rate and mean arterial blood pressure. Amino Acids 2006;31(4):471-476. PubMed
- Iyadurai, S. J. and Chung, S. S. New-onset seizures in adults: possible association with consumption of popular energy drinks. Epilepsy Behav 2007;10(3):504-508. PubMed
- Berger, A. J. and Alford, K. Cardiac arrest in a young man following excess consumption of caffeinated "energy drinks". Med J Aust. 1-5-2009;190(1):41-43. PubMed
- Worthley, M. I., Prabhu, A., De, Sciscio P., Schultz, C., Sanders, P., and Willoughby, S. R. Detrimental effects of energy drink consumption on platelet and endothelial function. Am J Med 2010;123(2):184-187. PubMed
- Morchon, Simon D. and Perez Castrillon, J. L. [Hypoglycemia by intake of taurine]. Rev.Clin Esp. 2010;210(1):49.
- Livshits, Z., Hoffman, R. S., Hymes, K. B., and Nelson, L. S. If vitamins could kill: massive hemolysis following naturopathic vitamin infusion. J Med Toxicol. 2011;7(3):224-226. PubMed
- Schoffl, I., Kothmann, J. F., Schoffl, V., Rupprecht, H. D., and Rupprecht, T. "Vodka energy": too much for the adolescent nephron? Pediatrics 2011;128(1):e227-e231. PubMed
- Calabro, R. S., Italiano, D., Gervasi, G., and Bramanti, P. Single tonic-clonic seizure after energy drink abuse. Epilepsy Behav 2012;23(3):384-385. PubMed
- Fujita, T., Ando, K., Noda, H., Ito, Y., and Sato, Y. Effects of increased adrenomedullary activity and taurine in young patients with borderline hypertension. Circulation 1987;75(3):525-532. PubMed
- Darling, P. B., Lepage, G., Leroy, C., Masson, P., and Roy, C. C. Effect of taurine supplements on fat absorption in cystic fibrosis. Pediatr Res 1985;19(6):578-582. PubMed
- Fukuyama, Y. and Ochiai, Y. Therapeutic trial by taurine for intractable childhood epilepsies. Brain Dev. 1982;4(1):63-69. PubMed
- Franconi, F., Bennardini, F., Mattana, A., Miceli, M., Ciuti, M., Mian, M., Gironi, A., Anichini, R., and Seghieri, G. Plasma and platelet taurine are reduced in subjects with insulin-dependent diabetes mellitus: effects of taurine supplementation. Am.J. DOI
- Stohs SJ, Miller M. A case study involving allergic reactions to sulfur-containing compounds including, sulfite, taurine, acesulfame potassium and sulfonamides. Food Chem Toxicol. 2014 Jan;63:240-3. PubMed
- Sun Q, Wang B, Li Y, Sun F, et al. Taurine supplementation lowers blood pressure and improves vascular function in prehypertension: randomized, double-blind, placebo-controlled study. Hypertension 2016 Mar;67(3):541-9. PubMed
- Jang ES, Hwang SH, Kim JW, Jeong SH. Effectiveness of 4-week oral taurine treatment for muscle cramps in patients with liver cirrhosis: a single-arm pilot study. Yonsei Med J 2021;62(1):21-8. PubMed
- Guan L, Miao P. The effects of taurine supplementation on obesity, blood pressure and lipid profile: A meta-analysis of randomized controlled trials. Eur J Pharmacol 2020;885:173533. PubMed
- Higgins JP, Liras GN, Liras IN, et al. Energy Drink Effects on Hemodynamics and Endothelial Function in Young Adults. Cardiology. 2021;146(2):258-262. PubMed
- Pallangyo P, Bhalia SV, Komba M, et al. Acute Myocardial Infarction Following the Consumption of Energy Drink in a 28-Year-Old Male: A Case Report. J Investig Med High Impact Case Rep. 2023 Jan-Dec;11:23247096231168811. PubMed
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Caffeine 236 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Tobias JD. Caffeine in the treatment of apnea associated with respiratory syncytial virus infection in neonates and infants. South Med J 2000;93:297-304. DOI
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Avisar R, Avisar E, Weinberger D. Effect of coffee consumption on intraocular pressure. Ann Pharmacother 2002;36:992-5.. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Dreher HM. The effect of caffeine reduction on sleep quality and well-being in persons with HIV. J Psychosom Res 2003;54:191-8.. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Schechter MD, Timmons GD. Objectively measured hyperactivity--II. Caffeine and amphetamine effects. J Clin Pharmacol 1985;25:276-80.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Balogh, A., Klinger, G., Henschel, L., Borner, A., Vollanth, R., and Kuhnz, W. Influence of ethinylestradiol-containing combination oral contraceptives with gestodene or levonorgestrel on caffeine elimination. Eur.J.Clin.Pharmacol. 1995;48(2):161-166. PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Bailey, D. N., Weibert, R. T., Naylor, A. J., and Shaw, R. F. A study of salicylate and caffeine excretion in the breast milk of two nursing mothers. J.Anal.Toxicol. 1982;6(2):64-68. PubMed
- Griffiths, R. R. and Chausmer, A. L. Caffeine as a model drug of dependence: recent developments in understanding caffeine withdrawal, the caffeine dependence syndrome, and caffeine negative reinforcement. Nihon Shinkei Seishin Yakurigaku Zasshi 2000;20(
- Karacan, I., Thornby, J. I., Anch, M., Booth, G. H., Williams, R. L., and Salis, P. J. Dose-related sleep disturbances induced by coffee and caffeine. Clin Pharmacol Ther 1976;20(6):682-689. PubMed
- Quirce, G. S., Freire, P., Fernandez, R. M., Davila, I., and Losada, E. Urticaria from caffeine. J.Allergy Clin Immunol. 1991;88(4):680-681. PubMed
- Hughes, J. R., Higgins, S. T., Bickel, W. K., Hunt, W. K., Fenwick, J. W., Gulliver, S. B., and Mireault, G. C. Caffeine self-administration, withdrawal, and adverse effects among coffee drinkers. Arch.Gen.Psychiatry 1991;48(7):611-617. PubMed
- Adams, B. A. and Brubaker, R. F. Caffeine has no clinically significant effect on aqueous humor flow in the normal human eye. Ophthalmology 1990;97(8):1030-1031. PubMed
- Davis, R. H. Does caffeine ingestion affect intraocular pressure?. Ophthalmology 1989;96(11):1680-1681. PubMed
- Higginbotham, E. J., Kilimanjaro, H. A., Wilensky, J. T., Batenhorst, R. L., and Hermann, D. The effect of caffeine on intraocular pressure in glaucoma patients. Ophthalmology 1989;96(5):624-626.
- Wrenn, K. D. and Oschner, I. Rhabdomyolysis induced by a caffeine overdose. Ann.Emerg.Med. 1989;18(1):94-97. PubMed
- Pola, J., Subiza, J., Armentia, A., Zapata, C., Hinojosa, M., Losada, E., and Valdivieso, R. Urticaria caused by caffeine. Ann.Allergy 1988;60(3):207-208.
- Lane, J. D. and Williams, R. B., Jr. Cardiovascular effects of caffeine and stress in regular coffee drinkers. Psychophysiology 1987;24(2):157-164. PubMed
- Shirlow, M. J. and Mathers, C. D. A study of caffeine consumption and symptoms; indigestion, palpitations, tremor, headache and insomnia. Int.J.Epidemiol. 1985;14(2):239-248. PubMed
- Stillner, V., Popkin, M. K., and Pierce, C. M. Caffeine-induced delirium during prolonged competitive stress. Am.J.Psychiatry 1978;135(7):855-856. PubMed
- Levy, M. and Zylber-Katz, E. Caffeine metabolism and coffee-attributed sleep disturbances. Clin Pharmacol Ther 1983;33(6):770-775. PubMed
- Brown, S. L., Salive, M. E., Pahor, M., Foley, D. J., Corti, M. C., Langlois, J. A., Wallace, R. B., and Harris, T. B. Occult caffeine as a source of sleep problems in an older population. J.Am.Geriatr.Soc. 1995;43(8):860-864. PubMed
- Sung, B. H., Whitsett, T. L., Lovallo, W. R., al'Absi, M., Pincomb, G. A., and Wilson, M. F. Prolonged increase in blood pressure by a single oral dose of caffeine in mildly hypertensive men. Am.J Hypertens. 1994;7(8):755-758. PubMed
- Caballero, T., Garcia-Ara, C., Pascual, C., Diaz-Pena, J. M., and Ojeda, A. Urticaria induced by caffeine. J.Investig.Allergol.Clin Immunol. 1993;3(3):160-162.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- Garrett, B. E. and Griffiths, R. R. Physical dependence increases the relative reinforcing effects of caffeine versus placebo. Psychopharmacology (Berl) 1998;139(3):195-202. PubMed
- Lane, J. D. and Phillips-Bute, B. G. Caffeine deprivation affects vigilance performance and mood. Physiol Behav. 1998;65(1):171-175. PubMed
- Boekema, P. J., Samsom, M., van Berge Henegouwen, G. P., and Smout, A. J. Coffee and gastrointestinal function: facts and fiction. A review. Scand J Gastroenterol.Suppl 1999;230:35-39. PubMed
- Terry, P., Lagergren, J., Wolk, A., and Nyren, O. Reflux-inducing dietary factors and risk of adenocarcinoma of the esophagus and gastric cardia. Nutr Cancer 2000;38(2):186-191.
- Pollak, C. P. and Bright, D. Caffeine consumption and weekly sleep patterns in US seventh-, eighth-, and ninth-graders. Pediatrics 2003;111(1):42-46. PubMed
- DiBaise, J. K. A randomized, double-blind comparison of two different coffee-roasting processes on development of heartburn and dyspepsia in coffee-sensitive individuals. Dig.Dis.Sci 2003;48(4):652-656. PubMed
- Wang, J. H., Luo, J. Y., Dong, L., Gong, J., and Tong, M. Epidemiology of gastroesophageal reflux disease: a general population-based study in Xi'an of Northwest China. World J Gastroenterol. 6-1-2004;10(11):1647-1651. PubMed
- Naliboff, B. D., Mayer, M., Fass, R., Fitzgerald, L. Z., Chang, L., Bolus, R., and Mayer, E. A. The effect of life stress on symptoms of heartburn. Psychosom.Med 2004;66(3):426-434. PubMed
- Massey, L. K. and Sutton, R. A. Acute caffeine effects on urine composition and calcium kidney stone risk in calcium stone formers. J.Urol. 2004;172(2):555-558. PubMed
- Tavani, A. and La, Vecchia C. Coffee, decaffeinated coffee, tea and cancer of the colon and rectum: a review of epidemiological studies, 1990-2003. Cancer Causes Control 2004;15(8):743-757. PubMed
- Noordzij, M., Uiterwaal, C. S., Arends, L. R., Kok, F. J., Grobbee, D. E., and Geleijnse, J. M. Blood pressure response to chronic intake of coffee and caffeine: a meta-analysis of randomized controlled trials. J Hypertens. 2005;23(5):921-928. PubMed
- Chandrasekaran, S., Rochtchina, E., and Mitchell, P. Effects of caffeine on intraocular pressure: the Blue Mountains Eye Study. J Glaucoma. 2005;14(6):504-507. PubMed
- Morgan, J. C. and Sethi, K. D. Drug-induced tremors. Lancet Neurol. 2005;4(12):866-876. PubMed
- Doan, B. K., Hickey, P. A., Lieberman, H. R., and Fischer, J. R. Caffeinated tube food effect on pilot performance during a 9-hour, simulated nighttime U-2 mission. Aviat.Space Environ Med 2006;77(10):1034-1040.
- Whalen, D. J., Silk, J. S., Semel, M., Forbes, E. E., Ryan, N. D., Axelson, D. A., Birmaher, B., and Dahl, R. E. Caffeine consumption, sleep, and affect in the natural environments of depressed youth and healthy controls. J Pediatr.Psychol. 2008;33(4):35 PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Mort, J. R. and Kruse, H. R. Timing of blood pressure measurement related to caffeine consumption. Ann Pharmacother. 2008;42(1):105-110.
- Ganmaa, D., Willett, W. C., Li, T. Y., Feskanich, D., van Dam, R. M., Lopez-Garcia, E., Hunter, D. J., and Holmes, M. D. Coffee, tea, caffeine and risk of breast cancer: a 22-year follow-up. Int J Cancer 5-1-2008;122(9):2071-2076. PubMed
- Killgore, W. D., Rupp, T. L., Grugle, N. L., Reichardt, R. M., Lipizzi, E. L., and Balkin, T. J. Effects of dextroamphetamine, caffeine and modafinil on psychomotor vigilance test performance after 44 h of continuous wakefulness. J Sleep Res 2008;17(3):3 PubMed
- Ozsungur, S., Brenner, D., and El-Sohemy, A. Fourteen well-described caffeine withdrawal symptoms factor into three clusters. Psychopharmacology (Berl) 2009;201(4):541-548. PubMed
- Ishitani, K., Lin, J., Manson, J. E., Buring, J. E., and Zhang, S. M. Caffeine consumption and the risk of breast cancer in a large prospective cohort of women. Arch Intern Med 10-13-2008;168(18):2022-2031. PubMed
- Tunnicliffe, J. M., Erdman, K. A., Reimer, R. A., Lun, V., and Shearer, J. Consumption of dietary caffeine and coffee in physically active populations: physiological interactions. Appl Physiol Nutr Metab 2008;33(6):1301-1310. PubMed
- Sin, C. W., Ho, J. S., and Chung, J. W. Systematic review on the effectiveness of caffeine abstinence on the quality of sleep. J Clin Nurs. 2009;18(1):13-21. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Killgore, W. D., Kahn-Greene, E. T., Grugle, N. L., Killgore, D. B., and Balkin, T. J. Sustaining executive functions during sleep deprivation: A comparison of caffeine, dextroamphetamine, and modafinil. Sleep 2-1-2009;32(2):205-216. PubMed
- Natale, F., Cirillo, C., Di Marco, G. M., di Vetta, L. S., Aronne, L., Siciliano, A., Mocerino, R., Tedesco, M. A., Golino, P., and Calabro, R. When chewing gum is more than just a bad habit. Lancet 5-30-2009;373(9678):1918. PubMed
- Calamaro, C. J., Mason, T. B., and Ratcliffe, S. J. Adolescents living the 24/7 lifestyle: effects of caffeine and technology on sleep duration and daytime functioning. Pediatrics 2009;123(6):e1005-e1010. PubMed
- Koran, L. M., Aboujaoude, E., and Gamel, N. N. Double-blind study of dextroamphetamine versus caffeine augmentation for treatment-resistant obsessive-compulsive disorder. J Clin Psychiatry 2009;70(11):1530-1535. PubMed
- Luebbe, A. M. and Bell, D. J. Mountain Dew or mountain don't?: a pilot investigation of caffeine use parameters and relations to depression and anxiety symptoms in 5th- and 10th-grade students. J Sch Health 2009;79(8):380-387.
- Skouroliakou, M., Bacopoulou, F., and Markantonis, S. L. Caffeine versus theophylline for apnea of prematurity: a randomised controlled trial. J Paediatr.Child Health 2009;45(10):587-592. PubMed
- Urade, Y. [Molecular mechanisms of insomnia]. Nippon Rinsho 2009;67(8):1489-1493.
- Montandon, G., Horner, R. L., Kinkead, R., and Bairam, A. Caffeine in the neonatal period induces long-lasting changes in sleep and breathing in adult rats. J Physiol 11-15-2009;587(Pt 22):5493-5507. PubMed
- Addicott, M. A. and Laurienti, P. J. A comparison of the effects of caffeine following abstinence and normal caffeine use. Psychopharmacology (Berl) 2009;207(3):423-431. PubMed
- Hashim, H. and Al, Mousa R. Management of fluid intake in patients with overactive bladder. Curr.Urol.Rep. 2009;10(6):428-433. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Attwood, A., Terry, P., and Higgs, S. Conditioned effects of caffeine on performance in humans. Physiol Behav 3-3-2010;99(3):286-293. PubMed
- Skinner, T. L., Jenkins, D. G., Coombes, J. S., Taaffe, D. R., and Leveritt, M. D. Dose response of caffeine on 2000-m rowing performance. Med Sci Sports Exerc. 2010;42(3):571-576. PubMed
- Holick, C. N., Smith, S. G., Giovannucci, E., and Michaud, D. S. Coffee, tea, caffeine intake, and risk of adult glioma in three prospective cohort studies. Cancer Epidemiol.Biomarkers Prev 2010;19(1):39-47. PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Greenwood, D. C., Alwan, N., Boylan, S., Cade, J. E., Charvill, J., Chipps, K. C., Cooke, M. S., Dolby, V. A., Hay, A. W., Kassam, S., Kirk, S. F., Konje, J. C., Potdar, N., Shires, S., Simpson, N., Taub, N., Thomas, J. D., Walker, J., White, K. L., and
- Mevcha, A., Gulur, D. M., and Gillatt, D. Diagnosing urological disorders in ageing men. Practitioner 2010;254(1726):25-9, 2.
- Brick, C. A., Seely, D. L., and Palermo, T. M. Association between sleep hygiene and sleep quality in medical students. Behav Sleep Med 2010;8(2):113-121. PubMed
- Digdon, N. L. Circadian preference and college students' beliefs about sleep education. Chronobiol.Int 2010;27(2):297-317. PubMed
- Boos, C. J., White, S. H., Bland, S. A., and McAllister, P. D. Dietary supplements and military operations: caution is advised. J R.Army Med Corps 2010;156(1):41-43. PubMed
- Casiglia, E., Bongiovi, S., Paleari, C. D., Petucco, S., Boni, M., Colangeli, G., Penzo, M., and Pessina, A. C. Haemodynamic effects of coffee and caffeine in normal volunteers: a placebo-controlled clinical study. J.Intern.Med. 1991;229(6):501-504. PubMed
- Aguggia, M. and Saracco, M. G. Pathophysiology of migraine chronification. Neurol.Sci 2010;31 Suppl 1:S15-S17. PubMed
- Torelli, P. and Manzoni, G. C. Fasting headache. Curr Pain Headache Rep. 2010;14(4):284-291.
- Farag, N. H., Whitsett, T. L., McKey, B. S., Wilson, M. F., Vincent, A. S., Everson-Rose, S. A., and Lovallo, W. R. Caffeine and blood pressure response: sex, age, and hormonal status. J Womens Health (Larchmt.) 2010;19(6):1171-1176. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Suen, L. K., Tam, W. W., and Hon, K. L. Association of sleep hygiene-related factors and sleep quality among university students in Hong Kong. Hong.Kong.Med.J 2010;16(3):180-185.
- Stafford, L. D., Wright, C., and Yeomans, M. R. The drink remains the same: implicit positive associations in high but not moderate or non-caffeine users. Psychol.Addict.Behav. 2010;24(2):274-281. PubMed
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Freire, R. C., Perna, G., and Nardi, A. E. Panic disorder respiratory subtype: psychopathology, laboratory challenge tests, and response to treatment. Harv.Rev.Psychiatry 2010;18(4):220-229. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Kujawa-Hadrys, M., Tosik, D., and Bartel, H. Changes in thickness of each layer of developing chicken cornea after administration of caffeine. Folia Histochem.Cytobiol. 2010;48(2):273-277. PubMed
- Boggs, D. A., Palmer, J. R., Stampfer, M. J., Spiegelman, D., Adams-Campbell, L. L., and Rosenberg, L. Tea and coffee intake in relation to risk of breast cancer in the Black Women's Health Study. Cancer Causes Control 2010;21(11):1941-1948. PubMed
- Li, S., Zhu, S., Jin, X., Yan, C., Wu, S., Jiang, F., and Shen, X. Risk factors associated with short sleep duration among Chinese school-aged children. Sleep Med. 2010;11(9):907-916. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Knight, J. M., Avery, E. F., Janssen, I., and Powell, L. H. Cortisol and depressive symptoms in a population-based cohort of midlife women. Psychosom.Med. 2010;72(9):855-861. PubMed
- Porkka-Heiskanen, T. Methylxanthines and sleep. Handb.Exp.Pharmacol 2011;(200):331-348. PubMed
- Mostofsky, E., Schlaug, G., Mukamal, K. J., Rosamond, W. D., and Mittleman, M. A. Coffee and acute ischemic stroke onset: the Stroke Onset Study. Neurology 11-2-2010;75(18):1583-1588. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Li, G. Z., Zhang, N., Du, P., Yang, Y., Wu, S. L., Xiao, Y. X., Jin, R., Liu, L., Shen, H., and Dai, Y. Risk factors for interstitial cystitis/painful bladder syndrome in patients with lower urinary tract symptoms: a Chinese multi-center study. Chin Med
- Duvnjak-Zaknich, D. M., Dawson, B. T., Wallman, K. E., and Henry, G. Effect of caffeine on reactive agility time when fresh and fatigued. Med.Sci.Sports Exerc. 2011;43(8):1523-1530. PubMed
- Astorino, T. A., Martin, B. J., Schachtsiek, L., Wong, K., and Ng, K. Minimal effect of acute caffeine ingestion on intense resistance training performance. J Strength.Cond.Res 2011;25(6):1752-1758. PubMed
- Kivity, S., Ben Aharon, Y., Man, A., and Topilsky, M. The effect of caffeine on exercise-induced bronchoconstriction. Chest 1990;97(5):1083-1085. PubMed
- Lubin, F. and Ron, E. Consumption of methylxanthine-containing beverages and the risk of breast cancer. Cancer Lett. 1990;53(2-3):81-90. PubMed
- Smits, P., Lenders, J. W., and Thien, T. Caffeine and theophylline attenuate adenosine-induced vasodilation in humans. Clin.Pharmacol.Ther. 1990;48(4):410-418. PubMed
- Rossignol, A. M. and Bonnlander, H. Caffeine-containing beverages, total fluid consumption, and premenstrual syndrome. Am.J.Public Health 1990;80(9):1106-1110. PubMed
- Birkett, N. J. and Logan, A. G. Caffeine-containing beverages and the prevalence of hypertension. J Hypertens.Suppl 1988;6(4):S620-S622. PubMed
- Fraumeni, J. F., Jr., Scotto, J., and Dunham, L. J. Coffee-drinking and bladder cancer. Lancet 11-27-1971;2(7735):1204. PubMed
- Greden, J. F. Anxiety or caffeinism: a diagnostic dilemma. Am J Psychiatry 1974;131(10):1089-1092. PubMed
- Whitsett, T. L., Manion, C. V., and Christensen, H. D. Cardiovascular effects of coffee and caffeine. Am.J.Cardiol. 3-15-1984;53(7):918-922. PubMed
- Firestone, P., Poitras-Wright, H., and Douglas, V. The effects of caffeine on hyperactive children. J.Learn.Disabil. 1978;11(3):133-141. PubMed
- Thomas, F. B., Steinbaugh, J. T., Fromkes, J. J., Mekhjian, H. S., and Caldwell, J. H. Inhibitory effect of coffee on lower esophageal sphincter pressure. Gastroenterology 1980;79(6):1262-1266. DOI
- Linn, S., Schoenbaum, S. C., Monson, R. R., Rosner, B., Stubblefield, P. G., and Ryan, K. J. No association between coffee consumption and adverse outcomes of pregnancy. N.Engl.J Med 1-21-1982;306(3):141-145. PubMed
- Cohen, S. Pathogenesis of coffee-induced gastrointestinal symptoms. N.Engl.J Med 7-17-1980;303(3):122-124. PubMed
- Feldman, M. and Barnett, C. Relationships between the acidity and osmolality of popular beverages and reported postprandial heartburn. Gastroenterology 1995;108(1):125-131. PubMed
- Quinlan, P., Lane, J., and Aspinall, L. Effects of hot tea, coffee and water ingestion on physiological responses and mood: the role of caffeine, water and beverage type. Psychopharmacology (Berl) 1997;134(2):164-173. PubMed
- Youngstedt, S. D., O'Connor, P. J., Crabbe, J. B., and Dishman, R. K. Acute exercise reduces caffeine-induced anxiogenesis. Med.Sci Sports Exerc. 1998;30(5):740-745. PubMed
- Kaminsky, L. A., Martin, C. A., and Whaley, M. H. Caffeine consumption habits do not influence the exercise blood pressure response following caffeine ingestion. J.Sports Med.Phys.Fitness 1998;38(1):53-58.
- McManamy, M. C. and Schube, P. G. Caffeine intoxication: report of a case the symptoms of which amounted to a psychosis. New England Journal of Medicine 1936;215:616-620. DOI
- Richter, J. E., Katz, P. O., and Waring, J. P. Gastroesophageal Reflux Disease. IFFGD 2000;
- Hsu, C., Harden, R. N., and Houle, T. Nicotine and caffeine intake in complex regional pain syndrome. Journal of Back and Musculoskeletal Rehabilitation 2002;16(1):33-38. PubMed
- Luebbe, A. M. Child and Adolescent Anxiety Sensitivity, Perceived Subjective Effects of Caffeine and Caffeine Consumption. J Caffeine Res 2011;1(4):213-218. DOI
- Li-Neng, Y., Greenstadt, L., and Shapiro, D. Effects of caffeine on blood pressure:A cross-cultural comparison. Psychophysiology 1983;20
- Fotherby, M. D., Ghandi, C., Haigh, R. A., Macdonald, T. A., and Potter, J. F. Sustained caffeine use has no pressor effect in the elderly. Cardiology in the Elderly 1994;2(6):499-503.
- Basurto Ona X, Uriona Tuma SM, Martínez García L, Solà I, Bonfill Cosp X. Drug therapy for preventing post-dural puncture headache. Cochrane Database Syst Rev. 2013 28;2:CD001792. doi: 10.1002/14651858.CD001792.pub3. Review. PubMed
- Beaudoin MS, Allen B, Mazzetti G, Sullivan PJ, Graham TE. Caffeine ingestion impairs insulin sensitivity in a dose-dependent manner in both men and women. Appl Physiol Nutr Metab. 2013;38(2):140-7. doi: 10.1139/apnm-2012-0201. Epub 2012 9. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Chen L, Bell EM, Browne ML, Druschel CM, Romitti PA, Schmidt RJ, Burns TL, Moslehi R, Olney RS; National Birth Defects Prevention Study. Maternal caffeine consumption and risk of congenital limb deficiencies. Birth Defects Res A Clin Mol Teratol. 2012 De PubMed
- Chen LW, Wu Y, Neelakantan N, Chong MF, Pan A, van Dam RM. Maternal caffeine intake during pregnancy is associated with risk of low birth weight: a systematic review and dose-response meta-analysis. BMC Med. 2014 19;12:174. doi: 10.1186/s12916-014-0174-6 PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- Chiaffarino F, Bravi F, Cipriani S, Parazzini F, Ricci E, Viganò P, La Vecchia C. Coffee and caffeine intake and risk of endometriosis: a meta-analysis. Eur J Nutr. 2014 Oct;53(7):1573-9. doi: 10.1007/s00394-014-0662-7. Epub 2014 31. PubMed
- Greenwood DC, Thatcher NJ, Ye J, Garrard L, Keogh G, King LG, Cade JE. Caffeine intake during pregnancy and adverse birth outcomes: a systematic review and dose-response meta-analysis. Eur J Epidemiol. 2014;29(10):725-34. doi: 10.1007/s10654-014-9944-x. PubMed
- Jiang W, Wu Y, Jiang X. Coffee and caffeine intake and breast cancer risk: an updated dose-response meta-analysis of 37 published studies. Gynecol Oncol. 2013 Jun;129(3):620-9. doi: 10.1016/j.ygyno.2013.03.014. Epub 2013 25. Review. PubMed
- Lee SM, Choi NK, Lee BC, Cho KH, Yoon BW, Park BJ. Caffeine-containing medicines increase the risk of hemorrhagic stroke. Stroke. 2013 Aug;44(8):2139-43. doi: 10.1161/STROKEAHA.111.674077. Epub 2013 6. PubMed
- Sanikini H, Dik VK, Siersema PD, Bhoo-Pathy N, Uiterwaal CS, Peeters PH, González CA, Zamora-Ros R, Overvad K, Tjønneland A, Roswall N, Boutron-Ruault MC, Fagherazzi G, Racine A, Kühn T, Katzke V, Boeing H, Trichopoulou A, Trichopoulos D, Lagiou P, Palli
- Simonin C, Duru C, Salleron J, Hincker P, Charles P, Delval A, Youssov K, Burnouf S, Azulay JP, Verny C, Scherer C, Tranchant C, Goizet C, Debruxelles S, Defebvre L, Sablonnière B, Romon-Rousseaux M, Buée L, Destée A, Godefroy O, Dürr A, Landwehrmeyer B;
- Szpak A, Allen D. A case of acute suicidality following excessive caffeine intake. J Psychopharmacol. 2012 Nov;26(11):1502-10. doi: 10.1177/0269881112442788. Epub 2012 2. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Sheppard SG. A preliminary investigation of ibogaine: case reports and recommendations for further study. J Subst Abuse Treat. 1994 Jul-Aug;11(4):379-85. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Rhee J, Kim R, Kim Y, et al. Maternal caffeine consumption during pregnancy and risk of low birth weight: a dose-response meta-analysis of observational studies. PLoS One. 2015 Jul 20;10(7):e0132334. PubMed
- Zuchinali P, Souza GC, Pimentel M, et al. Short-term effects of high-dose caffeine on cardiac arrhythmias in patients with heart failure: a randomized clinical trial. JAMA Intern Med. 2016 Dec 1;176(12):1752-59. PubMed
- Lystrup RM, Leggit JC. Caffeine toxicity due to supplement use in caffeine - naïve individual: a cautionary tale. Mil Med. 2015 Aug;180(8):e936-40. PubMed
- Magdalan J, Zawadzki M, Skowronek R, et al. Nonfatal and fata intoxications with pure caffeine - report of three different cases. Forensic Sci Med Pathol. 2017 Sep;13(3):355-58.
- Trexler ET, Smith-Ryan AE, Roelofs EJ, Hirsch KR, Persky AM, Mock AG. Effects of coffee and caffeine anhydrous intake during creatine loading. J Strength Cond Res. 2016 May;30(5):1438-46. PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Wang HR, Woo YS, Bahk WM. Caffeine-induced psychiatric manifestations: a review. Int Clin Psychopharmacol. 2015 Jul;30(4):179-82. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Vliegenthart R, Miedema M, Hutten GJ, van Kaam AH, Onland W. High versus standard dose caffeine for apnoea: a systematic review. Arch Dis Child Fetal Neonatal Ed 2018;103(6):F523-9. doi: 10.1136/archdischild-2017-313556. PubMed
- Modzelewska D, Bellocco R, Elfvin A, et al. Caffeine exposure during pregnancy, small for gestational age birth and neonatal outcome - results from the Norwegian Mother and Child Cohort Study. BMC Pregnancy Childbirth. 2019;19(1):80. PubMed
- Shen JG, Brooks MB, Cincotta J, Manjourides JD. Establishing a relationship between the effect of caffeine and duration of endurance athletic time trial events: A systematic review and meta-analysis. J Sci Med Sport. 2019;22(2):232-238. PubMed
- Berglundh S, Vollrath M, Brantsæter AL, et al. Maternal caffeine intake during pregnancy and child neurodevelopment up to eight years of age-Results from the Norwegian Mother, Father and Child Cohort Study. Eur J Nutr. 2020. PubMed
- Jin F, Qiao C. Association of maternal caffeine intake during pregnancy with low birth weight, childhood overweight, and obesity: a meta-analysis of cohort studies. Int J Obes (Lond). 2020. PubMed
- Krittanawong C, Tunhasiriwet A, Wang Z, et al. Is caffeine or coffee consumption a risk for new-onset atrial fibrillation? A systematic review and meta-analysis. Eur J Prev Cardiol. 2020:2047487320908385. PubMed
- Zhang H, Lee ZX, Qiu A. Caffeine intake and cognitive functions in children. Psychopharmacology (Berl). 2020;237(10):3109-3116. PubMed
- Stojanovic E, Scanlan AT, Milanovic Z, Fox JL, Stankovic R, Dalbo VJ. Acute caffeine supplementation improves jumping, sprinting, and change-of-direction performance in basketball players when ingested in the morning but not evening. Eur J Sport Sci. 2021 PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Hinkle SN, Gleason JL, Yisahak SF, et al. Assessment of Caffeine Consumption and Maternal Cardiometabolic Pregnancy Complications. JAMA Netw Open 2021;4(11):e2133401. PubMed
- Yartsev A, Peisah C. Caffeine-clozapine interaction associated with severe toxicity and multiorgan system failure: a case report. BMC Psychiatry 2021;21(1):192. PubMed
- Tinawi M. Severe Rhabdomyolysis Due to Strenuous Exercise With a Potential Role of a High-Caffeine Energy Drink. Cureus 2022;14(1):e20867. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Ismail RIH, Awad HA, Saber M, Shehata BM. Bone mineral content for preterm neonates treated with caffeine using dual energy X-ray absorptiometry: An observational study. J Neonatal Perinatal Med 2023;16(1):129-135. PubMed
- Zhao J, Huang Y, Yu X. Caffeine intake and the risk of incident kidney stones: a systematic review and meta-analysis. Int Urol Nephrol 2022;54(10):2457-2466. PubMed
- Abbas-Hashemi SA, Hosseininasab D, Rastgoo S, Shiraseb F, Asbaghi O. The effects of caffeine supplementation on blood pressure in adults: A systematic review and dose-response meta-analysis. Clin Nutr ESPEN 2023;58:165-177. PubMed
- Oliphant EA, Hanning SM, McKinlay CJD, Alsweiler JM. Caffeine for apnea and prevention of neurodevelopmental impairment in preterm infants: systematic review and meta-analysis. J Perinatol 2024;44(6):785-801. PubMed
- Kühne T, Wallace E, Herzig D, et al. Combined intake of caffeine and low-dose glucose to reduce exercise-related hypoglycaemia in individuals with type 1 diabetes on ultra-long-acting insulin degludec: A randomized, controlled, double-blind, cross-over tr
- Song JJ, Eyabi JC, Awatramani PD, Mitchell BG, Nene SY. Sudden Reduction in Caffeine Intake Increases Serum Lithium Concentration to Supratherapeutic Level: A Case Report. Prim Care Companion CNS Disord 2024;26(2):23cr03642. PubMed
Green Tea 219 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Mitscher LA, Mitscher LA, Jung M, Shankel D, et al. Chemoprotection: a review of the potential therapeutic antioxidant properties of green tea (Camellia sinensis) and certain of its constituents. Med Res Rev 1997;17:327-65.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Booth SL, Madabushi HT, Davidson KW, et al. Tea and coffee brews are not dietary sources of vitamin K-1 (phylloquinone). J Am Diet Assoc 1995;95:82-3. PubMed
- Lou FQ, Zhang MF, Zhang XG, et al. A study on tea-pigment in prevention of atherosclerosis. Chin Med J (Engl) 1989;102:579-83.
- Graham HN. Green tea composition, consumption, and polyphenol chemistry. Prev Med 1992;21:334-50. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Weisburger JH. Tea and health: the underlying mechanisms. Proc Soc Exp Biol Med 1999;220:271-5. PubMed
- Taylor JR, Wilt VM. Probable antagonism of warfarin by green tea. Ann Pharmacother 1999;33:426-8. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Pisters KM, Newman RA, Coldman B, et al. Phase I trial of oral green tea extract in adult patients with solid tumors. J Clin Oncol 2001;19:1830-8. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Ahn WS, Yoo J, Huh SW, et al. Protective effects of green tea extracts (polyphenon E and EGCG) on human cervical lesions. Eur J Cancer Prev 2003;12:383-90. PubMed
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Shirai T, Hayakawa H, Akiyama J, et al. Food allergy to green tea. J Allergy Clin Immunol 2003;112:805-6. PubMed
- Jatoi A, Ellison N, Burch PA, et al. A phase II trial of green tea in the treatment of patients with androgen independent metastatic prostate carcinoma. Cancer 2003;97:1442-6.. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Yang YC, Lu FH, Wu JS, et al. The protective effect of habitual tea consumption on hypertension. Arch Intern Med 2004 26;164:1534-40. PubMed
- Son DJ, Cho MR, Jin YR, et al. Antiplatelet effect of green tea catechins: a possible mechanism through arachidonic acid pathway. Prostaglandins Leukot Essent Fatty Acids 2004;71:25-31. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Bonkovsky HL. Hepatotoxicity associated with supplements containing Chinese green tea (Camellia sinensis). Ann Intern Med 2006;144:68-71.
- Gloro R, Hourmand-Ollivier I, Mosquet B, et al. Fulminant hepatitis during self-medication with hydroalcoholic extract of green tea. Eur J Gastroenterol Hepatol 2005;17:1135-7. PubMed
- Donovan JL, Chavin KD, Devane CL, et al. Green tea (Camellia sinensis) extract does not alter cytochrome P450 3A4 or 2D6 activity in healthy volunteers. Drug Metab Dispos 2004;32:906-8. PubMed
- Chu KO, Wang CC, Chu CY, et al. Pharmacokinetic studies of green tea catechins in maternal plasma and fetuses in rats. J Pharm Sci 2006;95:1372-81. PubMed
- Isbrucker RA, Edwards JA, Wolz E, et al. Safety studies on epigallocatechin gallate (EGCG) preparations. Part 3: teratogenicity and reproductive toxicity studies in rats. Food Chem Toxicol 2006;44:651-61. PubMed
- Navarro-Peran E, Cabezas-Herrera J, Garcia-Canovas F, et al. The antifolate activity of tea catechins. Cancer Res 2005;65:2059-64. PubMed
- Jimenez-Saenz M, Martinez-Sanchez, MDC. Acute hepatitis associated with the use of green tea infusions. J Hepatol 2006;44:616-9. PubMed
- Bradley Pharmaceuticals. Veregen Prescribing Information. October 2006.
- Correa A, Stolley A, Liu Y. Prenatal tea consumption and risks of anencephaly and spina bifida. Ann Epidemiol 2000;10:476-7. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Golden ED, Lam PY, Kardosh A, et al. Green tea polyphenols block the anticancer effects of bortezomib and other boronic acid-based proteasome inhibitors. Blood 2009;113:5927-37. PubMed
- Misaka S, Yatabe J, Muller F, et al. Green Tea Ingestion Greatly Reduces Plasma Concentrations of Nadolol in Healthy Subjects. Clin Pharmacol Ther 2014. [Epub ahead of print]. PubMed
- Roth M, Timmermann BN, Hagenbuch B. Interactions of green tea catechins with organic anion-transporting polypeptides. Drug Metab Dispos 2011;39:920-6. PubMed
- Kato Y, Miyazaki T, Kano T, et al. Involvement of influx and efflux transport systems in gastrointestinal absorption of celiprolol. J Pharm Sci 2009;98:2529-39. PubMed
- Chan, H. T., So, L. T., Li, S. W., Siu, C. W., Lau, C. P., and Tse, H. F. Effect of herbal consumption on time in therapeutic range of warfarin therapy in patients with atrial fibrillation. J.Cardiovasc.Pharmacol. 2011;58(1):87-90. PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extrac
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Wang, X. and Yeung, J. H. Effects of the aqueous extract from Salvia miltiorrhiza Bunge on caffeine pharmacokinetics and liver microsomal CYP1A2 activity in humans and rats. J Pharm Pharmacol 2010;62(8):1077-1083.
- Kot M, Daniel WA. Caffeine as a marker substrate for testing cytochrome P450 activity in human and rat. Pharmacol Rep 2008;60:789-97.
- Kjaerstad MB, Nielsen F, Nohr-Jensen L, et al. Systemic uptake of miconazole during vaginal suppository use and effect on CYP1A2 and CYP3A4 associated enzyme activities in women. Eur J Clin Pharmacol 2010;66:1189-97. PubMed
- Goh BC, Reddy NJ, Dandamudi UB, et al. An evaluation of the drug interaction potential of pazopanib, an oral vascular endothelial growth factor receptor tyrosine kinase inhibitor, using a modified Cooperstown 5+1 cocktail in patients with advanced solid t
- Chen Y, Kang Z, Yan J, et al. Liu wei di huang wan, a well-known traditional Chinese medicine induces CYP1A2 while suppressing CYP2A6 and N-acetyltransferase 2 acivities in man. J Ethnopharmacol 2010;132:213-8.
- Suzuki S, Murayama Y, Sugiyama E, et al. Estimating pediatric doses of drugs metabolized by cytochrome P450 (CYP) isozymes, based on physiological liver development and serum protein levels. Yakugaku Zasshi 2010;130:613-20. PubMed
- Chien CF, Wu YT, Lee WC, et al. Herb-drug interaction of Andrographis paniculata extract and andrographolide on the pharmacokinetics of theophylline in rats. Chem Biol Interact 2010;184:458-65. PubMed
- Mills BM, Zaya MJ, Walters RR, et al. Current cytochrome P450 phenotyping methods applied to metabolic drug -drug interaction prediction in dogs. Drug Metab Dispos 2010;38:396-404. PubMed
- Turpault S, Brian W, Van Horn R, et al. Pharmacokinetic assessment of a five-probe cocktail for CYPs 1A2, 2C9, 2C19, 2D6, and 3A. Br J Clin Pharmacol 2009;68:928-35. PubMed
- Filimonova AA, Ziganshina LE, Ziganshin AU, Chichirov AA. On the possibility of patient phenotyping on the basis of cytochrome p-450 1A2 isoenzyme activity using caffeine as the test substrate. Eksp Klin Farmakol 2009;72:61-5.
- Jenkins J, Williams D, Deng Y, et al. Eltrombopag, an oral thrombopoietin receptor agonist, has no impact on the pharmacokinetic profile of probe drugs for cytochrome P450 isoenzymes CYP3A4, CYP1A2, CYP2C9 and CYP2C19 in healthy men: a cocktail analysis.
- Chow, H. H., Cai, Y., Hakim, I. A., Crowell, J. A., Shahi, F., Brooks, C. A., Dorr, R. T., Hara, Y., and Alberts, D. S. Pharmacokinetics and safety of green tea polyphenols after multiple-dose administration of epigallocatechin gallate and polyphenon E i
- Gross, G., Meyer, K. G., Pres, H., Thielert, C., Tawfik, H., and Mescheder, A. A randomized, double-blind, four-arm parallel-group, placebo-controlled Phase II/III study to investigate the clinical efficacy of two galenic formulations of Polyphenon E in
- Stockfleth, E., Beti, H., Orasan, R., Grigorian, F., Mescheder, A., Tawfik, H., and Thielert, C. Topical Polyphenon E in the treatment of external genital and perianal warts: a randomized controlled trial. Br.J Dermatol. 2008;158(6):1329-1338.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Perera, V., Gross, A. S., and McLachlan, A. J. Caffeine and paraxanthine HPLC assay for CYP1A2 phenotype assessment using saliva and plasma. Biomed.Chromatogr. 2010;24(10):1136-1144. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Izzo, A. A. and Ernst, E. Interactions between herbal medicines and prescribed drugs: an updated systematic review. Drugs 2009;69(13):1777-1798. PubMed
- Laurie, S. A., Miller, V. A., Grant, S. C., Kris, M. G., and Ng, K. K. Phase I study of green tea extract in patients with advanced lung cancer. Cancer Chemother.Pharmacol. 2005;55(1):33-38. PubMed
- Chiu, A. E., Chan, J. L., Kern, D. G., Kohler, S., Rehmus, W. E., and Kimball, A. B. Double-blinded, placebo-controlled trial of green tea extracts in the clinical and histologic appearance of photoaging skin. Dermatol Surg. 2005;31(7 Pt 2):855-860. PubMed
- Javaid, A. and Bonkovsky, H. L. Hepatotoxicity due to extracts of Chinese green tea (Camellia sinensis): a growing concern. J Hepatol 2006;45(2):334-335. PubMed
- Martinez-Sierra, C., Rendon, Unceta P., and Martin, Herrera L. [Acute hepatitis after green tea ingestion]. Med Clin (Barc.) 6-17-2006;127(3):119.
- Molinari, M., Watt, K. D., Kruszyna, T., Nelson, R., Walsh, M., Huang, W. Y., Nashan, B., and Peltekian, K. Acute liver failure induced by green tea extracts: case report and review of the literature. Liver Transpl. 2006;12(12):1892-1895. PubMed
- Chow, H. H., Hakim, I. A., Vining, D. R., Crowell, J. A., Cordova, C. A., Chew, W. M., Xu, M. J., Hsu, C. H., Ranger-Moore, J., and Alberts, D. S. Effects of repeated green tea catechin administration on human cytochrome P450 activity. Cancer Epidemiol.B PubMed
- Federico, A., Tiso, A., and Loguercio, C. A case of hepatotoxicity caused by green tea. Free Radic.Biol Med 8-1-2007;43(3):474. PubMed
- Sarma, D. N., Barrett, M. L., Chavez, M. L., Gardiner, P., Ko, R., Mahady, G. B., Marles, R. J., Pellicore, L. S., Giancaspro, G. I., and Low, Dog T. Safety of green tea extracts : a systematic review by the US Pharmacopeia. Drug Saf 2008;31(6):469-484. PubMed
- Engdal, S. and Nilsen, O. G. In vitro inhibition of CYP3A4 by herbal remedies frequently used by cancer patients. Phytother.Res. 2009;23(7):906-912.
- Bergman, J. and Schjott, J. Hepatitis caused by Lotus-f3? Basic Clin Pharmacol.Toxicol. 2009;104(5):414-416. PubMed
- Kalus, U., Kiesewetter, H., and Radtke, H. Effect of CYSTUS052 and green tea on subjective symptoms in patients with infection of the upper respiratory tract. Phytother.Res. 2010;24(1):96-100.
- Tatti, S., Stockfleth, E., Beutner, K. R., Tawfik, H., Elsasser, U., Weyrauch, P., and Mescheder, A. Polyphenon E: a new treatment for external anogenital warts. Br.J Dermatol. 2010;162(1):176-184.
- Tsao, A. S., Liu, D., Martin, J., Tang, X. M., Lee, J. J., El-Naggar, A. K., Wistuba, I., Culotta, K. S., Mao, L., Gillenwater, A., Sagesaka, Y. M., Hong, W. K., and Papadimitrakopoulou, V. Phase II randomized, placebo-controlled trial of green tea extra
- Liatsos, G. D., Moulakakis, A., Ketikoglou, I., and Klonari, S. Possible green tea-induced thrombotic thrombocytopenic purpura. Am.J Health Syst.Pharm. 4-1-2010;67(7):531-534. PubMed
- Josic, J., Olsson, A. T., Wickeberg, J., Lindstedt, S., and Hlebowicz, J. Does green tea affect postprandial glucose, insulin and satiety in healthy subjects: a randomized controlled trial. Nutr.J. 2010;9:63. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on the acute responsiveness of vascular reactivity to a green tea extract. Br.J.Nutr. 2011;105(8):1138-1144.
- Rohde, J., Jacobsen, C., and Kromann-Andersen, H. [Toxic hepatitis triggered by green tea]. Ugeskr.Laeger 1-17-2011;173(3):205-206.
- Tzellos, T. G., Sardeli, C., Lallas, A., Papazisis, G., Chourdakis, M., and Kouvelas, D. Efficacy, safety and tolerability of green tea catechins in the treatment of external anogenital warts: a systematic review and meta-analysis. J.Eur.Acad.Dermatol.Ve PubMed
- Otera, H., Tada, K., Sakurai, T., Hashimoto, K., and Ikeda, A. Hypersensitivity pneumonitis associated with inhalation of catechin-rich green tea extracts. Respiration 2011;82(4):388-392. PubMed
- Yellapu, R. K., Mittal, V., Grewal, P., Fiel, M., and Schiano, T. Acute liver failure caused by 'fat burners' and dietary supplements: a case report and literature review. Can.J.Gastroenterol. 2011;25(3):157-160. PubMed
- Karth, A., Holoshitz, N., Kavinsky, C. J., Trohman, R., and McBride, B. F. A case report of atrial fibrillation potentially induced by hydroxycut: a multicomponent dietary weight loss supplement devoid of sympathomimetic amines. J.Pharm.Pract. 2010;23(3) PubMed
- Hsu, C. H., Liao, Y. L., Lin, S. C., Tsai, T. H., Huang, C. J., and Chou, P. Does supplementation with green tea extract improve insulin resistance in obese type 2 diabetics? A randomized, double-blind, and placebo-controlled clinical trial. Altern.Med.R
- Zheng XX, Xu YL, Li SH, et al. Green tea intake lowers fasting serum total and LDL cholesterol in adults: a meta-analysis of 14 randomized controlled trials. Am.J.Clin.Nutr. 2011;94:601-610. PubMed
- Miller, R. J., Jackson, K. G., Dadd, T., Mayes, A. E., Brown, A. L., Lovegrove, J. A., and Minihane, A. M. The impact of the catechol-O-methyltransferase genotype on vascular function and blood pressure after acute green tea ingestion. Mol.Nutr.Food Res.
- Bogdanski, P., Suliburska, J., Szulinska, M., Stepien, M., Pupek-Musialik, D., and Jablecka, A. Green tea extract reduces blood pressure, inflammatory biomarkers, and oxidative stress and improves parameters associated with insulin resistance in obese, h
- Jurgens, T. M., Whelan, A. M., Killian, L., Doucette, S., Kirk, S., and Foy, E. Green tea for weight loss and weight maintenance in overweight or obese adults. Cochrane.Database.Syst.Rev. 2012;12:CD008650. PubMed
- Sakamoto, O., Saita, N., Yamasaki, H., Tamanoi, M., and Ando, M. Pulmonary granulomatosis caused by aspirated green tea. Chest 1994;106(1):308-309. PubMed
- Jiménez-Encarnación E, Ríos G, Muñoz-Mirabal A, Vilá LM. Euforia-induced acute hepatitis in a patient with scleroderma. BMJ Case Rep 2012;2012. PubMed
- Choi JS, Burm JP. Effects of oral epigallocatechin gallate on the pharmacokinetics of nicardipine in rats. Arch Pharm Res. 2009 Dec;32(12):1721-5. PubMed
- Chung JH, Choi DH, Choi JS. Effects of oral epigallocatechin gallate on the oral pharmacokinetics of verapamil in rats. Biopharm Drug Dispos. 2009 Mar;30(2):90-3. PubMed
- Crew KD, Brown P, Greenlee H, Bevers TB, Arun B, Hudis C, McArthur HL, Chang J, Rimawi M, Vornik L, Cornelison TL, Wang A, Hibshoosh H, Ahmed A, Terry MB, Santella RM, Lippman SM, Hershman DL. Phase IB randomized, double-blinded, placebo-controlled, dose
- Dryden GW, Lam A, Beatty K, Qazzaz HH, McClain CJ. A pilot study to evaluate the safety and efficacy of an oral dose of (-)-epigallocatechin-3-gallate-rich polyphenon E in patients with mild to moderate ulcerative colitis. Inflamm Bowel Dis. 2013 Aug;19(9 PubMed
- Gallo E, Maggini V, Berardi M, Pugi A, Notaro R, Talini G, Vannozzi G, Bagnoli S, Forte P, Mugelli A, Annese V, Firenzuoli F, Vannacci A. Is green tea a potential trigger for autoimmune hepatitis? Phytomedicine. 2013 Oct 15;20(13):1186-9. PubMed
- Liu K, Zhou R, Wang B, Chen K, Shi LY, Zhu JD, Mi MT. Effect of green tea on glucose control and insulin sensitivity: a meta-analysis of 17 randomized controlled trials. Am J Clin Nutr. 2013 Aug;98(2):340-8. PubMed
- Onakpoya I, Spencer E, Heneghan C, Thompson M. The effect of green tea on blood pressure and lipid profile: a systematic review and meta-analysis of randomized clinical trials. Nutr Metab Cardiovasc Dis. 2014 Aug;24:823-36. PubMed
- Patel SS, Beer S, Kearney DL, Phillips G, Carter BA. Green tea extract: a potential cause of acute liver failure. World J Gastroenterol. 2013 Aug 21;19(31):5174-7. PubMed
- Pillukat MH, Bester C, Hensel A, Lechtenberg M, Petereit F, Beckebaum S, Müller KM, Schmidt HH. Concentrated green tea extract induces severe acute hepatitis in a 63-year-old woman--a case report with pharmaceutical analysis. J Ethnopharmacol. 2014 Aug 8; PubMed
- Schönthal AH. Adverse effects of concentrated green tea extracts. Mol Nutr Food Res. 2011 Jun;55(6):874-85. PubMed
- Shiraishi M, Haruna M, Matsuzaki M, Ota E, Murayama R, Murashima S. Association between the serum folate levels and tea consumption during pregnancy. Biosci Trends. 2010 Oct;4(5):225-30.
- Jang EH, Choi JY, Park CS, Lee SK, Kim CE, Park HJ, Kang JS, Lee JW, Kang JH. Effects of green tea extract administration on the pharmacokinetics of clozapine in rats. J Pharm Pharmacol. 2005 Mar;57(3):311-6. PubMed
- Trudel D, Labbé DP, Araya-Farias M, Doyen A, Bazinet L, Duchesne T, Plante M, Grégoire J, Renaud MC, Bachvarov D, Têtu B, Bairati I. A two-stage, single-arm, phase II study of EGCG-enriched green tea drink as a maintenance therapy in women with advanced s
- Zheng XX, Xu YL, Li SH, Hui R, Wu YJ, Huang XH. Effects of green tea catechins with or without caffeine on glycemic control in adults: a meta-analysis of randomized controlled trials. Am J Clin Nutr. 2013 Apr;97(4):750-62. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Health Canada. Health Product Info Watch. October 2016; 5-6. Available at: http://www.hc-sc.gc.ca/dhp-mps/medeff/bulletin/hpiw-ivps_2016-10-eng.php#a15.
- Green Tea Extract-Containing Natural Health Products - Rare Risk of Serious Liver Injury. Recalls & alerts. November 15, 2017. http://healthycanadians.gc.ca/recall-alert-rappel-avis/hc-sc/2017/65100a-eng.php. Accessed November 10, 2017.
- Mazzanti G, Di Sotto A, Vitalone A. Hepatotoxicity of green tea: an update. Arch Toxicol. 2015;89(8):1175-91. PubMed
- Isomura T, Suzuki S, Origasa H, et al. Liver-related safety assessment of green tea extracts in humans: a systematic review of randomized controlled trials. Eur J Clin Nutr. 2016;70(11):1221-1229. PubMed
- Drug Record: Green Tea (Camellia Sinesis). LiverTox: National Institutes of Health, U.S. Department of Health & Human Services, March 2014. https://livertox.nlm.nih.gov//GreenTea.htm. Accessed November 20, 2017.
- Yates AA, Erdman JW Jr, Shao A, Dolan LC, Griffiths JC. Bioactive nutrients - Time for tolerable upper intake levels to address safety. Regul Toxicol Pharmacol. 2017;84:94-101. PubMed
- Younes M, Aggett P, Aguilar F, et al. EFSA Panel on Food Additives and Nutrient Sources added to Food (ANS). Scientific opinion on the safety of green tea catechins. EFSA Journal 2018;16(4):5239. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Dostal AM, Samavat H, Bedell S, et al. The safety of green tea extract supplementation in postmenopausal women at risk for breast cancer: results of the Minnesota Green Tea Trial. Food Chem Toxicol. 2015 Sep;83:26-35. PubMed
- Shamekhi Z, Amani R, Habibagahi Z, Namjoyan F, Ghadiri A, Saki Malehi A. A Randomized, Double-blind, Placebo-controlled Clinical Trial Examining the Effects of Green Tea Extract on Systemic Lupus Erythematosus Disease Activity and Quality of Life. Phytoth PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Chong SJ, Howard KA, Knox C. Hypokalaemia and drinking green tea: a literature review and report of 2 cases. BMJ Case Rep. 2016;2016. pii: bcr2016214425. PubMed
- Qiao J, Gu C, Shang W, et al. Effect of green tea on pharmacokinetics of 5-fluorouracil in rats and pharmacodynamics in human cell lines in vitro. Food Chem Toxicol. 2011;49(6):1410-5. PubMed
- Abe O, Ono T, Sato H, et al. Role of (-)-epigallocatechin gallate in the pharmacokinetic interaction between nadolol and green tea in healthy volunteers. Eur J Clin Pharmacol 2018;74(6):775-83. doi: 10.1007/s00228-018-2436-2. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Nutescu EA, Shapiro NL, Ibrahim S, et al. Warfarin and its interactions with foods, herbs and other dietary supplements. Expert Opin Drug Saf. 2006;5(3):433-51. PubMed
- Abdelkawy KS, Abdelaziz RM, Abdelmageed AM, Donia AM, El-Khodary NM. Effects of green tea extract on atorvastatin pharmacokinetics in healthy volunteers. Eur J Drug Metab Pharmacokinet. 2020;45(3):351-360. PubMed
- Filippini T, Malavolti M, Borrelli F, et al. Green tea (Camellia sinensis) for the prevention of cancer. Cochrane Database Syst Rev. 2020;3(3):CD005004. PubMed
- Huang S, Xu Q, Liu L, et al. Effect of green tea and (-)-epigallocatechin gallate on the pharmacokinetics of rosuvastatin. Curr Drug Metab. 2020. PubMed
- Mahmoodi M, Hosseini R, Kazemi A, Ofori-Asenso R, Mazidi M, Mazloomi SM. Effects of green tea or green tea catechin on liver enzymes in healthy individuals and people with nonalcoholic fatty liver disease: A systematic review and meta-analysis of randomiz
- Misaka S, Abe O, Ono T, et al. Effects of single green tea ingestion on pharmacokinetics of nadolol in healthy volunteers. Br J Clin Pharmacol. 2020. PubMed
- Oketch-Rabah HA, Roe AL, Rider CV, et al. United States Pharmacopeia (USP) comprehensive review of the hepatotoxicity of green tea extracts. Toxicol Rep. 2020;7:386-402. PubMed
- Kim TE, Ha N, Kim Y, et al. Effect of epigallocatechin-3-gallate, major ingredient of green tea, on the pharmacokinetics of rosuvastatin in healthy volunteers. Drug Des Devel Ther. 2017;11:1409-1416. PubMed
- Misaka S, Ono Y, Uchida A, et al. Impact of green tea catechin ingestion on the pharmacokinetics of lisinopril in healthy volunteers. Clin Transl Sci. 2020. PubMed
- Darweesh RS, El-Elimat T, Zayed A, et al. The effect of grape seed and green tea extracts on the pharmacokinetics of imatinib and its main metabolite, N-desmethyl imatinib, in rats. BMC Pharmacol Toxicol. 2020;21(1):77. PubMed
- Sonoda J, Ogata K, Yoshikawa N, Sato K, Ikeda R, Shimodozono Y. Impact of green tea intake on the pharmacokinetics of celiprolol in healthy subjects. Int J Clin Pharmacol Ther. 2020. PubMed
- Kim S, Park TH, Kim WI, Park S, Kim JH, Cho MK. The effects of green tea on acne vulgaris: A systematic review and meta-analysis of randomized clinical trials. Phytother Res. 2021;35(1):374-383. PubMed
- Percevault S, Charpiat B, Lebossé F, Mabrut JY, Vial T, Colom M. Green tea and hepatoxicity: Two case reports. Therapie 2021. PubMed
- Kajita N, Miyama S, Kinoshita K, Yoshida K, Narita M. Green tea-induced anaphylaxis: The first pediatric case report. Allergol Int 2021;70(4):507-508. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Seufferlein T, Ettrich TJ, Menzler S, et al. Green tea extract to prevent colorectal adenomas, results of a randomized, placebo-controlled clinical trial. Am J Gastroenterol 2022;117(6):884-894. PubMed
- Teramoto M, Yamagishi K, Muraki I, Tamakoshi A, Iso H. Coffee and green tea consumption and cardiovascular disease mortality among people with and without hypertension. J Am Heart Assoc 2023;12(2):e026477. PubMed
- Veerman GDM, van der Werff SC, Koolen SLW, et al. The influence of green tea extract on nintedanib's bioavailability in patients with pulmonary fibrosis. Biomed Pharmacother 2022;151:113101. PubMed
- Misaka S, Ono Y, Taudte RV, et al. Exposure of fexofenadine, but not pseudoephedrine, is markedly decreased by green tea extract in healthy volunteers. Clin Pharmacol Ther 2022;112(3):627-634. PubMed
- Zhao H, Zhu W, Zhao X, et al. Efficacy of epigallocatechin-3-gallate in preventing dermatitis in patients with breast cancer receiving postoperative radiotherapy: A double-blind, placebo-controlled, phase 2 randomized clinical trial. JAMA Dermatol 2022;15 PubMed
- Pochet S, Lechon AS, Lescrainier C, et al. Herb-anticancer drug interactions in real life based on VigiBase, the WHO global database. Sci Rep 2022;12(1):14178. PubMed
Guarana 114 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Boozer CN, Nasser JA, Heymsfield SB, et al. An herbal supplement containing Ma Huang-Guarana for weight loss: a randomized, double-blind trial. Int J Obes Relat Metab Disord 2001;25:316-24. PubMed
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Tobias JD. Caffeine in the treatment of apnea associated with respiratory syncytial virus infection in neonates and infants. South Med J 2000;93:297-304. DOI
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Haller CA, Jacob P 3rd, Benowitz NL. Pharmacology of ephedra alkaloids and caffeine after single-dose dietary supplement use. Clin Pharmacol Ther 2002;71:421-32. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Nehlig A, Debry G. Consequences on the newborn of chronic maternal consumption of coffee during gestation and lactation: a review. J Am Coll Nutr 1994;13:6-21.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Schechter MD, Timmons GD. Objectively measured hyperactivity--II. Caffeine and amphetamine effects. J Clin Pharmacol 1985;25:276-80.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Holmgren P, Norden-Pettersson L, Ahlner J. Caffeine fatalities--four case reports. Forensic Sci Int 2004;139:71-3. PubMed
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Leson CL, McGuigan MA, Bryson SM. Caffeine overdose in an adolescent male. J Toxicol Clin Toxicol 1988;26:407-15. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Mansi IA, Huang J. Rhabdomyolysis in response to weight-loss herbal medicine. Am J Med Sci 2004;327:356-357. PubMed
- Spinella M. Herbal Medicines and Epilepsy: The Potential for Benefit and Adverse Effects. Epilepsy Behav 2001;2(6):524-532. PubMed
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Quirce, G. S., Freire, P., Fernandez, R. M., Davila, I., and Losada, E. Urticaria from caffeine. J.Allergy Clin Immunol. 1991;88(4):680-681. PubMed
- Wrenn, K. D. and Oschner, I. Rhabdomyolysis induced by a caffeine overdose. Ann.Emerg.Med. 1989;18(1):94-97. PubMed
- Pola, J., Subiza, J., Armentia, A., Zapata, C., Hinojosa, M., Losada, E., and Valdivieso, R. Urticaria caused by caffeine. Ann.Allergy 1988;60(3):207-208.
- Caballero, T., Garcia-Ara, C., Pascual, C., Diaz-Pena, J. M., and Ojeda, A. Urticaria induced by caffeine. J.Investig.Allergol.Clin Immunol. 1993;3(3):160-162.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- du, Boisgueheneuc F., Lannuzel, A., Caparros-Lefebvre, D., and De Broucker, T. [Cerebral infarction in a patient consuming MaHuang extract and guarana]. Presse Med 2-3-2001;30(4):166-167.
- Baghkhani, L. and Jafari, M. Cardiovascular adverse reactions associated with Guarana: is there a causal effect? J.Herb.Pharmacother. 2002;2(1):57-61. DOI
- Haller, C. A., Jacob, P., and Benowitz, N. L. Short-term metabolic and hemodynamic effects of ephedra and guarana combinations. Clin.Pharmacol.Ther. 2005;77(6):560-571. PubMed
- Bydlowski, S. P., D'Amico, E. A., and Chamone, D. A. An aqueous extract of guarana (Paullinia cupana) decreases platelet thromboxane synthesis. Braz.J.Med.Biol.Res. 1991;24(4):421-424.
- Bydlowski, S. P., Yunker, R. L., and Subbiah, M. T. A novel property of an aqueous guarana extract (Paullinia cupana): inhibition of platelet aggregation in vitro and in vivo. Braz.J.Med.Biol.Res. 1988;21(3):535-538.
- Galduroz, J. C. and Carlini, E. A. The effects of long-term administration of guarana on the cognition of normal, elderly volunteers. Sao Paulo Med.J. 1996;114(1):1073-1078. PubMed
- Mattei, R., Dias, R. F., Espinola, E. B., Carlini, E. A., and Barros, S. B. Guarana (Paullinia cupana): toxic behavioral effects in laboratory animals and antioxidants activity in vitro. J.Ethnopharmacol. 1998;60(2):111-116.
- Chamone, D. A., Silva, M. I., Cassaro, C., Bellotti, G., Massumoto, C. M., and Fujimura, A. Y. Guaraná (Paullinia cupana) inhibits aggregation in whole blood. Thrombosis and Haemostasis 1987;58(1):474.
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- del Giglio AB, Cubero Dde I, Lerner TG, Guariento RT, de Azevedo RG, Paiva H, Goldman C, Carelli B, Cruz FM, Schindler F, Pianowski L, de Matos LL, del Giglio A. Purified dry extract of Paullinia cupana (guaraná) (PC-18) for chemotherapy-related fatigue i
- Palma CG, Lera AT, Lerner T, de Oliveira MM, de Borta TM, Barbosa RP, Brito GM, Guazzelli CA, Cruz FJ, del Giglio A. Guarana (Paullinia cupana) Improves Anorexia in Patients with Advanced Cancer. J Diet Suppl. 2016;13(2):221-31.
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- de Araujo DP, Pereira PTVT, Fontes AJC, et al. The use of guarana (Paullinia cupana) as a dietary supplement for fatigue in cancer patients: a systematic review with a meta-analysis. Support Care Cancer 2021;29(12):7171-7182. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
Zinc 88 references
- Barceloux DG. Zinc. J Toxicol Clin Toxicol 1999;37:279-92.
- Eby GA, Davis DR, Halcomb WW. Reduction in duration of common colds by zinc gluconate lozenges in a double-blind study. Antimicrob Agents Chemother 1984;25:20-4. DOI
- Smith DS, Helzner EC, Nuttall CE Jr, et al. Failure of zinc gluconate in treatment of acute upper respiratory tract infections. Antimicrob Agents Chemother 1989;33:646-8. PubMed
- Blondeau JM. Expanded activity and utility of the new fluoroquinolones: a review. Clin Ther 1999;21:3-40. PubMed
- Reyes AJ, Olhaberry JV, Leary WP, et al. Urinary zinc excretion, diuretics, zinc deficiency and some side-effects of diuretics. S Afr Med J 1983;64:936-41.
- Kugelmas M. Preliminary observation: oral zinc sulfate replacement is effective in treating muscle cramps in cirrhotic patients. J Am Coll Nutr 2000;19:13-5. PubMed
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Chan S, Gerson B, Subramaniam S. The role of copper, molybdenum, selenium, and zinc in nutrition and health. Clin Lab Med 1998;18:673-85. DOI
- Brewer GJ, Yuzbasiyan-Gurkan V, Johnson V, et al. Treatment of Wilson's disease with zinc: XI. Interaction with other anticopper agents. J Am Coll Nutr 1993;12:26-30. PubMed
- Fosmire GJ. Zinc toxicity. Am J Clin Nutr 1990;51:225-7.
- Lomaestro BM, Bailie GR. Absorption interactions with fluoroquinolones. 1995 update. Drug Saf 1995;12:314-33. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Seelig MS. Auto-immune complications of D-penicillamine - A possible result of zinc and magnesium depletion and of pyridoxine inactivation. J Am Coll Nutr 1982;1:207-14. PubMed
- Neuvonen PJ. Interactions with the absorption of tetracyclines. Drugs 1976;11:45-54.. PubMed
- Hirt M, Nobel S, Barron E. Zinc nasal gel for the treatment of common cold symptoms: A double-blind, placebo-controlled trial. Ear Nose Throat J 2000;79:778-82.. DOI
- Simkin PA. Oral zinc sulphate in rheumatoid arthritis. Lancet 1976;2:539-42. PubMed
- Wray D. A double-blind trial of systemic zinc sulfate in recurrent aphthous stomatitis. Oral Surg Oral Med Oral Pathol 1982;53:469-72. PubMed
- Douglas RM, Miles HB, Moore BW, et al. Failure of effervescent zinc acetate lozenges to alter the course of upper respiratory tract infections in Australian adults. Antimicrob Agents Chemother 1987;31:1263-5. PubMed
- Lagiou P, Wuu J, Trichopoulou A, et al. Diet and benign prostatic hyperplasia: a study in Greece. Urology 1999;54:284-90. PubMed
- Ewing CI, Gibbs AC, Ashcroft C, David TJ. Failure of oral zinc supplementation in atopic eczema. Eur J Clin Nutr 1991;45:507-10.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Age-Related Eye Disease Study Research Group. A randomized, placebo-controlled, clinical trial of high-dose supplementation with vitamins C and E, beta carotene, and zinc for age-related macular degeneration and vision loss. AREDS report no. 8. Arch Oph
- Greenberg JE, Lynn M, Kirsner RS, et al. Mucocutaneous pigmented macule as a result of zinc deposition. J Cutan Pathol 2002;29:613-5. PubMed
- Godfrey HR, Godfrey NJ, Godfrey JC, Riley D. A randomized clinical trial on the treatment of oral herpes with topical zinc oxide/glycine. Altern Ther Health Med 2001;7:49-56.
- Turner RB. Ineffectiveness of intranasal zinc gluconate for prevention of experimental rhinovirus colds. Clin Infect Dis 2001;33:1865-70. PubMed
- Belongia EA, Berg R, Liu K. A randomized trial of zinc nasal spray for the treatment of upper respiratory illness in adults. Am J Med 2001;111:103-8. PubMed
- Mossad SB. Effect of zincum gluconicum nasal gel on the duration and symptom severity of the common cold in otherwise healthy adults. QJM 2003;96:35-43. DOI
- Leitzmann MF, Stampfer MJ, Wu K, et al. Zinc supplement use and risk of prostate cancer. J Natl Cancer Inst 2003;95:1004-7.. PubMed
- Jafek BW, Linschoten M, Murrow BW. Zicam Induced Anosmia. American Rhinologic Society 49th Annual Fall Scientific Meeting abstract. Orlando, Florida. September 20, 2003. http://app.american-rhinologic.org/programs/2003ARSFallProgram071503.pdf (Accessed 24
- Uebayashi H, Hatanaka T, Kanemura F, Tonosaki K. Acute anosmia in the mouse: behavioral discrimination among the four basic taste substances. Physiol Behav 2001;72:291-6.. PubMed
- Barrett S. Zicam Marketers Sued. United States District Court Western District of Michigan Southern Division, Filed October 14, 2003, Case No. 4:03CV0146.
- Bilici M, Yildirim F, Kandil S, et al. Double-blind, placebo-controlled study of zinc sulfate in the treatment of attention deficit hyperactivity disorder. Prog Neuropsychopharmacol Biol Psychiatry 2004;28:181-90.. PubMed
- Polk RE, Healy DP, Sahai J, et al. Effect of ferrous sulfate and multivitamins with zinc on absorption of ciprofloxacin in normal volunteers. Antimicrob Agents Chemother 1989;33:1841-4. PubMed
- Mery C, Delrieu F, Ghozlan R, et al. Controlled trial of D-penicillamine in rheumatoid arthritis. Dose effect and the role of zinc. Scand J Rheumatol 1976;5:241-7. PubMed
- Penttila O, Hurme H, Neuvonen PJ. Effect of zinc sulfate on the absorption of tetracycline and doxycycline in man. Eur J Clin Pharmacol 1975;9:131-4.
- Kondo Y, Yamagata K, Satoh M, et al. Optimal administration schedule of cisplatin for bladder tumor with minimal induction of metallothionein. J Urol 2003;170:2467-70. PubMed
- Doz F, Berens ME, Deschepper CF, et al. Experimental basis for increasing the therapeutic index of cis-diamminedicarboxylatocyclobutaneplatinum(II) in brain tumor therapy by a high-zinc diet. Cancer Chemother Pharmacol 1992;29:219-26.
- Wester PO. Urinary zinc excretion during treatment with different diuretics. Acta Med Scand 1980;208:209-12. PubMed
- Golik A, Modai D, Weissgarten J, et al. Hydrochlorothiazide-amiloride causes excessive urinary zinc excretion. Clin Pharmacol Ther 1987;42:42-4. PubMed
- Leary WP, Reyes AJ, Van der Byl K. Urinary magnesium and zinc excretion after two different single doses of amiloride in healthy adults. Curr Ther Res 1983;34:205-16.
- McBride K, Slotnick B, Margolis FL. Does intranasal application of zinc sulfate produce anosmia in the mouse? An olfactometric and anatomical study. Chem Senses 2003;28:659-70. PubMed
- Burd GD. Morphological study of the effects of intranasal zinc sulfate irrigation on the mouse olfactory epithelium and olfactory bulb. Microsc Res Tech 1993;24:195-213. PubMed
- Ducray A, Bondier JR, Michel G, et al. Recovery following peripheral destruction of olfactory neurons in young and adult mice. Eur J Neurosci 2002;15:1907-17. PubMed
- Mayer AD, Rosenblatt JS. Peripheral olfactory deafferentation of the primary olfactory system in rats using ZnSO4 nasal spray with special reference to maternal behavior. Physiol Behav 1993;53:587-92. PubMed
- DeCook CA, Hirsch AR. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Tisdall FF, Brown A, Defries RD. Persistent anosmia following zinc sulfate nasal spraying. JPed 1938;18:60-2. DOI
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Public Health Advisory. Loss of sense of smell with intranasal cold remedies containing zinc. U.S. Food and Drug Administration, June 16, 2009. Available at: http://www.fda.gov/Drugs/DrugSafety/PublicHealthAdvisories/ucm166059.htm (Accessed 16 June 2009)
- Dooren JC. FDA warns against use of Zicam. The Wall Street Journal, June 16, 2009. Available at: http://online.wsj.com/article/SB124516778692319231.html#mod=djemHL?mg=com-wsj (Accessed 16 June 2009).
- Alexander TH, Davidson TM. Intranasal zinc and anosmia: the zinc-induced anosmia syndrome. Laryngoscope 2006;116:217-20.
- Health Canada / GlaxoSmithKline Consumer Healthcare. Association of long-term, excessive use of zinc-containing Poli-Grip products with myeloneuropathy and blood dyscrasias. February 18, 2010. Available at: http://hc-sc.gc.ca/dhp-mps/alt_formats/pdf/medef
- GlaxoSmithKline Consumer Advisory. GlaxoSmithKline (GSK) warns about a potential health risk associated with long-term, excessive use of GSK's zinc-containing denture adhesives Super Polygrip Original, Ultra Fresh and Extra Care. February 18, 2010. Availa
- Science M, Johnstone J, Roth DE, et al. Zinc for the treatment of the common cold: a systematic review and meta-analysis of randomized controlled trials. CMAJ 2012;184:E551-61. PubMed
- Castilla-Higuero, L., Romero-Gomez, M., Suarez, E., and Castro, M. Acute hepatitis after starting zinc therapy in a patient with presymptomatic Wilson's disease. Hepatology 2000;32(4 Pt 1):877. PubMed
- Sharquie, K. E., Najim, R. A., Farjou, I. B., and Al Timimi, D. J. Oral zinc sulphate in the treatment of acute cutaneous leishmaniasis. Clin.Exp.Dermatol. 2001;26(1):21-26. PubMed
- Dreno, B., Moyse, D., Alirezai, M., Amblard, P., Auffret, N., Beylot, C., Bodokh, I., Chivot, M., Daniel, F., Humbert, P., Meynadier, J., and Poli, F. Multicenter randomized comparative double-blind controlled clinical trial of the safety and efficacy of
- Moore, R. Bleeding gastric erosion after oral zinc sulphate. Br.Med J 3-25-1978;1(6115):754. PubMed
- Jafek, B. W., Linschoten, M. R., and Murrow, B. W. Anosmia after intranasal zinc gluconate use. Am J Rhinol. 2004;18(3):137-141. DOI
- Simonart, T. and de, Maertelaer, V. Systemic treatments for cutaneous warts: a systematic review. J Dermatolog.Treat. 2012;23(1):72-77. PubMed
- Cochran, R. J., Tucker, S. B., and Flannigan, S. A. Topical zinc therapy for acne vulgaris. Int.J Dermatol. 1985;24(3):188-190. DOI
- Morgan, A. A. Bleeding gastric erosion after oral zinc sulphate. Br.Med.J. 5-13-1978;1(6122):1283-1284. PubMed
- Murphy, J. V. Intoxication following ingestion of elemental zinc. JAMA 6-22-1970;212(12):2119-2120.
- Lang, C. J., Rabas-Kolominsky, P., Engelhardt, A., Kobras, G., and Konig, H. J. Fatal deterioration of Wilson's disease after institution of oral zinc therapy. Arch Neurol. 1993;50(10):1007-1008. PubMed
- Fjellner, B. Drug-induced lupus erythematosus aggravated by oral zinc therapy. Acta Derm.Venereol. 1979;59(4):368-370. DOI
- Varas Lorenzo, M. J. Zinc acexamate and ranitidine in the short- and mid-term management of gastroduodenal ulcers. Curr Ther Res 21986;39:19-29.
- Bosch, F. and Jimenez, E. Post-marketing surveillance of zinc acexamate in peptic ulcer treatment. Clin Trials J 1990;27:301-312.
- DeCook, C. A. and Hirsch, A. R. Anosmia due to inhalational zinc: a case report (abstract). Chem Senses 2000;25:659.
- Crown LA, May JA. Zinc toxicity: denture adhesives, bone marrow failure and polyneuropathy. Tenn Med. 2012 Feb;105(2):39-40, 42.
- Dadamio J, Van Tournout M, Teughels W, Dekeyser C, Coucke W, Quirynen M. Efficacy of different mouthrinse formulations in reducing oral malodour: a randomized clinical trial. J Clin Periodontol. 2013 May;40(5):505-13. PubMed
- Moyle G, Else L, Jackson A, Back D, Yapa MH, Seymour N, Ringner-Nackter L, Karolia Z, Gazzard B, Boffito M. Coadministration of atazanavir-ritonavir and zinc sulfate: impact on hyperbilirubinemia and pharmacokinetics. Antimicrob Agents Chemother. 2013 Aug PubMed
- Zittel S, Ufer F, Gerloff C, Münchau A, Rosenkranz M. Severe myelopathy after denture cream use--is copper deficiency or excess zinc the cause? Clin Neurol Neurosurg. 2014 Jun;121:17-8. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Ding Y, Jia YY, Li F, et al. The effect of staggered administration of zinc sulfate on the pharmacokinetics of oral cephalexin. Br J Clin Pharmacol. 2012 Mar;73(3):422-7. PubMed
- Fallah R, Sabbaghzadegan S, Karbasi SA, Binesh F. Efficacy of zinc sulfate supplement on febrile seizure recurrence prevention in children with normal serum zinc level: A randomised clinical trial. Nutrition. 2015;31(11-12):1358-61. PubMed
- Lazzerini M, Wanzira H. Oral zinc for treating diarrhoea in children. Cochrane Database Syst Rev. 2016;12:CD005436. PubMed
- Mahmoud AM, Al-Alem U, Dabbous F, et al. Zinc intake and risk of prostate cancer: Case-control study and meta-analysis. PLoS One. 2016;11(11):e0165956. PubMed
- Nagraj SK, George RP, Shetty N, Levenson D, Ferraiolo DM, Shrestha A. Interventions for managing taste disturbances. Cochrane Database Syst Rev. 2017 Dec 20;12(12):CD010470. PubMed
- Yee BE, Richards P, Sui JY, Marsch AF. Serum zinc levels and efficacy of zinc treatment in acne vulgaris: A systematic review and meta-analysis. Dermatol Ther. 2020:e14252. PubMed
- Janyajirawong R, Vilaichone RK, Sethasine S. Efficacy of zinc supplement in minimal hepatic encephalopathy: A prospective, randomized controlled study (Zinc-MHE Trial). Asian Pac J Cancer Prev 2021;22(9):2879-2887. PubMed
- Nakano M, Nakamura Y, Miyazaki A, Takahashi J. Zinc pharmacotherapy for elderly osteoporotic patients with zinc deficiency in a clinical setting. Nutrients 2021;13(6):1814. PubMed
- Tolino E, Skroza N, Mambrin A, et al. An open-label study comparing oral zinc to lymecycline in the treatment of acne vulgaris. J Clin Aesthet Dermatol 2021;14(5):56-58.
- Hunter J, Arentz S, Goldenberg J, et al. Zinc for the prevention or treatment of acute viral respiratory tract infections in adults: a rapid systematic review and meta-analysis of randomised controlled trials. BMJ Open. 2021;11(11):e047474. PubMed
- Yamazaki K, Kageyama H, Fujiyama T, Ito T, Urano S, Honda T. A case of systemic contact dermatitis due to zinc supplements. Int J Dermatol 2022. PubMed
- Magham K, Han J, Eilbert W, Bunney EB. Severe copper deficiency anemia caused by zinc supplement use. Am J Emerg Med 2023;72:222. PubMed
- Sivakumar RR, Chinnaiah Govindareddy D, Sahoo J, Bobby Z, Chinnakali P. Effect of daily zinc supplementation for 12 weeks on serum thyroid auto-antibody levels in children and adolescents with autoimmune thyroiditis - a randomized controlled trial. J Pedi PubMed
- AlDhasee O, AlMalki H, AlKharashi N, AlJeraisy N, Al Deeb M. Acute zinc sulfate overdose: clinical presentation and management. BMJ Case Rep 2025;18(1):e263899. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Tyrosine 4 references
- Meyer JS, Welch KM, Deshmukh VD, et al. Neurotransmitter precursor amino acids in the treatment of multi-infarct dementia and Alzheimer's disease. J Amer Geriat Soc 1977;25:289-98.
- DiPiro JT, Talbert RL, Yee GC, et al; eds. Pharmacotherapy: A pathophysiologic approach. 4th ed. Stamford, CT: Appleton & Lange, 1999.
- Wood DR, Reimherr FW, Wender PH. Amino acid precursors for the treatment of attention deficit disorder, residual type. Psychopharmacol Bull 1985;21:146-9.
- van Spronsen FJ, van Rijn M, Bekhof J. Phenylketonuria: tyrosine supplementation in phenylalanine-restricted diets. Am J Clin Nutr 2001;73:153-7. PubMed
Folic Acid 56 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Duhra P. Treatment of gastrointestinal symptoms associated with methotrexate therapy for psoriasis. J Am Acad Dermatol 1993;28:466-9. PubMed
- Morgan SL, Baggott JE, Vaughn WH, et al. Supplementation with folic acid during methotrexate therapy for rheumatoid arthritis. A double-blind, placebo-controlled trial. Ann Intern Med 1994;121:833-41. PubMed
- Froscher W, Maier V, Laage M, et al. Folate deficiency, anticonvulsant drugs, and psychiatric morbidity. Clin Neuropharmacol 1995;18:165-82. PubMed
- Lewis DP, Van Dyke DC, Willhite LA, et al. Phenytoin-folic acid interaction. Ann Pharmacother 1995;29:726-35. PubMed
- Berg MJ, Stumbo PJ, Chenard CA, et al. Folic acid improves phenytoin pharmacokinetics. J Am Diet Assoc 1995;95:352-6. PubMed
- Berg MJ, Fincham RW, Ebert BE, et al. Phenytoin pharmacokinetics: Before and after folic acid administration. Epilepsia 1992;33:712-20. PubMed
- Shafer RB, Nuttall FQ. Calcium and folic acid absorption in patients taking anticonvulsant drugs. J Clin Endocrinol Metab 1975;41:1125-9. PubMed
- Leeb BF, Witzmann G, Ogris E, et al. Folic acid and cyanocobalamin levels in serum and erythrocytes during low-dose methotrexate therapy of rheumatoid arthritis and psoriatic arthritis patients. Clin Exp Rheumatol 1995;13:459-63.
- Morgan SL, Baggott JE, Lee JY, Alarcón GS. Folic acid supplementation prevents deficient blood folate levels and hyperhomocysteinemia during longterm, low dose methotrexate therapy for rheumatoid arthritis: implications for cardiovascular disease preventi
- Dijkmans BA. Folate supplementation and methotrexate. Br J Rheumatol 1995;34:1172-4. PubMed
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Lambie DG, Johnson RH. Drugs and folate metabolism. Drugs 1985;30:145-55. PubMed
- Amer College of Rheumatology ad hoc committee on clinical guidelines. Guidelines for monitoring drug therapy in rheumatoid arthritis. Arthritis Rheum 1996;39:723-31. DOI
- Suitor CW, Bailey LB. Dietary folate equivalents: interpretation and application. J Am Diet Assoc 2000;100:88-94. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Sandoval M, Charbonnet RM, Okuhama NN, et al. Cat's claw inhibits TNFalpha production and scavenges free radicals: role in cytoprotection. Free Radic Biol Med 2000;29:71-78.
- Antony AC. Megaloblastic Anemias. In: Hoffman R, Benz Jr EJ, Shattil SJ, et al. Hematology: Basic Principles and Practice. 3rd ed. New York, NY: Churchill Livingstone 2000: 451-79.
- Reynolds EH. Neurological aspects of folate and vitamin B12 metabolism. Clin Haematol 1976;5:661-96. DOI
- Reynolds EH. Folate metabolism and anticonvulsant therapy. Proc R Soc Med 1974;67:68.
- Ortiz Z, Shea B, Suarez Almazor M, et al. Folic acid and folinic acid for reducing side effects in patients receiving methotrexate for rheumatoid arthritis (Cochrane Review). Cochrane Database Syst Rev 2000;2:CD000951. PubMed
- Van Delden C, Hirschel B. Folinic acid supplements to pyrimethamine-sulfadiazine for Toxoplasma encephalitis are associated with better outcome (letter). J Infect Dis 1996;173:1294-5. PubMed
- Schroder H, Clausen N, Ostergard E, Pressler T. Folic acid supplements in vitamin tablets: a determinant of hematological drug tolerance in maintenance therapy of childhood acute lymphoblastic leukemia. Ped Hematol Oncol 1986;3:241-7. PubMed
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Morris MC, Evans DA, Bienias JL, et al. Dietary folate and vitamin B12 intake and cognitive decline among community-dwelling older persons. Arch Neurol 2005;62:641-5. PubMed
- Bonaa KH, Njolstad I, Ueland PM, et al. NORVIT: Homocysteine lowering and cardiovascular events after acute myocardial infarction. N Enlg J Med 2006;354:1578-88. PubMed
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Figueiredo JC, Grau MV, Haile RW, et al. Folic acid and risk of prostate cancer: Results from a randomized clinical trial. J Natl Cancer Inst 2009;101:432-5. PubMed
- Clippe C, Freyer G, Milano G, Trillet-Lenoir V. Lethal toxicity of capecitabine due to abusive folic acid prescription. Clin Oncol (R Coll Radiol) 2003;15:299-300. PubMed
- Bedford Laboratories. Leucovorin calcium [package insert]. Bedford, OH. September 2008. Available at: http://www.bedfordlabs.com/BedfordLabsWeb/products/inserts/LCV-P02.pdf.
- Ebbing M, Bonaa KH, Nygard O, et al. Cancer incidence and mortality after treatment with folic acid and vitamin B12. JAMA 2009;302:2119-26.
- Haberg, S. E., London, S. J., Stigum, H., Nafstad, P., and Nystad, W. Folic acid supplements in pregnancy and early childhood respiratory health. Arch Dis.Child 2009;94(3):180-184. PubMed
- Whitrow, M. J., Moore, V. M., Rumbold, A. R., and Davies, M. J. Effect of supplemental folic acid in pregnancy on childhood asthma: a prospective birth cohort study. Am J Epidemiol. 12-15-2009;170(12):1486-1493. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Baggott, J. E., Oster, R. A., and Tamura, T. Meta-analysis of cancer risk in folic acid supplementation trials. Cancer Epidemiol. 2012;36(1):78-81. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Taneja S, Strand TA, Kumar T, et al. Folic acid and vitamin B-12 supplementation and common infections in 6-30-mo-old children in India: a randomized placebo-controlled trial. Am J Clin Nutr 2013;98(3):731-7. PubMed
- van Wijngaarden JP, Swart KM, Enneman AW, et al. Effect of daily vitamin B-12 and folic acid supplementation on fracture incidence in elderly individuals with an elevated plasma homocysteine concentration: B-PROOF, a randomized controlled trial. Am J Clin
- Qin X, Fan F, Cui Y, Chen F, Chen Y, Cheng X, Li Y, Wang B, Xu X, Xu X, Huo Y, Wang X. Folic acid supplementation with and without vitamin B6 and revascularization risk: a meta-analysis of randomized controlled trials. Clin Nutr. 2014;33(4):603-12. PubMed
- Crider KS, Cordero AM, Qi YP, Mulinare J, Dowling NF, Berry RJ. Prenatal folic acid and risk of asthma in children: a systematic review and meta-analysis. Am J Clin Nutr. 2013;98(5):1272-81. PubMed
- Matsubara S, Imai K, Murayama K, Higashizawa T. Severe liver dysfunction during nausea and vomiting of pregnancy: folic acid supplement as a suggested culprit. J Obstet Gynaecol. 2012;32(7):701-2. PubMed
- Qin X, Cui Y, Shen L, Sun N, Zhang Y, Li J, Xu X, Wang B, Xu X, Huo Y, Wang X. Folic acid supplementation and cancer risk: a meta-analysis of randomized controlled trials. Int J Cancer. 2013 1;133(5):1033-41. PubMed
- Tio M, Andrici J, Cox MR, Eslick GD. Folate intake and the risk of prostate cancer: a systematic review and meta-analysis. Prostate Cancer Prostatic Dis. 2014;17(3):213-9. PubMed
- Tomaszewski JJ, Richman EL, Sadetsky N, O'Keefe DS, Carroll PR, Davies BJ, Chan JM. Impact of folate intake on prostate cancer recurrence following definitive therapy: data from CaPSURE. J Urol. 2014;191(4):971-6. PubMed
- Valera-Gran D, García de la Hera M, Navarrete-Muñoz EM, Fernandez-Somoano A, Tardón A, Julvez J, Forns J, Lertxundi N, Ibarluzea JM, Murcia M, Rebagliato M, Vioque J; Infancia y Medio Ambiente (INMA) Project. Folic acid supplements during pregnancy and ch
- Van Der Woude DA, De Vries J, Van Wijk EM, Verzijl JM, Pijnenborg JM. A randomized controlled trial examining the addition of folic acid to iron supplementation in the treatment of postpartum anemia. Int J Gynaecol Obstet. 2014;126(2):101-5. PubMed
- Vila-Nova C, Wehby GL, Queirós FC, Chakraborty H, Félix TM, Goco N, Moore J, Gewehr EV, Lins L, Affonso CM, Murray JC. Periconceptional use of folic acid and risk of miscarriage - findings of the Oral Cleft Prevention Program in Brazil. J Perinat Med. 201 PubMed
- Vollset SE, Clarke R, Lewington S, Ebbing M, Halsey J, Lonn E, Armitage J, Manson JE, Hankey GJ, Spence JD, Galan P, Bønaa KH, Jamison R, Gaziano JM, Guarino P, Baron JA, Logan RF, Giovannucci EL, den Heijer M, Ueland PM, Bennett D, Collins R, Peto R; B-V
- Wehby GL, Félix TM, Goco N, Richieri-Costa A, Chakraborty H, Souza J, Pereira R, Padovani C, Moretti-Ferreira D, Murray JC. High dosage folic acid supplementation, oral cleft recurrence and fetal growth. Int J Environ Res Public Health. 2013 4;10(2):590-6 PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Liu J, Li Z, Ye R, Liu J, Ren A. Periconceptional folic acid supplementation and risk of parent-reported asthma in children at 4-6 years of age. ERJ Open Res. 2020;6(1):00250-2019. PubMed
- Houghton LA, Sherwood KL, Pawlosky R, Ito S, O'Connor DL. [6S]-5-Methyltetrahydrofolate is at least as effective as folic acid in preventing a decline in blood folate concentrations during lactation. Am J Clin Nutr. 2006 Apr;83(4):842-50. PubMed
- Houghton LA, Yang J, O'Connor DL. Unmetabolized folic acid and total folate concentrations in breast milk are unaffected by low-dose folate supplements. Am J Clin Nutr. 2009 Jan;89(1):216-20. PubMed
- Chan SL, Chan AWH, Mo F, et al. Association Between Serum Folate Level and Toxicity of Capecitabine During Treatment for Colorectal Cancer. Oncologist. 2018 Dec;23(12):1436-1445. PubMed
- Sarris J, Ravindran A, Yatham LN, et al. Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals: The World Federation of Societies of Biological Psychiatry (WFSBP) and Canadian Network for Mood and Anxiety T
Glycine 5 references
- Heresco-Levy U, Javitt DC, Ermilov M, et al. Efficacy of high-dose glycine in the treatment of enduring negative symptoms of schizophrenia. Arch Gen Psychiatry 1999;56:29-36.. PubMed
- Potkin SG, Jin Y, Bunney BG, Costa J, Gulasekaram B. Effect of clozapine and adjunctive high-dose glycine in treatment-resistant schizophrenia. Am J Psychiatry 1999;156:145-7.. PubMed
- Gusev EI, Skvortsova VI, Dambinova SA, et al. Neuroprotective effects of glycine for therapy of acute ischaemic stroke. Cerebrovasc Dis 2000;10:49-60. PubMed
- Inagawa K, Kawai N, Ono K, Sukegawa E, Tsubuku S, Takahashi M. Assessment of acute adverse effects of glycine ingestion at a high dose in human volunteers. Seikatsu Eisei. 2006; 50:27-32.
- Woods SW, Walsh BC, Hawkins KA, Miller TJ, Saksa JR, D'Souza DC, Pearlson GD, Javitt DC, McGlashan TH, Krystal JH. Glycine treatment of the risk syndrome for psychosis: report of two pilot studies. Eur Neuropsychopharmacol. 2013 Aug;23(8):931-40. PubMed
Copper 11 references
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Campbell IA, Elmes PC. Ethambutol and the eye: zinc and copper (letter). Lancet 1975;2:711. DOI
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Kozak SF, Inderlied CB, Hsu HY, et al. The role of copper on ethambutol's antimicrobial action and implications for ethambutol-induced optic neuropathy. Diag Microbiol Infect Dis 1998;30:83-7. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Cantilena LR, Klaassen CD. The effect of chelating agents on the excretion of endogenous metals. Toxicol Appl Pharmacol 1982;63:344-50.
- Babic Z, Tariba B, Kovacic J, Pizent A, Varnai VM, Macan J. Relevance of serum copper elevation induced by oral contraceptives: a meta-analysis. Contraception. 2013 Jun;87(6):790-800. PubMed
- Qui Q, Zhang F, Zhu W, Wu J, Liang M. Copper in diabetes mellitus: a meta-analysis and systematic review of plasma and serum studies. Biol Trace Elem Res 2017;177(1):53-63.
- Walker-Smith PK, Keith DJ, Kennedy CT, Sansom JE. Allergic contact dermatitis caused by copper. Contact Dermatitis 2016;75(3):186-7. PubMed
- Gallentine A. Third-degree burn on the neuropathic lower extremity in a patient with diabetes while wearing a copper-containing compression sock: a case report. Wound Manag Prev 2021;67(12):26-29. DOI
- Chung KJ, Chin YM, Wong MS, Sanmugam A, Singaravel S, Nah SA. Effectiveness of table salt versus copper sulphate in treating umbilical granuloma: A pilot randomized controlled trial. J Pediatr Surg 2022;57(2):261-265. PubMed
Vitamin B12 30 references
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Hartman TJ, Woodson K, Stolzenberg-Solomon R, et al. Association of the B-vitamins pyridoxal 5'-phosphate (B6), B12, and folate with lung cancer risk in older men. Am J Epidemiol 2001;153:688-94.. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Geissbuhler, P., Mermillod, B., and Rapin, C. H. Elevated serum vitamin B12 levels associated with CRP as a predictive factor of mortality in palliative care cancer patients: a prospective study over five years. J.Pain Symptom.Manage. 2000;20(2):93-103. PubMed
- Salles, N., Herrmann, F., Sakbani, K., Rapin, C. H., and Sieber, C. High vitamin B12 level: a strong predictor of mortality in elderly inpatients. J Am Geriatr.Soc 2005;53(5):917-918.
- Looker, H. C., Fagot-Campagna, A., Gunter, E. W., Pfeiffer, C. M., Sievers, M. L., Bennett, P. H., Nelson, R. G., Hanson, R. L., and Knowler, W. C. Homocysteine and vitamin B(12) concentrations and mortality rates in type 2 diabetes. Diabetes Metab Res R
- Uhl, W., Nolting, A., Golor, G., Rost, K. L., and Kovar, A. Safety of hydroxocobalamin in healthy volunteers in a randomized, placebo-controlled study. Clin Toxicol (Phila) 2006;44 Suppl 1:17-28. PubMed
- Borron, S. W., Baud, F. J., Barriot, P., Imbert, M., and Bismuth, C. Prospective study of hydroxocobalamin for acute cyanide poisoning in smoke inhalation. Ann Emerg.Med 2007;49(6):794-801, 801. PubMed
- Borron, S. W., Baud, F. J., Megarbane, B., and Bismuth, C. Hydroxocobalamin for severe acute cyanide poisoning by ingestion or inhalation. Am J Emerg.Med 2007;25(5):551-558. PubMed
- Lewis, J. G. Gout, Steatorrhoea, and Megaloblastic Anaemia. Ann Rheum.Dis 1962;21(3):284-286. PubMed
- Tal, S., Shavit, Y., Stern, F., and Malnick, S. Association between vitamin B12 levels and mortality in hospitalized older adults. J Am Geriatr.Soc 2010;58(3):523-526. PubMed
- Baztan, J. J., Gavidia, J. J., Gomez-Pavon, J., Esteve, A., and Ruiperez, I. High vitamin B12 levels and in-hospital mortality. J Am Geriatr.Soc 2010;58(11):2237-2238. PubMed
- Omboni, E., Checchini, M., and Longoni, F. [Hypopotassemia and megaloblastic anemia. Presentation of a case]. Minerva Med 8-31-1987;78(16):1255-1257.
- Aalfs As, Scholvinck LH, Horvath B. Acneiform eruption in a 5-year old due to vitamin B12 supplementation. Eur J Dermatol 2013;23(5):726-7. PubMed
- Balta I, Ozuguz P. Vitamin B12-induced acneiform eruption. Cutan Ocul Toxicol 2014;33(2):94-5. PubMed
- Carman KB, Belgemen T, Yis U. Involuntary movements misdiagnosed as seizure during vitamin B12 treatment. Pediatr Emerg Care 2013;29(11):1223-4. PubMed
- Djuric V, Bogic M, Popadic AP, et al. Anaphylactic reaction to hydroxycobalamin with tolerance to cyanocobalamin. Ann Allergy Asthma Immunol 2012;108(3):207-8. PubMed
- Kartel O, Gulec M, Demirel F, et al. Vitamin B12 allergy and successful desensitization with cyanocobalamin: A case report. Allergol Immunopath (Madr) 2012;40(5):324-5.
- Patiroglu T, Unal E, Yildirim S. Infantile tremor syndrome associated with cobalamin therapy: A case report. Clin Neurol Neurosurg 2013;115(9):1903-5. PubMed
- Schulte S, Barkema LW, Kardaun SH. Long-lasting atypical acneiform eruption with prominent comedones induced by hydroxocobalamin (vitamin B12). J Dtsch Dermatol Ges 2014;12(6):502-3.
- Zanus C, Alberini E, Costa P, et al. Involuntary movements after correction of vitamin B12 deficiency: A video-case report. Epileptic Disord 2012;14(2):174-80. PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Fujita Y, Mizukami T, Maya Y, et al. Vitamin B12 allergy manifesting as lymphomatoid contact dermatitis. Eur J Dermatol. 2020;30(3):304-305. PubMed
- Dépret F, Hoffmann C, Daoud L, et al. Association between hydroxocobalamin administration and acute kidney injury after smoke inhalation: a multicenter retrospective study. Crit Care. 2019;23(1):421. PubMed
- Khairan P, Sobue T, Eshak ES, et al. Association of dietary intakes of vitamin B12, vitamin B6, folate, and methionine with the risk of esophageal cancer: the Japan Public Health Center-based (JPHC) prospective study. BMC Cancer 2021;21(1):982. PubMed
- Evans J, Pandya A, Ding Y, Qunibi WY. Hydroxocobalamin-Induced Oxalate Nephropathy in a Patient With Smoke Inhalation. Kidney Int Rep 2021;6(8):2228-2231. PubMed
- Lacombe V, Chabrun F, Lacout C, et al. Persistent elevation of plasma vitamin B12 is strongly associated with solid cancer. Sci Rep 2021;11(1):13361. PubMed
- Pegalajar-García MD, Cebolla-Verdugo M, Prados-Carmona Á, Llamas-Segura C, Navarro-Triviño FJ. Systemic allergic dermatitis to cobalt present in cyanocobalamin supplementation. Contact Dermatitis 2023;89(3):203-205. PubMed
Phenylalanine 23 references
- Rouse B, Azen C, Koch R, et al. Maternal phenylketonuria collaborative Study (MPKUCS) offspring: facial anomalies, malformations, and early neurological sequelae. Am J Med Genet 1997;69:89-95. DOI
- Sturtevant FM. Use of aspartame in pregnancy. Int J Fertil 1985;30:85-7.
- Silkaitis RP, Mosnaim AD. Pathways linking L-phenylalanine and 2-phenylethylamine with p-tyramine in rabbit brain. Brain Res 1976;114:105-15.
- Lehmann WD, Theobald N, Fischer R, Heinrich HC. Stereospecificity of phenylalanine plasma kinetics and hydroxylation in man following oral application of a stable isotope-labelled pseudo-racemic mixture of L- and D-phenylalanine. Clin Chim Acta 1983;128 PubMed
- Mosnik DM, Spring B, Rogers K, Baruah S. Tardive dyskinesia exacerbated after ingestion of phenylalanine by schizophrenic patients. Neuropsychopharmacology 1997;16:136-46. PubMed
- Siddiqui AH, Stolk LM, Bhaggoe R, et al. L-phenylalanine and UVA irradiation in the treatment of vitiligo. Dermatology 1994;88:215-8. PubMed
- Birkmayer W, Riederer P, Linauer W, Knoll J. L-deprenyl plus L-phenylalanine in the treatment of depression. J Neural Transm 1984;59:81-7. PubMed
- Nutt JG, Woodward WR, Hammerstad JP, et al. The "on-off" phenomenon in Parkinson's disease. Relation to levodopa absorption and transport. N Engl J Med 1984;310:483-8. PubMed
- Baruzzi A, Contin M, Riva R, et al. Influence of meal ingestion time on pharmacokinetics of orally administered levodopa in parkinsonian patients. Clin Neuropharmacol 1987;10:527-37. PubMed
- Juncos JL, Fabbrini G, Mouradian MM, et al. Dietary influences on the antiparkinsonian response to levodopa. Arch Neurol 1987;44:1003-5. PubMed
- Eriksson T, Granerus AK, Linde A, et al. "On-off" phenomenon in Parkinson's disease: relationship between dopa and other large neutral amino acids in plasma. Neurology 1988;38:1245-8. PubMed
- Baker GB, Bornstein RA, Rouget AC, et al. Phenylethylaminergic mechanisms in attention-deficit disorder. Biol Psychiatry 1991;29:15-22.. PubMed
- Wood DR, Reimherr FW, Wender PH. Treatment of attention deficit disorder with DL-phenylalanine. Psychiatry Res 1985;16:21-6.. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Energy, Carbohydrate, Fiber, Fat, Fatty Acids, Cholesterol, Protein, and Amino Acids (Macronutrients). Washington, DC: National Academy Press, 2002. Available at: http://www.n
- Cederbaum S. Phenylketonuria: an update. Curr Opin Pediatr 2002;14:702-6. PubMed
- Cejudo-Ferragud, E., Nacher, A., Polache, A., Cercos-Fortea, T., Merino, M., and Casabo, V. G. Evidence of competitive inhibition for the intestinal absorption of baclofen by phenylalanine. Int J of Pharm (Amsterdam) 1996;132:63-69. DOI
- Fischer, E., Heller, B., Nachon, M., and Spatz, H. Therapy of depression by phenylalanine. Preliminary note. Arzneimittelforschung. 1975;25(1):132.
- Beckmann, H., Strauss, M. A., and Ludolph, E. Dl-phenylalanine in depressed patients: an open study. J.Neural Transm. 1977;41(2-3):123-134. PubMed
- Sabelli, H. C., Fawcett, J., Gusovsky, F., Javaid, J. I., Wynn, P., Edwards, J., Jeffriess, H., and Kravitz, H. Clinical studies on the phenylethylamine hypothesis of affective disorder: urine and blood phenylacetic acid and phenylalanine dietary supplem
- Cotzias, G. C., Van Woert, M. H., and Schiffer, L. M. Aromatic amino acids and modification of parkinsonism. N Engl.J Med 2-16-1967;276(7):374-379. PubMed
- Kravitz, H. M., Sabelli, H. C., and Fawcett, J. Dietary supplements of phenylalanine and other amino acid precursors of brain neuroamines in the treatment of depressive disorders. J Am Osteopath.Assoc 1984;84(1 Suppl):119-123. DOI
- Mann, J., Peselow, E. D., Snyderman, S., and Gershon, S. D-phenylalanine in endogenous depression. Am.J.Psychiatry 1980;137(12):1611-1612. PubMed
- Katoulis AC, Alevizou A, Bozi E, et al. A randomized, double-blind, vehicle-controlled study of a preparation containing undecylenoyl phenylalanine 2% in the treatment of solar lentigines. Clin Exp Dermatol 2010;35(5):473-6. PubMed
Potassium 12 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Gennaro A. Remington: The Science and Practice of Pharmacy. 19th ed. Lippincott: Williams & Wilkins, 1996.
- Whelton PK, He J, Cutler JA, et al. Effects of oral potassium on blood pressure. Meta-analysis of randomized controlled clinical trials. JAMA 1997;277:1624-32. PubMed
- Phillips, C. O., Kashani, A., Ko, D. K., Francis, G., and Krumholz, H. M. Adverse effects of combination angiotensin II receptor blockers plus angiotensin-converting enzyme inhibitors for left ventricular dysfunction: a quantitative review of data from ra DOI
- Altieri, P. I., Herrero, C., Suero, R., and Ortiz, A. Bleeding duodenal ulcer in a patient taking slow-releasing potassium tablets. Bol.Asoc.Med P.R. 1977;69(8):276.
- Raf, L. E. Enteric-coated potassium chloride tablets and ulcer of the small intestine. Acta Chir Scand Suppl 1967;(374):1-87.
- Potassium chloride oral solution [package insert]. Allentown, PA: Lehigh Valley Technologies, Inc.; 2014.
- Potassium chloride injection [package insert]. Lake Forest, IL: Hospira Inc.; 2009.
- Patel RB, Tannenbaum S, Viana-Tejedor A, et al. Serum potassium levels, cardiac arrhythmias, and mortality following non-ST-elevation myocardial infarction or unstable angina: insights from MERLIN-TIMI 36. Eur Heart J Acute Cardiovasc Care 2017 Feb;6(1):1 PubMed
- Malta D, Arcand J, Ravindran A, Floras V, Allard JP, Newton GE. Adequate intake of potassium does not cause hyperkalemia in hypertensive individuals taking medications that antagonize the renin angiotensin aldosterone system. Am J Clin Nutr 2016 Oct;104(4 PubMed
- Keskin M, Kaya A, Tatlisu MA, et al. The effect of serum potassium level on in-hospital and long-term mortality in ST elevation myocardial infarction. Int J cardiol. 2016 Oct 15;221:505-10.
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
Niacinamide 22 references
- Pozzilli P, Browne PD, Kolb H. Meta-analysis of nicotinamide treatment in patients with recent-onset IDDM. The Nicotinamide Trialists. Diabetes Care 1996;19:1357-63. PubMed
- Greenbaum CJ, Kahn SE, Palmer JP. Nicotinamide's effects on glucose metabolism in subjects at risk for IDDM. Diabetes 1996;45:1631-4. DOI
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Anon. Niacinamide Monograph. Alt Med Rev 2002;7:525-9.
- Miralbell R, Mornex F, Greiner R, et al. Accelerated radiotherapy, carbogen, and nicotinamide in glioblastoma multiforme: report of European Organization for Research and Treatment of Cancer trial 22933. J Clin Oncol 1999;17:3143-9. PubMed
- Fatigante L, Ducci F, Cartei F, et al. Carbogen and nicotinamide combined with unconventional radiotherapy in glioblastoma multiforme: a new modality treatment. Int J Radiat Oncol Biol Phys 1997;37:499-504. PubMed
- Hoskin PJ, Stratford MR, Saunders MI, et al. Administration of nicotinamide during chart: pharmacokinetics, dose escalation, and clinical toxicity. Int J Radiat Oncol Biol Phys 1995;32:1111-9. PubMed
- Papa CM. Niacinamide and acanthosis nigricans (letter). Arch Dermatol 1984;120:1281. DOI
- Bourgeois BF, Dodson WE, Ferrendelli JA. Interactions between primidone, carbamazepine, and nicotinamide. Neurology 1982;32:1122-6.
- Visalli N, Cavallo MG, Signore A, et al. A multi-centre randomized trial of two different doses of nicotinamide in patients with recent-onset type 1 diabetes (the IMDIAB VI). Diabetes Metab Res Rev 1999;15:181-5. DOI
- Rottembourg JB, Launay-Vacher V, Massard J. Thrombocytopenia induced by nicotinamide in hemodialysis patients. Kidney Int. 2005;68(6):2911-2. PubMed
- Fabbrocini G, Cantelli M, Monfrecola G. Topical nicotinamide for seborrheic dermatitis: an open randomized study. J Dermatolog Treat. 2014 Jun;25(3):241-5. PubMed
- Khodaeiani E, Fouladi RF, Amirnia M, Saeidi M, Karimi ER. Topical 4% nicotinamide vs. 1% clindamycin in moderate inflammatory acne vulgaris. Int J Dermatol. 2013 Aug;52(8):999-1004. PubMed
- Zhang Y, Ma T, Zhang P. Efficacy and safety of nicotinamide on phosphorus metabolism in hemodialysis patients: A systematic review and meta-analysis. Medicine (Baltimore). 2018;97(41):e12731. PubMed
- Ketteler M, Wiecek A, Rosenkranz AR, et al. Efficacy and Safety of a Novel Nicotinamide Modified-Release Formulation in the Treatment of Refractory Hyperphosphatemia in Patients Receiving Hemodialysis-A Randomized Clinical Trial. Kidney Int Rep 2020;6(3): PubMed
- Mainville L, Smilga AS, Fortin PR. Effect of Nicotinamide in Skin Cancer and Actinic Keratoses Chemoprophylaxis, and Adverse Effects Related to Nicotinamide: A Systematic Review and Meta-Analysis. J Cutan Med Surg 2022;26(3):297-308. PubMed
- Nouh AH, Elshahid AR, Kadah AS, Zeyada YA. Topical niacinamide (Nicotinamide) treatment for discoid lupus erythematosus (DLE): A prospective pilot study. J Cosmet Dermatol 2023.
- El-Khalawany M, Nouh AH, Kadah AS, Elsheikh M, Said M. Evaluation of safety and efficacy of topical 4% nicotinamide in treatment of psoriasis; among a representative sample of Egyptians (an analytical observational study). Dermatol Ther 2022;35(9):e15734. PubMed
- Zhang H, George-Washburn EA, Hashemi KB, et al. Oral Nicotinamide for Actinic Keratosis Prevention in Kidney Transplant Recipients: A Pilot Double-Blind, Randomized, Placebo-Controlled Trial. Transplant Proc 2023;55(9):2079-2084. PubMed
- Oh HJ, Bae SC, Oh IJ, et al. Nicotinamide in Combination with EGFR-TKIs for the Treatment of Stage IV Lung Adenocarcinoma with EGFR Mutations: A Randomized Double-Blind (Phase IIb) Trial. Clin Cancer Res 2024;30(8):1478-1487. PubMed
- Schepers L, Jans I, Pot GK, Smilde AJ, Hofstra JM, de Roos NM. The Effect of Niacinamide Supplementation on Phosphate Concentrations in Dutch Dialysis Patients: A Randomized Crossover Trial. J Ren Nutr 2024;34(5):454-462. PubMed
- Markham DJ, Barbosa NS, Degesys CA. Elevated International Normalized Ratio After Initiation of Niacin and Niacinamide Chemoprophylaxis for Patients on Warfarin. Dermatol Surg 2024;50(7):690-692. PubMed
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Vitamin B6 32 references
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Yates AA, Schlicker SA, Suitor CW. Dietary reference intakes: The new basis for recommendations for calcium and related nutrients, B vitamins, and choline. J Am Diet Assoc 1998;98:699-706. PubMed
- Geerling BJ, Dagnelie PC, Badart-Smook A, et al. Diet as a risk factor for the development of ulcerative colitis. Am J Gastroenterol 2000;95:1008-13. PubMed
- South M. Neonatal seizures after pyridoxine use -- reply. Lancet 1999;354:2083. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Baxter P, Aicardi J. Neonatal seizures after pyridoxine use. Lancet 1999;354:2082-3. PubMed
- Bendich A, Cohen M. Vitamin B6 safety issues. Ann N Y Acad Sci 1990;585:321-30.
- Schaumburg H, Kaplan J, Windebank A. Sensory neuropathy from pyridoxine abuse. A new megavitamin syndrome. N Engl J Med 1983;309:445-8. PubMed
- Gordon N. Pyridoxine dependency: an update. Dev Med Child Neurol 1997;39:63-5. PubMed
- Lewis PJ. Pain in the hand and wrist. Pyridoxine supplements may help patients with carpal tunnel syndrome. BMJ 1995;310:1534. PubMed
- Kaufman G. Pyridoxine against amiodarone-induced photosensitivity (letter). Lancet 1984;1:51-2. PubMed
- Mulrow JP, Mulrow CD, McKenna WJ. Pyridoxine and amiodarone-induced photosensitivity. Ann Intern Med 1985;103:68-9. PubMed
- Kawada A, Kashima A, Shiraishi H, et al. Pyridoxine-induced photosensitivity and hypophosphatasia. Dermatology 2000;201:356-60.. PubMed
- Vasile A, Goldberg R, Kornberg B. Pyridoxine toxicity: report of a case. J Am Osteopath Assoc 1984;83:790-1. DOI
- Hansson O, Sillanpaa M. Pyridoxine and serum concentration of phenytoin and phenobarbitone. Lancet 1976;1:256. DOI
- Jansen T, Romiti R, Kreuter A, Altmeyer P. Rosacea fulminans triggered by high-dose vitamins B6 and B12. J Eur Acad Dermatol Venereol 2001;15:484-5..
- Chittumma P, Kaewkiattikun K, Wiriyasiriwach B. Comparison of the effectiveness of ginger and vitamin B6 for treatment of nausea and vomiting in early pregnancy: a randomized double-blind controlled trial. J Med Assoc Thai 2007;90:15-20.
- Hatzitolios, A., Iliadis, F., Katsiki, N., and Baltatzi, M. Is the anti-hypertensive effect of dietary supplements via aldehydes reduction evidence based? A systematic review. Clin Exp.Hypertens. 2008;30(7):628-639. PubMed
- Vasdev, S., Ford, C. A., Parai, S., Longerich, L., and Gadag, V. Dietary vitamin B6 supplementation attenuates hypertension in spontaneously hypertensive rats. Mol.Cell Biochem. 1999;200(1-2):155-162.
- de, Vogel S., Dindore, V., van, Engeland M., Goldbohm, R. A., van den Brandt, P. A., and Weijenberg, M. P. Dietary folate, methionine, riboflavin, and vitamin B-6 and risk of sporadic colorectal cancer. J Nutr 2008;138(12):2372-2378. PubMed
- Hagen, I., Nesheim, B. I., and Tuntland, T. No effect of vitamin B-6 against premenstrual tension. A controlled clinical study. Acta Obstet.Gynecol.Scand. 1985;64(8):667-670. PubMed
- Aybak, M., Sermet, A., Ayyildiz, M. O., and Karakilcik, A. Z. Effect of oral pyridoxine hydrochloride supplementation on arterial blood pressure in patients with essential hypertension. Arzneimittelforschung. 1995;45(12):1271-1273.
- Lal, K. J., Dakshinamurti, K., and Thliveris, J. The effect of vitamin B6 on the systolic blood pressure of rats in various animal models of hypertension. J Hypertens. 1996;14(3):355-363. PubMed
- Lauritzen CH, Reuter HD, Repges R, Bohnert K, and Schmidt U. Treatment of premenstrual tension syndrome with Vitex agnus castus. Controlled, double-blind study versus pyridoxine. Phytomed 1997;4(3):183-189. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Hoyer-Kuhn H, Kohbrok S, Volland R, Franklin J, Hero B, Beck BB, Hoppe B. Vitamin B6 in primary hyperoxaluria I: first prospective trial after 40 years of practice. Clin J Am Soc Nephrol. 2014 Mar;9(3):468-77. PubMed
- Mahmoud A, Tabassum S, Al Enazi S, et al. Amelioration of levetiracetam-induced behavioral side effects by pyridoxine. A randomized double blind controlled study. Pediatr Neurol 2021;119:15-21. PubMed
- Gupta M, Gallante B, Bamberger JN, et al. Prospective randomized evaluation of idiopathic hyperoxaluria treatments. J Endourol 2021;35(12):1844-1851. PubMed
- Li H, Chen M, Liang S, et al. Excessive vitamin B6 during treatment is related to poor prognosis of patients with nasopharyngeal carcinoma: A U-shaped distribution suggests low dose supplement. Clin Nutr 2021;40(4):2293-2300. PubMed
- Tanigawa J, Nabatame S, Tominaga K, et al. High-dose pyridoxine treatment for inherited glycosylphosphatidylinositol deficiency. Brain Dev 2021;43(6):680-687. PubMed
- Committee on Practice Bulletins-Obstetrics. ACOG Practice Bulletin No. 189: Nausea And Vomiting Of Pregnancy. Obstet Gynecol. 2018;131(1):e15-e30. PubMed
Yerba Mate 123 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Pintos J, Franco EL, Oliveira BV, et al. Mate, coffee, and tea consumption and risk of cancers of the upper aerodigestive tract in southern Brazil. Epidemiology 1994;5:583-90.
- De Stefani E, Fierro L, Mendilaharsu M, et al. Meat intake, 'mate' drinking and renal cell cancer in Uruguay: a case-control study. Br J Cancer 1998;78:1239-43. PubMed
- De Stefani E, Correa P, Fierro L, et al. Black tobacco, mate, and bladder cancer. A case-control study from Uruguay. Cancer 1991;67:536-40.
- De Stefani E, Fierro L, Correa P, et al. Mate drinking and risk of lung cancer in males: a case-control study from Uruguay. Cancer Epidemiol Biomarkers Prev 1996;5:515-9.
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- DiPiro JT, Talbert RL, Yee GC, et al; eds. Pharmacotherapy: A pathophysiologic approach. 4th ed. Stamford, CT: Appleton & Lange, 1999.
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- McGee J, Patrick RS, Wood CB, Blumgart LH. A case of veno-occlusive disease of the liver in Britain associated with herbal tea consumption. J Clin Pathol 1976;29:788-94. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Dreher HM. The effect of caffeine reduction on sleep quality and well-being in persons with HIV. J Psychosom Res 2003;54:191-8.. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Holmgren P, Norden-Pettersson L, Ahlner J. Caffeine fatalities--four case reports. Forensic Sci Int 2004;139:71-3. PubMed
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Goldenberg D, Golz A, Joachims HZ. The beverage mate: a risk factor for cancer of the head and neck. Head Neck 2003;25:595-601.
- Sewram V, De Stefani E, Brennan P, Boffetta P. Mate consumption and the risk of squamous cell esophageal cancer in uruguay. Cancer Epidemiol Biomarkers Prev 2003;12:508-13.
- Santos IS, Matijasevich A, Valle NC. Mate drinking during pregnancy and risk of preterm and small for gestational age birth. J Nutr 2005;135:1120-3.
- Benowitz NL, Osterloh J, Goldschlager N, et al. Massive catecholamine release from caffeine poisoning. JAMA 1982;248:1097-8. DOI
- Leson CL, McGuigan MA, Bryson SM. Caffeine overdose in an adolescent male. J Toxicol Clin Toxicol 1988;26:407-15. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Azcona O, Barbanoi MJ, Torrent J, Jane F. Evaluation of the central effects of alcohol and caffeine interaction. Br J Clin Pharmacol 1995;40:393-400. PubMed
- Broughton LJ, Rogers HJ. Decreased systemic clearance of caffeine due to cimetidine. Br J Clin Pharmacol 1981;12:155-9. PubMed
- File SE, Bond AJ, Lister RG. Interaction between effects of caffeine and lorazepam in performance tests and self-ratings. J Clin Psychopharmacol 1982;2:102-6. DOI
- Mattila MJ, Palva E, Savolainen K. Caffeine antagonizes diazepam effects in man. Med Biol 1982;60:121-3.
- Mattila MJ, Nuotto E. Caffeine and theophylline counteract diazepam effects in man. Med Biol 1983;61:337-43.
- Mattila ME, Mattila MJ, Nuotto E. Caffeine moderately antagonizes the effects of triazolam and zopiclone on the psychomotor performance of healthy subjects. Pharmacol Toxicol 1992;70:286-9.
- Mattila MJ, Vainio P, Nurminen ML, et al. Midazolam 12 mg is moderately counteracted by 250 mg caffeine in man. Int J Clin Pharmacol Ther 2000;38:581-7. PubMed
- Zelenitsky SA, Norman A, Nix DE. The effects of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. J Infect Dis Pharmacother 1995;1:1-11.
- Joeres R, Richter E. Mexiletine and caffeine elimination. N Engl J Med 1987;317:117. PubMed
- ROTH, J. L. Clinical evaluation of the caffeine gastric analysis in duodenal ulcer patients. Gastroenterology 1951;19(2):199-215. DOI
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Smits, P., Lenders, J. W., and Thien, T. Caffeine and theophylline attenuate adenosine-induced vasodilation in humans. Clin.Pharmacol.Ther. 1990;48(4):410-418. PubMed
- Jeppesen, U., Loft, S., Poulsen, H. E., and Brsen, K. A fluvoxamine-caffeine interaction study. Pharmacogenetics 1996;6(3):213-222. PubMed
- Bates, M. N., Rey, O. A., Biggs, M. L., Hopenhayn, C., Moore, L. E., Kalman, D., Steinmaus, C., and Smith, A. H. Case-control study of bladder cancer and exposure to arsenic in Argentina. Am J Epidemiol. 2-15-2004;159(4):381-389.
- Bates, M. N., Hopenhayn, C., Rey, O. A., and Moore, L. E. Bladder cancer and mate consumption in Argentina: a case-control study. Cancer Lett. 2-8-2007;246(1-2):268-273. PubMed
- Martin, I., Lopez-Vilchez, M. A., Mur, A., Garcia-Algar, O., Rossi, S., Marchei, E., and Pichini, S. Neonatal withdrawal syndrome after chronic maternal drinking of mate. Ther Drug Monit. 2007;29(1):127-129. PubMed
- de Morais, E. C., Stefanuto, A., Klein, G. A., Boaventura, B. C., de, Andrade F., Wazlawik, E., Di Pietro, P. F., Maraschin, M., and da Silva, E. L. Consumption of yerba mate ( Ilex paraguariensis ) improves serum lipid parameters in healthy dyslipidemic
- De, Stefani E., Correa, P., Oreggia, F., Deneo-Pellegrini, H., Fernandez, G., Zavala, D., Carzoglio, J., Leiva, J., Fontham, E., and Rivero, S. Black tobacco, wine and mate in oropharyngeal cancer. A case-control study from Uruguay. Rev.Epidemiol.Sante P
- Vassallo, A., Correa, P., De, Stefani E., Cendan, M., Zavala, D., Chen, V., Carzoglio, J., and Deneo-Pellegrini, H. Esophageal cancer in Uruguay: a case-control study. J Natl.Cancer Inst. 1985;75(6):1005-1009.
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Stefani ED, Moore M, Aune D, Deneo-Pellegrini H, Ronco AL, Boffetta P, et al. Maté consumption and risk of cancer: a multi-site case-control study in Uruguay. Asian Pac J Cancer Prev. 2011;12(4):1089-93.
- International Agency for Research on Cancer (IARC). IARC monographs evaluate drinking coffee, mate, and very hot beverages. https://www.iarc.fr/en/media-centre/pr/2016/pdfs/pr244_E.pdf. Accessed November 1, 2017.
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Feltrin C, Farias IV, Sandjo LP, Reginatto FH, Simões CMO. Effects of Standardized Medicinal Plant Extracts on Drug Metabolism Mediated by CYP3A4 and CYP2D6 Enzymes. Chem Res Toxicol 2020;33(9):2408-2419. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
Acai 2 references
- Udani JK, Singh BB, Singh VJ, Barrett ML. Effects of acai (Euterpe oleracea Mart.) berry preparation on metabolic parameters in a healthy overweight population: a pilot study. Nutr J 2011;10:45.
- de Liz S, Cardoso AL, Copetti CLK, et al. Açaí (Euterpe oleracea Mart.) and juçara (Euterpe edulis Mart.) juices improved HDL-c levels and antioxidant defense of healthy adults in a 4-week randomized cross-over study. Clin Nutr. 2020;39(12):3629-3636. PubMed
Mangosteen 6 references
- Chairungsrilerd N, Furukawa K, Ohta T, et al. Histaminergic and serotonergic receptor blocking substances from the medicinal plant Garcinia mangostana. Planta Med 1996;62:471-2.
- Wong LP, Klemmer PJ. Severe lactic acidosis associated with juice of the mangosteen fruit Garcinia mangostana. Am J Kidney Dis 2008;51:829-33. PubMed
- Furukawa, K., Chairungsrilerd, N., Ohta, T., Nozoe, S., and Ohizumi, Y. [Novel types of receptor antagonists from the medicinal plant Garcinia mangostana]. Nippon Yakurigaku Zasshi 1997;110 Suppl 1:153P-158P. PubMed
- Chairungsrilerd, N., Furukawa, K., Tadano, T., Kisara, K., and Ohizumi, Y. Effect of gamma-mangostin through the inhibition of 5-hydroxy-tryptamine2A receptors in 5-fluoro-alpha-methyltryptamine-induced head-twitch responses of mice. Br J Pharmacol. 1998
- Suthammarak W, Numpraphrut P, Charoensakdi R, et al. Antioxidant-enhancing property of the polar fraction of mangosteen pericarp extract and evaluation of its safety in humans. Oxid Med Cell Longev 2016;2016:1293036. PubMed
- Bae M, Han SY, Kim ES, et al. Effect of Water Extract of Mangosteen Pericarp on Donepezil Pharmacokinetics in Mice. Molecules 2021;26(17):5246. PubMed
Pomegranate 27 references
- Igea JM, Cuesta J, Cuevas M, et al. Adverse reaction to pomegranate ingestion. Allergy 1991;46:472-4. DOI
- Gaig P, Bartolome B, Lleonart R, et al. Allergy to pomegranate (Punica granatum). Allergy 1999;54:287-8.
- Aviram M, Dornfeld L. Pomegranate juice consumption inhibits serum angiotensin converting enzyme activity and reduces systolic blood pressure. Atherosclerosis 2001;158:195-8. PubMed
- Valsecchi R, Reseghetti A, Leghissa P, et al. Immediate contact hypersensitivity to pomegranate. Contact Dermatitis 1998;38:44-5. PubMed
- Esmaillzadeh A, Tahbaz F, Gaieni I, et al. Concentrated pomegranate juice improves lipid profiles in diabetic patients with hyperlipidemia. J Med Food 2004;7:305-8. PubMed
- Aviram M, Rosenblat M, Gaitini D, et al. Pomegranate juice consumption for 3 years by patients with carotid artery stenosis reduces common carotid intima-media thickness, blood pressure and LDL oxidation. Clin Nutr 2004;23:423-33. DOI
- Hidaka M, Okumura M, Fujita K, et al. Effects of pomegranate juice on human cytochrome p450 3A (CYP3A) and carbamazepine pharmacokinetics in rats. Drug Metab Dispos 2005;33:644-8. PubMed
- Loren DJ, Seeram NP, Schulman RN, Holtzman DM. Maternal dietary supplementation with pomegranate juice is neuroprotective in an animal model of neonatal hypoxic-ischemic brain injury. Pediatr Res 2005;57:858-64. PubMed
- Kim ND, Mehta R, Yu W, et al. Chemopreventive and adjuvant therapeutic potential of pomegranate (Punica granatum) for human breast cancer. Breast Cancer Res Treat 2002;71:203-17. PubMed
- Sorokin AV, Duncan B, Panetta R, Thompson PD. Rhabdomyolysis associated with pomegranate juice consumption. Am J Cardiol 2006;98:705-6. PubMed
- Farkas D, Oleson LE, Zhao Y, et al. Pomegranate juice does not impair clearance of oral or intravenous midazolam, a probe for cytochrome P450-3A activity: comparison with grapefruit juice. J Clin Pharmacol 2007;47:286-94. PubMed
- Yeo C, Shon J, Liu K, et al. The effects of pomegranate juice on the pharmacokinetics of simvastatin in healthy Korean subjects (PI-63). Clin Pharmacol Ther 2006;79:23.
- Farkas D, Greenblatt DJ. Influence of fruit juices on drug disposition: discrepancies between in vitro and clinical studies. Expert Opin Drug Metab Toxicol 2008;4:381-93.
- Nagata M, Hidaka M, Sekiya H, et al. Effects of pomegranate juice on human cytochrome P450 2C9 and tolbutamide pharmacokinetics in rats. Drug Metab Dispos 2007;35:302-5. PubMed
- Komperda KE. Potential interaction between pomegranate juice and warfarin. Pharmacotherapy 2009;29:1002-6. PubMed
- Gangemi S, Mistrello G, Roncarolo D, et al. Pomegranate-dependent exercise-induced anaphylaxis. J Investig Allergol Clin Immunol 2008;18:491-2.
- Misaka S, Nakamura R, Uchida S, et al. Effect of 2 weeks' consumption of pomegranate juice on the pharmacokinetics of a single dose of midazolam: an open-label, randomized, single-center, 2-period crossover study in healthy Japanese volunteers. Clin Ther PubMed
- Jarvis S, Li C, Bogle RG. Possible interaction between pomegranate juice and warfarin. Emerg Med J 2010;27:74-5. PubMed
- Esmaillzadeh, A., Tahbaz, F., Gaieni, I., Alavi-Majd, H., and Azadbakht, L. Cholesterol-lowering effect of concentrated pomegranate juice consumption in type II diabetic patients with hyperlipidemia. Int J Vitam.Nutr Res 2006;76(3):147-151. PubMed
- Forest, C. P., Padma-Nathan, H., and Liker, H. R. Efficacy and safety of pomegranate juice on improvement of erectile dysfunction in male patients with mild to moderate erectile dysfunction: a randomized, placebo-controlled, double-blind, crossover study PubMed
- Wright, H. and Pipkin F. B. Pomegranates (Punica granatum), kiwifruit (Actinidia deliciosa) and blood pressure: a pilot study. Proceedings of the Nutrition Society 2008;67(8):1.
- Sohrab G, Sotoodeh G, Siasi F, et al. Effect of pomegranate juice consumption on blood pressure in type 2 diabetic patients. Iranian Journal of Endocrinology and Metabolism 2008;9:399-405, 470.
- Enrique E, Utz M, De Mateo JA, et al. Allergy to lipid transfer proteins: cross-reactivity among pomegranate, hazelnut, and peanut. Ann Allergy Asthma Immunol 2006;96(1):122-3. PubMed
- Hanley MJ, Masse G, Harmatz JS, et al. Pomegranate juice and pomegranate extract do not impair oral clearance of flurbiprofen in human volunteers: divergence from in vitro results. Clin Pharmacol Ther 2012;92(5):651-7. PubMed
- Paller CJ, Ye X, Wozniak PJ, et al. A randomized phase II study of pomegranate extract for men with rising PSA following initial therapy for localized prostate cancer. Prostate Cancer Prostatic Dis 2013;16(1):50-5. PubMed
- Park SJ, Yeo CW, Shim EJ, et al. Pomegranate juice does not affect the disposition of simvastatin in healthy subjects. Eur J Drug Metab Pharmacokinet 2016;41(4):339-44. PubMed
- Ross MM, Cherkerzian S, Mikulis ND, et al. A randomized controlled trial investigating the impact of maternal dietary supplementation with pomegranate juice on brain injury in infants with IUGR. Sci Rep. 2021;11(1):3569. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC