
Feel the Beet Ingredients & Drug Interactions
by Live it Up
What is this page for?
First and foremost: checking Feel the Beet against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Feel the Beet is a dietary supplement by Live it Up with 16 active ingredients. Its ingredients are commonly taken for replacing fluids and electrolytes, preventing dehydration during exercise or illness, treating low blood sodium (under medical care).Based on those ingredients, 2,356 medications have a known interaction with it, the most serious rated major. The ingredients most likely to interact are Dietary Fiber, KSM-66, Ginkgo biloba Leaf Extract. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Feel the Beet by Live it Up
Ask about any prescription or over-the-counter medication and we check it for interactions with Feel the Beet by Live it Up — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Feel the Beet by Live it Up
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Feel the Beet contains 19 active ingredients: a mineral trio of sodium, calcium, iron, and magnesium; mushroom extracts from reishi, shiitake, lion's mane, turkey tail, and cordyceps; herbal extracts including maca powder, ashwagandha (KSM-66 brand), ginkgo leaf, bacopa, and pomegranate powder; plus caffeine, lemon juice powder, beet root juice powder, and proprietary blends (Vitality Blend, CognatiQ, and Peak O2). The product also contains inactive ingredients: coconut water powder, monk fruit extract, citric acid, and natural berry flavoring.
Does it work?
Strong evidence
The evidence for Feel the Beet's ingredients is mixed and often limited. Calcium is effective for bone health and certain conditions like kidney failure.
Iron is effective for iron-deficiency anemia. Caffeine is likely effective for mental alertness and athletic performance.
Beet root shows possible effectiveness for athletic performance and exercise-induced muscle soreness. Magnesium is effective for constipation and certain deficiency states.
Ginkgo, ashwagandha, and bacopa are possibly effective for anxiety and cognitive support, though evidence remains preliminary. For most of the other ingredients and blends—including reishi, shiitake, lion's mane, cordyceps, maca, and pomegranate in these formulations—the evidence in our data is insufficient to establish benefit, or they are rated possibly ineffective.
How safe is it?
Well-documented data
Individual ingredients show varying safety profiles. Sodium at high levels carries caution around blood pressure and heart strain; the product's sodium content should be checked against your daily intake.
Calcium, iron, and magnesium are generally well tolerated at recommended doses but can cause gastrointestinal upset (constipation, diarrhea, nausea). Caffeine commonly causes anxiety, insomnia, and jitteriness; high doses pose serious risks.
Herbal ingredients—reishi, ashwagandha, ginkgo, bacopa, cordyceps, and pomegranate—are generally well tolerated short-term, though long-term safety data are limited. Ashwagandha and ginkgo carry rare but serious concerns around liver damage and bleeding, respectively.
For pregnancy and breastfeeding: calcium, magnesium, and iron are likely safe in recommended amounts during pregnancy; ashwagandha, reishi, ginkgo, lion's mane, and cordyceps should be avoided during pregnancy and breastfeeding due to insufficient safety data.
Meds to double-check
Major interaction found
Before taking Feel the Beet, double-check these medication types with the tool on this page, worst interactions first: HIV integrase inhibitors (dolutegravir, elvitegravir) and intravenous ceftriaxone (Major risk from calcium); antihypertensive and blood pressure drugs (sodium, reishi, ashwagandha, pomegranate); blood thinners and anticoagulants (calcium, caffeine with ephedrine, ginkgo, pomegranate); thyroid hormones (calcium, iron, ashwagandha); and diabetes medications (ashwagandha, lion's mane, reishi). Also check for quinolone and tetracycline antibiotics (iron interaction), bisphosphonates (calcium and iron), and lithium (sodium).
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with strong clinical evidence behind its ingredients' uses. Major medication interactions have been identified, and safety information is well characterized.
Feel the Beet may appeal to someone looking for a broad-spectrum wellness powder with minerals, mushroom adaptogens, and herbal support. However, the 1,831 documented drug interactions mean you absolutely must check your medications before starting.
If you take blood pressure drugs, blood thinners, diabetes medications, thyroid hormones, HIV treatments, or any psychiatric or cardiac medication, run them through the checker on this page. Talk to your pharmacist or doctor, especially if you're pregnant, breastfeeding, or managing a chronic condition.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 17 of 20 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Aug 22, 2025.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Feel the Beet, straight from the product label.
| Brand | Live it Up |
|---|---|
| Net contents | 7.4 Ounce(s); 210 Gram(s) |
| Market status | On market |
| Date entered into DSLD | Aug 22, 2025 |
| DSLD ID | 339060 |
| Product type | Botanical With Nutrients |
| Supplement form | Powder |
| Dietary claims / uses | All Other |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
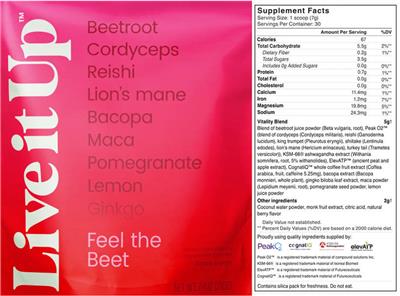
Supplement Facts
The label details for Feel the Beet by Live it Up, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Calories | 67 Calorie(s) | -- |
| Total Carbohydrates | 5.5 Gram(s) | 2% |
| Sodium | 24.3 mg | 1% |
| Calcium | 11.4 mg | 1% |
| Iron | 1.2 mg | 7% |
| Magnesium | 19.8 mg | 5% |
| Added Sugars | 0 Gram(s) | -- |
| Total Sugars | 3.5 Gram(s) | -- |
| Cholesterol | 0 Gram(s) | -- |
| Total Fat | 0 Gram(s) | -- |
| Dietary Fiber | 0.2 Gram(s) | 1% |
| Protein | 0.7 Gram(s) | 1% |
| Reishi | 0 NP | -- |
| King Trumpet | 0 NP | -- |
| Shiitake | 0 NP | -- |
| Lion's Mane | 0 NP | -- |
| Turkey Tail | 0 NP | -- |
| Maca, Powder | 0 NP | -- |
| Caffeine | 5.25 mg | -- |
| KSM-66 | 0 NP | -- |
| Cordyceps | 0 NP | -- |
| Lemon Juice, Powder | 0 NP | -- |
| Beet Root Juice, Powder | 0 NP | -- |
| Vitality Blend | 5 Gram(s) | -- |
| ElevATP | 0 NP | -- |
| Ginkgo biloba Leaf Extract | 0 NP | -- |
| Bacopa Whole Plant Extract | 0 NP | -- |
| CognatiQ | 0 NP | -- |
| Peak O2 | 0 NP | -- |
| Pomegranate, Powder | 0 NP | -- |
Other ingredients: Coconut Water, Powder, Monk Fruit Extract, Citric Acid, Berry Flavor, Natural
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
Beetroot Cordyceps Reishi Lion's Mane Bacopa Maca Pomegranate Lemon Ginkgo
Proudly using quality ingredients supplied by: Peak O2 CognatiQ KSM-66 Ashwaghanda elevATP
FDA Statement of Identity
Whole Food Dietary Supplement Powder
Brand IP Statement(s)
Peak 02 is a registered trademark material of compound solutions Inc. KSM-66 is a registered trademark material of Ixoreal Biomed ElevATP is a registered trademark material of Futureceuticals CognatiQ is a registered trademark material of Futureceuticals
Storage
Contains silica pack for freshness. Do not eat.
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Feel the Beet by Live it Up label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Feel the Beet by Live it Up
These are the 16 active ingredients this product is made of. Select any to open its full monograph.
Serving size7 Gram(s) Dosage formPowder Servings per container30 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Sodium
Interacts with205 drugs
Sodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets g...
Sodium monograph & interactionsCalcium
Interacts with168 drugs
Calcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet f...
Calcium monograph & interactionsIron
Interacts with80 drugs
Iron is an essential mineral your body needs to make hemoglobin and carry oxygen in the blood. Supplements are mainly useful for treating or preventin...
Iron monograph & interactionsMagnesium
Interacts with295 drugs
Magnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preven...
Magnesium monograph & interactionsDietary Fiber
Interacts with2,025 drugs
Black psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. I...
Dietary Fiber monograph & interactionsProtein
Vitality Blend
- › Maca, Powder
- › KSM-66
- › Lemon Juice, Powder
- › Beet Root Juice, Powder
- › ElevATP
- › Ginkgo biloba Leaf Extract
- › Bacopa Whole Plant Extract
- › CognatiQ
- › Peak O2
- › Pomegranate, Powder
Other (inactive) ingredients: Coconut Water, Powder, Monk Fruit Extract, Citric Acid, Berry Flavor, Natural. These complete the product’s ingredient list but are not active constituents.
Feel the Beet by Live it Up Drug Interactions
HelloPharmacist Interaction Report
Feel the Beet by Live it Up is a 19-ingredient powder with documented interactions affecting a broad range of medications.
The most serious interaction is with calcium and the HIV integrase inhibitor dolutegravir (Tivicay), which calcium can reduce by nearly 40%—a Major severity concern that may compromise viral suppression.
Read the full breakdown — every affected drug type, severity by severity
Moderate interactions span multiple medication categories. Sodium can reduce the effectiveness of blood pressure medications and alter lithium levels; calcium interacts with thyroid medications, certain antibiotics, and heart drugs; iron reduces absorption of several antibiotics, thyroid hormones, and other oral drugs; magnesium affects Parkinson's medications and bisphosphonates.
Caffeine at high doses interacts with stimulants like ephedrine (risk of serious cardiovascular effects) and can amplify effects of antipsychotics like clozapine. The herbal ingredients—reishi, ashwagandha (KSM-66), ginkgo, bacopa, and pomegranate—each carry Moderate interactions with blood pressure drugs, blood thinners, diabetes medications, and various enzyme-metabolized drugs.
Two ingredients we could not check for interactions are King Trumpet, Turkey Tail, ElevATP, and the blends Vitality Blend, CognatiQ, and Peak O2 (whose component ingredients are listed separately). Altogether, these interactions span 1,831 individual medications.
Check your exact medications with the search tool on this page before starting Feel the Beet.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Feel the Beet?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Feel the Beet interact with 2,356 drugs. Click any drug to see the details.
12 of the 16 ingredients in Feel the Beet interact with drugs. Each result below shows which ingredient is responsible. Dietary Fiber KSM-66 Ginkgo biloba Leaf Extract Bacopa Whole Plant Extract Pomegranate, Powder Beet Root Juice, Powder CognatiQ Magnesium Sodium Calcium Iron Lemon Juice, Powder
Acetaminophen, Chlorpheniramine, PhenylpropanolamineAlumadrine, Conex, Sinadrin Max Strength, Sinulin
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine interacts with Feel the Beet — through 8 ingredients. Tap an ingredient for the detail:
Ksm-66Cytochrome P450 3a4 (cyp3a4) Substrates, Serotonergic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ksm-66 + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionCognatiqPhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Read the full Cognatiq + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionCaffeinePhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionBacopa Whole Plant ExtractAnticholinergic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, concurrent use might decrease the effectiveness of both agents.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, OpiumHista-Derfule
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interacts with Feel the Beet — through 8 ingredients. Tap an ingredient for the detail:
Bacopa Whole Plant ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Anticholinergic Drugs +1 Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +3 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionGinkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionCognatiqStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionCaffeineStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Opium interactionAcetaminophen, Chlorpheniramine, Phenylpropanolamine, PhenyltoloxamineNorel Plus
How Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interacts with Feel the Beet — through 8 ingredients. Tap an ingredient for the detail:
CaffeinePhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionCognatiqStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionKsm-66Cytochrome P450 3a4 (cyp3a4) Substrates, Serotonergic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
Read the full Ksm-66 + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionBacopa Whole Plant ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Anticholinergic Drugs +1 Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionBeet Root Juice, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Phenylpropanolamine, Phenyltoloxamine interactionAcetaminophen, Chlorpheniramine, PseudoephedrineAlka-Seltzer PLUS Liquid Gels, Children's Tylenol Cold, Codimal, Comtrex, Extra Strength Tylenol Allergy Sinus, Lorsin +3 more
How Acetaminophen, Chlorpheniramine, Pseudoephedrine interacts with Feel the Beet — through 8 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticholinergic Drugs +1 Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionKsm-66Hepatotoxic Drugs, Serotonergic Drugs +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorpheniramine, Pseudoephedrine interactionAcetaminophen, ChlorzoxazoneAcetazone Forte, Extra Strength Tylenol Aches & Strains, Parafon Forte
How Acetaminophen, Chlorzoxazone interacts with Feel the Beet — through 6 ingredients. Tap an ingredient for the detail:
MagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Chlorzoxazone interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Chlorzoxazone interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Chlorzoxazone interactionKsm-66Hepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Chlorzoxazone interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Chlorzoxazone interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorzoxazone interactionAcetaminophen, Chlorzoxazone, CodeineAcetazone Forte C8, Parafon Forte C8
How Acetaminophen, Chlorzoxazone, Codeine interacts with Feel the Beet — through 8 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Chlorzoxazone, Codeine interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Chlorzoxazone, Codeine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Chlorzoxazone, Codeine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Chlorzoxazone, Codeine interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Chlorzoxazone, Codeine interactionPomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Chlorzoxazone, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Chlorzoxazone, Codeine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Chlorzoxazone, Codeine interactionAcetaminophen, CodeineTylenol No.3, Tylenol w/ Codeine
How Acetaminophen, Codeine interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ksm-66Hepatotoxic Drugs, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Codeine interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Codeine interactionPomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Codeine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Codeine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Codeine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Codeine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Codeine interactionAcetaminophen, Codeine, DoxylamineMersyndol
How Acetaminophen, Codeine, Doxylamine interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ksm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Codeine, Doxylamine interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Codeine, Doxylamine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticholinergic Drugs Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Codeine, Doxylamine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Codeine, Doxylamine interactionPomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Codeine, Doxylamine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Codeine, Doxylamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Codeine, Doxylamine interactionAcetaminophen, Codeine, MethocarbamolAcetaminophen, Codeine, Methocarbamol, Robaxacet 8
How Acetaminophen, Codeine, Methocarbamol interacts with Feel the Beet — through 8 ingredients. Tap an ingredient for the detail:
Pomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Codeine, Methocarbamol interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Codeine, Methocarbamol interactionKsm-66Cns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ksm-66 + Acetaminophen, Codeine, Methocarbamol interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Codeine, Methocarbamol interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Codeine, Methocarbamol interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Codeine, Methocarbamol interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Codeine, Methocarbamol interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Codeine, Methocarbamol interactionAcetaminophen, Dexbrompheniramine, PseudoephedrineSinadrin Plus
How Acetaminophen, Dexbrompheniramine, Pseudoephedrine interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Bacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dexbrompheniramine, Pseudoephedrine interactionAcetaminophen, DextromethorphanTylenol Cough Ex Strength
How Acetaminophen, Dextromethorphan interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Beet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dextromethorphan interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Dextromethorphan interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dextromethorphan interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Dextromethorphan interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dextromethorphan interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dextromethorphan interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dextromethorphan interactionAcetaminophen, Dextromethorphan, Doxylamine, PseudoephedrineVicks NyQuil
How Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interacts with Feel the Beet — through 9 ingredients. Tap an ingredient for the detail:
Ksm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Serotonergic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionPomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionBacopa Whole Plant ExtractAnticholinergic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, concurrent use might decrease the effectiveness of both agents.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dextromethorphan, Doxylamine, Pseudoephedrine interactionAcetaminophen, Dextromethorphan, Guaifenesin, PhenylephrineConar-A
How Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interacts with Feel the Beet — through 9 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionKsm-66Hepatotoxic Drugs, Serotonergic Drugs +2 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionBeet Root Juice, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylephrine interactionAcetaminophen, Dextromethorphan, Guaifenesin, PhenylpropanolamineAnatuss
How Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interacts with Feel the Beet — through 9 ingredients. Tap an ingredient for the detail:
Beet Root Juice, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionGinkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionPomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionCaffeineStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionCognatiqPhenylpropanolamine, Stimulant Drugs Moderate
Interaction Summary
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Read the full Cognatiq + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dextromethorphan, Guaifenesin, Phenylpropanolamine interactionAcetaminophen, Dextromethorphan, Guaifenesin, PseudoephedrineRobitussin Cold, Severe Cold, Suphedrine Cold/Cough
How Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interacts with Feel the Beet — through 9 ingredients. Tap an ingredient for the detail:
CognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionBeet Root Juice, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionBacopa Whole Plant ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dextromethorphan, Guaifenesin, Pseudoephedrine interactionAcetaminophen, Dextromethorphan, Phenylpropanolamine, PyrilamineTheracaps
How Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interacts with Feel the Beet — through 9 ingredients. Tap an ingredient for the detail:
Bacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticholinergic Drugs +1 Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionBeet Root Juice, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionGinkgo Biloba Leaf ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionCaffeineStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionCognatiqStimulant Drugs, Phenylpropanolamine Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dextromethorphan, Phenylpropanolamine, Pyrilamine interactionAcetaminophen, Dextromethorphan, PseudoephedrineAlka-Seltzer PLUS Flu Liquid Gels, Non Aspirin Cold Caps, Tylenol Cold, Tylenol Flu Daytime Ex Strength, Tylenol Flu Ex Strength
How Acetaminophen, Dextromethorphan, Pseudoephedrine interacts with Feel the Beet — through 9 ingredients. Tap an ingredient for the detail:
Pomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionBacopa Whole Plant ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Serotonergic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dextromethorphan, Pseudoephedrine interactionAcetaminophen, Dichloralantipyrine, IsomethepteneAmidrine, Midchlor, Migquin, Migratine
How Acetaminophen, Dichloralantipyrine, Isometheptene interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ksm-66Hepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Dichloralantipyrine, Isometheptene interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dichloralantipyrine, Isometheptene interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dichloralantipyrine, Isometheptene interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dichloralantipyrine, Isometheptene interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dichloralantipyrine, Isometheptene interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dichloralantipyrine, Isometheptene interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dichloralantipyrine, Isometheptene interactionAcetaminophen, Dichloralphenazone, IsomethepteneMidrin
How Acetaminophen, Dichloralphenazone, Isometheptene interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
CaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dichloralphenazone, Isometheptene interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dichloralphenazone, Isometheptene interactionKsm-66Hepatotoxic Drugs, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Dichloralphenazone, Isometheptene interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dichloralphenazone, Isometheptene interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dichloralphenazone, Isometheptene interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dichloralphenazone, Isometheptene interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dichloralphenazone, Isometheptene interactionAcetaminophen, Dichlorophenazone, IsometheptaneIsocom
How Acetaminophen, Dichlorophenazone, Isometheptane interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ksm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Dichlorophenazone, Isometheptane interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Dichlorophenazone, Isometheptane interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Dichlorophenazone, Isometheptane interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Dichlorophenazone, Isometheptane interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Dichlorophenazone, Isometheptane interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Dichlorophenazone, Isometheptane interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Dichlorophenazone, Isometheptane interactionAcetaminophen, DiphenhydramineTylenol PM, Tylenol PM Ex Strength
How Acetaminophen, Diphenhydramine interacts with Feel the Beet — through 5 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Diphenhydramine interactionKsm-66Cns Depressants, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Read the full Ksm-66 + Acetaminophen, Diphenhydramine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticholinergic Drugs Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Diphenhydramine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Diphenhydramine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Diphenhydramine interactionAcetaminophen, Diphenhydramine, PseudoephedrineChildren's Tylenol Allergy, Cold Control, Contac Night Allergy Relief
How Acetaminophen, Diphenhydramine, Pseudoephedrine interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionKsm-66Hepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionBacopa Whole Plant ExtractAnticholinergic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, concurrent use might decrease the effectiveness of both agents.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Diphenhydramine, Pseudoephedrine interactionAcetaminophen, Doxylamine, PseudoephedrineEx Strength Tylenol Sinus Nighttime
How Acetaminophen, Doxylamine, Pseudoephedrine interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ksm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Doxylamine, Pseudoephedrine interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Doxylamine, Pseudoephedrine interactionCognatiqStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Cognatiq + Acetaminophen, Doxylamine, Pseudoephedrine interactionCaffeineStimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase stimulant adverse effects.
Read the full Caffeine + Acetaminophen, Doxylamine, Pseudoephedrine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticholinergic Drugs Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Doxylamine, Pseudoephedrine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Doxylamine, Pseudoephedrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Doxylamine, Pseudoephedrine interactionAcetaminophen, HydrocodoneAnexsia, Anodynos DHC, Azdone, Co-Gesic, Doucet, Lorcet +9 more
How Acetaminophen, Hydrocodone interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
ShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Hydrocodone interactionBacopa Whole Plant ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Hydrocodone interactionGinkgo Biloba Leaf ExtractSeizure Threshold Lowering Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Hydrocodone interactionBeet Root Juice, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, beet might increase the levels of CYP3A4 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Hydrocodone interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Hydrocodone interactionPomegranate, PowderCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Read the full Pomegranate, Powder + Acetaminophen, Hydrocodone interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Hydrocodone interactionAcetaminophen, IbuprofenCombogesic
How Acetaminophen, Ibuprofen interacts with Feel the Beet — through 12 ingredients. Tap an ingredient for the detail:
CordycepsAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, cordyceps may increase the risk of bleeding when used with antiplatelet or anticoagulant drugs.
Read the full Cordyceps + Acetaminophen, Ibuprofen interactionGinkgo Biloba Leaf ExtractAnticoagulant/antiplatelet Drugs, Ibuprofen (advil, Others) +2 Moderate
Interaction Summary
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Ibuprofen interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2c9 (cyp2c9) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Ibuprofen interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Ibuprofen interactionReishiAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, high doses of reishi mushroom might increase the risk of bleeding.
Read the full Reishi + Acetaminophen, Ibuprofen interactionCaffeineAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, caffeine may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Caffeine + Acetaminophen, Ibuprofen interactionLion's ManeAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, lion's mane mushroom may increase the risk of bleeding when used with anticoagulant/antiplatelet drugs.
Read the full Lion's Mane + Acetaminophen, Ibuprofen interactionCognatiqAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, coffee may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Cognatiq + Acetaminophen, Ibuprofen interactionPomegranate, PowderCytochrome P450 2c9 (cyp2c9) Substrates Minor
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2C9.
Read the full Pomegranate, Powder + Acetaminophen, Ibuprofen interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Ibuprofen interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Ibuprofen interactionMagnesiumAnticoagulant/antiplatelet Drugs Minor
Interaction Summary
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
Read the full Magnesium + Acetaminophen, Ibuprofen interactionAcetaminophen, MeperidineDemerol APAP
How Acetaminophen, Meperidine interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
ShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Meperidine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Meperidine interactionPomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Meperidine interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Meperidine interactionKsm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +2 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Meperidine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Meperidine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Meperidine interactionAcetaminophen, MethocarbamolRobaxacet
How Acetaminophen, Methocarbamol interacts with Feel the Beet — through 6 ingredients. Tap an ingredient for the detail:
Ksm-66Hepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Methocarbamol interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Methocarbamol interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Methocarbamol interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Methocarbamol interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Methocarbamol interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Methocarbamol interactionAcetaminophen, OrphenadrineOrfenagesic
How Acetaminophen, Orphenadrine interacts with Feel the Beet — through 6 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Orphenadrine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Orphenadrine interactionKsm-66Hepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Orphenadrine interactionMagnesiumSkeletal Muscle Relaxants Moderate
Interaction Summary
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Read the full Magnesium + Acetaminophen, Orphenadrine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Orphenadrine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Orphenadrine interactionAcetaminophen, OxycodonePercocet, Roxicet, Tylox, Xartemis XR
How Acetaminophen, Oxycodone interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ksm-66Cytochrome P450 1a2 (cyp1a2) Substrates, Cns Depressants +1 Moderate
Interaction Summary
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Ksm-66 + Acetaminophen, Oxycodone interactionShiitakeCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, shiitake mushroom might decrease levels of drugs metabolized by CYP2D6.
Read the full Shiitake + Acetaminophen, Oxycodone interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Oxycodone interactionGinkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Seizure Threshold Lowering Drugs Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Oxycodone interactionPomegranate, PowderCytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
Read the full Pomegranate, Powder + Acetaminophen, Oxycodone interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Oxycodone interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Oxycodone interactionAcetaminophen, Pamabrom, PyrilamineMidol Max Strength PMS, Pamprin, Pamprin ES
How Acetaminophen, Pamabrom, Pyrilamine interacts with Feel the Beet — through 7 ingredients. Tap an ingredient for the detail:
Ginkgo Biloba Leaf ExtractCytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Read the full Ginkgo Biloba Leaf Extract + Acetaminophen, Pamabrom, Pyrilamine interactionKsm-66Hepatotoxic Drugs, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Read the full Ksm-66 + Acetaminophen, Pamabrom, Pyrilamine interactionCaffeineDiuretic Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, using caffeine with diuretic drugs might increase the risk of hypokalemia.
Read the full Caffeine + Acetaminophen, Pamabrom, Pyrilamine interactionBacopa Whole Plant ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticholinergic Drugs Moderate
Interaction Summary
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Read the full Bacopa Whole Plant Extract + Acetaminophen, Pamabrom, Pyrilamine interactionCognatiqDiuretic Drugs, Stimulant Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of hypokalemia.
Read the full Cognatiq + Acetaminophen, Pamabrom, Pyrilamine interactionBeet Root Juice, PowderCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
Read the full Beet Root Juice, Powder + Acetaminophen, Pamabrom, Pyrilamine interactionDietary FiberOral Drugs Minor
Interaction Summary
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Read the full Dietary Fiber + Acetaminophen, Pamabrom, Pyrilamine interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Feel the Beet with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Dietary Fiber
Carbamazepine (Tegretol)
Theoretically, black psyllium might reduce the effects of carbamazepine and increase the risk for convulsions.
Theoretically, black psyllium might reduce carbamazepine absorption. A preliminary study using blond psyllium reported decreased carbamazepine bioavailability due to binding of the drug to psyllium, as well as reduction of available fluid in the gut for dissolution of the drug. This interaction may also occur with black psyllium.
Lithium
Theoretically, taking black psyllium at the same time as lithium might reduce lithium absorption.
The fiber in black psyllium might reduce lithium absorption and plasma levels. Some case reports describe a reduction in plasma lithium levels with concomitant administration of blond psyllium. This was reversed when psyllium was stopped. This interaction may also occur with black psyllium.
Metformin (Glucophage)
Theoretically, black psyllium might increase the therapeutic and adverse effects of metformin.
Animal research shows that concurrent consumption of blond psyllium with metformin slows and increases the absorption of metformin. This interaction may also occur with black psyllium. To avoid changes in absorption, take psyllium 30-60 minutes after metformin.
Olanzapine (Zyprexa)
Theoretically, taking black psyllium at the same time as olanzapine might reduce olanzapine absorption.
The fiber in black psyllium might decrease the absorption of olanzapine. A single case report describes a reduction in the effectiveness of olanzapine when it was concomitantly administered with an unspecified type of psyllium 3 grams orally twice daily. This effect was reversed when psyllium was stopped.
Digoxin (Lanoxin)
Theoretically, taking black psyllium at the same time as digoxin might reduce digoxin absorption and decrease digoxin levels.
Psyllium might bind digoxin in the gut. However, some clinical evidence suggests that psyllium does not impact digoxin absorption.
Ethinyl Estradiol
Theoretically, taking black psyllium at the same time as ethinyl estradiol might alter levels of estradiol.
Concurrent use of blond psyllium with ethinyl estradiol results in a slight increase in the extent of ethinyl estradiol absorption and a slower rate of absorption. This is unlikely to be clinically significant.
Oral Drugs
Theoretically, psyllium might increase, decrease, or have no effect on the absorption of oral drugs.
Psyllium seems to have variable effects on drug absorption. To avoid changes in absorption, take psyllium 30-60 minutes after oral medications. Animal research shows that blond psyllium delays and increases the absorption of metformin and ethinyl estradiol. Case reports and animal research suggest that blond psyllium might reduce absorption of lithium, digoxin, olanzapine, and carbamazepine. Finally, some pharmacokinetic studies show that psyllium does not affect the absorption of levothyroxine or warfarin. Although many of these studies evaluated blond psyllium, the fiber content in black psyllium may have similar effects.
KSM-66
Antidiabetes Drugs
Theoretically, taking ashwagandha with antidiabetes drugs might increase the risk of hypoglycemia.
There is preliminary clinical evidence suggesting that ashwagandha might lower blood glucose levels. Theoretically, ashwagandha might have additive effects when used with antidiabetes drugs and increase the risk of hypoglycemia.
Antihypertensive Drugs
Theoretically, taking ashwagandha with antihypertensive drugs might increase the risk of hypotension.
Animal research suggests that ashwagandha might lower systolic and diastolic blood pressure. Theoretically, ashwagandha might have additive effects when used with antihypertensive drugs and increase the risk of hypotension.
Benzodiazepines
Theoretically, taking ashwagandha might increase the sedative effects of benzodiazepines.
There is preliminary evidence that ashwagandha might have an additive effect with diazepam (Valium) and clonazepam (Klonopin). This may also occur with other benzodiazepines.
Cns Depressants
Theoretically, taking ashwagandha might increase the sedative effects of CNS depressants.
Ashwagandha seems to have sedative effects. Theoretically, this may potentiate the effects of barbiturates, other sedatives, and anxiolytics.
Hepatotoxic Drugs
Theoretically, taking ashwagandha with hepatotoxic drugs might increase the risk of liver damage.
Ashwagandha has been linked to cases of acute hepatitis, liver failure, hepatic encephalopathy, autoimmune hepatitis, the need for liver transplantation, and death due to liver failure.
Immunosuppressants
Theoretically, taking ashwagandha might decrease the effects of immunosuppressants.
Ashwagandha has demonstrated immunostimulant effects in humans. Animal research has shown that ashwagandha can attenuate the immunosuppression caused by cyclophosphamide.
Thyroid Hormone
Ashwagandha might increase the effects and adverse effects of thyroid hormone.
Concomitant use of ashwagandha with thyroid hormones may cause additive therapeutic and adverse effects. Preliminary clinical research and animal studies suggest that ashwagandha boosts thyroid hormone synthesis and secretion. In one clinical study, ashwagandha increased triiodothyronine (T3) and thyroxine (T4) levels by 41.5% and 19.6%, respectively, and reduced serum TSH levels by 17.4% from baseline in adults with subclinical hypothyroidism.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research shows that ashwagandha extract induces CYP1A2 enzymes.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ashwagandha might decrease the levels and clinical effects of CYP3A4 substrates.
In vitro research shows that ashwagandha extract induces CYP3A4 enzymes.
Serotonergic Drugs
Some animal studies have reported that ashwagandha can enhance serotonergic transmission by altering certain serotonin (5-HT) receptors. However, there is no evidence to suggest that ashwagandha increases the risk of serotonin-related effects, and there have been no published case reports of serotonin syndrome when combined with other serotonergic drugs. Nevertheless, due to the lack of extensive studies on the matter and the fact that ashwagandha appears to affect serotonergic pathways, it would be prudent to exercise caution when combining it with drugs that affect serotonin. [References: - Effects of Withania somnifera (Ashwaga ndha) on Stress and the Stress-Related Neuropsychiatric Disorders Anxiety, Depression, and Insomnia. Curr Neuropharmacol. 2021 Sep 14; 19: 1468–1495. - A Prospective, Randomized Double-Blind, Placebo-Controlled Study of Safety and Efficacy of a High-Concentration Full-Spectrum Extract of Ashwagandha Root in Reducing Stress and Anxiety in Adults. https://www.ncbi.nlm.nih.gov/pmc/articles/PMC3573577/]
Ginkgo biloba Leaf Extract
Talinolol
Taking ginkgo with talinolol seems to increase blood levels of talinolol.
There is some evidence that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of talinolol by 36% in healthy male individuals. However, single doses of ginkgo do not seem to affect talinolol pharmacokinetics.
Alprazolam (Xanax)
Theoretically, ginkgo might decrease the levels and clinical effects of alprazolam.
In clinical research, ginkgo extract (Ginkgold) 120 mg twice daily seems to decrease alprazolam levels by about 17%. However, ginkgo does not appear to decrease the elimination half-life of alprazolam. This suggests that ginkgo is more likely to decrease absorption of alprazolam rather than induce hepatic metabolism of alprazolam.
Anticoagulant/Antiplatelet Drugs
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin. Theoretically, ginkgo might increase the risk of bleeding if used with other anticoagulant or antiplatelet drugs.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. However, population and clinical studies have produced mixed results. Some evidence shows that short-term use of ginkgo leaf does not significantly reduce platelet aggregation and blood clotting. A study in healthy males who took a specific ginkgo leaf extract (EGb 761) 160 mg twice daily for 7 days found no change in prothrombin time. An analysis of a large medical record database suggests that ginkgo increases the risk of a bleeding adverse event by 38% when taken concurrently with warfarin. It has been suggested that ginkgo has to be taken for at least 2-3 weeks to have a significant effect on platelet aggregation. However, a meta-analysis of 18 studies using standardized ginkgo extracts, 80-480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. In addition, a single dose of ginkgo plus clopidogrel or ticlopidine does not seem to significantly increase bleeding time or platelet aggregation. Also, taking ginkgo leaf extract daily for 8 days in conjunction with rivaroxaban does not affect anti-factor Xa activity; however, this study did not evaluate bleeding time.
Anticonvulsants
Theoretically, ginkgo might reduce the effectiveness of anticonvulsants.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Antidiabetes Drugs
Theoretically, taking ginkgo with antidiabetes drugs might alter the response to antidiabetes drugs.
Ginkgo leaf extract seems to alter insulin secretion and metabolism, and might affect blood glucose levels in people with type 2 diabetes. The effect of ginkgo seems to differ depending on the insulin and treatment status of the patient. In diet-controlled diabetes patients with hyperinsulinemia, taking ginkgo does not seem to significantly affect insulin or blood glucose levels. In patients with hyperinsulinemia who are treated with oral hypoglycemic agents, taking ginkgo seems to decrease insulin levels and increase blood glucose following an oral glucose tolerance test. Researchers speculate that this could be due to ginkgo-enhanced hepatic metabolism of insulin. In patients with pancreatic exhaustion, taking ginkgo seems to stimulate pancreatic beta-cells, resulting in increased insulin and C-peptide levels, but with no significant change in blood glucose levels in response to an oral glucose tolerance test.
Atorvastatin (Lipitor)
Theoretically, ginkgo might decrease the levels and clinical effects of atorvastatin.
In humans, intake of ginkgo extract appears to increase atorvastatin clearance, reducing the area under the curve of atorvastatin by 10% to 14% and the maximum concentration by 29%. However, this interaction does not appear to affect cholesterol synthesis and absorption. Further, a model in rats with hyperlipidemia suggests that administering ginkgo extract does not impact blood levels of atorvastatin and leads to lower total cholesterol, low-density lipoprotein cholesterol, and triglycerides when compared with rats given atorvastatin alone.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP1A2.
Laboratory research suggests that ginkgo leaf extract can mildly inhibit CYP1A2 enzymes. However, clinical research suggests ginkgo might not affect CYP1A2. Until more is known, use ginkgo cautiously in patients taking drugs metabolized by these enzymes.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP2C19.
Some clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce CYP2C19 enzymes and potentially decrease levels of drugs metabolized by these enzymes. However, other clinical research shows that taking ginkgo 120 mg twice daily for 12 days has no effect on levels of drugs metabolized by CYP2C19.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, ginkgo might increase levels of drugs metabolized by CYP2C9.
In vitro, a specific standardized extract of ginkgo leaf (EGb 761) inhibits CYP2C9 activity . The terpenoid (ginkgolides) and flavonoid (quercetin, kaempferol, etc.) constituents seem to be responsible for this effect. Most ginkgo extracts contain some amount of these constituents. Therefore, other ginkgo leaf extracts might also inhibit the CYP2C9 enzyme. However, clinical research suggests that ginkgo might not have a significant effect on CYP2C9 in humans. Ginkgo does not seem to significantly affect the pharmacokinetics of CYP2C9 substrates diclofenac or tolbutamide.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, ginkgo might decrease levels of drugs metabolized by CYP3A4.
There is conflicting evidence about whether ginkgo induces or inhibits CYP3A4. Ginkgo does not appear to affect hepatic CYP3A4. However, it is not known if ginkgo affects intestinal CYP3A4. Preliminary clinical research suggests that taking ginkgo does not significantly affect levels of donepezil, lopinavir, or ritonavir, which are all CYP3A4 substrates. Other clinical research also suggests ginkgo does not significantly affect CYP3A4 activity. However, there are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4).
Efavirenz (Sustiva)
Theoretically, ginkgo might decrease the levels and clinical effects of efavirenz.
There are two case reports of decreased efavirenz concentrations and increased viral load in patients taking ginkgo. In one case, an HIV-positive male experienced over a 50% decrease in efavirenz levels over the course of 14 months while taking ginkgo extract. HIV-1 RNA copies also increased substantially, from less than 50 to more than 1500. It is suspected that terpenoids from the ginkgo extract reduced drug levels by inducing cytochrome P450 3A4 (CYP3A4). In another case report, a patient stable on antiviral therapy including efavirenz for 10 years, had an increase in viral load from <50 copies/mL to 1350 copies/mL after 2 months of taking a combination of supplements including ginkgo. After stopping ginkgo, the viral load was again controlled with the same antiviral therapy regimen.
Ibuprofen (Advil, Others)
Theoretically, ginkgo might increase the risk of bleeding when used with ibuprofen.
Ginkgo might have antiplatelet effects and has been associated with several case reports of spontaneous bleeding. In one case, a 71-year-old male had taken a specific ginkgo extract (Gingium, Biocur) 40 mg twice daily for 2.5 years. About 4 weeks after starting ibuprofen 600 mg daily he experienced a fatal intracerebral hemorrhage. However, the antiplatelet effects of ginkgo have been questioned. A meta-analysis and other studies have not found a significant antiplatelet effect with standardized ginkgo extracts, 80 mg to 480 mg taken daily for up to 32 weeks.
P-Glycoprotein Substrates
Theoretically, taking ginkgo with P-glycoprotein substrates might increase the levels and adverse effects of these substrates.
A small clinical study in healthy volunteers shows that using ginkgo leaf extract 120 mg orally three times daily for 14 days can increase levels of the P-glycoprotein substrate, talinolol, by 36% in healthy male individuals. However, single doses of ginkgo do not have the same effect.
Risperidone (Risperdal)
Theoretically, taking ginkgo with risperidone might increase the levels and adverse effects of risperidone.
A single case of priapism has been reported for a 26-year-old male with schizophrenia who used risperidone 3 mg daily along with ginkgo extract 160 mg daily. Risperidone is metabolized by cytochrome P450 (CYP) 2D6 and CYP3A4. CYP3A4 activity might be affected by ginkgo. Theoretically, ginkgo may inhibit the metabolism of risperidone and increase the risk of adverse effects.
Rosiglitazone (Avandia)
Theoretically, ginkgo might decrease the levels and clinical effects of rosiglitazone.
Animal research shows that ginkgo leaf extract orally 100 or 200 mg/kg daily for 10 days alters the pharmacodynamics of rosiglitazone in a dose-dependent manner. The 100 mg/kg and 200 mg/kg doses reduce the area under the concentration time curve (AUC) of rosiglitazone by 39% and 52%, respectively, and the half-life by 28% and 39%, respectively. It is hypothesized that these changes may be due to induction of cytochrome P450 2C8 by ginkgo.
Seizure Threshold Lowering Drugs
Theoretically, taking ginkgo with drugs that lower the seizure threshold might increase the risk for convulsions.
Ginkgo seeds contain ginkgotoxin. Large amounts of ginkgotoxin can cause neurotoxicity and seizure. Ginkgotoxin is present in much larger amounts in ginkgo seeds than leaves. Ginkgo leaf extract contains trace amounts of ginkgotoxin. The amount of ginkgotoxin in ginkgo leaf and leaf extract seems unlikely to cause toxicity. However, there are anecdotal reports of seizure occurring after use of ginkgo leaf both in patients without a history of seizure disorder and in those with previously well-controlled epilepsy.
Simvastatin (Zocor)
Theoretically, ginkgo might decrease the levels and clinical effects of simvastatin.
Clinical research shows that taking ginkgo extract can reduce the area under the curve and maximum concentration of simvastatin by 32% to 39%. However, ginkgo extract does not seem to affect the cholesterol-lowering ability of simvastatin.
Sofosbuvir (Sovaldi)
Theoretically, ginkgo might increase the levels and clinical effects of sofosbuvir.
Animal research in rats shows that giving a ginkgo extract 25 mg/kg orally daily for 14 days increases the area under the concentration time curve (AUC) after a single sofosbuvir dose of 40 mg/kg by 11%, increases the half-life by 60%, and increases the plasma concentration at 4 hours by 38%. This interaction appears to be related to the inhibition of intestinal P-glycoprotein by ginkgo.
Tacrolimus (Prograf)
Theoretically, ginkgo might increase the blood levels of tacrolimus.
In vitro evidence suggests that certain biflavonoids in ginkgo leaves (i.e. amentoflavone, ginkgetin, bilobetin) may inhibit the metabolism of tacrolimus by up to 50%. This interaction appears to be time-dependent and due to inhibition of cytochrome P450 (CYP) 3A4 by these bioflavonoids. In rats given tacrolimus 1 mg/kg orally, amentoflavone was shown to increase the area under the concentration time curve (AUC) of tacrolimus by 3.8-fold.
Trazodone (Desyrel)
Theoretically, ginkgo might increase the levels and clinical effects of trazodone.
In a case report, an Alzheimer patient taking trazodone 20 mg twice daily and ginkgo leaf extract 80 mg twice daily for four doses became comatose. The coma was reversed by administration of flumazenil (Romazicon). Coma might have been induced by excessive GABA-ergic activity. Ginkgo flavonoids are thought to have GABA-ergic activity and act directly on benzodiazepine receptors. Ginkgo might also increase metabolism of trazodone to active GABA-ergic metabolites, possibly by inducing cytochrome P450 3A4 (CYP3A4) metabolism.
Warfarin (Coumadin)
Ginkgo has been shown to increase the risk of bleeding in some people when taken with warfarin.
Several pharmacodynamic studies suggest that ginkgo inhibits platelet aggregation. It is thought that the ginkgo constituent, ginkgolide B, displaces platelet-activating factor (PAF) from its binding sites, decreasing blood coagulation. Several case reports have documented serious bleeding events in patients taking ginkgo. Information from a medical database suggests that when taken concurrently with warfarin, ginkgo increases the risk of a bleeding adverse event by 38%. There is also some evidence that ginkgo leaf extract can inhibit cytochrome P450 2C9, an enzyme that metabolizes warfarin. This could result in increased warfarin levels. However, population and clinical research has produced mixed results. Clinical research in healthy people suggests that ginkgo has no effect on INR, or the pharmacokinetics or pharmacodynamics of warfarin. A meta-analysis of 18 studies using standardized ginkgo extracts, 80 mg to 480 mg daily for up to 32 weeks, did not find a significant effect on platelet aggregation, fibrinogen concentration, or PT/aPTT. There is also some preliminary clinical research that suggests ginkgo might not significantly increase the effects of warfarin in patients that have a stable INR.
Nifedipine (Procardia)
Theoretically, taking ginkgo with oral, but not intravenous, nifedipine might increase levels and adverse effects of nifedipine.
Animal research and some clinical evidence suggests that taking ginkgo leaf extract orally in combination with oral nifedipine might increase nifedipine levels and cause increased side effects, such as headaches, dizziness, and hot flushes. However, taking ginkgo orally does not seem to affect the pharmacokinetics of intravenous nifedipine.
Omeprazole (Prilosec)
Theoretically, taking ginkgo with omeprazole might decrease the levels and clinical effects of omeprazole.
Clinical research shows that a specific ginkgo leaf extract (Remembrance, Herbs Product LTD) 140 mg twice daily can induce cytochrome P450 (CYP) 2C19 enzymes and decrease levels of omeprazole by about 27% to 42%.
Bacopa Whole Plant Extract
Anticholinergic Drugs
Theoretically, concurrent use might decrease the effectiveness of both agents.
Bacopa seems to inhibit acetylcholinesterase and might increase acetylcholine levels, which could counteract the effects of anticholinergic drugs. Similarly, anticholinergic drugs might counteract the cholinergic effects of bacopa.
Cevimeline (Evoxac)
Theoretically, bacopa might increase the effects and adverse effects of cevimeline.
In one case, a 58-year-old female taking cevimeline long-term for Sjogren syndrome experienced hyperhidrosis, malaise, nausea, and tachycardia shortly after taking a single dose of bacopa. Symptoms resolved after two days. Cevimeline is metabolized by cytochrome P450 (CYP) 2D6 and CYP3A4, and researchers theorize that bacopa may have inhibited these isoenzymes. However, it is unclear if bacopa causes clinically significant inhibition of either CYP2D6 or CYP3A4.
Cholinergic Drugs
Theoretically, concurrent use of bacopa with other cholinergic drugs might have additive effects.
Bacopa seems to inhibit acetylcholinesterase and might increase acetylcholine levels. Theoretically, this could result in additive cholinergic effects when used with cholinergic drugs.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP1A2 substrates.
Research on the effects of bacopa extracts on CYP1A2 enzymes is conflicting. Some in vitro evidence shows that bacopa extract can moderately and non-competitively inhibit CYP1A2, while other in vitro evidence suggests that any effect is unlikely to be clinically significant.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP2C19 substrates.
In vitro evidence suggests that bacopa extract can moderately and non-competitively inhibit CYP2C19 enzymes. It is not known whether this is clinically significant.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP2C9 substrates.
Research on the effect of bacopa extracts on CYP2C9 enzymes is conflicting. Some in vitro evidence suggests that bacopa extract can moderately and non-competitively inhibit CYP2C9, while other in vitro evidence suggests that any effect is unlikely to be clinically significant.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, bacopa might increase the levels and adverse effects of CYP3A4 substrates.
Research on the effects of bacopa extracts on CYP3A4 enzymes is conflicting. Some in vitro evidence suggests that bacopa extract can moderately and competitively inhibit CYP3A4, while other in vitro evidence suggests that any effect is unlikely to be clinically significant.
Thyroid Hormone
Theoretically, bacopa might have additive effects when used with thyroid hormone.
Animal research suggests that bacopa increases thyroxine (T4) levels in mice by about 40%.
Pomegranate, Powder
Ace Inhibitors (Aceis)
Theoretically, taking pomegranate with ACEIs might increase the risk of adverse effects.
Pomegranate juice is thought to have ACE inhibitor-like effects.
Antihypertensive Drugs
Theoretically, taking pomegranate with antihypertensive drugs might increase the risk of hypotension.
Consuming pomegranate juice can modestly lower blood pressure.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2D6.
In vitro, pomegranate juice inhibits CYP2D6. However, the clinical significance of this potential interaction in humans is not known.
Rosuvastatin (Crestor)
Theoretically, taking pomegranate with rosuvastatin might increase the risk of adverse effects.
In one case, a patient taking rosuvastatin 5 mg every other day in combination with ezetimibe 10 mg daily developed rhabdomyolysis after drinking pomegranate juice 200 mL twice weekly for 3 weeks. This patient had a history of elevated creatine kinase levels while not receiving any statin treatment. This suggests a possible underlying myopathy and predisposition to rhabdomyolysis.
Warfarin (Coumadin)
Theoretically, pomegranate might increase warfarin levels and increase the risk of bleeding. Also, discontinuing regular consumption of pomegranate juice might decrease warfarin levels.
In one case report, a patient had a stable, therapeutic bleeding time, as measured by international normalized ratio (INR), while taking warfarin in combination with pomegranate juice 2-3 times per week. The patient became subtherapeutic within about 10 days after discontinuing pomegranate juice, which required a warfarin dose increase. In another case report, a patient with a stable INR for over one year presented with an INR of 14. The patient noted no changes to medications or diet but did report consuming around 3 liters of pomegranate juice over the previous week. The patient's INR stabilized upon moderation of pomegranate juice consumption. The mechanism of this potential interaction is unclear.
Carbamazepine (Tegretol)
Theoretically, taking pomegranate with carbamazepine might increase the risk of adverse effects, although research suggests this interaction is unlikely to be clinically significant.
Animal research shows that pomegranate juice may inhibit cytochrome P450 3A4 (CYP3A4) metabolism of carbamazepine and increase levels of carbamazepine by 1.5 times without prolonging the elimination half-life. This suggests that pomegranate juice inhibits intestinal CYP3A4, but might not inhibit hepatic CYP3A4. However, some human research suggests that pomegranate does not significantly inhibit CYP3A4 drug metabolism in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, pomegranate might increase levels of drugs metabolized by CYP2C9.
Some animal and in vitro research shows that pomegranate juice inhibits intestinal, but not hepatic, CYP2C9 isoenzyme activity. However, clinical research shows that neither pomegranate juice nor pomegranate extract have a significant effect on CYP2C9 activity in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, pomegranate might increase levels of drugs metabolized by CYP3A4, but most research suggests this interaction is unlikely to be clinically significant.
Pomegranate contains several polyphenols that have individually been shown to inhibit CYP3A4. However, there is contradictory evidence about the effect of whole pomegranate juice on CYP3A4 activity. In vitro, pomegranate juice significantly inhibits the CYP3A4 enzyme, with comparable inhibition to grapefruit juice. In an animal model, pomegranate juice inhibits CYP3A4 metabolism of carbamazepine and increases levels of carbamazepine by 1.5 times; however, in human volunteers, drinking a single glass of pomegranate juice 240 mL or taking 200 mL daily for 2 weeks does not significantly affect levels of the CYP3A4 substrate midazolam after oral or intravenous administration. Another study in healthy volunteers shows that consuming pomegranate juice 300 mL three times daily for three days also does not significantly affect levels of simvastatin, a CYP3A4 substrate This suggests that pomegranate is unlikely to significantly affect levels of CYP3A4 substrates in humans.
Tolbutamide (Orinase)
Theoretically, pomegranate might increase levels of tolbutamide, although research suggests this interaction is unlikely to be clinically significant.
Animal research shows that pomegranate juice inhibits the cytochrome P450 2C9 (CYP2C9) metabolism of tolbutamide. Pomegranate juice increased tolbutamide levels by 1.2 times without prolonging the elimination half-life. This suggests that pomegranate juice inhibits intestinal CYP2C9, but might not inhibit hepatic CYP2C9. Despite this evidence, clinical research shows that neither pomegranate juice nor pomegranate extract have a significant effect on CYP2C9 activity in humans. This interaction does not appear to be clinically significant in humans.
Beet Root Juice, Powder
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, beet might increase the levels of CYP3A4 substrates.
In vitro research suggests that betanin, the major pigment in beet, competitively inhibits CYP3A4 in a dose-dependent manner similarly to strong CYP3A4 inhibitor ketoconazole.
Antihypertensive Drugs
Beet and beetroot contain nitrates, which can cause vasodilation, potentially leading to lower blood pressure. However, a study published in the European Journal of Clinical Nutrition using concentrated beetroot juice found no significant impact on blood pressure or heart rate in different age groups. Other small clinical studies suggest that while beet consumption might transiently lower blood pressure due to vessel dilation, there's no consistent evidence of a lasting effect. Overall, the theoretical risk of reduced blood pressure due to beet's nitrate content exists, but studies generally indicate a low and temporary impact rather than a sustained decrease.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, beet might decrease the levels and clinical effects of CYP1A2 substrates.
In vitro research suggests that beet induces CYP1A2 enzymes.
CognatiQ
Ephedrine
Theoretically, concomitant use might increase the risk of stimulant adverse effects.
Coffee contains caffeine. There is evidence that using ephedrine with caffeine might increase the risk of serious life-threatening or debilitating adverse effects such as hypertension, myocardial infarction, stroke, seizures, and death. Tell patients to avoid taking caffeine with ephedrine and other stimulants.
Adenosine (Adenocard)
Theoretically, coffee might decrease the vasodilatory effects of adenosine and interfere with its use prior to stress testing.
Coffee contains caffeine. Caffeine is a competitive inhibitor of adenosine at the cellular level. However, caffeine does not seem to affect supplemental adenosine because high interstitial levels of adenosine overcome the antagonistic effects of caffeine. It is recommended that methylxanthines such as caffeine, as well as methylxanthine-containing products, be stopped 24 hours prior to pharmacological stress tests. However, methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Alendronate (Fosamax)
Coffee reduces alendronate bioavailability.
Separate coffee ingestion and alendronate administration by two hours. Coffee reduces alendronate bioavailability by 60%.
Anticoagulant/Antiplatelet Drugs
Theoretically, coffee may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Coffee contains caffeine. Caffeine is reported to have antiplatelet activity. Theoretically, the caffeine in coffee might increase the risk of bleeding when used concomitantly with these agents. However, this interaction has not been reported in humans. There is some evidence that caffeinated coffee might increase the fibrinolytic activity in blood.
Beta-Adrenergic Agonists
Theoretically, concomitant use of large amounts of coffee might increase cardiac inotropic effects of beta-agonists.
Coffee contains caffeine. Caffeine can increase cardiac inotropic effects of beta-agonists.
Cimetidine (Tagamet)
Theoretically, cimetidine might increase the effects and adverse effects of caffeine in coffee.
Coffee contains caffeine. Cimetidine can reduce caffeine clearance by 31% to 42%.
Clozapine (Clozaril)
Theoretically, coffee might increase the levels and adverse effects of clozapine and acutely exacerbate psychotic symptoms.
Coffee contains caffeine. Caffeine can increase the effects and toxicity of clozapine. Caffeine doses of 400-1000 mg daily inhibit clozapine metabolism. Clozapine is metabolized by cytochrome P450 1A2 (CYP1A2). Researchers speculate that caffeine might inhibit CYP1A2. However, there is no reliable evidence that caffeine affects CYP1A2. There is also speculation that genetic factors might make some patients be more sensitive to the interaction between clozapine and caffeine.
Contraceptive Drugs
Theoretically, concomitant use might increase the effects and adverse effects of caffeine found in coffee.
Coffee contains caffeine. Oral contraceptive drugs can decrease caffeine clearance by 40% to 65%.
Dipyridamole (Persantine)
Theoretically, coffee might decrease the vasodilatory effects of dipyridamole and interfere with its use prior to stress testing.
Coffee contains caffeine. Caffeine is a methylxyanthine that may inhibit dipyridamole-induced vasodilation. It is recommended that methylxanthines such as caffeine, as well as methylxanthine-containing products such as coffee, be stopped 24 hours prior to pharmacological stress tests. Methylxanthines appear more likely to interfere with dipyridamole (Persantine) than adenosine-induced stress testing.
Disulfiram (Antabuse)
Theoretically, disulfiram might increase the risk of adverse effects from caffeine.
Coffee contains caffeine. In human research, disulfiram decreases the clearance and increases the half-life of caffeine.
Diuretic Drugs
Theoretically, concomitant use might increase the risk of hypokalemia.
Coffee contains caffeine. Caffeine, especially in excessive amounts, can reduce potassium levels due to stimulation of the sodium-potassium pump. Diuretics can also cause lower potassium levels.
Estrogens
Theoretically, estrogens might increase the levels and adverse effects of caffeine.
Coffee contains caffeine. Estrogen inhibits caffeine metabolism.
Fluvoxamine (Luvox)
Theoretically, fluvoxamine might increase the levels and adverse effects of caffeine.
Coffee contains caffeine. Fluvoxamine reduces caffeine metabolism.
Lamotrigine (Lamictal)
Coffee consumption can decrease the levels and clinical effects of lamotrigine.
A pharmacokinetic study in patients taking lamotrigine shows that consumption of coffee, both caffeinated and decaffeinated, can decrease the area under the concentration-time curve (AUC) and the peak plasma level (Cmax) of lamotrigine. Each additional cup of coffee reduced the AUC and Cmax by 4% and 3%, respectively. It is unclear whether this interaction is due to induction of lamotrigine metabolism or inhibition of lamotrigine absorption.
Levothyroxine (Synthroid, Others)
Coffee can reduce the absorption of levothyroxine.
In some patients, coffee can reduce levothyroxine absorption, possibly through the formation of non-absorbable complexes. A pharmacokinetic study in these patients found that 25-30 mL of espresso coffee consumed with levothyroxine tablets delayed the time to peak plasma levels by 38-43 minutes, reduced the peak plasma level (Cmax) by 19% to 36%, and reduced the area under the curve (AUC) by 27% to 36%. Coffee consumed one hour after levothyroxine did not affect absorption. It is not known whether this interaction occurs with other types of coffee. Tell patients to avoid drinking coffee at the same time that they take their levothyroxine, and for up to an hour afterwards.
Lithium
Theoretically, abrupt coffee withdrawal might increase the levels and adverse effects of lithium.
Coffee contains caffeine. Abrupt caffeine withdrawal can increase serum lithium levels. Two cases of lithium tremor that worsened with abrupt coffee withdrawal have been reported. There is also one case of a 2.8-fold increase in blood lithium levels after a patient taking lithium reduced his coffee consumption from 13-20 cups daily to 10 cups daily.
Monoamine Oxidase Inhibitors (Maois)
Theoretically, concomitant use might increase the risk of a hypertensive crisis.
Coffee contains caffeine. Caffeine has been shown to inhibit monoamine oxidase (MAO) A and B in laboratory studies. Concomitant intake of large amounts of caffeine with MAOIs might precipitate a hypertensive crisis. In a case report, a patient that consumed 10-12 cups of caffeinated coffee and took the MAOI tranylcypromine presented with severe hypertension. Hypertension was resolved after the patient switched to drinking decaffeinated coffee.
Nicotine
Theoretically, concomitant use might increase the risk of hypertension.
Coffee contains caffeine. Concomitant use of caffeine and nicotine has been shown to have additive cardiovascular effects, including increased heart rate and blood pressure. Blood pressure was increased by 10.8/12.4 mmHg when the agents were used concomitantly.
Pentobarbital (Nembutal)
Theoretically, coffee might reduce the effects of pentobarbital.
Coffee contains caffeine. Theoretically, caffeine might negate the hypnotic effects of pentobarbital.
Phenylpropanolamine
Theoretically, phenylpropanolamine might increase the risk of hypertension, as well as the levels and adverse effects of caffeine.
Coffee contains caffeine. Concomitant use of phenylpropanolamine and caffeine might cause an additive increase in blood pressure. Phenylpropanolamine also seems to increase caffeine serum levels.
Pioglitazone (Actos)
Theoretically, coffee might increase the levels and clinical effects of pioglitazone.
Coffee contains caffeine. Animal research suggests that caffeine can modestly increase the maximum concentration, area under the curve, and half-life of pioglitazone, and also reduce its clearance. This increased the antidiabetic effects of pioglitazone. However, the exact mechanism of this interaction is unclear.
Quinolone Antibiotics
Theoretically, quinolone antibiotics might increase the levels and adverse effects of caffeine.
Coffee contains caffeine. Concomitant use of caffeine and quinolones can decrease caffeine clearance and increase effects and risk of adverse effects.
Riluzole (Rilutek)
Theoretically, concomitant use might increase the levels and adverse effects of both caffeine and riluzole.
Coffee contains caffeine. Caffeine and riluzole are both metabolized by cytochrome P450 1A2 (CYP1A2), and concomitant use might reduce metabolism of one or both agents.
Stimulant Drugs
Theoretically, concomitant use might increase stimulant adverse effects.
Coffee contains caffeine. Due to the central nervous system (CNS) stimulant effects of caffeine, concomitant use with stimulant drugs can increase the risk of adverse effects.
Theophylline
Theoretically, coffee might increase the levels and adverse effects of theophylline.
Coffee contains caffeine, which can increase theophylline levels.
Magnesium
Levodopa/Carbidopa (Sinemet)
Magnesium can reduce the bioavailability of levodopa/carbidopa.
Clinical research in healthy volunteers shows that taking magnesium oxide 1000 mg with levodopa 100 mg/carbidopa 10 mg reduces the area under the curve (AUC) of levodopa by 35% and of carbidopa by 81%. In vitro and animal research shows that magnesium produces an alkaline environment in the digestive tract, which might lead to degradation and reduced bioavailability of levodopa/carbidopa.
Aminoglycoside Antibiotics
Concomitant use of aminoglycoside antibiotics and magnesium can increase the risk for neuromuscular weakness.
Both aminoglycosides and magnesium reduce presynaptic acetylcholine release, which can lead to neuromuscular blockade and possible paralysis. This is most likely to occur with high doses of magnesium given intravenously.
Antacids
Use of acid reducers may reduce the laxative effect of magnesium oxide.
A retrospective analysis shows that, in the presence of H2 receptor antagonists (H2RAs) or proton pump inhibitors (PPIs), a higher dose of magnesium oxide is needed for a laxative effect. This may also occur with antacids. Under acidic conditions, magnesium oxide is converted to magnesium chloride and then to magnesium bicarbonate, which has an osmotic laxative effect. By reducing acidity, antacids may reduce the conversion of magnesium oxide to the active bicarbonate salt.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Magnesium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide should be taken at least 2 hours before or 6 hours after magnesium containing products.
Bisphosphonates
Magnesium can decrease absorption of bisphosphonates.
Cations, including magnesium, can decrease bisphosphonate absorption. Advise patients to separate doses of magnesium and these drugs by at least 2 hours.
Calcium Channel Blockers
Magnesium can have additive effects with calcium channel blockers, although evidence is conflicting.
Magnesium inhibits calcium entry into smooth muscle cells and may therefore have additive effects with calcium channel blockers. Severe hypotension and neuromuscular blockades may occur when nifedipine is used with intravenous magnesium, although some contradictory evidence suggests that concurrent use of magnesium with nifedipine does not increase the risk of neuromuscular weakness. High doses of magnesium could theoretically have additive effects with other calcium channel blockers.
Digoxin
Magnesium salts may reduce absorption of digoxin.
Clinical evidence suggests that treatment with oral magnesium hydroxide or magnesium trisilicate reduces absorption of digoxin from the intestines. This may reduce the blood levels of digoxin and decrease its therapeutic effects.
Potassium-Sparing Diuretics
Potassium-sparing diuretics decrease excretion of magnesium, possibly increasing magnesium levels.
Potassium-sparing diuretics also have magnesium-sparing properties, which can counteract the magnesium losses associated with loop and thiazide diuretics. Theoretically, increased magnesium levels could result from concomitant use of potassium-sparing diuretics and magnesium supplements.
Quinolone Antibiotics
Magnesium decreases absorption of quinolones.
Magnesium can form insoluble complexes with quinolones and decrease their absorption. Advise patients to take these drugs at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Skeletal Muscle Relaxants
Parenteral magnesium alters the pharmacokinetics of skeletal muscle relaxants, increasing their effects and accelerating the onset of effect.
Parenteral magnesium shortens the time to onset of skeletal muscle relaxants by about 1 minute and prolongs the duration of action by about 2 minutes. Magnesium potentiates the effects of skeletal muscle relaxants by decreasing calcium-mediated release of acetylcholine from presynaptic nerve terminals, reducing postsynaptic sensitivity to acetylcholine, and having a direct effect on the membrane potential of myocytes. Magnesium also has vasodilatory actions and increases cardiac output, allowing a greater amount of muscle relaxant to reach the motor end plate. A clinical study found that low-dose rocuronium (0.45 mg/kg), when given after administration of magnesium 30 mg/kg over 10 minutes, has an accelerated onset of effect, which matches the onset of effect seen with a full-dose rocuronium regimen (0.6 mg/kg). In another clinical study, onset times for rocuronium doses of 0.3, 0.6, and 1.2 mg/kg were 86, 76, and 50 seconds, respectively, when given alone, but were reduced to 66, 44, and 38 seconds, respectively, when the doses were given after a 15-minute infusion of magnesium sulfate 60 mg/kg. Giving intraoperative intravenous magnesium sulfate, 50 mg/kg loading dose followed by 15 mg/kg/hour, reduces the onset time of rocuronium, enhances its clinical effects, reduces the dose of intraoperative opiates, and prolongs the spontaneous recovery time. It does not affect the activity of subsequently administered neostigmine.
Sulfonylureas
Magnesium increases the systemic absorption of sulfonylureas, increasing their effects and side effects.
Clinical research shows that administration of magnesium hydroxide with glyburide increases glyburide absorption, increases maximal insulin response by 35-fold, and increases the risk of hypoglycemia, when compared with glyburide alone. A similar interaction occurs between magnesium hydroxide and glipizide. The mechanism of this effect appears to be related to the elevation of gastrointestinal pH by magnesium-based antacids, increasing solubility and enhancing absorption of sulfonylureas.
Tetracycline Antibiotics
Magnesium decreases absorption of tetracyclines.
Magnesium can form insoluble complexes with tetracyclines in the gut and decrease their absorption and antibacterial activity. Advise patients to take these drugs 1 hour before or 2 hours after magnesium supplements.
Anticoagulant/Antiplatelet Drugs
Theoretically, magnesium may have antiplatelet effects, but the evidence is conflicting.
In vitro evidence shows that magnesium sulfate inhibits platelet aggregation, even at low concentrations. Some preliminary clinical evidence shows that infusion of magnesium sulfate increases bleeding time by 48% and reduces platelet activity. However, other clinical research shows that magnesium does not affect platelet aggregation, although inhibition of platelet-dependent thrombosis can occur.
Gabapentin (Neurontin)
Gabapentin absorption can be decreased by magnesium.
Clinical research shows that giving magnesium oxide orally along with gabapentin decreases the maximum plasma concentration of gabapentin by 33%, time to maximum concentration by 36%, and area under the curve by 43%. Advise patients to take gabapentin at least 2 hours before, or 4 to 6 hours after, magnesium supplements.
Sevelamer (Renagel, Renvela)
Sevelamer may increase serum magnesium levels.
In patients on hemodialysis, sevelamer use was associated with a 0.28 mg/dL increase in serum magnesium. The mechanism of this interaction remains unclear.
Sodium
Antihypertensive Drugs
Theoretically, a high intake of dietary sodium might reduce the effectiveness of antihypertensive drugs.
High intake of dietary sodium can increase systolic and diastolic blood pressure. Also, high intake of sodium may necessitate increased use of antihypertensive medications to achieve blood pressure control in some patients, such as those with chronic kidney disease.
Corticosteroids
Concomitant use of mineralocorticoids and some glucocorticoids with sodium supplements might increase the risk of hypernatremia.
Mineralocorticoids and some glucocorticoids (corticosteroids) cause sodium retention. This effect is dose-related and depends on mineralocorticoid potency. It is most common with hydrocortisone, cortisone, and fludrocortisone, followed by prednisone and prednisolone.
Didanosine (Videx)
Concomitant use of didanosine with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia.
Didanosine formulations contain a significant amount of sodium.
Lithium
Altering dietary intake of sodium might alter the levels and clinical effects of lithium.
High sodium intake can reduce plasma concentrations of lithium by increasing lithium excretion. Reducing sodium intake can significantly increase plasma concentrations of lithium and cause lithium toxicity in patients being treated with lithium carbonate. Stabilizing sodium intake is shown to reduce the percentage of patients with lithium level fluctuations above 0.8 mEq/L. Patients taking lithium should avoid significant alterations in their dietary intake of sodium.
Sodium Phosphates
Theoretically, concomitant use of sodium phosphate with sodium supplements might increase the risk of hypernatremia.
Use of high doses (> 45 mL in 24 hours) of sodium phosphate, such as those used for bowel cleansing before surgery, can lead to serious electrolyte disturbances, including hypernatremia. The risk of hypernatremia is highest in the elderly and people with other risk factors for electrolyte disturbances.
Sodium-Containing Drugs
Concomitant use of sodium-containing drugs with additional sodium from dietary or supplemental sources may increase the risk of hypernatremia and long-term sodium-related complications.
The Chronic Disease Risk Reduction (CDRR) intake level of 2.3 grams of sodium daily indicates the intake at which it is believed that chronic disease risk increases for the apparently healthy population. Some medications contain high quantities of sodium. When used in conjunction with sodium supplements or high-sodium diets, the CDRR may be exceeded. Additionally, concomitant use may increase the risk for hypernatremia; this risk is highest in the elderly and people with other risk factors for electrolyte disturbances.
Tolvaptan (Samsca)
Theoretically, concomitant use of tolvaptan with sodium might increase the risk of hypernatremia.
Tolvaptan is a vasopressin receptor 2 antagonist that is used to increase sodium levels in patients with hyponatremia. Patients taking tolvaptan should use caution with the use of sodium salts such as sodium chloride.
Calcium
Ceftriaxone (Rocephin)
Co-administration of intravenous calcium and ceftriaxone can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys.
Avoid administering intravenous calcium in any form, such as parenteral nutrition or Lactated Ringers, within 48 hours of intravenous ceftriaxone. Case reports in neonates show that administering intravenous ceftriaxone and calcium can result in precipitation of a ceftriaxone-calcium salt in the lungs and kidneys. In several cases, neonates have died as a result of this interaction. So far there are no reports in adults; however, there is still concern that this interaction might occur in adults.
Dolutegravir (Tivicay)
Calcium seems to reduce levels of dolutegravir.
Advise patients to take dolutegravir either 2 hours before or 6 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium carbonate 1200 mg concomitantly with dolutegravir 50 mg reduces plasma levels of dolutegravir by almost 40%. Calcium appears to decrease levels of dolutegravir through chelation.
Elvitegravir (Vitekta)
Calcium seems to reduce levels of elvitegravir.
Advise patients to take elvitegravir either 2 hours before or 2 hours after taking calcium supplements. Pharmacokinetic research suggests that taking calcium along with elvitegravir can reduce blood levels of elvitegravir through chelation.
Aluminum
Calcium citrate might increase aluminum absorption and toxicity. Other types of calcium do not increase aluminum absorption.
Calcium citrate can increase the absorption of aluminum when taken with aluminum hydroxide. The increase in aluminum levels may become toxic, particularly in individuals with kidney disease. However, the effect of calcium citrate on aluminum absorption is due to the citrate anion rather than calcium cation. Calcium acetate does not appear to increase aluminum absorption.
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Calcium might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and calcium can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, calcium containing products.
Bisphosphonates
Calcium reduces the absorption of bisphosphonates.
Advise patients to take bisphosphonates at least 30 minutes before calcium, but preferably at a different time of day. Calcium supplements decrease absorption of bisphosphonates.
Calcipotriene (Dovonex)
Taking calcipotriene with calcium might increase the risk for hypercalcemia.
Calcipotriene is a vitamin D analog used topically for psoriasis. It can be absorbed in sufficient amounts to cause systemic effects, including hypercalcemia. Theoretically, combining calcipotriene with calcium supplements might increase the risk of hypercalcemia.
Digoxin (Lanoxin)
Using intravenous calcium with digoxin might increase the risk of fatal cardiac arrhythmias.
Hypercalcemia increases the risk of fatal cardiac arrhythmias with digoxin. However, one retrospective analysis of clinical data suggests that intravenous calcium does not increase the risk of dysrhythmias or mortality in patients receiving digoxin.
Diltiazem (Cardizem, Others)
Theoretically, calcium may reduce the therapeutic effects of diltiazem.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, calcium might increase this risk of hypercalcemia and reduce the effectiveness of diltiazem.
Levothyroxine (Synthroid, Others)
Calcium seems to reduce the absorption and effectiveness of levothyroxine.
Advise patients to take levothyroxine and calcium supplements at least 4 hours apart. Calcium reduces levothyroxine absorption, probably by forming insoluble complexes. Calcium carbonate supplements reduce effectiveness of levothyroxine in patients with hypothyroidism.
Lithium
Theoretically, concomitant use of calcium and lithium may increase this risk of hypercalcemia.
Clinical research suggests that long-term use of lithium may cause hypercalcemia in 10% to 60% of patients. Theoretically, concomitant use of lithium and calcium supplements may further increase this risk.
Quinolone Antibiotics
Calcium seems to reduce the absorption of quinolone antibiotics.
Advise patients to take oral quinolones at least 2 hours before or 4-6 hours after calcium supplements or calcium-fortified foods. Taking calcium at the same time as oral quinolones can reduce quinolone absorption. Calcium binds to quinolones in the gut.
Raltegravir (Isentress)
Calcium may reduce levels of raltegravir.
Pharmacokinetic research shows that taking a single dose of calcium carbonate 3000 mg along with raltegravir 400 mg twice daily modestly decreases the mean area under the curve of raltegravir, but the decrease does not necessitate a dose adjustment of raltegravir. However, a case of elevated HIV-1 RNA levels and documented resistance to raltegravir has been reported for a patient taking calcium carbonate 1 gram three times daily plus vitamin D3 (cholecalciferol) 400 IU three times daily in combination with raltegravir 400 mg twice daily for 11 months. It is thought that calcium reduced raltegravir levels by chelation, leading to treatment failure.
Sotalol (Betapace)
Calcium seems to reduce the absorption of sotalol.
Advise patients to separate doses by at least 2 hours before or 4-6 hours after calcium. Calcium appears to reduce the absorption of sotalol, probably by forming insoluble complexes.
Tetracycline Antibiotics
Calcium seems to reduce the absorption of tetracycline antibiotics.
Advise patients to take oral tetracyclines at least 2 hours before, or 4-6 hours after calcium supplements. Taking calcium at the same time as oral tetracyclines can reduce tetracycline absorption. Calcium binds to tetracyclines in the gut.
Thiazide Diuretics
Taking calcium along with thiazides might increase the risk of hypercalcemia and renal failure.
Thiazides reduce calcium excretion by the kidneys. Using thiazides along with moderately large amounts of calcium carbonate increases the risk of milk-alkali syndrome (hypercalcemia, metabolic alkalosis, renal failure). Patients may need to have their serum calcium levels and/or parathyroid function monitored regularly.
Verapamil (Calan, Others)
Theoretically, calcium may reduce the therapeutic effects of verapamil.
Hypercalcemia can reduce the effectiveness of verapamil in atrial fibrillation. Theoretically, use of calcium supplements may increase this risk of hypercalcemia and reduce the effectiveness of verapamil.
Calcium Channel Blockers
Intravenous calcium may decrease the effects of calcium channel blockers; oral calcium is unlikely to have this effect.
Intravenous calcium is used to decrease the effects of calcium channel blockers in the management of overdose. Intravenous calcium gluconate has been used before intravenous verapamil (Isoptin) to prevent or reduce the hypotensive effects without affecting the antiarrhythmic effects. But there is no evidence that dietary or supplemental calcium when taken orally interacts with calcium channel blockers.
Iron
Bictegravir/Emtricitabine/Tenofovir Alafenamide (Biktarvy)
Iron might decrease levels of bictegravir/emtricitabine/tenofovir alafenamide by reducing its absorption when taken in a fasting state.
Advise patients that bictegravir/emtricitabine/tenofovir alafenamide and iron can be taken together if taken with food. However, if taken on an empty stomach, bictegravir/emtricitabine/tenofovir alafenamide should not be taken with, or 2 hours after, iron containing products.
Bisphosphonates
Iron reduces the absorption of bisphosphonates.
Advise patients that doses of bisphosphonates should be separated by at least two hours from doses of all other medications, including supplements such as iron. Divalent cations, including iron, can decrease absorption of bisphosphonates by forming insoluble complexes in the gastrointestinal tract.
Denosumab (Prolia, Others)
Administration of intravenous iron within one month of denosumab administration might increase the risk of severe hypophosphatemia and hypocalcemia.
A case of severe hypocalcemia (albumin corrected calcium 6.88 mg/dL, ionized calcium 3.68 mg/dL) and hypophosphatemia (<0.5 mg/dL) with respiratory acidosis, QT interval prolongation, and nonsustained ventricular tachycardia was reported in a 76-year-old male who had received an iron polymaltose infusion within 2 weeks of a subcutaneous injection of denosumab. Serum parathyroid hormone was also elevated (348 pg/mL). Subsequent iron infusions with iron polymaltose and ferric carboxymaltose were followed by transient hypophosphatemia, but without hypocalcemia. Additionally, a literature review describes 6 additional cases of hypophosphatemia and hypocalcemia in patients 52-92 years of age who had been administered intravenous iron as either ferric carboxymaltose or iron polymaltose and subcutaneous denosumab within 1-4 weeks of each other.
Dolutegravir (Tivicay)
Iron might decrease dolutegravir levels by reducing its absorption.
Advise patients to take dolutegravir at least 2 hours before or 6 hours after taking iron. Pharmacokinetic research shows that iron can decrease the absorption of dolutegravir from the gastrointestinal tract through chelation. When taken under fasting conditions, a single dose of ferrous fumarate 324 mg orally along with dolutegravir 50 mg reduces overall exposure to dolutegravir by 54%.
Integrase Inhibitors
Theoretically, taking iron along with integrase inhibitors might decrease the levels and clinical effects of these drugs.
Iron is a divalent cation. There is concern that iron may decrease the absorption of integrase inhibitors from the gastrointestinal tract through chelation. One pharmacokinetic study shows that iron can decrease blood levels of the specific integrase inhibitor dolutegravir through chelation. Also, other pharmacokinetic research shows that other divalent cations such as calcium can decrease the absorption and levels of some integrase inhibitors through chelation.
Levodopa
Iron might decrease levodopa levels by reducing its absorption.
Advise patients to separate doses of levodopa and iron as much as possible. There is some evidence in healthy people that iron forms chelates with levodopa, reducing the amount of levodopa absorbed by around 50%. The clinical significance of this hasn't been determined.
Levothyroxine (Synthroid, Others)
Iron might decrease levothyroxine levels by reducing its absorption.
Advise patients to separate levothyroxine and iron doses by at least 2 hours. Iron can decrease the absorption and efficacy of levothyroxine by forming insoluble complexes in the gastrointestinal tract.
Methyldopa (Aldomet)
Iron might decrease methyldopa levels by reducing its absorption.
Advise patients to separate methyldopa and iron doses by at least 2 hours. Iron can decrease the absorption of methyldopa from the gastrointestinal tract through chelation, resulting in increases in blood pressure.
Mycophenolate Mofetil (Cellcept)
Theoretically, iron might decrease mycophenolate mofetil levels by reducing its absorption.
Advise patients to take iron 4-6 hours before, or 2 hours after, mycophenolate mofetil. It has been suggested that a decrease of absorption is possible, probably by forming nonabsorbable chelates. However, mycophenolate pharmacokinetics are not affected by iron supplementation in available clinical research.
Penicillamine (Cuprimine, Depen)
Iron might decrease penicillamine levels by reducing its absorption.
Advise patients to separate penicillamine and iron doses by at least 2 hours. Oral iron supplements can reduce absorption of penicillamine by 30% to 70%, probably due to chelate formation. In people with Wilson's disease, this interaction has led to reduced efficacy of penicillamine.
Quinolone Antibiotics
Iron might decrease levels of quinolone antibiotics by reducing their absorption.
Advise patients to separate quinolone antibiotics and iron doses by at least 2 hours. Iron decreases the absorption of quinolones due to formation of insoluble complexes in the gastrointestinal tract.
Tetracycline Antibiotics
Iron might decrease levels of tetracycline antibiotics by reducing their absorption.
Advise patients to take iron at least 2 hours before or 4 hours after tetracycline antibiotics. Concomitant use can decrease absorption of tetracycline antibiotics from the gastrointestinal tract by 50% to 90%.
Chloramphenicol
Theoretically, taking chloramphenicol with iron might reduce the response to iron therapy in iron deficiency anemia.
Chloramphenicol interferes with erythrocyte maturation. However, since chloramphenicol isn't usually taken for prolonged periods, this isn't likely to be clinically significant.
Lemon Juice, Powder
Itraconazole (Sporanox)
Theoretically, taking itraconazole capsules or tablets with a beverage containing lemon might increase the levels and clinical effects of itraconazole.
In one case report, dissolving itraconazole tablets in a small amount of specific beverages containing lemon prior to administration increased the level of itraconazole in a lung transplant patient. In this case, the increased bioavailability was desirable and was likely due to improved tablet dissolution in the acidic beverage.
Brand information
Manufacturer and brand details for Feel the Beet, from the product label.
Feel the Beet by Live it Up: Common Questions
Does Feel the Beet by Live it Up interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Does Feel the Beet contain caffeine, and how much?
Can I take this if I'm on a blood thinner like warfarin?
Is Feel the Beet safe during pregnancy?
Will this help with energy or athletic performance?
What are the common side effects?
Can I take this with my thyroid medication?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Feel the Beet is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Feel the Beet’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Sodium
Interacts with 205 drugsSodium is an essential mineral and electrolyte your body needs to balance fluids, support nerves, and help muscles work. Most people in modern diets get more than enough—often too much—from...
Read the full Sodium monograph → Herb & supplement monographCalcium
Interacts with 168 drugsCalcium is an essential mineral your body needs for strong bones, nerve signaling, and muscle function, and supplements can help fill gaps when diet falls short. Most people do best getting...
Read the full Calcium monograph → Herb & supplement monographIron
Interacts with 80 drugsIron is an essential mineral your body needs to make hemoglobin and carry oxygen in the blood. Supplements are mainly useful for treating or preventing iron deficiency and iron-deficiency an...
Read the full Iron monograph → Herb & supplement monographMagnesium
Interacts with 295 drugsMagnesium is an essential mineral your body needs for muscles, nerves, blood pressure, and many other functions, and supplements are useful for preventing or correcting deficiency. Some othe...
Read the full Magnesium monograph → Herb & supplement monographBlack Psyllium
Interacts with 2,025 drugsBlack psyllium is a soluble-fiber supplement made from the seeds of a Plantago plant, used mostly to ease constipation and support digestive health. It is best known and most studied for rel...
Read the full Black Psyllium monograph → Herb & supplement monographMaca
Maca is a nutrient-rich Andean root often used for energy, libido, and menopause symptoms. Early studies suggest it may modestly help sexual desire and some menopause symptoms, but the evide...
Read the full Maca monograph → Herb & supplement monographAshwagandha
Interacts with 1,372 drugsAshwagandha is an Ayurvedic herb most often taken to help with stress, anxiety, and sleep, and some small studies suggest it may help, though the evidence is still limited. It is generally w...
Read the full Ashwagandha monograph → Herb & supplement monographLemon
Interacts with 1 drugLemon is a common citrus fruit that is a good source of vitamin C and citric acid, and it is widely used in food, drinks, and home remedies. While it can support hydration and a healthy diet...
Read the full Lemon monograph → Herb & supplement monographBeet
Interacts with 861 drugsBeet, especially beetroot juice, is a nitrate-rich food that may modestly lower blood pressure and slightly improve exercise performance in some people. It is generally safe as a food, but s...
Read the full Beet monograph → Herb & supplement monographGinkgo
Interacts with 1,266 drugsGinkgo is one of the world's most popular herbal supplements, mostly taken to support memory and circulation. The evidence for these uses is mixed and generally weak, and it is not proven to...
Read the full Ginkgo monograph → Herb & supplement monographBacopa
Interacts with 930 drugsBacopa is an Ayurvedic herb most often used for memory and thinking. Some small studies suggest it may modestly help memory when taken regularly for several weeks, but the evidence is limite...
Read the full Bacopa monograph → Herb & supplement monographCoffee
Interacts with 591 drugsCoffee is a widely consumed beverage made from roasted coffee beans, valued mainly for its caffeine, which boosts alertness and energy. For most healthy adults, moderate coffee intake is gen...
Read the full Coffee monograph → Herb & supplement monographPomegranate
Interacts with 922 drugsPomegranate is a nutrient-rich fruit that is high in antioxidants and is widely enjoyed as food and juice. Early research suggests it may support heart health and blood pressure, but the evi...
Read the full Pomegranate monograph →Sources & How We Checked
Feel the Beet's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 972 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Sodium 38 references
- Garabedian-Ruffalo SM, Ruffalo RL. Drug and nutrient interactions. Am Fam Physician 1986;33:165-74.
- Food and Drug Administration Science Background: Safety of Sodium Phosphates Oral Solution. September 17, 2001. Available at: http://www.fda.gov/cder/drug/safety/sodiumphospate.htm
- Coton T, Mallaret C, Coilliot C, Carre D, Guisset M. Severe acute ulcerated gastritis induced by salt. Presse Med 2009;38(3):499-500. PubMed
- Frings-Meuthen P, Buehlmeier J, Baecker N, et al. High sodium chloride intake exacerbates immobilization-induced bone resorption and protein losses. J Appl Physiol 2011;111(2):537-542. PubMed
- Frings-Meuthen P, Baecker N, Heer M. Low-grade metabolic acidosis may be the cause of sodium chloride-induced exaggerated bone resorption. J Bone Miner Res 2008;23(4):517-524. PubMed
- Alam S, Johnson AG. A meta-analysis of randomised controlled trials (RCT) among healthy normotensive and essential hypertensive elderly patients to determine the effect of high salt (NaCl) diet of blood pressure. J Hum Hypertens 1999;13(6):367-74.
- Boudville N, Ward S, Benaroia M, House AA. Increased sodium intake correlates with greater use of antihypertensive agents by subjects with chronic kidney disease. Am J Hypertens 2005;18(10):1300-5. PubMed
- Bennett WM. Drug interactions and consequences of sodium restriction. Am J Clin Nutr 1997;65(2 Suppl):678S-681S. PubMed
- Okusa MD, Crystal LJ. Clinical manifestations and management of acute lithium intoxication. Am J Med 1994;97(4):383-9. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary reference intakes for water, potassium, sodium, chloride, and sulfate. Washington, DC: National Academy Press, 2005. Available at: http://www.nap.edu/openbook.php?record_id=10925. DOI
- D'Elia L, Rossi G, Ippolito R, Cappuccio FP, Strazzullo P. Habitual salt intake and risk of gastric cancer: a meta-analysis of prospective studies. Clin Nutr 2012;31(4):489-98. PubMed
- Goldsmith SR. Hyponatremia in heart failure: time for a trial. J Card Fail 2013;19(6):398-400. PubMed
- Willocks L, Brettle R, Keen J, Valentine C, Pinching AJ. Formulations of didanosine (ddI) and salt overload. Lancet 1992;339(8786):190.
- Chen L, Zhang Z, Chen W, Whelton PK, Appel LJ. Lower Sodium Intake and Risk of Headaches: Results From the Trial of Nonpharmacologic Interventions in the Elderly. Am J Public Health. 2016;106(7):1270-5. PubMed
- Cook NR, Appel LJ, Whelton PK. Lower levels of sodium intake and reduced cardiovascular risk. Circulation. 2014;129(9):981-9. PubMed
- Cook NR, Appel LJ, Whelton PK. Sodium Intake and All-Cause Mortality Over 20 Years in the Trials of Hypertension Prevention. J Am Coll Cardiol. 2016;68(15):1609-1617. PubMed
- Mente A, O'Donnell M, Rangarajan S, et al. Associations of urinary sodium excretion with cardiovascular events in individuals with and without hypertension: a pooled analysis of data from four studies. Lancet. 2016;388(10043):465-75. PubMed
- Moosavian SP, Haghighatdoost F, Surkan PJ, Azadbakht L. Salt and obesity: a systematic review and meta-analysis of observational studies. Int J Food Sci Nutr. 2017;68(3):265-277. PubMed
- O'Donnell M, Mente A, Rangarajan S, et al. Urinary sodium and potassium excretion, mortality, and cardiovascular events. N Engl J Med. 2014;371(7):612-23. DOI
- Poggio R, Gutierrez L, Matta MG, Elorriaga N, Irazola V, Rubinstein A. Daily sodium consumption and CVD mortality in the general population: systematic review and meta-analysis of prospective studies. Public Health Nutr. 2015;18(4):695-704. PubMed
- Stallings VA, Harrison M, Oria M; Committee to Review the Dietary Reference Intakes for Sodium and Potassium, Food and Nutrition Board, Health and Medicine Division, National Academies of Sciences, Engineering, and Medicine. Washington (DC): National Acad
- Mahtani KR, Heneghan C, Onakpoya I, et al. Reduced Salt Intake for Heart Failure: A Systematic Review. JAMA Intern Med. 2018 Dec 1;178(12):1693-1700. PubMed
- Yancy CW. Sodium Restriction in Heart Failure: Too Much Uncertainty-Do the Trials. JAMA Intern Med. 2018 Dec 1;178(12):1700-1701. PubMed
- He FJ, Campbell NRC, Ma Y, MacGregor GA, Cogswell ME, Cook NR. Errors in estimating usual sodium intake by the Kawasaki formula alter its relationship with mortality: implications for public health. Int J Epidemiol. 2018;47(6):1784-1795. PubMed
- Murthy K, Ondrey GJ, Malkani N, et al. THE EFFECTS OF HYPONATREMIA ON BONE DENSITY AND FRACTURES: A SYSTEMATIC REVIEW AND META-ANALYSIS. Endocr Pract. 2019;25(4):366-378. PubMed
- Messerli FH, Hofstetter L, Syrogiannouli L, et al. Sodium intake, life expectancy, and all-cause mortality. Eur Heart J 2021;42(21):2103-2112. PubMed
- Graudal NA, Hubeck-Graudal T, Jurgens G. Effects of low sodium diet versus high sodium diet on blood pressure, renin, aldosterone, catecholamines, cholesterol, and triglyceride. Cochrane Database Syst Rev 2020;12(12):CD004022. PubMed
- Giatti S, Santos RB, Aielo AN, et al. Association of sodium with obstructive sleep apnea. The ELSA-Brasil study. Ann Am Thorac Soc 2021;18(3):502-510. PubMed
- Nan X, Lu H, Wu J, et al. The interactive association between sodium intake, alcohol consumption and hypertension among elderly in northern China: a cross-sectional study. BMC Geriatr 2021;21(1):135. PubMed
- Kyozuka H, Fukusda T, Murata T, et al. Impact of preconception sodium intake on hypertensive disorders of pregnancy: The Japan Environment and Children's study. Pregnancy Hypertens 2021;23:66-72. PubMed
- Zhao L, Ogden CL, Yang Q, et al. Association of usual sodium intake with obesity among US children and adolescents, NHANES 2009-2016. Obesity (Silver Spring) 2021;29(3):587-594. PubMed
- Ma Y, He FJ, Sun Q, et al. 24-Hour urinary sodium and potassium excretion and cardiovascular risk. N Engl J Med 2022;386(3):252-263. PubMed
- Liu J, Yang X, Zhang P, et al. Association of urinary sodium excretion and left ventricular hypertrophy in people with type 2 diabetes mellitus: A cross-sectional study. Front Endocrinol (Lausanne) 2021;12:728493. PubMed
- Filippini T, Malavolti M, Whelton PK, Vinceti M. Sodium intake and risk of hypertension: A systematic review and dose-response meta-analysis of observational cohort studies. Curr Hypertens Rep 2022;24(5):133-144. PubMed
- Wang DD, Li Y, Nguyen XT, et al. Dietary sodium and potassium intake and risk of non-fatal cardiovascular diseases: The million veteran program. Nutrients 2022;14(5):1121. PubMed
- Kwak JH, Park CH, Eun CS, et al. The associations of dietary intake of high sodium and low zinc with gastric cancer mortality: A prospective cohort study in Korea. Nutr Cancer 2022;74(10):3501-3508. PubMed
- George S, Maiti R, Mishra BR, Jena M, Mohapatra D. Effect of regulated add-on sodium chloride intake on stabilization of serum lithium concentration in bipolar disorder: A randomized controlled trial. Bipolar Disord 2023;25(1):66-75. PubMed
- Zhou TL, Schütten MTJ, Kroon AA, et al. Urinary Sodium Excretion and Salt Intake Are Not Associated With Blood Pressure Variability in a White General Population. J Am Heart Assoc 2023;12(1):e026578. PubMed
Calcium 62 references
- Shils M, Olson A, Shike M. Modern Nutrition in Health and Disease. 8th ed. Philadelphia, PA: Lea and Febiger, 1994.
- Hernandez-Avila M, Gonzalez-Cossio T, Hernandez-Avila JE, et al. Dietary calcium supplements to lower blood lead levels in lactating women: a randomized placebo-controlled trial. Epidemiology 2003;14:206-12.. PubMed
- Thys-Jacobs S, Ceccarelli S, Bierman A, et al. Calcium supplementation in premenstrual syndrome: a randomized crossover trial. J Gen Intern Med 1989;4:183-9. PubMed
- Maton PN, Burton ME. Antacids revisited: a review of their clinical pharmacology and recommended therapeutic use. Drugs 1999;57:855-70.
- Clemens JD, Feinstein AR. Calcium carbonate and constipation: a historical review of medical mythopoeia. Gastroenterology 1977;72:957-61. DOI
- Saunders D, Sillery J, Chapman R. Effect of calcium carbonate and aluminum hydroxide on human intestinal function. Dig Dis Sci 1988;33:409-13. PubMed
- Friedman PA, Bushinsky DA. Diuretic effects on calcium metabolism. Semin Nephrol 1999;19:551-6.
- Koo WK, Walters JC, Esterlitz J, et al. Maternal calcium supplementation and fetal bone mineralization. Obstet Gynecol 1999;94:577-82. DOI
- Raman L, Rajalakshmi K, Krishnamachari KAVR, et al. Effect of calcium supplementation to undernourished mothers during pregnancy on the bone density of the neonates. Am J Clin Nutr 1978; 31:466-9. DOI
- Murry JJ, Healy MD. Drug-mineral interactions: a new responsibility for the hospital dietician. J Am Diet Assoc 1991;91:66-73.
- Chan JM, Giovannucci E, Andersson SO, et al. Dairy products, calcium, phosphorous, vitamin D, and risk of prostate cancer. Cancer Causes Control 1998;9:559-66.
- Butner LE, Fulco PP, Feldman G, et al. Calcium carbonate-induced hypothyroidism. Ann Intern Med 2000:132:595. PubMed
- Schneyer CR. Calcium carbonate and reduction of levothyroxine efficacy. JAMA 1998;279:750. PubMed
- Moser LR, Smythe MA, Tisdale JE. The use of calcium salts in the prevention and management of verapamil-induced hypotension. Ann Pharmacother 2000;34:622-9. PubMed
- Singh N, Singh PN, Hershman JM. Effect of calcium carbonate on the absorption of levothyroxine. JAMA 2000;283:2822-5. PubMed
- Kahela P, Anttila M, Tikkanen R, Sundquist H. Effect of food, food constituents and fluid volume on the bioavailability of sotalol. Acta Pharmacol Toxicol (Copenh) 1979;44:7-12.. PubMed
- Pletz MW, Petzold P, Allen A, et al. Effect of calcium carbonate on bioavailability of orally administered gemifloxacin. Antimicrob Agents Chemother 2003;47:2158-60.. PubMed
- Bar-Or D, Yoel G. Calcium and calciferol antagonize effect of verapamil in atrial fibrillation. Br Med J 1981;282:1585-6.
- Decktor DL, Robinson M, Maton PN, et al. Effects of aluminum/magnesium hydroxide and calcium carbonate on esophageal and gastric pH in subjects with heartburn. Am J Ther 1995;2:546-52. PubMed
- Simoneau G. Absence of rebound effect with calcium carbonate. Eur J Drug Metab Pharmacokinet 1996;21:351-7. PubMed
- Peters ML, Leonard M, Licata AA. Role of alendronate and risedronate in preventing and treating osteoporosis. Cleve Clin J Med 2001;68:945-51. PubMed
- Bourke JF, Mumford R, Whittaker P, et al. The effects of topical calcipotriol on systemic calcium homeostasis in patients with chronic plaque psoriasis. J Am Acad Dermatol 1997;37:929-34.
- Gueguen L, Pointillart A. The bioavailability of dietary calcium. J Am Coll Nutr 2000;19:119s-136s. PubMed
- Vella A, Gerber TC, Hayes DL, Reeder GS. Digoxin, hypercalcaemia, and cardiac conduction. Postgrad Med J 1999;75:554-6. PubMed
- Bania TC, Blaufeux B, Hughes S, et al. Calcium and digoxin vs. calcium alone for severe verapamil toxicity. Acad Emerg Med 2000;7:1089-96. PubMed
- Tseng M, Breslow RA, Graubard BI, Ziegler RG. Dairy, calcium, and vitamin D intakes and prostate cancer risk in the National Health and Nutrition Examination Epidemiologic Follow-up Study cohort. Am J Clin Nutr 2005;81:1147-54. PubMed
- Weingarten MA, Zalmanovici A, Yaphe J. Dietary calcium supplementation for preventing colorectal cancer and adenomatous polyps. Cochrane Database Syst Rev 2004;(1):CD003548. PubMed
- Tavani A, Bertuccio P, Bosetti C, et al. Dietary intake of calcium, vitamin D, phosphorus and the risk of prostate cancer. Eur Urol 2005;48:27-33. PubMed
- Giovannucci E, Liu Y, Stampfer MJ, Willett WC. A prospective study of calcium intake and incident and fatal prostate cancer. Cancer Epidemiol Biomarkers Prev 2006;15:203-10. PubMed
- Rocephin (ceftriaxone) and calcium interaction. Pharmacist's Letter / Prescriber's Letter 2007;23(10):231005.
- Bolland MJ, Barber PA, Doughty RN, et al. Vascular events in healthy older women receiving calcium supplementation: randomised control trial. BMJ 2008;336:262-6.
- Bolland MJ, Avenell A, Baron JA, et al. Effect of calcium supplements on risk of myocardial infarction and cardiovascular events: meta-analysis. BMJ 2010;341:c3691. PubMed
- Calcium supplementation and vascular events. Pharmacist's Letter / Prescriber's Letter 2008;24(3):240306.
- Dietary reference intakes for calcium and vitamin D. Institute of Medicine, November 30, 2010. Available at: http://www.iom.edu/~/media/Files/Report%20Files/2010/Dietary-Reference-Intakes-for-Calcium-and-Vitamin-D/Vitamin%20D%20and%20Calcium%202010%20Repo
- Coburn JW, Mischel MG, Goodman WG, et al. Calcium citrate markedly enhances aluminum absorption from aluminum hydroxide. Am J Kidney Dis. 1991;17(6):708-11. PubMed
- Bradley JS, Wassel RT, Lee L, et al. Intravenous ceftriaxone and calcium in the neonate: assessing the risk for cardiopulmonary adverse events. Pediatrics. 2009;123(4):e609-13. PubMed
- Kays MB, Overholser BR, Mueller BA, et al. Effects of sevelamer hydrochloride and calcium acetate on the oral bioavailability of ciprofloxacin. Am J Kidney Dis. 2003;42(6):1253-9. PubMed
- Neuhofel, A. L., Wilton, J. H., Victory, J. M., Hejmanowsk, L. G., and Amsden, G. W. Lack of bioequivalence of ciprofloxacin when administered with calcium-fortified orange juice: a new twist on an old interaction. J Clin Pharmacol. 2002;42(4):461-466. DOI
- Dickinson, H. O., Nicolson, D. J., Cook, J. V., Campbell, F., Beyer, F. R., Ford, G. A., and Mason, J. Calcium supplementation for the management of primary hypertension in adults. Cochrane.Database.Syst.Rev. 2006;(2):CD004639. PubMed
- Jones, B. J. and Twomey, P. J. Requesting patterns for serum calcium concentration in patients on long-term lithium therapy. Int J Clin Pract. 2009;63(1):170-172. PubMed
- Levine, M., Nikkanen, H., and Pallin, D. J. The effects of intravenous calcium in patients with digoxin toxicity. J Emerg.Med. 2011;40(1):41-46. PubMed
- Castelo-Branco, C., Ciria-Recasens, M., Cancelo-Hidalgo, M. J., Palacios, S., Haya-Palazuelos, J., Carbonell-Abello, J., Blanch-Rubio, J., Martinez-Zapata, M. J., Manasanch, J., and Perez-Edo, L. Efficacy of ossein-hydroxyapatite complex compared with ca
- Li K, Kaaks R, Linseisen J, Rohrmann S. Associations of dietary calcium intake and calcium supplementation with myocardial infarction and stroke risk and overall cardiovascular mortality in the Heidelberg cohort of the European Prospective Investigation i
- Chung M, Tang AM, Fu Z. Calcium Intake and Cardiovascular Disease Risk: An Updated Systematic Review and Meta-analysis. Ann Intern Med. 2016 Oct 25. PubMed
- Nolan CR, Califano JR, Butzin CA. Influence of calcium acetate or calcium citrate on intestinal aluminum absorption. Kidney Int. 1990;38(5):937-41. PubMed
- Lewis JR, Radavelli-Bagatini S, Rejnmark L, et al. The effects of calcium supplementation on verified coronary heart disease hospitalization and death in postmenopausal women: a collaborative meta-analysis of randomized controlled trials. J Bone Miner Res PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Lappe J, Watson P, Travers-Gustafson D, Recker R, Garland C, Gorham E, Baggerly K, McDonnell SL. Effect of Vitamin D and Calcium Supplementation on Cancer Incidence in Older Women: A Randomized Clinical Trial. JAMA. 2017 Mar 28;317(12):1234-1243. PubMed
- Grove ML, Cook D. Calcium and heart attacks. Doesn't apply to most calcium prescriptions. BMJ. 2010;341:c5003. PubMed
- Insentress [package insert]. Whitehouse Station, NJ: Merck Sharp & Dohme Corp.; 2014.
- Roberts JL, Kiser JJ, Hindman JT, Meditz AL. Virologic failure with a raltegravir-containing antiretroviral regimen and concomitant calcium administration. Pharmacotherapy 2011;31(10):298e-302e. DOI
- Vitekta [package insert]. Foster City, CA: Gilead Sciences, Inc.; 2014.
- Storan ER, O'Gorman SM, Murphy A, Laing M. Case Report of Calciphylaxis Secondary to Calcium and Vitamin D<sub>3</sub> Supplementation. J Cutan Med Surg. 2017;21(2):162-163. DOI
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Borkenhagen JF, Connor EL, Stafstrom CE. Neonatal hypocalcemic seizures due to excessive maternal calcium ingestion. Pediatr Neurol 2013;48(6):469-71. PubMed
- WHO recommendations on antenatal care for a positive pregnancy experience. Geneva: World Health Organization; 2016 (http://www.who.int/reproductivehealth/publications/maternal_perinatal_health/ anc-positive-pregnancy-experience/en/).
- Aune D, Navarro Rosenblatt DA, Chan DS, et al. Dairy products, calcium, and prostate cancer risk: a systematic review and meta-analysis of cohort studies. Am J Clin Nutr. 2015;101(1):87-117. PubMed
- Lan T, Park Y, Colditz GA, et al. Adolescent dairy product and calcium intake in relation to later prostate cancer risk and mortality in the NIH-AARP Diet and Health Study. Cancer Causes Control. 2020;31(10):891-904. PubMed
- Zhang Y, Li Y, Liu J, et al. Association of Vitamin D or Calcium Supplementation with Cardiovascular Outcomes and Mortality: A Meta-Analysis with Trial Sequential Analysis. J Nutr Health Aging 2021;25(2):263-270. PubMed
- Myung SK, Kim HB, Lee YJ, Choi YJ, Oh SW. Calcium Supplements and Risk of Cardiovascular Disease: A Meta-Analysis of Clinical Trials. Nutrients 2021;13(2):368. PubMed
- Hetaimish B. Neonatal Calcinosis Cutis After Treatment of Hypocalcemia with Calcium Gluconate: A Report of 2 Cases. Am J Case Rep 2024;25:e943397. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Iron 72 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Bruner AB, Joffe A, Duggan AK, et al. Randomized study of cognitive effects of iron supplementation in non- anaemic iron-deficient adolescent girls. Lancet 1996;348:992-6.
- Ullen H, Augustsson K, Gustavsson C, Steineck G. Supplementary iron intake and risk of cancer: reversed causality? Cancer Lett 1997;114:215-6.
- Reunanen A, Takkunen H, Knekt P, et al. Body iron stores, dietary iron intake and coronary heart disease mortality. J Intern Med 1995;238:223-30. PubMed
- Lund EK, Wharf SG, Fairweather-Tait SJ, Johnson IT. Oral ferrous sulfate supplements increase the free radical-generating capacity of feces from healthy volunteers. Am J Clin Nutr 1999;69:250-5.
- Rehman A, Collis CS, Yang M, et al. The effects of iron and vitamin C co-supplementation on oxidative damage to DNA in healthy volunteers. Biochem Biophys Res Comm 1998;246:293-8. PubMed
- Klipstein-Grobusch K, Grobbee DE, den Breeijen JH, et al. Dietary iron and risk of myocardial infarction in the Rotterdam Study. Am J Epidemiol 1999;149:421-8. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Tatro DS, ed. Drug Interactions Facts. Facts and Comparisons Inc., St. Louis, MO. 1999.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin A, Vitamin K, Arsenic, Boron, Chromium, Copper, Iodine, Iron, Manganese, Molybdenum, Nickel, Silicon, Vanadium, and Zinc. Washington, DC: National Academy Press, 2002.
- Campbell N, Paddock V, Sundaram R. Alteration of methyldopa absorption, metabolism, and blood pressure control by ferrous sulfate and ferrous gluconate. Clin Pharmacol Ther 1988;43:381-6..
- Schumann K, Borch-Iohnsen B, Hentze MW, Marx JJ. Tolerable upper intakes for dietary iron set by the US Food and Nutrition Board (commentary). Am J Clin Nutr 2002;76:499-500. PubMed
- Tuomainen TP, Punnonen K, Nyyssonen K, Salonen JT. Association between body iron stores and the risk of acute myocardial infarction in men. Circulation 1998;97:1461-6.. PubMed
- Salonen JT, Nyyssonen K, Korpela H, et al. High stored iron levels are associated with excess risk of myocardial infarction in Eastern Finnish men. Circulation 1992;86:803-11.. PubMed
- Campbell NRC, Hasinoff B. Ferrous sulfate reduces levodopa bioavailability: Chelation as a possible mechanism. Clin Pharmacol Ther 1989;45:220-5.. PubMed
- Campbell NRC, Hasinoff BB, Stalts H, et al. Ferrous sulfate reduces thyroxine efficacy in patients with hypothyroidism. Ann Int Med 1992;117:1010-3.. PubMed
- Kiechl S, Willeit J, Egger G, et al. Body iron stores and the risk of carotid atherosclerosis: prospective results from the Bruneck study. Circulation 1997;96:3300-07. PubMed
- Comparison of oral iron supplements. Pharmacist's Letter / Prescriber's Letter 2008;24(8):240811.
- Tran T., Wax J. R., Philput C., Steinfeld J. D., Ingardia C. J. Intentional iron overdose in pregnancy--management and outcome. J Emerg Med 2000;18(2):225-228. PubMed
- Toblli J. E., Brignoli, R. Iron(III)-hydroxide polymaltose complex in iron deficiency anemia / review and meta-analysis. Arzneimittelforschung 2007;57(6A):431-438. PubMed
- Köpcke W., Sauerland M. C. Meta-analysis of efficacy and tolerability data on iron proteinsuccinylate in patients with iron deficiency anemia of different severity. Arzneimittelforschung 1995;45(11):1211-1216.
- Campbell N. R., Campbell R. R., Hasinoff B. B. Ferrous sulfate reduces methyldopa absorption: methyldopa: iron complex formation as a likely mechanism. Clin Invest Med 1990;13(6):329-332.
- Morii M., Ueno K., Ogawa A., Kato R., Yoshimura H., Wada K., Hashimoto H., Takada M., Tanaka K., Nakatani T., Shibakawa M. Impairment of mycophenolate mofetil absorption by iron ion. Clin Pharmacol Ther 2000;68(6):613-616. PubMed
- Gelone D. K., Park J. M., Lake K. D. Lack of an effect of oral iron administration on mycophenolic acid pharmacokinetics in stable renal transplant recipients. Pharmacotherapy 2007;27(9):1272-1278. PubMed
- Ducray P. S., Banken L., Gerber M., Boutouyrie B., Zandt H. Absence of an interaction between iron and mycophenolate mofetil absorption. Br J Clin Pharmacol 2006;62(4):492-495. PubMed
- Lorenz M., Wolzt M., Weigel G., Puttinger H., Hörl W. H., Födinger M., Speiser W., Sunder-Plassmann G. Ferrous sulfate does not affect mycophenolic acid pharmacokinetics in kidney transplant patients. Am J Kidney Dis 2004;43(6):1098-1103. PubMed
- Osman M. A., Patel R. B., Schuna A., Sundstrom W. R., Welling P. G. Reduction in oral penicillamine absorption by food, antacid, and ferrous sulfate. Clin Pharmacol Ther 1983;33(4):465-470. PubMed
- Michael, B., Coyne, D. W., Fishbane, S., Folkert, V., Lynn, R., Nissenson, A. R., Agarwal, R., Eschbach, J. W., Fadem, S. Z., Trout, J. R., Strobos, J., and Warnock, D. G. Sodium ferric gluconate complex in hemodialysis patients: adverse reactions compar
- Zhang, X., Ouyang, J., Wieczorek, R., and DeSoto, F. Iron medication-induced gastric mucosal injury. Pathol.Res Pract 2009;205(8):579-581. PubMed
- Barbieri, P. G. [To-day exposure to occupational carcinogens and their effects. The experience of the rubber industry, iron metallurgy, asphalt work and aviculture]. Epidemiol.Prev 2009;33(4-5 Suppl 2):94-105.
- Macedo, A. and Cardoso, S. [Routine iron supplementation in pregnancy]. Acta Med Port. 2010;23(5):785-792.
- Bastide, N. M., Pierre, F. H., and Corpet, D. E. Heme iron from meat and risk of colorectal cancer: a meta-analysis and a review of the mechanisms involved. Cancer Prev Res (Phila) 2011;4(2):177-184. PubMed
- Stevens, R. G. Iron and the risk of cancer. Med Oncol Tumor Pharmacother. 1990;7(2-3):177-181. PubMed
- van den, Hombergh J., Dalderop, E., and Smit, Y. Does iron therapy benefit children with severe malaria-associated anaemia? A clinical trial with 12 weeks supplementation of oral iron in young children from the Turiani Division, Tanzania. J.Trop.Pediatr. PubMed
- Liabeuf S, Gras V, Moragny J, et al. Ulceration of the oral mucosa following direct contact with ferrous sulfate in elderly patients: a case report and a review of the French National Pharmacovigilance Database. Clin Interv Aging. 2014 Apr 25;9:737-40. PubMed
- Qiao L, Feng Y. Intakes of heme iron and zinc and colorectal cancer incidence: a meta-analysis of prospective studies. Cancer Causes Control. 2013 Jun;24(6):1175-83. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Guidelines for the Use of Antiretroviral Agents in HIV-1-Infected Adults and Adolescents: Drug Interactions between Integrase Inhibitors and Other Drugs. AIDSinfo. July 14, 2016. Available at: https://aidsinfo.nih.gov/guidelines/html/1/adult-and-adolescen
- Song I, Borland J, Arya N, Wynne B, Piscitelli S. Pharmacokinetics of dolutegravir when administered with mineral supplements in healthy adult subjects. J Clin Pharmacol. 2015;55(5):490-6. PubMed
- Esan MO, Boele van Hensbroek M, Nkhoma E, et al. Iron supplementation in HIV infected Malawian children with anemia: a double-blind, randomized, controlled trial. Clin Inf Dis 2013;57(11):1626-34.doi:10.1093/cid/cit528. PubMed
- Zlotkin S, Newton S, Aimone AM, et al. Effect of iron fortification on malaria incidence in infants and young children in Ghana: a randomized trial. JAMA 2013;310(9):938-47. PubMed
- Khambalia AZ, Aimone A, Nagubandi P, et al. High maternal iron status, dietary iron intake and iron supplement use in pregnancy and risk of gestational diabetes mellitus: a prospective study and systematic review. Diabet Med. 2016;33(9):1211-21. PubMed
- Kinnunen TI, Luoto R, Helin A, Hemminki E. Supplemental iron intake and the risk of glucose intolerance in pregnancy: re-analysis of a randomised controlled trial in Finland. Matern Child Nutr. 2016;12(1):74-84.
- Low MS, Speedy J, Styles CE, De-Regil LM, Pasricha SR. Daily iron supplementation for improving anaemia, iron status and health in menstruating women. Cochrane Database Syst Rev. 2016;4:CD009747. PubMed
- Melit LE, Marginean CO, Mocanu S, Marginean MO. A rare case of iron-pill induced gastritis in a female teenager: A case report and a review of the literature. Medicine (Baltimore). 2017;96(30):e7550. PubMed
- Neuberger A, Okebe J, Yahav D, Paul M. Oral iron supplements for children in malaria-endemic areas. Cochrane Database Syst Rev. 2016;2:CD006589. PubMed
- Peña-Rosas JP, De-Regil LM, Gomez Malave H, Flores-Urrutia MC, Dowswell T. Intermittent oral iron supplementation during pregnancy. Cochrane Database Syst Rev. 2015;(10):CD009997. PubMed
- Brabin B, Gies S, Roberts SA, et al. Excess risk of preterm birth with periconceptional iron supplementation in a malaria endemic area: analysis of secondary data on birth outcomes in a double blind randomized controlled safety trial in Burkina Faso. Mala PubMed
- Kaundal R, Bhatia P, Jain A, et al. Randomized controlled trial of twice-daily versus alternate-day oral iron therapy in the treatment of iron-deficiency anemia. Ann Hematol 2020;99(1):57-63. PubMed
- Li N, Zhao G, Wu W, et al. The efficacy and safety of vitamin C for iron supplementation in adult patients with iron deficiency anemia: A randomized clinical trial. JAMA Netw Open. 2020;3(11):e2023644.<br> PubMed
- Houston BL, Hurrie D, Graham J, et al. Efficacy of iron supplementation on fatigue and physical capacity in non-anaemic iron-deficient adults: a systematic review of randomised controlled trials. BMJ Open. 2018;8(4):e019240. PubMed
- Koch RM, Tchernodrinski S, Principe DR. Case report: Rapid onset, ischemic-type gastritis after initiating oral iron supplementation. Front Med (Lausanne) 2022;9:1010897. PubMed
- Milman NT. Iron supplementation in pregnant Danish women revisited: Effects on prepartum and postpartum iron deficiency, anemia, serum erythropoietin; including iron status, erythropoietin and anthropometrics in newborns. A randomized, placebo-controlled
- Rogozinska E, Daru J, Nicolaides M, et al. Iron preparations for women of reproductive age with iron deficiency anaemia in pregnancy (FRIDA): a systematic review and network meta-analysis. Lancet Haematol 2021;8(7):e503-e512. PubMed
- Shah AA, Donovan K, Seeley C, et al. Risk of infection associated with administration of intravenous iron: A systematic review and meta-analysis. JAMA Netw Open 2021;4(11):e2133935. PubMed
- Gamad N, Saha PK, Sharma P, Suri V, Chakrabarti A, Saha L. A randomized controlled trial comparing the efficacy, tolerability, and cost of oral iron preparations in iron-deficiency anemia in pregnancy. J Obstet Gynaecol Res 2021;47(11):3828-3841. PubMed
- El-Hawy MA, Abd Al-Salam SA, Bahbah WA. Comparing oral iron bisglycinate chelate, lactoferrin, lactoferrin with iron and iron polymaltose complex in the treatment of children with iron deficiency anemia. Clin Nutr ESPEN 2021;46:367-371. PubMed
- Adams A, Scheckel B, Habsaoui A, et al. Intravenous iron versus oral iron versus no iron with or without erythropoiesis- stimulating agents (ESA) for cancer patients with anaemia: a systematic review and network meta-analysis. Cochrane Database Syst Rev 2 PubMed
- Kancherla K, Constantin H, Kanawati A, Graham E. Iron-induced Hypophosphatemic Osteomalacia-An Atypical Case of Bilateral Femoral Stress Fractures. J Am Acad Orthop Surg Glob Res Rev 2023;7(5):e22. PubMed
- Shi R, Marin JG, Beaulieu M. Skin staining following intravenous iron extravasation in a patient with chronic kidney disease: A case report. Can J Kidney Health Dis 2023;10:20543581231165705. PubMed
- Varandas C, Vieira J, Correia CJ, et al. Hypersensitivity reactions to iron products: 10-year experience in a Portuguese tertiary Centre. Eur Ann Allergy Clin Immunol 2023.
- Jara Vidal M, López García MC, Quílez Toboso RP. Kounis syndrome after intravenous iron administration. Med Clin (Barc) 2023. DOI
- Jara Vidal M, Ruiz de Assín Valverde A, Aznar Rodríguez S. Severe hypophospathemia secondary to intravenous iron. Med Clin (Barc) 2023. DOI
- Samões B, Silva B, Martins A, et al. Hypophosphatemic osteomalacia induced by intravenous iron therapy: a case report. Joint Bone Spine 2023;90(5):105586. PubMed
- Seng NW, Barco JB, Wong MH, et al. Hypophosphatemia related to intravenous iron therapy with ferric carboxymaltose: A case series. Transfus Med 2023. PubMed
- Fernandez-Flores A, Fernandez-Parrado M, Alzoghby-Abi Chaker J, Angulo AG. Axillary cutaneous hemosiderosis in a patient with hyperhidrosis, after intravenous iron infusion. Am J Dermatopathol 2023;45(7):463-465. PubMed
- Ye S, Grill V, Luo J, Nguyen HH. Concurrent Denosumab and Parenteral Iron Therapy Precipitating Severe Hypocalcemia and Hypophosphatemia. JCEM Case Rep 2024;2(2):luae005. PubMed
- Yerigeri K. Hemochromatosis in an Adult Female With Previous Iron Deficiency Anemia on Iron Supplementation. Cureus 2023;15(12):e50166. PubMed
- Meyers M, Salmon M, Libert I, Klášterský J. A meta-analysis on the risk of infection associated with intravenous iron therapy in cancer-associated anaemia: a double-edged sword?. Curr Opin Oncol 2024;36(4):223-232. PubMed
- Short V, Allen R, Earley CJ, et al. A randomized double-blind pilot study to evaluate the efficacy, safety, and tolerability of intravenous iron versus oral iron for the treatment of restless legs syndrome in patients with iron deficiency anemia. Am J Hem PubMed
- Bellos I, Frountzas M, Pergialiotis V. Comparative Risk of Hypophosphatemia Following the Administration of Intravenous Iron Formulations: A Network Meta-Analysis. Transfus Med Rev 2020;34(3):188-194. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Magnesium 82 references
- Rodin SM, Johnson BF. Pharmacokinetic interactions with digoxin. Clin Pharmacokinet 1988;15:227-44.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Dahle LO, Berg G, Hammar M, et al. The effect of oral magnesium substitution on pregnancy-induced leg cramps. Am J Obstet Gynecol 1995;173:175-80. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Peikert A, Wilimzig C, Kohne-Volland R. Prophylaxis of migraine with oral magnesium: results from a prospective, multi-center, placebo-controlled and double-blind randomized study. Cephalalgia 1996;16:257-63. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Calcium, Phosphorus, Magnesium, Vitamin D, and Fluoride. Washington, DC: National Academy Press, 1999. Available at: http://books.nap.edu/books/0309063507/html/index.html.
- Birrer RB, Shallash AJ, Totten V. Hypermagnesemia-induced fatality following epsom salt gargles. J Emerg Med 2002;22:185-8. PubMed
- Ryan MP. Diuretics and potassium/magnesium depletion. Directions for treatment. Am J Med 1987;82:38-47.. PubMed
- Hollifield JW. Magnesium depletion, diuretics, and arrhythmias. Am J Med 1987;82:30-7.. PubMed
- Heidenreich O. Mode of action of conventional and potassium-sparing diuretics--aspects with relevance to Mg-sparing effects. Magnesium 1984;3:248-56..
- Pfaffenrath V, Wessely P, Meyer C, et al. Magnesium in the prophylaxis of migraine--a double-blind placebo-controlled study. Cephalalgia 1996;16:436-40.. PubMed
- Wang F, Van Den Eeden SK, Ackerson LM, et al. Oral magnesium oxide prophylaxis of frequent migrainous headache in children: a randomized, double-blind, placebo-controlled trial. Headache 2003;43:601-10.. PubMed
- Sompolinsky D, Samra Z. Influence of magnesium and manganese on some biological and physical properties of tetracycline. J Bacteriol 1972;110:468-76.. PubMed
- Jeyabalan A, Caritis SN. Pharmacologic inhibition of preterm labor. Clin Obstet Gynecol 2002;45:99-113. PubMed
- Mittendorf R, Dambrosia J, Pryde PG, et al. Association between the use of antenatal magnesium sulfate in preterm labor and adverse health outcomes in infants. Am J Obstet Gynecol 2002;186:1111-8.. PubMed
- Witlin AG, Sibai BM. Magnesium sulfate therapy in preeclampsia and eclampsia. Obstet Gynecol 1998;92:883-9.. DOI
- Crowther CA, Hiller JE, Doyle LW. Magnesium sulphate for preventing preterm birth in threatened preterm labour. Cochrane Database Syst Rev 2002;4:CD001060. . PubMed
- Davey MJ, Teubner D. A randomized controlled trial of magnesium sulfate, in addition to usual care, for rate control in atrial fibrillation. Ann Emerg Med 2005;45:347-53.. PubMed
- L'Hommedieu CS, Nicholas D, Armes DA, et al. Potentiation of magnesium sulfate--induced neuromuscular weakness by gentamicin, tobramycin, and amikacin. J Pediatr 1983;102:629-31..
- Dunn CJ, Goa KL. Risedronate: a review of its pharmacological properties and clinical use in resorptive bone disease. Drugs 2001;61:685-712..
- Kass L, Weekes J, Carpenter L. Effect of magnesium supplementation on blood pressure: a meta-analysis. Eur J Clin Nutr 2012;66:411-8. PubMed
- Koontz SL, Friedman SA, Schwartz ML. Symptomatic hypocalcemia after tocolytic therapy with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 2004;190(6):1773-6. PubMed
- Snyder SW, Cardwell MS. Neuromuscular blockade with magnesium sulfate and nifedipine. Am J Obstet Gynecol. 1989;161(1):35-6. PubMed
- Waisman GD, Mayorga LM, Cámera MI, et al. Magnesium plus nifedipine: potentiation of hypotensive effect in preeclampsia? Am J Obstet Gynecol. 1988;159(2):308-9. PubMed
- Brown DD, Juhl RP. Decreased bioavailability of digoxin due to antacids and kaolin-pectin. N Engl J Med. 1976;295(19):1034-7. PubMed
- Allen MD, Greenblatt DJ, Harmatz JS, et al. Effect of magnesium--aluminum hydroxide and kaolin--pectin on absorption of digoxin from tablets and capsules. J Clin Pharmacol. 1981;21(1):26-30. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an in vitro study. Thromb Haemost. 1996;76(1):88-93. DOI
- Ravn HB, Kristensen SD, Vissinger H, et al. Magnesium inhibits human platelets. Blood Coagul Fibrinolysis. 1996;7(2):241-4. PubMed
- Ravn HB, Vissinger H, Kristensen SD, et al. Magnesium inhibits platelet activity--an infusion study in healthy volunteers. Thromb Haemost. 1996;75(6):939-44. DOI
- Neuvonen PJ, Kivistö KT. The effects of magnesium hydroxide on the absorption and efficacy of two glibenclamide preparations. Br J Clin Pharmacol. 1991;32(2):215-20. PubMed
- Kivistö KT, Neuvonen PJ. Enhancement of absorption and effect of glipizide by magnesium hydroxide. Clin Pharmacol Ther. 1991;49(1):39-43. PubMed
- Neuvonen PJ, Kivistö KT. Enhancement of drug absorption by antacids. An unrecognised drug interaction. Clin Pharmacokinet. 1994;27(2):120-8. PubMed
- Shechter, M., Merz, C. N., Paul-Labrador, M., Meisel, S. R., Rude, R. K., Molloy, M. D., Dwyer, J. H., Shah, P. K., and Kaul, S. Beneficial antithrombotic effects of the association of pharmacological oral magnesium therapy with aspirin in coronary heart
- Ganzevoort, J. W., Hoogerwaard, E. M., and van der Post, J. A. [Hypocalcemic delirium due to magnesium sulphate therapy in a pregnant woman with pre-eclampsia]. Ned.Tijdschr.Geneeskd. 8-3-2002;146(31):1453-1456.
- Horner, S. M. Efficacy of intravenous magnesium in acute myocardial infarction in reducing arrhythmias and mortality. Meta-analysis of magnesium in acute myocardial infarction. Circulation 1992;86(3):774-779. PubMed
- Azria, E., Tsatsaris, V., Goffinet, F., Kayem, G., Mignon, A., and Cabrol, D. [Magnesium sulfate in obstetrics: current data]. J Gynecol.Obstet.Biol.Reprod.(Paris) 2004;33(6 Pt 1):510-517.
- Magee, L. A., Miremadi, S., Li, J., Cheng, C., Ensom, M. H., Carleton, B., Cote, A. M., and von Dadelszen, P. Therapy with both magnesium sulfate and nifedipine does not increase the risk of serious magnesium-related maternal side effects in women with p
- Henyan, N. N., Gillespie, E. L., White, C. M., Kluger, J., and Coleman, C. I. Impact of intravenous magnesium on post-cardiothoracic surgery atrial fibrillation and length of hospital stay: a meta-analysis. Ann.Thorac.Surg. 2005;80(6):2402-2406. PubMed
- Li, J., Zhang, Q., Zhang, M., and Egger, M. Intravenous magnesium for acute myocardial infarction. Cochrane.Database.Syst.Rev. 2007;(2):CD002755. PubMed
- Doyle, L. W., Crowther, C. A., Middleton, P., Marret, S., and Rouse, D. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane.Database.Syst.Rev. 2009;(1):CD004661. PubMed
- Han, S., Crowther, C. A., and Moore, V. Magnesium maintenance therapy for preventing preterm birth after threatened preterm labour. Cochrane.Database.Syst.Rev. 2010;(7):CD000940. PubMed
- Duley, L., Gulmezoglu, A. M., Henderson-Smart, D. J., and Chou, D. Magnesium sulphate and other anticonvulsants for women with pre-eclampsia. Cochrane.Database.Syst.Rev. 2010;(11):CD000025. PubMed
- Conde-Agudelo, A., Romero, R., and Kusanovic, J. P. Nifedipine in the management of preterm labor: a systematic review and metaanalysis. Am J Obstet.Gynecol. 2011;204(2):134-20. PubMed
- Wong, G. K., Boet, R., Poon, W. S., Chan, M. T., Gin, T., Ng, S. C., and Zee, B. C. Intravenous magnesium sulphate for aneurysmal subarachnoid hemorrhage: an updated systemic review and meta-analysis. Crit Care 2011;15(1):R52. PubMed
- Magee, L., Sawchuck, D., Synnes, A., and von, Dadelszen P. SOGC Clinical Practice Guideline. Magnesium sulphate for fetal neuroprotection. J Obstet.Gynaecol.Can. 2011;33(5):516-529.
- Doyle, L. W. Antenatal magnesium sulfate and neuroprotection. Curr Opin Pediatr 2012;24(2):154-159. PubMed
- McDonald, S. D., Lutsiv, O., Dzaja, N., and Duley, L. A systematic review of maternal and infant outcomes following magnesium sulfate for pre-eclampsia/eclampsia in real-world use. Int J Gynaecol.Obstet. 2012;118(2):90-96. PubMed
- Gordon, M., Naidoo, K., Akobeng, A. K., and Thomas, A. G. Osmotic and stimulant laxatives for the management of childhood constipation. Cochrane.Database.Syst.Rev. 2012;7:CD009118. PubMed
- Dodd, J. M., Crowther, C. A., and Middleton, P. Oral betamimetics for maintenance therapy after threatened preterm labour. Cochrane.Database.Syst.Rev. 2012;12:CD003927. PubMed
- Wu, X., Wang, C., Zhu, J., Zhang, C., Zhang, Y., and Gao, Y. Meta-analysis of randomized controlled trials on magnesium in addition to beta-blocker for prevention of postoperative atrial arrhythmias after coronary artery bypass grafting. BMC.Cardiovasc.D PubMed
- Thorp, J. M., Jr., Katz, V. L., Campbell, D., and Cefalo, R. C. Hypersensitivity to magnesium sulfate. Am.J.Obstet.Gynecol. 1989;161(4):889-890. PubMed
- Duley L and Gulmezoglu AM. Magnesium sulphate versus lytic cocktail for eclampsia. Cochrane Database of Systematic Reviews 2000;(3) PubMed
- Gibbins KJ, Browning KR, Lopes VV, Anderson BL, Rouse DJ. Evaluation of the clinical use of magnesium sulfate for cerebral palsy prevention. Obstet Gynecol 2013;121(2 Pt 1):235-40. PubMed
- Ji D. Oral magnesium sulfate causes perforation during bowel preparation for fiberoptic colonoscopy in patients with colorectal cancer. J Emerg Med 2012;43(4):716-7. PubMed
- Yagi T, Naito T, Mino Y, Umemura K, Kawakami J. Impact of concomitant antacid administration on gabapentin plasma exposure and oral bioavailability in healthy adult subjects. Drug Metab Pharmacokinet 2012;27(2):248-54. PubMed
- Yamasaki M, Funakoshi S, Matsuda S, Imazu T, Takeda Y, Murakami T, Maeda Y. Interaction of magnesium oxide with gastric acid secretion inhibitors in clinical pharmacotherapy. Eur J Clin Pharmacol 2014;70(8):921-4. PubMed
- Choi ES, Jeong WJ, Ahn SH, Oh AY, Jeon YT, Do SH. Magnesium sulfate accelerates the onset of low-dose rocuronium in patients undergoing laryngeal microsurgery. J Clin Anesth. 2017 Feb;36:102-106. PubMed
- Ikee R, Toyoyama T, Endo T, Tsunoda M, Hashimoto N. Impact of sevelamer hydrochloride on serum magnesium concentrations in hemodialysis patients. Magnes Res. 2016 Apr 1;29(4):184-90. PubMed
- Miller ES, Sakowicz A, Leger E. Lange E, Yee LM. The association between receipt of intrapartum magnesium and postpartum hemorrhage. Am J Obstet Gynecol 2018;218(1 Suppl):S165.
- Rodríguez-Rubio L, Solis Garcia Del Pozo J, Nava E, Jordán J. Interaction between magnesium sulfate and neuromuscular blockers during the perioperative period. A systematic review and meta-analysis. J Clin Anesth. 2016;34:524-34. PubMed
- Brown RS. Magnesium Sulfate: Another Cause of a Solute Diuresis. Am J Kidney Dis. 2017;69(4):550-551. PubMed
- Park H, Qin R, Smith TJ, et al. North Central Cancer Treatment Group N10C2 (Alliance): a double-blind placebo-controlled study of magnesium supplements to reduce menopausal hot flashes. Menopause. 2015;22(6):627-32. PubMed
- Sakanoue M, Sanada J, Kanekura T. Skin eruption elicited by magnesium oxide (Maglax). J Dermatol. 2016;43(2):221-2.
- Iwamuro M, Saito S, Yoshioka M, et al. A Magnesium Oxide Bezoar. Intern Med. 2018;57(21):3087-3091. PubMed
- Vilchez G, Dai J, Kumar K, Mundy D, Kontopoulos E, Sokol RJ. Racial/ethnic disparities in magnesium sulfate neuroprotection: a subgroup analysis of a multicenter randomized controlled trial. J Matern Fetal Neonatal Med. 2018;31(17):2304-2311. PubMed
- Drug Safety Communication: FDA Recommends Against Prolonged Use of Magnesium Sulfate to Stop Pre-term Labor Due to Bone Changes in Exposed Babies. U.S. Food and Drug Administration (FDA), May 30, 2013. https://www.fda.gov/downloads/Drugs/DrugSafety/UCM353
- Committee Opinion: Magnesium Sulfate Use in Obstetrics. The American College of Obstetricians and Gynecologists Committee on Obstetric Practice Society for Maternal-Fetal Medicine, Number 652, January 2016. https://www.acog.org/Clinical-Guidance-and-Publi
- Kashihara Y, Terao Y, Yoda K, et al. Effects of magnesium oxide on pharmacokinetics of L-dopa/carbidopa and assessment of pharmacodynamic changes by a model-based simulation. Eur J Clin Pharmacol. 2019;75(3):351-361. PubMed
- Shepherd E, Salam RA, Manhas D, et al. Antenatal magnesium sulphate and adverse neonatal outcomes: A systematic review and meta-analysis. PLoS Med. 2019;16(12):e1002988. PubMed
- Hong JY, Hong JY, Choi YS, et al. Antenatal magnesium sulfate treatment and risk of necrotizing enterocolitis in preterm infants born at less than 32 weeks of gestation. Sci Rep. 2020;10(1):12826. PubMed
- Schuh S, Sweeney J, Rumantir M, et al. Effect of nebulized magnesium vs placebo added to albuterol on hospitalization among children with refractory acute asthma treated in the emergency department: a randomized clinical trial. JAMA. 2020;324(20):2038-20 PubMed
- Almeida CED, Carvalho LR, Andrade CVC, Nascimento PD Jr, Barros GAM, Modolo NSP. Effects of magnesium sulphate on the onset time of rocuronium at different doses: a randomized clinical trial. Braz J Anesthesiol. 2021;71(5):482-8. PubMed
- Gochi Valdovinos A, Arriaga-Redondo M, Dejuan Bitriá E, Pérez Rodríguez I, Márquez Isidro E, Blanco Bravo D. Prenatal therapy with magnesium sulphate and intestinal obstruction due to meconium in preterm newborns. An Pediatr (Engl Ed). 2022 Feb;96(2):138- PubMed
- Iio K, Kondo E, Shibata E, et al. Long-term tocolysis with magnesium sulfate as a risk factor for low bone mass: a case series. J Med Cases. 2022 Feb;13(2):47-50. PubMed
- Eiraku K, Uozumi Y, Hieda M, Maruyama T, Nomura H. A senile case of heart failure associated with hypermagnesemia induced by magnesium-containing laxative agent. Geriatr Gerontol Int. 2022;22(10):897-899.
- Enayati A, Gin JH, Sajeev JK, et al. Efficacy of intravenous magnesium for the management of non-post operative atrial fibrillation with rapid ventricular response: A systematic review and meta-analysis. J Cardiovasc Electrophysiol 2023;34(5):1286-1295. PubMed
- Su YH, Luo DC, Pang Y. Effects of intraoperative Magnesium sulfate infusion on emergency agitation during general anesthesia in patients undergoing radical mastectomy: a randomized controlled study. BMC Anesthesiol 2023;23(1):326. PubMed
- Han J, Park HY, Shin HJ, Chung SH, Do SH. Effects of magnesium sulphate on neostigmine-induced recovery from moderate neuromuscular blockade with rocuronium: a randomized controlled trial. Magnes Res 2023;36(2):31-39. PubMed
- Lee AT, Cordova JC, Jamplis RP, Pomicter GR. Posterior Reversible Encephalopathy Syndrome and Eclampsia in the Setting of Magnesium Toxicity: A Case Report. A A Pract 2023;17(11):e01726. PubMed
- Darmawan D, Rengganis I, Rumende CM, et al. Effectiveness and Safety of Nebulized Magnesium as Last Line Treatment in Adults with Acute Asthma Attack: A Systematic Review and Meta-Analysis. Acta Med Indones 2024;56(1):3-12.
- Shepherd ES, Goldsmith S, Doyle LW, et al. Magnesium sulphate for women at risk of preterm birth for neuroprotection of the fetus. Cochrane Database Syst Rev 2024;5(5):CD004661. PubMed
- US Food and Drug Administration (FDA). Biktarvy Prescribing Information. October 2024. Available at: https://www.accessdata.fda.gov/drugsatfda_docs/label/2024/210251Orig1s020lbl.pdf. Accessed July 16, 2025.
Black Psyllium 18 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Covington TR, et al. Handbook of Nonprescription Drugs. 11th ed. Washington, DC: American Pharmaceutical Association, 1996.
- Etman M. Effect of a bulk forming laxative on the bioavailablility of carbamazepine in man. Drug Dev Ind Pharm 1995;21:1901-6.
- Perlman BB. Interaction between lithium salts and ispaghula husk. Lancet 1990;335:416.
- Vaswani SK, Hamilton RG, Valentine MD, Adkinson NF. Psyllium laxative-induced anaphylaxis, asthma, and rhinitis. Allergy 1996;51:266-8. PubMed
- Lantner RR, Espiritu BR, Zumerchik P, Tobin MC. Anaphylaxis following ingestion of a psyllium-containing cereal. JAMA 1990;264:2534-6. DOI
- Kaplan MJ. Anaphylactic reaction to "Heartwise." N Engl J Med 1990;323:1072-3. DOI
- Nordstrom M, Melander A, Robertsson E, Steen B. Influence of wheat bran and of a bulk-forming ispaghula cathartic on the bioavailability of digoxin in geriatric in-patients. Drug Nutr Interact 1987;5:67-9..
- Robinson DS, Benjamin DM, McCormack JJ. Interaction of warfarin and nonsystemic gastrointestinal drugs. Clin Pharmacol Ther 1971;12:491-5. PubMed
- Garcia JJ, Fernandez N, Diez MJ, et al. Influence of two dietary fibers in the oral bioavailability and other pharmacokinetic parameters of ethinyloestradiol. Contraception 2000;62:253-7. PubMed
- Fernandez N, Lopez C, Díez R, et al. Drug interactions with the dietary fiber Plantago ovata husk. Expert Opin Drug Metab Toxicol 2012;8(11):1377-86.
- Semen plantaginis in: WHO Monographs on Selected Medicinal Plants, volume 1. World Health Organization, Geneva, 1999. Available at http://apps.who.int/medicinedocs/en/d/Js2200e/. Accessed November 26, 1026.
- Code of Federal Regulations, Title 21 (21CFR 101.17). Food labeling warning, notice, and safe handling statements. Available at www.ecfr.gov/cgi-bin/text-idx?SID=20f647d3b74161501f46564b915b4048&mc=true&node=se21.2.101_117&rgn=div8. Accessed December 3, 2
- Code of Federal Regulations, Title 21 (21CFR 201.319). Specific labeling requirements - water-soluble gums, hydrophilic gums, and hydrophilic mucilloids. Available at www.accessdata.fda.gov/scripts/cdrh/cfdocs/cfcfr/CFRSearch.cfm?fr=201.319. Accessed Dece
- Diez R, Garcia JJ, Diez MJ, Sierra M, Sahagun AM, Fernandez N. Influence of Plantago ovata husk (dietary fiber) on the bioavailability and other pharmacokinetic parameters of metformin in diabetic rabbits. BMC Complement Altern Med. 2017 Jun 7;17(1):298. PubMed
- Chiu AC, Sherman SI. Effects of pharmacological fiber supplements on levothyroxine absorption. Thyroid. 1998;8(8):667-71. PubMed
- Merrick C, Madden CA, Capurso NA. A Case of Blunted Orally Disintegrating Olanzapine Effect Due to Coadministered Psyllium. J Clin Psychiatry 2021;82(2):20cr13633. PubMed
Reishi Mushroom 17 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Tao J, Feng KY. Experimental and clinical studies on inhibitory effect of ganoderma lucidum on platelet aggregation. J Tongji Med Univ 1990;10:240-3. PubMed
- Singh AB, Gupta SK, Pereira BM, Prakash D. Sensitization to Ganoderma lucidum in patients with respiratory allergy in India. Clin Exp Allergy 1995;25:440-7.
- Lee SY, Rhee HM. Cardiovascular effects of mycelium extract of Ganoderma lucidum: inhibition of sympathetic outflow as a mechanism of its hypotensive action. Chem Pharm Bull (Tokyo) 1990;38:1359-64. PubMed
- Kwok Y, Ng KFJ, Li, CCF, et al. A prospective, randomized, double-blind, placebo-controlled study of the platelet and global hemostatic effects of Ganoderma lucidum (Ling-Zhi) in healthy volunteers. Anesth Analg 2005;101:423-6. PubMed
- Wanmuang, H., Leopairut, J., Kositchaiwat, C., Wananukul, W., and Bunyaratvej, S. Fatal fulminant hepatitis associated with Ganoderma lucidum (Lingzhi) mushroom powder. J Med Assoc Thai. 2007;90(1):179-181.
- Seto, S. W., Lam, T. Y., Tam, H. L., Au, A. L., Chan, S. W., Wu, J. H., Yu, P. H., Leung, G. P., Ngai, S. M., Yeung, J. H., Leung, P. S., Lee, S. M., and Kwan, Y. W. Novel hypoglycemic effects of Ganoderma lucidum water-extract in obese/diabetic (+db/+db
- Chu, T. T., Benzie, I. F., Lam, C. W., Fok, B. S., Lee, K. K., and Tomlinson, B. Study of potential cardioprotective effects of Ganoderma lucidum (Lingzhi): results of a controlled human intervention trial. Br.J.Nutr. 2012;107(7):1017-1027.
- Jin, X., Ruiz, Beguerie J., Sze, D. M., and Chan, G. C. Ganoderma lucidum (Reishi mushroom) for cancer treatment. Cochrane.Database.Syst.Rev. 2012;6:CD007731.
- Kabir, Y., Kimura, S., and Tamura, T. Dietary effect of Ganoderma lucidum mushroom on blood pressure and lipid levels in spontaneously hypertensive rats (SHR). J Nutr Sci Vitaminol.(Tokyo) 1988;34(4):433-438. PubMed
- Kanmatsuse, K., Kajiwara, N., Hayashi, K., Shimogaichi, S., Fukinbara, I., Ishikawa, H., and Tamura, T. [Studies on Ganoderma lucidum. I. Efficacy against hypertension and side effects]. Yakugaku Zasshi 1985;105(10):942-947. PubMed
- Gao, Y., Lan, J., Dai, X., Ye, J., and Zhou, S. A Phase I/II Study of Ling Zhi Mushroom Ganoderma lucidum(W.Curt: Fr.) Lloyd (Aphyllophoromycetideae) Extract in Patients with Type II Diabetes Mellitus. International Journal of Medicinal Mushrooms 2004;6. DOI
- Jin H, Zhang G, Cao X, and et al. Treatment of hypertension by linzhi combined with hypotensor and its effects on arterial, arteriolar and capillary pressure and microcirculation. In: Niimi H, Xiu RJ, Sawada T, and et al. Microcirculatory Approach to Asi
- Klupp NL, Chang D, Hawke F, Kiat H, Cao H, Grant SJ, Bensoussan A. Ganoderma lucidum mushroom for the treatment of cardiovascular risk factors. Cochrane Database Syst Rev. 2015 Feb 17;2:CD007259. PubMed
- Zhao H, Zhang Q, Zhao L, Huang X, Wang J, Kang X. Spore Powder of Ganoderma lucidum Improves Cancer-Related Fatigue in Breast Cancer Patients Undergoing Endocrine Therapy: A Pilot Clinical Trial. Evid Based Complement Alternat Med. 2012;2012:809614.
- Pazzi F, Adsuar JC, Domínguez-Muñoz FJ, García-Gordillo MA, Gusi N, Collado-Mateo D. Ganoderma lucidum effects on mood and health-related quality of life in women with fibromyalgia. Healthcare (Basel) 2020;8(4):520. PubMed
- Kogure T, Koiwai A, Fukushi D, et al. Hypereosinophilia with hepatic nodule formation caused by Ganoderma lucidum. Intern Med 2021;60(24):3897-3903.
Shiitake Mushroom 67 references
- Hitosugi M, Kitamura O, Takatsu A, Yoshino Y. Autopsy case of duodenal obstruction from impacted mushroom. J Gastroenterol 1998;33:562-5. PubMed
- Hanada K, Hashimoto I. Flagellate mushroom (Shiitake) dermatitis and photosensitivity. Dermatol 1998;197:255-7. PubMed
- Levy AM, Kita H, Phillips SF, et al. Eosinophilia and gastrointestinal symptoms after ingestion of shiitake mushrooms. J Allergy Clin Immunol 1998;101:613-20. PubMed
- Murakami M, Kawabe K, Hosoi Y, et al. Decreased pulmonary perfusion in hypersensitivity pneumonitis caused by Shiitake mushroom spores. J Intern Med 1997;241:85-8. PubMed
- Matsui S, Nakazawa T, Umegae Y, Mori M. Hypersensitivity pneumonitis induced by Shiitake mushroom spores. Intern Med 1992;31:1204-6.
- Nakamura T. Shiitake (Lentinus edodes) dermatitis. Contact Dermatitis 1992;27:65-70.
- Ueda A, Obama K, Aoyama K, et al. Allergic contact dermatitis in shiitake (Lentinus edodes (Berk) Sing) growers. Contact Dermatitis 1992;26:228-33.
- Burikhanov, R. B., Wakame, K., Igarashi, Y., Wang, S., and Matsuzaki, S. Suppressive effect of active hexose correlated compound (AHCC) on thymic apoptosis induced by dexamethasone in the rat. Endocr.Regul. 2000;34(4):181-188.
- Gao, Y., Zhang, D., Sun, B., Fujii, H., Kosuna, K., and Yin, Z. Active hexose correlated compound enhances tumor surveillance through regulating both innate and adaptive immune responses. Cancer Immunol.Immunother. 2006;55(10):1258-1266. PubMed
- Ritz, B. W., Nogusa, S., Ackerman, E. A., and Gardner, E. M. Supplementation with active hexose correlated compound increases the innate immune response of young mice to primary influenza infection. J Nutr. 2006;136(11):2868-2873. PubMed
- Aviles, H., O'Donnell, P., Sun, B., and Sonnenfeld, G. Active hexose correlated compound (AHCC) enhances resistance to infection in a mouse model of surgical wound infection. Surg.Infect.(Larchmt.) 2006;7(6):527-535. PubMed
- Spierings, E. L., Fujii, H., Sun, B., and Walshe, T. A Phase I study of the safety of the nutritional supplement, active hexose correlated compound, AHCC, in healthy volunteers. J Nutr Sci Vitaminol.(Tokyo) 2007;53(6):536-539. PubMed
- Aviles, H., O'Donnell, P., Orshal, J., Fujii, H., Sun, B., and Sonnenfeld, G. Active hexose correlated compound activates immune function to decrease bacterial load in a murine model of intramuscular infection. Am J Surg. 2008;195(4):537-545. PubMed
- Ritz, B. W. Supplementation with active hexose correlated compound increases survival following infectious challenge in mice. Nutr.Rev. 2008;66(9):526-531. PubMed
- Terakawa, N., Matsui, Y., Satoi, S., Yanagimoto, H., Takahashi, K., Yamamoto, T., Yamao, J., Takai, S., Kwon, A. H., and Kamiyama, Y. Immunological effect of active hexose correlated compound (AHCC) in healthy volunteers: a double-blind, placebo-controll
- Mach, C. M., Fugii, H., Wakame, K., and Smith, J. Evaluation of active hexose correlated compound hepatic metabolism and potential for drug interactions with chemotherapy agents. J Soc Integr.Oncol. 2008;6(3):105-109.
- Wang, S., Welte, T., Fang, H., Chang, G. J., Born, W. K., O'Brien, R. L., Sun, B., Fujii, H., Kosuna, K., and Wang, T. Oral administration of active hexose correlated compound enhances host resistance to West Nile encephalitis in mice. J Nutr. 2009;139(3 PubMed
- Sumiyoshi, Y., Hashine, K., Kakehi, Y., Yoshimura, K., Satou, T., Kuruma, H., Namiki, S., and Shinohara, N. Dietary administration of mushroom mycelium extracts in patients with early stage prostate cancers managed expectantly: a phase II study. Jpn.J Cl PubMed
- Yin, Z., Fujii, H., and Walshe, T. Effects of active hexose correlated compound on frequency of CD4+ and CD8+ T cells producing interferon-gamma and/or tumor necrosis factor-alpha in healthy adults. Hum.Immunol. 2010;71(12):1187-1190.
- Lee, W. W., Lee, N., Fujii, H., and Kang, I. Active Hexose Correlated Compound promotes T helper (Th) 17 and 1 cell responses via inducing IL-1beta production from monocytes in humans. Cell Immunol. 2012;275(1-2):19-23.
- Daddaoua, A., Martinez-Plata, E., Ortega-Gonzalez, M., Ocon, B., Aranda, C. J., Zarzuelo, A., Suarez, M. D., de Medina, F. S., and Martinez-Augustin, O. The nutritional supplement Active Hexose Correlated Compound (AHCC) has direct immunomodulatory actio
- Roman, B. E., Beli, E., Duriancik, D. M., and Gardner, E. M. Short-term supplementation with active hexose correlated compound improves the antibody response to influenza B vaccine. Nutr Res. 2013;33(1):12-17. PubMed
- Uno, K., Kosuna, K., Sun, B., Fujii, H., Wakame, K., Chikumaru, S., Hosokawa, G., and Ueda, Y. Active Hexose Correlated Compound (AHCC) Improves Immunological Parameters and Performance Status of Patients with Solid Tumors. Biotherapy 2000;14(3):303-309.
- Ghoneum, M., Wimbley, M., Salem, F., McKlain, A., Attallah, N., and Gill, G. Immunomodulatory and anticancer effects of active hexose correlated compound (AHCC). Int J Immunother 1995;11:23-28.
- Thaiudom, S., Piyaniran, W., and Chutaputthi, A. A study of the efficacy of Active Hexose Correlated Compound (AHCC) in the treatment of chronic Hepatitis C patients at Phramongkutklao Hospital. The Medical News (Thailand) 2010;325:13-16.
- Smith, J. A., Hunter, R. J., Fujii, H., Wakame, K., and Wolf, J. Defining Synergistic Activity ofthe Combination of Active Hexose Correlated Compound (AHCC) with Liposomal Doxorubicin (Doxil). Presented at the 18th International Congress on Nutrition and
- Sia, G. M. and Candlish, J. K. Effects of shiitake (Lentinus edodes) extract on human neutrophils and the U937 monocytic cell line. Phytother.Res. 1999;13(2):133-137. DOI
- Fujiwara, K., Sato, T., Yonei, T., Genba, K., Nogami, N., and Yamadori, I. [A case of chronic hypersensitivity pneumonitis induced by shiitake mushroom spores]. Nihon Kokyuki.Gakkai Zasshi 2000;38(12):908-913.
- Lippert, U., Martin, V., Schwertfeger, C., Junghans, V., Ellinghaus, B., and Fuchs, T. Shiitake dermatitis. Br.J Dermatol. 2003;148(1):178-179.
- Lobanok, A. G., Babitskaia, V. G., Plenina, L. V., Puchkova, T. A., and Osadchaia, O. V. [Composition and biological activity of submerged mycelium of the xylotrophic basidiomycete Lentinus edodes]. Prikl.Biokhim.Mikrobiol. 2003;39(1):69-73. DOI
- Curnow, P. and Tam, M. Contact dermatitis to Shiitake mushroom. Australas.J.Dermatol. 2003;44(2):155-157. PubMed
- Mak, R. K. and Wakelin, S. H. Shiitake dermatitis: the first case reported from a European country. Br J Dermatol 2006;154(4):800-801. PubMed
- Sastre, J., Ibanez, M. D., Lopez, M., and Lehrer, S. B. Respiratory and immunological reactions among Shiitake (Lentinus edodes) mushroom workers. Clin.Exp.Allergy 1990;20(1):13-19.
- Liu, M., Li, J., Kong, F., Lin, J., and Gao, Y. Induction of immunomodulating cytokines by a new polysaccharide-peptide complex from culture mycelia of Lentinus edodes. Immunopharmacology 1998;40(3):187-198. PubMed
- Ade R, Sukut C, Wiser HJ, Shockman S, Buescher L. Shiitake dermatitis demonstrating Köebner phenomenon. Int J Dermatol. 2015;54(5):e179-81.
- Adler MJ, Larsen WG. Clinical variability of shiitake dermatitis. J Am Acad Dermatol. 2012 Oct;67(4):e140-1. PubMed
- Adriano AR, Acosta ML, Azulay DR, Quiroz CD, Talarico SR. Shiitake dermatitis: the first case reported in Brazil. An Bras Dermatol. 2013 May-Jun;88(3):417-9. PubMed
- Ampere A, Delhaes L, Soots J, Bart F, Wallaert B. Hypersensitivity pneumonitis induced by Shiitake mushroom spores. Med Mycol. 2012 Aug;50(6):654-7. PubMed
- Baran W, Batycka-Baran A, Maj J, Szepietowski JC. Shiitake dermatitis - now also in Poland. Acta Derm Venereol. 2015 Jan;95(1):102-3. PubMed
- Boels D, Landreau A, Bruneau C, et al. Shiitake dermatitis recorded by French Poison Control Centers - new case series with clinical observations. Clin Toxicol (Phila). 2014 Jul;52(6):625-8. PubMed
- Chu EY, Anand D, Dawn A, Elenitsas R, Adler DJ. Shiitake dermatitis: a report of 3 cases and review of the literature. Cutis. 2013 Jun;91(6):287-90.
- Corazza M, Zauli S, Ricci M, et al. Shiitake dermatitis: toxic or allergic reaction? J Eur Acad Dermatol Venereol. 2015 Jul;29(7):1449-51. PubMed
- Czarnecka AB, Kreft B, Marsch WCh. Flagellate dermatitis after consumption of Shiitake mushrooms. Postepy Dermatol Alergol. 2014 Jun;31(3):187-90. PubMed
- Dai X, Stanilka JM, Rowe CA, et al. Consuming Lentinula edodes (Shiitake) Mushrooms Daily Improves Human Immunity: A Randomized Dietary Intervention in Healthy Young Adults. J Am Coll Nutr. 2015;34(6):478-87.
- Hamer SE, Kulkarni K, Cohen SN. Shiitake dermatitis with oral ulceration and pustules. Clin Exp Dermatol. 2015 Apr;40(3):332-3. PubMed
- Hiernickel C, Metz S, Elsner P. Shiitake dermatitis: an impressive case report. J Dtsch Dermatol Ges. 2015 May;13(5):455-6. PubMed
- Karanovic S, George S, Topham E. Don't miss shiitake dermatitis: a case report. Br J Gen Pract. 2014 Aug;64(625):426-7. PubMed
- Kopp T, Mastan P, Mothes N, Tzaneva S, Stingl G, Tanew A. Systemic allergic contact dermatitis due to consumption of raw shiitake mushroom. Clin Exp Dermatol. 2009 Dec;34(8):e910-3. PubMed
- Lingström P, Zaura E, Hassan H, et al. The anticaries effect of a food extract (shiitake) in a short-term clinical study. J Biomed Biotechnol. 2012;2012:217164. PubMed
- Loo HV, Oon HH. Flagellate dermatitis following consumption of shiitake mushroom. Dermatol Reports. 2011 Oct 5;3(2):e21. PubMed
- Luber AJ, Ackerman LS. Flagellate shiitake mushroom dermatitis. Dermatol Online J. 2015 Aug 15;21(8). pii: 13030/qt7rm57553. DOI
- Mendonça CN, Silva PM, Avelleira JC, Nishimori FS, Cassia Fde F. Shiitake dermatitis. An Bras Dermatol. 2015 Mar-Apr;90(2):276-8.
- Netchiporouk E, Pehr K, Ben-Shoshan M, Billick RC, Sasseville D, Singer M. Pustular flagellate dermatitis after consumption of shiitake mushrooms. JAAD Case Rep. 2015 May 2;1(3):117-9. PubMed
- Nguyen AH, Gonzaga MI, Lim VM, Adler MJ, Mitkov MV, Cappel MA. Clinical features of shiitake dermatitis: a systematic review. Int J Dermatol. 2017 Jun;56(6):610-616. PubMed
- Poppe LM, Anders D, Kneitz H, Bröcker EB, Benoit S. Flagellate dermatitis caused by shiitake mushrooms. An Bras Dermatol. 2012 May-Jun;87(3):463-5. PubMed
- Pravettoni V, Primavesi L, Piantanida M. Shiitake mushroom (Lentinus edodes): a poorly known allergen in Western countries responsible for severe work-related asthma. Int J Occup Med Environ Health. 2014 Oct;27(5):871-4. PubMed
- Ricar J, Pizinger K, Cetkovska P. Shiitake dermatitis: a distinctive clinical entity. Int J Dermatol. 2013 Dec;52(12):1620-1. PubMed
- Shozushima M, Ohata K, Nonaka K, Matsuhashi N. Shiitake mushroom-induced ileus managed using double-balloon enteroscopy. Endoscopy. 2013;45 Suppl 2 UCTN:E437. PubMed
- Uslu U, Linkner RV. Shiitake mushroom dermatitis. Cutis. 2015 May;95(5):E11-2.
- Wang AS, Barr KL, Jagdeo J. Shiitake mushroom-induced flagellate erythema: A striking case and review of the literature. Dermatol Online J. 2013 Apr 15;19(4):5. DOI
- Tan J, Yuan K, Zuo J, et al. Two cases of small bowel obstruction due to a shiitake mushroom. Gastroenterol Rep (Oxf) 2019;7(4):298-300. doi: 10.1093/gastro/gox028. PubMed
- Boels D, Greillet C, Langrand J, et al. Shiitake dermatitis: experience of the Poison Control Centre Network in France from 2014 to 2019. Clin Toxicol (Phila) 2022. PubMed
- Miyagishima D, Inoue M, Kinjo K, et al. A case of bowel obstruction due to shiitake mushrooms: Diagnostic features on computed tomography. Intern Med 2022. PubMed
- Soga K, Mukai H, Kitae H. Management of shiitake mushroom-induced ileus using balloon enteroscopy. Dig Endosc 2022;34(4):e58-e59. PubMed
- Ma JY, Liu JW. Shiitake flagellate dermatitis. Mayo Clin Proc 2022;97(12):2192-2193. PubMed
- Booms A, Rashid Z, Al-Rubaie V, Bal A. Shiitake dermatitis: a case report of a rare mushroom-induced dermatitis in the United States. Int J Dermatol 2022. PubMed
- Sudy E, Urbina F. Shiitake dermatitis: clinical forms of presentation. Int J Dermatol 2023. PubMed
Lion's Mane Mushroom 6 references
- Product information for <em>Niaspan</em>. Abbott Laboratories. North Chicago, IL 60064. April 2015.
- Liang B, Guo Z, Xie F, Zhao A. Antihyperglycemic and antihyperlipidemic activities of aqueous extract of Hericium erinaceus in experimental diabetic rats. BMC Complement Altern Med. 2013;13:253. PubMed
- Mori K, Inatomi S, Ouchi K, Azumi Y, Tuchida T. Improving effects of the mushroom Yamabushitake (Hericium erinaceus) on mild cognitive impairment: a double-blind placebo-controlled clinical trial. Phytother Res. 2009;23(3):367-72.
- Mori K, Kikuchi H, Obara Y, et al. Inhibitory effect of hericenone B from Hericium erinaceus on collagen-induced platelet aggregation. Phytomedicine. 2010;17(14):1082-5. PubMed
- Li IC, Chang HH, Lin CH, et al. Prevention of early Alzheimer's disease by erinacine A-enriched Hericium erinaceus mycelia pilot double-blind placebo-controlled study. Front Aging Neurosci 2020 Jun 3;12:155. doi: 10.3389/fnagi.2020.00155. PubMed
- Tian B, Liu R, Xu T, et al. Modulating effects of Hericium erinaceus polysaccharides on the immune response by regulating gut microbiota in cyclophosphamide-treated mice. J Sci Food Agric 2023;103(6):3050-3064.
See these in context on the Lion's Mane Mushroom monograph →
Maca 1 reference
- Valerio, L. G., Jr. and Gonzales, G. F. Toxicological aspects of the South American herbs cat's claw (Uncaria tomentosa) and Maca (Lepidium meyenii) : a critical synopsis. Toxicol.Rev 2005;24(1):11-35. PubMed
Caffeine 236 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Tobias JD. Caffeine in the treatment of apnea associated with respiratory syncytial virus infection in neonates and infants. South Med J 2000;93:297-304. DOI
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Avisar R, Avisar E, Weinberger D. Effect of coffee consumption on intraocular pressure. Ann Pharmacother 2002;36:992-5.. PubMed
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Dreher HM. The effect of caffeine reduction on sleep quality and well-being in persons with HIV. J Psychosom Res 2003;54:191-8.. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Schechter MD, Timmons GD. Objectively measured hyperactivity--II. Caffeine and amphetamine effects. J Clin Pharmacol 1985;25:276-80.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Shet, M. S., McPhaul, M., Fisher, C. W., Stallings, N. R., and Estabrook, R. W. Metabolism of the antiandrogenic drug (Flutamide) by human CYP1A2. Drug Metab Dispos. 1997;25(11):1298-1303.
- Staib, A. H., Stille, W., Dietlein, G., Shah, P. M., Harder, S., Mieke, S., and Beer, C. Interaction between quinolones and caffeine. Drugs 1987;34 Suppl 1:170-174. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Fuhr, U., Strobl, G., Manaut, F., Anders, E. M., Sorgel, F., Lopez-de-Brinas, E., Chu, D. T., Pernet, A. G., Mahr, G., Sanz, F., and . Quinolone antibacterial agents: relationship between structure and in vitro inhibition of the human cytochrome P450 isof
- Kot, M. and Daniel, W. A. Effect of diethyldithiocarbamate (DDC) and ticlopidine on CYP1A2 activity and caffeine metabolism: an in vitro comparative study with human cDNA-expressed CYP1A2 and liver microsomes. Pharmacol Rep. 2009;61(6):1216-1220. PubMed
- Gasior, M., Borowicz, K., Buszewicz, G., Kleinrok, Z., and Czuczwar, S. J. Anticonvulsant activity of phenobarbital and valproate against maximal electroshock in mice during chronic treatment with caffeine and caffeine discontinuation. Epilepsia 1996;37(3 PubMed
- Jankiewicz, K., Chroscinska-Krawczyk, M., Blaszczyk, B., and Czuczwar, S. J. [Caffeine and antiepileptic drugs: experimental and clinical data]. Przegl.Lek. 2007;64(11):965-967.
- Luszczki, J. J., Zuchora, M., Sawicka, K. M., Kozinska, J., and Czuczwar, S. J. Acute exposure to caffeine decreases the anticonvulsant action of ethosuximide, but not that of clonazepam, phenobarbital and valproate against pentetrazole-induced seizures i
- Chroscinska-Krawczyk, M., Jargiello-Baszak, M., Walek, M., Tylus, B., and Czuczwar, S. J. Caffeine and the anticonvulsant potency of antiepileptic drugs: experimental and clinical data. Pharmacol.Rep. 2011;63(1):12-18. PubMed
- Vaz, J., Kulkarni, C., David, J., and Joseph, T. Influence of caffeine on pharmacokinetic profile of sodium valproate and carbamazepine in normal human volunteers. Indian J.Exp.Biol. 1998;36(1):112-114.
- Gasior, M., Swiader, M., Przybylko, M., Borowicz, K., Turski, W. A., Kleinrok, Z., and Czuczwar, S. J. Felbamate demonstrates low propensity for interaction with methylxanthines and Ca2+ channel modulators against experimental seizures in mice. Eur.J Phar PubMed
- Balogh, A., Klinger, G., Henschel, L., Borner, A., Vollanth, R., and Kuhnz, W. Influence of ethinylestradiol-containing combination oral contraceptives with gestodene or levonorgestrel on caffeine elimination. Eur.J.Clin.Pharmacol. 1995;48(2):161-166. PubMed
- Mohiuddin, M., Azam, A. T., Amran, M. S., and Hossain, M. A. In vive effects of gliclazide and metformin on the plasma concentration of caffeine in healthy rats. Pak.J Biol Sci 5-1-2009;12(9):734-737.
- Mays, D. C., Camisa, C., Cheney, P., Pacula, C. M., Nawoot, S., and Gerber, N. Methoxsalen is a potent inhibitor of the metabolism of caffeine in humans. Clin.Pharmacol.Ther. 1987;42(6):621-626. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Bailey, D. N., Weibert, R. T., Naylor, A. J., and Shaw, R. F. A study of salicylate and caffeine excretion in the breast milk of two nursing mothers. J.Anal.Toxicol. 1982;6(2):64-68. PubMed
- Griffiths, R. R. and Chausmer, A. L. Caffeine as a model drug of dependence: recent developments in understanding caffeine withdrawal, the caffeine dependence syndrome, and caffeine negative reinforcement. Nihon Shinkei Seishin Yakurigaku Zasshi 2000;20(
- Karacan, I., Thornby, J. I., Anch, M., Booth, G. H., Williams, R. L., and Salis, P. J. Dose-related sleep disturbances induced by coffee and caffeine. Clin Pharmacol Ther 1976;20(6):682-689. PubMed
- Quirce, G. S., Freire, P., Fernandez, R. M., Davila, I., and Losada, E. Urticaria from caffeine. J.Allergy Clin Immunol. 1991;88(4):680-681. PubMed
- Hughes, J. R., Higgins, S. T., Bickel, W. K., Hunt, W. K., Fenwick, J. W., Gulliver, S. B., and Mireault, G. C. Caffeine self-administration, withdrawal, and adverse effects among coffee drinkers. Arch.Gen.Psychiatry 1991;48(7):611-617. PubMed
- Adams, B. A. and Brubaker, R. F. Caffeine has no clinically significant effect on aqueous humor flow in the normal human eye. Ophthalmology 1990;97(8):1030-1031. PubMed
- Davis, R. H. Does caffeine ingestion affect intraocular pressure?. Ophthalmology 1989;96(11):1680-1681. PubMed
- Higginbotham, E. J., Kilimanjaro, H. A., Wilensky, J. T., Batenhorst, R. L., and Hermann, D. The effect of caffeine on intraocular pressure in glaucoma patients. Ophthalmology 1989;96(5):624-626.
- Wrenn, K. D. and Oschner, I. Rhabdomyolysis induced by a caffeine overdose. Ann.Emerg.Med. 1989;18(1):94-97. PubMed
- Pola, J., Subiza, J., Armentia, A., Zapata, C., Hinojosa, M., Losada, E., and Valdivieso, R. Urticaria caused by caffeine. Ann.Allergy 1988;60(3):207-208.
- Lane, J. D. and Williams, R. B., Jr. Cardiovascular effects of caffeine and stress in regular coffee drinkers. Psychophysiology 1987;24(2):157-164. PubMed
- Shirlow, M. J. and Mathers, C. D. A study of caffeine consumption and symptoms; indigestion, palpitations, tremor, headache and insomnia. Int.J.Epidemiol. 1985;14(2):239-248. PubMed
- Stillner, V., Popkin, M. K., and Pierce, C. M. Caffeine-induced delirium during prolonged competitive stress. Am.J.Psychiatry 1978;135(7):855-856. PubMed
- Levy, M. and Zylber-Katz, E. Caffeine metabolism and coffee-attributed sleep disturbances. Clin Pharmacol Ther 1983;33(6):770-775. PubMed
- Brown, S. L., Salive, M. E., Pahor, M., Foley, D. J., Corti, M. C., Langlois, J. A., Wallace, R. B., and Harris, T. B. Occult caffeine as a source of sleep problems in an older population. J.Am.Geriatr.Soc. 1995;43(8):860-864. PubMed
- Sung, B. H., Whitsett, T. L., Lovallo, W. R., al'Absi, M., Pincomb, G. A., and Wilson, M. F. Prolonged increase in blood pressure by a single oral dose of caffeine in mildly hypertensive men. Am.J Hypertens. 1994;7(8):755-758. PubMed
- Caballero, T., Garcia-Ara, C., Pascual, C., Diaz-Pena, J. M., and Ojeda, A. Urticaria induced by caffeine. J.Investig.Allergol.Clin Immunol. 1993;3(3):160-162.
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- Garrett, B. E. and Griffiths, R. R. Physical dependence increases the relative reinforcing effects of caffeine versus placebo. Psychopharmacology (Berl) 1998;139(3):195-202. PubMed
- Lane, J. D. and Phillips-Bute, B. G. Caffeine deprivation affects vigilance performance and mood. Physiol Behav. 1998;65(1):171-175. PubMed
- Boekema, P. J., Samsom, M., van Berge Henegouwen, G. P., and Smout, A. J. Coffee and gastrointestinal function: facts and fiction. A review. Scand J Gastroenterol.Suppl 1999;230:35-39. PubMed
- Terry, P., Lagergren, J., Wolk, A., and Nyren, O. Reflux-inducing dietary factors and risk of adenocarcinoma of the esophagus and gastric cardia. Nutr Cancer 2000;38(2):186-191.
- Pollak, C. P. and Bright, D. Caffeine consumption and weekly sleep patterns in US seventh-, eighth-, and ninth-graders. Pediatrics 2003;111(1):42-46. PubMed
- DiBaise, J. K. A randomized, double-blind comparison of two different coffee-roasting processes on development of heartburn and dyspepsia in coffee-sensitive individuals. Dig.Dis.Sci 2003;48(4):652-656. PubMed
- Wang, J. H., Luo, J. Y., Dong, L., Gong, J., and Tong, M. Epidemiology of gastroesophageal reflux disease: a general population-based study in Xi'an of Northwest China. World J Gastroenterol. 6-1-2004;10(11):1647-1651. PubMed
- Naliboff, B. D., Mayer, M., Fass, R., Fitzgerald, L. Z., Chang, L., Bolus, R., and Mayer, E. A. The effect of life stress on symptoms of heartburn. Psychosom.Med 2004;66(3):426-434. PubMed
- Massey, L. K. and Sutton, R. A. Acute caffeine effects on urine composition and calcium kidney stone risk in calcium stone formers. J.Urol. 2004;172(2):555-558. PubMed
- Tavani, A. and La, Vecchia C. Coffee, decaffeinated coffee, tea and cancer of the colon and rectum: a review of epidemiological studies, 1990-2003. Cancer Causes Control 2004;15(8):743-757. PubMed
- Noordzij, M., Uiterwaal, C. S., Arends, L. R., Kok, F. J., Grobbee, D. E., and Geleijnse, J. M. Blood pressure response to chronic intake of coffee and caffeine: a meta-analysis of randomized controlled trials. J Hypertens. 2005;23(5):921-928. PubMed
- Chandrasekaran, S., Rochtchina, E., and Mitchell, P. Effects of caffeine on intraocular pressure: the Blue Mountains Eye Study. J Glaucoma. 2005;14(6):504-507. PubMed
- Morgan, J. C. and Sethi, K. D. Drug-induced tremors. Lancet Neurol. 2005;4(12):866-876. PubMed
- Doan, B. K., Hickey, P. A., Lieberman, H. R., and Fischer, J. R. Caffeinated tube food effect on pilot performance during a 9-hour, simulated nighttime U-2 mission. Aviat.Space Environ Med 2006;77(10):1034-1040.
- Whalen, D. J., Silk, J. S., Semel, M., Forbes, E. E., Ryan, N. D., Axelson, D. A., Birmaher, B., and Dahl, R. E. Caffeine consumption, sleep, and affect in the natural environments of depressed youth and healthy controls. J Pediatr.Psychol. 2008;33(4):35 PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Mort, J. R. and Kruse, H. R. Timing of blood pressure measurement related to caffeine consumption. Ann Pharmacother. 2008;42(1):105-110.
- Ganmaa, D., Willett, W. C., Li, T. Y., Feskanich, D., van Dam, R. M., Lopez-Garcia, E., Hunter, D. J., and Holmes, M. D. Coffee, tea, caffeine and risk of breast cancer: a 22-year follow-up. Int J Cancer 5-1-2008;122(9):2071-2076. PubMed
- Killgore, W. D., Rupp, T. L., Grugle, N. L., Reichardt, R. M., Lipizzi, E. L., and Balkin, T. J. Effects of dextroamphetamine, caffeine and modafinil on psychomotor vigilance test performance after 44 h of continuous wakefulness. J Sleep Res 2008;17(3):3 PubMed
- Ozsungur, S., Brenner, D., and El-Sohemy, A. Fourteen well-described caffeine withdrawal symptoms factor into three clusters. Psychopharmacology (Berl) 2009;201(4):541-548. PubMed
- Ishitani, K., Lin, J., Manson, J. E., Buring, J. E., and Zhang, S. M. Caffeine consumption and the risk of breast cancer in a large prospective cohort of women. Arch Intern Med 10-13-2008;168(18):2022-2031. PubMed
- Tunnicliffe, J. M., Erdman, K. A., Reimer, R. A., Lun, V., and Shearer, J. Consumption of dietary caffeine and coffee in physically active populations: physiological interactions. Appl Physiol Nutr Metab 2008;33(6):1301-1310. PubMed
- Sin, C. W., Ho, J. S., and Chung, J. W. Systematic review on the effectiveness of caffeine abstinence on the quality of sleep. J Clin Nurs. 2009;18(1):13-21. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Killgore, W. D., Kahn-Greene, E. T., Grugle, N. L., Killgore, D. B., and Balkin, T. J. Sustaining executive functions during sleep deprivation: A comparison of caffeine, dextroamphetamine, and modafinil. Sleep 2-1-2009;32(2):205-216. PubMed
- Natale, F., Cirillo, C., Di Marco, G. M., di Vetta, L. S., Aronne, L., Siciliano, A., Mocerino, R., Tedesco, M. A., Golino, P., and Calabro, R. When chewing gum is more than just a bad habit. Lancet 5-30-2009;373(9678):1918. PubMed
- Calamaro, C. J., Mason, T. B., and Ratcliffe, S. J. Adolescents living the 24/7 lifestyle: effects of caffeine and technology on sleep duration and daytime functioning. Pediatrics 2009;123(6):e1005-e1010. PubMed
- Koran, L. M., Aboujaoude, E., and Gamel, N. N. Double-blind study of dextroamphetamine versus caffeine augmentation for treatment-resistant obsessive-compulsive disorder. J Clin Psychiatry 2009;70(11):1530-1535. PubMed
- Luebbe, A. M. and Bell, D. J. Mountain Dew or mountain don't?: a pilot investigation of caffeine use parameters and relations to depression and anxiety symptoms in 5th- and 10th-grade students. J Sch Health 2009;79(8):380-387.
- Skouroliakou, M., Bacopoulou, F., and Markantonis, S. L. Caffeine versus theophylline for apnea of prematurity: a randomised controlled trial. J Paediatr.Child Health 2009;45(10):587-592. PubMed
- Urade, Y. [Molecular mechanisms of insomnia]. Nippon Rinsho 2009;67(8):1489-1493.
- Montandon, G., Horner, R. L., Kinkead, R., and Bairam, A. Caffeine in the neonatal period induces long-lasting changes in sleep and breathing in adult rats. J Physiol 11-15-2009;587(Pt 22):5493-5507. PubMed
- Addicott, M. A. and Laurienti, P. J. A comparison of the effects of caffeine following abstinence and normal caffeine use. Psychopharmacology (Berl) 2009;207(3):423-431. PubMed
- Hashim, H. and Al, Mousa R. Management of fluid intake in patients with overactive bladder. Curr.Urol.Rep. 2009;10(6):428-433. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Chroscinska-Krawczyk, M., Ratnaraj, N., Patsalos, P. N., and Czuczwar, S. J. Effect of caffeine on the anticonvulsant effects of oxcarbazepine, lamotrigine and tiagabine in a mouse model of generalized tonic-clonic seizures. Pharmacol Rep. 2009;61(5):819 PubMed
- Attwood, A., Terry, P., and Higgs, S. Conditioned effects of caffeine on performance in humans. Physiol Behav 3-3-2010;99(3):286-293. PubMed
- Skinner, T. L., Jenkins, D. G., Coombes, J. S., Taaffe, D. R., and Leveritt, M. D. Dose response of caffeine on 2000-m rowing performance. Med Sci Sports Exerc. 2010;42(3):571-576. PubMed
- Holick, C. N., Smith, S. G., Giovannucci, E., and Michaud, D. S. Coffee, tea, caffeine intake, and risk of adult glioma in three prospective cohort studies. Cancer Epidemiol.Biomarkers Prev 2010;19(1):39-47. PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Greenwood, D. C., Alwan, N., Boylan, S., Cade, J. E., Charvill, J., Chipps, K. C., Cooke, M. S., Dolby, V. A., Hay, A. W., Kassam, S., Kirk, S. F., Konje, J. C., Potdar, N., Shires, S., Simpson, N., Taub, N., Thomas, J. D., Walker, J., White, K. L., and
- Mevcha, A., Gulur, D. M., and Gillatt, D. Diagnosing urological disorders in ageing men. Practitioner 2010;254(1726):25-9, 2.
- Brick, C. A., Seely, D. L., and Palermo, T. M. Association between sleep hygiene and sleep quality in medical students. Behav Sleep Med 2010;8(2):113-121. PubMed
- Digdon, N. L. Circadian preference and college students' beliefs about sleep education. Chronobiol.Int 2010;27(2):297-317. PubMed
- Boos, C. J., White, S. H., Bland, S. A., and McAllister, P. D. Dietary supplements and military operations: caution is advised. J R.Army Med Corps 2010;156(1):41-43. PubMed
- Casiglia, E., Bongiovi, S., Paleari, C. D., Petucco, S., Boni, M., Colangeli, G., Penzo, M., and Pessina, A. C. Haemodynamic effects of coffee and caffeine in normal volunteers: a placebo-controlled clinical study. J.Intern.Med. 1991;229(6):501-504. PubMed
- Aguggia, M. and Saracco, M. G. Pathophysiology of migraine chronification. Neurol.Sci 2010;31 Suppl 1:S15-S17. PubMed
- Torelli, P. and Manzoni, G. C. Fasting headache. Curr Pain Headache Rep. 2010;14(4):284-291.
- Farag, N. H., Whitsett, T. L., McKey, B. S., Wilson, M. F., Vincent, A. S., Everson-Rose, S. A., and Lovallo, W. R. Caffeine and blood pressure response: sex, age, and hormonal status. J Womens Health (Larchmt.) 2010;19(6):1171-1176. PubMed
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Suen, L. K., Tam, W. W., and Hon, K. L. Association of sleep hygiene-related factors and sleep quality among university students in Hong Kong. Hong.Kong.Med.J 2010;16(3):180-185.
- Stafford, L. D., Wright, C., and Yeomans, M. R. The drink remains the same: implicit positive associations in high but not moderate or non-caffeine users. Psychol.Addict.Behav. 2010;24(2):274-281. PubMed
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Freire, R. C., Perna, G., and Nardi, A. E. Panic disorder respiratory subtype: psychopathology, laboratory challenge tests, and response to treatment. Harv.Rev.Psychiatry 2010;18(4):220-229. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Kujawa-Hadrys, M., Tosik, D., and Bartel, H. Changes in thickness of each layer of developing chicken cornea after administration of caffeine. Folia Histochem.Cytobiol. 2010;48(2):273-277. PubMed
- Boggs, D. A., Palmer, J. R., Stampfer, M. J., Spiegelman, D., Adams-Campbell, L. L., and Rosenberg, L. Tea and coffee intake in relation to risk of breast cancer in the Black Women's Health Study. Cancer Causes Control 2010;21(11):1941-1948. PubMed
- Li, S., Zhu, S., Jin, X., Yan, C., Wu, S., Jiang, F., and Shen, X. Risk factors associated with short sleep duration among Chinese school-aged children. Sleep Med. 2010;11(9):907-916. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Knight, J. M., Avery, E. F., Janssen, I., and Powell, L. H. Cortisol and depressive symptoms in a population-based cohort of midlife women. Psychosom.Med. 2010;72(9):855-861. PubMed
- Porkka-Heiskanen, T. Methylxanthines and sleep. Handb.Exp.Pharmacol 2011;(200):331-348. PubMed
- Mostofsky, E., Schlaug, G., Mukamal, K. J., Rosamond, W. D., and Mittleman, M. A. Coffee and acute ischemic stroke onset: the Stroke Onset Study. Neurology 11-2-2010;75(18):1583-1588. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Li, G. Z., Zhang, N., Du, P., Yang, Y., Wu, S. L., Xiao, Y. X., Jin, R., Liu, L., Shen, H., and Dai, Y. Risk factors for interstitial cystitis/painful bladder syndrome in patients with lower urinary tract symptoms: a Chinese multi-center study. Chin Med
- Duvnjak-Zaknich, D. M., Dawson, B. T., Wallman, K. E., and Henry, G. Effect of caffeine on reactive agility time when fresh and fatigued. Med.Sci.Sports Exerc. 2011;43(8):1523-1530. PubMed
- Astorino, T. A., Martin, B. J., Schachtsiek, L., Wong, K., and Ng, K. Minimal effect of acute caffeine ingestion on intense resistance training performance. J Strength.Cond.Res 2011;25(6):1752-1758. PubMed
- Kivity, S., Ben Aharon, Y., Man, A., and Topilsky, M. The effect of caffeine on exercise-induced bronchoconstriction. Chest 1990;97(5):1083-1085. PubMed
- Lubin, F. and Ron, E. Consumption of methylxanthine-containing beverages and the risk of breast cancer. Cancer Lett. 1990;53(2-3):81-90. PubMed
- Smits, P., Lenders, J. W., and Thien, T. Caffeine and theophylline attenuate adenosine-induced vasodilation in humans. Clin.Pharmacol.Ther. 1990;48(4):410-418. PubMed
- Rossignol, A. M. and Bonnlander, H. Caffeine-containing beverages, total fluid consumption, and premenstrual syndrome. Am.J.Public Health 1990;80(9):1106-1110. PubMed
- Birkett, N. J. and Logan, A. G. Caffeine-containing beverages and the prevalence of hypertension. J Hypertens.Suppl 1988;6(4):S620-S622. PubMed
- Fraumeni, J. F., Jr., Scotto, J., and Dunham, L. J. Coffee-drinking and bladder cancer. Lancet 11-27-1971;2(7735):1204. PubMed
- Greden, J. F. Anxiety or caffeinism: a diagnostic dilemma. Am J Psychiatry 1974;131(10):1089-1092. PubMed
- Whitsett, T. L., Manion, C. V., and Christensen, H. D. Cardiovascular effects of coffee and caffeine. Am.J.Cardiol. 3-15-1984;53(7):918-922. PubMed
- Firestone, P., Poitras-Wright, H., and Douglas, V. The effects of caffeine on hyperactive children. J.Learn.Disabil. 1978;11(3):133-141. PubMed
- Thomas, F. B., Steinbaugh, J. T., Fromkes, J. J., Mekhjian, H. S., and Caldwell, J. H. Inhibitory effect of coffee on lower esophageal sphincter pressure. Gastroenterology 1980;79(6):1262-1266. DOI
- Linn, S., Schoenbaum, S. C., Monson, R. R., Rosner, B., Stubblefield, P. G., and Ryan, K. J. No association between coffee consumption and adverse outcomes of pregnancy. N.Engl.J Med 1-21-1982;306(3):141-145. PubMed
- Cohen, S. Pathogenesis of coffee-induced gastrointestinal symptoms. N.Engl.J Med 7-17-1980;303(3):122-124. PubMed
- Feldman, M. and Barnett, C. Relationships between the acidity and osmolality of popular beverages and reported postprandial heartburn. Gastroenterology 1995;108(1):125-131. PubMed
- Quinlan, P., Lane, J., and Aspinall, L. Effects of hot tea, coffee and water ingestion on physiological responses and mood: the role of caffeine, water and beverage type. Psychopharmacology (Berl) 1997;134(2):164-173. PubMed
- Youngstedt, S. D., O'Connor, P. J., Crabbe, J. B., and Dishman, R. K. Acute exercise reduces caffeine-induced anxiogenesis. Med.Sci Sports Exerc. 1998;30(5):740-745. PubMed
- Kaminsky, L. A., Martin, C. A., and Whaley, M. H. Caffeine consumption habits do not influence the exercise blood pressure response following caffeine ingestion. J.Sports Med.Phys.Fitness 1998;38(1):53-58.
- McManamy, M. C. and Schube, P. G. Caffeine intoxication: report of a case the symptoms of which amounted to a psychosis. New England Journal of Medicine 1936;215:616-620. DOI
- Richter, J. E., Katz, P. O., and Waring, J. P. Gastroesophageal Reflux Disease. IFFGD 2000;
- Hsu, C., Harden, R. N., and Houle, T. Nicotine and caffeine intake in complex regional pain syndrome. Journal of Back and Musculoskeletal Rehabilitation 2002;16(1):33-38. PubMed
- Luebbe, A. M. Child and Adolescent Anxiety Sensitivity, Perceived Subjective Effects of Caffeine and Caffeine Consumption. J Caffeine Res 2011;1(4):213-218. DOI
- Li-Neng, Y., Greenstadt, L., and Shapiro, D. Effects of caffeine on blood pressure:A cross-cultural comparison. Psychophysiology 1983;20
- Fotherby, M. D., Ghandi, C., Haigh, R. A., Macdonald, T. A., and Potter, J. F. Sustained caffeine use has no pressor effect in the elderly. Cardiology in the Elderly 1994;2(6):499-503.
- Basurto Ona X, Uriona Tuma SM, Martínez García L, Solà I, Bonfill Cosp X. Drug therapy for preventing post-dural puncture headache. Cochrane Database Syst Rev. 2013 28;2:CD001792. doi: 10.1002/14651858.CD001792.pub3. Review. PubMed
- Beaudoin MS, Allen B, Mazzetti G, Sullivan PJ, Graham TE. Caffeine ingestion impairs insulin sensitivity in a dose-dependent manner in both men and women. Appl Physiol Nutr Metab. 2013;38(2):140-7. doi: 10.1139/apnm-2012-0201. Epub 2012 9. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Chen L, Bell EM, Browne ML, Druschel CM, Romitti PA, Schmidt RJ, Burns TL, Moslehi R, Olney RS; National Birth Defects Prevention Study. Maternal caffeine consumption and risk of congenital limb deficiencies. Birth Defects Res A Clin Mol Teratol. 2012 De PubMed
- Chen LW, Wu Y, Neelakantan N, Chong MF, Pan A, van Dam RM. Maternal caffeine intake during pregnancy is associated with risk of low birth weight: a systematic review and dose-response meta-analysis. BMC Med. 2014 19;12:174. doi: 10.1186/s12916-014-0174-6 PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- Chiaffarino F, Bravi F, Cipriani S, Parazzini F, Ricci E, Viganò P, La Vecchia C. Coffee and caffeine intake and risk of endometriosis: a meta-analysis. Eur J Nutr. 2014 Oct;53(7):1573-9. doi: 10.1007/s00394-014-0662-7. Epub 2014 31. PubMed
- Greenwood DC, Thatcher NJ, Ye J, Garrard L, Keogh G, King LG, Cade JE. Caffeine intake during pregnancy and adverse birth outcomes: a systematic review and dose-response meta-analysis. Eur J Epidemiol. 2014;29(10):725-34. doi: 10.1007/s10654-014-9944-x. PubMed
- Jiang W, Wu Y, Jiang X. Coffee and caffeine intake and breast cancer risk: an updated dose-response meta-analysis of 37 published studies. Gynecol Oncol. 2013 Jun;129(3):620-9. doi: 10.1016/j.ygyno.2013.03.014. Epub 2013 25. Review. PubMed
- Lee SM, Choi NK, Lee BC, Cho KH, Yoon BW, Park BJ. Caffeine-containing medicines increase the risk of hemorrhagic stroke. Stroke. 2013 Aug;44(8):2139-43. doi: 10.1161/STROKEAHA.111.674077. Epub 2013 6. PubMed
- Sanikini H, Dik VK, Siersema PD, Bhoo-Pathy N, Uiterwaal CS, Peeters PH, González CA, Zamora-Ros R, Overvad K, Tjønneland A, Roswall N, Boutron-Ruault MC, Fagherazzi G, Racine A, Kühn T, Katzke V, Boeing H, Trichopoulou A, Trichopoulos D, Lagiou P, Palli
- Simonin C, Duru C, Salleron J, Hincker P, Charles P, Delval A, Youssov K, Burnouf S, Azulay JP, Verny C, Scherer C, Tranchant C, Goizet C, Debruxelles S, Defebvre L, Sablonnière B, Romon-Rousseaux M, Buée L, Destée A, Godefroy O, Dürr A, Landwehrmeyer B;
- Szpak A, Allen D. A case of acute suicidality following excessive caffeine intake. J Psychopharmacol. 2012 Nov;26(11):1502-10. doi: 10.1177/0269881112442788. Epub 2012 2. PubMed
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Sheppard SG. A preliminary investigation of ibogaine: case reports and recommendations for further study. J Subst Abuse Treat. 1994 Jul-Aug;11(4):379-85. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Rhee J, Kim R, Kim Y, et al. Maternal caffeine consumption during pregnancy and risk of low birth weight: a dose-response meta-analysis of observational studies. PLoS One. 2015 Jul 20;10(7):e0132334. PubMed
- Zuchinali P, Souza GC, Pimentel M, et al. Short-term effects of high-dose caffeine on cardiac arrhythmias in patients with heart failure: a randomized clinical trial. JAMA Intern Med. 2016 Dec 1;176(12):1752-59. PubMed
- Lystrup RM, Leggit JC. Caffeine toxicity due to supplement use in caffeine - naïve individual: a cautionary tale. Mil Med. 2015 Aug;180(8):e936-40. PubMed
- Magdalan J, Zawadzki M, Skowronek R, et al. Nonfatal and fata intoxications with pure caffeine - report of three different cases. Forensic Sci Med Pathol. 2017 Sep;13(3):355-58.
- Trexler ET, Smith-Ryan AE, Roelofs EJ, Hirsch KR, Persky AM, Mock AG. Effects of coffee and caffeine anhydrous intake during creatine loading. J Strength Cond Res. 2016 May;30(5):1438-46. PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Wang HR, Woo YS, Bahk WM. Caffeine-induced psychiatric manifestations: a review. Int Clin Psychopharmacol. 2015 Jul;30(4):179-82. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Vliegenthart R, Miedema M, Hutten GJ, van Kaam AH, Onland W. High versus standard dose caffeine for apnoea: a systematic review. Arch Dis Child Fetal Neonatal Ed 2018;103(6):F523-9. doi: 10.1136/archdischild-2017-313556. PubMed
- Modzelewska D, Bellocco R, Elfvin A, et al. Caffeine exposure during pregnancy, small for gestational age birth and neonatal outcome - results from the Norwegian Mother and Child Cohort Study. BMC Pregnancy Childbirth. 2019;19(1):80. PubMed
- Shen JG, Brooks MB, Cincotta J, Manjourides JD. Establishing a relationship between the effect of caffeine and duration of endurance athletic time trial events: A systematic review and meta-analysis. J Sci Med Sport. 2019;22(2):232-238. PubMed
- Berglundh S, Vollrath M, Brantsæter AL, et al. Maternal caffeine intake during pregnancy and child neurodevelopment up to eight years of age-Results from the Norwegian Mother, Father and Child Cohort Study. Eur J Nutr. 2020. PubMed
- Jin F, Qiao C. Association of maternal caffeine intake during pregnancy with low birth weight, childhood overweight, and obesity: a meta-analysis of cohort studies. Int J Obes (Lond). 2020. PubMed
- Krittanawong C, Tunhasiriwet A, Wang Z, et al. Is caffeine or coffee consumption a risk for new-onset atrial fibrillation? A systematic review and meta-analysis. Eur J Prev Cardiol. 2020:2047487320908385. PubMed
- Zhang H, Lee ZX, Qiu A. Caffeine intake and cognitive functions in children. Psychopharmacology (Berl). 2020;237(10):3109-3116. PubMed
- Stojanovic E, Scanlan AT, Milanovic Z, Fox JL, Stankovic R, Dalbo VJ. Acute caffeine supplementation improves jumping, sprinting, and change-of-direction performance in basketball players when ingested in the morning but not evening. Eur J Sport Sci. 2021 PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Hinkle SN, Gleason JL, Yisahak SF, et al. Assessment of Caffeine Consumption and Maternal Cardiometabolic Pregnancy Complications. JAMA Netw Open 2021;4(11):e2133401. PubMed
- Yartsev A, Peisah C. Caffeine-clozapine interaction associated with severe toxicity and multiorgan system failure: a case report. BMC Psychiatry 2021;21(1):192. PubMed
- Tinawi M. Severe Rhabdomyolysis Due to Strenuous Exercise With a Potential Role of a High-Caffeine Energy Drink. Cureus 2022;14(1):e20867. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Ismail RIH, Awad HA, Saber M, Shehata BM. Bone mineral content for preterm neonates treated with caffeine using dual energy X-ray absorptiometry: An observational study. J Neonatal Perinatal Med 2023;16(1):129-135. PubMed
- Zhao J, Huang Y, Yu X. Caffeine intake and the risk of incident kidney stones: a systematic review and meta-analysis. Int Urol Nephrol 2022;54(10):2457-2466. PubMed
- Abbas-Hashemi SA, Hosseininasab D, Rastgoo S, Shiraseb F, Asbaghi O. The effects of caffeine supplementation on blood pressure in adults: A systematic review and dose-response meta-analysis. Clin Nutr ESPEN 2023;58:165-177. PubMed
- Oliphant EA, Hanning SM, McKinlay CJD, Alsweiler JM. Caffeine for apnea and prevention of neurodevelopmental impairment in preterm infants: systematic review and meta-analysis. J Perinatol 2024;44(6):785-801. PubMed
- Kühne T, Wallace E, Herzig D, et al. Combined intake of caffeine and low-dose glucose to reduce exercise-related hypoglycaemia in individuals with type 1 diabetes on ultra-long-acting insulin degludec: A randomized, controlled, double-blind, cross-over tr
- Song JJ, Eyabi JC, Awatramani PD, Mitchell BG, Nene SY. Sudden Reduction in Caffeine Intake Increases Serum Lithium Concentration to Supratherapeutic Level: A Case Report. Prim Care Companion CNS Disord 2024;26(2):23cr03642. PubMed
Ashwagandha 32 references
- McGuffin M, Hobbs C, Upton R, Goldberg A, eds. American Herbal Products Association's Botanical Safety Handbook. Boca Raton, FL: CRC Press, LLC 1997.
- Upton R, ed. Ashwagandha Root (Withania somnifera): Analytical, quality control, and therapuetic monograph. Santa Cruz, CA: American Herbal Pharmacopoeia 2000:1-25.
- Davis L, Kuttan G. Effect of Withania somnifera on cyclophosphamide-induced urotoxicity. Cancer Lett 2000;148:9-17. PubMed
- Davis L, Kuttan G. Suppressive effect of cyclophosphamide-induced toxicity by Withania somnifera extract in mice. J Ethnopharmacol 1998;62:209-14. PubMed
- Mishra LC, Singh BB, Dagenais S. Scientific basis for the therapeutic use of Withania somnifera (ashwagandha): a review. Altern Med Rev 2000;5:334-46. DOI
- Andallu B, Radhika B. Hypoglycemic, diuretic and hypocholesterolemic effect of winter cherry (Withania somnifera, Dunal) root. Indian J Exp Biol 2000;38:607-9.
- Kulkarni RR, Patki PS, Jog VP, et al. Treatment of osteoarthritis with a herbomineral formulation: a double-blind, placebo-controlled, cross-over study. J Ethnopharmacol 1991;33:91-5. PubMed
- Ahumada F, Aspee F, Wikman G, Hancke J. Withania somnifera exract. Its effects on arterial blood pressure in anaesthetized dogs. Phytother Res 1991;5:111-14.
- Panda S, Kar A. Withania somnifera and Bauhinia purpurea in the regulation of circulating thyroid hormone concentrations in female mice. J Ethnopharmacol 1999;67:233-39. PubMed
- Panda S, Kar A. Changes in thyroid hormone concentrations after administration of ashwagandha root extract to adult male mice. J Pharm Pharmacol 1998;50:1065-68. PubMed
- Sehgal, V. N., Verma, P., and Bhattacharya, S. N. Fixed-drug eruption caused by ashwagandha (Withania somnifera): a widely used Ayurvedic drug. Skinmed. 2012;10(1):48-49.
- Agnihotri AP, Sontakke SD, Thawani VR, Saoji A, Goswami VS. Effects of Withania somnifera in patients of schizophrenia: a randomized, double blind, placebo controlled pilot trial study. Indian J Pharmacol. 2013;45(4):417-8. PubMed
- Biswal BM, Sulaiman SA, Ismail HC, Zakaria H, Musa KI. Effect of Withania somnifera (Ashwagandha) on the development of chemotherapy-induced fatigue and quality of life in breast cancer patients. Integr Cancer Ther. 2013;12(4):312-22.
- Sharma AK, Basu I, Singh S. Efficacy and safety of Ashwagandha root extract in subclinical hypothyroid patients: a double-blind, randomized placebo-controlled trial. J Altern Complement Med. 2018 Mar;24(3):243-248. PubMed
- Durg S, Bavage S, Shivaram SB. Withania somnifera (Indian ginseng) in diabetes mellitus: A systematic review and meta-analysis of scientific evidence from experimental research to clinical application. Phytother Res. 2020;34(5):1041-1059.
- Björnsson HK, Björnsson ES, Avula B, et al. Ashwagandha-induced liver injury: A case series from Iceland and the US Drug-Induced Liver Injury Network. Liver Int. 2020;40(4):825-829. PubMed
- Tharakan A, Shukla H, Benny IR, Tharakan M, George L, Koshy S. Immunomodulatory Effect of Withania somnifera (Ashwagandha) Extract-A Randomized, Double-Blind, Placebo Controlled Trial with an Open Label Extension on Healthy Participants. J Clin Med 2021;1 PubMed
- Ireland PJ, Hardy T, Burt AD, Donnelly MC. Drug-induced hepatocellular injury due to herbal supplement ashwagandha. J R Coll Physicians Edinb. 2021;51(4):363-365. PubMed
- Kamal HI, Patel K, Brdak A, Heffernan J, Ahmad N. Ashwagandha as a unique cause of thyrotoxicosis presenting with supraventricular tachycardia. Cureus. 2022 Mar 25;14(3):e23494. PubMed
- Suryawanshi G, Abdallah M, Thomson M, Desai N, Chauhan A, Lim N. Ashwagandha-Associated Acute Liver Failure Requiring Liver Transplantation. Am J Ther 2023;30(1):e80-e83. PubMed
- Pusec CM, Wolsky R, Llerena C, Sura P. A Case of Supplement-Induced Hepatitis. Cureus 2022;14(10):e30433. PubMed
- Ajgaonkar A, Jain M, Debnath K. Efficacy and Safety of Ashwagandha (Withania somnifera) Root Extract for Improvement of Sexual Health in Healthy Women: A Prospective, Randomized, Placebo-Controlled Study. Cureus 2022;14(10):e30787. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lubarska M, Halasinski P, Hryhorowicz S, et al. Liver Dangers of Herbal Products: A Case Report of Ashwagandha-Induced Liver Injury. Int J Environ Res Public Health 2023;20(5):3921. PubMed
- Tóth M, Benedek AE, Longerich T, Seitz HK. Ashwagandha-induced acute liver injury: A case report. Clin Case Rep 2023;11(3):e7078.
- Bokan G, Glamocanin T, Mavija Z, et al. Herb-Induced Liver Injury by Ayurvedic Ashwagandha as Assessed for Causality by the Updated RUCAM: An Emerging Cause. Pharmaceuticals (Basel) 2023;16(8):1129. PubMed
- Patel PA, Sanborn E, Then R, Williams DM. Recurrent Reversible Cerebral Vasoconstriction Syndrome: A Report of Two Cases. Cureus 2023;15(8):e42992. PubMed
- Majeed M, Nagabhushanam K, Murali A, Vishwanathan DT, Mamidala RV, Mundkur L. A Standardized Withania somniferra (Linn.) Root Extract with Piperine Alleviates the Symptoms of Anxiety and Depression by Increasing Serotonin Levels: A Double-Blind, Randomize
- Philips CA, Valsan A, Theruvath AH, et al. Ashwagandha-induced liver injury-A case series from India and literature review. Hepatol Commun 2023;7(10):e0270. PubMed
- Hayashi M, Hamada H, Azuma SI, Hayashi K. Painless Thyroiditis by Withania somnifera (Ashwagandha). Cureus 2024;16(3):e55352. PubMed
- Vazirani S, Kothari A, Fujimoto J, Gomez M. Supplements Are Not a Synonym for Safe: Suspected Liver Injury From Ashwagandha. Fed Pract 2023;40(9):315-319. PubMed
- Patel M, Newell R, Hillier M, Ramalingam R. Herbal remedies as a potential cause of hypoadrenalism. Br J Hosp Med (Lond) 2024;85(6):1-4. PubMed
Cordyceps 14 references
- Zhu JS, Halpern GM, Jones K. The scientific rediscovery of an ancient Chinese herbal medicine: Cordyceps sinensis: part I. J Altern Complement Med 1998;4:289-303.
- Zhu JS, Halpern GM, Jones K. The scientific rediscovery of a precious ancient Chinese herbal regimen: Cordyceps sinensis: part II. J Altern Complement Med 1998;4:429-57.
- Chen YJ, Shiao MS, Lee SS, Wang SY. Effect of Cordyceps sinensis on the proliferation and differentiation of human leukemic U937 cells. Life Sci 1997;60:2349-59. PubMed
- Zhao Y. [Inhibitory effects of alcoholic extract of Cordyceps sinensis on abdominal aortic thrombus formation in rabbits]. Chung Hua I Hsueh Tsa Chih (Taipei) 1991;71:612-5, 42.
- Chen GZ, Chen GL, Sun T, et al. Effects of Cordyceps sinensis on murine T lymphocyte subsets. Chin Med J (English) 1991;104:4-8.
- Zhu XY, Yu HY. [Immunosuppressive effect of cultured Cordyceps sinensis on cellular immune response]. Chung Hsi I Chieh Ho Tsa Chih 1990;10:485-7, 454.
- Hsu, C. C., Huang, Y. L., Tsai, S. J., Sheu, C. C., and Huang, B. M. In vivo and in vitro stimulatory effects of Cordyceps sinensis on testosterone production in mouse Leydig cells. Life Sci 9-5-2003;73(16):2127-2136. PubMed
- Ikumoto, T., Sasaki, S., Namba, H., Toyama, R., Moritoki, H., and Mouri, T. [Physiologically active compounds in the extracts from tochukaso and cultured mycelia of Cordyceps and Isaria]. Yakugaku Zasshi 1991;111(9):504-509. PubMed
- Wu, T. N., Yang, K. C., Wang, C. M., Lai, J. S., Ko, K. N., Chang, P. Y., and Liou, S. H. Lead poisoning caused by contaminated Cordyceps, a Chinese herbal medicine: two case reports. Sci.Total Environ. 4-5-1996;182(1-3):193-195. PubMed
- Hong T, Zhang M, Fan J. Cordyceps sinensis (a traditional Chinese medicine) for kidney transplant recipients (Review). Cochrane Database Syst Rev. 2015;(10):CD009698. doi: 10.1002/14651858.CD009698.pub2.
- Zhang HW, Lin ZX, Tung YS, Kwan TH, Mok CK, Leung C, Chan LS. Cordyceps sinensis (a traditional Chinese medicine) for treating chronic kidney disease (Review). Cochrane Database Syst Rev. 2014;(12):CD008353. doi: 10.1002/14651858.CD008353.pub2. PubMed
- Bee Yean O, Zoriah A. Efficacy of Cordyceps sinensis as an adjunctive treatment in hemodialysis patients: a systematic review and Meta-analysis. J Tradit Chin Med. 2019;39(1):1-14.
- Thurian D, Montani M, Stickel F. Drug-induced, mixed-type hepatitis following ingestion of Cordyceps sinensis. Int J Clin Pharmacol Ther 2022;60(2):115-120. PubMed
- Yu X, Mao Y, Shergis JL, et al. Effectiveness and safety of oral Cordyceps sinensis on stable COPD of GOLD stages 2-3: Systematic review and meta-analysis. Evid Based Complement Alternat Med. 2019;2019:4903671.
Lemon 2 references
- Ruggenenti P, Caruso MR, Cortinovis M, et al. Fresh lemon juice supplementation for the prevention of recurrent stones in calcium oxalate nephrolithiasis: A pragmatic, prospective, randomised, open, blinded endpoint (PROBE) trial. EClinicalMedicine 2021;4 PubMed
- Umemura K, Katada Y, Nakagawa S, et al. Improved absorption of itraconazole tablet by co-administration with lemon beverages in a lung transplant recipient: A case report. J Infect Chemother 2022;28(8):1203-1207. PubMed
Beet 14 references
- Gruenwald J, Brendler T, Jaenicke C. PDR for Herbal Medicines. 1st ed. Montvale, NJ: Medical Economics Company, Inc., 1998.
- Clifford T, Berntzen B, Davison GW, et al. Effects of beetroot juice on recovery of muscle function and performance between bouts of repeated sprint exercise. Nutrients 2016;8. pii: E506. PubMed
- Siervo M, Lara J, Ogbonmwan I, Mathers JC. Inorganic nitrate and beetroot juice supplementation reduces blood pressure in adults: a systematic review and meta-analysis. J Nutr 2013;143:818-26. PubMed
- Clifford T, Howatson G, West DJ, Stevenson EJ. Beetroot juice is more beneficial than sodium nitrate for attenuating muscle pain after strenuous eccentric-bias exercise. Appl Physiol Nutr Metab. 2017;42(11):1185-1191. PubMed
- Clifford T, Bell O, West DJ, Howatson G, Stevenson EJ. The effects of beetroot juice supplementation on indices of muscle damage following eccentric exercise. Eur J Appl Physiol. 2016;116(2):353-62. PubMed
- Wylie LJ, Kelly J, Bailey SJ, et al. Beetroot juice and exercise: pharmacodynamic and dose-response relationships. J Appl Physiol (1985). 2013;115(3):325-36. PubMed
- Garnacho-Castaño MV, Palau-Salvà G, Cuenca E, et al. Effects of a single dose of beetroot juice on cycling time trial performance at ventilatory thresholds intensity in male triathletes. J Int Soc Sports Nutr. 2018;15(1):49. PubMed
- Rasica L, Porcelli S, Marzorati M, et al. Ergogenic effects of beetroot juice supplementation during severe-intensity exercise in obese adolescents. Am J Physiol Regul Integr Comp Physiol. 2018;315(3):R453-R460. PubMed
- Henrohn D, Björkstrand K, Lundberg JO, et al. Effects of oral supplementation with nitrate-rich beetroot juice in patients with pulmonary arterial hypertension-results from BEET-PAH, an exploratory randomized, double-blind, placebo-controlled, crosso
- Serra-Payá N, Garnacho-Castaño MV, Sánchez-Nuño S, et al. The relationship between resistance exercise performance and ventilatory efficiency after beetroot juice intake in well-trained athletes. Nutrients 2021;13(4):1094. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Hemmatinafar M, Zaremoayedi L, Koushkie Jahromi M, et al. Effect of Beetroot Juice Supplementation on Muscle Soreness and Performance Recovery after Exercise-Induced Muscle Damage in Female Volleyball Players. Nutrients 2023;15(17):3763. PubMed
- Lim SH, Bae S, Lee HS, Han HK, Choi CI. Effect of Betanin, the Major Pigment of Red Beetroot (Beta vulgaris L.), on the Activity of Recombinant Human Cytochrome P450 Enzymes. Pharmaceuticals (Basel) 2023;16(9):1224. PubMed
- Oscherwitz M, Tamayo RM, Heudebert A, Centor R. A Case of Pseudo-Hematochezia from Beet Supplement Ingestion. Am J Med 2023;136(9):e177-e178. PubMed
Ginkgo 97 references
- Davydov L, Stirling AL. Stevens-Johnson syndrome with Ginkgo biloba. J Herb Pharmacother 2001;1:65-9. DOI
- Benjamin J, Muir T, Briggs K, Pentland B. A case of cerebral haemorrhage-can Ginkgo biloba be implicated? Postgrad Med J 2001;77:112-3.
- Matthews, MK. Association of Ginkgo biloba with intracerebral hemorrhage. Neurology 1998;50:1934.
- Rowin J, Lewis SL. Spontaneous bilateral subdural hemotomas with chronic Ginkgo biloba ingestion. Neurology 1996;46:1775-6.
- Rosenblatt M, Mindel T. Spontaneous hyphema associated with ingestion of Ginkgo biloba extract. N Engl J Med 1997;336:1108.
- Fessenden JM, Wittenborn W, Clarke L. Gingko biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67:33-5. DOI
- Gurley BJ, Gardner SF, Hubbard MA. Clinical assessment of potential cytochrome P450-mediated herb-drug interactions. AAPS Ann Mtg & Expo Indianapolis, IN: 2000; Oct 29 - Nov 2:presentation #3460.
- Cohen AJ, Bartlik B. Ginkgo biloba for antidepressant-induced sexual dysfunction. J Sex Marital Ther 1998;24:139-43. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract on pancreatic beta-cell function in response to glucose loading in normal glucose tolerant individuals. J Clin Pharmacol 2000;40:647-54.
- Heck AM, DeWitt BA, Lukes AL. Potential interactions between alternative therapies and warfarin. Am J Health Syst Pharm 2000;57:1221-7. DOI
- Cesarani A, Meloni F, Alpini D, et al. Ginkgo biloba (EGb 761) in the treatment of equilibrium disorders. Adv Ther 1998;15:291-304.
- Galluzzi S, Zanetti O, Binetti G, et al. Coma in a patient with Alzheimer's disease taking low dose trazodone and Ginkgo biloba. J Neurol Neurosurg Psychiatry 2000;68:679-80. DOI
- Budzinski JW, Foster BC, Vandenhoek S, Arnason JT. An in vitro evaluation of human cytochrome P450 3A4 inhibition by selected commercial herbal extracts and tinctures. Phytomedicine 2000;7:273-82. PubMed
- Gregory PJ. Seizure associated with Ginkgo biloba? Ann Intern Med 2001;134:344.
- Granger AS. Ginkgo biloba precipitating epileptic seizures. Age Ageing 2001;30:523-5. PubMed
- Kajiyama Y, Fujii K, Takeuchi H, Manabe Y. Ginkgo seed poisoning. Pediatrics 2002;109:325-7. PubMed
- Miwa H, Iijima M, Tanaka S, Mizuno Y. Generalized convulsions after consuming a large amount of gingko nuts. Epilepsia 2001;42:280-1. DOI
- Burschka MA, Hassan HA, Reineke T, et al. Effect of treatment with Ginkgo biloba extract EGb 761 (oral) on unilateral idiopathic sudden hearing loss in a prospective randomized double-blind study of 106 outpatients. Eur Arch Otorhinolaryngol 2001;258:213- PubMed
- Miller LG, Freeman B. Possible subdural hematoma associated with Ginkgo biloba. J Herb Pharmacother 2002;2:57-63.
- Kudolo GB, Dorsey S, Blodgett J. Effect of the ingestion of Ginkgo biloba extract on platelet aggregation and urinary prostanoid excretion in healthy and Type 2 diabetic subjects. Thromb Res 2002;108:151-60.. PubMed
- Fong KC, Kinnear PE. Retrobulbar haemorrhage associated with chronic Ginkgo biloba ingestion. Postgrad Med J 2003;79:531-2..
- Gurley BJ, Gardner SF, Hubbard MA, et al. Cytochrome P450 phenotypic ratios for predicting herb-drug interactions in humans. Clin Pharmacol Ther 2002;72:276-87.. PubMed
- Kang BJ, Lee SJ, Kim MD, Cho MJ. A placebo-controlled, double-blind trial of Ginkgo biloba for antidepressant-induced sexual dysfunction. Hum Psychopharmacol 2002;17:279-84.
- Yale SH, Glurich I. Analysis of the inhibitory potential of Ginkgo biloba, Echinacea purpurea, and Serenoa repens on the metabolic activity of cytochrome P450 3A4, 2D6, and 2C9. J Altern Complement Med 2005;11:433-9.
- Yasui-Furukori N, Furukori H, Kaneda A, et al. The effects of Ginkgo biloba extracts on the pharmacokinetics and pharmacodynamics of donepezil. J Clin Pharmacol 2004;44:538-42.
- Markowitz JS, Donovan JL, Lindsay DeVane C, et al. Multiple-dose administration of Ginkgo biloba did not affect cytochrome P-450 2D6 or 3A4 activity in normal volunteers. J Clin Psychopharmacol 2003;23:576-81. PubMed
- Arenz A, Kelin M, Flehe K, et al. Occurrence of neurotoxic 4'-O-methylpyridoxine in ginkgo biloba leaves, ginkgo medications and Japanese ginkgo food. Planta Med 1996;62:548-51.
- Engelsen J, Nielsen JD, Winther K. Effect of coenzyme Q10 and Ginkgo biloba on warfarin dosage in stable, long-term warfarin treated outpatients. A randomised, double blind, placebo-crossover trial. Thromb Haemost 2002;87:1075-6. DOI
- Gaudineau C, Beckerman R, Welbourn S, Auclair K. Inhibition of human P450 enzymes by multiple constituents of the Ginkgo biloba extract. Biochem Biophys Res Comm 2004;318:1072–8. PubMed
- Kohler S, Funk P, Kieser M. Influence of a 7-day treatment with Ginkgo biloba special extract EGb 761 on bleeding time and coagulation: a randomized, placebo-controlled, double-blind study in healthy volunteers. Blood Coagul Fibrinolysis 2004;15:303–9. PubMed
- Jiang X, Williams KM, Liauw WS, et al. Effect of ginkgo and ginger on the pharmacokinetics and pharmacodynamics of warfarin in healthy subjects. Br J Clin Pharmacol 2005;59:425-32. PubMed
- Destro MW, Speranzini MB, Cavalheiro Filho C, et al. Bilateral haematoma after rhytidoplasty and blepharoplasty following chronic use of Ginkgo biloba. Br J Plast Surg 2005;58:100-1. PubMed
- Yin OQ, Tomlinson B, Waye MM, et al. Pharmacogenetics and herb-drug interactions: experience with Ginkgo biloba and omeprazole. Pharmacogenetics 2004;14:841-50. PubMed
- Bent S, Goldberg H, Padula A, Avins AL. Spontaneous bleeding associated with Ginkgo biloba: a case report and systematic review of the literature. J Gen Intern Med 2005;20;657-61. DOI
- Meisel C, Johne A, Roots I. Fatal intracerebral mass bleeding associated with Ginkgo biloba and ibuprofen. Atherosclerosis 2003;167:367. PubMed
- Bebbington A, Kulkarni R, Roberts P. Ginkgo biloba: Persistent bleeding after total hip arthroplasty caused by herbal self-medication. J Arthroplasty 2005;20:125-6. .
- Kupiec T, Raj V. Fatal seizures due to potential herb-drug interactions with Ginkgo biloba. J Anal Toxicol 2005:755-8. PubMed
- Hauser D, Gayowski T, Singh N. Bleeding complications precipitated by unrecognized Gingko biloba use after liver transplantation. Transpl Int 2002;15:377-9. DOI
- Mohutsky MA, Anderson GD, Miller JW, Elmer GW. Ginkgo biloba: evaluation of CYP2C9 drug interactions in vitro and in vivo. Am J Ther 2006;13:24-31. PubMed
- Kudolo GB. The effect of 3-month ingestion of Ginkgo biloba extract (EGb 761) on pancreatic beta-cell function in response to glucose loading in individuals with non-insulin-dependent diabetes mellitus. J Clin Pharmacol 2001;41:600-11.
- Pennisi RS. Acute generalised exanthematous pustulosis induced by the herbal remedy Ginkgo biloba. Med J Aust 2006;184:583-4. PubMed
- Yagmur E, Piatkowski A, Groger A, et al. Bleeding complication under Gingko biloba medication. Am J Hematol 2005;79:343-4. PubMed
- Vale S. Subarachnoid haemorrhage associated with Ginkgo biloba. Lancet 1998;352:36. PubMed
- Aruna D, Naidu MU. Pharmacodynamic interaction studies of Ginkgo biloba with cilostazol and clopidogrel in healthy human subjects. Br J Clin Pharmacol 2007;63:333-8.
- Dugoua JJ, Mills E, Perri D, Koren G. Safety and efficacy of ginkgo (Ginkgo biloba) during pregnancy and lactation. Can J Clin Pharmacol 2006;13:e277-84.
- Jiang X, Blair EY, McLachlan AJ. Investigation of the effects of herbal medicines on warfarin response in healthy subjects: a population pharmacokinetic-pharmacodynamic modeling approach. J Clin Pharmacol 2006;46:1370-8. PubMed
- Woelk H, Arnoldt KH, Kieser M, Hoerr R. Ginkgo biloba special extract EGb 761 in generalized anxiety disorder and adjustment disorder with anxious mood: a randomized, double-blind, placebo-controlled trial. J Psychiatr Res 2007;41:472-80. PubMed
- DeKosky ST, Williamson JD, Fitzpatrick AL, et al. Ginkgo biloba for prevention of dementia. JAMA 2008;300:2253-62.
- Dodge HH, Zitzelberger T, Oken BS, et al. A randomized placebo-controlled trial of ginkgo biloba for the prevention of cognitive decline. Neurology 2008;70(19 Pt 2):1809-17. PubMed
- Wiegman DJ, Brinkman K, Franssen EJ. Interaction of Ginkgo biloba with efavirenz. AIDS 2009;23:1184-5. PubMed
- Kim BH, Kim KP, Lim KS, et al. Influence of Ginkgo biloba extract on the pharmacodynamic effects and pharmacokinetic properties of ticlopidine: An open-label, randomized, two-period, two-treatment, two-sequence, single-dose crossover study in healthy Kor
- Salehi B, Imani R, Mohammadi MR, et al. Ginkgo biloba for attention-deficit/hyperactivity disorder in children and adolescents: a double blind, randomized controlled trial. Prog Neuropsychopharmacol Biol Psychiatry 2010;34:76-80. PubMed
- Kellermann AJ, Kloft C. Is there a risk of bleeding associated with standardized ginkgo biloba extract therapy? A systematic review and meta-analysis. Pharmacotherapy 2011;31:490-502.
- Kuller LH, Ives DG, Fitzpatrick AL, et al. Does Ginkgo biloba reduce the risk of cardiovascular events? Circ Cardiovasc Qual Outcomes 2010;3:41-7.
- Naccarato M, Yoong D, Gough K. A potential drug-herbal interaction between Ginkgo biloba and efavirenz. J Int Assoc Physicians AIDS Care (Chic). 2012;11(2):98-100. doi: 10.1177/1545109711435364. Epub 2012 Feb 9.
- Engelsen, J., Nielsen, J. D., and Hansen, K. F. [Effect of Coenzyme Q10 and Ginkgo biloba on warfarin dosage in patients on long-term warfarin treatment. A randomized, double-blind, placebo-controlled cross-over trial]. Ugeskr.Laeger 4-28-2003;165(18):18
- Parsad, D., Pandhi, R., and Juneja, A. Effectiveness of oral Ginkgo biloba in treating limited, slowly spreading vitiligo. Clin Exp.Dermatol. 2003;28(3):285-287.
- Bal Dit, Sollier C., Caplain, H., and Drouet, L. No alteration in platelet function or coagulation induced by EGb761 in a controlled study. Clin Lab Haematol. 2003;25(4):251-253. PubMed
- Yoshioka, M., Ohnishi, N., Koishi, T., Obata, Y., Nakagawa, M., Matsumoto, T., Tagagi, K., Takara, K., Ohkuni, T., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. IV. Effects of ginkgo b
- Yoshioka, M., Ohnishi, N., Sone, N., Egami, S., Takara, K., Yokoyama, T., and Kuroda, K. Studies on interactions between functional foods or dietary supplements and medicines. III. Effects of ginkgo biloba leaf extract on the pharmacokinetics of nifedipi
- Lovera, J., Bagert, B., Smoot, K., Morris, C. D., Frank, R., Bogardus, K., Wild, K., Oken, B., Whitham, R., and Bourdette, D. Ginkgo biloba for the improvement of cognitive performance in multiple sclerosis: a randomized, placebo-controlled trial. Mult.S PubMed
- Lin, Y. Y., Chu, S. J., and Tsai, S. H. Association between priapism and concurrent use of risperidone and Ginkgo biloba. Mayo Clin Proc 2007;82(10):1289-1290.
- Robertson, S. M., Davey, R. T., Voell, J., Formentini, E., Alfaro, R. M., and Penzak, S. R. Effect of Ginkgo biloba extract on lopinavir, midazolam and fexofenadine pharmacokinetics in healthy subjects. Curr Med Res Opin 2008;24(2):591-599. PubMed
- Penzak, S. R., Busse, K. H., Robertson, S. M., Formentini, E., Alfaro, R. M., and Davey, R. T., Jr. Limitations of using a single postdose midazolam concentration to predict CYP3A-mediated drug interactions. J Clin Pharmacol 2008;48(6):671-680. PubMed
- May, B. H., Yang, A. W., Zhang, A. L., Owens, M. D., Bennett, L., Head, R., Cobiac, L., Li, C. G., Hugel, H., Story, D. F., and Xue, C. C. Chinese herbal medicine for Mild Cognitive Impairment and Age Associated Memory Impairment: a review of randomised
- Choi, W. S., Choi, C. J., Kim, K. S., Lee, J. H., Song, C. H., Chung, J. H., Ock, S. M., Lee, J. B., and Kim, C. M. To compare the efficacy and safety of nifedipine sustained release with Ginkgo biloba extract to treat patients with primary Raynaud's phe
- Lei, H. P., Wang, G., Wang, L. S., Ou-yang, D. S., Chen, H., Li, Q., Zhang, W., Tan, Z. R., Fan, L., He, Y. J., and Zhou, H. H. Lack of effect of Ginkgo biloba on voriconazole pharmacokinetics in Chinese volunteers identified as CYP2C19 poor and extensiv
- Russo, V., Stella, A., Appezzati, L., Barone, A., Stagni, E., Roszkowska, A., and Delle, Noci N. Clinical efficacy of a Ginkgo biloba extract in the topical treatment of allergic conjunctivitis. Eur J Ophthalmol. 2009;19(3):331-336. PubMed
- Fan, L., Tao, G. Y., Wang, G., Chen, Y., Zhang, W., He, Y. J., Li, Q., Lei, H. P., Jiang, F., Hu, D. L., Huang, Y. F., and Zhou, H. H. Effects of Ginkgo biloba extract ingestion on the pharmacokinetics of talinolol in healthy Chinese volunteers. Ann Phar PubMed
- Ozgoli, G., Selselei, E. A., Mojab, F., and Majd, H. A. A randomized, placebo-controlled trial of Ginkgo biloba L. in treatment of premenstrual syndrome. J Altern.Complement Med 2009;15(8):845-851.
- Singh, V., Singh, S. P., and Chan, K. Review and meta-analysis of usage of ginkgo as an adjunct therapy in chronic schizophrenia. Int J Neuropsychopharmacol. 2010;13(2):257-271.
- Kim, T. E., Kim, B. H., Kim, J., Kim, K. P., Yi, S., Shin, H. S., Lee, Y. O., Lee, K. H., Shin, S. G., Jang, I. J., and Yu, K. S. Comparison of the pharmacokinetics of ticlopidine between administration of a combined fixed-dose tablet formulation of ticl
- Nicolai, S. P., Gerardu, V. C., Kruidenier, L. M., Prins, M. H., and Teijink, J. A. From the Cochrane library: Ginkgo biloba for intermittent claudication. Vasa 2010;39(2):153-158. PubMed
- Patel, N. Herbal remedies. Br.Dent.J 8-28-2010;209(4):153.
- Pedroso, J. L., Henriques Aquino, C. C., Escorcio Bezerra, M. L., Baiense, R. F., Suarez, M. M., Dutra, L. A., Braga-Neto, P., and Povoas Barsottini, O. G. Ginkgo biloba and cerebral bleeding: a case report and critical review. Neurologist. 2011;17(2):89 PubMed
- Russo, V., Rago, A., Russo, G. M., Calabro, R., and Nigro, G. Ginkgo biloba: an ancient tree with new arrhythmic side effects. J Postgrad.Med 2011;57(3):221.
- Zhou, Y. and Zeng, R. [Effects of Ginkgo biloba extract on anticoagulation and blood drug level of warfarin in healthy wolunteers]. Zhongguo Zhong Yao Za Zhi 2011;36(16):2290-2293. DOI
- Skogh, M. Extracts of Ginkgo biloba and bleeding or haemorrhage. Lancet 10-3-1998;352(9134):1145-1146. PubMed
- Fessenden JM, Wittenborn W, and Clarke L. Ginkgo biloba: a case report of herbal medicine and bleeding postoperatively from a laparoscopic cholecystectomy. Am Surg 2001;67(1):33-35.
- Burkard G. [The efficacy and safety of ginkgo biloba extract in dementia]. Fortschr Med [Supp] 1991;109(107):6-8.
- Dai LL, Fan L, Wu HZ, Tan ZR, Chen Y, Peng XD, Shen MX, Yang GP, Zhou HH. Assessment of a pharmacokinetic and pharmacodynamic interaction between simvastatin and Ginkgo biloba extracts in healthy subjects. Xenobiotica 2013;43(10):862-7.
- Guo CX, Pei Q, Yin JY, Peng XD, Zhou BT, Zhao YC, Wu LX, Meng XG, Wang G, Li Q, Ouyang DS, Liu ZQ, Zhang W, Zhou HH. Effects of Ginkgo biloba extracts on pharmacokinetics and efficacy of atorvastatin based on plasma indices. Xenobiotica 2012;42(8):784-90.
- Stoddard GJ, Archer M, Shane-McWhorter L, Bray BE, Redd DF, Proulx J, Zeng-Treitler Q. Ginkgo and Warfarin Interaction in a Large Veterans Administration Population. AMIA Annu Symp Proc. 2015 Nov 5;2015:1174-83.
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Carlile PV. Unexplained alveolar hemorrhage associated with ginkgo and ginseng use. J Bronchology Interv Pulmonol. 2015;22(2):170-2. doi: 10.1097/LBR.0000000000000150. PubMed
- Han EJ, Park HL, Kim SH. Allergic Reaction to Ginkgo Nut on FDG PET/CT. Clin Nucl Med. 2016 Sep;41(9):716-7. doi: 10.1097/RLU.0000000000001276. PubMed
- Rho SS, Woo YS, Bahk WM. Ginkgo biloba induced mood dysregulation: a case report. BMC Complement Altern Med. 2018 Jan 15;18(1):14. PubMed
- Aziz TA, Hussain SA, Mahwi TO, Ahmed ZA, Rahman HS, Rasedee A. The efficacy and safety of Ginkgo biloba extract as an adjuvant in type 2 diabetes mellitus patients ineffectively managed with metformin: a double-blind, randomized, placebo-controlled trial.
- World Health Organization. WHO pharmaceuticals newsletter: 2020, No. 3. Available at: https://www.who.int/medicines/publications/WHO_Pharmaceuticals_Newslet3_20.pdf?ua=1. Accessed June 23, 2021.
- Health Canada. Ginkgo biloba-containing products and the risk of cardiac arrhythmias. Health Product InfoWatch. February 2021. Available at: https://www.canada.ca/en/health-canada/services/drugs-health-products/medeffect-canada/health-product-infowatch/fe
- Wasef AK, Wahdan SA, Saeed NM, El-Demerdash E. Effects of aged garlic and ginkgo biloba extracts on the pharmacokinetics of sofosbuvir in rats. Biopharm Drug Dispos. 2022;43(4):152-62. PubMed
- Xing X, Kong M, Hou Q, Li J, Qian W, Chen X, Li H, Yang C. Effects of ginkgo leaf tablet on the pharmacokinetics of rosiglitazone in rats and its potential mechanism. Pharm Biol. 2022;60(1):1190-7. PubMed
- Hoerr R, Zimmermann A, Seitz F, Dienel A. Single and repeated doses of EGb 761® do not affect pharmacokinetics or pharmacodynamics of rivaroxaban in healthy subjects. Front Pharmacol. 2022 Apr 20;13:868843. PubMed
- Bai J, Zhang C. Metabolic interaction between biflavonoids in Ginkgo biloba leaves and tacrolimus. Biopharm Drug Dispos 2023;44(2):157-164.
- Wang Q, Liu Z, Wang R, et al. Effect of Ginkgo biloba extract on pharmacology and pharmacokinetics of atorvastatin in rats with hyperlipidaemia. Food Funct 2023;14(7):3051-3066.
- Burnett CL, Bergfeld WF, Belsito DV, et al. Safety Assessment of Ginkgo biloba-Derived Ingredients as Used in Cosmetics. Int J Toxicol. 2023 Nov 6:10915818231210792.
- Yao Y, Zhao J, Li C, et al. Ginkgo biloba extract safety: Insights from a real-world pharmacovigilance study of FDA adverse event reporting system (FAERS) events. J Ethnopharmacol 2025;337(Pt 3):119010. PubMed
Bacopa 12 references
- Stough C, Lloyd J, Clarke J, et al. The chronic effects of an extract of Bacopa monniera (Brahmi) on cognitive function in healthy human subjects. Psychopharmacology 2001;156:481-4..
- Yadav SK, Jain AK, Tripathi SN, Gupta JP. Irritable bowel syndrome: therapeutic evaluation of indigenous drugs. Indian J Med Res 1989;90:496-503..
- Morgan A, Stevens J. Does Bacopa monnieri improve memory performance in older persons? Results of a randomized, placebo-controlled, double-blind trial. J Altern Complement Med 2010;16:753-9.
- Kar, A., Panda, S., and Bharti, S. Relative efficacy of three medicinal plant extracts in the alteration of thyroid hormone concentrations in male mice. J Ethnopharmacol. 2002;81(2):281-285. PubMed
- Mukherjee, G. D. and Dey, C. D. Clinical trial on Brahmi. I. J.Exp.Med.Sci. 1966;10(1):5-11.
- Kar A, Pandit S, Mukherjee K, Bahadur S, Mukherjee PK. Safety assessment of selected medicinal food plants used in Ayurveda through CYP450 enzyme inhibition study. J Sci Food Agric 2017;97(1):333-40. doi: 10.1002/jsfa.7739. PubMed
- Kongkeaw C, Dilokthornsakul P, Thanarangsarit P, et al. Meta-analysis of randomized controlled trials on cognitive effects of Bacopa monnieri extract. J Ethnopharmacol 2014;151(1):528-35. PubMed
- Ramasamy S, Kiew LV, Chung LY. Inhibition of human cytochrome P450 enzymes by Bacopa monnieri standardized extract and constituents. Molecules 2014;19(2):2588-601. PubMed
- Prabhakar S, Vishnu VY, Modi M, et al. Efficacy of Bacopa monnieri (Brahmi) and donepezil in Alzheimer's disease and mild cognitive impairment: a randomized double-blind parallel phase 2b study. Ann Indian Acad Neurol 2020;23(6):767-73. PubMed
- Acquarulo B, Tandon P, Macica CM. Suspected cholinergic toxicity due to cevimeline hydrochloride and Bacopa monnieri interaction: a case report. J Med Case Rep 2022;16(1):253. PubMed
- Keegan AP, Stough C, Paris D, et al. Bacopa monnieri supplementation has no effect on serum brain-derived neurotrophic factor levels but beneficially modulates nuclear factor kappa B and cyclic AMP response element-binding protein levels in healthy elderl
- Yaworski AM, Blyumin M, Chang T, Mammen AL, Greene M. Necrotizing myopathy with elevated anti-HMGCR antibodies following exposure to the supplement Bacopa. Muscle Nerve 2023;67(2):E1-E3.
Coffee 175 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Harder S, Fuhr U, Staib AH, Wolff T. Ciprofloxacin-caffeine: a drug interaction established using in vivo and in vitro investigations. Am J Med 1989;87:89S-91S. PubMed
- Carbo M, Segura J, De la Torre R, et al. Effect of quinolones on caffeine disposition. Clin Pharmacol Ther 1989;45:234-40. PubMed
- Healy DP, Polk RE, Kanawati L, et al. Interaction between oral ciprofloxacin and caffeine in normal volunteers. Antimicrob Agents Chemother 1989;33:474-8. PubMed
- Mester R, Toren P, Mizrachi I, et al. Caffeine withdrawal increases lithium blood levels. Biol Psychiatry 1995;37:348-50. PubMed
- Jefferson JW. Lithium tremor and caffeine intake: two cases of drinking less and shaking more. J Clin Psychiatry 1988;49:72-3.
- Lasswell WL Jr, Weber SS, Wilkins JM. In vitro interaction of neuroleptics and tricylic antidepressants with coffee, tea, and gallotannic acid. J Pharm Sci 1984;73:1056-8. PubMed
- Kulhanek F, Linde OK, Meisenberg G. Precipitation of antipsychotic drugs in interaction with coffee or tea. Lancet 1979;2:1130.
- Joeres R, Klinker H, Heusler H, et al. Influence of mexiletine on caffeine elimination. Pharmacol Ther 1987;33:163-9. PubMed
- Vahedi K, Domingo V, Amarenco P, Bousser MG. Ischemic stroke in a sportsman who consumed MaHuang extract and creatine monohydrate for bodybuilding. J Neurol Neurosurg Psychiatr 2000;68:112-3.
- Grubben MJ, Boers GH, Blom HJ, et al. Unfiltered coffee increases plasma homocysteine concentrations in healthy volunteers: a randomized trial. Am J Clin Nutr 2000;71:480-4. PubMed
- Wakabayashi K, Kono S, Shinchi K, et al. Habitual coffee consumption and blood pressure: A study of self-defense officials in Japan. Eur J Epidemiol 1998;14:669-73. PubMed
- Hodgson JM, Puddey IB, Burke V, et al. Effects on blood pressure of drinking green and black tea. J Hypertens 1999;17:457-63. PubMed
- Rapuri PB, Gallagher JC, Kinyamu HK, Ryschon KL. Caffeine intake increases the rate of bone loss in elderly women and interacts with vitamin D receptor genotypes. Am J Clin Nutr 2001;74:694-700. PubMed
- The National Toxicology Program (NTP). Caffeine. Center for the Evaluation of Risks to Human Reproduction (CERHR). Available at: http://cerhr.niehs.nih.gov/common/caffeine.html.
- Klebanoff MA, Levine RJ, DerSimonian R, et al. Maternal serum paraxanthine, a caffeine metabolite, and the risk of spontaneous abortion. N Engl J Med 1999;341:1639-44. PubMed
- Eskenazi B. Caffeine—filtering the facts. N Engl J Med 1999;341:1688-9. PubMed
- Fernandes O, Sabharwal M, Smiley T, et al. Moderate to heavy caffeine consumption during pregnancy and relationship to spontaneous abortion and abnormal fetal growth: a meta-analysis. Reprod Toxicol 1998;12:435-44. PubMed
- Pollock BG, Wylie M, Stack JA, et al. Inhibition of caffeine metabolism by estrogen replacement therapy in postmenopausal women. J Clin Pharmacol 1999;39:936-40. PubMed
- Nurminen ML, Niittynen L, Korpela R, Vapaatalo H. Coffee, caffeine and blood pressure: a critical review. Eur J Clin Nutr 1999;53:831-9. PubMed
- Dews PB, Curtis GL, Hanford KJ, O'Brien CP. The frequency of caffeine withdrawal in a population-based survey and in a controlled, blinded pilot experiment. J Clin Pharmacol 1999;39:1221-32. PubMed
- FDA. Proposed rule: dietary supplements containing ephedrine alkaloids. Available at: www.verity.fda.gov (Accessed 25 January 2000).
- Margolin KA, Green MR. Polymicrobial enteric septicemia from coffee enemas. West J Med 1984;140:460.
- Urgert R, Vliet TV, Zock PL, et al. Heavy coffee consumption and plasma homocysteine: a randomized controlled trial in healthy volunteers. Am J Clin Nutr 2000;72:1107-10. PubMed
- Green S. A critique of the rationale for cancer treatment with coffee enemas and diet. JAMA 1992;268:3224-7. DOI
- Shils ME, Herman MG. Unproved dietary claims in the treatment of patients with cancer. Bull N Y Acad Med 1982;58:323-39.
- Boozer CN, Nasser JA, Heymsfield SB, et al. An herbal supplement containing Ma Huang-Guarana for weight loss: a randomized, double-blind trial. Int J Obes Relat Metab Disord 2001;25:316-24. PubMed
- Bak AA, Grobbee DE. The effect of serum cholesterol levels of coffee brewed by filtering or boiling. N Engl J Med 1989;321:1432-7.
- Briggs GB, Freeman RK, Yaffe SJ. Drugs in Pregnancy and Lactation. 5th ed. Philadelphia, PA: Lippincott Williams & Wilkins; 1998.
- Hagg S, Spigset O, Mjorndal T, Dahlqvist R. Effect of caffeine on clozapine pharmacokinetics in healthy volunteers. Br J Clin Pharmacol 2000;49:59-63. PubMed
- Watson JM, Jenkins EJ, Hamilton P, et al. Influence of caffeine on the frequency and perception of hypoglycemia in free-living patients with type 1 diabetes. Diabetes Care 2000;23:455-9. PubMed
- Lloyd T, Johnson-Rollings N, Eggli DF, et al. Bone status among postmenopausal women with different habitual caffeine intakes: a longitudinal investigation. J Am Coll Nutr 2000;19:256-61. PubMed
- American Academy of Pediatrics. The transfer of drugs and other chemicals into human milk. Pediatrics 2001;108:776-89. PubMed
- Sinclair CJ, Geiger JD. Caffeine use in sports. A pharmacological review. J Sports Med Phys Fitness 2000;40:71-9.
- Heliovaara M, Aho K, Knekt P, et al. Coffee consumption, rheumatoid factor, and the risk of rheumatoid arthritis. Ann Rheum Dis 2000;59:631-5. PubMed
- Haller CA, Benowitz NL. Adverse cardiovascular and central nervous system events associated with dietary supplements containing ephedra alkaloids. N Engl J Med 2000;343:1833-8. PubMed
- Brown BT. Treating cancer with coffee enemas and diet. JAMA 1993;269:1635-6. DOI
- Ali M, Afzal M. A potent inhibitor of thrombin stimulated platelet thromboxane formation from unprocessed tea. Prostaglandins Leukot Med 1987;27:9-13. PubMed
- Ardlie NG, Glew G, Schultz BG, Schwartz CJ. Inhibition and reversal of platelet aggregation by methyl xanthines. Thromb Diath Haemorrh 1967;18:670-3. DOI
- Samarrae WA, Truswell AS. Short-term effect of coffee on blood fibrinolytic activity in healthy adults. Atherosclerosis 1977;26:255-60. PubMed
- Klag MJ, Wang NY, Meoni LA, et al. Coffee intake and risk of hypertension: The John Hopkins precursors study. Arch Intern Med 2002;162:657-62. DOI
- Brenner H, Rothenbacher D, Bode G, Adler G. Relation of smoking and alcohol and coffee consumption to active Helicobacter pylori infection: cross sectional study. BMJ 1997;315:1489-92.
- Jee SH, He J, Appel LJ, et al. Coffee consumption and serum lipids: a meta-analysis of randomized controlled clinical trials. Am J Epidemiol 2001:153:353-62. PubMed
- Michaud DS, Giovannucci E, Willett WC, et al. Coffee and alcohol consumption and risk of pancreatic cancer in two prospective United States cohorts. Cancer Epidemiol Biomarkers Prev 2001;10:429-37.
- Tavani A, Pregnolato A, La Vecchia C, et al. Coffee consumption and the risk of breast cancer. Eur J Cancer Prev 1998;7:77-82.
- Tavani A, La Vecchia C. Coffee and cancer: a review of epidemiological studies, 1990-1999. Eur J Cancer Prev 2000;9:241-56.
- Hartman TJ, Tangrea JA, Pietinen P, et al. Tea and coffee consumption and risk of colon and rectal cancer in middle-aged Finnish men. Nutr Cancer 1998;31:41-8. PubMed
- Anon. Filtering the news about coffee. University of California, Berkeley Wellness Letter 2001:17:1-2.
- Ferrini RL, Barrett-Connor E. Caffeine intake and endogenous sex steroid levels in postmenopausal women. The Rancho Bernardo Study. Am J Epidemiol 1996:144:642-4. PubMed
- Jacobsen BK, Heuch I. Coffee, K-ras mutations and pancreatic cancer: a heterogeneous aetiology or an artefact? J Epidemiol Community Health 2000;54:654-5.
- Porta M, Malats N, Alguacil J, et al. Coffee, pancreatic cancer, and K-ras mutations: updating the research agenda. J Epidemiol Community Health 2000;54:656-9.
- Kuper HE, Mucci LA, Trichopoulos D. Coffee, pancreatic cancer, and the question of causation. J Epidemiol Community Health 2000;54:650-1.
- Urgert R, Meyboom S, Kuilman M, et al. Comparison of effect of cafetiere and filtered coffee on serum concentrations of liver aminotransferases and lipids: six month randomised controlled trial. BMJ 1996;313:1362-6.. DOI
- Bell DG, Jacobs I, Ellerington K. Effect of caffeine and ephedrine ingestion on anaerobic exercise performance. Med Sci Sports Exerc 2001;33:1399-403. PubMed
- Horner NK, Lampe JW. Potential mechanisms of diet therapy for fibrocystic breast conditions show inadequate evidence of effectiveness. J Am Diet Assoc 2000;100:1368-80. PubMed
- Bracken MB, Triche EW, Belanger K, et al. Association of maternal caffeine consumption with decrements in fetal growth. Am J Epidemiol 2003;157:456-66.. PubMed
- Shekelle PG, Hardy ML, Morton SC, et al. Efficacy and safety of ephedra and ephedrine for weight loss and athletic performance: a meta-analysis. JAMA 2003;289:1537-45.. PubMed
- McGowan JD, Altman RE, Kanto WP Jr. Neonatal withdrawal symptoms after chronic maternal ingestion of caffeine. South Med J 1988;81:1092-4.. PubMed
- Massey LK. Is caffeine a risk factor for bone loss in the elderly? Am J Clin Nutr 2001;74:569-70. PubMed
- Kockler DR, McCarthy MW, Lawson CL. Seizure activity and unresponsiveness after hydroxycut ingestion. Pharmacotherapy 2001;21:647-51.. PubMed
- Wisborg K, Kesmodel U, Bech BH, et al. Maternal consumption of coffee during pregnancy and stillbirth and infant death in first year of life: prospective study. BMJ 2003;326:420.. PubMed
- Nix D, Zelenitsky S, Symonds W, et al. The effect of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. Clin Pharmacol Ther 1992;51:183. DOI
- Infante S, Baeza ML, Calvo M, et al. Anaphylaxis due to caffeine. Allergy 2003;58:681-2. PubMed
- Massey LK, Whiting SJ. Caffeine, urinary calcium, calcium metabolism and bone. J Nutr 1993;123:1611-4. PubMed
- Panagiotakos DB, Pitsavos C, Chrysohoou C, et al. The J-shaped effect of coffee consumption on the risk of developing acute coronary syndromes: the CARDIO2000 case-control study. J Nutr 2003;133:3228-32. PubMed
- Nawrot P, Jordan S, Eastwood J, et al. Effects of caffeine on human health. Food Addit Contam 2003;20:1-30. PubMed
- Food and Nutrition Board, Institute of Medicine. Nutrition during lactation. Washington, DC: National Academy Press, 1991. Available at: http://books.nap.edu/books/0309043913/html.
- Gertz BJ, Holland SD, Kline WF, et al. Studies of the oral bioavailability of alendronate. Clin Pharmacol Ther 1995;58:288-98. PubMed
- May DC, Jarboe CH, VanBakel AB, Williams WM. Effects of cimetidine on caffeine disposition in smokers and nonsmokers. Clin Pharmacol Ther 1982;31:656-61. PubMed
- Abernethy DR, Todd EL. Impairment of caffeine clearance by chronic use of low-dose oestrogen-containing oral contraceptives. Eur J Clin Pharmacol 1985;28:425-8. PubMed
- Brown NJ, Ryder D, Branch RA. A pharmacodynamic interaction between caffeine and phenylpropanolamine. Clin Pharmacol Ther 1991;50:363-71. PubMed
- Sanderink GJ, Bournique B, Stevens J, et al. Involvement of human CYP1A isoenzymes in the metabolism and drug interactions of riluzole in vitro. Pharmacol Exp Ther 1997;282:1465-72. DOI
- Wahllander A, Paumgartner G. Effect of ketoconazole and terbinafine on the pharmacokinetics of caffeine in healthy volunteers. Eur J Clin Pharmacol 1989;37:279-83. PubMed
- Carrillo JA, Benitez J. Clinically significant pharmacokinetic interactions between dietary caffeine and medications. Clin Pharmacokinet 2000;39:127-53. PubMed
- Underwood DA. Which medications should be held before a pharmacologic or exercise stress test? Cleve Clin J Med 2002;69:449-50. PubMed
- Aqel RA, Zoghbi GJ, Trimm JR, et al. Effect of caffeine administered intravenously on intracoronary-administered adenosine-induced coronary hemodynamics in patients with coronary artery disease. Am J Cardiol 2004;93:343-6. PubMed
- Zheng XM, Williams RC. Serum caffeine levels after 24-hour abstention: clinical implications on dipyridamole (201)Tl myocardial perfusion imaging. J Nucl Med Technol 2002;30:123-7.
- Institute of Medicine. Caffeine for the Sustainment of Mental Task Performance: Formulations for Military Operations. Washington, DC: National Academy Press, 2001. Available at: http://books.nap.edu/books/0309082587/html/index.html. DOI
- Holmgren P, Norden-Pettersson L, Ahlner J. Caffeine fatalities--four case reports. Forensic Sci Int 2004;139:71-3. PubMed
- Dews PB, O'Brien CP, Bergman J. Caffeine: behavioral effects of withdrawal and related issues. Food Chem Toxicol 2002;40:1257-61. PubMed
- Beach CA, Mays DC, Guiler RC, et al. Inhibition of elimination of caffeine by disulfiram in normal subjects and recovering alcoholics. Clin Pharmacol Ther 1986;39:265-70. PubMed
- Sato J, Nakata H, Owada E, et al. Influence of usual intake of dietary caffeine on single-dose kinetics of theophylline in healthy human subjects. Eur J Clin Pharmacol 1993;44:295-8. PubMed
- Baker JA, McCann SE, Reid ME, et al. Associations between black tea and coffee consumption and risk of lung cancer among current and former smokers. Nutr Cancer 2005;52:15-21. PubMed
- Benowitz NL, Osterloh J, Goldschlager N, et al. Massive catecholamine release from caffeine poisoning. JAMA 1982;248:1097-8. DOI
- Leson CL, McGuigan MA, Bryson SM. Caffeine overdose in an adolescent male. J Toxicol Clin Toxicol 1988;26:407-15. PubMed
- Juliano LM, Griffiths RR. A critical review of caffeine withdrawal: empirical validation of symptoms and signs, incidence, severity, and associated features. Psychopharmacology (Berl) 2004;176:1-29. PubMed
- Winkelmayer WC, Stampfer MJ, Willett WC, Curhan GC. Habitual caffeine intake and the risk of hypertension in women. JAMA 2005;294:2330-5. PubMed
- Raaska K, Raitasuo V, Laitila J, Neuvonen PJ. Effect of caffeine-containing versus decaffeinated coffee on serum clozapine concentrations in hospitalised patients. Basic Clin Pharmacol Toxicol 2004;94:13-8. DOI
- Forrest WH Jr, Bellville JW, Brown BW Jr. The interaction of caffeine with pentobarbital as a nighttime hypnotic. Anesthesiology 1972;36:37-41. PubMed
- Lake CR, Rosenberg DB, Gallant S, et al. Phenylpropanolamine increases plasma caffeine levels. Clin Pharmacol Ther 1990;47:675-85. PubMed
- Lopez-Garcia E, van Dam RM, Willett WC, et al. Coffee consumption and coronary heart disease in men and women: a prospective cohort study. Circulation 2006;113:2045-53. PubMed
- Baylin A, Hernandez-Diaz S, Kabagambe EK, et al. Transient exposure to coffee as a trigger of a first nonfatal myocardial infarction. Epidemiology 2006;17:506-11. PubMed
- Weng X, Odouli R, Li DK. Maternal caffeine consumption during pregnancy and the risk of miscarriage: a prospective cohort study. Am J Obstet Gynecol 2008;198:279.e1-8. PubMed
- Savitz DA, Chan RL, Herring AH, et al. Caffeine and miscarriage risk. Epidemiology 2008;19:55-62. PubMed
- Benvenga S. Bartolone L, Pappalardo MA, et al. Altered intestinal absorption of L-thyroxine caused by coffee. Thyroid 2008;18:293-301. PubMed
- Stille, W., Harder, S., Mieke, S., Beer, C., Shah, P. M., Frech, K., and Staib, A. H. Decrease of caffeine elimination in man during co-administration of 4-quinolones. J.Antimicrob.Chemother. 1987;20(5):729-734. PubMed
- Wojcikowski, J. and Daniel, W. A. Perazine at therapeutic drug concentrations inhibits human cytochrome P450 isoenzyme 1A2 (CYP1A2) and caffeine metabolism--an in vitro study. Pharmacol Rep. 2009;61(5):851-858. PubMed
- Daniel, W. A., Syrek, M., Rylko, Z., and Kot, M. Effects of phenothiazine neuroleptics on the rate of caffeine demethylation and hydroxylation in the rat liver. Pol.J Pharmacol 2001;53(6):615-621.
- Norager, C. B., Jensen, M. B., Weimann, A., and Madsen, M. R. Metabolic effects of caffeine ingestion and physical work in 75-year old citizens. A randomized, double-blind, placebo-controlled, cross-over study. Clin Endocrinol (Oxf) 2006;65(2):223-228. PubMed
- Azcona O, Barbanoi MJ, Torrent J, Jane F. Evaluation of the central effects of alcohol and caffeine interaction. Br J Clin Pharmacol 1995;40:393-400. PubMed
- Harder S, Staib AH, Beer C, et al. 4-quinolones inhibit biotransformation of caffeine. Eur J Clin Pharmacol 1988;35:651-6. PubMed
- Zhang LL, Zhang JR, Guo K, et al. Effects of fluoroquinolones on CYP4501A and 3A in male broilers. Res Vet Sci 2011;90:99-105. PubMed
- Cesana M, Broccali G, Imbimbo BP, Crema A. Effect of single doses of rufloxacin on the disposition of theophylline and caffeine after single administration. Int J Clin Pharmacol Ther Toxicol 1991:29:133-8.
- Broughton LJ, Rogers HJ. Decreased systemic clearance of caffeine due to cimetidine. Br J Clin Pharmacol 1981;12:155-9. PubMed
- Smits P, Straatman C, Pijpers E, Thien T. Dose-dependent inhibition of the hemodynamic response to dipyridamole by caffeine. Clin Pharmacol Ther 1991;50:529-37. PubMed
- Zelenitsky SA, Norman A, Nix DE. The effects of fluconazole on the pharmacokinetics of caffeine in young and elderly subjects. J Infect Dis Pharmacother 1995;1:1-11.
- Joeres R, Richter E. Mexiletine and caffeine elimination. N Engl J Med 1987;317:117. PubMed
- Jonkman JH, Sollie FA, Sauter R, Steinijans VW. The influence of caffeine on the steady-state pharmacokinetics of theophylline. Clin Pharmacol Ther 1991;49:248-55. PubMed
- Smits, P., Temme, L., and Thien, T. The cardiovascular interaction between caffeine and nicotine in humans. Clin Pharmacol Ther 1993;54(2):194-204. PubMed
- MacKenzie, T., Comi, R., Sluss, P., Keisari, R., Manwar, S., Kim, J., Larson, R., and Baron, J. A. Metabolic and hormonal effects of caffeine: randomized, double-blind, placebo-controlled crossover trial. Metabolism 2007;56(12):1694-1698. PubMed
- Lopez-Garcia, E., Rodriguez-Artalejo, F., Rexrode, K. M., Logroscino, G., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of stroke in women. Circulation 3-3-2009;119(8):1116-1123. PubMed
- Zhang, W., Lopez-Garcia, E., Li, T. Y., Hu, F. B., and van Dam, R. M. Coffee consumption and risk of cardiovascular diseases and all-cause mortality among men with type 2 diabetes. Diabetes Care 2009;32(6):1043-1045. PubMed
- Hashim, H. and Al, Mousa R. Management of fluid intake in patients with overactive bladder. Curr.Urol.Rep. 2009;10(6):428-433. PubMed
- Moisey, L. L., Robinson, L. E., and Graham, T. E. Consumption of caffeinated coffee and a high carbohydrate meal affects postprandial metabolism of a subsequent oral glucose tolerance test in young, healthy males. Br.J Nutr. 2010;103(6):833-841. PubMed
- Simmonds, M. J., Minahan, C. L., and Sabapathy, S. Caffeine improves supramaximal cycling but not the rate of anaerobic energy release. Eur.J Appl Physiol 2010;109(2):287-295. PubMed
- Buscemi, S., Verga, S., Batsis, J. A., Donatelli, M., Tranchina, M. R., Belmonte, S., Mattina, A., Re, A., and Cerasola, G. Acute effects of coffee on endothelial function in healthy subjects. Eur.J Clin Nutr. 2010;64(5):483-489. PubMed
- Rigato, I., Blarasin, L., and Kette, F. Severe hypokalemia in 2 young bicycle riders due to massive caffeine intake. Clin J Sport Med. 2010;20(2):128-130. PubMed
- Mevcha, A., Gulur, D. M., and Gillatt, D. Diagnosing urological disorders in ageing men. Practitioner 2010;254(1726):25-9, 2.
- Banko, L. T., Haq, S. A., Rainaldi, D. A., Klem, I., Siegler, J., Fogel, J., Sacchi, T. J., and Heitner, J. F. Incidence of caffeine in serum of patients undergoing dipyridamole myocardial perfusion stress test by an intensive versus routine caffeine his
- Ernest, D., Chia, M., and Corallo, C. E. Profound hypokalaemia due to Nurofen Plus and Red Bull misuse. Crit Care Resusc. 2010;12(2):109-110. DOI
- Conen, D., Chiuve, S. E., Everett, B. M., Zhang, S. M., Buring, J. E., and Albert, C. M. Caffeine consumption and incident atrial fibrillation in women. Am J Clin Nutr 2010;92(3):509-514. PubMed
- Reis, J. P., Loria, C. M., Steffen, L. M., Zhou, X., van, Horn L., Siscovick, D. S., Jacobs, D. R., Jr., and Carr, J. J. Coffee, decaffeinated coffee, caffeine, and tea consumption in young adulthood and atherosclerosis later in life: the CARDIA study. A PubMed
- Clausen, T. Hormonal and pharmacological modification of plasma potassium homeostasis. Fundam.Clin Pharmacol 2010;24(5):595-605. PubMed
- Gronroos, N. N. and Alonso, A. Diet and risk of atrial fibrillation - epidemiologic and clinical evidence -. Circ.J 2010;74(10):2029-2038. PubMed
- Mostofsky, E., Schlaug, G., Mukamal, K. J., Rosamond, W. D., and Mittleman, M. A. Coffee and acute ischemic stroke onset: the Stroke Onset Study. Neurology 11-2-2010;75(18):1583-1588. PubMed
- Orozco-Gregorio, H., Mota-Rojas, D., Bonilla-Jaime, H., Trujillo-Ortega, M. E., Becerril-Herrera, M., Hernandez-Gonzalez, R., and Villanueva-Garcia, D. Effects of administration of caffeine on metabolic variables in neonatal pigs with peripartum asphyxia PubMed
- Li, G. Z., Zhang, N., Du, P., Yang, Y., Wu, S. L., Xiao, Y. X., Jin, R., Liu, L., Shen, H., and Dai, Y. Risk factors for interstitial cystitis/painful bladder syndrome in patients with lower urinary tract symptoms: a Chinese multi-center study. Chin Med
- Smits, P., Lenders, J. W., and Thien, T. Caffeine and theophylline attenuate adenosine-induced vasodilation in humans. Clin.Pharmacol.Ther. 1990;48(4):410-418. PubMed
- Rossignol, A. M. and Bonnlander, H. Caffeine-containing beverages, total fluid consumption, and premenstrual syndrome. Am.J.Public Health 1990;80(9):1106-1110. PubMed
- Jeppesen, U., Loft, S., Poulsen, H. E., and Brsen, K. A fluvoxamine-caffeine interaction study. Pharmacogenetics 1996;6(3):213-222. PubMed
- Smits, P., Corstens, F. H., Aengevaeren, W. R., Wackers, F. J., and Thien, T. False-negative dipyridamole-thallium-201 myocardial imaging after caffeine infusion. J Nucl.Med. 1991;32(8):1538-1541. DOI
- Wang Y, Yu X, Wu Y, Zhang D. Coffee and tea consumption and risk of lung cancer: a dose-response analysis of observational studies. Lung Cancer. 2012;78(2):169-70. PubMed
- Caldeira D, Martins C, Alves LB, Pereira H, Ferreira JJ, Costa J. Caffeine does not increase the risk of atrial fibrillation: a systematic review and meta-analysis of observational studies. Heart. 2013;99(19):1383-9. doi: 10.1136/heartjnl-2013-303950. Re PubMed
- Cheng M, Hu Z, Lu X, Huang J, Gu D. Caffeine intake and atrial fibrillation incidence: dose response meta-analysis of prospective cohort studies. Can J Cardiol. 2014 Apr;30(4):448-54. doi: 10.1016/j.cjca.2013.12.026. Epub 2014 2. Review. PubMed
- Chiaffarino F, Bravi F, Cipriani S, Parazzini F, Ricci E, Viganò P, La Vecchia C. Coffee and caffeine intake and risk of endometriosis: a meta-analysis. Eur J Nutr. 2014 Oct;53(7):1573-9. doi: 10.1007/s00394-014-0662-7. Epub 2014 31. PubMed
- Jiang W, Wu Y, Jiang X. Coffee and caffeine intake and breast cancer risk: an updated dose-response meta-analysis of 37 published studies. Gynecol Oncol. 2013 Jun;129(3):620-9. doi: 10.1016/j.ygyno.2013.03.014. Epub 2013 25. Review. PubMed
- Sanikini H, Dik VK, Siersema PD, Bhoo-Pathy N, Uiterwaal CS, Peeters PH, González CA, Zamora-Ros R, Overvad K, Tjønneland A, Roswall N, Boutron-Ruault MC, Fagherazzi G, Racine A, Kühn T, Katzke V, Boeing H, Trichopoulou A, Trichopoulos D, Lagiou P, Palli
- van der Hoeven N, Visser I, Schene A, van den Born BJ. Severe hypertension related to caffeinated coffee and tranylcypromine: a case report. Ann Intern Med. 2014 May 6;160(9):657-8. doi: 10.7326/L14-5009-8. No abstract available. PubMed
- Dixit S, Stein PK, Dewland TA, Dukes JW, Vittinghoff E, Heckbert SR, Marcus GM. Consumption of Caffeinated Products and Cardiac Ectopy. J Am Heart Assoc. 2016 26;5(1). pii: e002503. doi: 10.1161/JAHA.115.002503. PubMed
- Turati F, Galeone C, Talamini R, et al. Coffee, decaffeinated coffee, tea, and pancreatic cancer risk: a pooled-analysis of two Italian case-control studies. Eur J Cancer Prev 2011;20(4):287-92. PubMed
- Zuchinali P, Riberio PA, Pimentel M, da Rosa PR, Zimerman LI, Rohde LE. Effect of caffeine on ventricular arrhythmia: a systematic review and meta-analysis of experimental and clinical studies. Europace 2016 Feb;18(2):257-66. PubMed
- Acosta RD, Cash BD. Clinical effects of colonic cleansing for general health promotion: a systematic review. Am J Gastroenterol. 2009;104(11):2830-6. PubMed
- Kunitake Y, Mizoguchi Y, Sogawa R, et al. Effect of excessive coffee consumption on the clinical course of a patient with bipolar disorder: a case report and literature review. Clin Neuropharmacol. 2017 Jul/Aug;40(4):160-162. doi: 10.1097/WNF.00000000 PubMed
- Crippa A, Discacciati A, Larsson SC, Wolk A, Orsini N. Coffee consumption and mortality from all causes, cardiovascular disease, and cancer: a dose-response meta-analysis. Am J Epidemiol. 2014 Oct 15;180(8):763-75. doi: 10.1093/aje/kwu194. PubMed
- Loftfield E, Cornelis MC, Caporaso N, Yu K, Sinha R, Freedman N. Association of coffee drinking With mortality by genetic variation in caffeine metabolism: findings from the UK biobank. JAMA Intern Med. 2018 Aug 1;178(8):1086-1097. doi: 10.1001/jamaintern PubMed
- Lagier D, Nee L, Guieu R, et al. Peri-operative oral caffeine does not prevent postoperative atrial fibrillation after heart valve surgery with cardiopulmonary bypass: a randomized controlled clinical trial. Eur J Anaesthesiol. 2018 Apr 26. [Epub ahead of DOI
- Voskoboinik A, Kalman JM, Kistler PM. Caffeine and arrhythmias: time to grind the data. JACC: Clin Electrophysiol. 2018;4(4):425-32. PubMed
- Wikoff D, Welsh BT, Henderson R, et al. Systematic review of the potential adverse effects of caffeine consumption in healthy adults, pregnant women, adolescents, and children. Food Chem Toxicol 2017;109:585-648. PubMed
- Lee AH, Kabashneh S, Tsouvalas CP, et al. Proctocolitis from coffee enema. ACG Case Rep J. 2020;7(1):e00292. PubMed
- Tverdal A, Selmer R, Cohen JM, Thelle DS. Coffee consumption and mortality from cardiovascular diseases and total mortality: Does the brewing method matter? Eur J Prev Cardiol. 2020:2047487320914443. PubMed
- Yamakawa M, Wada K, Goto Y, et al. Associations between coffee consumption and all-cause and cause-specific mortality in a Japanese city: the Takayama study. Public Health Nutr. 2019;22(14):2561-2568. PubMed
- Zhou CD, Kuan AS, Reeves GK, et al. Coffee and pancreatic cancer risk among never-smokers in the UK prospective Million Women Study. Int J Cancer. 2019;145(6):1484-1492. PubMed
- Stojanovic E, Scanlan AT, Milanovic Z, Fox JL, Stankovic R, Dalbo VJ. Acute caffeine supplementation improves jumping, sprinting, and change-of-direction performance in basketball players when ingested in the morning but not evening. Eur J Sport Sci. 2021 PubMed
- Ruggiero E, Di Castelnuovo A, Costanzo S, et al. Daily coffee drinking is associated with lower risks of cardiovascular and total mortality in a general Italian population: Results from the Moli-sani study. J Nutr. 2020:nxaa365. PubMed
- Kim Y, Je Y, Giovannucci E. Coffee consumption and all-cause and cause-specific mortality: a meta-analysis by potential modifiers. Eur J Epidemiol. 2019 Aug;34(8):731-752. doi: 10.1007/s10654-019-00524-3. Epub 2019 May 4. PubMed
- Stevens LM, Linstead E, Hall JL, Kao DP. Association between coffee intake and incident heart failure risk: A machine learning analysis of the FHS, the ARIC Study, and the CHS. Circ Heart Fail. 2021:CIRCHEARTFAILURE119006799. PubMed
- Ribeiro EM, Alves M, Costa J, Ferreira JJ, Pinto FJ, Caldeira D. Safety of coffee consumption after myocardial infarction: A systematic review and meta-analysis. Nutr Metab Cardiovasc Dis. 2020;30(12):2146-2158. PubMed
- Grosso G, Micek A, Godos J, ET AL. Coffee consumption and risk of all-cause, cardiovascular, and cancer mortality in smokers and non-smokers: a dose-response meta-analysis. Eur J Epidemiol. 2016;31(12):1191-1205. PubMed
- Kim EJ, Hoffmann TJ, Nah G, Vittinghoff E, Delling F, Marcus GM. Coffee consumption and incident tachyarrhythmias: Reported behavior, mendelian randomization, and their interactions. JAMA Intern Med. 2021. PubMed
- Loftfield E, Freedman ND, Graubard BI, et al. Association of coffee consumption with overall and cause-specific mortality in a large US prospective cohort study. Am J Epidemiol. 2015;182(12):1010-22. PubMed
- Mesas AE, Leon-Muñoz LM, Rodriguez-Artalejo F, Lopez-Garcia E. The effect of coffee on blood pressure and cardiovascular disease in hypertensive individuals: a systematic review and meta-analysis. Am J Clin Nutr. 2011;94(4):1113-26. PubMed
- Miranda AM, Goulart AC, Benseñor IM, Lotufo PA, Marchioni DM. Moderate coffee consumption is associated with lower risk of mortality in prior Acute Coronary Syndrome patients: a prospective analysis in the ERICO cohort. Int J Food Sci Nutr. 2020:1-11.
- Nordestgaard AT, Nordestgaard BG. Coffee intake, cardiovascular disease and all-cause mortality: observational and Mendelian randomization analyses in 95?000-223?000 individuals. Int J Epidemiol. 2016;45(6):1938-1952. PubMed
- Zhang Y, Yang H, Li S, Li WD, Wang Y. Consumption of coffee and tea and risk of developing stroke, dementia, and poststroke dementia: A cohort study in the UK Biobank. PLoS Med 2021;18(11):e1003830. PubMed
- Chan L, Hong CT, Bai CH. Coffee consumption and the risk of cerebrovascular disease: a meta-analysis of prospective cohort studies. BMC Neurol 2021;21(1):380. PubMed
- Welty TE, Gidal BE, Duan J, et al. Coffee and cigarette smoking interactions with lamotrigine. Epilepsy Behav 2021;116:107741. PubMed
- Zheng KH, Zhu K, Wactawski-Wende J, et al. Caffeine intake from coffee and tea and invasive breast cancer incidence among postmenopausal women in the Women's Health Initiative. Int J Cancer 2021;149(12):2032-2044. PubMed
- Wang S, Li X, Yang Y, et al. Does coffee, tea and caffeine consumption reduce the risk of incident breast cancer? A systematic review and network meta-analysis. Public Health Nutr 2021;24(18):6377-6389. PubMed
- Alshabi AM, Alkahtani SA, Shaikh IA, Habeeb MS. Caffeine modulates pharmacokinetic and pharmacodynamic profiles of pioglitazone in diabetic rats: Impact on therapeutics. Saudi Med J 2021;42(2):151-160. PubMed
- Gleason JL, Sundaram R, Mitro SD, et al. Association of maternal caffeine consumption during pregnancy with child growth. JAMA Netw Open. 2022;5(10):e2239609. PubMed
- Teramoto M, Yamagishi K, Muraki I, Tamakoshi A, Iso H. Coffee and green tea consumption and cardiovascular disease mortality among people with and without hypertension. J Am Heart Assoc 2023;12(2):e026477. PubMed
- Han M, Oh Y, Myung SK. Coffee intake and risk of hypertension: A meta-analysis of cohort studies. J Korean Med Sci 2022;37(45):e332. PubMed
- Sehrawat O, Mehra NS, Kowlgi NG, et al. Association between coffee consumption and incident atrial fibrillation (from the Multi-Ethnic Study of Atherosclerosis [MESA]). Am J Cardiol 2023;186:5-10. PubMed
- Marcus GM, Rosenthal DG, Nah G, et al. Acute effects of coffee consumption on health among ambulatory adults. N Engl J Med. 2023;388(12):1092-1100. PubMed
- Abtan J, Ducrocq G, Elbez Y, et al. Association between coffee or tea consumption and cardiovascular outcomes in patients with stable coronary artery disease: Analysis from the CLARIFY registry. Arch Cardiovasc Dis 2023;116(8-9):382-389. PubMed
Pomegranate 27 references
- Igea JM, Cuesta J, Cuevas M, et al. Adverse reaction to pomegranate ingestion. Allergy 1991;46:472-4. DOI
- Gaig P, Bartolome B, Lleonart R, et al. Allergy to pomegranate (Punica granatum). Allergy 1999;54:287-8.
- Aviram M, Dornfeld L. Pomegranate juice consumption inhibits serum angiotensin converting enzyme activity and reduces systolic blood pressure. Atherosclerosis 2001;158:195-8. PubMed
- Valsecchi R, Reseghetti A, Leghissa P, et al. Immediate contact hypersensitivity to pomegranate. Contact Dermatitis 1998;38:44-5. PubMed
- Esmaillzadeh A, Tahbaz F, Gaieni I, et al. Concentrated pomegranate juice improves lipid profiles in diabetic patients with hyperlipidemia. J Med Food 2004;7:305-8. PubMed
- Aviram M, Rosenblat M, Gaitini D, et al. Pomegranate juice consumption for 3 years by patients with carotid artery stenosis reduces common carotid intima-media thickness, blood pressure and LDL oxidation. Clin Nutr 2004;23:423-33. DOI
- Hidaka M, Okumura M, Fujita K, et al. Effects of pomegranate juice on human cytochrome p450 3A (CYP3A) and carbamazepine pharmacokinetics in rats. Drug Metab Dispos 2005;33:644-8. PubMed
- Loren DJ, Seeram NP, Schulman RN, Holtzman DM. Maternal dietary supplementation with pomegranate juice is neuroprotective in an animal model of neonatal hypoxic-ischemic brain injury. Pediatr Res 2005;57:858-64. PubMed
- Kim ND, Mehta R, Yu W, et al. Chemopreventive and adjuvant therapeutic potential of pomegranate (Punica granatum) for human breast cancer. Breast Cancer Res Treat 2002;71:203-17. PubMed
- Sorokin AV, Duncan B, Panetta R, Thompson PD. Rhabdomyolysis associated with pomegranate juice consumption. Am J Cardiol 2006;98:705-6. PubMed
- Farkas D, Oleson LE, Zhao Y, et al. Pomegranate juice does not impair clearance of oral or intravenous midazolam, a probe for cytochrome P450-3A activity: comparison with grapefruit juice. J Clin Pharmacol 2007;47:286-94. PubMed
- Yeo C, Shon J, Liu K, et al. The effects of pomegranate juice on the pharmacokinetics of simvastatin in healthy Korean subjects (PI-63). Clin Pharmacol Ther 2006;79:23.
- Farkas D, Greenblatt DJ. Influence of fruit juices on drug disposition: discrepancies between in vitro and clinical studies. Expert Opin Drug Metab Toxicol 2008;4:381-93.
- Nagata M, Hidaka M, Sekiya H, et al. Effects of pomegranate juice on human cytochrome P450 2C9 and tolbutamide pharmacokinetics in rats. Drug Metab Dispos 2007;35:302-5. PubMed
- Komperda KE. Potential interaction between pomegranate juice and warfarin. Pharmacotherapy 2009;29:1002-6. PubMed
- Gangemi S, Mistrello G, Roncarolo D, et al. Pomegranate-dependent exercise-induced anaphylaxis. J Investig Allergol Clin Immunol 2008;18:491-2.
- Misaka S, Nakamura R, Uchida S, et al. Effect of 2 weeks' consumption of pomegranate juice on the pharmacokinetics of a single dose of midazolam: an open-label, randomized, single-center, 2-period crossover study in healthy Japanese volunteers. Clin Ther PubMed
- Jarvis S, Li C, Bogle RG. Possible interaction between pomegranate juice and warfarin. Emerg Med J 2010;27:74-5. PubMed
- Esmaillzadeh, A., Tahbaz, F., Gaieni, I., Alavi-Majd, H., and Azadbakht, L. Cholesterol-lowering effect of concentrated pomegranate juice consumption in type II diabetic patients with hyperlipidemia. Int J Vitam.Nutr Res 2006;76(3):147-151. PubMed
- Forest, C. P., Padma-Nathan, H., and Liker, H. R. Efficacy and safety of pomegranate juice on improvement of erectile dysfunction in male patients with mild to moderate erectile dysfunction: a randomized, placebo-controlled, double-blind, crossover study PubMed
- Wright, H. and Pipkin F. B. Pomegranates (Punica granatum), kiwifruit (Actinidia deliciosa) and blood pressure: a pilot study. Proceedings of the Nutrition Society 2008;67(8):1.
- Sohrab G, Sotoodeh G, Siasi F, et al. Effect of pomegranate juice consumption on blood pressure in type 2 diabetic patients. Iranian Journal of Endocrinology and Metabolism 2008;9:399-405, 470.
- Enrique E, Utz M, De Mateo JA, et al. Allergy to lipid transfer proteins: cross-reactivity among pomegranate, hazelnut, and peanut. Ann Allergy Asthma Immunol 2006;96(1):122-3. PubMed
- Hanley MJ, Masse G, Harmatz JS, et al. Pomegranate juice and pomegranate extract do not impair oral clearance of flurbiprofen in human volunteers: divergence from in vitro results. Clin Pharmacol Ther 2012;92(5):651-7. PubMed
- Paller CJ, Ye X, Wozniak PJ, et al. A randomized phase II study of pomegranate extract for men with rising PSA following initial therapy for localized prostate cancer. Prostate Cancer Prostatic Dis 2013;16(1):50-5. PubMed
- Park SJ, Yeo CW, Shim EJ, et al. Pomegranate juice does not affect the disposition of simvastatin in healthy subjects. Eur J Drug Metab Pharmacokinet 2016;41(4):339-44. PubMed
- Ross MM, Cherkerzian S, Mikulis ND, et al. A randomized controlled trial investigating the impact of maternal dietary supplementation with pomegranate juice on brain injury in infants with IUGR. Sci Rep. 2021;11(1):3569. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC