
Restore Ingredients & Drug Interactions
What is this page for?
First and foremost: checking Restore against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
Restore is a dietary supplement by Herbal Nutrition with 5 active ingredients. Its ingredients are commonly taken for preventing neural tube birth defects, treating or preventing folate deficiency, supporting pregnancy health.Based on those ingredients, 1,343 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Black Pepper Extract, Grape Seed Extract, Vitamin B3. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against Restore by Herbal Nutrition
Ask about any prescription or over-the-counter medication and we check it for interactions with Restore by Herbal Nutrition — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of Restore by Herbal Nutrition
Our pharmacy team’s full take, with four database checks built into the cards below — a summary of what is known, not a grade of the product itself.
What’s inside
Low disclosure
Restore contains five active ingredients. Folic acid is a B vitamin that helps your body make new cells and is often used to prevent or treat folate deficiency.
Red yeast rice is a fermented rice product that contains statin-like compounds and has been studied for cholesterol support. Grape seed extract comes from grape seeds and has been researched for circulation and antioxidant properties.
Black pepper extract supplies piperine, black pepper's active compound, which may enhance absorption of other ingredients. The product also contains four inactive ingredients (Hypromellose, Microcrystalline Cellulose, Magnesium Stearate, and Silicon Dioxide) that serve as capsule material and binders.
Does it work?
Moderate evidence
Folic acid is effective for treating folate deficiency and likely effective for preventing neural tube birth defects (like spina bifida) and reducing methotrexate side effects. It's possibly effective for depression, phenytoin-induced gingival hyperplasia (swollen gums from seizure medication), and cognitive impairment.
Red yeast rice is possibly effective for HIV/AIDS-related dyslipidemia (abnormal cholesterol in people with HIV) and possibly effective for myocardial infarction (heart attack) prevention, though evidence is limited. Grape seed extract is possibly effective for chronic venous insufficiency (poor circulation in the legs) but possibly ineffective for chemotherapy-induced nausea, hay fever, and obesity.
For black pepper extract, the evidence we hold is insufficient to rate it for hay fever, asthma, athletic performance, headache, depression, or diarrhea.
How safe is it?
Well-documented data
Folic acid is generally well tolerated at recommended doses for most adults. At doses of 5 mg daily, some people experience abdominal cramps, diarrhea, and rash; at 15 mg daily, bitter taste, confusion, hyperactivity, impaired judgment, irritability, nausea, and sleep disturbances have been reported.
Rarely, long-term use has been associated with cancer, cardiovascular complications, liver injury, and seizures. Very large doses can also cause or worsen vitamin B12 deficiency neuropathy (nerve damage), and folic acid should never be used to self-treat anemia without medical evaluation, as it can mask pernicious anemia and lead to serious neurological damage.
Red yeast rice works like a statin drug and carries similar risks — it can cause liver damage and muscle breakdown (rhabdomyolysis), though these are rare. It's unsafe during pregnancy and should be avoided while breastfeeding because safety data are lacking.
Grape seed extract appears generally well tolerated; the whole fruit and extracts are safe for most people as food, though concentrated supplements during pregnancy should be avoided due to limited safety data. Black pepper as a food spice is safe; concentrated supplements should be used cautiously, and pregnancy and breastfeeding safety data are not well studied.
Meds to double-check
Moderate interaction found
Before taking Restore, check with your pharmacist if you're on seizure medications (phenytoin, phenobarbital, primidone), cancer or chemotherapy drugs (methotrexate, capecitabine, 5-fluorouracil), or any statin (atorvastatin, etc.) — all moderate interactions. Also double-check if you take gemfibrozil, cyclosporine, high-dose niacin, blood thinners (anticoagulants or antiplatelet drugs), propranolol, nevirapine, rifampin, or theophylline.
The red yeast rice and black pepper ingredients may significantly raise levels of some medications or lower the effect of others.
The bottom line
Scorecard at a glanceFormula with limited ingredient disclosure with some supporting evidence for its stated purpose. Moderate medication interactions have been identified, and safety information is well characterized.
Restore is a multi-ingredient supplement that may appeal to people managing folate deficiency or seeking cholesterol support through red yeast rice. However, anyone taking seizure medications, cancer drugs, immunosuppressants, statins, or beta-blockers should absolutely talk to their pharmacist before starting it — the interactions are real and potentially serious.
Pregnant or breastfeeding women should not use red yeast rice, and folic acid in late pregnancy may carry some risk; discuss this product with your doctor beforehand.
Educational only — not medical advice; always confirm with your pharmacist. Our editorial policy · How we use AI
Assessment coverage: 5 of 5 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Sep 25, 2024.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about Restore, straight from the product label.
| Brand | Herbal Nutrition |
|---|---|
| Barcode (UPC) | 743970258261 |
| Net contents | 60 Capsule(s) |
| Market status | On market |
| Date entered into DSLD | Sep 25, 2024 |
| DSLD ID | 317389 |
| Product type | Botanical With Nutrients |
| Supplement form | Capsule |
| Dietary claims / uses | All Other, Structure/Function |
| Intended target group(s) | Adult (18 - 50 Years), Women (not pregnant or lactating) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
Supplement Facts
The label details for Restore by Herbal Nutrition, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Folic Acid | 100 mcg | 25% |
| Proprietary Blend | 545 mg | -- |
| Red Yeast Rice | 0 NP | -- |
| Vitamin B3 | 7 mg | 35% |
| Grape Seed Extract | 0 NP | -- |
| Black Pepper Extract | 0 NP | -- |
Other ingredients: Hypromellose, Microcrystalline Cellulose, Magnesium Stearate, Silicon Dioxide
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
Formula
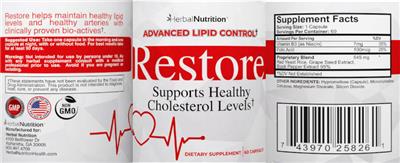
Restore helps maintain healthy lipid levels and healthy arteries with clinically proven bio-actives.
Suggested/Recommended/Usage/Directions
Suggested Use: Take one capsule in the morning and one capsule at night, with or without food. For best results take for at least 90 days.
Precautions
Warning: Not intended for use by persons under 18.
As with any herbal supplement consult with a medical professional prior to use.
Avoid if you are pregnant or lactating.
FDA Disclaimer Statement
These statements have not been evaluated by the Food and Drug Administration. This product is not intended to diagnose, treat, cure, or prevent any disease.
Seals/Symbols
GMP Good Manufacturing Practice Consistent Quality Made in the USA
Formulation
Non GMO
Advanced Lipid control
Supports healthy cholesterol levels
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
Restore by Herbal Nutrition label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in Restore by Herbal Nutrition
These are the 5 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Capsule(s) Dosage formCapsule Servings per container60 Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Folic Acid
Interacts with40 drugs
Folic acid is the man-made form of vitamin B9 and is one of the most well-studied supplements, especially for preventing serious birth defects when ta...
Folic Acid monograph & interactionsProprietary Blend
Vitamin B3
Interacts with727 drugs
Niacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescr...
Vitamin B3 monograph & interactionsOther (inactive) ingredients: Hypromellose, Microcrystalline Cellulose, Magnesium Stearate, Silicon Dioxide. These complete the product’s ingredient list but are not active constituents.
Restore by Herbal Nutrition Drug Interactions
HelloPharmacist Interaction Report
Restore by Herbal Nutrition contains five active ingredients, and the ones we checked show moderate-severity interactions with a broad range of medications.
Folic acid is the primary concern — it can antagonize seizure medications like phenytoin (Dilantin) and phenobarbital (Luminal), reducing their effectiveness and increasing seizure risk. It also reduces the efficacy of methotrexate (a cancer drug) and can worsen toxicity from capecitabine (Xeloda) and 5-fluorouracil (chemotherapy drugs).
Read the full breakdown — every affected drug type, severity by severity
Red yeast rice, which contains the statin-like compound lovastatin, interacts with other cholesterol-lowering statins, drugs that inhibit the CYP3A4 enzyme system, cyclosporine (an immunosuppressant), gemfibrozil (a fibrate), and high-dose niacin — all carrying moderate risk of muscle damage or liver injury. Grape seed extract may alter how your body metabolizes many drugs through multiple enzyme systems (CYP1A2, CYP2D6, CYP3A4, and CYP2E1), and it can reduce cyclosporine absorption or theoretically increase bleeding risk with blood thinners (anticoagulants) and antiplatelet drugs.
Black pepper extract can raise blood levels of phenytoin, propranolol (a beta-blocker), nevirapine (an antiretroviral), rifampin (an antibiotic), theophylline (a bronchodilator), and several others, all moderate severity.
We could not check vitamin B3 — no interaction data is on file for it. Altogether, these interactions span 1,197 individual medications.
Before starting this product, use the medication checker below to search for your exact prescriptions.
Check your own medications below · Editorial policy · How we use AI
Want to check YOUR meds against Restore?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in Restore interact with 1,343 drugs. Click any drug to see the details.
5 of the 5 ingredients in Restore interact with drugs. Each result below shows which ingredient is responsible. Black Pepper Extract Grape Seed Extract Vitamin B3 Red Yeast Rice Folic Acid
6-mercaptopurinePurinethol
How 6-mercaptopurine interacts with Restore — through 2 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + 6-mercaptopurine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + 6-mercaptopurine interactionAdo-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with Restore — through 2 ingredients. Tap an ingredient for the detail:
Grape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Ado-trastuzumab Emtansine interactionBlack Pepper ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Black Pepper Extract + Ado-trastuzumab Emtansine interactionAbacavir Sulfate, Dolutegravir, LamivudineTriumeq
How Abacavir Sulfate, Dolutegravir, Lamivudine interacts with Restore — through 2 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Abacavir Sulfate, Dolutegravir, Lamivudine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Abacavir Sulfate, Dolutegravir, Lamivudine interactionAbacavir, LamivudineEpzicom
How Abacavir, Lamivudine interacts with Restore — through 2 ingredients. Tap an ingredient for the detail:
Vitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Abacavir, Lamivudine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Abacavir, Lamivudine interactionAbametapirXeglyze
How Abametapir interacts with Restore — through 1 ingredient. Tap an ingredient for the detail:
Red Yeast RiceCytochrome P450 3a4 (cyp3a4) Inhibitors Moderate
Interaction Summary
Theoretically, drugs that inhibit the CYP3A4 enzymes might increase levels of lovastatin from red yeast rice.
Read the full Red Yeast Rice + Abametapir interactionAbciximabReoPro
How Abciximab interacts with Restore — through 3 ingredients. Tap an ingredient for the detail:
Vitamin B3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Vitamin B3 + Abciximab interactionGrape Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, grape extracts may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Grape Seed Extract + Abciximab interactionBlack Pepper ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Black Pepper Extract + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with Restore — through 2 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Black Pepper Extract + Abemaciclib interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Abemaciclib interactionAbiraterone
How Abiraterone interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Grape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Abiraterone interactionRed Yeast RiceCytochrome P450 3a4 (cyp3a4) Inhibitors, Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, drugs that inhibit the CYP3A4 enzymes might increase levels of lovastatin from red yeast rice.
Read the full Red Yeast Rice + Abiraterone interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Abiraterone interactionBlack Pepper ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Black Pepper Extract + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Black Pepper Extract + Abiraterone Acetate interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Abiraterone Acetate interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Abiraterone Acetate interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with Restore — through 3 ingredients. Tap an ingredient for the detail:
Vitamin B3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Vitamin B3 + Abrocitinib interactionBlack Pepper ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Black Pepper Extract + Abrocitinib interactionGrape Seed ExtractCytochrome P450 2c9 (cyp2c9) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
It is unclear if grape juice or grape seed extract inhibits CYP2C9; research is conflicting.
Read the full Grape Seed Extract + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with Restore — through 2 ingredients. Tap an ingredient for the detail:
Grape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Acalabrutinib interactionBlack Pepper ExtractCytochrome P450 3a4 (cyp3a4) Substrates, P-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Black Pepper Extract + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with Restore — through 3 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Read the full Black Pepper Extract + Acarbose interactionVitamin B3Hepatotoxic Drugs, Antidiabetes Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acarbose interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with Restore — through 2 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acebutolol interactionVitamin B3Hepatotoxic Drugs, Antihypertensive Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with Restore — through 3 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Black Pepper Extract + Acenocoumarol interactionVitamin B3Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Read the full Vitamin B3 + Acenocoumarol interactionGrape Seed ExtractAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, grape extracts may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Grape Seed Extract + Acenocoumarol interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Grape Seed ExtractCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, grape seed extract might increase the levels of CYP2E1 substrates.
Read the full Grape Seed Extract + Acetaminophen interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen interactionBlack Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Aspirin interactionVitamin B3Aspirin, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Large doses of aspirin might alter the clearance of niacin.
Read the full Vitamin B3 + Acetaminophen, Aspirin interactionGrape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Acetaminophen, Aspirin interactionBlack Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Anticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractAnticoagulant/antiplatelet Drugs, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Black Pepper Extract + Acetaminophen, Aspirin, Caffeine interactionVitamin B3Hepatotoxic Drugs, Anticoagulant/antiplatelet Drugs +1 Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Aspirin, Caffeine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Aspirin, Caffeine interactionGrape Seed ExtractAnticoagulant/antiplatelet Drugs, Cytochrome P450 2e1 (cyp2e1) Substrates +2 Moderate
Interaction Summary
Theoretically, grape extracts may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Grape Seed Extract + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Grape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionBlack Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Butalbital interactionGrape Seed ExtractCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, grape seed extract might increase the levels of CYP2E1 substrates.
Read the full Grape Seed Extract + Acetaminophen, Butalbital interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Butalbital interactionBlack Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates Minor
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen, Butalbital, Caffeine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Butalbital, Caffeine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Butalbital, Caffeine interactionGrape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +1 Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Grape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionBlack Pepper ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Black Pepper Extract + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Butalbital, Caffeine, Codeine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Butalbital, Codeine interactionBlack Pepper ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Black Pepper Extract + Acetaminophen, Butalbital, Codeine interactionGrape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +1 Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Acetaminophen, Butalbital, Codeine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Vitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Butalbital, Codeine Phosphate interactionBlack Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Butalbital, Codeine Phosphate interactionGrape Seed ExtractCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, grape seed extract might increase the levels of CYP2E1 substrates.
Read the full Grape Seed Extract + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Black Pepper Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +2 Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Caffeine, Codeine interactionGrape Seed ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
Read the full Grape Seed Extract + Acetaminophen, Caffeine, Codeine interactionBlack Pepper ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Black Pepper Extract + Acetaminophen, Caffeine, Codeine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Vitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Caffeine, Codeine, Salicylamide interactionBlack Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Caffeine, Codeine, Salicylamide interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Black Pepper Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Caffeine, Dihydrocodeine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Red Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Caffeine, Isometheptene interactionGrape Seed ExtractCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, grape seed extract might increase the levels of CYP2E1 substrates.
Read the full Grape Seed Extract + Acetaminophen, Caffeine, Isometheptene interactionBlack Pepper ExtractCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
Read the full Black Pepper Extract + Acetaminophen, Caffeine, Isometheptene interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Black Pepper ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
Read the full Black Pepper Extract + Acetaminophen, Caffeine, Pyrilamine interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Caffeine, Pyrilamine interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Caffeine, Pyrilamine interactionGrape Seed ExtractCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
Read the full Grape Seed Extract + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with Restore — through 4 ingredients. Tap an ingredient for the detail:
Grape Seed ExtractCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, grape seed extract might increase the levels of CYP2E1 substrates.
Read the full Grape Seed Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionBlack Pepper ExtractCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
Read the full Black Pepper Extract + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin B3Hepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Read the full Vitamin B3 + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionRed Yeast RiceHepatotoxic Drugs Moderate
Interaction Summary
Theoretically, concomitant use might increase the risk of liver damage.
Read the full Red Yeast Rice + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionEach ingredient & the kinds of drugs it affects
For each ingredient in Restore with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Black Pepper Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, black pepper might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit platelet aggregation. This has not been reported in humans.
Antidiabetes Drugs
Theoretically, black pepper might increase the risk of hypoglycemia when taken with antidiabetes drugs.
Animal research shows that piperine, a constituent of black pepper, can reduce blood glucose levels. Monitor blood glucose levels closely. Dose adjustments might be necessary.
Atorvastatin (Lipitor)
Theoretically, black pepper might increase blood levels of atorvastatin.
Animal research shows that taking piperine, a constituent of black pepper, 35 mg/kg can increase the maximum serum concentration of atorvastatin three-fold. This has not been reported in humans.
Cyclosporine (Neoral, Sandimmune)
Theoretically, black pepper might increase the effects and side effects of cyclosporine.
In vitro research shows that piperine, a constituent of black pepper, increases the bioavailability of cyclosporine. This has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP2D6.
In vitro research suggests that some constituents of black pepper inhibit CYP2D6. This has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, black pepper might increase levels of drugs metabolized by CYP3A4.
In vitro research and pharmacokinetic simulation data suggest that piperine, a constituent of black pepper, as well as the pepper fruit seem to inhibit CYP3A4. This has not been reported in humans.
Lithium
Theoretically, black pepper might increase blood levels of lithium due to its diuretic effects. The dose of lithium might need to be reduced.
Black pepper is thought to have diuretic properties.
Nevirapine (Viramune)
Black pepper might increase blood levels of nevirapine.
Clinical research shows that piperine, a constituent of black pepper, increases the plasma concentration of nevirapine. However, no adverse effects were observed in this study.
P-Glycoprotein Substrates
Theoretically, black pepper might increase levels of P-glycoprotein substrates.
In vitro research shows that piperine, a constituent of black pepper, seems to inhibit P-glycoprotein.
Pentobarbital (Nembutal)
Theoretically, black pepper might increase the sedative effects of pentobarbital.
Animal research shows that piperine, a constituent of black pepper, increases pentobarbital-induced sleeping time.
Phenytoin (Dilantin)
Black pepper might increase blood levels of phenytoin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption, slow elimination, and increase levels of phenytoin. Taking a single dose of black pepper 1 gram along with phenytoin seems to double the serum concentration of phenytoin. Consuming a soup with black pepper providing piperine 44 mg/200 mL of soup along with phenytoin also seems to increase phenytoin levels when compared with consuming the same soup without black pepper.
Propranolol (Inderal)
Black pepper might increase blood levels of propranolol.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of propranolol.
Rifampin (Rifadin)
Black pepper might increase blood levels of rifampin.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and serum levels of rifampin.
Theophylline
Black pepper might increase blood levels of theophylline.
Clinical research shows that piperine, a constituent of black pepper, seems to increase absorption and slow elimination of theophylline.
Amoxicillin (Amoxil, Trimox)
Theoretically, black pepper might increase the effects and side effects of amoxicillin.
Animal research shows that taking piperine, a constituent of black pepper, with amoxicillin increases plasma levels of amoxicillin. This has not been reported in humans.
Carbamazepine (Tegretol)
Theoretically, black pepper might increase blood levels of carbamazepine, potentially increasing the effects and side effects of carbamazepine.
One clinical study in patients taking carbamazepine 300 mg or 500 mg twice daily shows that taking a single 20 mg dose of purified piperine, a constituent of black pepper, increases carbamazepine levels. Piperine may increase carbamazepine absorption by increasing blood flow to the GI tract, increasing the surface area of the small intestine, or inhibiting cytochrome P450 3A4 (CYP3A4) in the gut wall. Absorption was significantly increased by 7-10 mcg/mL/hour. The time to eliminate carbamazepine was also increased by 4-8 hours. Although carbamazepine levels were increased, this did not appear to increase side effects. In vitro research also shows that piperine can increase carbamazepine levels by 11% in a time-dependent manner.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, black pepper might decrease levels and clinical effects of drugs metabolized by CYP1A2.
In vitro research suggests that black pepper induces CYP1A2. This has not been reported in humans.
Grape Seed Extract
Anticoagulant/Antiplatelet Drugs
Theoretically, grape extracts may have antiplatelet effects and may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
In vitro evidence suggests that grape extracts might decrease platelet aggregation.
Cyclosporine (Neoral, Sandimmune)
Ingesting grape juice with cyclosporine can reduce cyclosporine absorption.
A small pharmacokinetic study in healthy young adults shows that intake of purple grape juice 200 mL along with cyclosporine can decrease the absorption of cyclosporine by up to 30% when compared with water. Separate doses of grape juice and cyclosporine by at least 2 hours to avoid this interaction.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, grape juice might reduce the levels of CYP1A2 substrates.
A small pharmacokinetic study in healthy adults shows that ingestion of 200 mL of grape juice decreases phenacetin plasma levels. This is thought to be due to induction of CYP1A2.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, grape seed extract may increase the levels of CYP2D6 substrates.
In vitro evidence suggests that grape seed extract might inhibit CYP2D6 enzymes. However, this interaction has not been reported in humans.
Cytochrome P450 2E1 (Cyp2E1) Substrates
Theoretically, grape seed extract might increase the levels of CYP2E1 substrates.
In vitro and animal research suggests that grape seed proanthocyanidin extract inhibits CYP2E1 enzymes. However, this interaction has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
It is unclear if grape seed extract inhibits or induces CYP3A4; research is conflicting.
In vitro evidence suggests that grape seed extract might inhibit CYP3A4 enzymes. However, evidence from animal research shows that grape seed extract may induce CYP3A4 in the liver. So far, these interactions have not been reported in humans.
Midazolam (Versed)
Theoretically, long-term intake of grape seed extract might decrease the effects of midazolam.
Animal research shows that subchronic ingestions of grape seed extract can increase the elimination of intravenous midazolam by increasing hepatic CYP3A4 activity. Single doses of grape seed extract do not appear to affect midazolam elimination.
Phenacetin
Grape juice might decrease phenacetin absorption.
A small pharmacokinetic study in healthy adults shows that ingestion of 200 mL of grape juice decreases phenacetin plasma levels. This is thought to be due to induction of cytochrome P450 1A2 (CYP1A2).
Cytochrome P450 2C9 (Cyp2C9) Substrates
It is unclear if grape juice or grape seed extract inhibits CYP2C9; research is conflicting.
In vitro evidence shows that grape seed extract or grape juice might inhibit CYP2C9 enzymes. However, a small pharmacokinetic study in healthy adults shows that drinking 8 ounces of grape juice once does not affect the clearance of flurbiprofen, a probe-drug for CYP2C9 metabolism. The effects of continued grape juice consumption are unclear.
Vitamin B3
Alcohol (Ethanol)
Concomitant use of alcohol and niacin might increase the risk of flushing and hepatotoxicity.
Alcohol can exacerbate the flushing and pruritus associated with niacin. Large doses of niacin might also exacerbate liver dysfunction associated with chronic alcohol use. A case report describes delirium and lactic acidosis in a patient taking niacin 3 grams daily who ingested 1 liter of wine. Advise patients to avoid large amounts of alcohol while taking niacin.
Allopurinol (Zyloprim)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as allopurinol.
Large doses of niacin can reduce urinary excretion of uric acid, potentially resulting in hyperuricemia. Doses of uricosurics such as allopurinol might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Anticoagulant/Antiplatelet Drugs
Theoretically, niacin may have additive effects when used with anticoagulant or antiplatelet drugs.
Several cases of clotting factor synthesis deficiency and coagulopathy have been reported in patients taking sustained-release niacin. Also, thrombocytopenia has been reported in patients treated with niacin or niacin plus lovastatin.
Antidiabetes Drugs
Niacin can increase blood glucose levels and may diminish the effects of antidiabetes drugs.
Niacin impairs glucose tolerance in a dose-dependent manner, probably by causing or aggravating insulin resistance and increasing hepatic production of glucose. In diabetes patients, niacin 4.5 grams daily for 5 weeks can increase plasma glucose by an average of 16% and glycated hemoglobin (HbA1c) by 21%. However, lower doses of 1.5 grams daily or less appear to have minimal effects on blood glucose. In some patients, glucose levels increase when niacin is started, but then return to baseline when a stable dose is reached. Up to 35% of patients with diabetes may need adjustments in hypoglycemic therapy when niacin is added.
Antihypertensive Drugs
Theoretically, niacin may increase the risk of hypotension when used with antihypertensive drugs.
The vasodilating effects of niacin can cause hypotension. Furthermore, some clinical evidence suggests that a one-hour infusion of niacin can reduce systolic, diastolic, and mean blood pressure in hypertensive patients. This effect is not observed in normotensive patients.
Bile Acid Sequestrants
Bile acid sequestrants can bind niacin and decrease absorption. Separate administration by 4-6 hours to avoid an interaction.
In vitro studies show that colestipol (Colestid) binds about 98% of available niacin and cholestyramine (Questran) binds 10% to 30%.
Gemfibrozil (Lopid)
Theoretically, concomitant use of niacin and gemfibrozil might increase the risk of myopathy in some patients.
A case of myopathy from concomitant use of niacin and gemfibrozil has been reported. Niacin alone has also been associated with cases of myopathy. Using gemfibrozil with niacin might further increase the risk of developing myopathy.
Hepatotoxic Drugs
Theoretically, concomitant use of niacin and hepatotoxic drugs might increase the risk of hepatotoxicity.
Niacin has been associated with cases of liver toxicity, especially when used in pharmacologic doses. Sustained-release niacin preparations appear to be associated with a higher risk of hepatotoxicity than immediate-release niacin.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, concomitant use of niacin and statins might increase the risk of myopathy and rhabdomyolysis in some patients.
Some case reports have raised concerns that niacin might increase the risk of myopathy and rhabdomyolysis when combined with statins. However, a significantly increased risk of myopathy has not been demonstrated in clinical trials, including those using an FDA-approved combination of lovastatin and niacin (Advicor).
Probenecid (Benemid)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as probenecid.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as probenecid might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Sulfinpyrazone (Anturane)
Theoretically, niacin might antagonize the therapeutic effects of uricosurics such as sulfinpyrazone.
Large doses of niacin reduce urinary excretion of uric acid, potentially causing hyperuricemia. Doses of uricosurics such as sulfinpyrazone might need to be increased to maintain control of gout in patients who start taking niacin. People who have frequent attacks of gout despite uricosuric therapy should avoid niacin.
Thyroid Hormone
Theoretically, niacin might antagonize the therapeutic effects of thyroid hormones.
Clinical research and case reports suggests that taking niacin can reduce serum levels of thyroxine-binding globulin by up to 25% and moderately reduce levels of thyroxine (T4). Patients taking thyroid hormone for hypothyroidism might need dose adjustments when using niacin.
Transdermal Nicotine (Nicoderm)
Theoretically, concomitant use of niacin and transdermal nicotine might increase the risk of flushing and dizziness.
Niacin and nicotine can both cause flushing and dizziness.
Warfarin (Coumadin)
There is limited evidence that niacin may increase the anticoagulant effects of warfarin.
In a case report, a patient on warfarin developed an elevated international normalized ratio (INR) of 3.9 after taking niacin for two weeks. The patient's INR was previously stable, ranging between 2 and 3 in recent months, and no other medication changes were identified. The elevated INR returned to therapeutic range within 4 days following the discontinuation of niacin.
Aspirin
Large doses of aspirin might alter the clearance of niacin.
Aspirin is often used with niacin to reduce niacin-induced flushing. Doses of 80-975 mg aspirin have been used, but 325 mg appears to be optimal. Aspirin also seems to reduce the clearance of niacin by competing for glycine conjugation. Taking aspirin 1 gram seems to reduce niacin clearance by 45%. This is probably a dose-related effect and not clinically significant with the more common aspirin dose of 325 mg.
Red Yeast Rice
Cyclosporine (Neoral, Sandimmune)
Theoretically, taking red yeast rice in combination with cyclosporine might increase the risk of myopathy.
Red yeast rice contains varying levels of the statin drug lovastatin. Cyclosporine has been reported to increase plasma levels of lovastatin by 5- to 20-fold, resulting in reports of myopathy and rhabdomyolysis.
Cytochrome P450 3A4 (Cyp3A4) Inhibitors
Theoretically, drugs that inhibit the CYP3A4 enzymes might increase levels of lovastatin from red yeast rice.
Red yeast rice contains varying levels of the statin drug lovastatin, which is metabolized by CYP3A4. Combining red yeast rice with CYP3A4 inhibitors might increase serum levels of lovastatin from red yeast rice.
Gemfibrozil (Lopid)
Theoretically, taking red yeast rice in combination with gemfibrozil might increase the risk of rhabdomyolysis.
Red yeast rice contains varying levels of the statin drug lovastatin. Gemfibrozil has been reported to increase the risk of rhabdomyolysis when used in combination with lovastatin.
Hepatotoxic Drugs
Theoretically, concomitant use might increase the risk of liver damage.
Red yeast rice contains varying levels of the drug lovastatin. Lovastatin can cause liver damage in some people. Some clinical research suggests that supplements containing red yeast rice might increase liver enzyme levels in some, but not all, participants. Cases of acute hepatitis have been associated with red yeast rice. Combining it with hepatotoxic drugs might further increase this risk.
Hmg-Coa Reductase Inhibitors ("Statins")
Theoretically, taking red yeast rice with other statins might increase the risk of potential adverse effects.
Red yeast rice contains varying levels of the statin drug lovastatin and might result in supratherapeutic levels when used with other statins. Based on evaluation of data from the US Food and Drug Administration's adverse event reporting system (FAERS), it is recommended that red yeast rice products be avoided in people taking prescription statins.
Niacin
Theoretically, taking red yeast rice in combination with high-dose niacin might increase the risk of rhabdomyolysis.
Red yeast rice contains varying levels of the statin drug lovastatin and has been linked to reports of myopathy. Niacin has been reported to increase the risk of rhabdomyolysis when used in combination with lovastatin.
Folic Acid
5-Fluorouracil
Theoretically, high doses of folic acid might increase the toxicity of 5-fluorouracil.
Increases in gastrointestinal side effects of 5-fluorouracil, such as stomatitis and diarrhea, have been described in two clinical studies when leucovorin, a form of folic acid, was administered with 5-fluorouracil.
Capecitabine (Xeloda)
Use of high-dose folic acid might contribute to capecitabine toxicity.
Clinical research suggests that higher serum folate levels are associated with an increased risk for moderate or severe toxicity during capecitabine-based treatment for colorectal cancer. Additionally, in one case report, taking folic acid 15 mg daily might have contributed to increased toxicity, including severe diarrhea, vomiting, edema, hand-foot syndrome, and eventually death, in a patient prescribed capecitabine.
Methotrexate (Trexall, Others)
Folic acid might reduce the efficacy of methotrexate as a cancer treatment when given concurrently.
Methotrexate exerts its cytotoxic effects by preventing conversion of folic acid to the active form needed by cells. There is some evidence that folic acid supplements reduce the efficacy of methotrexate in the treatment of acute lymphoblastic leukemia, and theoretically they could reduce its efficacy in the treatment of other cancers. Advise cancer patients to consult their oncologist before using folic acid supplements. In patients treated with long-term, low-dose methotrexate for rheumatoid arthritis (RA) or psoriasis, folic acid supplements can reduce the incidence of side effects, without reducing efficacy.
Phenobarbital (Luminal)
Folic acid might have antagonistic effects on phenobarbital and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of phenobarbital and worsening seizure control. Monitor closely for increased seizure activity.
Phenytoin (Dilantin)
Folic acid might reduce serum levels of phenytoin in some patients.
Folic acid may be a cofactor in phenytoin metabolism. Folic acid, in doses of 1 mg daily or more, can reduce serum levels of phenytoin in some patients. Increases in seizure frequency have been reported. If folic acid supplements are added to established phenytoin therapy, monitor serum phenytoin levels closely. If phenytoin and folic acid are started at the same time and continued together, adverse changes in phenytoin pharmacokinetics are avoided. Note that phenytoin also reduces serum folate levels.
Primidone (Mysoline)
Folic acid might have antagonistic effects on primidone and increase the risk for seizures.
Folic acid can have direct convulsant activity in some people, reversing the effects of primidone and worsening seizure control. Monitor closely for increased seizure activity. Note that primidone also reduces serum folate levels.
Pyrimethamine (Daraprim)
Folic acid might antagonize the effects of pyrimethamine.
Folic acid can antagonize the antiparasitic effects of pyrimethamine against toxoplasmosis and Pneumocystis carinii pneumonia. Folic acid doesn't antagonize the effects of pyrimethamine in the treatment of malaria, because malarial parasites cannot use exogenous folic acid. Use folinic acid as an alternative to folic acid when indicated.
Brand information
Manufacturer and brand details for Restore, from the product label.
Herbal Nutrition
See all Herbal Nutrition products- Name
- Herbal Nutrition
- Street Address
- 4100 Bellflower Dr
- City
- Alpharetta
- State
- GA
- ZipCode
- 30005
- Phone Number
- 800.497.4709
- Web Address
- HerbalNutritionHealth.com
Restore by Herbal Nutrition: Common Questions
Does Restore by Herbal Nutrition interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Can I take Restore while pregnant?
Is it safe to breastfeed while taking Restore?
What's red yeast rice, and why is it in this product?
Why does this product have black pepper in it?
What are the most common side effects of folic acid in Restore?
Does grape seed extract in this product actually work?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if Restore is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind Restore’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Folic Acid
Interacts with 40 drugsFolic acid is the man-made form of vitamin B9 and is one of the most well-studied supplements, especially for preventing serious birth defects when taken before and during early pregnancy. I...
Read the full Folic Acid monograph → Herb & supplement monographRed Yeast Rice
Interacts with 477 drugsRed yeast rice contains monacolin K, which is chemically identical to the prescription statin lovastatin, and it can lower LDL ('bad') cholesterol. Because of this, it carries the same risks...
Read the full Red Yeast Rice monograph → Herb & supplement monographGrape
Interacts with 910 drugsGrapes and grape products like grape seed extract contain antioxidant compounds such as resveratrol and proanthocyanidins that may support heart and blood vessel health. While the food is he...
Read the full Grape monograph → Herb & supplement monographBlack Pepper
Interacts with 1,019 drugsBlack pepper is a common kitchen spice that is generally safe in the amounts used in food. Its extract, piperine, is mostly added to supplements to help the body absorb other ingredients (li...
Read the full Black Pepper monograph → Herb & supplement monographNiacin
Interacts with 727 drugsNiacin (vitamin B3) is an essential nutrient your body needs for energy and metabolism, and deficiency is uncommon in most developed countries. Prescription-strength niacin has been used to...
Read the full Niacin monograph →Sources & How We Checked
Restore's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 235 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Folic Acid 56 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Duhra P. Treatment of gastrointestinal symptoms associated with methotrexate therapy for psoriasis. J Am Acad Dermatol 1993;28:466-9. PubMed
- Morgan SL, Baggott JE, Vaughn WH, et al. Supplementation with folic acid during methotrexate therapy for rheumatoid arthritis. A double-blind, placebo-controlled trial. Ann Intern Med 1994;121:833-41. PubMed
- Froscher W, Maier V, Laage M, et al. Folate deficiency, anticonvulsant drugs, and psychiatric morbidity. Clin Neuropharmacol 1995;18:165-82. PubMed
- Lewis DP, Van Dyke DC, Willhite LA, et al. Phenytoin-folic acid interaction. Ann Pharmacother 1995;29:726-35. PubMed
- Berg MJ, Stumbo PJ, Chenard CA, et al. Folic acid improves phenytoin pharmacokinetics. J Am Diet Assoc 1995;95:352-6. PubMed
- Berg MJ, Fincham RW, Ebert BE, et al. Phenytoin pharmacokinetics: Before and after folic acid administration. Epilepsia 1992;33:712-20. PubMed
- Shafer RB, Nuttall FQ. Calcium and folic acid absorption in patients taking anticonvulsant drugs. J Clin Endocrinol Metab 1975;41:1125-9. PubMed
- Leeb BF, Witzmann G, Ogris E, et al. Folic acid and cyanocobalamin levels in serum and erythrocytes during low-dose methotrexate therapy of rheumatoid arthritis and psoriatic arthritis patients. Clin Exp Rheumatol 1995;13:459-63.
- Morgan SL, Baggott JE, Lee JY, Alarcón GS. Folic acid supplementation prevents deficient blood folate levels and hyperhomocysteinemia during longterm, low dose methotrexate therapy for rheumatoid arthritis: implications for cardiovascular disease preventi
- Dijkmans BA. Folate supplementation and methotrexate. Br J Rheumatol 1995;34:1172-4. PubMed
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Lambie DG, Johnson RH. Drugs and folate metabolism. Drugs 1985;30:145-55. PubMed
- Amer College of Rheumatology ad hoc committee on clinical guidelines. Guidelines for monitoring drug therapy in rheumatoid arthritis. Arthritis Rheum 1996;39:723-31. DOI
- Suitor CW, Bailey LB. Dietary folate equivalents: interpretation and application. J Am Diet Assoc 2000;100:88-94. PubMed
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Sandoval M, Charbonnet RM, Okuhama NN, et al. Cat's claw inhibits TNFalpha production and scavenges free radicals: role in cytoprotection. Free Radic Biol Med 2000;29:71-78.
- Antony AC. Megaloblastic Anemias. In: Hoffman R, Benz Jr EJ, Shattil SJ, et al. Hematology: Basic Principles and Practice. 3rd ed. New York, NY: Churchill Livingstone 2000: 451-79.
- Reynolds EH. Neurological aspects of folate and vitamin B12 metabolism. Clin Haematol 1976;5:661-96. DOI
- Reynolds EH. Folate metabolism and anticonvulsant therapy. Proc R Soc Med 1974;67:68.
- Ortiz Z, Shea B, Suarez Almazor M, et al. Folic acid and folinic acid for reducing side effects in patients receiving methotrexate for rheumatoid arthritis (Cochrane Review). Cochrane Database Syst Rev 2000;2:CD000951. PubMed
- Van Delden C, Hirschel B. Folinic acid supplements to pyrimethamine-sulfadiazine for Toxoplasma encephalitis are associated with better outcome (letter). J Infect Dis 1996;173:1294-5. PubMed
- Schroder H, Clausen N, Ostergard E, Pressler T. Folic acid supplements in vitamin tablets: a determinant of hematological drug tolerance in maintenance therapy of childhood acute lymphoblastic leukemia. Ped Hematol Oncol 1986;3:241-7. PubMed
- Lange H, Suryapranata H, De Luca G, et al. Folate therapy and in-stent restenosis after coronary stenting. N Engl J Med 2004;350:2673-81. PubMed
- Morris MC, Evans DA, Bienias JL, et al. Dietary folate and vitamin B12 intake and cognitive decline among community-dwelling older persons. Arch Neurol 2005;62:641-5. PubMed
- Bonaa KH, Njolstad I, Ueland PM, et al. NORVIT: Homocysteine lowering and cardiovascular events after acute myocardial infarction. N Enlg J Med 2006;354:1578-88. PubMed
- Lawson KA, Wright ME, Subar A, et al. Multivitamin use and risk of prostate cancer in the National Institutes of Health-AARP Diet and Health Study. J Natl Cancer Inst 2007;99:754-64. PubMed
- Figueiredo JC, Grau MV, Haile RW, et al. Folic acid and risk of prostate cancer: Results from a randomized clinical trial. J Natl Cancer Inst 2009;101:432-5. PubMed
- Clippe C, Freyer G, Milano G, Trillet-Lenoir V. Lethal toxicity of capecitabine due to abusive folic acid prescription. Clin Oncol (R Coll Radiol) 2003;15:299-300. PubMed
- Bedford Laboratories. Leucovorin calcium [package insert]. Bedford, OH. September 2008. Available at: http://www.bedfordlabs.com/BedfordLabsWeb/products/inserts/LCV-P02.pdf.
- Ebbing M, Bonaa KH, Nygard O, et al. Cancer incidence and mortality after treatment with folic acid and vitamin B12. JAMA 2009;302:2119-26.
- Haberg, S. E., London, S. J., Stigum, H., Nafstad, P., and Nystad, W. Folic acid supplements in pregnancy and early childhood respiratory health. Arch Dis.Child 2009;94(3):180-184. PubMed
- Whitrow, M. J., Moore, V. M., Rumbold, A. R., and Davies, M. J. Effect of supplemental folic acid in pregnancy on childhood asthma: a prospective birth cohort study. Am J Epidemiol. 12-15-2009;170(12):1486-1493. PubMed
- Collin, S. M., Metcalfe, C., Refsum, H., Lewis, S. J., Zuccolo, L., Smith, G. D., Chen, L., Harris, R., Davis, M., Marsden, G., Johnston, C., Lane, J. A., Ebbing, M., Bonaa, K. H., Nygard, O., Ueland, P. M., Grau, M. V., Baron, J. A., Donovan, J. L., Nea
- Baggott, J. E., Oster, R. A., and Tamura, T. Meta-analysis of cancer risk in folic acid supplementation trials. Cancer Epidemiol. 2012;36(1):78-81. PubMed
- Fonseca VA, Lavery LA, Thethi TK, et al. Metanx in type 2 diabetes with peripheral neuropathy: A randomized trial. Am J Med 2013;126(2):141-9. PubMed
- Hankey GJ, Eikelboom JW, Yi Q, et al. Treatment with B vitamins and incidence of cancer in patients with previous stroke or transient ischemic attack: Results of a randomized placebo-controlled trial. Stroke 2012;43(6):1572-7. PubMed
- Taneja S, Strand TA, Kumar T, et al. Folic acid and vitamin B-12 supplementation and common infections in 6-30-mo-old children in India: a randomized placebo-controlled trial. Am J Clin Nutr 2013;98(3):731-7. PubMed
- van Wijngaarden JP, Swart KM, Enneman AW, et al. Effect of daily vitamin B-12 and folic acid supplementation on fracture incidence in elderly individuals with an elevated plasma homocysteine concentration: B-PROOF, a randomized controlled trial. Am J Clin
- Qin X, Fan F, Cui Y, Chen F, Chen Y, Cheng X, Li Y, Wang B, Xu X, Xu X, Huo Y, Wang X. Folic acid supplementation with and without vitamin B6 and revascularization risk: a meta-analysis of randomized controlled trials. Clin Nutr. 2014;33(4):603-12. PubMed
- Crider KS, Cordero AM, Qi YP, Mulinare J, Dowling NF, Berry RJ. Prenatal folic acid and risk of asthma in children: a systematic review and meta-analysis. Am J Clin Nutr. 2013;98(5):1272-81. PubMed
- Matsubara S, Imai K, Murayama K, Higashizawa T. Severe liver dysfunction during nausea and vomiting of pregnancy: folic acid supplement as a suggested culprit. J Obstet Gynaecol. 2012;32(7):701-2. PubMed
- Qin X, Cui Y, Shen L, Sun N, Zhang Y, Li J, Xu X, Wang B, Xu X, Huo Y, Wang X. Folic acid supplementation and cancer risk: a meta-analysis of randomized controlled trials. Int J Cancer. 2013 1;133(5):1033-41. PubMed
- Tio M, Andrici J, Cox MR, Eslick GD. Folate intake and the risk of prostate cancer: a systematic review and meta-analysis. Prostate Cancer Prostatic Dis. 2014;17(3):213-9. PubMed
- Tomaszewski JJ, Richman EL, Sadetsky N, O'Keefe DS, Carroll PR, Davies BJ, Chan JM. Impact of folate intake on prostate cancer recurrence following definitive therapy: data from CaPSURE. J Urol. 2014;191(4):971-6. PubMed
- Valera-Gran D, García de la Hera M, Navarrete-Muñoz EM, Fernandez-Somoano A, Tardón A, Julvez J, Forns J, Lertxundi N, Ibarluzea JM, Murcia M, Rebagliato M, Vioque J; Infancia y Medio Ambiente (INMA) Project. Folic acid supplements during pregnancy and ch
- Van Der Woude DA, De Vries J, Van Wijk EM, Verzijl JM, Pijnenborg JM. A randomized controlled trial examining the addition of folic acid to iron supplementation in the treatment of postpartum anemia. Int J Gynaecol Obstet. 2014;126(2):101-5. PubMed
- Vila-Nova C, Wehby GL, Queirós FC, Chakraborty H, Félix TM, Goco N, Moore J, Gewehr EV, Lins L, Affonso CM, Murray JC. Periconceptional use of folic acid and risk of miscarriage - findings of the Oral Cleft Prevention Program in Brazil. J Perinat Med. 201 PubMed
- Vollset SE, Clarke R, Lewington S, Ebbing M, Halsey J, Lonn E, Armitage J, Manson JE, Hankey GJ, Spence JD, Galan P, Bønaa KH, Jamison R, Gaziano JM, Guarino P, Baron JA, Logan RF, Giovannucci EL, den Heijer M, Ueland PM, Bennett D, Collins R, Peto R; B-V
- Wehby GL, Félix TM, Goco N, Richieri-Costa A, Chakraborty H, Souza J, Pereira R, Padovani C, Moretti-Ferreira D, Murray JC. High dosage folic acid supplementation, oral cleft recurrence and fetal growth. Int J Environ Res Public Health. 2013 4;10(2):590-6 PubMed
- Fanidi A, Carreras-Torres R, Larose TL, et al. Is high vitamin B12 status a cause of lung cancer? Int J Cancer. 2019 Sep 15;145(6):1499-1503. PubMed
- Liu J, Li Z, Ye R, Liu J, Ren A. Periconceptional folic acid supplementation and risk of parent-reported asthma in children at 4-6 years of age. ERJ Open Res. 2020;6(1):00250-2019. PubMed
- Houghton LA, Sherwood KL, Pawlosky R, Ito S, O'Connor DL. [6S]-5-Methyltetrahydrofolate is at least as effective as folic acid in preventing a decline in blood folate concentrations during lactation. Am J Clin Nutr. 2006 Apr;83(4):842-50. PubMed
- Houghton LA, Yang J, O'Connor DL. Unmetabolized folic acid and total folate concentrations in breast milk are unaffected by low-dose folate supplements. Am J Clin Nutr. 2009 Jan;89(1):216-20. PubMed
- Chan SL, Chan AWH, Mo F, et al. Association Between Serum Folate Level and Toxicity of Capecitabine During Treatment for Colorectal Cancer. Oncologist. 2018 Dec;23(12):1436-1445. PubMed
- Sarris J, Ravindran A, Yatham LN, et al. Clinician guidelines for the treatment of psychiatric disorders with nutraceuticals and phytoceuticals: The World Federation of Societies of Biological Psychiatry (WFSBP) and Canadian Network for Mood and Anxiety T
Red Yeast Rice 50 references
- Hebel SK, ed. Drug Facts and Comparisons. 52nd ed. St. Louis: Facts and Comparisons, 1998.
- Heber D, Yip I, Ashley JM, et al. Cholesterol-lowering effects of a proprietary Chinese red-yeast-rice dietary supplement. Am J Clin Nutr 1999;69:231-6. PubMed
- Wang J, Lu A, Chi J. Multicenter clinical trial of the serum lipid-lowering effects of a monascus purpureus (red yeast) rice preparation from traditional Chinese medicine. Cur Ther Res 1997;58:964-78. DOI
- Wigger-Alberti W, Bauer A, Hipler UC, Elsner P. Anaphylaxis due to Monascus purpureus-fermented rice (red yeast rice). Allergy 1999;54:1330-1.
- Prasad GV, Wong T, Meliton G, Bhaloo S. Rhabdomyolysis due to red yeast rice (Monascus purpureus) in a renal transplant recipient. Transplantation 2002;74:1200-1. PubMed
- Heber D, Lembertas A, Lu QY, et al. An analysis of nine proprietary Chinese red yeast rice dietary supplements: implications of variability in chemical profile and contents. J Altern Complement Med 2001;7:133-9. PubMed
- Mueller PS. Symptomatic myopathy due to red yeast rice. Ann Intern Med 2006;145:474-5. PubMed
- Roselle H, Ekatan A, Tzeng J, et al. Symptomatic hepatitis associated with the use of herbal red yeast rice. Ann Intern Med 2008;149:516-7. PubMed
- Lapi F, Gallo E, Bernasconi S, et al. Myopathies associated with red yeast rice and liquorice: spontaneous reports from the Italian Surveillance System of Natural Health Products. Br J Clin Pharmacol 2008;66:572-74. PubMed
- Becker DJ, Gordon RY, Halbert SC, et al. Red yeast rice for dyslipidemia in statin-intolerant patients: A randomized trial. Ann Intern Med 2009;150:830-9. PubMed
- Halbert SC, French B, Gordon RY, et al. Tolerability of red yeast rice (2,400 mg twice daily) versus pravastatin (20 mg twice daily) in patients with previous statin intolerance. Am J Cardiol 2010;105:198-204. PubMed
- Gordon RY, Cooperman T, Obermeyer W, Becker DJ. Marked variability of monacolin levels in commercial red yeast rice products: buyer beware! Arch Intern Med 2010;170:1722-7. PubMed
- Karl M, Rubenstein M, Rudnick C, Brejda J. A multicenter study of nutraceutical drinks for cholesterol (evaluating effectiveness and tolerability). J Clin Lipidology 2012;6:150-158. PubMed
- Huang, J., Frohlich, J., and Ignaszewski, A. P. The impact of dietary changes and dietary supplements on lipid profile. Can J Cardiol 2011;27(4):488-505. PubMed
- Grieco, A., Miele, L., Pompili, M., Biolato, M., Vecchio, F. M., Grattagliano, I., and Gasbarrini, G. Acute hepatitis caused by a natural lipid-lowering product: when "alternative" medicine is no "alternative" at all. J Hepatol 2009;50(6):1273-1277. PubMed
- Smith, D. J. and Olive, K. E. Chinese red rice-induced myopathy. South.Med J 2003;96(12):1265-1267. PubMed
- Liu, B. H., Wu, T. S., Su, M. C., Chung, C. P., and Yu, F. Y. Evaluation of citrinin occurrence and cytotoxicity in Monascus fermentation products. J Agric.Food Chem. 1-12-2005;53(1):170-175.
- Lin, C. C., Li, T. C., and Lai, M. M. Efficacy and safety of Monascus purpureus Went rice in subjects with hyperlipidemia. Eur J Endocrinol 2005;153(5):679-686. PubMed
- Zhao, S. P., Lu, Z. L., Du, B. M., Chen, Z., Wu, Y. F., Yu, X. H., Zhao, Y. C., Liu, L., Ye, H. J., and Wu, Z. H. Xuezhikang, an extract of cholestin, reduces cardiovascular events in type 2 diabetes patients with coronary heart disease: subgroup analysis
- Lu, Z., Kou, W., Du, B., Wu, Y., Zhao, S., Brusco, O. A., Morgan, J. M., Capuzzi, D. M., and Li, S. Effect of Xuezhikang, an extract from red yeast Chinese rice, on coronary events in a Chinese population with previous myocardial infarction. Am J Cardiol PubMed
- Li, J. J., Lu, Z. L., Kou, W. R., Chen, Z., Wu, Y. F., Yu, X. H., and Zhao, Y. C. Beneficial impact of Xuezhikang on cardiovascular events and mortality in elderly hypertensive patients with previous myocardial infarction from the China Coronary Secondary
- Li, J. J., Lu, Z. L., Kou, W. R., Chen, Z., Wu, Y. F., Yu, X. H., and Zhao, Y. C. Impact of Xuezhikang on coronary events in hypertensive patients with previous myocardial infarction from the China Coronary Secondary Prevention Study (CCSPS). Ann Med 2010 PubMed
- Li, J. J., Lu, Z. L., Kou, W. R., Chen, Z., Wu, Y. F., Yu, X. H., and Zhao, Y. C. Long-term effects of Xuezhikang on blood pressure in hypertensive patients with previous myocardial infarction: data from the Chinese Coronary Secondary Prevention Study (CC
- Liu, Z. L., Liu, J. P., Zhang, A. L., Wu, Q., Ruan, Y., Lewith, G., and Visconte, D. Chinese herbal medicines for hypercholesterolemia. Cochrane Database Syst Rev 2011;(7):CD008305. PubMed
- Chagas, G. M., Kluppel, M. L., Campello, Ade P., Buchi, Dde F., and de Oliveira, M. B. Alterations induced by citrinin in cultured kidney cells. Cell Struct.Funct. 1994;19(2):103-108. PubMed
- Krejci, M. E., Bretz, N. S., and Koechel, D. A. Citrinin produces acute adverse changes in renal function and ultrastructure in pentobarbital-anesthetized dogs without concomitant reductions in [potassium] plasma. Toxicology 1-8-1996;106(1-3):167-177. PubMed
- Blanc PJ, Laussac JP, Le Bars J, et al. Characterization of monascidin A from Monascus as citrinin. Int J Food Microbiol. 1995;27(2-3):201-213. PubMed
- Lu, Z. L., Xu, S., and Kou, W. R. The clinical observation of treatment of hyperlipidemia with different dose of Xuezhikang. National Symposium of Clinical Therapies for Cardiovascular Diseases 1995;1997:53-57.
- Bonovich, K., Colfer, H., Petoskey, M. I., and et al. A multi-center, self-controlled study of cholestin in subjects with elevated cholesterol. Journal of Investigative Medicine 1999;47(2):54A.
- Pisciotta, L., Boscarini, M., and Corio, R. Studi clinici su Normolip5, integratore alimentare per il controllo del colesterolo. Medicina Naturale 2004;68-70.
- Barrat E, Zaïr Y, Sirvent P, et al. Effect on LDL-cholesterol of a large dose of a dietary supplement with plant extracts in subjects with untreated moderate hypercholesterolaemia: a randomised, double-blind, placebo-controlled study. Eur J Nutr. 2013;52( PubMed
- Kumari S, Sherriff JM, Spooner D, Beckett R. Peripheral neuropathy induced by red yeast rice in a patient with a known small bowel gastrointestinal tumour. BMJ Case Rep. 2013;2013. PubMed
- Mazzanti G, Moro PA, Raschi E, Da Cas R, Menniti-Ippolito F. Adverse reactions to dietary supplements containing red yeast rice: assessment of cases from the Italian surveillance system. Br J Clin Pharmacol 2017;83(4):894-908. PubMed
- Gerards MC, Terlou RJ, Yu H, Koks CH, Gerdes VE. Traditional Chinese lipid-lowering agent red yeast rice results in significant LDL reduction but safety is uncertain - a systematic review and meta-analysis. Atherosclerosis. 2015;240(2):415-23. doi: 10.101 PubMed
- Venhuis BJ, van Hunsel F, van de Koppel S, Keizers PH, Jeurissen SM, De Kaste D. Pharmacologically effective red yeast rice preparations marketed as dietary supplements illustrated by a case report. Drug Test Anal. 2016;8(3-4):315-8. doi: 10.1002/dta.1929 PubMed
- Raschi E, Girardi A, Poluzzi E, et al. Adverse events to food supplements containing red yeast rice: comparative analysis of FAERS and CAERS reporting systems. Drug Saf 2018;41(8):745-52. doi: 10.1007/s40264-018-0661-3. PubMed
- Mercurio V, Pucci G, Bosso G, et al. A nutraceutical combination reduces left ventricular mass in subjects with metabolic syndrome and left ventricular hypertrophy: A multicenter, randomized, double-blind, placebo-controlled trial. Clin Nutr. 2020;39(5):1 PubMed
- Prescribing Information. Mevacor (lovastatin). Whitehouse Station, NJ: Merck & Co., Inc., February 2012.
- Cicero AFG, Kennedy C, Knezevic T, et al. Efficacy and Safety of Armolipid Plus(®): An Updated PRISMA Compliant Systematic Review and Meta-Analysis of Randomized Controlled Clinical Trials. Nutrients 2021;13(2):638. PubMed
- Cicero AFG, Bove M, Cincione RI, Fogacci F, Veronesi M. Effect of combined lipid-lowering and antioxidant nutraceutical on plasma lipids, endothelial function, and estimated cardiovascular disease risk in moderately hypercholesterolemic patients: a double
- 7-20-21 FDA Drug Safety Communication. FDA requests removal of strongest warning against using cholesterol-lowering statins during pregnancy; still advises most pregnant patients should stop taking statins. Available at: https://www.fda.gov/drugs/drug-s
- García-García MD, Bellido Muñoz F, Cordero Ruiz P, Caunedo Álvarez Á. Drug-induced liver injury associated to red yeast rice. Rev Esp Enferm Dig 2023. PubMed
- Santos S, Gomes S, Carvalho I, Bonito I, Carmo C. Rhabdomyolysis Related to Red Yeast Rice Ingestion. Cureus 2023;15(1):e33532. PubMed
- Banach M, Norata GD. Rhabdomyolysis or severe acute hepatitis associated with the use of red yeast rice extracts: an update from the adverse event reporting systems. Curr Atheroscler Rep 2023;25(11):879-888. PubMed
- Wang YH, Zhang SS, Li HT, Zhi HW, Wu HY. Rhabdomyolysis-induced acute kidney injury after administration of a red yeast rice supplement: A case report. World J Clin Cases 2023;11(23):5547-5553. PubMed
- Norata GD, Banach M. The Impact of Red Yeast Rice Extract Use on the Occurrence of Muscle Symptoms and Liver Dysfunction: An Update from the Adverse Event Reporting Systems and Available Meta-Analyses. Nutrients 2024;16(3):444. PubMed
- Trogkanis E, Karalexi MA, Sergentanis TN, Kornarou E, Vassilakou T. Safety and Efficacy of the Consumption of the Nutraceutical "Red Yeast Rice Extract" for the Reduction of Hypercholesterolemia in Humans: A Systematic Review and Meta-Analysis. Nutrients PubMed
- Maiguma M, Kihara M, Hamaguchi M, et al. Successful treatment of acute tubulointerstitial nephritis probably due to Benikoji CholesteHelp(®), a supplement containing red yeast rice. CEN Case Rep 2024. PubMed
- Oda K, Murata T, Tanaka F, et al. A case of acute kidney injury and Fanconi syndrome while taking multiple supplements, including Red Yeast Rice Cholesterol Help(®). CEN Case Rep 2024. PubMed
- Miyazaki R, Takahashi Y, Kawamura T, Ueda H, Tsuboi N, Yokoo T. Acute kidney tubular injury after ingestion of red yeast rice supplement. Clin Kidney J 2024;17(6):sfae151. PubMed
Niacin 66 references
- Garg R, Malinow MR, Pettinger M, et al. Niacin treatment increases plasma homocysteine levels. Am Heart J 1999;138:1082-7.
- Anon. Inositol hexaniacinate. Altern Med Rev 1998;3:222-3.
- Knodel LC, Talbert RL. Adverse effects of hypolipidaemic drugs. Med Toxicol 1987;2:10-32. PubMed
- Guyton JR, Blazing MA, Hagar J, et al. Extended-release niacin vs gemfibrozil for the treatment of low levels of high-density lipoprotein cholesterol. Niaspan-Gemfibrozil Study Group. Arch Intern Med 2000;160:1177-84. PubMed
- Gibbons LW, Gonzalez V, Gordon N, Grundy S. The prevalence of side effects with regular and sustained-release nicotinic acid. Am J Med 1995;99:378-85. PubMed
- Whelan AM, Price SO, Fowler SF, Hainer BL. The effect of aspirin on niacin-induced cutaneous reactions. J Fam Pract 1992;34:165-8.
- Jungnickel PW, Maloley PA, Vander Tuin EL, et al. Effect of two aspirin pretreatment regimens on niacin-induced cutaneous reactions. J Gen Intern Med 1997;12:591-6. PubMed
- Capuzzi DM, Guyton JR, Morgan JM, et al. Efficacy and safety of an extended-release niacin (Niaspan): a long-term study. Am J Cardiol 1998;82:74-81;disc. 85U-6U. PubMed
- Gray DR, Morgan T, Chretien SD, Kashyap ML. Efficacy and safety of controlled-release niacin in dyslipoproteinemic veterans. Ann Intern Med 1994;121:252-8. PubMed
- McKenney JM, Proctor JD, Harris S, Chinchili VM. A comparison of the efficacy and toxic effects of sustained- vs immediate-release niacin in hypercholesterolemic patients. JAMA 1994;271:672-7. DOI
- Knopp RH, Alagona P, Davidson M, et al. Equivalent efficacy of a time-release form of niacin (Niaspan) given once-a-night versus plain niacin in the management of hyperlipidemia. Metabolism 1998;47:1097-104. PubMed
- Knopp RH. Clinical profiles of plain versus sustained-release niacin (Niaspan) and the physiologic rationale for nighttime dosing. Am J Cardiol 1998;82:24U-28U;discussion 39U-41U. PubMed
- Garg A, Grundy SM. Nicotinic acid as therapy for dyslipidemia in non-insulin-dependent diabetes mellitus. JAMA 1990;264:723-6. DOI
- Leighton RF, Gordon NF, Small GS, et al. Dental and gingival pain as side effects of niacin therapy. Chest 1998;114:1472-4. PubMed
- American Society of Health-System Pharmacists. ASHP Therapeutic Position Statement on the safe use of niacin in the management of dyslipidemias. Am J Health Syst Pharm 1997;54:2815-9. DOI
- Vega GL, Grundy SM. Lipoprotein responses to treatment with lovastatin, gemfibrozil, and nicotinic acid in normolipidemic patients with hypoalphalipoproteinemia. Arch Intern Med 1994;154:73-82. DOI
- Guyton JR, Goldberg AC, Kreisberg RA, et al. Effectiveness of once-nightly dosing of extended-release niacin alone and in combination for hypercholesterolemia. Am J Cardiol 1998;82:737-43.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Thiamin, Riboflavin, Niacin, Vitamin B6, Folate, Vitamin B12, Pantothenic Acid, Biotin, and Choline (2000). Washington, DC: National Academy Press, 2000. Available at: http://b
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Bays HE, Dujovne CA. Drug interactions of lipid-altering drugs. Drug Saf 1998;19:355-71. PubMed
- Rader JI, Calvert RJ, Hathcock JN. Hepatic toxicity of unmodified and time-release preparations of niacin. Am J Med 1992;92:77-81. PubMed
- Kahn SE, Beard JC, Schwartz MW, et al. Increased B-cell secretory capacity as mechanism for islet adaptation to nicotinic acid-induced insulin resistance. Diabetes 1989;38:562-8.
- Schwartz ML. Severe reversible hyperglycemia as a consequence of niacin therapy. Arch Int Med 1993;153:2050-2. DOI
- Raising HDL and Niacin Use. Pharmacist's Letter/Prescriber's Letter 2004;20(5):200504.
- McKenney J. New perspectives on the use of niacin in the treatment of lipid disorders. Arch Intern Med 2004;164:697-705. PubMed
- Reaven P, Witztum JL. Lovastatin, nicotinic acid and rhabdomyolysis (letter). Ann Int Med 1988;109:597-8. PubMed
- Ito MK. Advances in the understanding and management of dyslipidemia: using niacin-based therapies. Am J Health-Syst Pharm 2003;60(suppl 2):s15-21. PubMed
- Schwab RA, Bachhuber BH. Delirium and lactic acidosis caused by ethanol and niacin coingestion. Am J Emerg Med 1991;9:363-5. PubMed
- Product information: Niaspan. Kos Pharmaceuticals. Cranbury, NJ. 2005. Available at www.niaspan.com/professional/content/pdfs/productinfo.pdf. (Accessed 3 March 2006).
- Ding RW, Kolbe K, Merz B, et al. Pharmacokinetics of nicotinic acid-salicylic acid interaction. Clin Pharmacol Ther 1989;46:642-7. PubMed
- NIH News. NIH stops clinical trial on combination cholesterol treatment. May 26, 2011. http://www.nih.gov/news/health/may2011/nhlbi-26.htm. (Accessed 3 June 2011).
- Dearing BD, Lavie CJ, Lohmann TP, Genton E. Niacin-induced clotting factor synthesis deficiency with coagulopathy. Arch Intern Med. 1992;152(4):861-3. DOI
- O'Brien T, Silverberg JD, Nguyen TT. Nicotinic acid-induced toxicity associated with cytopenia and decreased levels of thyroxine-binding globulin. Mayo Clin Proc. 1992;67(5):465-8. PubMed
- Gadegbeku CA, Dhandayuthapani A, Shrayyef MZ, Egan BM. Hemodynamic effects of nicotinic acid infusion in normotensive and hypertensive subjects. Am J Hypertens. 2003;16(1):67-71. PubMed
- Garnett WR. Interactions with hydroxymethylglutaryl-coenzyme A reductase inhibitors. Am J Health Syst Pharm. 1995;52(15):1639-45. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Dunn RT, Ford MA, Rindone JP, Kwiecinski FA. Low-Dose Aspirin and Ibuprofen Reduce the Cutaneous Reactions Following Niacin Administration. Am J Ther. 1995;2(7):478-480. PubMed
- Cashin-Hemphill L, Spencer CA, Nicoloff JT, et al. Alterations in serum thyroid hormonal indices with colestipol-niacin therapy. Ann Intern Med. 1987;107(3):324-9. PubMed
- Drinka PJ. Alterations in thyroid and hepatic function tests associated with preparations of sustained-release niacin. Mayo Clin Proc. 1992;67(12):1206. PubMed
- Shakir KM, Kroll S, Aprill BS, Drake AJ 3rd, Eisold JF. Nicotinic acid decreases serum thyroid hormone levels while maintaining a euthyroid state. Mayo Clin Proc. 1995;70(6):556-8. PubMed
- Etchason JA, Miller TD, Squires RW, et al. Niacin-induced hepatitis: a potential side effect with low-dose time-release niacin. Mayo Clin Proc. 1991;66(1):23-8. PubMed
- Henkin Y, Johnson KC, Segrest JP. Rechallenge with crystalline niacin after drug-induced hepatitis from sustained-release niacin. JAMA. 1990;264(2):241-3. DOI
- Henkin Y, Oberman A, Hurst DC, Segrest JP. Niacin revisited: clinical observations on an important but underutilized drug. Am J Med. 1991;91(3):239-46. PubMed
- Brown BG, Bardsley J, Poulin D, et al. Moderate dose, three-drug therapy with niacin, lovastatin, and colestipol to reduce low-density lipoprotein cholesterol <100 mg/dl in patients with hyperlipidemia and coronary artery disease. Am J Cardiol. 1997;80(2)
- Goldberg A, Alagona P Jr, Capuzzi DM, et al. Multiple-dose efficacy and safety of an extended-release form of niacin in the management of hyperlipidemia. Am J Cardiol. 2000;85(9):1100-5. PubMed
- Aronov DM, Keenan JM, Akhmedzhanov NM, et al. Clinical trial of wax-matrix sustained-release niacin in a Russian population with hypercholesterolemia. Arch Fam Med. 1996;5(10):567-75. PubMed
- Morgan JM, Capuzzi DM, Guyton JR, et al. Treatment Effect of Niaspan, a Controlled-release Niacin, in Patients With Hypercholesterolemia: A Placebo-controlled Trial. J Cardiovasc Pharmacol Ther. 1996;1(3):195-202. PubMed
- Andersson RG, Aberg G, Brattsand R, Ericsson E, Lundholm L. Studies on the mechanism of flush induced by nicotinic acid. Acta Pharmacol Toxicol (Copenh). 1977 Jul;41(1):1-10. PubMed
- Brown WV. Niacin for lipid disorders. Indications, effectiveness, and safety. Postgrad Med. 1995 Aug;98(2):185-9, 192-3. PubMed
- O'REILLY PO, CALLBECK MJ, HOFFER A. Sustained-release nicotinic acid (nicospan); effect on (1) cholesterol levels and (2) leukocytes. Can Med Assoc J. 1959;80(5):359-62.
- Gharavi AG, Diamond JA, Smith DA, Phillips RA. Niacin-induced myopathy. Am J Cardiol. 1994;74(8):841-2. PubMed
- Litin SC, Anderson CF. Nicotinic acid-associated myopathy: a report of three cases. Am J Med. 1989;86(4):481-3. PubMed
- Fraunfelder FW, Fraunfelder FT, Illingworth DR. Adverse ocular effects associated with niacin therapy. Br J Ophthalmol 1995;79:54-56. PubMed
- Ali EH, McJunkin B, Jubelirer S, Hood W. Niacin induced coagulopathy as a manifestation of occult liver injury. W V Med J. 2013 Jan-Feb;109(1):12-4
- Aramwit P, Srisawadwong R, Supasyndh O. Effectiveness and safety of extended-release nicotinic acid for reducing serum phosphorus in hemodialysis patients. J Nephrol. 2012 May-Jun;25(3):354-62. PubMed
- Bassan M. A case for immediate-release niacin. Heart Lung. 2012 Jan-Feb;41(1):95-8. PubMed
- Davidson MH, Rooney M, Pollock E, Drucker J, Choy Y. Effect of colesevelam and niacin on low-density lipoprotein cholesterol and glycemic control in subjects with dyslipidemia and impaired fasting glucose. J Clin Lipidol. 2013 Sep-Oct;7(5):423-32. PubMed
- Guyton JR, Fazio S, Adewale AJ, Jensen E, Tomassini JE, Shah A, Tershakovec AM. Effect of extended-release niacin on new-onset diabetes among hyperlipidemic patients treated with ezetimibe/simvastatin in a randomized controlled trial. Diabetes Care. 2012 PubMed
- Loebl T, Raskin S. A novel case report: acute manic psychotic episode after treatment with niacin. J Neuropsychiatry Clin Neurosci. 2013 Fall;25(4):E14. PubMed
- Teo KK, Goldstein LB, Chaitman BR, Grant S, Weintraub WS, Anderson DC, Sila CA, Cruz-Flores S, Padley RJ, Kostuk WJ, Boden WE; AIM-HIGH Investigators. Extended-release niacin therapy and risk of ischemic stroke in patients with cardiovascular disease: the
- Goldie C, Taylor AJ, Nguyen P, McCoy C, Zhao XQ, Preiss D. Niacin therapy and the risk of new-onset diabetes: a meta-analysis of randomized controlled trials. Heart. 2016 Feb;102(3):198-203.
- Schandelmaier S, Briel M, Saccilotto R, Olu KK, Arpagaus A, Hemkens LG, Nordmann AJ. Niacin for primary and secondary prevention of cardiovascular events. Cochrane Database Syst Rev. 2017 Jun 14;6:CD009744. PubMed
- Jenkins DJA, Spence JD, Giovannucci EL, et al. Supplemental vitamins and minerals for CVD prevention and treatment. J Am Coll Cardiol 2018;71(22):2570-84. PubMed
- Song S, Lee CJ, Oh J, Park S, Kang SM, Lee SH. Effect of Niacin on Carotid Atherosclerosis in Patients at Low-Density Lipoprotein-Cholesterol Goal but High Lipoprotein (a) Level: a 2-Year Follow-Up Study. J Lipid Atheroscler. 2019;8(1):58-66. PubMed
- Kimura H, Umemori Y, Yuki D. Anaphylactic shock-like symptoms due to niacin overdose: A case report. J Dermatol 2022;49(8):e287-e288. PubMed
- Nawaz N, Mistretta T, Karime C, Lewis J, Wolf E. Cholestatic Drug-Induced Liver Injury in a Patient Taking High-Dose Niacin for Hyperlipidemia. J Investig Med High Impact Case Rep 2024;12:23247096231224349. PubMed
Grape 34 references
- Kiesewetter H, Koscielny J, Kalus U, et al. Efficacy of orally administered extract of red vine leaf AS 195 (folia vitis viniferae) in chronic venous insufficiency (stages I-II). A randomized, double-blind, placebo-controlled trial. Arzneimittelforschung
- Xiao Dong S, Zhi Ping Z, Zhong Xiao W, et al. Possible enhancement of the first-pass metabolism of phenacetin by ingestion of grape juice in Chinese subjects. Br J Clin Pharmacol 1999;48:638-40. PubMed
- Vaswani SK, Hamilton RG, Carey RN, et al. Anaphylaxis recurrent urticaria and angioedema from grape hypersensitivity. J Allergy Clin Immunol 1998;101:S31.
- Chevallier A. The Encyclopedia of Medicinal Plants. London, UK: Dorling Kindersley, Ltd., 1996.
- Bernstein DI, Bernstein CK, Deng C, et al. Evaluation of the clinical efficacy and safety of grapeseed extract in the treatment of fall seasonal allergic rhinitis: a pilot study. Ann Allergy Asthma Immunol 2002;88:272-8.. PubMed
- Greenblatt DJ, von Moltke LL, Perloff ES, et al. Interaction of flurbiprofen with cranberry juice, grape juice, tea, and fluconazole: in vitro and clinical studies. Clin Pharmacol Ther 2006;79:125-33. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Ray, S. D., Parikh, H., Hickey, E., Bagchi, M., and Bagchi, D. Differential effects of IH636 grape seed proanthocyanidin extract and a DNA repair modulator 4-aminobenzamide on liver microsomal cytochrome 4502E1-dependent aniline hydroxylation. Mol Cell B PubMed
- O'Byrne, D. J., Devaraj, S., Grundy, S. M., and Jialal, I. Comparison of the antioxidant effects of Concord grape juice flavonoids alpha-tocopherol on markers of oxidative stress in healthy adults. Am J Clin.Nutr. 2002;76(6):1367-1374.
- Schaefer, E., Peil, H., Ambrosetti, L., and Petrini, O. Oedema protective properties of the red vine leaf extract AS 195 (Folia vitis viniferae) in the treatment of chronic venous insufficiency. A 6-week observational clinical trial. Arzneimittelforschun PubMed
- Nishikawa, M., Ariyoshi, N., Kotani, A., Ishii, I., Nakamura, H., Nakasa, H., Ida, M., Nakamura, H., Kimura, N., Kimura, M., Hasegawa, A., Kusu, F., Ohmori, S., Nakazawa, K., and Kitada, M. Effects of continuous ingestion of green tea or grape seed extra
- de Lange, D. W., Scholman, W. L., Kraaijenhagen, R. J., Akkerman, J. W., and van de Wiel, A. Alcohol and polyphenolic grape extract inhibit platelet adhesion in flowing blood. Eur.J Clin.Invest 2004;34(12):818-824. PubMed
- Samet, J. M. and Coultas, D. B. Reduced forced vital capacity in California grape workers. What does it mean? Am Rev.Respir.Dis 1992;145(2 Pt 1):255-256. PubMed
- Gamsky, T. E., McCurdy, S. A., Samuels, S. J., and Schenker, M. B. Reduced FVC among California grape workers. Am Rev.Respir.Dis 1992;145(2 Pt 1):257-262. PubMed
- de Lange, D. W., Verhoef, S., Gorter, G., Kraaijenhagen, R. J., van de Wiel, A., and Akkerman, J. W. Polyphenolic grape extract inhibits platelet activation through PECAM-1: an explanation for the French paradox. Alcohol Clin.Exp.Res 2007;31(8):1308-1314 PubMed
- Etheridge, A. S., Black, S. R., Patel, P. R., So, J., and Mathews, J. M. An in vitro evaluation of cytochrome P450 inhibition and P-glycoprotein interaction with goldenseal, Ginkgo biloba, grape seed, milk thistle, and ginseng extracts and their constitu
- Krikorian, R., Nash, T. A., Shidler, M. D., Shukitt-Hale, B., and Joseph, J. A. Concord grape juice supplementation improves memory function in older adults with mild cognitive impairment. Br J Nutr. 2010;103(5):730-734. PubMed
- Ingersoll, G. L., Wasilewski, A., Haller, M., Pandya, K., Bennett, J., He, H., Hoffmire, C., and Berry, C. Effect of concord grape juice on chemotherapy-induced nausea and vomiting: results of a pilot study. Oncol.Nurs.Forum 2010;37(2):213-221. PubMed
- Oliveira-Freitas, V. L., Dalla, Costa T., Manfro, R. C., Cruz, L. B., and Schwartsmann, G. Influence of purple grape juice in cyclosporine bioavailability. J Ren Nutr. 2010;20(5):309-313. PubMed
- Hollis, J. H., Houchins, J. A., Blumberg, J. B., and Mattes, R. D. Effects of concord grape juice on appetite, diet, body weight, lipid profile, and antioxidant status of adults. J Am Coll.Nutr. 2009;28(5):574-582. PubMed
- Dohadwala, M. M., Hamburg, N. M., Holbrook, M., Kim, B. H., Duess, M. A., Levit, A., Titas, M., Chung, W. B., Vincent, F. B., Caiano, T. L., Frame, A. A., Keaney, J. F., Jr., and Vita, J. A. Effects of Concord grape juice on ambulatory blood pressure in
- Rabe, E., Stucker, M., Esperester, A., Schafer, E., and Ottillinger, B. Efficacy and tolerability of a red-vine-leaf extract in patients suffering from chronic venous insufficiency--results of a double-blind placebo-controlled study. Eur.J Vasc.Endovasc. PubMed
- Trotta, M., Cesaretti, M., Conzi, R., Derchi, L. E., and Borgonovo, G. Elderly male with mesogastric pain. Small bowel obstruction caused by an intact fresh grape. Ann.Emerg.Med 2011;58(4):e1-e2. PubMed
- McCurdy, S. A., Wiggins, P., Schenker, M. B., Munn, S., Shaieb, A. M., Weinbaum, Z., Goldsmith, D., McGillis, S. T., Berman, B., and Samuels, S. Assessing dermatitis in epidemiologic studies: occupational skin disease among California grape and tomato ha
- Winter, C. K. and Kurtz, P. H. Factors influencing grape worker susceptibility to skin rashes. Bull.Environ.Contam Toxicol. 1985;35(3):418-426. PubMed
- Yamasaki, R., Dekio, S., and Jidoi, J. Contact dermatitis from grape bud. Contact Dermatitis 1985;12(4):226-227. PubMed
- Cox, J. and Grigg, M. Small bowel obstruction by an intact grape. J Am Geriatr.Soc 1986;34(7):550. PubMed
- Faircloth, D. E. and Robison, W. J. Obstruction of the sigmoid colon by grape seeds. JAMA 11-27-1981;246(21):2430. PubMed
- Marguerie, C. and Drouet, M. [Occupational eosinophilic lung in a grape grower: role of sulfites]. Allerg.Immunol.(Paris) 1995;27(5):163-167.
- Brito, FF., Martinez, A., Palacios, R., Mur, P., Gomez, E., Galindo, P. A., Borja, J., and Martinez, J. Rhinoconjunctivitis and asthma caused by vine pollen: a case report. J Allergy Clin Immunol 1999;103(2 Pt 1):262-266. PubMed
- Ras RT, Zock PL, Zebregs YE, et al. Effect of polyphenol-rich grape seed extract on ambulatory blood pressure in subjects with pre- and stage I hypertension. Br J Nutr 2013;110(12):2234-41. PubMed
- Berry AC, Nakshabendi R, Abidali H, et al. Adverse effects of grape seed extract supplement: A clinical case and long-term follow-up. J Diet Suppl. 2016;13(2):232-5. PubMed
- Martínez-Maqueda D, Zapatera B, Gallego-Narbón A, Vaquero MP, Saura-Calixto F, Pérez-Jiménez J. A 6-week supplementation with grape pomace to subjects at cardiometabolic risk ameliorates insulin sensitivity, without affecting other metabolic syndrome mark
- Moon SW, Shin YU, Cho H, Bae SH, Kim HK; and for the Mogen Study Group. Effect of grape seed proanthocyanidin extract on hard exudates in patients with non-proliferative diabetic retinopathy. Medicine (Baltimore) 2019;98(21):e15515. PubMed
Black Pepper 29 references
- Leung AY, Foster S. Encyclopedia of Common Natural Ingredients Used in Food, Drugs and Cosmetics. 2nd ed. New York, NY: John Wiley & Sons, 1996.
- Brinker F. Herb Contraindications and Drug Interactions. 2nd ed. Sandy, OR: Eclectic Medical Publications, 1998.
- Bano G, Amla V, Raina RK, et al. The effect of piperine on pharmacokinetics of phenytoin in healthy volunteers. Planta Med 1987;53:568-9. PubMed
- Bano G, et al. Effect of piperine on bioavailability and pharmacokinetics of propranolol and theophylline in healthy volunteers. Eur J Clin Pharmacol 1991;41;615-7. PubMed
- Cohle SD, Trestrail JD III, Graham MA, et al. Fatal pepper aspiration. Am J Dis Child 1988;142:633-6. PubMed
- Bhardwaj RK, Glaeser H, Becquemont L, et al. Piperine, a major constituent of black pepper, inhibits human P-glycoprotein and CYP3A4. J Pharmacol Exp Ther 2002;302:645-50. PubMed
- Velpandian T, Jasuja R, Bhardwaj RK, et al. Piperine in food: interference in the pharmacokinetics of phenytoin. Eur J Drug Metab Pharmacokinet 2001;26:241-7. PubMed
- Pattanaik S, Hota D, Prabhakar S, et al. Pharmacokinetic interaction of a single dose of piperine with steady-state carbamazepine in epilepsy patients. Phytother Res 2009;23:1281-6.
- Munakata, M., Kobayashi, K., Niisato-Nezu, J., Tanaka, S., Kakisaka, Y., Ebihara, T., Ebihara, S., Haginoya, K., Tsuchiya, S., and Onuma, A. Olfactory stimulation using black pepper oil facilitates oral feeding in pediatric patients receiving long-term en
- Myers, B. M., Smith, J. L., and Graham, D. Y. Effect of red pepper and black pepper on the stomach. Am J Gastroenterol 1987;82(3):211-214.
- Raghavendra, R. H. and Naidu, K. A. Spice active principles as the inhibitors of human platelet aggregation and thromboxane biosynthesis. Prostaglandins Leukot.Essent.Fatty Acids 2009;81(1):73-78. PubMed
- Subehan, Usia, T., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of human liver microsomal cytochrome P450 2D6 (CYP2D6) by alkamides of Piper nigrum. Planta Med 2006;72(6):527-532.
- Kasibhatta, R. and Naidu, M. U. Influence of piperine on the pharmacokinetics of nevirapine under fasting conditions: a randomised, crossover, placebo-controlled study. Drugs R.D. 2007;8(6):383-391. PubMed
- Usia, T., Iwata, H., Hiratsuka, A., Watabe, T., Kadota, S., and Tezuka, Y. CYP3A4 and CYP2D6 inhibitory activities of Indonesian medicinal plants. Phytomedicine. 2006;13(1-2):67-73. PubMed
- Mujumdar, A. M., Dhuley, J. N., Deshmukh, V. K., Raman, P. H., Thorat, S. L., and Naik, S. R. Effect of piperine on pentobarbitone induced hypnosis in rats. Indian J Exp.Biol. 1990;28(5):486-487.
- Panda, S. and Kar, A. Piperine lowers the serum concentrations of thyroid hormones, glucose and hepatic 5'D activity in adult male mice. Horm.Metab Res. 2003;35(9):523-526. PubMed
- Lawless, H. and Stevens, D. A. Effects of oral chemical irritation on taste. Physiol Behav. 1984;32(6):995-998. PubMed
- Hiwale, A. R., Dhuley, J. N., and Naik, S. R. Effect of co-administration of piperine on pharmacokinetics of beta-lactam antibiotics in rats. Indian J Exp.Biol. 2002;40(3):277-281.
- Han, Y., Chin Tan, T. M., and Lim, L. Y. In vitro and in vivo evaluation of the effects of piperine on P-gp function and expression. Toxicol.Appl.Pharmacol. 8-1-2008;230(3):283-289. PubMed
- Sharma, P., Varma, M. V., Chawla, H. P., and Panchagnula, R. In situ and in vivo efficacy of peroral absorption enhancers in rats and correlation to in vitro mechanistic studies. Farmaco 2005;60(11-12):874-883. PubMed
- Aher, S., Biradar, S., Gopu, C. L., and Paradkar, A. Novel pepper extract for enhanced P-glycoprotein inhibition. J Pharm.Pharmacol. 2009;61(9):1179-1186. PubMed
- Zutshi, R. K., Singh, R., Zutshi, U., Johri, R. K., and Atal, C. K. Influence of piperine on rifampicin blood levels in patients of pulmonary tuberculosis. J Assoc.Physicians India 1985;33(3):223-224.
- Marotta, R. B. and Floch, M. H. Diet and nutrition in ulcer disease. Med Clin North Am 1991;75(4):967-979. PubMed
- Subehan, Usia, T., Iwata, H., Kadota, S., and Tezuka, Y. Mechanism-based inhibition of CYP3A4 and CYP2D6 by Indonesian medicinal plants. J Ethnopharmacol. 5-24-2006;105(3):449-455. PubMed
- Gimenez L, Zacharisen M. Severe pepper allergy in a young child. WMJ. 2011 Jun;110(3):138-9.
- Ren T, Yang M, Xiao M, Zhu J, Xie W, Zuo Z. Time-dependent inhibition of carbamazepine metabolism by piperine in anti-epileptic treatment. Life Sci. 2019;218:314-323. PubMed
- Thomas AB, Choudhary DC, Raje A, Nagrik SS. Pharmacokinetics and pharmacodynamic herb-drug interaction of piperine with atorvastatin in rats. J Chromatogr Sci 2021;59(4):371-80. PubMed
- Haron MH, Dale O, Martin K, et al. Evaluation of the Herb-Drug Interaction Potential of Commonly Used Botanicals on the US Market with Regard to PXR- and AhR-Mediated Influences on CYP3A4 and CYP1A2. J Diet Suppl 2022. PubMed
- Lin F, Hu Y, Zhang Y, Zhao L, Zhong D, Liu J. Predicting Food-Drug Interactions between Piperine and CYP3A4 Substrate Drugs Using PBPK Modeling. Int J Mol Sci 2024;25(20):10955. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC