
SAGO-C-500 Ingredients & Drug Interactions
by Nutri-West
What is this page for?
First and foremost: checking SAGO-C-500 against your medications. The heart of this page is the interaction checker and the full interaction report — how this product’s ingredients may interact with prescription and over-the-counter medicines you may be taking.
Around that, we add a pharmacist’s high-level view of the product as a whole — what’s inside, the evidence for its stated use, how transparent the label is, and what safety data exists — so you can see the full picture in one place. It’s educational information from our licensed clinical databases and the clinical staff at HelloPharmacist — not medical advice — and we don’t sell or endorse products. Our editorial policy
SAGO-C-500 is a dietary supplement by Nutri-West with 8 active ingredients. Its ingredients are commonly taken for varicose veins and chronic venous insufficiency, hemorrhoids, easy bruising and fragile capillaries.Based on those ingredients, 1,312 medications have a known interaction with it, the most serious rated moderate. The ingredients most likely to interact are Propolis, Hesperidin, Vitamin C. Use the checker below to test your specific medication, or read the full HelloPharmacist Interaction Report.
Check Your Meds Against SAGO-C-500 by Nutri-West
Ask about any prescription or over-the-counter medication and we check it for interactions with SAGO-C-500 by Nutri-West — and tell you which ingredient is responsible.
AI summaries are generated from our interaction database for education only — always confirm with your pharmacist. How we use AI
Ask the Pharmacist
A licensed pharmacist will answer your question by email — free, usually within 24 hours.
Got it — thank you!
A licensed pharmacist will answer within 24 hours. Keep an eye on your email (worth checking spam, just in case).
HelloPharmacist Scorecard of SAGO-C-500 by Nutri-West
Four independent checks of what is known — a summary of the available information, not a grade of the product itself.
By FDA rules, dietary supplements can’t claim to treat, cure, or prevent disease — so labels speak in careful marketing language. We discern each product’s intended use from its name, label claims, and label statements, then grade the clinical evidence for that use. How these ratings are computed
The stated purpose hasn't been mapped to our evidence data yet.
Why this rating?
- We haven't mapped this product's purpose to our evidence data yet — it'll be graded on the next content refresh.
Most active ingredients don't disclose an individual amount — you can't tell how much of each you're getting.
Why this rating?
- The label discloses an exact amount for 1 of its 8 active ingredients.
- “Proprietary Blend” is a proprietary blend — the label gives one combined amount (53 mg) without saying how much of each component you get.
The most serious documented interaction for these ingredients is Moderate. Check your medications for a personalized result.
Why this rating?
- 5 of the 5 matched ingredients can interact with medications — Rutin, Propolis, Lemon, Vitamin C, Hesperidin.
- The most serious interaction on file is rated Moderate.
- Some involve high-stakes drug classes: anticoagulant / antiplatelet drugs; cancer treatments; diabetes medications.
- For scale: 1,313 individual medications appear in the full list. A big number alone doesn't make a product dangerous — what matters is whether YOUR medication is on it, so run yours through the interaction checker on this page.
Adverse-effect, pregnancy, and general safety data are on file for most of these ingredients.
Why this rating?
- We hold adverse-effect (side-effect) data for 5 of the 5 matched ingredients.
- Pregnancy & breastfeeding safety ratings cover 5 of 5.
- General safety write-ups exist for 5 of 5.
- Remember: this measures how much safety information exists. Thin data is not the same as being safe.
HelloPharmacist summaryFormula with limited ingredient disclosure with no assessable stated purpose. Moderate medication interactions have been identified, and safety information is well characterized.
Assessment coverage: 5 of 8 active ingredients matched to our full ingredient reviews (monographs). Based on the product label dated Mar 24, 2020.
This Scorecard evaluates available label information, ingredient evidence, and known medication-safety considerations. It does not independently verify product identity, purity, potency, contamination, or manufacturing quality. How these ratings are computed
General information
Key facts about SAGO-C-500, straight from the product label.
| Brand | Nutri-West |
|---|---|
| Net contents | 90 Tablet(s) |
| Market status | Off market |
| Date entered into DSLD | Mar 24, 2020 |
| DSLD ID | 215098 |
| Product type | Other Combinations |
| Supplement form | Tablet Or Pill |
| Dietary claims / uses | All Other |
| Intended target group(s) | Adult (18 - 50 Years) |
Everything in this section is reproduced from the manufacturer’s own product label — it’s the label speaking, not HelloPharmacist. We show it so you can see exactly what the maker states; we don’t verify or endorse those statements.
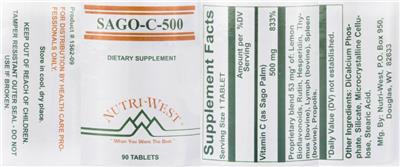
Supplement Facts
The label details for SAGO-C-500 by Nutri-West, sourced from the NIH Dietary Supplement Label Database.
Supplement Facts
| Ingredient | Amount | % DV |
|---|---|---|
| Proprietary Blend | 53 mg | -- |
| Rutin | 0 NP | -- |
| Hesperidin | 0 NP | -- |
| Lemon Bioflavonoids | 0 NP | -- |
| Spleen | 0 NP | -- |
| Propolis | 0 NP | -- |
| Thymus | 0 NP | -- |
| Vitamin C | 500 mg | 833% |
| Lymph | 0 NP | -- |
Other ingredients: Dicalcium Phosphate, Silicate, Microcrystalline Cellulose, Stearic Acid
Tap any ingredient to jump to its full detail below.
These statements are the manufacturer’s wording, reproduced from the product label — the label is saying it, not HelloPharmacist. We don’t verify or endorse them.
General Statements
For distribution by health care professionals only.
“When you want the best”
Storage
Store in cool, dry place.
Precautions
Keep out of reach of children.
Tamper resistant outer seal – do not use if broken.
FDA Statement of Identity
Dietary Supplement
Is this label outdated? Report a formula or label change and our pharmacy team will review it.
SAGO-C-500 by Nutri-West label
The label scan from the NIH Dietary Supplement Label Database. Tap to enlarge.
Label images are published by the NIH Dietary Supplement Label Database for the version of this product on file. Always read your actual product label.
View the full label (PDF)The Ingredients in SAGO-C-500 by Nutri-West
These are the 8 active ingredients this product is made of. Select any to open its full monograph.
Serving size1 Tablet(s) Dosage formTablet Or Pill Amounts shown are per serving.
Most supplement products combine several ingredients, and a medication can interact with the product through any one of them. Each ingredient below shows whether it has known drug interactions.
Proprietary Blend
- › Rutin
- › Hesperidin
- › Lemon Bioflavonoids
- › Spleen
- › Propolis
- › Thymus
- › Lymph
Vitamin C
Interacts with207 drugs
Vitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for im...
Vitamin C monograph & interactionsOther (inactive) ingredients: Dicalcium Phosphate, Silicate, Microcrystalline Cellulose, Stearic Acid. These complete the product’s ingredient list but are not active constituents.
SAGO-C-500 by Nutri-West Drug Interactions
SAGO-C-500 contains 8 ingredients, and 5 of them have known drug interactions. Altogether they interact with 1,312 medications. Here’s the picture, then you can look up your own drug.
Want to check YOUR meds against SAGO-C-500?
Ask about interactions with your drugs in plain English — “Can I take it with lisinopril?” — and we find you the answer in seconds, ingredient by ingredient.
Go to the checkerIngredients driving the most interactions
Individual Drug Interactions
The ingredients in SAGO-C-500 interact with 1,312 drugs. Click any drug to see the details.
5 of the 8 ingredients in SAGO-C-500 interact with drugs. Each result below shows which ingredient is responsible. Propolis Hesperidin Vitamin C Rutin Lemon Bioflavonoids
Ado-trastuzumab EmtansineKadcyla
How Ado-trastuzumab Emtansine interacts with SAGO-C-500 — through 1 ingredient. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Ado-trastuzumab Emtansine interactionAbciximabReoPro
How Abciximab interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
HesperidinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, hesperidin may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Hesperidin + Abciximab interactionPropolisAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, propolis might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Propolis + Abciximab interactionAbemaciclibVerzenio
How Abemaciclib interacts with SAGO-C-500 — through 1 ingredient. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Abemaciclib interactionAbiraterone
How Abiraterone interacts with SAGO-C-500 — through 1 ingredient. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Abiraterone interactionAbiraterone AcetateYonsa, Zytiga
How Abiraterone Acetate interacts with SAGO-C-500 — through 1 ingredient. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Abiraterone Acetate interactionAbrocitinibCibinqo
How Abrocitinib interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
HesperidinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, hesperidin may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Hesperidin + Abrocitinib interactionPropolisAnticoagulant/antiplatelet Drugs, Cytochrome P450 2c19 (cyp2c19) Substrates +1 Moderate
Interaction Summary
Theoretically, propolis might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Propolis + Abrocitinib interactionAcalabrutinibCalquence
How Acalabrutinib interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Acalabrutinib interactionHesperidinP-glycoprotein Substrates Moderate
Interaction Summary
Theoretically, hesperidin might inhibit P-glycoprotein-mediated drug efflux and potentially increase levels of drugs that are substrates of P-glycoprotein.
Read the full Hesperidin + Acalabrutinib interactionAcarboseGlucobay, Prandase, Precose
How Acarbose interacts with SAGO-C-500 — through 1 ingredient. Tap an ingredient for the detail:
RutinAntidiabetes Drugs Moderate
Interaction Summary
Theoretically, taking rutin with antidiabetes drugs might increase the risk of hypoglycemia.
Read the full Rutin + Acarbose interactionAcebutololRhotral, Sectral
How Acebutolol interacts with SAGO-C-500 — through 1 ingredient. Tap an ingredient for the detail:
HesperidinAntihypertensive Drugs Moderate
Interaction Summary
Theoretically, taking hesperidin with antihypertensive drugs might increase the risk of hypotension.
Read the full Hesperidin + Acebutolol interactionAcenocoumarolSintrom
How Acenocoumarol interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
HesperidinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, hesperidin may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Hesperidin + Acenocoumarol interactionPropolisAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, propolis might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Propolis + Acenocoumarol interactionAcepromazineAtravet
How Acepromazine interacts with SAGO-C-500 — through 1 ingredient. Tap an ingredient for the detail:
HesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acepromazine interactionAcetaminophenChildren's Tylenol, Children's Tylenol Meltaways, Tylenol, Tylenol Ex Strength
How Acetaminophen interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, propolis might increase levels of drugs metabolized by CYP2E1.
Read the full Propolis + Acetaminophen interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen interactionAcetaminophen, AspirinGemnisyn
How Acetaminophen, Aspirin interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +1 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP1A2.
Read the full Propolis + Acetaminophen, Aspirin interactionHesperidinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, hesperidin may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Hesperidin + Acetaminophen, Aspirin interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin interactionAcetaminophen, Aspirin, CaffeineExcedrin, Excedrin Extra Strength, Excedrin Migraine
How Acetaminophen, Aspirin, Caffeine interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisAnticoagulant/antiplatelet Drugs, Cytochrome P450 2e1 (cyp2e1) Substrates +2 Moderate
Interaction Summary
Theoretically, propolis might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
Read the full Propolis + Acetaminophen, Aspirin, Caffeine interactionHesperidinAnticoagulant/antiplatelet Drugs Moderate
Interaction Summary
Theoretically, hesperidin may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Read the full Hesperidin + Acetaminophen, Aspirin, Caffeine interactionVitamin CAcetaminophen (tylenol, Others), Aspirin Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Aspirin, Caffeine interactionAcetaminophen, Brompheniramine, PhenylpropanolamineDimetapp Cold and Flu
How Acetaminophen, Brompheniramine, Phenylpropanolamine interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP1A2.
Read the full Propolis + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Brompheniramine, Phenylpropanolamine interactionAcetaminophen, ButalbitalAxocet, Bancap, Bucet, Butex Forte, Esgic CF, Orbivan CF +5 more
How Acetaminophen, Butalbital interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates Moderate
Interaction Summary
Theoretically, propolis might increase levels of drugs metabolized by CYP2E1.
Read the full Propolis + Acetaminophen, Butalbital interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital interactionAcetaminophen, Butalbital, CaffeineEsgic, Esgic Plus, Fiogesic, Fioricet, Repan, Tecnal +1 more
How Acetaminophen, Butalbital, Caffeine interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +1 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP1A2.
Read the full Propolis + Acetaminophen, Butalbital, Caffeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine interactionAcetaminophen, Butalbital, Caffeine, CodeineEsgic with Codeine, Fioricet w/ Codeine
How Acetaminophen, Butalbital, Caffeine, Codeine interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Acetaminophen, Butalbital, Caffeine, Codeine interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Butalbital, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Caffeine, Codeine interactionAcetaminophen, Butalbital, CodeineBancap w/ Codeine
How Acetaminophen, Butalbital, Codeine interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, propolis might increase levels of drugs metabolized by CYP2E1.
Read the full Propolis + Acetaminophen, Butalbital, Codeine interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Butalbital, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine interactionAcetaminophen, Butalbital, Codeine PhosphatePhrenilin #3
How Acetaminophen, Butalbital, Codeine Phosphate interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +1 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP2D6.
Read the full Propolis + Acetaminophen, Butalbital, Codeine Phosphate interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Butalbital, Codeine Phosphate interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Butalbital, Codeine Phosphate interactionAcetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, PhenylephrineHycomine Compound
How Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP1A2.
Read the full Propolis + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Chlorpheniramine, Hydrocodone, Phenylephrine interactionAcetaminophen, Caffeine, CodeineGesic C15, Gesic C30, Gesic C8, Lenoltec 1, Lenoltec 2, Lenoltec 3 +1 more
How Acetaminophen, Caffeine, Codeine interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, propolis might increase levels of drugs metabolized by CYP2E1.
Read the full Propolis + Acetaminophen, Caffeine, Codeine interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Caffeine, Codeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine interactionAcetaminophen, Caffeine, Codeine, SalicylamideCodalan No.1, Codalan No.2, Codalan No.3
How Acetaminophen, Caffeine, Codeine, Salicylamide interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Acetaminophen, Caffeine, Codeine, Salicylamide interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Caffeine, Codeine, Salicylamide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Codeine, Salicylamide interactionAcetaminophen, Caffeine, DihydrocodeineDHC Plus, Panlor DC, Panlor SS
How Acetaminophen, Caffeine, Dihydrocodeine interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 1a2 (cyp1a2) Substrates, Cytochrome P450 2d6 (cyp2d6) Substrates +2 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP1A2.
Read the full Propolis + Acetaminophen, Caffeine, Dihydrocodeine interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Caffeine, Dihydrocodeine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Dihydrocodeine interactionAcetaminophen, Caffeine, IsomethepteneMigralam
How Acetaminophen, Caffeine, Isometheptene interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +1 Moderate
Interaction Summary
Theoretically, propolis might increase levels of drugs metabolized by CYP2E1.
Read the full Propolis + Acetaminophen, Caffeine, Isometheptene interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Isometheptene interactionAcetaminophen, Caffeine, PyrilamineMidol Max Strength Menstrual
How Acetaminophen, Caffeine, Pyrilamine interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +1 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Acetaminophen, Caffeine, Pyrilamine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Caffeine, Pyrilamine interactionAcetaminophen, Chlorpheniramine Maleate, Dextromethorphan HbrVicks Formula 44M Cough, Cold & Flu Relief
How Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 1a2 (cyp1a2) Substrates +2 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP2D6.
Read the full Propolis + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine Maleate, Dextromethorphan Hbr interactionAcetaminophen, Chlorpheniramine, Codeine, PhenylephrineColrex
How Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interacts with SAGO-C-500 — through 3 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2e1 (cyp2e1) Substrates, Cytochrome P450 3a4 (cyp3a4) Substrates +2 Moderate
Interaction Summary
Theoretically, propolis might increase levels of drugs metabolized by CYP2E1.
Read the full Propolis + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionHesperidinCns Depressants Moderate
Interaction Summary
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Read the full Hesperidin + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Codeine, Phenylephrine interactionAcetaminophen, Chlorpheniramine, DextromethorphanCoricidin II Extra Strength Cold and Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 2d6 (cyp2d6) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +2 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP2D6.
Read the full Propolis + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan interactionAcetaminophen, Chlorpheniramine, Dextromethorphan HydrobromideCoricidin HBP Maximum Strength Flu
How Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interacts with SAGO-C-500 — through 2 ingredients. Tap an ingredient for the detail:
PropolisCytochrome P450 3a4 (cyp3a4) Substrates, Cytochrome P450 2e1 (cyp2e1) Substrates +2 Moderate
Interaction Summary
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Read the full Propolis + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionVitamin CAcetaminophen (tylenol, Others) Minor
Interaction Summary
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
Read the full Vitamin C + Acetaminophen, Chlorpheniramine, Dextromethorphan Hydrobromide interactionEach ingredient & the kinds of drugs it affects
For each ingredient in SAGO-C-500 with known interactions, here are the types of medications they can affect. Open any type for the detail — or search your exact drug in the checker above.
Propolis
Anticoagulant/Antiplatelet Drugs
Theoretically, propolis might increase the risk of bleeding when taken with antiplatelet or anticoagulant drugs.
In vitro research shows that propolis water extract and the propolis constituent, caffeic acid phenethyl ester, can inhibit platelet aggregation. Additionally, evidence from an animal model shows that taking propolis in addition to warfarin decreases INR, suggesting that propolis can decrease the effectiveness of warfarin.
Cytochrome P450 1A2 (Cyp1A2) Substrates
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP1A2.
In vitro research shows that propolis extract can inhibit CYP1A2. However, animal research shows that propolis extract does not significantly affect CYP1A2 activity when administered to rats at doses up to 250 mg/kg. It is postulated that the constituents of propolis that inhibit CYP1A2 in vitro do not have significant effects in vivo due to low bioavailability and hepatic first-pass effect. This effect has not been reported in humans.
Cytochrome P450 2C19 (Cyp2C19) Substrates
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP2C19.
In vitro research shows that propolis extract can inhibit CYP2C19. However, animal research shows that propolis extract does not significantly affect CYP2C19 activity when administered to rats at doses up to 250 mg/kg. It is postulated that the constituents of propolis that inhibit CYP2C19 in vitro do not have significant effects in vivo due to low bioavailability and hepatic first-pass effect. This effect has not been reported in humans.
Cytochrome P450 2C9 (Cyp2C9) Substrates
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP2C9.
In vitro research shows that propolis extract can inhibit CYP2C9. However, animal research shows that propolis extract does not significantly affect CYP2C9 activity when administered to rats at doses up to 250 mg/kg. It is postulated that the constituents of propolis that inhibit CYP2C9 in vitro do not have significant effects in vivo due to low bioavailability and hepatic first-pass effect. This effect has not been reported in humans.
Cytochrome P450 2D6 (Cyp2D6) Substrates
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP2D6.
In vitro research shows that propolis extract can inhibit CYP2D6. However, animal research shows that propolis extract does not significantly affect CYP2D6 activity when administered to rats at doses up to 250 mg/kg. It is postulated that the constituents of propolis that inhibit CYP2D6 in vitro do not have significant effects in vivo due to low bioavailability and hepatic first-pass effect. This effect has not been reported in humans.
Cytochrome P450 2E1 (Cyp2E1) Substrates
Theoretically, propolis might increase levels of drugs metabolized by CYP2E1.
In vitro research shows that propolis can inhibit CYP2E1. This effect has not been reported in humans.
Cytochrome P450 3A4 (Cyp3A4) Substrates
Theoretically, high doses of propolis might increase blood levels of drugs metabolized by CYP3A4.
Some in vitro research shows that propolis extract can inhibit CYP3A4; however, other in vitro research shows that propolis has no effect on CYP3A4 activity. Furthermore, animal research shows that propolis extract does not significantly affect CYP3A4 activity when administered to rats at doses up to 250 mg/kg. It is postulated that the constituents of propolis that might in inhibit CYP3A4 in vitro do not have significant effects in vivo due to low bioavailability and hepatic first-pass effect. This effect has not been reported in humans.
Warfarin (Coumadin)
Theoretically, propolis might decrease the effectiveness of warfarin.
Animal research shows that taking propolis in addition to warfarin decreases the international normalized ratio (INR). This effect has not been reported in humans.
Hesperidin
Anticoagulant/Antiplatelet Drugs
Theoretically, hesperidin may increase the risk of bleeding if used with anticoagulant or antiplatelet drugs.
Animal research suggests that hesperetin, a bioflavonoid aglycone derivative of hesperidin, may have antiplatelet activity.
Antihypertensive Drugs
Theoretically, taking hesperidin with antihypertensive drugs might increase the risk of hypotension.
Some clinical and animal research shows that hesperidin can decrease blood pressure. However, other clinical research shows that hesperidin does not affect blood pressure.
Celiprolol (Celicard)
Theoretically, hesperidin may decrease the levels and clinical effects of celiprolol.
Animal research shows that concomitant use of hesperidin may reduce the plasma area under the curve of celiprolol by up to 75%. This effect has not been reported in humans.
Cns Depressants
Theoretically, concomitant use with CNS depressants may cause additive sedative effects.
Animal studies show that hesperidin has sedative effects, due to opioid receptor activity and can increase sedation when used with diazepam. This effect has not been reported in humans.
Diltiazem (Cardizem, Others)
Theoretically, hesperidin may increase the levels and clinical effects of diltiazem.
Animal research suggests that hesperidin may enhance the bioavailability of diltiazem, increasing the plasma area under the curve of diltiazem by up to 65.3%. This effect has not been reported in humans.
P-Glycoprotein Substrates
Theoretically, hesperidin might inhibit P-glycoprotein-mediated drug efflux and potentially increase levels of drugs that are substrates of P-glycoprotein.
In vitro research shows that hesperidin can inhibit P-glycoprotein efflux. This effect has not been reported in humans.
Verapamil (Calan, Others)
Theoretically, hesperidin might increase the levels and clinical effects of verapamil.
Animal research suggests that hesperidin may enhance the bioavailability of verapamil, increasing the plasma area under the curve of verapamil by 96.8%. This effect has not been reported in humans
Vitamin C
Alkylating Agents
Theoretically, antioxidant effects of vitamin C might reduce the effectiveness of alkylating agents.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs that generate free radicals, such as cyclophosphamide, chlorambucil, carmustine, busulfan, and thiotepa. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effect, if any, antioxidants such as vitamin C have on chemotherapy.
Aluminum
Vitamin C can increase the amount of aluminum absorbed from aluminum compounds.
Research in animals and humans shows that vitamin C increases aluminum absorption, theoretically by chelating aluminum and keeping it in solution where it is available for absorption. In people with normal renal function, urinary excretion of aluminum will likely increase, making aluminum retention and toxicity unlikely. Patients with renal failure who take aluminum-containing compounds such as phosphate binders should avoid vitamin C supplements in doses above the recommended dietary allowances.
Antitumor Antibiotics
Theoretically, the antioxidant effects of vitamin C might reduce the effectiveness of antitumor antibiotics.
The use of antioxidants like vitamin C during chemotherapy is controversial. There is concern that antioxidants could reduce the activity of chemotherapy drugs which generate free radicals, such as doxorubicin. In contrast, some researchers theorize that antioxidants might make chemotherapy more effective by reducing oxidative stress that could interfere with apoptosis (cell death) of cancer cells. More evidence is needed to determine what effects, if any, antioxidants such as vitamin C have on chemotherapy.
Estrogens
Vitamin C might increase blood levels of estrogens.
Increases in plasma estrogen levels of up to 55% occur under some circumstances when vitamin C is taken concurrently with oral contraceptives or hormone replacement therapy, including topical products. It is suggested that vitamin C prevents oxidation of estrogen in the tissues, regenerates oxidized estrogen, and reduces sulfate conjugation of estrogen in the gut wall. When tissue levels of vitamin C are high, these processes are already maximized and supplemental vitamin C does not have any effect on estrogen levels. Increases in plasma estrogen levels may occur when patients who are deficient in vitamin C take supplements. Monitor these patients for estrogen-related side effects.
Fluphenazine (Prolixin)
Theoretically, vitamin C might decrease levels of fluphenazine.
In one patient there was a clinically significant decrease in fluphenazine levels when vitamin C (500 mg twice daily) was started. The mechanism is not known, and there is no further data to confirm this interaction.
Indinavir (Crixivan)
Vitamin C can modestly reduce indinavir levels.
One pharmacokinetic study shows that taking vitamin C 1 gram orally once daily along with indinavir 800 mg orally three times daily reduces the area under the concentration-time curve of indinavir by 14%. The mechanism of this interaction is unknown, but it is unlikely to be clinically significant in most patients. The effect of higher doses of vitamin C on indinavir levels is unknown.
Levothyroxine (Synthroid, Others)
Vitamin C can increase levothyroxine absorption.
Two clinical studies in adults with poorly controlled hypothyroidism show that swallowing levothyroxine with a glass of water containing vitamin C 500-1000 mg in solution reduces thyroid stimulating hormone (TSH) levels and increases thyroxine (T4) levels when compared with taking levothyroxine alone. This suggests that vitamin C increases the oral absorption of levothyroxine, possibly due to a reduction in pH.
Warfarin (Coumadin)
High-dose vitamin C might reduce the levels and effectiveness of warfarin.
Vitamin C in high doses may cause diarrhea and possibly reduce warfarin absorption. There are reports of two people who took up to 16 grams daily of vitamin C and had a reduction in prothrombin time. Lower doses of 5-10 grams daily can also reduce warfarin absorption. In many cases, this does not seem to be clinically significant. However, a case of warfarin resistance has been reported for a patient who took vitamin C 500 mg twice daily. Cessation of vitamin C supplementation resulted in a rapid increase in international normalized ratio (INR). Tell patients taking warfarin to avoid taking vitamin C in excessively high doses (greater than 10 grams daily). Lower doses may be safe, but the anticoagulation activity of warfarin should be monitored. Patients who are stabilized on warfarin while taking vitamin C should avoid adjusting vitamin C dosage to prevent the possibility of warfarin resistance.
Acetaminophen (Tylenol, Others)
High-dose vitamin C might slightly prolong the clearance of acetaminophen.
A small pharmacokinetic study in healthy volunteers shows that taking high-dose vitamin C (3 grams) 1.5 hours after taking acetaminophen 1 gram slightly increases the apparent half-life of acetaminophen from around 2.3 hours to 3.1 hours. Ascorbic acid competitively inhibits sulfate conjugation of acetaminophen. However, to compensate, elimination of acetaminophen glucuronide and unconjugated acetaminophen increases. This effect is not likely to be clinically significant.
Aspirin
Acidification of the urine by vitamin C might increase aspirin levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction is not clinically significant.
Choline Magnesium Trisalicylate (Trilisate)
Acidification of the urine by vitamin C might increase choline magnesium trisalicylate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams daily of vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Niacin
Vitamin C might decrease the beneficial effects of niacin on high-density lipoprotein (HDL) cholesterol levels.
A combination of niacin and simvastatin (Zocor) effectively raises HDL cholesterol levels in patients with coronary disease and low HDL levels. Clinical research shows that taking a combination of antioxidants (vitamin C, vitamin E, beta-carotene, and selenium) along with niacin and simvastatin (Zocor) attenuates this rise in HDL, specifically the HDL-2 and apolipoprotein A1 fractions, by more than 50% in patients with coronary disease. It is not known whether this adverse effect is due to a single antioxidant such as vitamin C, or to the combination. It also is not known whether it will occur in other patient populations.
Salsalate (Disalcid)
Acidification of the urine by vitamin C might increase salsalate levels.
It has been suggested that acidification of the urine by vitamin C could increase reabsorption of salicylates by the renal tubules, and increase plasma salicylate levels. However, short-term use of up to 6 grams/day vitamin C does not seem to affect urinary pH or salicylate excretion, suggesting this interaction probably is not clinically significant.
Rutin
Antidiabetes Drugs
Theoretically, taking rutin with antidiabetes drugs might increase the risk of hypoglycemia.
Animal research suggests that rutin has hypoglycemic effects.
Lemon Bioflavonoids
Itraconazole (Sporanox)
Theoretically, taking itraconazole capsules or tablets with a beverage containing lemon might increase the levels and clinical effects of itraconazole.
In one case report, dissolving itraconazole tablets in a small amount of specific beverages containing lemon prior to administration increased the level of itraconazole in a lung transplant patient. In this case, the increased bioavailability was desirable and was likely due to improved tablet dissolution in the acidic beverage.
Brand information
Manufacturer and brand details for SAGO-C-500, from the product label.
Nutri-West
See all Nutri-West products- Name
- Nutri-West
- Street Address
- P.O. Box 950
- City
- Douglas
- State
- WY
- ZipCode
- 82633
SAGO-C-500 by Nutri-West: Common Questions
Does SAGO-C-500 by Nutri-West interact with any medications?
How can one product interact with so many drugs?
Where does this information come from?
Written and reviewed by the HelloPharmacist editorial staff. Our editorial policy
Not sure if SAGO-C-500 is safe with your meds?
Our pharmacists answer your medication & supplement questions — free.
Label information is sourced from the NIH Dietary Supplement Label Database and reflects the product version on file; always read your actual product label. This page is for education only and is not a substitute for professional medical advice. Confirm with your pharmacist or doctor before combining supplements and medications.
The Full Monographs Behind SAGO-C-500’s Ingredients
Every ingredient we hold a full HelloPharmacist monograph for — uses, evidence, safety, and the complete interaction list.
Rutin
Interacts with 86 drugsRutin is a plant flavonoid (often taken from buckwheat or citrus) that people use mainly for blood vessel and circulation problems like varicose veins and hemorrhoids. The evidence is limite...
Read the full Rutin monograph → Herb & supplement monographHesperidin
Interacts with 702 drugsHesperidin is a flavonoid found in citrus fruits that is often combined with diosmin and used for vein and circulation problems like hemorrhoids and varicose veins. Some evidence supports th...
Read the full Hesperidin monograph → Herb & supplement monographLemon
Interacts with 1 drugLemon is a common citrus fruit that is a good source of vitamin C and citric acid, and it is widely used in food, drinks, and home remedies. While it can support hydration and a healthy diet...
Read the full Lemon monograph → Herb & supplement monographPropolis
Interacts with 921 drugsPropolis is a natural, resin-like substance made by bees that has antimicrobial and anti-inflammatory properties in lab studies. Early research suggests it may help with cold sores, mouth so...
Read the full Propolis monograph → Herb & supplement monographVitamin C
Interacts with 207 drugsVitamin C (ascorbic acid) is an essential nutrient your body needs but cannot make, so you must get it from food or supplements. It's important for immune function, collagen, and acts as an...
Read the full Vitamin C monograph →Sources & How We Checked
SAGO-C-500's label data comes from the NIH Dietary Supplement Label Database; the ingredient interaction data is from the Natural Medicines database, reviewed by our pharmacists.
- NIH Dietary Supplement Label Database (DSLD) — The official product label on file for this supplement.
- Natural Medicines (Therapeutic Research Center) — Evidence-graded clinical reference behind the ingredient interaction data.
Content is written and reviewed by licensed HelloPharmacist pharmacists. See our data sources and editorial standards for how this information is built and checked.
The 90 references behind this product’s interaction data
Every citation that drives the interaction findings for this product’s ingredients, from the evidence-graded Natural Medicines (TRC Healthcare) database. Open an ingredient to browse its citations — links open the study on PubMed or the publisher’s site.
Rutin 2 references
- Mehta DK (Ex Ed). British National Formulary, Number 37. British Medical Association and Royal Pharmaceutical Society of Great Britain: London, England, March 1999.
- Sun C, Wang L, Sun J, Wang Z, Tang Z. Hypoglycemic and hypolipidemic effects of rutin on hyperglycemic rats. J Tradit Chin Med. 2020;40(4):640-645.
Hesperidin 14 references
- Fernandez, S. P., Wasowski, C., Paladini, A. C., and Marder, M. Synergistic interaction between hesperidin, a natural flavonoid, and diazepam. Eur.J.Pharmacol. 4-11-2005;512(2-3):189-198. PubMed
- Jin, Y. R., Han, X. H., Zhang, Y. H., Lee, J. J., Lim, Y., Chung, J. H., and Yun, Y. P. Antiplatelet activity of hesperetin, a bioflavonoid, is mainly mediated by inhibition of PLC-gamma2 phosphorylation and cyclooxygenase-1 activity. Atherosclerosis 200
- Loscalzo, L. M., Wasowski, C., Paladini, A. C., and Marder, M. Opioid receptors are involved in the sedative and antinociceptive effects of hesperidin as well as in its potentiation with benzodiazepines. Eur.J.Pharmacol. 2-12-2008;580(3):306-313. PubMed
- Yamamoto, M., Suzuki, A., Jokura, H., Yamamoto, N., and Hase, T. Glucosyl hesperidin prevents endothelial dysfunction and oxidative stress in spontaneously hypertensive rats. Nutrition 2008;24(5):470-476. PubMed
- El-Readi, M. Z., Hamdan, D., Farrag, N., El-Shazly, A., and Wink, M. Inhibition of P-glycoprotein activity by limonin and other secondary metabolites from Citrus species in human colon and leukaemia cell lines. Eur.J.Pharmacol. 1-25-2010;626(2-3):139-145 PubMed
- Buckshee, K., Takkar, D., and Aggarwal, N. Micronized flavonoid therapy in internal hemorrhoids of pregnancy. Int J Gynaecol Obstet 1997;57(2):145-151. PubMed
- Uesawa, Y. and Mohri, K. Hesperidin in orange juice reduces the absorption of celiprolol in rats. Biopharm Drug Dispos. 2008;29(3):185-188. PubMed
- Cho, YA, Choi, DH, and Choi, JS. Effect of hesperidin on the oral pharmacokinetics of diltiazem and its main metabolite, desacetyldiltiazem, in rats. J Pharm Pharmacol. 2009;61(6):825-829. PubMed
- Piao, YJ and Choi, JS. Enhanced bioavailability of verapamil after oral administration with hesperidin in rats. Arch Pharm Res. 2008;31(4):518-522. PubMed
- Andersen KE. Hesperidin methyl chalcone?-?a new cosmetic contact allergen. Contact Dermatitis. 2015;72(6):402-4. PubMed
- Morand C, Dubray C, Milenkovic D, et al. Hesperidin contributes to the vascular protective effects of orange juice: a randomized crossover study in healthy volunteers. Am J Clin Nutr 2011;93(1):73-80. PubMed
- Homayouni F, Haidari F, Hedayati M, Zakerkish M, Ahmadi K. Blood pressure lowering and anti-inflammatory effects of hesperidin in type 2 diabetes; a randomized double-blind controlled clinical trial. Phytother Res. 2018;32(6):1073-1079. PubMed
- Mohammadi M, Ramezani-Jolfaie N, Lorzadeh E, Khoshbakht Y, Salehi-Abargouei A. Hesperidin, a major flavonoid in orange juice, might not affect lipid profile and blood pressure: A systematic review and meta-analysis of randomized controlled clinical trials PubMed
- Valls RM, Pedret A, Calderón-Pérez L, et al. Effects of hesperidin in orange juice on blood and pulse pressures in mildly hypertensive individuals: a randomized controlled trial (Citrus study). Eur J Nutr. 2021;60(3):1277-1288. PubMed
Lemon 2 references
- Ruggenenti P, Caruso MR, Cortinovis M, et al. Fresh lemon juice supplementation for the prevention of recurrent stones in calcium oxalate nephrolithiasis: A pragmatic, prospective, randomised, open, blinded endpoint (PROBE) trial. EClinicalMedicine 2021;4 PubMed
- Umemura K, Katada Y, Nakagawa S, et al. Improved absorption of itraconazole tablet by co-administration with lemon beverages in a lung transplant recipient: A case report. J Infect Chemother 2022;28(8):1203-1207. PubMed
Propolis 21 references
- Hay KD, Greig DE. Propolis allergy: a cause of oral mucositis with ulceration. Oral Surg Oral Med Oral Pathol 1990;70:584-6. PubMed
- Li YJ, Lin JL, Yang CW, Yu CC. Acute renal failure induced by a Brazilian variety of propolis. Am J Kidney Dis 2005;46:e125-9. PubMed
- Jensen CD, Andersen KE. Allergic contact dermatitis from cera alba (purified propolis) in a lip balm and candy. Contact Dermatitis 2006;55:312-3. PubMed
- Chen, T. G., Lee, J. J., Lin, K. H., Shen, C. H., Chou, D. S., and Sheu, J. R. Antiplatelet activity of caffeic acid phenethyl ester is mediated through a cyclic GMP-dependent pathway in human platelets. Chin J Physiol 6-30-2007;50(3):121-126.
- Hsu, C. Y., Chiang, W. C., Weng, T. I., Chen, W. J., and Yuan, A. Laryngeal edema and anaphalactic shock after topical propolis use for acute pharyngitis. Am J Emerg.Med 2004;22(5):432-433. PubMed
- Black, R. J. Vulval eczema associated with propolis sensitization from topical therapies treated successfully with pimecrolimus cream. Clin Exp.Dermatol. 2005;30(1):91-92. PubMed
- Matos D, Serrano P, Brandao FM. A case of allergic contact dermatitis caused by propolis-enriched honey. Contact Dermatitis 2015;72(1):59-60. PubMed
- Naramoto K, Kato M, Ichihara K. Effects of an ethanol extract of Brazilian green propolis on human cytochrome P450 enzyme activities in vitro. J Agric Food Chem 2014;62(46):11296-302. PubMed
- Nyman G, Hagvall L. A case of allergic contact cheilitis caused by propolis and honey. Contact Dermatitis 2016;74(3):186-7. PubMed
- Ryu CS, Oh SJ, Oh JM, et al. Inhibition of cytochrome P450 by propolis in human liver microsomes. Toxicol Res 2016;32(3):207-13. PubMed
- Akbay E, Özenirler Ç, Çelemli ÖG, Durukan AB, Onur MA, Sorkun K. Effects of propolis on warfarin efficacy. Kardiochir Torakochirurgia Pol. 2017;14(1):43-46. PubMed
- Lamoureux A, Meharon M, Durand AL, Darrigade AS, Doutre MS, Milpied B. A first case of erythema multiforme-like contact dermatitis caused by propolis. Contact Dermatitis. 2017;77(4):263-264. PubMed
- Piredda M, Facchinetti G, Biagioli V, et al. Propolis in the prevention of oral mucositis in breast cancer patients receiving adjuvant chemotherapy: A pilot randomised controlled trial. Eur J Cancer Care (Engl). 2017;26(6). PubMed
- Zhang YX, Yang TT, Xia L, Zhang WF, Wang JF, Wu YP. Inhibitory Effect of Propolis on Platelet Aggregation In Vitro. J Healthc Eng. 2017;2017:3050895. PubMed
- Nyman GSA, Tang M, Inerot A, Osmancevic A, Malmberg P, Hagvall L. Contact allergy to beeswax and propolis among patients with cheilitis or facial dermatitis. Contact Dermatitis 2019;81(2):110-6. PubMed
- Igarashi G, Segawa T, Akiyama N, et al. Efficacy of Brazilian propolis supplementation for japanese lactating women for atopic sensitization and nonspecific symptoms in their offspring: a randomized, double-blind, placebo-controlled trial. Evid Based Comp PubMed
- Soleimani D, Rezaie M, Rajabzadeh F, et al. Protective effects of propolis on hepatic steatosis and fibrosis among patients with nonalcoholic fatty liver disease (NAFLD) evaluated by real-time two-dimensional shear wave elastography: a randomized clinical
- D'Ercole MC. Prolonged use of propolis can increase liver enzymes. J Gastrointestin Liver Dis 2020;29(3):468-9. PubMed
- Cho E, Lee JD, Cho SH. Systemic contact dermatitis from propolis ingestion. Ann Dermatol. 2011;23(1):85-88. PubMed
- Hallajzadeh J, Milajerdi A, Amirani E, Attari VE, Maghsoudi H, Mirhashemi SM. Effects of propolis supplementation on glycemic status, lipid profiles, inflammation and oxidative stress, liver enzymes, and body weight: a systematic review and meta-analysis
- Gheflati A, Dehnavi Z, Ghannadzadeh Yazdi A, Khorasanchi Z, Raeisi-Dehkordi H, Ranjbar G. The effects of propolis supplementation on metabolic parameters: a systematic review and meta-analysis of randomized controlled clinical trials. Avicenna J Phytomed
Vitamin C 51 references
- McEvoy GK, ed. AHFS Drug Information. Bethesda, MD: American Society of Health-System Pharmacists, 1998.
- Back DJ, Breckenridge AM, MacIver M, et al. Interaction of ethinyloestradiol with ascorbic acid in man. Br Med J (Clin Res Ed) 1981;282:1516.
- Morris JC, Beeley L, Ballantine N. Interaction of ethinyloestradiol with ascorbic acid in man [letter]. Br Med J (Clin Res Ed) 1981;283:503.
- Labriola D, Livingston R. Possible interactions between dietary antioxidants and chemotherapy. Oncology 1999;13:1003-8.
- Dwyer JH, Merz NB, Shirocre AM, et al. Progression of early atherosclerosis and intake of vitamin C and vitamin E from supplements and food. The Los Angeles Atherosclerosis Study. 41st Annual Conference on Cardiovascular Disease Epidemiology and Prevent
- Levine M, Rumsey SC, Daruwala R, et al. Criteria and recommendations for vitamin C intake. JAMA 1999;281:1415-23. PubMed
- Hansten PD, Horn JR. Drug Interactions Analysis and Management. Vancouver, WA: Applied Therapeutics Inc., 1997 and updates.
- Segal S, Kaminski S. Drug-nutrient interactions. American Druggist 1996 Jul;42-8.
- Food and Nutrition Board, Institute of Medicine. Dietary Reference Intakes for Vitamin C, Vitamin E, Selenium, and Carotenoids. Washington, DC: National Academy Press, 2000. Available at: http://www.nap.edu/books/0309069351/html/.
- Houston JB, Levy G. Drug biotransformation interactions in man VI: Acetaminophen and ascorbic acid. J Pharm Sci 1976;65:1218-21. PubMed
- Brown BG, Zhao XQ, Chait A, et al. Simvastatin and niacin, antioxidant vitamins, or the combination for the prevention of coronary disease. N Engl J Med 2001;345:1583-93. DOI
- Rosenthal G. Interaction of ascorbic acid and warfarin. JAMA 1971;215:1671. DOI
- Hume R, Johnstone JM, Weyers E. Interaction of ascorbic acid and warfarin. JAMA 1972;219:1479. DOI
- Smith EC, Skalski RJ, Johnson GC, Rossi GV. Interaction of ascorbic acid and warfarin. JAMA 1972;221:1166. DOI
- Traxer O, Huet B, Poindexter J, et al. Effect of ascorbic acid consumption on urinary stone risk factors. J Urol 2003;170:397-401.. PubMed
- Domingo JL, Gomez M, Llobet JM, Richart C. Effect of ascorbic acid on gastrointestinal aluminum absorption (letter). Lancet 1991;338:1467.
- Domingo JL, Gomez M, Llobet JM, Corbella J. Influence of some dietary constituents on aluminum absorption and retention in rats. Kidney Int 1991;39:598-601. PubMed
- Partridge NA, Regnier FE, White JL, Hem SL. Influence of dietary constituents on intestinal absorption of aluminum. Kidney Int 1989;35:1413-7. PubMed
- Mc Leod DC, Nahata MC. Inefficacy of ascorbic acid as a urinary acidifier (letter). N Engl J Med 1977;296:1413. DOI
- Hansten PD, Hayton WL. Effect of antacid and ascorbic acid on serum salicylate concentration. J Clin Pharmacol 1980;20:326-31. PubMed
- Dysken MW, Cumming RJ, Channon RA, Davis JM. Drug interaction between ascorbic acid and fluphenazine. JAMA 1979;241:2008. DOI
- Vihtamaki T, Parantainen J, Koivisto AM, et al. Oral ascorbic acid increases plasma oestradiol during postmenopausal hormone replacement therapy. Maturitas 2002;42:129-35. PubMed
- Slain D, Amsden JR, Khakoo RA, et al. Effect of high-dose vitamin C on the steady-state pharmacokinetics of the protease inhibitor indinavir in healthy volunteers. Pharmacotherapy 2005;25:165-70. PubMed
- Cheung MC, Zhao XQ, Chait A, et al. Antioxidant supplements block the response of HDL to simvastatin-niacin therapy in patients with coronary artery disease and low HDL. Arterioscler Thromb Vasc Biol 2001;21:1320-6. PubMed
- Feetam CL, Leach RH, Meynell MJ. Lack of a clinically important interaction between warfarin and ascorbic acid. Toxicol Appl Pharmacol 1975;31:544-7. PubMed
- Weintraub M, Griner PF. Warfarin and ascorbic acid: lack of evidence for a drug interaction. Toxicol Appl Pharmacol 1974;28:53-6. PubMed
- Lee DH, Folsom AR, Harnack L, et al. Does supplemental vitamin C increase cardiovascular disease risk in women with diabetes? Am J Clin Nutr 2004;80:1194-200. PubMed
- Taylor EN, Stampfer MJ, Curhan GC. Dietary factors and the risk of incident kidney stones in men: new insights after 14 years of follow-up. J Am Soc Nephrol 2004;15:3225-32. PubMed
- Ward NC, Hodgson JM, Croft KD, et al. The combination of vitamin C and grape-seed polyphenols increases blood pressure: a randomized, double-blind, placebo-controlled trial. J Hypertens 2005;23:427-34.. PubMed
- Prasad KN. Rationale for using high-dose multiple dietary antioxidants as an adjunct to radiation therapy and chemotherapy. J Nutr 2004;134:3182S-3S. PubMed
- Conklin KA. Cancer chemotherapy and antioxidants. J Nutr 2004;134:3201S-3204S. PubMed
- Fairweather-Tait S, Hickson K, McGaw B, et al. Orange juice enhances aluminium absorption from antacid preparation. Eur J Clin Nutr. 1994;48(1):71-3.
- Gruenwald, J., Graubaum, H. J., Busch, R., and Bentley, C. Safety and tolerance of ester-C compared with regular ascorbic acid. Adv.Ther. 2006;23(1):171-178.
- Rahimi, R., Nikfar, S., Rezaie, A., and Abdollahi, M. A meta-analysis on the efficacy and safety of combined vitamin C and E supplementation in preeclamptic women. Hypertens.Pregnancy. 2009;28(4):417-434. PubMed
- Einerson, B., Nathorn, C., Kitiyakara, C., Sirada, M., and Thamlikitkul, V. The efficacy of ascorbic acid in suboptimal responsive anemic hemodialysis patients receiving erythropoietin: a meta-analysis. J Med.Assoc.Thai. 2011;94 Suppl 1:S134-S146.
- Li, G., Li, L., Yu, C., and Chen, L. Effect of vitamins C and E supplementation on Helicobacter pylori eradication: a meta-analysis. Br.J Nutr 2011;106(11):1632-1637.
- Chen X, Shen L, Gu X, et al. High-dose supplementation with vitamin C--induced pediatric urolithiasis: the first case report in a child and literature review. Urology. 2014;84(4):922-4. PubMed
- Sattar A, Willman JE, Kolluri R. Possible warfarin resistance due to interaction with ascorbic acid: case report and literature review. Am J Health Syst Pharm. 2013;70(9):782-6. PubMed
- Yaich S, Chaabouni Y, Charfeddine K, et al. Secondary oxalosis due to excess vitamin C intake: a cause of graft loss in a renal transplant recipient. Saudi J Kidney Dis Transpl. 2014;25(1):113-6. PubMed
- Jalloh MA, Gregory PJ, Hein D, et al. Dietary supplement interactions with antiretrovirals: a systematic review. Int J STD AIDS. 2017 Jan;28(1):4-15. PubMed
- Rumbold A, Ota E, Nagata C, Shahrook S, Crowther CA. Vitamin C supplementation in pregnancy. Cochrane Database Syst Rev. 2015;(9):CD004072. PubMed
- Seo MS, Kim JK, Shim JY. High-dose vitamin C promotes regression of multiple pulmonary metastases originating from hepatocellular carcinoma. Yonsei Med J. 2015;56(5):1449-52. PubMed
- Skelin M, Lucijanic T, Amidzic Klaric D, et al. Factors Affecting Gastrointestinal Absorption of Levothyroxine: A Review. Clin Ther. 2017 Feb;39(2):378-403. PubMed
- Jiang K, Tang K, Liu H, Xu H, Ye Z, Chen Z. Ascorbic acid supplements and kidney stones incidence among men and women: a systematic review and meta-analysis. Urol J. 2019;16(2):115-120.
- Thomas S, Patel D, Bittel B, et al. Effect of High-Dose Zinc and Ascorbic Acid Supplementation vs Usual Care on Symptom Length and Reduction Among Ambulatory Patients With SARS-CoV-2 Infection: The COVID A to Z Randomized Clinical Trial. JAMA Netw Open. 2 PubMed
- Giffen MA, McLemore JL. Hyperoxalosis Secondary to Intravenous Vitamin C Administration as a Non-Allopathic Treatment for Cancer. Acad Forensic Pathol 2019;9(1-2):118-126. PubMed
- Maike A, Sturgill D, Gallan A. Oxalate Nephropathy in a Renal Transplant Recipient After Receiving High Dose Ascorbic Acid. Am J Med Sci 2021. PubMed
- Shen ZY, Chen YR, Wang MC, Chang SS. High-dose vitamin C-induced acute oxalate nephropathy in a renal transplant recipient: a case report and literature review. Asian J Surg 2022. PubMed
- Yanase F, Spano S, Maeda A, et al. Mega-dose sodium ascorbate: a pilot, single-dose, physiological effect, double-blind, randomized, controlled trial. Crit Care 2023;27(1):371. PubMed
- Sharma Y, Sumanadasa S, Shahi R, et al. Efficacy and safety of vitamin C supplementation in the treatment of community-acquired pneumonia: a systematic review and meta-analysis with trial sequential analysis. Sci Rep 2024;14(1):11846. PubMed
- Pejcic AV, Petrovic NZ, Djordjic MD, Milosavljevic MN. Vitamin C Levels in Pregnant Women and the Efficacy of Vitamin C Supplements in Preventing Premature Rupture of Membranes: A Systematic Review and Meta-Analysis. Balkan Med J 2024;41(4):248-260. PubMed
Parts of this content are provided by the Therapeutic Research Center, LLC.
DISCLAIMER: Currently this does not check for drug-drug interactions. This is not an all-inclusive comprehensive list of potential interactions and is for informational purposes only. Not all interactions are known or well-reported in the scientific literature, and new interactions are continually being reported. Input is needed from a qualified healthcare provider including a pharmacist before starting any therapy. Application of clinical judgment is necessary.
© 2021 Therapeutic Research Center, LLC