
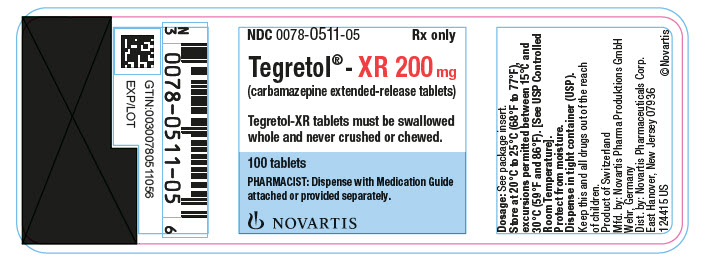
Tegretol XR carbamazepine 200 mg Tablet, Extended Release, 100-count
Other active recalls for Carbamazepine (different manufacturers) — 3 · tap to view
🆔 Identity & classification
Where does this data come from?
🏷️ RxNorm drug class
This medicine belongs to the Mood Stabilizer class.
Where does this data come from?
🏭 Manufacturer & labeler
Where does this data come from?
🩺 Clinical
- That depends on why your doctor prescribed it. If you have epilepsy, it helps prevent certain types of seizures by calming overactive electrical signals in the brain. If you have t...
- What exactly is carbamazepine supposed to do for me?
- Please don't stop it suddenly without talking to your doctor first — this is really important. Stopping carbamazepine abruptly can trigger serious seizures or even a dangerous cond...
- Can I just stop taking it if I feel better or if I don't like the side effects?
Patient education
Supplement & herbal interactions
Some supplements/herbs that may interact with Carbamazepine — tap one for details:
Carbamazepine may be associated with lower levels of 11 nutrients — worth a chat with your pharmacist, not a cause for alarm.
Where does this data come from?
Ask a licensed pharmacist directly — free, answered by our team.
💊 What it looks like
Where does this data come from?
🧪 Inactive Ingredients / Excipients
Inactive ingredients, also called excipients, are components of the drug product other than the active ingredient. They may include fillers, dyes, coatings, preservatives, flavors, or other formulation ingredients.
💡 Tap an ingredient (hover on desktop) to see what it is and why it’s used.
-
UNII G263MI44RU
Dextrates are a carbohydrate mixture made from corn or potato starch. They work as fillers and binders in tablets and capsules to add bulk and help hold the medicine together.
-
UNII 70097M6I30
Magnesium stearate is a salt made from magnesium and stearic acid, a fatty substance. It's used in tablets and capsules as a lubricant and glidant to help ingredients flow smoothly during manufacturing and prevent sticking.
-
UNII 3OWL53L36A
A natural sugar alcohol derived from seaweed or synthesized in the lab. It's used as a filler to add bulk, a sweetener in sugar-free formulas, and a disintegrant to help tablets break apart in the stomach.
-
UNII 3WJQ0SDW1A
Polyethylene glycol is a synthetic liquid or solid polymer used in medicines as a solvent, lubricant, and humectant. It helps dissolve active ingredients, reduces friction during manufacturing, and retains moisture in the final product.
-
UNII 368GB5141J
A detergent and foaming agent derived from coconut or palm oil. In medications, it helps break down and mix oil and water-based ingredients, aids in tablet disintegration, and improves how the drug dissolves and spreads in the mouth or digestive system.
-
UNII 15FIX9V2JP
Titanium dioxide is a bright white mineral powder commonly used as a colorant and opacifying agent. It makes pills and tablets white or lighter in color and helps make coatings non-transparent.
6 inactive ingredients listed in the exact product block matched to this NDC.
Where does this data come from?
ingredient classCode="IACT" elements from the exact product block matched by this NDC. Label-section narrative from DailyMed / the openFDA label index is shown separately when available.Inactive ingredient FAQ
Are inactive ingredients the same for every manufacturer?
Why might an inactive ingredient be missing?
Can inactive ingredients matter?
💲 Pricing
A drug doesn't have one price. Each row is a different public payment system, and none is what you'd pay at the counter — that depends on your insurance. The ⓘ on each row explains what it measures.
| Price system | Per ea | Per package |
|---|---|---|
| Retail pharmacies payNADAC · weekly | $3.244 | $324.35 / 100 tablets |
| Medicaid paysCMS SDUD · 12 mo | $3.18 | $318.34 / 100 tablets |
| Medicare drug plans payPart D · Q2 2026 | $3.16 | $315.77 / 100 tablets |
Where does this data come from?
🔁 Therapeutic equivalents
| Product | Labeler | Pack | NADAC/unit | TE | Status | Price vs. this |
|---|---|---|---|---|---|---|
| Carbamazepin 200 mg 00832-6023-11 | Upsher-Smith | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 50742-0258-01 | Ingenus | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 60687-0583-21 | American | 1 tablet | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 16571-0681-01 | Rising | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 51672-4124-01 | Sun | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 72603-0887-01 | Northstar | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine ER 200 mg 42806-0275-01 | Epic | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| carbamazepine 200 mg 16714-0064-01 | Northstar | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 62332-0421-31 | Alembic | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 13668-0285-01 | Torrent | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine 200 mg 59746-0790-01 | Jubilant | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Carbamazepine ER 200 mg 72516-0020-01 | Oryza | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| carbamazepine 200 mg 68382-0556-01 | Zydus | 100 tablets | $0.378 | AB | Availability likely | save 88% |
| Tegretol XR 200 mgthis 00078-0511-05 | Novartis | 100 tablets | $3.243 | AB | Availability likely | — |
| Carbamazepine 200 mg 51407-0896-01 | Golden | 100 tablets | — | AB | FDA listed | — |
| carbamazepine 200 mg 70771-1469-01 | Zydus | 100 tablets | — | AB | FDA listed | — |
| Carbamazepine 200 mg 27241-0232-01 | Ajanta | 100 tablets | — | — | FDA listed | — |
| Carbamazepine 200 mg 70518-3699-00 | REMEDYREPACK | 1 tablet | — | AB | FDA listed | — |
| Carbamazepine 200 mg 60290-0059-01 | Umedica | 100 tablets | — | AB | FDA listed | — |
| Carbamazepine 200 mg 67877-0798-01 | Ascend | 100 tablets | — | AB | FDA listed | — |
| Carbamazepine Er 200 mg 35561-0356-12 | Bostal | 100 tablets | — | AB | FDA listed | — |
| Carbamazepine 200 mg 46708-0421-31 | Alembic | 100 tablets | — | AB | FDA listed | — |
Where does this data come from?
⏳ Availability & generic status
FDA-approved generic versions are listed, and recent pricing/market data suggests they may be available — see Therapeutic equivalents.
Where does this data come from?
🗺️ Medicaid utilization & spend
📊 Medicare Part D spend CMS · PART D · 2026 (Q1)
📦 Packaging — all sizes for this product
| Package NDC | Description | Marketing start | Status |
|---|---|---|---|
| 00078-0511-05 You're viewing this | 100 TABLET, EXTENDED RELEASE in 1 BOTTLE (0078-0511-05) | 1996-03-25 | Active |
📄 Full prescribing information FDA SPL
🚨 Boxed Warning ▾
WARNINGS SERIOUS DERMATOLOGIC REACTIONS AND HLA-B*1502 ALLELE SERIOUS AND SOMETIMES FATAL DERMATOLOGIC REACTIONS, INCLUDING TOXIC EPIDERMAL NECROLYSIS (TEN) AND STEVENS-JOHNSON SYNDROME (SJS), HAVE BEEN REPORTED DURING TREATMENT WITH TEGRETOL. THESE REACTIONS ARE ESTIMATED TO OCCUR IN 1 TO 6 PER 10,000 NEW USERS IN COUNTRIES WITH MAINLY CAUCASIAN POPULATIONS, BUT THE RISK IN SOME ASIAN COUNTRIES IS ESTIMATED TO BE ABOUT 10 TIMES HIGHER. STUDIES IN PATIENTS OF CHINESE ANCESTRY HAVE FOUND A STRONG ASSOCIATION BETWEEN THE RISK OF DEVELOPING SJS/TEN AND THE PRESENCE OF HLA-B*1502, AN INHERITED ALLELIC VARIANT OF THE HLA-B GENE.
HLA-B*1502 IS FOUND ALMOST EXCLUSIVELY IN PATIENTS WITH ANCESTRY ACROSS BROAD AREAS OF ASIA. PATIENTS WITH ANCESTRY IN GENETICALLY AT-RISK POPULATIONS SHOULD BE SCREENED FOR THE PRESENCE OF HLA-B*1502 PRIOR TO INITIATING TREATMENT WITH TEGRETOL. PATIENTS TESTING POSITIVE FOR THE ALLELE SHOULD NOT BE TREATED WITH TEGRETOL UNLESS THE BENEFIT CLEARLY OUTWEIGHS THE RISK (SEE WARNINGS AND PRECAUTIONS, LABORATORY TESTS).
APLASTIC ANEMIA AND AGRANULOCYTOSIS APLASTIC ANEMIA AND AGRANULOCYTOSIS HAVE BEEN REPORTED IN ASSOCIATION WITH THE USE OF TEGRETOL. DATA FROM A POPULATION-BASED CASE CONTROL STUDY DEMONSTRATE THAT THE RISK OF DEVELOPING THESE REACTIONS IS 5 TO 8 TIMES GREATER THAN IN THE GENERAL POPULATION. HOWEVER, THE OVERALL RISK OF THESE REACTIONS IN THE UNTREATED GENERAL POPULATION IS LOW, APPROXIMATELY SIX PATIENTS PER ONE MILLION POPULATION PER YEAR FOR AGRANULOCYTOSIS AND TWO PATIENTS PER ONE MILLION POPULATION PER YEAR FOR APLASTIC ANEMIA.
ALTHOUGH REPORTS OF TRANSIENT OR PERSISTENT DECREASED PLATELET OR WHITE BLOOD CELL COUNTS ARE NOT UNCOMMON IN ASSOCIATION WITH THE USE OF TEGRETOL, DATA ARE NOT AVAILABLE TO ESTIMATE ACCURATELY THEIR INCIDENCE OR OUTCOME. HOWEVER, THE VAST MAJORITY OF THE CASES OF LEUKOPENIA HAVE NOT PROGRESSED TO THE MORE SERIOUS CONDITIONS OF APLASTIC ANEMIA OR AGRANULOCYTOSIS. BECAUSE OF THE VERY LOW INCIDENCE OF AGRANULOCYTOSIS AND APLASTIC ANEMIA, THE VAST MAJORITY OF MINOR HEMATOLOGIC CHANGES OBSERVED IN MONITORING OF PATIENTS ON TEGRETOL ARE UNLIKELY TO SIGNAL THE OCCURRENCE OF EITHER ABNORMALITY.
NONETHELESS, COMPLETE PRETREATMENT HEMATOLOGICAL TESTING SHOULD BE OBTAINED AS A BASELINE. IF A PATIENT IN THE COURSE OF TREATMENT EXHIBITS LOW OR DECREASED WHITE BLOOD CELL OR PLATELET COUNTS, THE PATIENT SHOULD BE MONITORED CLOSELY. DISCONTINUATION OF THE DRUG SHOULD BE CONSIDERED IF ANY EVIDENCE OF SIGNIFICANT BONE MARROW DEPRESSION DEVELOPS.
🎯 Indications and Usage ▾
INDICATIONS AND USAGE Epilepsy Tegretol is indicated for use as an anticonvulsant drug. Evidence supporting efficacy of Tegretol as an anticonvulsant was derived from active drug-controlled studies that enrolled patients with the following seizure types: Partial seizures with complex symptomatology (psychomotor, temporal lobe). Patients with these seizures appear to show greater improvement than those with other types.
Generalized tonic-clonic seizures (grand mal). Mixed seizure patterns which include the above, or other partial or generalized seizures. Absence seizures (petit mal) do not appear to be controlled by Tegretol (see PRECAUTIONS, General).
Trigeminal Neuralgia Tegretol is indicated in the treatment of the pain associated with true trigeminal neuralgia. Beneficial results have also been reported in glossopharyngeal neuralgia. This drug is not a simple analgesic and should not be used for the relief of trivial aches or pains.
⏱️ Dosage and Administration ▾
DOSAGE AND ADMINISTRATION (SEE TABLE BELOW) Tegretol suspension in combination with liquid chlorpromazine or thioridazine results in precipitate formation, and, in the case of chlorpromazine, there has been a report of a patient passing an orange rubbery precipitate in the stool following coadministration of the two drugs (see PRECAUTIONS, Drug Interactions). Because the extent to which this occurs with other liquid medications is not known, Tegretol suspension should not be administered simultaneously with other liquid medications or diluents.
Monitoring of blood levels has increased the efficacy and safety of anticonvulsants (see PRECAUTIONS, Laboratory Tests). Dosage should be adjusted to the needs of the individual patient. A low initial daily dosage with a gradual increase is advised.
As soon as adequate control is achieved, the dosage may be reduced very gradually to the minimum effective level. Medication should be taken with meals. Since a given dose of Tegretol suspension will produce higher peak levels than the same dose given as the tablet, it is recommended to start with low doses (children 6 to 12 years: ½ teaspoon four times a day and to increase slowly to avoid unwanted side effects.
Conversion of patients from oral Tegretol tablets to Tegretol suspension: Patients should be converted by administering the same number of mg per day in smaller, more frequent doses (i.e., twice a day tablets to three times a day suspension). Tegretol-XR is an extended-release formulation for twice a day administration. When converting patients from Tegretol conventional tablets to Tegretol-XR, the same total daily mg dose of Tegretol-XR should be administered.
Tegretol -XR tablets must be swallowed whole and never crushed or chewed. Tegretol-XR tablets should be inspected for chips or cracks. Damaged tablets, or tablets without a release portal, should not be consumed.
Tegretol-XR tablet coating is not absorbed and is excreted in the feces; these coatings may be noticeable in the stool. Epilepsy (see INDICATIONS AND USAGE) Adults and children over 12 years of age-Initial: Either 200 mg twice a day for tablets and XR tablets, or 1 teaspoon four times a day for suspension (400 mg/day). Increase at weekly intervals by adding up to 200 mg/day using a twice a day regimen of Tegretol-XR or a three times a day or four times a day regimen of the other formulations until the optimal response is obtained.
Dosage generally should not exceed 1000 mg daily in children 12 to 15 years of age, and 1200 mg daily in patients above 15 years of age. Doses up to 1600 mg daily have been used in adults in rare instances. Maintenance: Adjust dosage to the minimum effective level, usually 800 to 1200 mg daily.
Children 6 to 12 years of age-Initial: Either 100 mg twice a day for tablets or XR tablets, or ½ teaspoon four times a day for suspension (200 mg/day). Increase at weekly intervals by adding up to 100 mg/day using a twice a day regimen of Tegretol-XR or a three times a day or four times a day regimen of the other formulations until the optimal response is obtained. Dosage generally should not exceed 1000 mg daily.
Maintenance: Adjust dosage to the minimum effective level, usually 400 to 800 mg daily. Children under 6 years of age-Initial: 10 to 20 mg/kg/day twice a day or three times a day as tablets, or four times a day as suspension. Increase weekly to achieve optimal clinical response administered three times a day or four times a day.
Maintenance: Ordinarily, optimal clinical response is achieved at daily doses below 35 mg/kg. If satisfactory clinical response has not been achieved, plasma levels should be measured to determine whether or not they are in the therapeutic range. No recommendation regarding the safety of carbamazepine for use at doses above 35 mg/kg/24 hours can be made.
Combination Therapy: Tegretol may be used alone or with other anticonvulsants. When added to existing anticonvulsant therapy, the drug should be added gradually whi…
⛔ Contraindications ▾
CONTRAINDICATIONS Tegretol should not be used in patients with a history of previous bone marrow depression, hypersensitivity to the drug, or known sensitivity to any of the tricyclic compounds, such as amitriptyline, desipramine, imipramine, protriptyline, nortriptyline, etc. Likewise, on theoretical grounds its use with monoamine oxidase (MAO) inhibitors is not recommended. Before administration of Tegretol, MAO inhibitors should be discontinued for a minimum of 14 days, or longer if the clinical situation permits.
Coadministration of carbamazepine and nefazodone may result in insufficient plasma concentrations of nefazodone and its active metabolite to achieve a therapeutic effect. Coadministration of carbamazepine with nefazodone is contraindicated.
⚠️ Warnings ▾
WARNINGS Serious Dermatologic Reactions Serious and sometimes fatal dermatologic reactions, including toxic epidermal necrolysis (TEN) and Stevens-Johnson syndrome (SJS), have been reported with Tegretol treatment. The risk of these events is estimated to be about 1 to 6 per 10,000 new users in countries with mainly Caucasian populations. However, the risk in some Asian countries is estimated to be about 10 times higher.
Fixed drug eruption (FDE), which presents with single or multiple, circumscribed patches that occur in the same location with each exposure to an offending drug, has been reported with Tegretol. With repeated exposure to Tegretol, the skin lesions may progress to generalized bullous fixed drug eruption (GBFDE), a serious skin reaction which may resemble SJS/TEN. Tegretol should be discontinued at the first sign of a rash, unless the rash is clearly not drug related.
If signs or symptoms suggest SJS/TEN, FDE, or GBFDE, use of this drug should not be resumed, and alternative therapy should be considered. SJS/TEN and HLA -B*1502 Allele Retrospective case-control studies have found that in patients of Chinese ancestry there is a strong association between the risk of developing SJS/TEN with carbamazepine treatment and the presence of an inherited variant of the HLA-B gene, HLA-B*1502. The occurrence of higher rates of these reactions in countries with higher frequencies of this allele suggests that the risk may be increased in allele-positive individuals of any ethnicity.
Across Asian populations, notable variation exists in the prevalence of HLA-B*1502. Greater than 15% of the population is reported positive in Hong Kong, Thailand, Malaysia, and parts of the Philippines, compared to about 10% in Taiwan and 4% in North China. South Asians, including Indians, appear to have intermediate prevalence of HLA-B*1502, averaging 2% to 4%, but higher in some groups.
HLA-B*1502 is present in less than 1% of the population in Japan and Korea. HLA-B*1502 is largely absent in individuals not of Asian origin (e.g., Caucasians, African-Americans, Hispanics, and Native Americans). Prior to initiating Tegretol therapy, testing for HLA-B*1502 should be performed in patients with ancestry in populations in which HLA-B*1502 may be present.
In deciding which patients to screen, the rates provided above for the prevalence of HLA-B*1502 may offer a rough guide, keeping in mind the limitations of these figures due to wide variability in rates even within ethnic groups, the difficulty in ascertaining ethnic ancestry, and the likelihood of mixed ancestry. Tegretol should not be used in patients positive for HLA-B*1502 unless the benefits clearly outweigh the risks. Tested patients who are found to be negative for the allele are thought to have a low risk of SJS/TEN (see BOXED WARNING and PRECAUTIONS, Laboratory Tests).
Over 90% of Tegretol treated patients who will experience SJS/TEN have this reaction within the first few months of treatment. This information may be taken into consideration in determining the need for screening of genetically at-risk patients currently on Tegretol. The HLA-B*1502 allele has not been found to predict risk of less severe adverse cutaneous reactions from Tegretol, such as maculopapular eruption (MPE) or to predict Drug Reaction with Eosinophilia and Systemic Symptoms (DRESS).
Limited evidence suggests that HLA-B*1502 may be a risk factor for the development of SJS/TEN in patients of Chinese ancestry taking other antiepileptic drugs associated with SJS/TEN, including phenytoin. Consideration should be given to avoiding use of other drugs associated with SJS/TEN in HLA-B*1502 positive patients, when alternative therapies are otherwise equally acceptable. Hypersensitivity Reactions and HLA-A*3101 Allele Retrospective case-control studies in patients of European, Korean, and Japanese ancestry have found a moderate association between the risk of developing hypersensitivity reactions and the presence of HLA-A*310…
🤒 Adverse Reactions ▾
ADVERSE REACTIONS If adverse reactions are of such severity that the drug must be discontinued, the physician must be aware that abrupt discontinuation of any anticonvulsant drug in a responsive epileptic patient may lead to seizures or even status epilepticus with its life-threatening hazards. The most severe adverse reactions have been observed in the hemopoietic system and skin (see BOXED WARNING), the liver, and the cardiovascular system. The most frequently observed adverse reactions, particularly during the initial phases of therapy, are dizziness, drowsiness, unsteadiness, nausea, and vomiting.
To minimize the possibility of such reactions, therapy should be initiated at the lowest dosage recommended. The following additional adverse reactions have been reported: Hemopoietic System: Aplastic anemia, agranulocytosis, pancytopenia, bone marrow depression, thrombocytopenia, leukopenia, leukocytosis, eosinophilia, acute intermittent porphyria, variegate porphyria, porphyria cutanea tarda. Skin: TEN and SJS (see BOXED WARNING), Acute Generalized Exanthematous Pustulosis (AGEP), pruritic and erythematous rashes, urticaria, photosensitivity reactions, fixed drug eruption, generalized bullous fixed drug eruption, alterations in skin pigmentation, exfoliative dermatitis, erythema multiforme and nodosum, purpura, aggravation of disseminated lupus erythematosus, alopecia, diaphoresis, onychomadesis and hirsutism.
In certain cases, discontinuation of therapy may be necessary. Cardiovascular System: Congestive heart failure, edema, aggravation of hypertension, hypotension, syncope and collapse, aggravation of coronary artery disease, arrhythmias and AV block, thrombophlebitis, thromboembolism (e.g., pulmonary embolism), and adenopathy or lymphadenopathy. Some of these cardiovascular complications have resulted in fatalities.
Myocardial infarction has been associated with other tricyclic compounds. Liver: Abnormalities in liver function tests, cholestatic and hepatocellular jaundice, hepatitis, very rare cases of hepatic failure. Pancreatic: Pancreatitis.
Respiratory System: Pulmonary hypersensitivity characterized by fever, dyspnea, pneumonitis, or pneumonia. Genitourinary System: Urinary frequency, acute urinary retention, oliguria with elevated blood pressure, azotemia, renal failure, and impotence. Albuminuria, glycosuria, elevated BUN, and microscopic deposits in the urine have also been reported.
There have been rare reports of impaired male fertility and/or abnormal spermatogenesis. Testicular atrophy occurred in rats receiving Tegretol orally from 4 to 52 weeks at dosage levels of 50 to 400 mg/kg/day. Additionally, rats receiving Tegretol in the diet for 2 years at dosage levels of 25, 75, and 250 mg/kg/day had a dose-related incidence of testicular atrophy and aspermatogenesis.
In dogs, it produced a brownish discoloration, presumably a metabolite, in the urinary bladder at dosage levels of 50 mg/kg and higher. Relevance of these findings to humans is unknown. Nervous System: Dizziness, drowsiness, disturbances of coordination, confusion, headache, fatigue, blurred vision, visual hallucinations, transient diplopia, oculomotor disturbances, nystagmus, speech disturbances, abnormal involuntary movements, peripheral neuritis and paresthesias, depression with agitation, talkativeness, tinnitus, hyperacusis, neuroleptic malignant syndrome.
There have been reports of associated paralysis and other symptoms of cerebral arterial insufficiency, but the exact relationship of these reactions to the drug has not been established. Isolated cases of neuroleptic malignant syndrome have been reported both with and without concomitant use of psychotropic drugs. Digestive System: Nausea, vomiting, gastric distress and abdominal pain, diarrhea, constipation, anorexia, and dryness of the mouth and pharynx, including glossitis and stomatitis.
Eyes: Scattered punctate cortical lens opacities, increased intraocular pressure (see WARNINGS, General)…
🔄 Drug Interactions ▾
Drug Interactions There has been a report of a patient who passed an orange rubbery precipitate in his stool the day after ingesting Tegretol suspension immediately followed by Thorazine ® * solution. Subsequent testing has shown that mixing Tegretol suspension and chlorpromazine solution (both generic and brand name) as well as Tegretol suspension and liquid Mellaril ® , resulted in the occurrence of this precipitate. Because the extent to which this occurs with other liquid medications is not known, Tegretol suspension should not be administered simultaneously with other liquid medicinal agents or diluents (see DOSAGE AND ADMINISTRATION).
Clinically meaningful drug interactions have occurred with concomitant medications and include (but are not limited to) the following: Agents That May Affect Tegretol Plasma Levels When carbamazepine is given with drugs that can increase or decrease carbamazepine levels, close monitoring of carbamazepine levels is indicated and dosage adjustment may be required. Agents That Increase Carbamazepine Levels CYP3A4 inhibitors inhibit Tegretol metabolism and can thus increase plasma carbamazepine levels. Drugs that have been shown, or would be expected, to increase plasma carbamazepine levels include aprepitant, cimetidine, ciprofloxacin, danazol, diltiazem, macrolides (e.g., erythromycin, clarithromycin), fluoxetine, fluvoxamine, trazodone, omeprazole, oxybutynin, isoniazid, niacinamide (nicotinamide), azoles (e.g., ketaconazole, itraconazole, fluconazole, voriconazole), acetazolamide, verapamil, ticlopidine, grapefruit juice, and protease inhibitors.
Human microsomal epoxide hydrolase has been identified as the enzyme responsible for the formation of the 10,11-transdiol derivative from carbamazepine-10,11 epoxide. Coadministration of inhibitors of human microsomal epoxide hydrolase may result in increased carbamazepine-10,11 epoxide plasma concentrations. Accordingly, the dosage of Tegretol should be adjusted and/or the plasma levels monitored when used concomitantly with loxapine, quetiapine, valproic acid, or brivaracetam.
Agents That Decrease Carbamazepine Levels CYP3A4 inducers can increase the rate of Tegretol metabolism. Drugs that have been shown, or that would be expected, to decrease plasma carbamazepine levels include cisplatin, doxorubicin HCl, felbamate, fosphenytoin, rifampin, phenobarbital, phenytoin, primidone, methsuximide, theophylline, aminophylline. Effect of Tegretol on Plasma Levels of Concomitant Agents Decreased Levels of Concomitant Medications Tegretol is a potent inducer of hepatic 3A4 and is also known to be an inducer of CYP1A2, 2B6, 2C8/9/19, and may therefore reduce plasma concentrations of co-medications mainly metabolized by CYP1A2, 2B6, 2C8/9/19, and 3A4, through induction of their metabolism.
When used concomitantly with Tegretol, monitoring of concentrations or dosage adjustment of these agents may be necessary: When carbamazepine is added to aripiprazole, the aripiprazole dose should be doubled. Additional dose increases should be based on clinical evaluation. If carbamazepine is later withdrawn, the aripiprazole dose should be reduced.
When carbamazepine is used with tacrolimus, monitoring of tacrolimus blood concentrations and appropriate dosage adjustments are recommended. The use of concomitant strong CYP3A4 inducers, such as carbamazepine should be avoided with temsirolimus. If patients must be coadministered carbamazepine with temsirolimus, an adjustment of temsirolimus dosage should be considered.
The use of carbamazepine with lapatinib should generally be avoided. If carbamazepine is started in a patient already taking lapatinib, the dose of lapatinib should be gradually titrated up. If carbamazepine is discontinued, the lapatinib dose should be reduced.
Concomitant use of carbamazepine with nefazodone results in plasma concentrations of nefazodone and its active metabolite insufficient to achieve a therapeutic effect. Coadministration of carbamazepin…
🤰 Pregnancy ▾
Usage in Pregnancy Carbamazepine can cause fetal harm when administered to a pregnant woman. Epidemiological data suggest that there may be an association between the use of carbamazepine during pregnancy and congenital malformations, including spina bifida. There have also been reports that associate carbamazepine with developmental disorders and congenital anomalies (e.g., craniofacial defects, cardiovascular malformations, and anomalies involving various body systems).
Developmental delays based on neurobehavioral assessments have been reported. When treating or counseling women of childbearing potential, the prescribing physician will wish to weigh the benefits of therapy against the risks. If this drug is used during pregnancy, or if the patient becomes pregnant while taking this drug, the patient should be apprised of the potential hazard to the fetus.
Retrospective case reviews suggest that, compared with monotherapy, there may be a higher prevalence of teratogenic effects associated with the use of anticonvulsants in combination therapy. Therefore, if therapy is to be continued, monotherapy may be preferable for pregnant women. In humans, transplacental passage of carbamazepine is rapid (30 to 60 minutes), and the drug is accumulated in the fetal tissues, with higher levels found in liver and kidney than in brain and lung.
Carbamazepine has been shown to have adverse effects in reproduction studies in rats when given orally in dosages 10 to 25 times the maximum human daily dosage (MHDD) of 1200 mg on a mg/kg basis or 1.5 to 4 times the MHDD on a mg/m 2 basis. In rat teratology studies, 2 of 135 offspring showed kinked ribs at 250 mg/kg and 4 of 119 offspring at 650 mg/kg showed other anomalies (cleft palate, 1; talipes, 1; anophthalmos, 2). In reproduction studies in rats, nursing offspring demonstrated a lack of weight gain and an unkempt appearance at a maternal dosage level of 200 mg/kg.
There have been a few cases of neonatal seizures and/or respiratory depression associated with maternal Tegretol and other concomitant anticonvulsant drug use. A few cases of neonatal vomiting, diarrhea, and/or decreased feeding have also been reported in association with maternal Tegretol use. These symptoms may represent a neonatal withdrawal syndrome.
To provide information regarding the effects of in utero exposure to Tegretol, physicians are advised to recommend that pregnant patients taking Tegretol enroll in the North American Antiepileptic Drug (NAAED) Pregnancy Registry. This can be done by calling the toll-free number 1-888-233-2334 and must be done by patients themselves. Information on the registry can also be found at the website http://www.aedpregnancyregistry.org/ .
Clinical Considerations Disease-associated Maternal and/or Embryofetal Risk Epilepsy, with or without exposure to antiepileptic drugs, has been associated with several adverse outcomes during pregnancy, including preeclampsia, preterm labor, antepartum and postpartum hemorrhage, placental abruption, poor fetal growth, prematurity, fetal death, and maternal mortality. The risk of maternal or fetal injury may be greatest for patients with untreated or poorly controlled convulsive seizures. Women with epilepsy who become pregnant should not abruptly discontinue antiepileptic drugs, including TEGRETOL, due to the risk of status epilepticus or severe seizures, which may be life-threatening.
Usage in Pregnancy (see WARNINGS).
🧒 Pediatric Use ▾
Pediatric Use Substantial evidence of Tegretol’s effectiveness for use in the management of children with epilepsy (see INDICATIONS AND USAGE for specific seizure types) is derived from clinical investigations performed in adults and from studies in several in vitro systems which support the conclusion that (1) the pathogenetic mechanisms underlying seizure propagation are essentially identical in adults and children, and (2) the mechanism of action of carbamazepine in treating seizures is essentially identical in adults and children.
Taken as a whole, this information supports a conclusion that the generally accepted therapeutic range of total carbamazepine in plasma (i.e., 4 to 12 mcg/mL) is the same in children and adults. The evidence assembled was primarily obtained from short-term use of carbamazepine. The safety of carbamazepine in children has been systematically studied up to 6 months.
No longer-term data from clinical trials is available. Tegretol suspension contains propylene glycol as an inactive ingredient. Patients less than 5 years of age are at the highest risk for propylene glycol toxicity due to incomplete alcohol dehydrogenase maturity.
Particularly, neonates (including full-term babies and pre-term babies less than 44 post-menstrual weeks of age). The total daily intake of propylene glycol from all sources, including concomitant drugs, should be considered in managing the risk of propylene glycol toxicity (see WARNINGS Propylene Glycol Toxicity).
🧓 Geriatric Use ▾
Geriatric Use No systematic studies in geriatric patients have been conducted.
🆘 Overdosage ▾
OVERDOSAGE Acute Toxicity Lowest known lethal dose: adults, 3.2 g (a 24-year-old woman died of a cardiac arrest and a 24-year-old man died of pneumonia and hypoxic encephalopathy); children, 4 g (a 14-year-old girl died of a cardiac arrest), 1.6 g (a 3-year-old girl died of aspiration pneumonia). Oral LD 50 in animals (mg/kg): mice, 1100 to 3750; rats, 3850 to 4025; rabbits, 1500 to 2680; guinea pigs, 920. Signs and Symptoms The first signs and symptoms appear after 1 to 3 hours.
Neuromuscular disturbances are the most prominent. Cardiovascular disorders are generally milder, and severe cardiac complications occur only when very high doses (greater than 60 g) have been ingested. Respiration: Irregular breathing, respiratory depression.
Cardiovascular System: Tachycardia, hypotension or hypertension, shock, conduction disorders. Nervous System and Muscles: Impairment of consciousness ranging in severity to deep coma. Convulsions, especially in small children.
Motor restlessness, muscular twitching, tremor, athetoid movements, opisthotonos, ataxia, drowsiness, dizziness, mydriasis, nystagmus, adiadochokinesia, ballism, psychomotor disturbances, dysmetria. Initial hyperreflexia, followed by hyporeflexia. Gastrointestinal Tract: Nausea, vomiting.
Kidneys and Bladder: Anuria or oliguria, urinary retention. Laboratory Findings: Isolated instances of overdosage have included leukocytosis, reduced leukocyte count, glycosuria, and acetonuria. EEG may show dysrhythmias.
Combined Poisoning: When alcohol, tricyclic antidepressants, barbiturates, or hydantoins are taken at the same time, the signs and symptoms of acute poisoning with Tegretol may be aggravated or modified. Propylene Glycol Toxicity: In cases of suspected overdose with Tegretol suspension, which contains 25 mg of propylene glycol per mL, monitor for signs of propylene glycol toxicity, including hemolysis, hyperosmolarity with anion gap metabolic acidosis, acute kidney injury, CNS toxicity, and multi-organ failure. Treatment The prognosis in cases of severe poisoning is critically dependent upon prompt elimination of the drug, which may be achieved by inducing vomiting, irrigating the stomach, and by taking appropriate steps to diminish absorption.
If these measures cannot be implemented without risk on the spot, the patient should be transferred at once to a hospital, while ensuring that vital functions are safeguarded. There is no specific antidote. Elimination of the Drug: Induction of vomiting.
Gastric lavage. Even when more than 4 hours have elapsed following ingestion of the drug, the stomach should be repeatedly irrigated, especially if the patient has also consumed alcohol. Measures to Reduce Absorption: Activated charcoal, laxatives.
Measures to Accelerate Elimination: Forced diuresis. Dialysis is indicated only in severe poisoning associated with renal failure. Replacement transfusion is indicated in severe poisoning in small children.
Respiratory Depression: Keep the airways free; resort, if necessary, to endotracheal intubation, artificial respiration, and administration of oxygen. Hypotension, Shock: Keep the patient’s legs raised and administer a plasma expander. If blood pressure fails to rise despite measures taken to increase plasma volume, use of vasoactive substances should be considered.
Convulsions: Diazepam or barbiturates. Warning: Diazepam or barbiturates may aggravate respiratory depression (especially in children), hypotension, and coma. However, barbiturates should not be used if drugs that inhibit monoamine oxidase have also been taken by the patient either in overdosage or in recent therapy (within 1 week).
Surveillance: Respiration, cardiac function (ECG monitoring), blood pressure, body temperature, pupillary reflexes, and kidney and bladder function should be monitored for several days. Treatment of Blood Count Abnormalities: If evidence of significant bone marrow depression develops, the following recommendations are suggested: (1) stop the d…
🧬 Clinical Pharmacology ▾
CLINICAL PHARMACOLOGY In controlled clinical trials, Tegretol has been shown to be effective in the treatment of psychomotor and grand mal seizures, as well as trigeminal neuralgia. Mechanism of Action Tegretol has demonstrated anticonvulsant properties in rats and mice with electrically and chemically induced seizures. It appears to act by reducing polysynaptic responses and blocking the post-tetanic potentiation.
Tegretol greatly reduces or abolishes pain induced by stimulation of the infraorbital nerve in cats and rats. It depresses thalamic potential and bulbar and polysynaptic reflexes, including the linguomandibular reflex in cats. Tegretol is chemically unrelated to other anticonvulsants or other drugs used to control the pain of trigeminal neuralgia.
The mechanism of action remains unknown. The principal metabolite of Tegretol, carbamazepine-10,11-epoxide, has anticonvulsant activity as demonstrated in several in vivo animal models of seizures. Though clinical activity for the epoxide has been postulated, the significance of its activity with respect to the safety and efficacy of Tegretol has not been established.
Pharmacokinetics In clinical studies, Tegretol suspension, conventional tablets, and XR tablets delivered equivalent amounts of drug to the systemic circulation. However, the suspension was absorbed somewhat faster, and the XR tablet slightly slower, than the conventional tablet. The bioavailability of the XR tablet was 89% compared to suspension.
Following a twice a day dosage regimen, the suspension provides higher peak levels and lower trough levels than those obtained from the conventional tablet for the same dosage regimen. On the other hand, following a three times a day dosage regimen, Tegretol suspension affords steady-state plasma levels comparable to Tegretol tablets given twice a day when administered at the same total mg daily dose. Following a twice a day dosage regimen, Tegretol-XR tablets afford steady-state plasma levels comparable to conventional Tegretol tablets given four times a day, when administered at the same total mg daily dose.
Tegretol in blood is 76% bound to plasma proteins. Plasma levels of Tegretol are variable and may range from 0.5 to 25 mcg/mL, with no apparent relationship to the daily intake of the drug. Usual adult therapeutic levels are between 4 and 12 mcg/mL.
In polytherapy, the concentration of Tegretol and concomitant drugs may be increased or decreased during therapy, and drug effects may be altered (see PRECAUTIONS, Drug Interactions). Following chronic oral administration of suspension, plasma levels peak at approximately 1.5 hours compared to 4 to 5 hours after administration of conventional Tegretol tablets, and 3 to 12 hours after administration of Tegretol-XR tablets. The CSF/serum ratio is 0.22, similar to the 24% unbound Tegretol in serum.
Because Tegretol induces its own metabolism, the half-life is also variable. Autoinduction is completed after 3 to 5 weeks of a fixed dosing regimen. Initial half-life values range from 25 to 65 hours, decreasing to 12 to 17 hours on repeated doses.
Tegretol is metabolized in the liver. Cytochrome P450 3A4 was identified as the major isoform responsible for the formation of carbamazepine-10,11-epoxide from Tegretol. Human microsomal epoxide hydrolase has been identified as the enzyme responsible for the formation of the 10,11-transdiol derivative from carbamazepine-10,11 epoxide.
After oral administration of 14 C-carbamazepine, 72% of the administered radioactivity was found in the urine and 28% in the feces. This urinary radioactivity was composed largely of hydroxylated and conjugated metabolites, with only 3% of unchanged Tegretol. The pharmacokinetic parameters of Tegretol disposition are similar in children and in adults.
However, there is a poor correlation between plasma concentrations of carbamazepine and Tegretol dose in children. Carbamazepine is more rapidly metabolized to carbamazepine-10,11-epoxide (a metabolit…
🧬 Mechanism of Action ▾
Mechanism of Action Tegretol has demonstrated anticonvulsant properties in rats and mice with electrically and chemically induced seizures. It appears to act by reducing polysynaptic responses and blocking the post-tetanic potentiation. Tegretol greatly reduces or abolishes pain induced by stimulation of the infraorbital nerve in cats and rats.
It depresses thalamic potential and bulbar and polysynaptic reflexes, including the linguomandibular reflex in cats. Tegretol is chemically unrelated to other anticonvulsants or other drugs used to control the pain of trigeminal neuralgia. The mechanism of action remains unknown.
The principal metabolite of Tegretol, carbamazepine-10,11-epoxide, has anticonvulsant activity as demonstrated in several in vivo animal models of seizures. Though clinical activity for the epoxide has been postulated, the significance of its activity with respect to the safety and efficacy of Tegretol has not been established.
📦 How Supplied / Storage and Handling ▾
HOW SUPPLIED Tablets 200 mg - capsule-shaped, pink, single-scored (imprinted Tegretol on one side and 27 twice on the partially scored side) Bottles of 100.............................................................................................................................NDC 0078-0509-05 Bottles of 60...............................................................................................................................NDC 0078-0509-20 Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F). [See USP Controlled Room Temperature].
Protect from moisture. Dispense in tight container (USP). Meets USP Dissolution Test 2.
XR Tablets 100 mg - round, yellow, coated (imprinted “T” on one side and 100 mg on the other), release portal on one side Bottles of 100.............................................................................................................................NDC 0078-0510-05 XR Tablets 200 mg - round, pink, coated (imprinted “T” on one side and 200 mg on the other), release portal on one side Bottles of 100.............................................................................................................................NDC 0078-0511-05 XR Tablets 400 mg - round, brown, coated (imprinted “T” on one side and 400 mg on the other), release portal on one side Bottles of 100.............................................................................................................................NDC 0078-0512-05 Store at 20°C to 25°C (68°F to 77°F), excursions permitted between 15°C and 30°C (59°F and 86°F) [See USP Controlled Room Temperature].
Protect from moisture. Dispense in tight container (USP). Suspension 100 mg/5 mL (teaspoon) – yellow-orange, citrus-vanilla flavored Bottles of 450 mL.......................................................................................................................................NDC 0078-0508-83 Shake well before using.
Do not store above 30°C (86°F). Dispense in tight, light -resistant container (USP). *Thorazine ® is a registered trademark of GlaxoSmithKline. July 2026 T2026-27
📋 Description ▾
DESCRIPTION Tegretol, carbamazepine USP, is an anticonvulsant and specific analgesic for trigeminal neuralgia, available for oral administration as tablets of 200 mg, XR tablets of 100, 200, and 400 mg, and as a suspension of 100 mg/5 mL (teaspoon). Its chemical name is 5 H -dibenz[ b,f ]azepine-5-carboxamide, and its structural formula is: Carbamazepine USP is a white to off-white powder, practically insoluble in water and soluble in alcohol and in acetone. Its molecular weight is 236.27 g/mol.
Inactive Ingredients Tablets: Colloidal silicon dioxide, FD&C Red No. 40, gelatin, glycerin, magnesium stearate, starch, and stearic acid. Suspension: Citric acid, FD&C Yellow No.
6, flavoring, polymer, potassium sorbate, propylene glycol, purified water, sorbitol, sucrose, and xanthan gum. The amount of propylene glycol in Tegretol suspension is 25 mg per mL (see WARNINGS Propylene Glycol Toxicity). Tegretol-XR tablets: cellulose compounds, dextrates, iron oxides, magnesium stearate, mannitol, polyethylene glycol, sodium lauryl sulfate, titanium dioxide (200 mg tablets only).
Tegretol, carbamazepine structural formula
💬 Information for Patients ▾
Information for Patients Patients should be informed of the availability of a Medication Guide, and they should be instructed to read the Medication Guide before taking Tegretol. Patients should be made aware of the early toxic signs and symptoms of a potential hematologic problem, as well as dermatologic, hypersensitivity or hepatic reactions. These symptoms may include, but are not limited to, fever, sore throat, rash, ulcers in the mouth, easy bruising, lymphadenopathy and petechial or purpuric hemorrhage, and in the case of liver reactions, anorexia, nausea/vomiting, or jaundice.
The patient should be advised that, because these signs and symptoms may signal a serious reaction, that they must report any occurrence immediately to a physician. In addition, the patient should be advised that these signs and symptoms should be reported even if mild or when occurring after extended use. Patients should be advised that serious skin reactions have been reported in association with Tegretol.
In the event a skin reaction should occur while taking Tegretol, patients should consult with their physician immediately (see WARNINGS). Patients should be advised that anaphylactic reactions and angioedema may occur during treatment with Tegretol (see WARNINGS). Advise patients to immediately report signs and symptoms suggesting angioedema (swelling of the face, eyes, lips, or tongue, or difficulty in swallowing or breathing) and to stop taking the drug until they have consulted with their healthcare provider.
Patients, their caregivers, and families should be counseled that AEDs, including Tegretol, may increase the risk of suicidal thoughts and behavior and should be advised of the need to be alert for the emergence or worsening of symptoms of depression, any unusual changes in mood or behavior, or the emergence of suicidal thoughts, behavior, or thoughts about self-harm. Behaviors of concern should be reported immediately to healthcare providers. Tegretol may interact with some drugs.
Therefore, patients should be advised to report to their doctors the use of any other prescription or non-prescription medications or herbal products. Caution should be exercised if alcohol is taken in combination with Tegretol therapy, due to a possible additive sedative effect. Since dizziness and drowsiness may occur, patients should be cautioned about the hazards of operating machinery or automobiles or engaging in other potentially dangerous tasks.
Patients should be encouraged to enroll in the NAAED Pregnancy Registry if they become pregnant. This registry is collecting information about the safety of antiepileptic drugs during pregnancy. To enroll, patients can call the toll-free number 1-888-233-2334 (see WARNINGS, Usage in Pregnancy subsection).
💬 Medication Guide ▾
MEDICATION GUIDE TEGRETOL ® and TEGRETOL ® -XR (Teg-ret-ol) (carbamazepine) Tablets, Suspension, Extended-Release Tablets Read this Medication Guide before you start taking TEGRETOL or TEGRETOL–XR (TEGRETOL) and each time you get a refill. There may be new information. This information does not take the place of talking to your healthcare provider about your medical condition or treatment.
What is the most important information I should know about TEGRETOL? Do not stop taking TEGRETOL without first talking to your healthcare provider. Stopping TEGRETOL suddenly can cause serious problems.
TEGRETOL can cause serious side effects, including: TEGRETOL may cause rare but serious skin rashes that may lead to death. These serious skin reactions are more likely to happen when you begin taking TEGRETOL within the first four months of treatment but may occur at later times. These reactions can happen in anyone, but some types of skin reactions are more likely in people of Asian descent.
If you are of Asian descent, you may need a genetic blood test before you take TEGRETOL to see if you are at a higher risk for serious skin reactions with this medicine. Reactions may include: skin rash hives sores in your mouth blistering or peeling of the skin round or oval patches, which can include redness, swelling, blistering, itching, peeling or darkening of the skin, that appear in the same place on your body as when you took Tegretol in the past. This may progress to a serious reaction.
TEGRETOL may cause rare but serious blood problems. Symptoms may include: fever, sore throat, or other infections that come and go or do not go away easy bruising red or purple spots on your body bleeding gums or nose bleeds severe fatigue or weakness TEGRETOL may cause allergic reactions or serious problems, which may affect organs and other parts of your body like the liver or blood cells. You may or may not have a rash with these types of reactions.
Call your healthcare provider right away if you have any of the following: swelling of your face, eyes, lips, or tongue a skin rash painful sores in the mouth or around your eyes unusual bruising or bleeding frequent infections or infections that do not go away fever, swollen glands, or sore throat that do not go away or come and go trouble swallowing or breathing hives yellowing of your skin or eyes severe fatigue or weakness severe muscle pain Tegretol suspension contains 25 mg propylene glycol in each mL. Your healthcare provider will monitor you for side effects of propylene glycol, especially if you are younger than 5 years of age (particularly babies less than 4 weeks old), you have liver or kidney problems, or you are taking other drugs that have propylene glycol or that are broken down by the same enzyme.
Like other antiepileptic drugs, TEGRETOL may cause suicidal thoughts or actions in a very small number of people, about 1 in 500. Call your healthcare provider right away if you have any of these symptoms, especially if they are new, worse, or worry you: thoughts about suicide or dying attempts to commit suicide new or worse depression new or worse anxiety feeling agitated or restless panic attacks trouble sleeping (insomnia) new or worse irritability acting aggressive, being angry, or violent acting on dangerous impulses an extreme increase in activity and talking (mania) other unusual changes in behavior or mood How can I watch for early symptoms of suicidal thoughts and actions?
Pay attention to any changes, especially sudden changes, in mood, behaviors, thoughts, or feelings. Keep all follow-up visits with your healthcare provider as scheduled. Call your healthcare provider between visits as needed, especially if you are worried about symptoms.
Do not stop TEGRETOL without first talking to a healthcare provider. Stopping TEGRETOL suddenly can cause serious problems. You should talk to your healthcare provider before stopping.
Suicidal thoughts or actions can be caused by things other than medicines. I…